Thoracoscopy
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article describes the historical technique of thoracoscopy as it was practiced in the 1930s, primarily for the purpose of performing Jacobaeus thoracocautery to treat pulmonary tuberculosis. It details the instrumentation, surgical procedure, indications, contraindications, and potential complications associated with the method.
Encyclopedia article (1928–1936)
THORACOSCOPY, a method for examining the pleura and lung during artificial pneumothorax. It was first proposed in 1911 by the Swedish phthisiologist Jacobaeus, initially exclusively for assessing the condition of the surface of the lungs, the pleura, and the entire cavity, and then in 1913 for cauterizing lung adhesions that interfere with the full effectiveness of artificial pneumothorax (see below). The first attempts at thoracoscopy were performed by Jacobaeus using a cystoscope, which he later modified
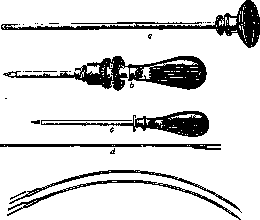
Figure 1: a—thoracoscope; b and c—trocars; d—galvanocauteries.
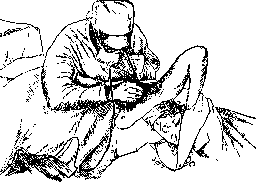
according to local needs in thoracoscopy. Thoracoscopy gained the greatest development and popularity in Germany after substantial changes were made to the instrumentation and methodology by Unverricht, Ulrici, Kremer, and Gross in 1916–1922. In the USSR, the method began to be used in 1929. At the present time, thoracoscopy is performed using the instrumentation shown in Fig. 1. A straight thoracoscope (a) is inserted into the thoracic cavity through the cannula of a trocar (b), which is inserted under local anesthesia into the intercostal space and equipped with an automatically acting valve that limits the entry of air into the pleural cavity when the trocar stylet is removed and allows thoracoscopy to be performed during pneumothorax in negative phases of intrapleural pressure; the examination is performed in the same way as with cystoscopy. However, the ovoid shape and dimensions of the pleural cavity amplify the shortcomings of the thoracoscope inherent in optical instruments of the cystoscope type. The perspective is distorted with particular force, and one must reckon to a greater degree with the deviations of the image in the opposite direction at certain ratios of the endoscope axis to the object being examined. Nevertheless, upon achieving skill, thoracoscopy makes it possible to perform an examination and manipulate in the pleural cavity quite clearly, bringing the optical "eyepiece" of the thoracoscope closer to or moving it away from the site of the examination or operation by pushing it into and pulling it out of the trocar cannula and rotating it along the axis (see color plate, Figs. 1–10). Thoracoscopy is used primarily for tuberculosis of the lungs and pleura as a preliminary stage or simultaneously with Jacobaeus thoracocautery. Jacobaeus thoracocautery consists of the cauterization of adhesions of the lung to the pleura under the control of a thoracoscope without opening the thoracic cavity with an incision. The goal of the method is to eliminate, under visual control, the bands holding tuberculous cavities in a stretched state and preventing them from collapsing during treatment with artificial pneumothorax. The operation is performed under novocaine in the presence of an air bubble in the pleural cavity and consists of 2 steps: 1) puncture of the chest wall with a trocar for the thoracoscope to examine the existing adhesions, and 2) insertion of a new trocar for the introduction of a galvanocautery (complex thoracoscopes proposed by Mendel and Kremer, which include optics and a cautery like catheterizing cystoscopes, have not received wide distribution in practice). The Unverricht galvanocautery has a straight or curved shape (Fig. 1d), corresponding to which a straight or curved trocar cannula is used, or, even better, a spiral flexible cannula according to Unverricht, suitable for any curvature. The long dimensions of the cauteries make it possible to cauterize bands at different levels of the lung from a single insertion point. Some bands, however, are more advantageous to eliminate from specific insertion sites (Fig. 2). The greatest freedom of action is provided by such a placement of both trocars in which the thoracoscope and the cautery cross in the cavity at an angle close to a right angle. The overwhelming number of adhesions can be eliminated by inserting one instrument into the II–III–IV intercostal space from the axillary region at the edge of the pectoralis major muscle and the other at the edge of the latissimus dorsi muscle (Fig. 3). The presence of several adhesions, upper and lower, sometimes requires 2 insertions for the cautery at different levels. In the case of multiple or
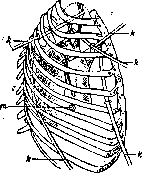
Figure 2. Scheme of Dyll and Kremer: t—opening for thoracoscope; k—opening for cautery.
Figure 3.
very short, mostly apical, bands that are dangerous due to their anatomical position, or during a long operation, it is rational to perform the cauterization in 2, 3, or more sessions, using artificial pneumothorax in the intervals between them. To perform thoracocautery, the following is required: 1) the presence of an air bubble sufficient for the movement of the instrument in the cavity without the risk of damaging the lung, 2) bringing the intrapleural pressure to 0 or low negative or positive figures (-2, -4), and 3) a clearly executed radiograph. Contraindications are a general severe condition, severe shortness of breath, very persistent cough, fresh progressive exudative pleurisy, planar adhesion of the lung, and very short (less than 1 cm) bands. Bilateral artificial pneumothorax with good compensation is not an obstacle to thoracocautery. The technique of thoracocautery is very delicate and requires good knowledge of local topography, attention, and caution in work. The duration of the operation usually ranges from a few minutes to 1–2 hours and depends on the nature of the structure of the bands. The latter may consist of connective tissue with a rich or poor inclusion of adipose tissue, vessels, and sometimes with a greater or lesser content of lung tissue, into which the wall of a peripheral cavity may be drawn. The bands themselves may have the appearance of thin or thick plates, threads, or cords, the thickness of which may reach the diameter of a thumb. In these varieties may lie the source of difficulties for
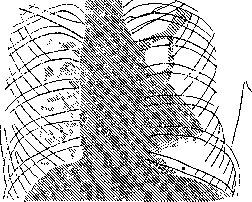
Figure 4. Scheme of a hanging cavity before cauterization.
thoracocautery, the reason for the impossibility of rapid work. In addition, considerable delays are created by the need to stop the cauterization to remove, with the help of a cannula, the smoke obscuring the field of vision from the cavity. For this purpose, there is a suction device proposed by Ulrici that reduces time loss. The postoperative period is conducted with strict bed rest. The resumption of artificial pneumothorax must be started 7–15 days after thoracocautery. A successful result of the operation manifests itself in the coming weeks: the cavity collapses (Figs. 4 and 5), tubercle bacilli and elastic fibers disappear, sputum decreases, temperature drops, and the blood composition improves rapidly. Complications: 1) The most formidable complication can be bleeding during cautery or after it, when the patient is already in the ward. It is possible in case of unsuccessful cauterization of a band too close to the chest wall (a branch of an intercostal vessel) or to the lung (lung parenchyma or bronchial artery on its surface). Often the bands themselves are richly vascularized and bleed easily. This complication is not common, ranging among different authors from 0 to 3–5%; usually, the bleeding is venous and stops easily on its own. In cases of arterial bleeding, it is recommended to compress the band or its stump along its length with the cautery sheath and stop the bleeding by pressure or cauterize the bleeding vessel with the cautery. A preventive measure is the use of a red, rather than white, glow of the cautery loop. Maurer almost completely eliminated the complication of bleeding by proposing a device that coagulates the vessels of the band with diathermy before cauterization. 2) The danger of burning the lung, the wall of the cavity, the pericardium,
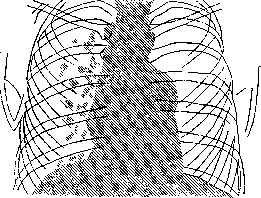
Figure 5. Disappearance of the cavity after cauterization of the band (scheme). the subclavian or azygos vein, etc., is prevented by caution in measures and precise orientation in topography. In addition to these complications, shock, acute shortness of breath during accelerated increase in intrapleural pressure before the operation, and spontaneous pneumothorax are possible (Unverricht—3 cases, Dyll and Kremer—2 cases, Stoyko—1 case, Yesipov—1 case). A very frequent complication (50–70%) in the postoperative period is subcutaneous emphysema, which usually disappears very quickly, and an increase in temperature to 38–39°. The latter usually drops after 6–15 days if it is not associated with pleural infection. Quite often after cautery, pleural exudate is observed. Its frequency is very different—from 16% (Dyll and Kremer) to 72% (W. Lüdke). The exudate arises most often from irritation and, with this etiology, disappears after 8–10 days. A delay in resorption is associated with infection, which can come from the lung stump, in severe cases—from damage to the lung parenchyma, and sometimes from the wall of the cavity itself. Tuberculous exudative pleurisy can occur during the cauterization of bands containing tuberculous nodules, which most authors recognize as not subject to cautery. The final result of thoracocautery is usually good. With strict selection of cases for cautery, it reaches 75% (Pomplun); with a bolder attitude toward cautery, namely when performing thoracocautery in 80–85% of thoracoscopies, the method yields up to 60–62% success, i.e., the conversion of an ineffective pneumothorax into a full-fledged, effective one (Unverricht, Dyll and Kremer, Stoyko, Yesipov, and others).
Related articles
Mentioned in
Cite this page
“Thoracoscopy.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/thoracoscopy/