Electrodiagnosis
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia describes the historical methods of electrodiagnosis, primarily used for assessing nervous system and motor apparatus disorders. It details the use of galvanic and faradic currents, the application of Pflüger's law of contraction, and the clinical interpretation of muscle response patterns, including the reaction of degeneration.
Encyclopedia article (1928–1936)
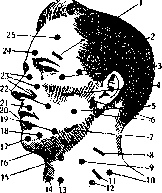
ELECTRODIAGNOSIS, the application of electrical energy for the purpose of diagnosing diseases. Electrodiagnosis is of greatest importance in diseases of the nervous system, especially of the motor apparatus. Galvanic and faradic currents are usually used for electrodiagnosis. High-voltage currents and Franklinic sparks have no diagnostic value. Pflüger's law of contraction, based on experimental bipolar stimulation of an exposed nerve, encounters certain difficulties when applied to humans. With the unipolar nerve stimulation used in clinical practice, the current does not spread exclusively along the nerve, but goes partly obliquely and across the nerve. The point of current entry is called the polar zone, and the point of exit is called the peripolar zone (Fig. 1). The current partially exits the nerve not far from the point of application of the active pole. This opposing current is called virtual. When any point of the body is stimulated by a cathode, the current tends toward the anode along several lines, spreading through the whole body—current loops (Fig. 2). Nevertheless, the organ near which a pole is placed is under its predominant influence. The unipolar method of examination used in clinical practice for electrodiagnostic purposes is based on this. Nerves and muscles are stimulated by electric current through an active electrode at specific points corresponding to the most superficial location of the nerves and the points of entry into the muscles (Figs. 3 and 4). A passive, indifferent large electrode is placed on a part of the body devoid of large nerves or muscles, for example, on the sternum or sacrum. With weak currents, contraction occurs only upon closing the cathode, since the stimulating effect of the cathode on the nerve exceeds the effect of the anode. With medium currents, contraction also appears upon opening the anode and at almost the same current strength upon closing it; in the latter case, when closing the current, the anode of which is located on the active electrode, virtual cathodes come into play, exerting a great effect on the neuromuscular apparatus. With strong currents, stimulation by the cathode causes a tetanic contraction; the influence of the virtual anode, despite its relative weakness, is still sufficient for a contraction to appear upon opening the cathode. In electrodiagnosis, the current strength required to obtain a contraction, the pole, the moments of closing and opening, and the character of the muscle response are taken into account. To judge the norm and deviations from it, Stinzing's tables are used, which provide the average values of electrical excitability for each nerve and muscle, the extreme highest and lowest figures that still lie within the limits of the norm, and the difference in electrical excitability between nerves and muscles on both sides. For example, the lower limit of galvanic excitability of the facial nerve is 0.8 mA, the upper is 2.8, the average value is 1.75; normal figures for galvanic excitability of the common extensor of the fingers of the hand range from 0.6 to 3.0 mA. Changes in the strength of the current capable of causing contractions constitute the quantitative side of the electrodiagnostic examination and are of particular importance in the examination
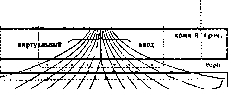
Figure 1. (After Watteville.) ... peripolar (catelectrotonic) zone ... polar (anelectrotonic) zone ... actual ... anode
virtual
cathode
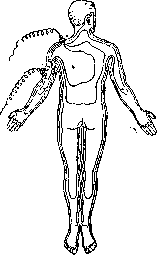
muscles, etc. Figure 1. (After Watteville.)
of nerves. A change in the very character of the muscle contraction is revealed mainly during muscle stimulation and forms the qualitative side. A decrease in the electrical excitability of a nerve is expressed by three phenomena: 1) currents of significantly greater strength than in the norm are required to elicit a minimal contraction; 2) the strongest currents elicit only weak contractions; 3) some elements of the Brenner formula (see Brenner-Erb formula) do not occur even at the strongest currents (for example, Cathode Closing Contraction).
In neurogenic lesions of the motor apparatus, electrodiagnostic data are included in the distinguishing features of flaccid and spastic paralysis. First of all, Pflüger's law of contraction is checked for an individual nerve and muscle. For this purpose, the same nerve or muscle point is acted upon first with a faradic current, and then alternately with the cathode and anode of a galvanic current at the same current strength. Thus, the minimal contraction obtained from stimulation is established, and the weakest current necessary for such a contraction serves as the electrodiagnostic measure. In pathological cases, when stimulated with the same pole of the electric current, predominantly quantitative changes in electrical excitability are discovered; qualitative changes are revealed when the poles are switched. The combination of qualitative and quantitative changes is called the reaction of degeneration. It occurs when the connection between the neuromuscular apparatus and its trophic center is disrupted, i.e., in diseases of the peripheral neuron. Conversely, as a rule, the reaction of degeneration is not observed in primary diseases of the musculature and lesions of the central neuron. In the reaction of degeneration, the excitability of the nerve to both currents and the faradic excitability of the muscle decrease; however, the galvanic excitability of the muscle in the first period of the reaction of degeneration may even be increased and only then falls. The most important sign of the reaction of degeneration is the sluggishness of the muscle contraction. In a severe form of the reaction of degeneration, the nerve loses electrical excitability altogether; the faradic excitability of the muscle also disappears, and only its galvanic excitability to strong currents remains. The Brenner formula in the reaction of degeneration of moderate and severe degree often changes; Anode Closing Contraction and Cathode Opening Contraction in their strength approach Cathode Closing Contraction and Anode Opening Contraction. The latent period increases with sluggish contraction up to four times. In the norm, the muscle contraction is greater with the same stimulus strength the closer the stimulus is applied to the point of nerve entry (Ranvier's motor points); with
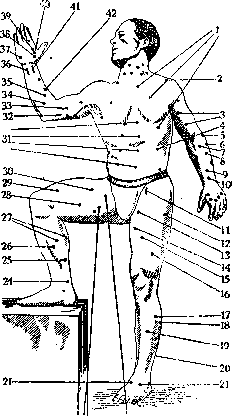
23 .22
Figure 4. Diagram of motor points on the trunk and limbs: 1- m. pectoralis; 2-m. deltoideus; 3- m. biceps; 4- m. obliquus abdominis externus; 5-m. supinator longus; 6-m. extensor carpi ulnaris; 7-m. flexor carpi radialis; 8-m. extensor digitorum communis; 9-m. extensor indicis; 10-m. extensor pollicis longus; 11-n. femoralis; 12-m. tensor fasciae latae; 13-m. sartorius; 14-a. obturatorius; 15-m. adductor longus; 16-m. vastus lateralis; 17-m. peroneus longus; 18-m. gastrocnemius lateralis; 19-m. tibialis ant. et extensor dig. communis longus; 20-m. extensor hallucis longus; 21-m. extensor digitorum communis brevis; 22-m. interosseus dorsalis I; 23-m. sartorius; 24-n. obturatorius; 25-n. tibialis; 26-m. flexor digitorum communis longus; 27-m. gastrocnemii; 28-m. adductor longus; 29-m. vastus medialis; 30-m. rectus femoris; 31-m. rectus abdominis; 32-n. ulnaris; 33-n. medianus; 34-m. flexor digitorum profundus; 35-m. flexor digitorum sublimis; 36-n. ulnaris; 37-m. flexor digiti minimi; 38-m. abductor pollicis; 39-m. adductor pollicis brevis; 40-m. opponens pollicis; 41-n. medianus; 42-m. flexor carpi radialis. In reactions of degeneration, sometimes there is a displacement of motor points (the Wertheim-Salomonson phenomenon). Besides its diagnostic significance, the reaction of degeneration also plays a major role in prognosis, formulated by Erb in the following propositions. With the same disease form and the cause producing it, the more significant the lesion, the longer the duration of the disease, the less favorable the outcome, the more pronounced the reaction of degeneration. A partial reaction of degeneration gives a better prognosis than a complete one. The reaction of degeneration in the late stage of the disease is prognostically more unfavorable than in the early stage. Increased excitability as an independent phenomenon is observed in tetany, where sometimes contraction occurs with AR and KR with a current below 5 μA (the Mann-Timikh phenomenon). The neurotonic reaction (the reaction of Remak and Marin) consists in the appearance of tetanus upon irritation of the nerve with weak currents not only with CC but also with AC. The neurotonic reaction was observed in muscular dystrophy, epidemic encephalitis (Krol).-Myasthenic reaction (Jolly) consists in the gradual extinction of muscular excitability with successive direct and indirect irritations. After a short pause, the previous excitability is restored. With repeated irritation, the sequential extinction is repeated again. The myasthenic reaction is encountered in myasthenia, obliterating endarteritis, epidemic encephalitis.-The cadaveric reaction consists in the complete disappearance of excitability to both currents, occurring during an attack of periodic paralysis of the limbs. The myatonic reaction consists in a decrease in faradic excitability of the muscles with preservation of galvanic excitability. It is sometimes encountered in congenital amyotonia (myatonia).-In the myotonic reaction, the excitability of nerves for medium currents is normal. The electrical excitability of muscles is sharply increased for both currents. With faradization of the muscle even with a weak current, a prolonged contraction occurs. With a galvanic current, the contraction is very sluggish, persists after breaking the circuit and slowly subsides. With prolonged passage of current through the muscle, rhythmic contractions appear in it, spreading from the cathode to the anode. Sometimes they also appear upon irritation of nerves with a strong current. The myotonic reaction occurs in myotonia, epidemic encephalitis and syringomyelia.-The reaction with a gap (Benedict) consists in the fact that upon irritation with a galvanic current, single contractions occur, which do not appear with subsequent irritants; to obtain a contraction, increasingly stronger currents become necessary. The reaction with a gap was noted in progressive muscular dystrophy. In the longitudinal reaction, the muscle responds with a contraction to a galvanic current only when the current is passed along it. The active electrode is placed on the tendon of the muscle being examined and even away from it. Sometimes the longitudinal method is used in cases of loss of faradic excitability of the muscle in the reaction of degeneration. By passing a galvanic current along the entire limb, it is sometimes possible to simultaneously cause a contraction of the muscle with a strong faradic current. The basis of the longitudinal reaction is the property of a degenerating muscle to lose excitability first at the points where the nerve enters it and last in its terminal parts. The motor effect in the longitudinal reaction is sometimes more extensive than in the reaction of degeneration. Sometimes the longitudinal reaction for a long time replaces the reaction of degeneration. E. in application to changes in sensitivity has much less significance than in changes of the motor apparatus. In the examination of the latter, E. operates on the contraction of the musculature, subject to observation and precise measurement; in E. of sensitivity, the results are controlled only by the subjective sensations of the subject. According to the principle of specific energy, although an adequate stimulus, the electric current causes specific forms of sensation from the sense organs themselves and their nerves. Therefore, in the electrical examination of such nerves as the optic, auditory, gustatory, olfactory, it is impossible to distinguish between irritation of the sense organ itself and its nerves. Somewhat greater significance is attached to E. of cutaneous nerves. Faradic cutaneous sensitivity does not always run parallel with other forms of sensitivity. Its pathways and endings are not exactly established. The electro-myesthetic sensitivity of Duchenne in the form of the painful sensation of muscle contraction is not entirely identical with the sensation of ordinary muscle contraction. Similar to the figures of Stintzing's table for motor nerves, Hoffmann established the minimum current figures necessary to obtain a sensation upon irritation of sensory nerves. A sensitive reaction of degeneration, analogous to the motor one, is sometimes observed in tabes dorsalis and herpes zoster. Faradic cutaneous sensitivity is absent or diminished in it, galvanic sensitivity may be increased, the anode is somewhat more painful than the cathode. Irritation with a faradic current of a nerve exposed during operation or as a result of trauma causes a sensation of itching. A galvanic current passed through an exposed nerve produces a sensation of heat; with simultaneous passage of galvanic and faradic current, a sensation of pressure appears. This sensation is sometimes strictly localized in the area of the irritated nerve, sometimes it extends beyond its limits.-For diagnostic purposes, the degree of resistance of the skin to electric current is used. Increased resistance is characteristic of Basedow's disease, more rarely it occurs in hysteria and traumatic neurosis. Increased resistance is observed in scleroderma, myxedema, elephantiasis. The resistance of the skin to current is determined by its moisture, depending on vascular factors and the degree of perspiration. Electrodiagnosis on the brain exposed during operation is used to determine individual motor and sensory centers.
Related articles
Mentioned in
Cite this page
“Electrodiagnosis.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/electrodiagnosis/