False Joint
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia discusses the pathology, etiology, and clinical features of false joints or pseudarthrosis, covering congenital, pathological, and traumatic forms. It details mechanical, biological, and inflammatory factors that prevent normal bone fracture healing.
Encyclopedia article (1928–1936)
FALSE JOINT, or pseudarthrosis, is a persistent abnormal mobility along the course of a bone (Figs. 1–5). The connection between the fragments may be loose-fibrous, dense-scar-like, or joint-like. A false joint forms on the basis of developmental anomalies or as a result of pathological or traumatic changes. Congenital false joints represent a local developmental defect (aplasia). With a general defectiveness of periosteal bone formation, intrauterine fractures are multiple in character and are not devoid of the capacity for spontaneous union. Purely traumatic fractures, if they occur in the intrauterine period, during birth, or in infancy, tend to rapid healing without outside help. Meanwhile, congenital false joints are distinguished precisely by 1) localization almost exclusively at the border of the middle and lower thirds of the leg, and 2) the inability to form callus by their own forces and local means. At the same time, at the moment of the child's birth, the false joint may not yet exist, and there is only an angular bend or saber-like curvature of the tibia. Under the influence of minor trauma or sharp muscle tension, acutely in some cases, and slowly and without any external cause in others, there are formed

Figure 1.
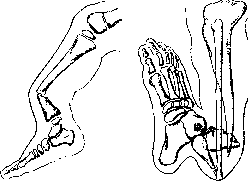
Figure 2.
Figure 3. - fracture and false joint. The hidden forms of such anomalies explain the fact that, according to Jüngling's pooled statistics, out of 100 fractures of tubular bones in children (up to 10 years of age), 9 cases fall on the leg, while out of 100 pseudarthroses in children, 76 fall on the shin bones. Teratology assigns congenital false joints of the leg an average place in severity in the long series of aplastic changes, starting from the anatomical predisposition of a certain area to fractures and ending with a defect of the entire bone. This area lies at the junction of longitudinal growth from the upper and lower epiphysis. The boundary zone may remain cartilaginous or fibrous to a greater or lesser extent, and may turn into a false joint and into a bone defect. The defect may be of early, embryonic origin and of various sizes, up to the absence of the en-
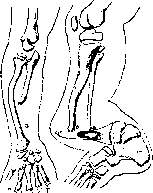
Figure 4.
entire bone (Fig. 6). Of the bones of the leg, the tibia is much less frequently missing, but its false joint is more frequent, because it has a poorer blood supply than the fibula, which is surrounded on all sides by muscles and is sometimes capable of surprising hypertrophy in tibial defects. In congenital pseudarthroses of both bones of the leg, atrophy of the ends, especially the distal ones, often reaches extreme proportions. The fragments are thinned, pointed, and amorphous-porous. The angular bend at the site of the false joint becomes increasingly acute, the anterior surface of the leg adjoins the dorsum of the foot, the entire limb lags in growth and is shorter than the healthy one by 20 or more cm. Pathological false joints are formed not without the influence of mechanical factors, but their origin is based on a pathological process. Diaphyseal osteomyelitis in a violent course rapidly disrupts the nutrition of the periosteum or leads to necrosis before the periosteum has time to create a new protective cover around the dead bone. In a chronic course, with the formation of sequestra and fistulas, reactively abundantly layered bone may turn out to be insufficiently strong throughout for physiological loading conditions. In both cases, sometimes without traumatic impact, "spontaneously," the bone breaks and, due to abnormal nutritional conditions, no longer unites. As the infection subsides, in the stage of granulation walling-off and scarring, a fibrous connection forms between the ends of the diaphysis, i.e., a false joint is formed. The disproportion between pathological passive mobility and the loss of active movements will depend on the size of the bone defect, the state of the soft parts, innervation, and blood circulation. - Enchondromas and malignant neoplasms, predominantly myelogenic sarcomas, less often metastatic carcinomas, destroying the bone, also create conditions for "spontaneous" fractures ending in a false joint. It must be emphasized, however, that in a number of cases not only does consolidation occur, but the formation of callus even favorably affects the underlying process. Even more prominently displayed

Figure 5.
is the healing effect of a pathological fracture in fibrous osteitis, if the entire cortical layer was not involved in the degeneration and the reactive capacity of the periosteum was preserved. Otherwise, fibrous masses remain between the fragments, and the cyst-like cavity resembles a false joint. Gummatous and other syphilitic lesions of the bones are a frequent cause of increased bone fragility and improper union of fractures. The danger of a false joint is prevented by timely initiated specific therapy. - The rarity of pseudarthroses in tuberculosis, despite the osteoporosis characteristic of this disease, depends on the rarity of tubercular involvement of the diaphyseal sections. Destructive displacements of joint ends with some mobility at a new site should be attributed not to false joints, but to pathological dislocations or non-arthroses. - Rachitic processes, due to the development of osteoid tissue and insufficient deposition of lime salts, lead to skeletal curvatures and delayed union of traumatic fractures, but in childhood they do not entail the formation of false joints. This is prevented by the osteosclerosis occurring in the reparative stage of the disease. Late rickets and alimentary osteopathies, which became especially widespread in Germany by the end of and after the imperialist war, more than childhood rickets predispose to weak, fibrous union of fragments or to secondary resorption of callus. Sometimes at the site of a former fracture, even under normal nutritional conditions, without signs of constitutional skeletal disease and without new trauma, a few months after consolidation, pain reappears, the callus begins to be resorbed, and an X-ray image reveals a transverse cleft splitting the bone instead of the previous continuous shadow. Such belt-like thinnings, or fibrous interlayers, are called "zones of restructuring" (Umbauzonen) and can turn into false joints. Martin and Müller proved experimentally that after resection of one of two parallel parallel bones, a zone of restructuring or a false joint can appear on the other at the same level. - The role of biochemical, endocrine, mechanical, or nervous factors in the pathogenesis of these regressive local changes has not yet been clarified. The gradual development of lacunae with reactive thickening of the periosteum on the tibia and metatarsal bones is often found in young soldiers as a consequence of intense drill exercises. Traumatic false joints [see separate table (p. 371-372), Figs. 6 and 7] occur most frequently and do not require either local or general predisposition for their occurrence, although both can play the role of an important conditional factor. The periods of possible fracture union vary within very wide limits, and before half a year one should speak not of a false joint, but only of delayed consolidation. Final failure in a healthy subject can depend on three kinds of causes: a lack of bone material between the fragments, exhaustion of local osteogenic forces, and finally, improper treatment. 1. Too large a diastasis, or separation of fragments (Fig. 7), is the simplest explanation for why the broken ends do not connect with each other. For example, so-called "fenestrated" gunshot fractures do not unite, in which large pieces of muscle and bone tissue are torn out. Displacements in which fragments "ride astride," i.e., one fragment rests against the outer layers of the periosteum of the other, are also an absolute obstacle to the formation of a strong adhesion (Fig. 8). Finally, the mechanical role of the interposition of muscles and fasciae between fragments is obvious. Such interposition of soft parts is likely if crepitus cannot be elicited. It is observed more often in closed fractures than in gunshot fractures. In 120 operations for fractures (among which 92 were closed), König (Congress of German Surgeons in 1930) found it in 30% of cases. 2. The regenerative capacity of bone depends on the presence of endosteal and periosteal osteoblasts. The destruction of these cells occurs from the trauma itself or as a result of infection. The more intense the trauma and the heavier the infection, the greater the danger of a false joint, since bacterial influence, purulent decay and necrosis, and subsequent disruption of blood supply are added to the mechanical destruction of osteogenic elements. If a bone is broken at such a level that the main feeding vessel is simultaneously ruptured, this circumstance may be sufficient for the premature exhaustion
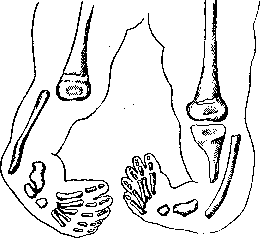
Figure 6.
of the bone's restorative energy.

regenerative powers. Nerve interruption exerts a harmful effect on the quality of the bone callus, and partial damage to nerve trunks sometimes reflexively retards consolidation. 3. The most frequent cause of false joint formation is treatment errors. Since the aforementioned harmful factors are eliminable, the refusal of active intervention for the reposition of fragments, for combating infection, etc., can contribute to the development of a false joint. No less harmful, however, is excessive and unskilled radicalism. During the recent war, the antiseptic toilet (or so-called debridement) of gunshot fractures was performed by many surgeons so early and energetically that, due to the removal of fragments still connected with soft parts, the refreshing of fragments, and the excision of muscles, the extremity was deprived of the bone material necessary for restoring integrity and the collateral pathways necessary for blood supply. The aspiration to replace splint immobilization and limb traction with direct operative fastening of the fragments using Lane's metal plates also had the opposite effect in the overwhelming majority of gunshot fractures: rarefying osteitis and loosening of the screws, an outbreak of infection, and prolonged suppuration resulting in pseudarthrosis. Another circumstance that very harmfully affects the course of injuries, especially combat ones, is the transport traumatization inevitably associated with evacuation and the failure to observe the principle of continuous immobilization of the extremity, even during wound dressing. It should be noted, however, that with extensive bone comminution, overly energetic traction separates the fragments and delays consolidation. For closed civilian fractures, the main therapeutic error leading to the development of a false joint is also insufficient immobilization. Furthermore, unlike gunshot fractures, inadequate reduction is of decisive importance. Eliminating the displacement of an obliquely or spirally fractured diaphysis on the forearm or leg, or putting a dislocated epicondyle back into place, is sometimes impossible without surgery, even if such as direct bone traction. But proper alignment almost always succeeds in preventing the development of a false joint, provided the achieved position is maintained for the necessary time without prejudice to future function. A not inconsiderable number of mysterious cases of fracture relapse or late false joint owe their origin to the fact that bone and vascular bridges between the fragments were gradually torn and obliterated during the outpatient treatment period due to oblique loading in removable plaster casts as a result of uncontrolled massage and stereotyped passive gymnastics. To reduce the number of false joints, it is necessary to shorten the currently practiced periods of general immobilization and lengthen the local ones. In addition, the methods of immobilization during first aid and hospital care are subject to revision and standardization. Therapeutic measures are reduced to prosthetics or surgical interventions. Pathological anatomy of the false joint is very diverse depending on the type and location of the fracture and the physiological properties of the affected limb. Flail pseudarthroses with great mobility at the site of the false joint have a connective tissue bridge;
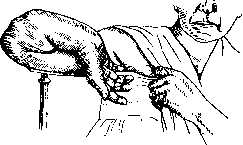
Figure 9. they form with large defects of bone material or with significant displacement of the fragments. The fragments are pointed, porous, and the bone marrow cavity is closed by a scar. Atrophy is more pronounced the closer the false joint is located to the epiphyses. The favorite site for such false joints is the humerus, which generally yields the highest number of traumatic pseudarthroses. Springing pseudarthroses have a tight fibrous connection and a relatively narrow gap with a serrated surface and osteoid-cartilaginous layers. The proximal end is often thicker and embraces the distal one with spikes or an overhang. Most often, such false joints occur on the forearm (Fig. 9) and leg, arising gradually and relatively late. "True" false joints are a comparative rarity and require a lot of time and active movements for their development. They are characterized by the fact that the ends of the fragments are filled and surrounded by smoothly polished fibrous masses or even have a cartilaginous covering. The resemblance to a normal joint is aggravated by the development of a fibrous capsule containing a cavity filled with synovial fluid and sometimes rice bodies.
E. Osten-Sacken.
Related articles
Mentioned in
Cite this page
“False Joint.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/false-joint/