Phototherapy
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article outlines the historical development and scientific principles of phototherapy in the early 20th century. It details the discovery of the bactericidal effects of light, the evolution of light-based medical treatments, and the physiological mechanisms of skin reactions to ultraviolet radiation.
Encyclopedia article (1928–1936)
PHOTOTHERAPY (phototherapy, from the Greek phos, photos—light and therapeia—care, treatment). Modern phototherapy is based on an understanding of the so-called chemical action of light. First and foremost, the action of light on bacteria was subjected to study. In 1877, Downes and Blunt established that light (short-wave rays) is capable of killing bacteria. Based on this, the Danish scientist Niels Finsen (1860–1904) built his method of actinic therapy (in the 1890s). Starting with sunlight, he then moved on to electric arc light. Subsequently, heliotherapy (see) appeared at high altitudes (Bernhard, 1902, and Rollier, 1904), which gained recognition especially for surgical tuberculosis. In connection with the progress of technology, particularly in the field of the application of electricity, phototherapy naturally gravitated toward the use of electric light. In 1894, the American physician Kellogg proposed his electric light bath. In 1891, the Russian physician Minin proposed the blue incandescent lamp with a reflector, which gained such wide distribution. Mercury-quartz lamps, introduced into use by Kromayer (1906) and then successfully modified by Bach (1911), play an especially large role in modern phototherapy due to their significant content of ultraviolet (chemically active) rays. Recently, data have been obtained indicating the indirect action of light in its short-wave part and its ability to activate food substances (A. Hess) (see Irradiated preparations). Regarding the physical nature of radiant energy and the biological action of light, see Radiant energy, Radiation, Light. Passage of light through tissues. Various rays penetrate the human body unevenly. The most common opinion, that the human body generally transmits rays poorly, is not entirely accurate. Thus, with sufficient light intensity, long-wave rays can penetrate the body to a fairly significant depth, but short rays also penetrate much deeper than was initially assumed. According to Godnev's experiments, glass tubes filled with silver chloride paper and placed under the skin of dogs, cats, and under the human prepuce blackened under the influence of light. Busk, passing concentrated sunlight through a hand 2.8 cm thick, was able to note its effect on isochromatic plates. The same effect was obtained with concentrated arc light (70 amperes and 50 volts), with an exposure of 1 second required, and through the wrist joint (3.7 cm thick)—4 minutes. Negative results were obtained when illuminating the forearm (5.6 cm thick), even with an exposure duration of up to 30 minutes. Comparative studies of the ability of various rays to penetrate animal tissues (a rabbit's ear engorged with blood) showed that the curve, starting from the extreme ultraviolet rays, where it is very low, gradually rises, reaching the infrared part. In the final part of the infrared rays, the curve lowers again. On this issue, Hasselbalch conducted a series of interesting experiments. He took the skin of the chest of adults and newborns. First of all, he established that there is no difference between the passage of ultraviolet rays through living or dead exsanguinated skin. As the thickness of the skin increases, the absorption of short-wave rays also increases, with a considerable part of them reaching the vascular papillae of the skin, where they are captured by the blood circulation. According to Keller, ultraviolet rays are capable of penetrating into the depth of tissues by 0.63 mm, i.e., to the papillary network of capillaries. However, there are indications of deeper penetration of ultraviolet rays (Gassul, Remezov). Glitscher investigated the same question in relation to visible rays. He used the tissue of a pig's bladder, which is similar in structure to human skin. His data confirm previous observations about the increase in the penetrating ability of light rays as their wavelength increases. The penetrating ability of infrared rays appears to be especially great. Among the frequently observed phenomena, especially in the spring and summer, is the inflammatory state of human skin under the influence of sunlight (erythema solare, photoerythema). To clarify which rays play a role in this, Finsen attached a series of differently colored glasses and a plate of rock crystal to the flexor side of the hand, drew letters with ink, and applied an ointment. Having subjected such a hand to the action of light from a strong carbon voltaic arc, he could observe, immediately after the experiment, a uniform reddening of the skin of the hand even on the covered areas. Two hours after the end of the irradiation, the redness decreased somewhat, but the skin still remained uniformly colored. An hour later, the erythema intensified, but only on the areas that were not covered. The next morning, the result was sharply defined. The skin that had been covered with ink during the experiment was completely normal and sharply demarcated from the adjacent inflamed surface. On the site of the ointment and the glasses, the skin was also unchanged. Where the skin was covered with a plate of rock crystal, it was intensely red, hot, and sensitive. The erythema lasted for several days and gradually began to weaken, being replaced by peeling and finally pigmentation. These experiments by Finsen are conclusive in the sense of the importance of ultraviolet rays for the appearance of a photochemical reaction. In those places where there were various media that did not transmit ultraviolet rays (glass, ointment, ink), photoerythema did not develop. On uncovered skin and on the site of the rock crystal plate, which, as is known, transmits these rays, erythema appeared. Furthermore, Finsen noted the importance of pigment as a manifestation of the protective reaction of the organism. He showed that in all places where pigmentation was already present due to initial illumination, the skin no longer reacted to the irritating action of ultraviolet rays. These data were followed by a series of experiments, generally confirming the role of ultraviolet rays as the cause of cutaneous erythema. In recent times, this question was investigated by Hausser and Vahle. The authors found that shortly after irradiation, identical reddening appeared at a wavelength of up to 313 mµ; the maximum, however, was at a wavelength of 313–280 mµ, which manifests itself rapidly within a few hours and decreases the day after irradiation. With redness developing after irradiation with shorter-wave rays, this process proceeds even faster. The authors establish that the ability of rays to cause erythema begins to manifest itself only from a wavelength of 320 mµ, after which (in the direction of decreasing λ) this ability rapidly reaches its maximum (300 mµ). Their later studies showed that there is one more, albeit less significant, maximum at 250 mµ. The histology of the skin during light inflammation has been studied by a number of authors. After 10–15 minutes, the first changes are detected in the capillaries. The smallest capillaries dilate, the blood circulation in them slows down and finally ceases completely, with thrombi forming. Gradually, diapedesis of a multitude of white and individual red blood cells develops. After 24 hours, the swelling usually increases, and the tissues become cloudy. Diapedesis occurs only in deeper, somewhat dilated, but not thrombosed vessels. After 48 hours, the edema has already significantly subsided. In places where there were thrombi, circulation is restored again. According to Dreyer and Jansen, small vessels remain dilated even when blood circulation has already been restored. These authors pointed out that this phenomenon completely coincides with the observation noted earlier by Finsen on humans, that such dilation of vessels remains long-lasting, and the irradiated areas of the skin react more strongly to mechanical irritation even 5–6 months later (a sharper hyperemia is obtained) than an unirradiated area of skin. The sensitivity of irradiated skin depends mainly on the following 3 factors: 1) on the constitution of the individual, 2) on the different reactive capacity of different areas of the skin to ultraviolet irradiation (regional photosensitivity), and 3) on external irritations added to the irradiation (Wellisch). Individual photosensitivity is one of the manifestations of constitution. Photosensitivity increases with increased blood supply to the skin. Increased photosensitivity is apparently characteristic of subjects with a labile vasomotor system, those prone to urticaria, and asthmatics. Children exhibit high photosensitivity, the elderly—lower. Women before menstruation are more sensitive to light than after it. In pregnant women, the skin of the abdomen is more sensitive to light than the skin of the chest. In the same individual, the skin on different areas is not equally sensitive to irradiation. The reason lies first of all in the different thickness of the horny layer, and then in the different habituation to light of skin covered and uncovered by clothing. External irritations can modify the photoreaction. Rubbing the skin before or after irradiation intensifies the reaction. On the other hand, pressure applied after irradiation suppresses the development of erythema.
When using a source with a longer wavelength of radiation simultaneously with ultraviolet irradiation, or upon preliminary exposure to a hot air shower, an intensification of erythema is observed.
The same effect is obtained when using photodynamic substances, such as: eosin, methylene blue, chlorophyll, hematoporphyrin.
Rays of a longer wavelength (red, infrared) cause a reaction on the skin that has certain peculiarities.
With erythema from infrared rays, there is no latent period; with a larger surface of irradiation, the redness is not continuous, it presents a clearly reticular pattern, which is explained by the deeper penetration of infrared rays to the subpapillary and deeper-lying small arteries and veins and the dilation of the latter.
The course of such erythema depends on the intensity of the radiation: it may disappear after a very short time or persist for several days.
The pigmentation corresponds entirely to the reticular redness; it is darker than with ultraviolet rays (Wellisch).
The influence of light, and in particular ultraviolet rays, on internal organs is undoubted. This has been proven by a large number of observations in the clinic and in experiments.
Nevertheless, one can hardly speak of a direct effect of light on internal organs during its therapeutic application.
After all, the most active part of the phototherapeutic spectrum—ultraviolet rays—acts mainly as a skin irritant. Hence, the influence on internal organs is through the medium of the skin.
The influence of irradiation on the blood has been studied by many authors. However, the data from these studies are so contradictory that it is not yet possible to discern any consistency in the changes obtained thereby.
It is undoubted that both erythrocytes and, in particular, leukocytes undergo changes.
Regarding the circulatory apparatus, there is a fair number of observations concerning the state of blood pressure.
Authors note a lowering of blood pressure as a long-term effect, lasting for months.
In the opinion of Kestner and Kimmerle, the lowering of blood pressure, where it occurs during irradiation, depends not on the radiation, but on the inhalation of gases developing during the burning of an arc lamp, and most likely on nitrogen oxide compounds.
Plotnikov and Broderzon, on the same issue, undertook experimental studies in Brushtein's laboratory on the vessels of a rabbit's ear using the method of isolated organs.
They obtained results indicating that the radiation of a mercury-quartz lamp changes the lumen of the vessels, and in such a way that in the majority of cases their constriction is observed, while in the minority of cases—dilation.
This fact does not contradict clinical observations, since here the effect immediately following illumination is noted, whereas the dilation observed in the clinic relates already to the time of the development of erythema.
After illumination of a medium-sized area of skin with a carbon voltaic arc, the respiratory rate decreases, and the depth of respiratory movements increases.
This phenomenon lasts for a longer time than erythema (Hasselbalch).
In the Alps (3,290 m above sea level), a similar state occurs even when only the skin of the face and hands is subjected to irradiation.
Breathing, quickened under the influence of altitude, drops when the skin is subjected to the action of ultraviolet rays and erythema develops. The depth of breathing increases noticeably.
Upon descent into the valley, the number of breaths increases, as well as, to a lesser extent, the depth of breathing (Hasselbalch and Lindhard).
There are indications of the influence of light on gas exchange.
According to experiments on animals, an increase in oxygen absorption and carbon dioxide excretion is observed under the influence of light. The same has been noted in humans.
Various tissues of the animal organism (blood, kidneys, liver, etc.) are able, under the influence of light, to absorb more oxygen than in the dark (Quincke).
Ultraviolet irradiations increase the phosphorus content in the blood of rachitics and bring the calcium content to normal.
Protein metabolism undergoes some intensification, which apparently is a reaction to the large influx into the blood of protein broken down due to irradiation.
Residual nitrogen decreases under the influence of irradiation (Pincussen).
The change in carbohydrate metabolism is manifested by a decrease in the sugar content in the blood.
Ultraviolet rays in a small dose have an irritating effect on enzymes, and in a large dose—a suppressive one.
Body temperature does not undergo changes during irradiation with a quartz lamp (Bach), although after energetic general and erythemal irradiations, a subfebrile temperature sometimes occurs, which, in the opinion of Kellogg, depends on the absorption of protein breakdown products.
On the other hand, in febrile states, body temperature drops somewhat.
Rays of the visible part of the spectrum are able to raise the temperature of the blood to a greater extent than infrared ones.
Experiments on the influence of general electric light baths on the state of the associative-motor reflex in humans have shown that the indicated reflex changes differently depending on the illumination used (colorless light, blue, red).
Thus, the human nervous system responds to different irradiation, perceived by the nervous apparatus of the skin, with a different reaction (Brushtein).
In the literature, there are further a number of indications regarding the influence of colored illuminations on the psyche.
Immediately after irradiation, a certain hypalgesia appears, which, however, within an hour, therefore still during the latent period, passes into hyperalgesia, increasing with the development of erythema and decreasing with its disappearance.
With the appearance of pigmentation, hypalgesia appears again.
For the appearance of erythema from ultraviolet irradiation, the state of the sensory nerves of the skin is of great importance.
In the nerve endings of the skin, under the influence of irradiation, physico-chemical changes develop, spreading to the entire nerve and causing a lowering of its tone.
Nerve endings in the skin proliferate under the influence of ultraviolet irradiation, and nerve plexuses in the hair follicles increase.
Changes in sensory nerve endings in the skin from the action of ultraviolet rays are similar to changes after the action of X-rays, differing from them only quantitatively.
Light exerts an influence on the sympathetic nervous system, acting on the endings of the sympathetic nerve.
Ultraviolet rays lower the tone of the sympathetic nervous system.
The tonic influence of light on the animal organism has long been noted.
This action ("photodermatic reflex") is also detected in animals devoid of vision (Graber).
In lower animals, there is an antagonistic action of blue and red light (Finsen).
Such antagonism also affects the muscle tone of humans.
Illumination with the red color of a Sollux lamp of certain areas of the skin affects horizontally extended arms, deflecting them in the direction of the illumination.
When irradiating with blue light, however, a deflection in the opposite direction is observed (Ehrenwald's photodermatic reflex).
Blue light, acting on the skin, strengthens, while red weakens the associative-motor reflex in humans (Brushtein).
The reflex action of infrared rays on internal organs is of great importance for therapy.
The redness on the skin of the abdomen caused by them increases the tone and peristalsis of the stomach musculature and reduces abdominal pain.
In humans, higher and lower animals, pigmentation develops under the influence of light.
However, pigmentation as a manifestation of a biological reaction can arise not only under the influence of light, but also under the influence of a number of other irritants.
In almost all animals, the coloration of parts of the body subjected to the action of light turns out to be more intense (Finsen).
The skin of the dorsal surface of the human hand is colored more strongly than the palmar one.
As a result of previous photodermatitis, pigmentation develops.
However, with gradual irradiation, skin pigmentation can develop even without prior inflammation.
As for which rays cause the development of pigmentation, short-wave rays must be placed in the first place (Unna, Finsen).
However, both the visible part of the spectrum and, possibly, its dark thermal part also take part in this.
The question of the appearance of pigmentation under the action of so-called thermal rays has aroused very great practical interest in recent times.
Kisch obtained intense darkening of the skin after exposure to apparatuses that emitted almost no short-wave rays.
In his opinion, short-wave rays alone are not able to cause skin darkening at all analogous to that which is obtained from solar rays.
At the same time, he cites the observation that the skin of patients, strongly pigmented from the action of solar rays, gradually lost its pigmentation while continuing treatment with a mercury-quartz lamp.
How does pigment arise? Is it a product of the coloring matter of the blood, or does it arise in the epidermis of the skin?
A whole series of studies has established that the pigment arises in the epidermis itself and is not carried there.
Skin pigmentation must apparently be attributed to the activity of the basal layers of the epidermis, as a manifestation of a reaction to irritation.
Moreover, such a reaction—the formation of pigment—is observed not only under the action of light; it also occurs with other irritations—chemical, thermal, and mechanical. What role does pigmentation play? There are various opinions on this matter. According to some (Unna, Finsen), pigment serves as a kind of fuse for the organism, protecting the underlying layers from the harmful action of rays. According to some authors, pigment has an essential role in the regulation of heat in the organism. However, there are also opponents of the view regarding the positive role of pigment. Rost, for example, even directly points to the necessity of avoiding the formation of pigment as a phenomenon that hinders the therapeutic effect. Thus, the significance of pigment in the organism cannot yet be considered established with sufficient certainty. In therapeutic practice, however, the question always arises: how should one regard pigment? Is it necessary to strive for its appearance? We believe that in phototherapy, pigment is primarily a manifestation of the organism's reaction to the action of short-wave rays on the skin. Not considering these or other views on its significance to be sufficiently grounded, we, based on our experience, come to the conclusion that a therapeutic effect can be expected more likely in cases where the skin reacts with a pronounced photoerythema and where more or less significant pigmentation develops. In the majority of cases, however, we regard the appearance of pigmentation as a manifestation of the organism's capacity for a positive reaction. What is the mechanism of the action of light? How can one imagine its therapeutic influence? The main site of application of light irritation is undoubtedly the skin, which perceives it directly through nerve endings (including sympathetic ones), which are very numerous in it. Through them, the irritation is transmitted via the central nervous system to the internal organs, causing various reactive phenomena in them (reflex theory). This same action can also be realized in another way. In the skin, under the influence of irradiation, special substances are produced, partly penetrating into the bloodstream, and partly irritating the nerve endings directly, and thus, through the blood, indirectly affecting the nervous system. Light causes the disintegration of numerous epidermal cells (according to Keller, irradiation of the entire body with a quartz lamp only to the degree of slight reddening results in up to 12 million damaged cells). Thanks to such cell damage, inflammation-causing products of cellular disintegration arise. At the same time, from the cells damaged by light, there occurs a diffusion into the tissue spaces and lymphatic pathways of a special vessel-dilating substance of a histamine-like nature. This histamine substance causes photoerythema and is the cause of vasodilation after mechanical, thermal, and other skin irritations. Products of protein disintegration partly enter the bloodstream as well. The favorable influence of various skin irritations on pathological processes is explained by the protective capacity inherent in the skin, which Hoffmann calls “esophylaxis” and which consists in the formation of skin hormones, named by him “dermo-lexins” (see also Heliotherapy, Irradiated preparations). Treatment with light. The therapeutic action of light is based on its stimulating action, which increases the vital tone of tissues, and on its influence on the growth and development of the organism. Furthermore, light influences the nervous system, pulse, blood pressure, metabolism, and blood composition. Light possesses an undoubted analgesic effect. One must also reckon with the bactericidal action of light. Finally, it is necessary to note its diaphoretic and resolvent action, and its ability to induce a special inflammatory state in the skin, accompanied by persistent vasodilation. In particular, the application of infrared radiation is indicated in cases where the therapeutic influence of hyperemia is intended. It is contraindicated in acute inflammatory processes, since as a result of the application of infrared rays, an intensification of pain may occur; then, in purulent processes in cases where it is possible to expect the spread of infection to the entire organism, and finally, in pathological processes accompanied by a tendency to bleeding (Wellisch). In treatment with light, attention was naturally first turned to the sun as a source distinguished by its accessibility and possessing rays of various wavelengths. However, sunlight is not distinguished by constancy. Its brightness changes depending on the weather, cloudiness, dust, etc. When passing through the atmosphere, sunlight loses a more or less significant part of its rays depending on the state of the atmosphere, the purity of the air, and the height of the sun (see Heliotherapy). Phototherapy utilizes light, both solar and artificial. Both are applied either in a form not decomposed into their constituent parts or in the form of separate parts of the spectrum—both in concentrated and non-concentrated form. Sun treatment (see Heliotherapy). Recently, thanks to the works of Dorno and Hill, and in our country, Kalitin, the use of scattered radiation from the blue sky for therapeutic purposes has been of particular interest. In this case, a great biological effect is obtained, and overheating of the body does not occur. The application of such radiation should have particular significance in pediatric practice. Besides the use of solar radiation in toto, phototherapy knows another type of sun treatment, where not the entire spectrum is applied, but its separate parts (chromotherapy). There are the following grounds for such therapy. Thus, Goethe had already noted the influence of colored lighting on mood. In 1881, Moleschott and Fubini published their studies on animals whose eyes had been completely destroyed with scissors and a red-hot iron. In experiments with the influence of various colors (liquid filtrates), the authors obtained the following results. Blue-violet and red light increase the excretion of CO2 in birds and mammals, with red light doing so somewhat less. Red light has absolutely no effect on frogs. In blind mammals, violet and red light likewise intensifies the excretion of carbon dioxide, although to a lesser degree than in sighted ones. The amount of excreted carbon dioxide increases with the intensification of light. This fact is observed equally in both blind and sighted animals. In relation to nitrogen metabolism, there are studies indicating that red light weakens the processes of assimilation and dissimilation, while yellow and violet light, especially the latter, most increase vital processes (Kogan). Under the influence of different lighting, the pulse volume changes. Violet light acts most depressingly on the pulse, and red light least. Akopenko investigated the influence of colored rays on the speed of psychic processes and came to the conclusion that colored lighting undoubtedly influences this phenomenon, and moreover, different rays exert different actions depending on their position in the spectrum. Rays located closer to the thermal end of the spectrum act more invigoratingly. At the same time, mood also changes: it becomes more cheerful and lively. Yellow color occupies an intermediate position. Its influence on psychic processes is not captured. Green color already reveals a slowing, depressing influence. Such an action increases as one approaches the violet part of the spectrum. Violet color influences both the speed of psychic processes and mood extremely strongly, producing a sharply depressing effect. There are many indications regarding the influence of light, and in particular its individual colors, on the nervous system. Our studies using the method of associative-motor reflexes (see above) provide objective indications that the human nervous system reacts differently to different colors of the spectrum. Ponza found that under the influence of red light, the depressed mood of patients was replaced in a few hours by a good disposition. Patients who had previously refused food ate with appetite. Blue color exerted a calming effect on manic-excited patients. Schlager, on the basis of his observations, came to the conclusion that in the majority of cases, when applying light to the mentally ill, no influence can be detected. In some cases, however, during a state of strong agitation, calming occurred, and moreover, shortly after placing the patient in a blue room. Finsen, proceeding from the fact that light irritates the skin, mainly with rays of a shorter wavelength, proposed treating smallpox patients with red light by placing them in wards whose windows were covered with red fabric. As a result, the suppuration of the vesicles was very insignificant, as was the suppurative fever. There were also no pitted scars on the face. Finsen's observations were confirmed from various sides, although there are also indications of the insufficient effectiveness of this method. Goldmann vaccinated against smallpox under red light and applied a red bandage to the site of vaccination. In this case, no swelling of the axillary glands or inflammatory reaction around the smallpox pustules was observed. In control observations, however, where the vaccination was performed under ordinary conditions, a rather significant reaction was always observed.
At the same time, even with a weak reaction in the first observations, complete immunization was achieved. Repeated vaccinations after five weeks gave a negative result in them. Besides1 smallpox, the use of red color has also been proposed for measles, erysipelas, and scarlet fever. Furthermore, there are indications of the beneficial effect of red color in certain skin diseases. Winternitz, in cases of chronic eczema, covered the parts exposed to the sun with red fabric and observed a reduction in skin hyperemia and an improvement in the painful symptoms. Along with sunlight, chromotherapy also uses, and to a greater extent, incandescent electric light and arc light (Minin lamp, Sollux, spotlight with color filters, etc.). The significance of concentrated light for therapy was first appreciated by Finsen. Initially, Finsen used sunlight, but then he switched to electric light. Electric light in phototherapy is used in the form of voltaic arc light, as well as in the form of incandescent light.
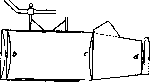
Fig. 1. Diagram of the construction of the collecting apparatus. This includes the following devices: 1) Finsen's large collecting apparatus for the treatment of lupus [see separate table 2 (p. 711-712), Fig. 4]. This device aims to collect and concentrate rays on a specific diseased area. The apparatus itself appears as follows: in two copper cylinders, sliding one into the other like a telescope
(Fig. 1), four lenses made of quartz or rock crystal are placed (only such a lens transmits ultraviolet rays). These lenses have the task of making diverging rays converging. Between the lenses is distilled water for absorbing heat rays. The light source is a voltaic carbon arc of 60-80 amperes, suspended from the ceiling in a special metal case. One arc serves 4 collecting apparatuses simultaneously. However, the radiation of such an apparatus still produces thermal irritation, which eventually becomes very sensitive for the patient. Furthermore, it was established by research that tissues rich in blood, for example, the skin, absorb ultraviolet rays. Therefore, Finsen introduced his compressors into practice. They consist of a wide metal ring, on both sides of which are placed two round plates of rock crystal. Cold water, circulating all the time, is passed through the cavity formed by the plates. Such a small device is applied to the place being subjected to irradiation, and thereby, on the one hand, cooling is achieved, and on the other, pressure and, consequently, local bloodlessness. The described device—the original Finsen apparatus—appears relatively expensive, quite complex, and consumes a large amount of electrical energy during operation. Therefore, the desire to simplify the apparatus itself appeared soon after its introduction into practice. A quite significant number of devices were proposed, of which we will mention only a few. Lortel and Genaud proposed a lamp with a current strength of 15-20 A, with the light source being at a distance of 3-4 cm from the patient's skin, whereas in the Finsen apparatus it is 100 cm. However, this lamp did not achieve the goal, as it did not provide sufficient concentration of rays with its relatively weak light source. A more successful proposal should be considered that of Finsen's closest student, Axel Reyn. The Reyn apparatus likewise consists of a collecting device and is adapted for illuminating only one patient. The arc
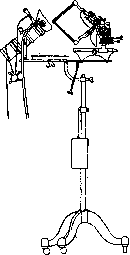
Fig. 2. Finsen-Reyn apparatus. The arc lamp (50 V and 20 A) is constructed in such a way that the carbons in it are positioned at an angle to each other, which achieves the direction of radiation towards the concentrator, which is designed on the same principle as in the large Finsen apparatus.

Figure 3. General electric light arc bath.
The entire device is mounted on a stand, allowing its movement in various directions. Otherwise, the compressors are the same as with the large apparatus. The Finsen-Reyn lamp, emitting a fairly strong concentrated radiation, is the most successful replacement for the original apparatus (Fig. 2). 2) General electric light arc bath. The radiation of a voltaic arc (with carbon electrodes) is in its properties closest to sunlight. At the same time, the spectrum of arc light is continuous, i.e., it does not have those absorption bands that are present in the solar spectrum due to the latter's loss of certain rays when passing through the atmosphere (Fraunhofer lines). Arc light is used mainly for local treatment and only partly for general treatment. Furthermore, it is used in the form of non-concentrated radiation, in concentrated form, and finally after reflection from reflectors. For general use, carbon voltaic arcs suspended from the ceiling are used, with the radiation spreading throughout the room, in which naked patients are placed (Fig. 3). With sufficient radiation strength and with 10-15 minutes of application, erythema begins to develop on the skin, as happens with sunlight. For such a chemically strong light bath, the Finsen clinic uses an arc lamp of 150 A or two lamps of 75 A at 50 V. The carbons are installed vertically. The lamps are equipped with regulation. The patient is placed clo
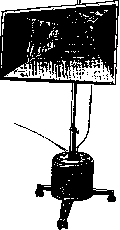
Figure 4. Jesionek lamp.
se to the lamp at the closest possible distance, as far as the high temperature developed by it during burning allows. The face and genitals, as well as the patient's eyes, are protected. Since the heat from such a lamp reaches a significant degree, the necessity became clear to arrange some kind of device that would eliminate this drawback. This goal is very successfully achieved with the help of a cooler proposed by Mahler. The construction of such a cooler consists in the fact that between the lamp and the patient, cold water flows during the entire session from a specially constructed flat funnel in the form of a kind of water wall, which absorbs the heat developed by the arc lamp. The duration of the bath depends on whether it is desirable to cause strong or weak erythema. Usually, sessions begin with a 5-minute duration. Then they wait 2 days to find out what the reaction is. After that, they gradually reach a 30-minute session duration, prescribing a bath every 3-4 days. As a rule, it is necessary that erythema appears after each bath. 3) Spotlight. This device consists of an arc lamp of 10-30 A, enclosed in a metal nickel-plated cylinder. Behind the arc, a movable reflector is placed, which makes it possible to cast rays onto the patient's body with sufficient fullness. The radiation of such a spotlight is quite significant, and moreover, it contains rays of both long and short wavelengths. The spotlight is used in cases where an analgesic and resolving effect is required (neuralgias, myositis, arthritis, exudates, etc.). 4) Having the greatest significance in therapy are mercury-quartz lamps. Back in 1892, Arons in Berlin established that mercury vapor in rar
efied air, when an electric current passes through it, gives radiation richer in the ultraviolet part than arc carbon light. Kromayer in 1905, introducing some technical modifications, proposed his mercury-quartz lamp for the treatment of skin diseases according to the principle of the Finsen method. More perfect is the Bach lamp (see Bach mercury-quartz lamp). For irradiating the entire body and simultaneous use by several people, Jesionek constructed a special apparatus consisting of a mercury-quartz burner of up to 3,000 candles and a large reflector (Fig. 4). 5) Cold quartz lamp (Ultrakontaktlampe), distinguished by the fact that the burner in it heats up so insignificantly that it can be brought into direct contact with the skin or mucous membrane (Fig. 5). 6) Quartz-cadmium lamp (poles consist of cadmium). The radiation spectrum is especially 76v
Fig. 6. Quartz-cadmium lamp. [It is] rich in lines between 330 mµ and 350 mµ, as well as between 280 mµ and 298 mµ (Fig. 6). 7) In order to approximate the radiation of artificial sources to the solar spectrum, a number of devices have been proposed: a) The Siemens aureole lamp consists of a glass bulb containing a carbon voltaic arc; b) Spectrosol lamp. The radiation source is a metal filament placed in a glass tube; c) Landeker's Ultra-Sonne with a voltaic arc, the carbons of which, thanks to metal impregnation, possess the property of intensely producing ultraviolet rays. Due to the absence of irritating rays, the light of this lamp is especially suitable for irradiating mucous membranes (vagina, mouth, etc.). 8) Incandescent light. In addition to the already mentioned use of the blue bulb (Minin), electric light baths, both general and local, are widely used. The general electric light bath was proposed by the American physician Kellogg. A bath of the usual type is in the form of a cabinet having the shape of an octagonal prism, the height of which is such that the head of an adult sitting in it on a chair is outside. For the latter purpose, a hole of the appropriate size is cut in the lid. One can enter such a bath only through a special door. Inside the bath, in the middle, is placed a screw chair, rotating around its axis and also providing the possibility, if necessary, to raise or lower it in height. Along the walls of such a box, incandescent bulbs with a power of 16-25 candlepower are evenly placed, of one or several colors, in the amount of 50-90, and in some baths, 3-4 voltaic arcs of 800-1000 candlepower each are installed on the sides. Both incandescent bulbs and voltaic arcs allow for gradual and separate switching on. In addition, for the purpose of regulating the received radiation, a rheostat is introduced into the circuit. Through special small windows, one can observe the body of the patient, as well as examine the state of his pulse. A thermometer is built into the lid of the bath (the mercury bulb is inside), showing the air temperature in
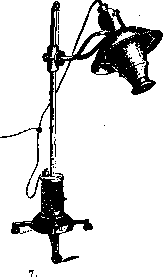
Solux lamp. [in] it. The walls of such a light box are lined with mirrors, milk glass, painted with white enamel paint, etc. Physiotherapy also uses so-called intensive light baths, which include "Radiotherm" and "Polysol". These baths, while retaining the same design as ordinary ones, differ from them in the shape of the bulbs and the provision of each bulb with a special reflector. The bulb of such a bath is in the form of a long tube with a vertically standing incandescent filament, and not in the shape of a coil, as is the case in ordinary pear-shaped bulbs. Behind the lamp is placed a special rotating reflector, which is set so that the lamp filament is exactly in its focus. In an ordinary electric light bath, a large part of the rays, despite reflection from the walls, does not reach the patient. Barely 1/10 of the radiation reaches him. At the same time, due to the heating of the walls of the bath and the air inside it, the temperature around the patient increases extremely - on average to 60-70°. In an intensive light bath, the air surrounding the patient is heated
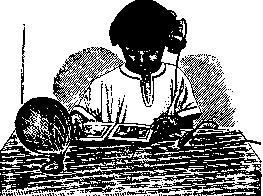
Fig. 8. Small Solux lamp directly applied to the surface of the body
relatively little, and significantly more rays reach the patient. To achieve the same radiation that a patient receives in an ordinary electric light bath, it would be sufficient to install 5 tubular lamps with reflectors in an intensive light bath. However, in this case, the air temperature in the bath would be too low. For this purpose, 16-20 tubular incandescent lamps with the same number of reflectors are installed in intensive light baths. Thus, the radiation in such a bath will be 3 or more times stronger than in an ordinary one. The air temperature of the bath in this case is 25-40°. The general electric light bath is an agent that causes more or less significant changes in the physiological functions of the organism. These boil down to an increase in body temperature, an increase in pulmonary gas exchange and general metabolism, increased sweating, rapid breathing, changes in cardiac activity and blood pressure, and changes in the blood and functions of the nervous system. All these data fully justify the therapeutic use of general electric light baths, although here, as in many other cases, medical practice has gone far ahead and left the study of physiological influence behind. The extremely wide spread of electric light baths has contributed to the fact that they began to be used outside of medical supervision, under the guidance of persons unable to realize the seriousness of this means. Such baths require strict individualization, and therefore the first 2-3 sessions must be conducted in the presence of a doctor, who must establish the temperature and duration of the bath. Cases have been observed where the improper use of such baths has caused harm to the patient. Local electric light baths, intended, as their very name indicates, for application to one or another part of the body, are constructed in a corresponding manner. The action of local electric light baths is the same as that of general ones. They present, in comparison with the latter, some features related to the possibility of subjecting not the whole body of the patient to the influence, but one or another part of it. Therefore, with a local bath, a significantly higher temperature (up to 100° and higher) is tolerated. Unpleasant side effects (flushes to the head, states of weakness, excitement, etc.) are usually not observed. Duration

O O O: O O
Figure 10. Device for determining individual photosensitivity. Figure 9. Profundus lamp. The duration of the session is on average 20-30 minutes. Indications are mainly gouty and rheumatic diseases of the bones, joints, muscles, tendons, transudates and exudates, etc. 9) The Sollux lamp is a glass hood containing a luminous body [an incandescent lamp with a metal tungsten filament (Figs. 7 and 8)]. 10) The Profundus lamp consists of a wire rheostat that heats up when current passes through it, but not to the point of incandescence. It emits only infrared rays (Fig. 9). Dosimetry. In practice, the dosage of ultraviolet rays is of particular importance. However, this problem remains unresolved to any satisfactory degree. Among the methods proposed for this purpose, we note the following: 1) chemical method - the Bering and Meyer method, improved by Keller. It is based on the release of free iodine from an acidified solution of potassium iodide under the influence of ultraviolet rays; 2) photographic method: a) Keller's erythema dosimeter (the most common) is based on the blackening of photographic paper placed under glass filters under the influence of rays; b) Zalkindson's photoquantimeter is based on the property of chloro-silver paper to change its color under the influence of violet and ultraviolet rays. The unit (1 UFE) is taken as the tone of darkening of aristotype paper, which is obtained from irradiation with a new alternating current burner at 110 V at a distance of 1 m and an exposure of 1/2 min. In this way, it is possible to measure with greater or lesser accuracy the magnitude of the incident radiation in the ultraviolet part. As for the individual sensitivity of a particular patient, it is determined in a very simple way. For this purpose, 5 small circles with a diameter of 2 cm are cut out on a piece of paper (Fig. 10). Covering the rest of the skin, all circles are irradiated sequentially for 1-2, etc., minutes each. The next day, from 5 different degrees of erythema, one can choose the desired one and use it for the planned session. Regarding dosage for various diseases, a scheme covering 5 groups (Zalkindson) has been proposed (see table). Photopathology. Irradiation of excessive intensity in individuals with normal photosensitivity, on the one hand, and irradiation of medium intensity in particularly light-sensitive subjects, on the other, can cause a painful condition. Under normal conditions of the light regime (climatic and others), people with normal photosensitivity do not get sick from exposure to light. A known predisposition - increased sensitivity to light - therefore plays a major role in the pathogenesis of diseases caused by light. They are divided into endogenous and exogenous. Exogenous diseases include those after prolonged intake of eosin and diseases in workers dealing with certain coal-tar dyes. Among the endogenous ones are known hydroa, some forms of urticaria, eczema solare, xeroderma pigmentosum, and some others. Mercury-quartz irradiation of cases of latent malaria can cause an exacerbation of the disease and the appearance of parasites in the peripheral blood. Phototherapy for individual diseases. Internal diseases. Of metabolic diseases, phototherapy finds application primarily in diabetes. Ultraviolet rays reduce the sugar content in the blood. A mercury-quartz lamp, Ultrasonne (for irradiation of mucous membranes), Sollux (blue filter), and a local electric light bath are used. For obesity, sun baths and general electric light baths are recommended. In view of the effect of short-wave rays on metabolism and in particular on purine metabolism, general and local application of a mercury-quartz lamp is recommended. Furthermore, sun baths and general electric light baths with incandescent bulbs. In states of exhaustion due to physical or mental overstrain, as well as in the stage of convalescence, general ultraviolet irradiation is recommended. In secondary anemia, general mercury-quartz irradiation has a beneficial effect. Regarding diseases of the respiratory apparatus, phototherapy for pulmonary tuberculosis is of particular importance. Despite the large discrepancies existing on this issue in the literature, one thing is certain: when using phototherapy in cases of pulmonary tuberculosis, it must be carried out extremely carefully, only gradually increasing both the size of the irradiated surface and the duration of irradiation (Rollier). This should apply equally to sun therapy and to artificial sources (mercury-quartz lamp alone or in combination with Sollux). When clarifying the mechanism of the action of light in tuberculosis, it is necessary to proceed from the idea of tuberculosis as a disease of the entire organism. Treatment should pursue the task of increasing immuno-biological processes in the body. On the other hand, phototherapy is one of the types of non-specific therapy that gives the desired effect with proper dosage. In this case, phototherapy acts by causing inflammatory changes in the skin, accompanied by an increase in the vital activity of cellular elements, the formation of special substances irritating various tissues and organs (esophylaxins), as well as the formation of vitamin D. Along with this, there is irritation of nerve endings in the skin, leading reflexively to a decrease in the tone of the sympathetic nerve with subsequent hyperemia. The roborant influence of light (especially during insolation) on the psyche of patients (Brushtein) also remains significant. Irradiation with a mercury-quartz lamp is indicated for the sequential treatment of acute pneumonias - croupous and influenzal (resorption of infiltrates), as well as dry and exudative pleurisy. For limited, long-standing exudates, a spotlight with a red filter, Sollux, and infrared light are indicated. One can sometimes use a Minin lamp (but not blue, rather red). Duration of irradiation 15-20 min. For chronic bronchitis - a spotlight on the front and back of the chest, 10-15 min. For bronchial asthma - a spotlight, general electric light baths (Strümpell), ultraviolet irradiation, infrared light. For diseases of the cardiovascular apparatus, the use of ultraviolet therapy is based on the reduction of high blood pressure and is indicated for such conditions as arteriosclerosis, essential hypertension, renal hypertension. For local circulatory disorders - blue arc light or Sollux lamp, local electric light bath (Laqueur). For angina pectoris - ultraviolet irradiation. Of abdominal diseases, the use of a mercury-quartz lamp is indicated for tuberculous peritonitis. The best results are obtained in peritonitis with serous exudate, with a cure rate of 50-70%. For scars and adhesions in the abdominal cavity - voltaic arc light or Sollux (blue at first, in case of significant irritability, and then red). For ulcus ventriculi (duodeni), intensive local irradiation with a mercury-quartz lamp is recommended. For diseases of the stomach, intestines, and gallbladder - infrared irradiation. For kidney diseases (chronic nephritis), sun baths are used, as well as mercury-quartz irradiation. An attempt with a satisfactory result was made in initial forms of influenza, with the torso being subjected to ultraviolet irradiation with suberythemal doses (in some cases together with Sollux). In case of sharply pronounced symptoms in the throat and nasal mucosa, these areas were also subjected to irradiation. Observations were conducted on workers at the "Kauchuk", Lyubertsy, and Kolomna factories. As a result - a rapid drop in temperature and the disappearance of catarrhal symptoms. A beneficial effect of general whole-body irradiation in carbon monoxide poisoning was noted. General ultraviolet irradiation is used for prophylactic purposes, e.g., in school-age children and in sports training. Ultraviolet irradiation increases work capacity. In rheumatic diseases (in the understanding of the unified classification adopted by the All-Union Committee for the Study of Rheumatism and the Fight Against It), phototherapy in the form of electric light baths, mercury-quartz lamp, and Sollux is widely used in cases of chronic polyarthritis. In acute articular rheumatism, mercury-quartz irradiation causes pain relief and has a beneficial effect on the course of the process.
Infrared rays are widely used both for chronic rheumatism and for acute rheumatism. For chronic articular rheumatism with a tendency toward deformities, a combination of infrared baths with subsequent ultraviolet irradiation is recommended. For muscular rheumatism: sun baths, electric light baths, red spotlight, Sollux, Spectrosol. For myalgias: quartz in combination with Sollux. For rheumatic neuralgias: quartz, Minin's blue light, Sollux, Spectrosol. For nervous diseases, phototherapy is used mainly for conditions accompanied by pain. The analgesic effect of solar irradiation has long been known. In the study of the local application of strong electric light, especially its so-called chemical rays, Russian doctors played a significant role. Stein and Gachkovsky were the first to note the analgesic effect of the light of an incandescent electric bulb. As for the light of the voltaic arc, the first observations belong to Ewald, a doctor at the Kolomna plant in the early 90s of the 19th century. Ewald noted that since the introduction of cast iron smelting at the plant using the Benardos method (electric smelting), the number of workers suffering from rheumatism, neuralgias, migraines, etc., had sharply decreased. Having found that the workers had found the source of their healing by exposing the diseased part of the body to the light emitted during such smelting, Ewald set up a phototherapy clinic in his factory hospital, where he began to treat various nervous and rheumatic diseases with great success. Subsequently, observations were conducted by Kozlovsky and Griboedov based on the same principle, and these authors obtained very encouraging results in the treatment of various kinds of neuralgic diseases. Furthermore, in 1909, Brushtein first proposed the use of a mercury-quartz lamp for neuralgias. Subsequently, Brushtein's observations were confirmed from various sides. Erythema doses of quartz often give good results for shooting pains in tabetics. There are observations indicating the favorable effect of general ultraviolet irradiation in parkinsonism. Furthermore, sun baths and general ultraviolet irradiation can be used for neurasthenic conditions. Among mental diseases, in patients with manic-depressive psychosis and in schizophrenics, under the influence of ultraviolet irradiation, some improvement in appetite, weight gain, revitalization of muscle movements, and improvement in well-being have been noted. The same applies to the use of colored lighting: blue for states of agitation and red for states of depression. Skin diseases. Regarding the treatment of skin tuberculosis with light, see Tuberculous diseases of the skin. Diseases of the hair and skin of the scalp are amenable to treatment with a mercury-quartz lamp (alopecia areata, alopecia seborrhoica). Subacute and chronic forms of eczema often respond well to quartz therapy. For lichen ruber, mercury-quartz irradiation gives exceptionally good results (Jesionek). The same for psoriasis. Children's diseases. There are numerous observations regarding the favorable effect of sun therapy on rickets. Recently, the question of treating rickets (see) with a mercury-quartz lamp has aroused great interest. It has been established that only a narrow strip of the spectrum with a wavelength of 302-289 mµ (Ra-Strahlen) exerts this therapeutic effect in rickets. The antirachitic effect of ultraviolet irradiation is based on its action on ergosterol, which is thereby converted into vitamin D. Preventive irradiation of children undoubtedly contributes to protecting them from contracting rickets [see separate table (col. 711-712), fig. 5]. Regarding the use of ultraviolet rays of the solar spectrum, see Lighting. Mercury-quartz irradiation is very effective in rachitogenic therapy and in childhood asthma. Ultraviolet irradiation is further recommended for scrofulosis, whooping cough, and erysipelas of newborns. There are positive observations regarding ultraviolet irradiation of diphtheria bacillus carriers. Surgical diseases. Irradiation with mercury-quartz light is a very effective remedy for poorly healing wounds and sluggish granulations. It can enhance the process of epithelialization. Ultraviolet rays are indicated for wound infections. Good results have been obtained for superficial wound infections with B. pyocyaneus; the same for tetanus-infected wounds. When workers who had sustained injuries were irradiated with a mercury-quartz lamp at the "Kauchuk", Lyubertsy, and Kolomna plants, not a single case of complication was noted, and a large reduction in cases of abscesses, phlegmons, and loss of working days due to them was achieved. In the matter of treating surgical tuberculosis with irradiation, the school of Prof. Bier occupies a special place. Based on observations conducted over a number of years at the clinical sanatorium in Hohenlychen near Berlin, Bier's assistant, Kisch, published a special monograph, which sets forth the basic tenets of the school on this issue. Kisch criticizes existing views on the role of ultraviolet rays in pigment formation, on the physiological significance of pigment, and other questions of theory as well as the practice of phototherapy, and arrives at a whole series of propositions that do not coincide with more or less established notions. He asserts that pigmentation is caused not only by ultraviolet rays but also by rays of longer wavelength, and that perhaps the latter are capable of producing such strong pigmentation, which is never achieved, for example, by a mercury-quartz lamp, which is, as is well known, especially rich in ultraviolet rays. Based on the measurement of skin temperature at sites that were artificially pigmented and non-pigmented, he concludes that the main task of pigment is the regulation of heat in the body. The author identifies the essence of the action of heliotherapy with the action of passive hyperemia. By combining both methods, he achieved a sharp enhancement of the therapeutic effect. Regarding sun therapy in the mountains, Kisch expresses himself decisively to the effect that it has no advantages over the same on the plains, especially in summer, [and] some [advantages] in spring and autumn; as for winter, here the difference can be very significantly smoothed out by the hyperemizing power of the Bier bandage and the use of light apparatuses proposed by Kisch, which abundantly emit so-called heat rays. Proceeding from the view that the healing effect of the sun is based on the power of its heat radiation, to which the organism responds by hyperemizing the tissue as a defense against burns, Kisch presents a requirement for the apparatus: to develop a high temperature and to induce a real brown coloration of the skin. Such an apparatus was constructed by the Zeiss firm for acetylene and electric light. In Hohenlychen, combined treatment is carried out, with its components being heliotherapy, treatment with artificial light, passive hyperemia, and iodine. Success is achieved in general in 70-80% [of cases]. For various forms of surgical tuberculosis, mercury-quartz irradiation is a very valuable method (for lymphadenitis, for lesions of bones and joints). The methodology boils down to general and local application. For osteomyelitis, sun therapy is an excellent postoperative procedure, i.e., after trepanation of the infected bone (Rollier). Likewise quartz. Interesting is Rollier's experience in organizing a clinic-factory that meets a dual task: to treat patients with extrapulmonary tuberculosis with the sun and to serve as a workshop. The idea was based on the premise that "precisely in tuberculosis, more than in any other disease, the outcome to a significant degree depends on the patient's will to recover," and that labor should stimulate this "will to recover" in chronic patients languishing from idleness and boredom. The wards and terraces of such a clinic (opened in 1930) are built like workshops and are equipped with electric motors as engines. The working patients manufacture parts for small and precision mechanics instruments. More complex work is performed by convalescents in workshops specially located on the lower floor. All work is conducted under the best hygienic conditions, with the workers having the opportunity to simultaneously utilize sun therapy. The equipment is constructed in such a way that its use is possible in any position conditioned by orthopedic requirements. Women's diseases. For direct action on the genital organs, special devices have been proposed. These include: 1) the Seitz vaginal lamp, predominantly of infrared radiation, 2) the Wintz vaginal lamp (in spectrum it approaches the Spectrosol lamp), 3) the Landecker Ultrazonne (see above), and 4) the vaginal attachment for Bach and Kromayer lamps. Good results have been noted for inflammations of the vagina and external parts, for poorly healing perineal tears, and for pruritus vulvae. For endometritis and metritis, a combination of general irradiation with vaginal [irradiation] is recommended. Phototherapy is further indicated for parametritis and perimetritis, as well as for retroflexio fixata caused by old inflammatory adhesions. Combined phototherapy (superficial and vaginal) gives good results for adnexitis and oophoritis. Likewise, phototherapy (quartz, Ultrazonne) has a favorable effect on menstrual disorders, such as: amenorrhea, increased or too frequent bleeding, and dysmenorrheal disorders.
During pregnancy in weak, anemic women, general ultraviolet irradiation is indicated. General mercury-quartz irradiation has a favorable effect on eclamptic seizures. Erythema-producing irradiation also yields good results in cases of insufficient milk supply. Lacker attributes this to cases where the cause lies in the general condition, which is why he recommends administering general irradiation. Ear, nose, and throat diseases. The primary indication is for tuberculosis of the nose.
Eye diseases. Figure 11. Mercury-quartz lamp - Dentaimodeii.
General irradiation with ultraviolet rays is used for keratoconjunctivitis eczematosa (phlyctenulosa) with good results, as well as for hemeralopia idiopathica and keratomalacia. Local irradiation using a Kromayer lamp is used for trachoma and tuberculosis.
Diseases of the teeth and oral cavity. For dental purposes, there is a special device—Dentaimodeii (mercury-quartz lamp). Very good results are obtained in the treatment of cicatricial formations (Fig. 11) in the oral cavity with quartz light, as well as for paradentosis, severe gingivitis, and alveolar pyorrhea. Pain in periodontitis and periostitis in not very acute cases is relieved by the use of a Sollux lamp.
Related articles
Mentioned in
Cite this page
“Phototherapy.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/light-therapy/