Tendon Suture
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This 1930s article from the Great Medical Encyclopedia discusses the techniques, indications, and outcomes of primary and secondary tendon sutures in surgery. It reviews various historical suture methods, materials like silk and catgut, and the debate between postoperative immobilization and early mobilization to prevent adhesions.
Encyclopedia article (1928–1936)
TENDON SUTURE. To restore tendon function when its integrity is disrupted, a primary tendon suture is used. The tendon suture was first used according to Ambroise Paré by Variquell. At the 5th Congress of German Surgeons in 1876, Küster recommended applying a suture to a tendon, and the participants showed great interest in the suture technique. Recently in the medical literature, especially foreign literature, sufficient attention has been paid to the method of tendon suture. At present, there are more than 20 methods of applying a tendon suture. Such a large number of methods shows that in this direction there is still no single method that would meet all requirements and yield good results. A tendon suture must meet the following requirements. It must provide good contact between the sutured ends of the tendon without cutting through. When applying a tendon suture, necrosis of the tendon should not occur. Subsequently, there should be no adhesion of the tendon to neighboring tissues. The tendon suture method should be technically simple for an average surgeon to perform. The most appropriate moment for applying a tendon suture is the time of primary wound toilet. Only in exceptional cases, with severe infection and crushing of wound tissues, one does not have to resort to applying a primary suture to the tendon.
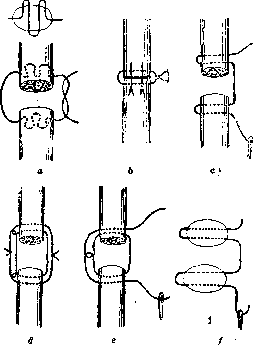
Figure 1: a—Bölflers method; b—Hägler's; c–f—Trnkka.
As a material for tendon suture, most authors recommend silk and only isolated authors (Jensen, Bartels) recommend catgut. Catgut does not guarantee the strength of the suture because it is absorbed very soon and therefore cannot provide the necessary strength to the suture, especially when prescribing early movements after surgery recommended by most authors as a prophylactic method against adhesions of the sutured tendon with surrounding tissues. After the ends of the severed tendon are found, the latter must be freshened and sutured in case of fraying or cicatricial change. It is necessary to strive to apply a tendon suture so that the transverse cuts of the tendon are in good contact and, if possible, avoid lateral overlapping of the tendon ends. The simplest method of applying a tendon suture is Hägler's method (Fig. 1 b), when one suture is applied by piercing the tendon in a transverse direction, and then sutures are applied in a longitudinal direction, making the needle entry below the pierced transverse thread; the latter thus restrains the longitudinal sutures from cutting through. A similar modification was proposed by Friedrich (Fig. 2 a). Not difficult in its technique is the suture proposed by Krasin from Kazan and described by Fishman (Fig. 2 b) and Lange (Fig. 2 c and d). Krasin's method consists of splitting the ends of the severed tendon over a length of 1 cm into equal halves, inserting a piece of fascia specially cut from the neighborhood into the split ends, and fixing the tendon ends together with the fascia using 4 sutures at the corners. The Lange method is the application of sutures to the ends of the tendon in the longitudinal direction, a mattress suture. Technically somewhat more difficult is the application of the suture according to Wölfler (Fig. 1 a) and Trnkka (Fig. 1 c–f). The latter applies a suture in the form of a through double loop in the transverse direction. Experimental determinations (Kimura, Malevitsch) of suture strength on corpses with suspended weights up to 3,000 g on tendons sutured by various methods showed that the strength of the tendon suture according to the methods of Wilms, Lange, and Hägler is quite large. It is recommended to open the tendon sheath along its lateral surface with subsequent application of fine sutures to it. Bier and Hueck do not recommend suturing the tendon sheath. To avoid subsequent adhesion of the tendon to the skin scar, it is proposed to make the skin incision not over the tendon, but, for example, in the form of a flap incision. After applying the tendon suture, some recommend giving rest to the limb for 8–10 days (Pels-Leusden), for 2–3 weeks (Just), while others advise early movements: Bier from the 8th day, Dreyer and Bayer immediately after surgery. The bandage is usually applied with tendon sutures of extensors in the position of maximum extension and with tendon sutures of flexors in the position of maximum flexion. Müller believes that tendon healing occurs after 8 days. Nevertheless, cases have been described (Just) when tendon rupture occurred 30 days after suture application. The prognosis regarding the functional result after applying a primary suture is considered good by most

authors consider it good, while other authors are pessimistic about the final result. In particular, Bier points out a good result
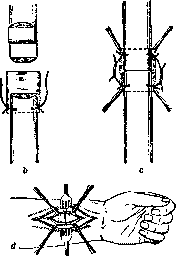
Figure 1: a—Friedrich's method; b—Fishman's; c and d—Lange's.
for extensor tendon sutures; as for flexors, especially of the fingers and hand, the final results of suturing leave much to be desired. The causes of failures lie, on the one hand, in wound infection, and on the other hand, in cicatricial adhesion of the tendon to neighboring tissues. In case of wound infection, there is a great danger of infection spreading to the tendon sheath. It is necessary to immediately release the skin sutures and carry out wound treatment in the usual way; in this case, sometimes the tendon suture is preserved, and in individual cases, recovery even occurs with preservation of function. According to Müller, out of 136 cases, suppuration occurred in 46, and recovery ensued. Failures caused by tendon adhesions to neighboring tissues were found, according to Lier's study of 450 injuries of finger and hand tendons, in extensors in 39.5% and in flexors in 53%. The percentage of cures after primary tendon suture for individual authors is as follows: Authors Cure percentage extensors flexors Dubs 45 62 22 20 10 38 80 68 85 50 61. These figures show that the final result for flexors is significantly worse compared to extensors. To avoid subsequent adhesion of the tendon to neighboring tissues, some authors (Henschen) recommend surrounding the tendon with adipose tissue, while others for the same purpose advise creating a sort of sleeve for the tendon from a vein (Thole), from gelatin (Lotheissen), and by other means. Recently, most authors lean toward the use of early movements as the method giving the best guarantee against subsequent adhesion, and recommend starting movements on the 2nd–3rd day after surgery. The application of a secondary tendon suture must be performed after complete healing of the skin wound, but not earlier than 1 month. The prognosis when applying a secondary tendon suture is poor according to many authors, and therefore they suggest refraining from applying a secondary suture, especially on flexors. Statistical data from Lier and Dubs clearly show this. Authors Muscles Cure percentage primary suture secondary suture Dubs Flexors — 10 Extensors — 50 Lier Flexors 38 17 Extensors 61 32. The authors see the reason for such a poor result of secondary tendon suture, firstly, in the rapidly occurring muscle atrophy, and therefore Rehn recommends in such cases to suture the proximal end of the tendon to a healthy muscle or to a neighboring tendon; secondly, during secondary tendon suture surgery, the operation is complicated by the appearance of a large defect between the tendon ends after excision of scar tissue and freshening of its ends, so that the application of a secondary tendon suture is often accompanied by high tension. In such cases, it is better to use tendon plastics. The final result after applying a secondary tendon suture is unfavorable in the majority of cases, and therefore it is necessary to strive during primary wound toilet to apply a primary tendon suture with the use of early movements after surgery.
I. Minin
Related articles
Mentioned in
Cite this page
“Tendon Suture.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/tendon-suture/