Lymphatic System (LYMPHATIC SYSTEM)
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the first edition of the Soviet Great Medical Encyclopedia details the anatomical structure, distribution, and pathways of the lymphatic system, including lymphatic vessels and nodes of the human body.
Encyclopedia article (1928–1936)
LYMPHATIC SYSTEM (GLANDS, VESSELS)
The section of the lymphatic vessels of the digestive tube, which continue in the form of lymphatic trunks located in the mesentery until they connect with the thoracic duct, bears the name of lacteal vessels (Figure 14). The lymphatic vessels of the intestines (lacteals) (see Intestine), having passed through the lymphatic glands of the mesentery, gather into a single trunk (sometimes 2–3), truncus intestinalis, which flows into the initial end of the thoracic duct (cisterna chyli), located on the anterior surface of the two upper lumbar vertebrae.
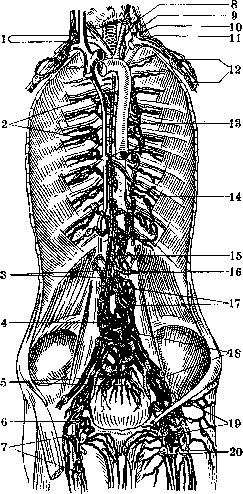
Figure 13. Lymph glands of the axillary and subclavicular regions, pelvis, posterior abdominal wall, and thoracic cavity. Main trunks of the lymphatic system—thoracic (left) duct and right duct, their formation and connection with veins: 1 — ductus lymphaticus dexter (truncus jugularis dexter et truncus subclavius dexter); 2 — lymphoglandulae intercostales; 3 — trunci lumbales dexter et sinister; 4 — plexus lymphaticus lumbalis; 5 — lymphoglandulae sacrales; 6 — Rosenmüller's lymph gland; 7 — lymphoglandulae subinguinales; 8 and 13 — ductus thoracicus; 9 — vena jugularis interna; 10 — truncus jugularis sinister; 11 — truncus subclavius sinister; 12 — lymphoglandulae axillares; 14 — vena hemiazygos; 15 — cisterna chyli; 16 — truncus intestinalis; 17 — lymphoglandulae lumbales; 18 — lymphoglandulae iliacae; 19 — lymphoglandulae inguinales; 20 — lymphoglandulae subinguinales. Human lymphatic system. Lymphatic vessels and glands of the lower extremity and abdominal wall. The lymphatic vessels of the lower extremity are divided into superficial and deep.
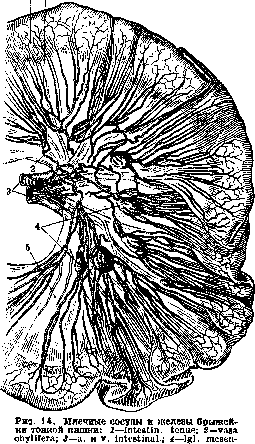
ter.; 5 — mesenterium.
The vessels of the lower extremity are located between the skin and fascia, in the subcutaneous adipose tissue. Passing partly more superficially, partly deeper than the main subcutaneous veins, and in other places forming two layers of vessels separated from each other by a thin fascia, they originate from the abundant lymphatic networks of the skin, subcutaneous adipose tissue, and partly from the periosteum of those areas that are covered only by skin; small and large (main) trunks can be distinguished among them. The main ones serve as collectors for the small ones. The main ones can be traced from the skin and subcutaneous adipose tissue of the toes or foot to the lymph glands of the popliteal fossa or inguinal region. The small ones, starting from the capillary network of the lymphatic vessels of small areas of the skin and fatty tissue of the limb, travel a relatively short distance from their origin until they meet the nearest main superficial trunks into which they empty. The main subcutaneous trunks are divided into two groups — internal and posterior; the internal group, with a large number of trunks, runs in a direction parallel to the main branches and the main trunk of the great saphenous vein, along the inner surface of the leg and thigh.
LYMPHATIC SYSTEM (GLANDS, VESSELS)
The most distant initial regions for this group are the toes and the inner edge of the foot. On the thigh, one can count up to 15 large trunks; on the leg, there are somewhat more. Reaching the inguinal region, this inner group of main subcutaneous vessels empties into the lower group of superficial inguinal glands (lymphoglandulae inguinales superficiales) [see vol. III, pp. 100–101, separate table (I and II) to the article Femoral Triangle], lying at the lower edge of the oval fossa (Fig. 15). The posterior group of main subcutaneous vessels is small in number compared to the internal group. It runs parallel to the main branches of the small saphenous vein. The most distant initial regions for this group of vessels are the outer edge of the skin of the foot and the entire heel. In the upper two-thirds of the posterior surface of the leg, this group of lymphatic vessels consists of only one trunk accompanying the trunk of the small saphenous vein, together with which it penetrates into the depth of the popliteal fossa, piercing the fascia of this region, where it is frequently interrupted by the superficial popliteal gland (lymphoglandulae popliteae superficiales), usually located in the splitting of the fascia or more rarely directly under the fascia. — Variations: 1. One or two subcutaneous main trunks running along the inner surface of the thigh may empty directly into the deep inguinal glands, bypassing the superficial ones. 2. Sometimes the superficial popliteal gland is absent; in this case, the posterior group of subcutaneous vessels empties directly into the outer deep popliteal gland. 3. One of the subcutaneous vessels of the leg can penetrate under the fascia of the leg together with the saphenous nerve and empty in the middle of the thigh into the anterior deep femoral gland. From the foregoing, it is clear that in diseases of the skin of the lower extremity, the glands of the inguinal region located at the lower edge of the oval fossa are most frequently affected, since the superficial popliteal gland receives lymph only from the outer edge of the foot, the entire heel, and the posterior surface of the leg. Deep lymphatic vessels of the lower extremity. Numerous studies have established that the deep lymphatic vessels of the lower extremity originate
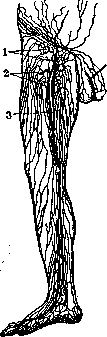
Figure 15. Subcutaneous lymphatic vessels and glands of the right lower extremity, male genitalia, and anterior abdominal wall: 1 — lymphoglandulae inguinales; 2 — lymphoglandulae subinguinales superficiales; 3 — vena saphena magna.
beginning in the capillary network of the bone marrow, periosteum, joints and synovial bursae, ligaments, nerves, fasciae, muscular and bony tissue, and fatty tissue located between deep organs. Among the deep vessels, it is necessary to distinguish the main (large) trunks that travel a long path and secondary (small) trunks that travel a short path. The small vessels, emerging from individual organs together with small blood vessels, either quickly flow directly into the main deep trunks (collectors) located near the main arteries, veins, and nerves of the lower extremity, or carry lymph to the main collectors through secondary collectors accompanying secondary arteries. Usually, secondary collectors consist of two lymphatic trunks lying on either side of the artery, and the number of lymphatic trunks that make up the main collectors can range from 3 to 8 depending on the caliber of the arterial trunk. The thicker the arterial trunk, the greater the number of lymphatic trunks that accompany this artery. The main deep lymphatic trunks are connected to the main subcutaneous trunks by anastomoses, by means of which lymph flows mainly from deep to superficial. In addition, along the path of the main deep trunks, deep lymphatic glands are inserted at certain places, the number of which varies considerably. It is also necessary to note that the course of deep lymphatic vessels is more intimately connected with blood vessels (arteries and veins) than with nerves. Therefore, by all authors (with the exception of Malinovsky), the course of individual main lymphatic trunks (subcutaneous and deep) is described in accordance with the course of the blood vessels, from which they receive their name. Deep lymphatic vessels of the toes. The main deep lymphatic trunks on the toes go along the plantar surface, accompanying the arteries. Deep L. vessels of the foot. In view of the fact that in the posterior part of both the dorsal and plantar surfaces, two layers of muscles and two layers of blood vessels can be distinguished, separated by a thin fascia, the deep L. vessels can also be divided into two layers-superficial and deep. On the sole there are two main collectors accompanying aa. plantaris medialis et lateralis, and on the dorsal side one, accompanying a. dorsalis pedis. Similar to the arteries, these collectors form arches, and in the first interosseous space, these plantar collectors are connected by a large anastomosis with the dorsal one. Both plantar collectors pass to the posterior surface of the leg, where they accompany a. tibialis post., and the dorsal collector passes to the anterior surface of the leg, where it accompanies art. tibialis anterior. On the sole and dorsal side, secondary collectors accompany secondary arterial branches, namely: aa. metatarseae dorsales et volares, aa. tarsea et arcuata, and all muscle branches arising from the main arteries that directly supply the fascia, muscles, joint bursae, ligaments, and bones. Secondary collectors, collecting lymph directly from organs, carry it to the main trunks. They, like the arteries, are connected to each other by large and small anastomoses. Deep L. vessels of the leg. Corresponding to the three main arterial trunks on the leg, there are three main lymphatic collectors, which are interrupted by glands in the popliteal fossa. Despite the fact that all glands of the popliteal fossa are connected to each other by lymphatic vessels representing well-developed direct and collector paths, it is still necessary to indicate which of the individual collectors tends to a particular popliteal gland, due to the ability of lymphatic glands to retain pathogenic bacteria in themselves. The collector accompanying a. tibialis post. is a continuation of the plantar collectors. On its course, one can encounter from 1 to 3 glands, of which the gland located in the upper third of the leg (first described by Hewson) is more common. This collector is the most powerful on the leg and consists of 2-5 trunks, which more often empty into the deep internal popliteal gland, and in the lower half of the leg it gives off anastomoses to subcutaneous trunks accompanying cutaneous arterial branches. The collector accompanying arteria peronaea receives its distant origin from deep organs (muscles and bones) in the heel area, consists of one or two trunks, which empty into either the external deep popliteal gland or both-external and internal. In 2/3 of cases, this collector is interrupted by a gland, lgl. peronaea (in this case, lgl. Hewson's is usually absent). The collector accompanying art. tibialis anterior is a continuation of the dorsal collector of the foot. It consists of 1-2 trunks, which more often empty into the external deep popliteal gland, and on its course is interrupted by 1-3 glands (lgl. tibiales ant.), of which the gland in the upper third of the leg (first described by Mascagni) is more common. Secondary collectors of the leg accompany the following secondary arteries: aa. malleolares, recurrens tibialis and rami musculares. Variations. In the absence of a. tibialis post., lymphatic trunks go exclusively along the course of a. peronaea. With underdevelopment of a. tibialis ant., when a. dorsalis pedis arises from a. peronaea, the dorsal lymphatic collector accompanies a. peronaea. With an arching anastomosis in the lower third of the leg between a. tibialis post. and a. peronaea, there is an arching anastomosis between the lymphatic collectors accompanying these arteries. Deep L. vessels of the popliteal fossa are a continuation of the deep collectors of the leg. They are located on both sides of the popliteal artery. On their course, 3 to 8 deep lymphatic glands are inserted, connected to each other by L. vessels, the number of which reaches more than ten. The vessels form a plexus, which is important for the formation of direct and collateral paths from one gland to another. Into these glands and plexus empty secondary collectors accompanying aa. genu sup. et inf. and a. azygos and carrying lymph from the knee joint and muscles surrounding the joint. Deep L. vessels of the thigh. Efferent lymphatic vessels of the popliteal glands, numbering 2-5 and even 8 trunks, form the main collector of the thigh, accompanying the femoral artery. The trunks of this collector often empty simultaneously into the inguinal and iliac glands (fig. 12 and 13). Secondary collectors are 1) lymphatic trunks accompanying a. profunda femoris and a. genu suprema, and 2) muscle branches arising directly from the femoral artery. Secondary collectors empty either directly into the main one or into glands (lgl. prof. femorales ant.) interrupting the path of the main collector. On the posterior surface of m. adduct. mag., one or two glands (lgl. prof. femorales post.) are encountered, interrupting the path of L. vessels accompanying aa. perforantes, branches of a. profundae femoris. Additional collectors are lymphatic vessels accompanying a. obturatoria and the artery accompanying the sciatic nerve. Both of these collectors, small in size, carry lymph through the pelvis from organs supplied by these arteries; they undoubtedly have capillary intramuscular anastomoses with the main lymphatic femoral collector. The regional gland of the obturator collector is lgl. obturatoria, located at the external opening of the obturator canal, and for the sciatic collector- lgl. glutaea inf., located at the entrance to the pelvis on a. glutaea inf. In the absence of lgl. obturatoriae et glutaeae, additional collectors pour lymph into lgl. hypogastricae et sacrales. Superficial and deep lymphatic glands of the inguinal area (fig. 12 and 13)-see Femoral triangle.-Glands of the popliteal fossa. In the fatty tissue surrounding the artery, vein, and nerves of the popliteal fossa, there are 4-8 glands (lymphoglandulae popliteae), which are divided into superficial and deep. The superficial gland (sometimes two) is not constant, lies under the fascia (or in its splitting) at the level of the perforation of the fascia by vena saphena parva. The deep ones (numbering from 3 to 8) lie near the popliteal vein and artery; sometimes one of them lies on the anterior surface of the latter at the beginning of a. azygos. The superficial one receives lymph from the skin and fatty tissue of the heel and posterior surface of the leg. Its efferent vessels empty into the deep popliteal glands. The deep popliteal glands interrupt the path of deep lymphatic vessels of the leg accompanying aa. tibialis ant. et post. and a. peronaea. In addition, they receive vessels from the knee joint, muscles, and nerves surrounding the joint. The efferent vessels of these glands, numbering from 2 to 8, accompany the femoral artery through the Hunter's canal. Posterior deep glands of the thigh (lgl. femorales prof. post.) are encountered in number 2-3 on the posterior surface of m. adduct. mag. along the course of aa. perforantes I and III (fig. 16). 159
LYMPHATIC SYSTEM (GLANDS, VESSELS)
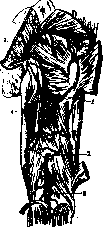
Figure 16. Deep lymphatic vessels and glands of the thigh, posterior view: 1- lgl femor. prof. post. sup.; 2-lgl. femor. prof. post. med.; 3-lgl. popl. prof.; 4- vas lymphaticus n. ischiadici; 5 and 6-lgl. glutaeae inf. et sup.
Superficial and deep lymphatic vessels of the lower half of the trunk, abdominal walls, and pelvis. A. Superficial lymphatic vessels originating in the skin of the lower half of the abdomen, gluteal region, perineum, anus, and external male and female genitalia drain into the superficial inguinal lymph nodes (lgl. inguinales superficiales superiores) (see Femoral triangle) located at the upper edge of the oval fossa, parallel to the edge of Poupart's ligament, whereby the outer subgroup of nodes receives lymph from the skin of the gluteal region, the middle from the skin of the abdomen, and the inner from the skin of the anus, perineum, and genitalia. Sometimes along the path of the superficial lymphatic vessels of the genitalia, one or more lymph nodes (lgl. pubicae) are encountered, located in front of the suspensory ligament of the penis or clitoris; in addition, a rare lymph node (lgl. penis) has also been described, which was located on its lateral surface at a distance of 1.5 cm from the root. - B. Deep vessels of the lower half of the abdominal cavity walls originate in lymphatic networks embedded in the bones, joints, fascia, muscles, deep cellular tissue, and peritoneum. The deep vessels of the anterior section of the abdominal wall run accompanying the inferior epigastric vessels and deep circumflex iliac vessels, and empty into the terminal nodes (lgl. suprafemorales, s. iliacae) located on the external iliac artery. Along the way, the vessels are interrupted by the inferior epigastric nodes (Figure 17) and inconstant circumflex iliac nodes. The deep vessels of the posterior section of the abdominal wall run accompanying the lumbar vessels and iliolumbar vessels. They empty into the lumbar, gluteal, and iliac nodes. The deep lymphatic vessels of the gluteal region run correspondingly to the blood vessels present here, accompanying the gluteal, sacral, and obturator arteries and veins, and draining into the nodes lying along the path of these blood vessels, namely: superior and inferior gluteal nodes, sacral nodes, and obturator nodes. The lymphatic vessels draining these nodes empty into the hypogastric and iliac nodes (Fig. 13). Lymphatic vessels and nodes of the upper extremity and the upper half of the trunk. Superficial lymphatic vessels of the upper extremity are located between the skin and fascia, in the subcutaneous fatty tissue, in most cases more superficially than the subcutaneous veins. Most of the main subcutaneous trunks follow a long path from the nail phalanges to the axillary nodes, while another, smaller part has a relatively short extent compared to the former, because, piercing the fascia in the region of the elbow fold, it empties into the deep vessels of the arm. At the site of the fascial perforation, there is a (1-2) inconstant superficial cubital lymph node (lgl. cubitalis superficialis), in which these vessels are interrupted in most cases. The main trunks serve as collectors for small vessels originating in small areas of the skin and subcutaneous fatty tissue throughout the entire limb. The number of main trunks on the arm varies between 8-10; on the forearm, there are significantly more of them. The direction of the main lymphatic trunks generally corresponds to the direction of the main subcutaneous veins (cephalic and basilic veins), and therefore on the fingers of the hand and forearm they occupy predominantly their dorsal surface. Among them, one can distinguish 1) the inner group of lymphatic vessels originating in the skin of the III, IV, and V fingers and in the skin of the inner parts of the hand and forearm, accompanying the basilic vein and occupying the inner edge of the forearm, and 2) the outer group originating in the skin of the I and II fingers and in the skin of the outer parts of the hand and forearm and accompanying the cephalic vein (Fig. 18). Of the first inner group, only 1-2 trunks, as indicated above, penetrate together with the basilic vein under the fascia of the arm to join the deep lymphatic vessels of the arm, whereas the major part of the lymphatic trunks of this group, continuing its path along the inner surface of the arm to the axillary nodes, deviates significantly from the course of the basilic vein. The lymphatic vessels of the 2nd group (with the exception of one) also deviate from the direction of the cephalic vein, heading inward to the axillary nodes, while the vein
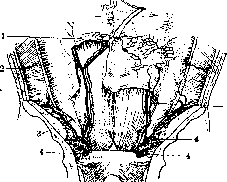
Figure 17. Deep lymphatic vessels of the abdominal wall originating in the umbilical region: 1 - network on the inner surface of the posterior aponeurosis; 2 - trunk accompanying the lumbar artery; 3 - nodes and vessels accompanying the inferior epigastric artery; 4 - nodes at the internal opening of the femoral canal.
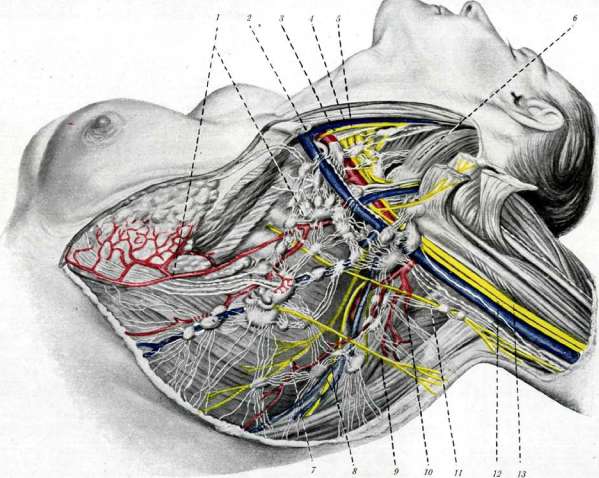
/-v. lateralis; 2 - v. axillaris; 3 - a. axillaris; 4 - v. thoraco-acromialis; 5 - n. thoracodorsalis; 6 - n. phrenicus; 7 - m. trapezius; 8 - n. thoracicus lateralis (Brachial plexus). To the article Lymphatic system. TTCF _ ICi.rini-,1 161
LYMPHATIC SYSTEM (NODES, VESSELS)
162 vessels of the upper extremity most frequently affected are the nodes of the axillary fossa. Superficial cubital nodes can be involved in diseases of the skin of the III, IV, and V fingers and the skin of the inner edge of the hand and forearm. Even more rarely is the deltopectoral node involved, which receives lymph from the skin of the thumb and the skin of the outer edge of the forearm and arm. Deep lymphatic vessels of the upper extremity. Small deep lymphatic vessels of the upper extremity originate in the capillary network of synovial and articular bursae, ligaments, periosteum, fascia, nerves, muscular, and bone tissue. They emerge from the indicated organs together with blood vessels and immediately empty into the main or secondary deep lymphatic trunks. - Deep vessels of the fingers. The main deep lymphatic trunks on the fingers run along the edge of their palmar surface, accompanying the arteries. They originate with small branches from the bones (through the periosteum), articular bursae, ligaments, and tendon sheaths, and accompany the digital arteries only to the base of the fingers, passing then to the dorsum of the hand, where they merge with the superficial ones. Both subcutaneous and deep vessels in the fingers lie in the same layer of fatty tissue. - Deep vessels of the palm. The deep and superficial arterial arches are accompanied by the main lymphatic collectors, consisting of two trunks, often running in a spiral fashion, connected along the way by anastomoses and passing on the forearm into the corresponding collectors accompanying the radial and ulnar artery. Into these arched (superficial and deep) collectors empty secondary collectors accompanying the common digital arteries of the palm and muscular branches and collecting lymph from all deep organs of the palm. In general, the deep lymphatic vessels of the palm, as in other parts of the body, accompanying the blood vessels, correspond to the distribution and course of the latter. Lymphatic nodes along the course of these vessels are not encountered. This entire system is connected by anastomoses at the bases of the fingers with the subcutaneous vessels of the dorsum of the hand. On the dorsal surface of the hand, the deep vessels, originating from the muscles, bones, articular bursae, and synovial tendon sheaths, accompany the arterial branches forming the dorsal carpal rete. Through these branches, the vessels reach the main deep collectors of the back and volar surface of the forearm, but in addition have a wide connection with the subcutaneous
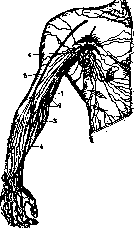
Figure 18. Superficial lymphatic vessels of the upper extremity, anterior and lateral walls of the trunk and chest glands with adjacent nodes of the elbow fold and axillary fossa: 1 - basilic vein; 2 - superficial cubital nodes; 3 - median cubital vein; 4 and 5 - cephalic vein; 6 - axillary nodes.
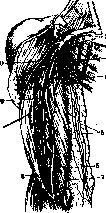
taneous vessels of the back -
Figure 19. Deep lymphatic vessels and glands of the upper extremity from the palmar surface: 1-venous apex; 2-infraclavicular gland; 3-deep axillary gland; 4-superficial axillary gland; 5-subcutaneous vessels; 6-superficial cubital gland; 7-subcutaneous lymphatic vessels; 8-deep and superficial cubital gland; 9-deep brachial gland; 10-deltoid-pectoral gland. - Deep vessels of the forearm. The main collectors consist of 2-4 trunks accompanying the radial, ulnar, and both interosseous arteries. Along the course of all four collectors, deep forearm glands and ulnar glands can be found in children's bodies; in adults, glands are encountered less frequently. The trunks of these collectors are connected by anastomoses and often spiral around the blood vessels. Along their course, they receive lymph from secondary collectors. In the region of the lower third of the forearm, the main deep collectors are connected with subcutaneous anastomoses, which in most cases consist of two vessels accompanying the arterial branches that supply the fascia, subcutaneous fatty layer, and skin. - Deep vessels of the arm. The main brachial collector, accompanying the brachial artery, usually consists of 2 trunks (sometimes 4-6) and is a continuation of the main collectors of the forearm. Along its course, it receives lymph from secondary collectors accompanying the following secondary arteries of the arm: superior and inferior collateral arteries, independent muscular branches of a. brachialis and a. brachialis profunda. In general, the course and distribution of lymphatic vessels correspond to the blood vessels. Along the course of the collectors, deep brachial glands (lgl. brachiales profundae) are encountered (fig. 19). - Variations. One of the lymphatic vessels accompanying the radial or ulnar artery may pierce the fascia and become superficial. The efferent vessels of the superficial ulnar gland in the lower half of the arm may accompany the n. cutaneus antibrachii medialis and then, reaching the upper half of the arm, empty into the main collector accompanying the brachial artery (fig. 19). Lymphatic glands of the upper extremity. Glands of the forearm. In the forearm, non-constant glands are encountered along the course of all four collectors. In adult bodies, glands are encountered less frequently. Due to their existence on both the palmar and dorsal surfaces of the forearm, it would be more correct to divide them
LYMPHATIC SYSTEM (GLANDS, VESSELS)
16* to the deep dorsal and palmar glands of the forearm (lgl. antebrachii profundae volares et dorsales).- The cubital glands are divided into superficial and deep. The superficial, inconstant glands, numbering 1-3, lie on the fascia or more often under the fascia medial to v. basilica and receive lymph from the internal group of subcutaneous vessels of the hand and forearm. The deep cubital glands are divided into upper ones, lying above the cubital groove, and lower ones, lying below this groove. -The brachial glands. The superficial brachial gland (lgl. brachialis superficialis, s. deltoideo-pectoralis) lies in the cleft between m. deltoid and m. pect. maj. near v. cephalica. It receives the subcutaneous vessels of the outer edge of the forearm and arm. The deep glands of the arm are found on the path of the main collector and less frequently at the beginning of a. profundae brachii or on the path of a. collateralis ulnaris sup. (fig. 19). --Glands of the shoulder girdle. 1) Lgl. infraclavicularis lies along the course of a. circumflexae humeri at the anterior edge of capitis longi m. tricipitis humeri. 2) Lgl. interscapulares post.- along the course of a. circumflexae scapulae, at the posterior edge of the same muscle. 3) Lgl. suprascapularis- along the course of a. transversae scapulae near incisura scapulae. 4) Lgl. scapulares post.- along the course of a. transversae scapulae at the medial edge of the scapula. The above-mentioned glands receive mainly lymph from organs that make up the shoulder girdle. The glands of the axillary fossa (fig. 19) vary considerably in number-from 8 to 50; more often they are found in the number of 15-18, of uneven size, lie in the fatty tissue that fills this deep fossa together with the vessels and nerves. One part of them lies superficially in the subcutaneous fat layer, the other part lies deeply along the course of the vessels. The glands lying in the superficial layer of fatty tissue play the role of a center to which the superficial vessels carrying lymph from the skin of the upper limb, shoulder girdle, chest, and mammary gland converge [see separate table (art. 159-160)]. Bartels divides the deep axillary lymphatic glands, located along the course of the vessels and nerves of the axillary and infraclavicular fossa, according to topographic position into 7 groups: 1) lymphoglandulae pectorales, which also include the glands of the following names: gland of Sorgius (on the 3rd tooth of m. serratus), lgl. paramammillares and lgl. cutaneae later., s. paramammillaria (Frob.), numbering 3-6, lying at the lower edge of m. pect. major, or behind this edge. 2) Lgl. subscapulares, s. thoracicae post., numbering 1-5, lying near the nerve, artery and vein of the same name, at the level of the V rib. 3) Lgl. brachiales, s. thoracicae sup., numbering 1-6, lying behind the axillary vessels. 4) Lgl. subpectorales, numbering 2-3, lying under m. pector. minor, medial to vasa axillaria, at the level of II-III ribs. 5) Lgl. intermediae, numbering 2-6, lying near n. thoracicus longus, at the beginning of vasa thoracica longa and being in connection with all other axillary glands. 6) Lgl. infraclavicularis, numbering 1-11, lying between the upper edge of m. pector. min. and the clavicle, on the subclavian vein and medial to it; the efferent vessels of these glands pierce fascia coraco-clavicularis and, anastomosing with the vessels of lgl. supraclaviculares, merge into truncus subclavius. 7) Lgl. deltoideo-pectoralis lies in sulcus deltoideo-pectoralis; its efferent vessels flow into truncus subclavius, and its afferent vessels receive lymph from the upper limb, mammary gland, as well as the skin and muscles of adjacent areas.. The glands of the axillary fossa according to Bartels' nomenclature receive lymph from the following areas: 1) Lgl. brachiales et intermediae-from the upper limb. 2) Lgl. pectorales-from the anterolateral surface of the chest wall and abdomen. 3) Lgl. subscapulares-from the area of the scapula, arm, and posterior surface of the neck. 4) Lgl. deltoideo-pectoralis-subcutaneous of the upper limb and shoulder joint. 5) Lgl. infraclaviculares et supraclaviculares receive lymph from the above-mentioned glands and in addition receive deep vessels of the limbs, sternoclavicular and shoulder joints, as well as muscles and bones that make up the shoulder girdle. The vessels carrying lymph from all the above-mentioned axillary glands form a rich axillary plexus (plexus axillaris), lying along the axillary blood vessels. From the axillary plexus, the outflow of lymph occurs by means of one (rarely two) large trunk (truncus subclavius), which on the left side flows into the thoracic duct, and on the right side joins with the jugular to form the right lymphatic trunk (fig. 13). Variations. Very often on the right side the lymph subclavian trunk does not join with the jugular to form the right lymph duct. In these cases, the latter independently flows into the angle of confluence of the jugular and subclavian veins. Similarly, on the left side the left subclavian trunk can independently flow into the subclavian vein. Then the lymphatic system connects with the veins on the left side with two trunks: the subclavian trunk and the thoracic duct. On the left side there is another variation: all three trunks-jugular, subclavian and thoracic duct-flow independently into the veins. Superficial and deep lymphatic vessels of the chest wall and shoulder girdle - see Mammary gland, Thoracic cage. L. vessels and glands of the head and neck - see Face, Neck. Due to the large number of deep cervical glands, which also have different topographic positions and different significance, it is necessary to divide them into groups according to their position and significance as centers. This subdivision is given according to Bartels. To the deep cervical glands (lgl. cervicales profundae) belong only those that are part of plexus jugulares, and they are divided into upper and lower glands; the latter are divided into internal and external depending on their position relative to the jugular vein. The upper ones lie in trigon. carot. and in the upper part of the triangle formed by mm. omotrapezoides; the lower ones, or supraclavicular lymphatic glands lie in the supraclavicular triangle, large and small (fig. 20). One or two superficial glands lie in front of m. sternohyoidei; the deep numerous glands lie near the pharynx, larynx and respiratory tract. Depending on their position and function Bartels divides the deep glands into groups. The external 2-3 lie along a. carot. int., the internal ones lie on the median line and are found only in children of the first years of life. L. vessels of the oral cavity - see Mouth. L. vessels of the pharynx - see Pharynx. L. vessels of the nasal mucosa - see Nose. L. vessels of the larynx are divided into upper and lower. The upper ones originate from the mucous membrane of the larynx above the vocal cords and merge with the lower vessels of the lower part of the larynx. After piercing the membrane hyo-thyreoidea these common collectors go along a. laryngea sup. to the deep cervical glands. On the membrane hyo-thyreoidea lies lgl. infrahyoidea, through which they pass. The lower ones arise from the mucous membrane of the larynx below the vocal cords. The anterior group of these vessels, piercing lig. crico-thyreoideum, flows into lgl. praelaryngeae, and the posterior, piercing lig. crico-tracheale, flows into the nearby lgl. praetracheales.- Lymphatic vessels of the respiratory tract, originating from the mucous membrane and piercing pars membranacea, flow into lgl. praelaryngeae, praetracheales, paratracheales et supraclavicularis. The lymphatic vessels originating from the networks of the mucous and muscular membrane of the cervical part of the esophagus also flow into these glands. - Lymphatic vessels of the thyroid gland - see Thyroid gland. L. vessels of the brain. As an exception, the L. vessels of the brain do not have regional lymphatic glands. The lymph of the brain flows into the subarachnoid and subpial spaces, which through the Pacchionian granulations communicate with the cranial venous sinuses (fig.21). Similarly, the lymph of the eyeball flows through lig. pectinatum into the canal of Schlemm, which is a vein. The outflow of lymph from the brain directly into the cranial venous sinuses does not exclude the connection of the submeningeal spaces with lymphatic vessels.

Fig. 20. Lymphatic vessels and glands of the head and neck.

21. Pacchionian granulations, serving
ional fluid from the subarachnoid spaces into the longitudinal venous sinus, the mucous membrane of the nasal cavity, and the cerebrospinal nerve ganglia. The medulla is abundantly supplied with blood vessels, and consequently the secretion of lymph in it also occurs in a corresponding abundance, which is confirmed by the abundance of serous fluid permeating its substance and filling the cavities existing inside the brain (ventricles) and on its surface between the membranes: the subpial, subdural, and subarachnoid spaces (the first between the brain surface and the pia mater, the second between the dura and arachnoid, and the third between the arachnoid and pia mater). At present, the view on these cavities as lymphatic ones has firmly established itself, serving for the outflow of cerebrospinal fluid, having not only mechanical significance for protecting the brain from pressure and regulating blood circulation, but also significance in the process of brain nutrition, in metabolism, i.e., the significance of a circulating lymph fluid. The subarachnoid lymphatic space, firstly, communicates with the ventricles of the brain through the foramen Magendii in the posterior medullary velum, and secondly, continues into the substance of the brain in the form of adventitial (perivascular) spaces communicating with the pericellular and perifibrillar lymph clefts of the brain. Lymphatic vessels of the ear - see Ear; Lymphatic vessels and glands of the thoracic cavity - see Thorax, Pleura, and Mediastinum; Lymphatic vessels and glands of the lungs - see Lungs; Lymphatic vessels of the heart - see Heart; Lymphatic vessels of the esophagus - see Esophagus; Lymphatic vessels of the diaphragm - see Diaphragm; Lymphatic vessels and glands of the abdominal cavity and pelvis - see the corresponding organs of these cavities. Lymphatic glands (more correctly, lymph nodes), dense, round or oblong, sometimes flattened organs, the size of which varies significantly in humans and animals. Some of the glands are of microscopic size, others, visible to the naked eye, are the size of a millet seed, and some reach the size of a hazelnut. Under the influence of pathological processes, they can increase to the size of a chicken egg and larger. Lymphatic glands consist of a capsule and adenoid tissue. The capsule of the lymph gland represents a dense connective tissue membrane containing smooth muscle cells and an admixture of elastic fibers. The capsule sends trabeculae into the interior of the gland. Between the capsule and the trabeculae, adenoid tissue is located in such a way that gaps remain between the adenoid tissue and the capsule with its processes, lined both on the side of the capsule and its processes and on the side of the adenoid substance by an endothelial covering. These gaps are called sinuses (Fig. 22) and serve for the flow of lymph entering the lymphatic glands from the lymphatic vessels. Lymph sinuses do not represent
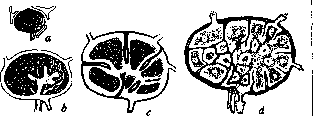
Figure 22. Development of the marginal and central lymph sinus: a-d - stages of division of an unsegmented nodule into individual nodules; cortical nodules and medullary cords are shaded; sinuses and blood vessels are black; in fig. d - on the left, the network of trabeculae; on the right, the network of medullary rays.
free passages for lymph, like vessels, but this entire path is penetrated by a delicate network (reticulum), which on the one hand is attached to the capsule and its processes, and on the other continues into the stroma of the adenoid tissue. This network does not impede the flow of lymph, but only slows it down. The adenoid substance, fulfilling in the indicated manner the cavity of the capsule of the lymph gland, consists of follicles and their continuation - follicular trabeculae. The follicles constitute the peripheral part of the adenoid substance, and the follicular trabeculae - the central part; in other words, the former constitute the cortical, and the latter the medullary or pulp substance. If one examines a section of the gland at low magnification, the follicles appear as round bodies located on the periphery and giving off relatively narrow processes (trabeculae) inside the gland, which, connecting with each other, form a network (Fig. 23). Follicles and the follicular network of trabeculae, together constituting the adenoid substance of the lymph gland, therefore have the same structure and consist of a network or stroma of adenoid tissue and lymphoid cells embedded in the meshes of this network. The network consists of fibers coated with cellular protoplasm. At the intersection points of the fibers, protoplasm forms bounded, angular stellate cells with large pale-staining nuclei - reticular cells or (according to newer research) a reticular syncytium. Adenoid tissue is a focus of reproduction of the cellular elements of lymph - lymphocytes. In the adenoid tissue of the cortical follicles and medullary trabeculae, cells multiply by mitosis. Mitoses are especially abundant in the light central parts of the cortical follicles, called germinal centers. Flemming called these light centers of lymph nodules germinal centers (Germinzentren), since he found karyokinetically dividing cells in them. Flemming's view was subsequently opposed by the view of Hellmann and Heiberg, who explained the formation of light centers in the follicles by the reactive swelling of reticular cells with their frequent subsequent death under the phenomena of karyorrhexis ("reactive centers"). Wätjen found that the light centers are germinal centers in the spirit of Flemming's doctrine, but simultaneously can also be reactive centers in the sense of the view of Hellmann and Heiberg. Newly formed cells, lymphocytes, migrate into the cavity of the sinuses of the lymph gland and thus turn out to be constituent parts of the lymph flowing through these sinuses. Lymphatic vessels carrying lymph from the organs to the center (vasa afferentia) open into the sinuses of the lymph gland. These vessels, numbering 2-4 or more, pierce the capsule in an oblique direction. In this case, the walls of the vessels bringing the lymph enter directly into the composition of the capsule, and the endothelium of the lymph vessels continues into the endothelial lining of the sinuses of the lymph gland. It is understandable that the contents of the vessels during these
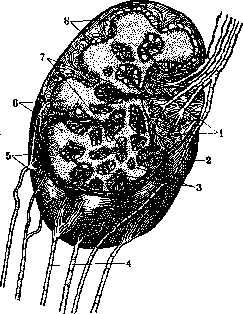
Figure 23. Schematic representation of the internal structure of a lymph gland: 1 - hilus; 2 - anastomosis between efferent and afferent (4) vessels; 3 - trabeculae; 5 - capsule; 6 - follicles; 7 - middle layer; 8 - reticular tissue.
under certain conditions, it flows directly into the sinuses and, passing through them, then enters the efferent vessels of the gland (vasa efferentia), which leave the gland in smaller numbers but with a larger lumen and on the side opposite to where the afferent vessels enter (Fig. 23). Sometimes the afferent and efferent vessels of the lymph gland are connected by a direct anastomosis passing over its surface, and in these cases part of the lymph passes, bypassing the gland. It must be noted that as a rule, vessels forming direct anastomoses exist in significantly smaller numbers than vessels directly connected with the lymph gland. On the surface of the lymph gland there is a small depression or fissure called the hilus of the gland. Through them exit the aforementioned lymph vessels, as well as blood vessels, arteries and veins penetrate. In addition, arteries can penetrate the lymph gland at various points of its surface and besides the hilus of the gland. Upon entering the gland, the arteries branch in the capsule and its trabeculae, but mainly give branches to the follicles and their processes. According to the research of Tonkov and Bushmakin, the supply of the lymph gland with nourishing arteries occurs from large arterial trunks located in the vicinity. Nerve fibers, both myelinated and non-myelinated, enter the lymph gland in small numbers. The lymph glands, consisting mainly of adenoid tissue having the function of reproducing the formed elements of lymph, are, as indicated above, in very close connection with the lymph vessels. The latter, approaching the gland, as it were widen and form the lymph sinuses of the gland. As was indicated above, these lymph sinuses do not represent free passages for lymph, but the entire path is permeated with a thin net which, without impeding the flow of lymph, slows it down. This latter circumstance probably serves as one of the main reasons why pathogenic agents (cancer cells, pus microbes and other bacteria) are retained in the lymph glands when absorbed by the lymph vessels from foci of disease; consequently, in infectious diseases of organs, the lymph glands are as a rule also affected, which as it were filter the lymph of the diseased organ passing through them. Blood L. g. - see Hemolymphatic nodes. The number and size of lymph glands (as well as other elements of the lymph apparatus, the so-called follicles) vary; some glands disappear with the onset of mature age, obviously undergoing for some reasons degeneration and resorption. This is also confirmed by Bartels (Bartels). In addition, in old people, a distinct sclerosis of the lymph glands and vessels is observed: the glands are dense and hard, and the walls of the vessels are thickened and little elastic, which speaks of senile degeneration of the lymph glands and vessels. In contrast to the above observation about atrophy and disappearance during life of lymph glands, there are clinical, patho-anatomical (Gussenbauer) and experimental (Bauer, Ritter) facts speaking in favor of the formation of new glands (e.g., of the elbow, axillary). Such formation sometimes takes place in the adipose tissue, e.g., in chronic irritations coming from the side of inflamed tissues. The existence in some individuals of an increased number of glands compared to the usual (normal) can also be explained by hypertrophy of microscopic, invisible to the naked eye rudimentary glands, which exist along with well-developed glands.
G. Iosifov. Regarding the functions of the lymph glands, little is yet known. The hematopoietic function of the lymph glands is completely unquestionable: lymphocytes of the blood are formed in the lymph nodes and enter the bloodstream with the lymph, which is enriched with lymphocytes when passing through the lymph sinuses. The details of this process are little elucidated. While some researchers attribute the function of multiplication only to the light centers of the lymph nodules (Flemming) and consider their cells lymphoblasts, others believe that the multiplication of lymphocytes occurs in the peripheral zone of the nodules and in the medullary cords, i.e., in the lymphoid tissue. It is very probable that the process of multiplication extends to the entire system of lymphatic tissue down to the small nodules of the mucous membranes and peritoneum. Under pathological conditions, especially in infectious diseases, cells of the myeloid series are also formed in the lymph nodes: eosinophils and myelocytes. Myelopoiesis is concentrated mainly in the medullary layer, leaving the follicles of the cortical layer almost untouched. Another function of the lymph glands is the processing of substances entering them with the flow of lymph and the retention of colloidal-soluble and mechanically suspended particles in the lymph: coal, pigments, metallic compounds, etc. The important role of lymph glands in the process of assimilation of food fats is already evident from the fact that all fat passes through the lymph glands of the mesentery before entering the blood. Reticulo-endothelial cells of the lymph channels and sinuses of the lymph glands have the ability to deposit in their protoplasm a huge amount of suspended particles and to cleanse the flowing lymph of them. It is sufficient to point to the huge mass of coal dust that gets stuck in the bronchial glands (anthracosis of the lymph glands). But also with respect to infectious agents, the role of lymph glands is enormous: numerous microbes coming to the lymph glands from the periphery in inflammations and injuries are stopped in them and do not penetrate beyond their limits, e.g., in bubonic plague, tbc. The failure of this barrier can lead to general infection of the organism with fatal consequences. The lymph glands undoubtedly possess the ability to destroy infectious agents retained by them and are thus an important factor of immunity. It is sufficient to point to the role they play in the pathogenesis of tbc. There are a number of indications that Koch's bacilli, having penetrated through the mucous membranes into the tissues, are retained in the regional lymph glands for a long time. In this way so-called tuberculous lymphadenitis can arise. In the late stages of pulmonary tbc (in the so-called secondary tbc), the bronchial and other lymph glands undoubtedly acquire the ability to destroy Koch's bacilli: although they arrive there from the lungs in large numbers, they do not cause in the lymph glands those specific changes (caseation and periadenitis) which are characteristic of the early stages of the tuberculous process. Such observations formed the basis for Bergel (Bergel) to express the hypothesis of the lipolytic function of lymphocytes, i.e., their ability to produce the enzyme lipase, which breaks down fats as well as the fatty-wax coatings of tubercle bacilli. This hypothesis has not been confirmed by other researchers, but some facts nevertheless force one to think that the lymph glands have some role in the assimilation of food substances, i.e., in their chemical processing. This is indicated besides by the accumulation of lymphocytes in foci of chronic inflammation, around fistulas, in granulomas, etc., by the fact that intensified feeding with proteins is accompanied by an increase in all lymph glands of the body, and the parenteral introduction of foreign protein (Kuchinsky) causes besides the deposition of amyloid in the outer zones of the lymph nodules, i.e., in the location of the reticulo-endothelium. All these facts indicate that the system of lymph nodes is in close connection with the character of general metabolism, especially protein. From this point of view, the differences in the development of the lymph apparatus, first pointed out by Paltauf (Paltauf), in creating his doctrine of the goiter-lymphatic state (status thymico-lymphaticus), or constitution (see Goiter gland, Lymphatism), acquire a certain significance. However, in recent times, the entire doctrine of hyperplasia of lymph glands as a constitutional peculiarity has undergone fundamental criticism, after Groll (Groll) proved that in completely healthy young subjects such hyperplasia is the norm. But if hyperplasia of lymph glands does not express a special form of constitutional state, it undoubtedly plays a large role in childhood, which is extremely prone to swellings of the lymph apparatus. This tendency is particularly often expressed in the age from 4 to 11 years. The causes of such increased sensitivity of the child lymph apparatus, the so-called adenopathy, are of the most varied nature, and often hyperplasia of the thymus gland precedes the swelling of the lymph glands. The immediate occasion for such adenopathies (swellings) are both diseases of general metabolism, mainly rickets, and infectious factors. Inflammatory swellings bear the name of lymphadenitis (see). Systemic diseases of the lymph glands. Leukemia, Lymphogranulomatosis, Lymphosarcoma. The lymph glands are often the site of development of metastases of malignant tumors, mainly carcinomas.
f. chistovich.
Related articles
Cite this page
“Lymphatic System (LYMPHATIC SYSTEM).” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/lymphatic-system-3/