Tenon's Capsule
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Tenon's capsule is a complex system of orbital fasciae that envelops the eyeball and its appendages, serving to fix the eye in position while allowing for movement. This 1930s encyclopedia entry details its anatomical structure, including the anterior and posterior capsules, the 'ligamentous wings,' and the pathology of inflammation known as tenonitis.
Encyclopedia article (1928–1936)
Tenon's capsule (syn. Bonnet's capsule) is a complex system of orbital fasciae that tightly binds together all of its contents and covers the eye with all its appendages. It was first described in 1806 by the French surgeon Tenon, after whom it is named. This system of fasciae can be traced from the very apex of the orbit, where its individual bundles fuse with the periosteum of the latter, as well as with the fibrous sheath of the optic nerve, in the area of the attachment of the eye muscles and the upper eyelid. From here, it extends anteriorly, covering each of the muscles individually with its sheaths in the form of a thin layer of connective tissue and giving off a multitude of lateral branches of the same nature, which divide the entire mass of the surrounding orbital adipose tissue into separate fat lobules (Fig. 1). The bundles of nerves and vessels located here, which nourish the eyeball, are in turn enclosed between the duplications of such thin septa. In the vicinity of the posterior pole of the eye, the muscular sheaths suddenly thicken sharply, turning from cobweb-like films into a dense elastic tissue of a yellowish-white color, with that
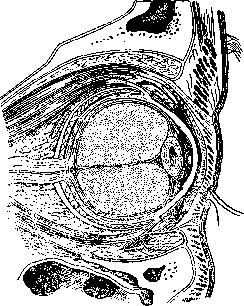
Figure 1. View of Tenon's capsule with its ramifications and Tenon's space on a sagittal section of the eye and its appendages.
part of them which covers the inner (facing the eye) surface of the muscles, without reaching 2–3 mm to the equator of the eye, leaves the muscle and wraps around the eye itself, extending over its entire posterior half in the form of a continuous fibrous capsule (capsula posterior) (Fig. 2). At the same time, the part of the fascia,
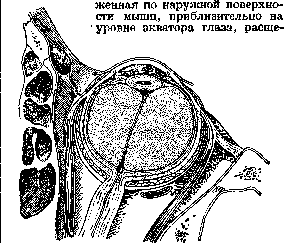
Figure 2. View of Tenon's capsule and Tenon's space on a horizontal section of the eye and its appendages.
splits into two leaves, of which the first continues its initial path along the surface of the muscles and tendons up to their scleral attachments,

Figure 3. 'Ligamentous wings' (a), or lateral processes of Tenon's capsule, connecting the anterior parts of the eye muscles with the edge of the orbit.
and then passes onto the sclera and extends along the latter on one side to the edge of the cornea, and on the other—in the intervals between the muscles, to the equator of the eye, covering its anterior half with a fibrous capsule (capsula anterior). Not far from the scleral attachments of the rectus muscles, this leaf of the fascia for a distance of 10–12 mm seems to detach from their surface.
Thanks to this, a kind of elongated cavity is formed here, filled with serous fluid, or so-called 'pre-tendinous serous sacs,' which facilitate the movements of the muscle tendons. Between the equator of the eye and the line of muscle attachments, the anterior capsule is separated from the sclera by a capillary slit, and anteriorly it gradually fuses with the surface of the sclera, with the adhesions being most dense at the edge of the cornea. In this same area, it is also tightly fused with the subconjunctival tissue. The second of the fascial leaves turns into a dense fibrous tissue, which on one side connects to the capsule of the eye along its equator, and on the other—attaches to the edge of the orbit along its entire circumference, forming a kind of aponeurotic funnel, dividing the orbital cavity into two halves: anterior and posterior. At the same time, those parts of this funnel that correspond to each of the muscles differ from the surrounding tissue by their special density and massiveness. French authors distinguish them as special anatomical formations and give them the special name of 'ligamentous wings or winglets' (ailes ou ailerons ligamenteux) (Fig. 3). Each of the rectus muscles possesses at least one of such 'wings,' and they are especially strongly developed in the external and internal rectus. The superior rectus, connected with the levator palpebrae superioris muscle, has two 'wings' extending from it to the sides (Fig. 4); in addition, it is connected by bundles of fascia with the skin of the upper eyelid and its transitional fold; an analogous connection exists between the inferior rectus muscle and the lower eyelid with its transitional fold. By its purpose, the aponeurotic funnel, as if suspending the eye to the edge of the orbit, fixes it in its position, and the 'ligamentous wings,' tightening during muscle contraction, protect the eye from sharp movements. Both halves of the fibrous sheath (capsula anterior et posterior), merging with each other near the equator of the eye, form a common membrane, or capsule, starting from the edge of the cornea and up to the optic nerve itself, onto which it passes, covering the latter with a special sheath over its own, up to the optic foramen. It is to this membrane that the name Tenon's capsule properly belongs, since the author apparently considered it the central part of the entire aponeurosis of the orbit. Near the place where the optic nerve enters the eye, Tenon's capsule is pierced by a number of ciliary nerves and vessels, which receive their own sheaths from it, thanks to which it is firmly connected to the sclera in this area; at the equator, it is pierced in the same way by four vortex veins. Tenon's capsule is separated from the sclera by a narrow cavity, which in a normal state is a capillary slit filled with lymph and called Tenon's space. The anterior boundary of this cavity passes through the line of attachment of the muscle tendons, i.e., at a distance of 6–8 mm from the edge of the cornea, moving away from the latter up to 11 mm only in the area of the attachment of the superior rectus muscle. Posteriorly, it passes directly into the supravaginal space of the optic nerve and thus enters into connection with the subarachnoid space of the brain. The walls of Tenon's space are lined with a layer of endothelium and have the character of serous membranes; the cavity itself is pierced by a multitude of the finest fibers stretched between its walls, which speaks against the fairly widespread opinion that Tenon's capsule is a kind of articular cavity for the eye, in which it can freely rotate in all directions. In the opinion of some authors, this rotation of the eye can rather occur together with Tenon's capsule in relation to the orbital fat that fills the entire space of the orbit.

Figure 4. Relationships between Tenon's capsule and the superior muscles of the orbit. The pathology of Tenon's capsule boils down to its inflammatory processes or so-called tenonitis, which belong to fairly rare diseases and, depending on the properties of the exudate in Tenon's space, can be of a serous or purulent nature. Distinctive signs of them are moderate protrusion of the eye straight forward (exophthalmos), swelling of the eyelids and conjunctiva (chemosis) with a yellowish tint, and sharp pains of a periorbital type, as well as pain upon pressure on the eye and especially during its movements, which are often limited and accompanied by diplopia. Simple edema of Tenon's capsule and the adjacent connective tissue with subsequent exophthalmos is often observed in severe diseases of the eye itself, especially in panophthalmitis. Purulent tenonitis as a rule develops as a result of the direct introduction of infection into Tenon's space, mainly during wounds, most often as a result of operations for strabismus performed with unclean instruments. All the described symptoms in purulent tenonitis are more pronounced than in serous ones, and the pus accumulated in the cavity usually breaks through to the outside at the site of attachment of one of the rectus muscles. As a complication of purulent tenonitis, optic neuritis is sometimes observed. Serous tenonitis always develops on the basis of a general infection, most often of a rheumatic or grippal nature, and therefore is often bilateral and accompanied by a febrile state. The disease usually begins quite violently, reaches its apogee within 2–3 days, and under the influence of appropriate treatment passes without a trace after a few days; sometimes relapses are also observed. According to the observations of some authors, influenza can also cause primary purulent tenonitis. The therapy of the latter boils down to opening Tenon's space and draining it, and in serous tenonitis to the use of heat, anti-rheumatic, and diaphoretic treatment.
Related articles
Cite this page
“Tenon's Capsule.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/tenons-capsule/