Pneumonia
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia defines pneumonia as an acute infectious disease of the lungs and discusses its classification into lobar (croupous) and catarrhal (bronchopneumonia) types. It details the etiology of lobar pneumonia, emphasizing the role of the Fraenkel-Weichselbaum pneumococcus and the importance of typing pneumococci for prognosis and serum therapy.
Encyclopedia article (1928–1936)
Pneumonia is an acute infectious disease arising independently or as a complication of other diseases, primarily infectious ones as well, and is accompanied by inflammation of the pulmonary parenchyma and bronchi to a greater or lesser extent. However, not every inflammation of the pulmonary-bronchial tissue is an inflammation of the lung, i.e., pneumonia in the clinical-anatomical sense; the concept of pneumonia does not include inflammatory processes that arise, for example, at the site of infarcts or at the site of lung wounds, along the path of a bullet track, etc. In all these cases, we have only a demarcation zone of inflammatory reaction surrounding one or another local process. This distinction is necessary also because the same infarct or wound can, under certain conditions, produce not only or not so much a zonal inflammation as a typical pneumonia, i.e., an effect of general pathological significance that goes far beyond the limits of a regularly developing local reaction.
It is customary to distinguish two main types of pneumonia—croupous and catarrhal (or otherwise bronchopneumonia)—and to make further subdivisions within these types. The subdivision of pneumonia into croupous and catarrhal is, however, not something strictly fundamental that would draw a sharp line between them in all respects; bronchopneumonia can even be a complete equivalent of croupous pneumonia. If such a subdivision is nevertheless maintained, it is done mainly for the purpose of convenience in analyzing phenomena in clinical-anatomical and pathogenetic respects. The classic, most striking form is considered to be croupous pneumonia; it is also the one that usually appears under the name "pneumonia" among the main acute infectious diseases.
I. Croupous pneumonia. Etiology. The vast majority of cases of lobar croupous pneumonia in humans are caused by the Fraenkel-Weichselbaum pneumococcus [see separate table (p. 623-624), fig. 6] (see Pneumococcus). In favor of the etiological significance of the pneumococcus, besides its constant isolation from the affected lung tissue, speak also the experimental observations of a number of authors, in particular Blake and Cecil, who succeeded in inducing a typical clinical and anatomical picture of croupous pneumonia in monkeys by intratracheal administration of minute doses of pneumococcal culture. The pneumococcus, however, is not the only causative agent of croupous pneumonia. Besides Friedländer's bacillus, the etiological role of which in certain forms of this disease has long been generally recognized, other microorganisms, such as streptococcus, staphylococcus, and Pfeiffer's bacillus, can undoubtedly also cause lobar croupous inflammation of the lungs.
Thus, in the material of the clinic of the Rockefeller Institute in New York, the causative agents of croupous pneumonia were distributed as follows: Pneumococcus 454 cases, Bac. Friedländer 3, Bac. influenzae 6, Streptococcus pyogenes 7, Streptococcus mucosus 1, Staphylococcus aureus 3, mixed infections 6. Systematic bacteriological examination of sputum and blood in patients with croupous pneumonia at the Medsantrud Hospital in Moscow during 1929–31 yielded the following results regarding the frequency of isolation of individual microorganisms: Pneumococcus 361 cases, Bac. Friedländer 4, Bac. Friedländer + Pneumococcus 6, Streptococcus haemolyticus 7, Streptococcus viridans 3, Staphylococcus haemolyticus 2. Cases of croupous pneumonia caused by the listed microorganisms present, depending on the pathogen, certain anatomical as well as clinical features. These features have been studied in most detail in relation to Friedländer's pneumonia.
As observations by Neufeld, expanded and deepened by Dochez, Gillespie, Avery, Cole, and other staff of the Rockefeller Institute in New York, have shown, there exists a number of varieties of pneumococcus that differ from one another in their immuno-biological properties. According to these authors, three varieties of pneumococcus (the so-called types I, II, and III—see Pneumococcus) are most frequently encountered (in 70–80% of all pneumococcus cultures) in croupous pneumonia. As for the remaining varieties of pneumococcus, of which, based on observations by Park and Cooper, there are over 20, they are encountered so rarely that isolating them into separate types with the preparation of corresponding sera for their identification is complex and inexpedient. At the suggestion of the staff of the Rockefeller Institute, all strains of pneumococcus that do not give specific immunity reactions with the sera of the indicated three types are classified as type IV. The latter, therefore, does not represent a variety with definite biological properties, but is a collective group uniting those numerous varieties of pneumococcus that are not part of the indicated three fixed types.
The differentiation of the pneumococcus into specific biological groups, besides theoretical interest, also has practical, clinical, and epidemiological significance. Almost all authors who have studied croupous pneumonia from the point of view of pneumococcus typing note the dependence between mortality and the type of pneumococcus with which a given patient is infected (see below, prognosis). Determination of the type, therefore, to a certain extent predetermines the prognosis of the disease. For the successful application of serum therapy, preliminary determination of the pneumococcus type is also necessary, since specific serum in relation to type I is predominantly used. The establishment of the type of pneumococci is also of great importance when resolving epidemiological problems. Recent observations have shown that the type of pneumococcus to a certain extent also leaves its mark on the clinical picture of croupous pneumonia (temperature curve, character of the termination of the infection, etc.) (Ettinger, Viktorov, Mazel). Until recently, the study of croupous pneumonia from the point of view of pneumococcus type was conducted mainly by American and English authors. Although the frequency of isolation of individual types of pneumococcus in patients with croupous pneumonia varies among different authors depending on the season and the geographical location of the given area, nevertheless, in the majority of observation series, approximately one-third of all cases fall to types I and II, 10–15% to type III, and the remaining 25–30% to type IV. The dependence of pneumococcus typing on the geographical location of the given area is clearly illustrated by the observations of Lister, according to whose research the ratio of individual varieties of pneumococcus in South Africa differs sharply from that in North America. Thus, about 1/3 of the strains isolated by him in patients with croupous pneumonia fall to a variety of pneumococcus that is part of type IV, which is rarely observed in our latitudes. In Moscow, at the Medsantrud Hospital, systematic determination of the pneumococcus type in patients with croupous pneumonia for the period since 1929 yielded the following results: type I 16.5%, type II 34%, type III 9.5%, type IV 40%.
Characteristic for the Moscow pneumococcus, at least in the indicated period, in comparison with the data of American authors, is thus a sharp predominance of type I over type II. The frequency of cases of types III and IV in Moscow and America approximately coincides (Etinger, Viktorov, Mazel). The pneumococcus, and in rare cases other listed microorganisms, are thus the primary factor which, on the one hand, causes the infection, and on the other, determines the specificity and cyclicity of its course. The circumstance, however, that the pneumococcus is extremely widespread as a saprophyte inhabiting the mucous membrane of the oral cavity and upper respiratory tract indicates that the entry of this microbe into the human body does not at all mean the onset of pneumonia. Consequently, some other predisposing factors are required. Among the latter, meteorological factors apparently play a prevailing role. Working and living conditions and the constitutional properties of the organism, understood in the broad sense of this word and associated with age, sex, previous diseases, intoxications, etc., are also of great importance. Seasons of the year and meteorological factors. Statistical data from a number of authors show that cases of croupous pneumonia are not distributed evenly throughout the year. In temperate geographical zones, the greatest number of cases of croupous pneumonia is observed in the winter and early spring months (December-April). During this period of maximum incidence, in turn, rather sharp rises and falls in the disease curve are observed. In the summer and early autumn months, the incidence of croupous pneumonia usually reaches minimum figures. From which meteorological factors the sharp fluctuations in the incidence of croupous pneumonia depend in connection with the seasons and weather has not yet been established. In addition to fluctuations in temperature, barometric pressure, and humidity, so-called movements of air masses (cyclones, anticyclones) apparently also have significance. Old authors, who asserted that frigus pneumoniae unica causa (cold is the sole cause of pneumonia), undoubtedly exaggerated the importance of cooling in the process of the onset of croupous pneumonia. However, there are no grounds to completely reject cooling as a factor predisposing to the disease of croupous pneumonia, as some authors do: even a single sharp cooling, as numerous observations show, can be a factor triggering croupous pneumonia, provided, of course, that the corresponding pathogens are present in the body. Prolonged stay and work in the open air are undoubtedly also a predisposing factor. Among patients with croupous pneumonia admitted to hospitals, a large percentage consists of representatives of professions working in unprotected premises or in the open air and constantly exposed as a result to temperature and other atmospheric influences. Heavy physical labor and severe overwork apparently also predispose to the disease of croupous pneumonia. German and French statistics show that croupous pneumonia is observed more often among soldiers than among the civilian population. This applies especially to recruits who are not yet sufficiently trained and not accustomed to the conditions of military life. According to the data of American authors, croupous pneumonia is observed less frequently among the rural population than among the urban population. In cities, croupous pneumonia is observed more often in areas with crowded populations and poor sanitary-hygienic conditions. Among the adult population, the greatest number of diseases falls on the age from 20 to 40 years and older than 60 years. These extensive indicators, however, have very limited significance, as they do not take into account the number of persons in the corresponding age groups. According to hospital statistics from different countries, men among patients with croupous pneumonia sharply (by 3-4 times) predominate over women. This is partly explained by the greater tendency of men with croupous pneumonia to seek hospital care. Statistics covering non-hospital material, although they also show a predominance of the male sex, do so to a less sharp degree. The lower incidence of croupous pneumonia in women is apparently caused not by special properties of their organism, but by those exogenous influences to which representatives of both sexes are exposed to an unequal degree (work in the open air, alcoholism, etc.). In childhood, both sexes suffer from croupous pneumonia with equal frequency. Croupous pneumonia belongs to those diseases which do not leave any lasting immunity. In the anamnesis of these patients, on the contrary, there are often indications of having suffered from croupous pneumonia in the past. The literature describes cases of a person contracting croupous pneumonia ten and even twenty-eight times. These observations point to the significance of individual predisposition. When analyzing these cases, however, one should take into account the possibility of the influence of identical external factors during individual illnesses. A frequent predisposing factor is further general exhaustion on the basis of previous severe chronic diseases. Pneumonia is often observed in severe cardiac and renal patients, severe diabetics, in malignant neoplasms, and other cachectic states. In these diseases, pneumonia of the croupous or catarrhal type is often a terminal process. Of the acute infections of adulthood, influenza, typhoid fever, and typhus are often complicated by croupous or catarrhal pneumonia. Of chronic intoxications, alcoholism plays a large role as a factor predisposing to the disease of croupous pneumonia. The latter in alcoholics usually proceeds particularly severely. Of acute intoxications, anesthesia, especially ether anesthesia, is of significance. The significance of chest trauma as a predisposing factor in the onset of croupous pneumonia, which was overestimated by old authors, began to be almost completely ignored after the discovery of the Fraenkel pneumococcus. Meanwhile, observations by a number of authors have established with certainty that some time after severe contusions of the chest, even in the absence of external injuries, croupous pneumonia can develop in a small, it is true, percentage of cases; the incubation period, according to different authors, ranges from 10 hours to 18 days. According to the observations of Proust, out of 100 cases of severe chest contusions, there are about 4 cases of subsequent so-called traumatic pneumonia. The latter is apparently caused by a decrease in the resistance of the traumatized lung tissue. It is quite possible, however, that traumas first cause a breach in the integrity of the lung and hemorrhage into it. Epidemiology. Until recently, croupous pneumonia was viewed as an autogenous infection. The circumstance that the pneumococcus very often vegetates in the oral cavity and pharynx of healthy people caused a certain indifferent, fatalistic attitude toward the possibility of fighting this infectious disease along the lines of the microorganism. The main attention was paid to the predisposition of the macroorganism and the influence on it of various exogenous factors, such as cooling and other meteorological factors, traumas, etc. The view of the autogenous nature of pneumococcal infection, however, was in contradiction with the repeatedly observed mass outbreaks of croupous pneumonia in barracks, camps, prisons, dormitories, on ships, etc. Such outbreaks of croupous pneumonia of particularly large proportions were observed among workers during the digging of the Panama Canal, as well as among black miners in South Africa. Proponents of the autogenous nature of pneumococcal infection always emphasized the circumstance that the transmission of the disease from a patient to those around them is never observed, even under the most unfavorable sanitary-hygienic conditions. American authors, staff members of the Rockefeller Institute in New York, approached this problem from a new point of view. Having confirmed the long-known fact that the pneumococcus as a saprophyte vegetates on the mucous membrane of the oral cavity and pharynx in approximately half of the entire population, they showed, however, that the ratio of individual types of pneumococcus in healthy people differs sharply from that in patients with croupous pneumonia. As we have already seen, in patients with croupous pneumonia, types I and II account for about 2/3 of all isolated strains, whereas in healthy persons who have not been in contact with patients with croupous pneumonia, types I and II of the pneumococcus are encountered extremely rarely—less than 1%. Almost all strains isolated from them belong to type IV or III. A significantly higher percentage of type I and II pneumococci, although far from reaching the corresponding figures in patients with croupous pneumonia, is encountered in healthy persons who are in contact with patients with croupous pneumonia (about 12% of pneumococcus carriers of the corresponding types according to the data of the indicated authors). As a rule, among persons in contact with type I pneumonic patients, exclusively type I pneumococcus carriers are observed. The same applies to type II. In convalescents after croupous pneumonia of the first two types, the corresponding pneumococci can usually be detected in the oral cavity and pharynx during the first 3-4 weeks after the end of the infection. After this period, they disappear or are replaced by type IV pneumococcus.
The disappearance of pneumococci of the first two types some time after the crisis indicates that they are not permanent inhabitants of the oral cavity in these individuals. The circumstance that pneumococci of the first two types are extremely rarely encountered in healthy individuals who have not been in contact with patients with lobar pneumonia, but are almost exclusively isolated from patients with this infection during the period of the disease, as well as during recovery, or from individuals who have been in contact with the corresponding patients, indicates that these types of pneumococcus occupy a special place among the varieties of this microorganism. The listed epidemiological facts suggest that pneumococci of the first two types are closely related to pneumonic infection and, in contrast to other varieties of pneumococcus (types III and IV), cannot be classified as saprophytes. Based on the stated epidemiological observations, a number of American and European microbiologists and clinicians have come to the conclusion that lobar pneumonia, caused by pneumococci of type I and II, is not an autogenous but a contagious infection. As for cases of lobar pneumonia caused by pneumococci of type III and IV, which are extremely common as saprophytes, these authors allow for the old view regarding the autogenous nature of the infection in relation to these varieties of the microorganism. The fact, disputed by no one, that direct transmission of lobar pneumonia from a patient to those around them is observed extremely rarely, by no means argues against the contagious nature of the infection in the broader sense of the word. At the present time, no one denies the contagiousness of cerebrospinal meningitis, yet the danger of direct infection in this disease is extremely small. The complete similarity of phenomena observed in the study of the epidemiology of cerebrospinal meningitis (see Meningitis) and lobar pneumonia of type I and II argues for an analogy in the routes of spread of these infections. For final proof of the contagious nature of lobar pneumonia of type I and II, however, further epidemiological observations are required.
Ya. Ettinger. Statistics and geographical distribution of Pneumonia. 1. Mortality. Among the main causes of death, pneumonia, along with tuberculosis, cancer, and organic heart diseases, occupies one of the first places. In most countries of Europe and the USA, mortality from pneumonia ranges from 50 to 100 persons per 100,000 population per year (Table 1). Table 1. Mortality from Pneumonia (all forms) for the period from 1925 to 1929 (per 100,000 population). States 1925 1926 1927 1928 1929 Austria 114.0 120.0 129.0 122.0 England 95.1 62.8 94.8 78.6 Belgium 89.1 99.4 105.5 95.9 Hungary 160.0 160.0 195.0 184.0 Germany 93.0 88.0 96.0 93.0 Holland 80.0 91.0 87.0 Denmark 121.0 130.0 139.0 131.0 Norway 43.4* 73.0 82.0 France 43.3 47.5 32.2 Switzerland 76.0 74.0 77.0 Sweden 62.0 70.0 82.0 93.5 103.0 Czechoslovakia 170.2 176.8 163.5 * Mortality from lobar pneumonia. Over the five-year period 1925-29, mortality was highest in Hungary, Denmark, and Czechoslovakia, and lowest in France. When comparing mortality rates across individual countries, one must, however, keep in mind the diversity of systems for registering causes of death and the varying degree of medical staffing in individual states, as well as the insufficient delimitation of the disease forms covered by the term pneumonia from other respiratory diseases. Furthermore, one must take into account that pneumonia is a frequent complication of many other diseases that directly lead to death. In the statistical practice of individual countries, the classification of causes of death in cases of multiple causes is carried out far from uniformly, with significant deviations from the rules developed by the international conference. Fluctuations in the pneumonia mortality rate by individual years are to a significant degree connected with the level of mortality from influenza. Each rise in the curve
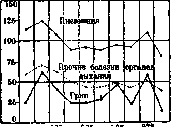
Figure 1. Mortality from pneumonia, other respiratory diseases, and influenza (per 100,000 population). The curve of mortality from influenza is immediately reflected in the curve of mortality from pneumonia and, to a lesser extent, in the curve of mortality from other respiratory diseases (Fig. 1 shows mortality from pneumonia, other respiratory diseases, and influenza in Germany from 1921 to 1929; see also Influenza—the curve of mortality from pneumonia and influenza in England for 1853-1926). An idea of mortality from pneumonia in the USSR can be provided by the following data, Figure 2.
relating to Leningrad (Table 2 and Fig. 2); for comparison, the mortality rate from influenza is also provided. Table 2. Mortality from Pneumonia (all forms) and influenza in Leningrad for 1917-1928 (per 100,000 population). Years Pneumonia Influenza Years Pneumonia Influenza 1917 284.6 12.6 1924 188.4 15.9 1918 544.0 94.2 1925 145.5 11.4 1919 1084.1 257.9 1926 158.2 41.4 1920 453.4 91.6 1927 172.0 42.0 1921 307.8 35.2 1928 167.5 32.5 1922 302.8 26.5 1929 158.9 30.7 1923 176.0 25.3 1930 175.2 25.3 Over the last 8 years, mortality from pneumonia in Leningrad has fluctuated from 145.5 to 188.4 per 100,000 population, against 301.8 in 1911-13. This significant reduction in mortality depends mainly on the sharp decrease in mortality from pneumonia in infancy (Table 9). For Moscow, where mortality from lobar pneumonia is registered, the following data are available (Table 3 and Figure 3). Lobar pneumonia in Moscow in recent years yields a mortality rate 2-3 times lower than in pre-revolutionary years. During the years of the influenza pandemic (1918-19), the highest mortality from lobar pneumonia was observed in Moscow. Table 3. Mortality from lobar pneumonia and influenza in the city of Moscow for 1903-1930 (per 100,000 population).
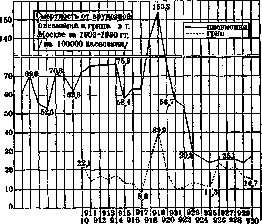
Figure 3. ...exceeding the mortality of previous years by 2.5 times. 2. Mortality from pneumonia in cities and rural areas is not the same. Data for Leningrad and the Leningrad Governorate (Table 4) indicate that mortality from pneumonia in rural areas is higher than in cities; at the same time, the mortality rate from pneumonia in small towns is lower than in Leningrad. Table 4. Mortality from pneumonia (all forms) in cities and other localities of the Leningrad Governorate (per 100,000 population). In Germany, the mortality rate from pneumonia in settlements with 15,000 or more inhabitants is lower than the corresponding rate for the whole country (Table 5). 3. Mortality by sex and age. Table 6 and Fig. 4 present mortality from all forms of pneumonia by age and sex in Germany in 1930; Table 7 and Fig. 5 provide the same data for Leningrad for 1923. From these tables, it is evident that the mortality of men in all age groups exceeds that of women; the only exception is the age group of 60 years and older, which in Leningrad in 1923 showed the opposite ratio. From the same tables, one can see the extremely sharp differences observed in relation to the values of mortality from pneumonia for individual ages.
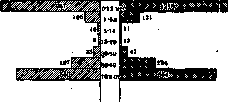
Figure 4. Mortality from pneumonia by age and sex in Germany in 1930.
ages. These differences significantly exceed those that exist in relation to age-specific coefficients of general mortality. The extremely high mortality from pneumonia in the first year of life drops sharply at the age of 1 to 4 years, with

Figure 5. Mortality from pneumonia by age and sex in Leningrad in 1923.
to reach its minimum at the age of 10 to 14 years; after the age with minimum mortality, mortality begins to rise, at first slowly, and then at a faster pace, again yielding high coefficients in old and especially senile age. Table 8 shows that the bulk of deaths from pneumonia falls on the age under 5 years and on the age of 50 years and older. Among the causes of death at the age under one year, pneumonia occupies one of the first places. Table 7. Mortality from Pneumonia (all forms) by age and sex in Leningrad in 1923 (per 100,000 of the population of the corresponding group). Age Men Women Both sexes 0-12 m....... 3,550.6 3,124.1 3,343.8 1-4 y....... 858.3 763.1 745.2 5-9 y....... 42.3 40.6 41.4 10-14 y....... 23.8 19.9 21.8 15-19 y....... 40.4 32.3 36.8 20-29 y....... 47.0 22.3 34.0 30-39 y....... 43.9 40.8 42.4 40-49 y....... 101.0 43.6 71.6 50-59 y....... 190.4 150.6 167.7 60 y. and older... 483.7 540.0 524.3. Table 8. Mortality from Pneumonia (all forms) by age in Leningrad in 1921-1923 (per 1,000 deaths in all ages). Age 0-12 m. ... 1-4 y. ... 5-9 y. ... 10-14 y. ... 15-19 y. ... 20-29 y. ... 30-39 y. ... 40-49 y. ... 50-59 y. ... 60 y. and older 1921 1922 1923.
Age-specific mortality from lobar pneumonia is illustrated by Table 9. In general, age-specific mortality from lobar pneumonia bears the same character as mortality from all forms of pneumonia, with the difference that here maximum mortality is given by senile age, and not by infancy (Fig. 6). Table 9. Mortality from lobar Pneumonia by age in Moscow in 1931 (per 100,000 of the population of the corresponding group). Age Mortality 0-4 y. ... 33.0 5-9 y. ... 12.3 10-14 y. ... 4.4 15-19 y. ... 9.1 20-29 y. ... 8.1 30-39 y. ... 16.8 Age 40-49 y. ... 59.0 50-59 y. ... 111.1 60 y. and older ... 321.4 All ages ... 42.1.
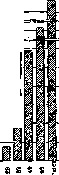
4. Morbidity. Registration of morbidity from Pneumonia began to be conducted relatively recently and in a very small number of countries. In 1928, Pneumonia was registered by England, Scotland, Ireland (Northern), Ireland (Free State), Denmark, Iceland, Norway, the USA (28 states), Canada, New Zealand, and some other states. Usually, summary data on all cases of Pneumonia are published without separation into individual forms. For Moscow and Moscow Governorate, the morbidity of lobar Pneumonia is distinguished. In 1925, in the city of Moscow, 13.6 cases of lobar pneumonia per 10,000 population were registered, in 1926—15.2; in the Moscow Governorate in 1906-1908, 31.0 cases were registered, in 1925—34.0, in 1926—25.6. Table 10 gives an idea of the morbidity of lobar Pneumonia by age and sex.
Table 10. Morbidity of lobar Pneumonia by age and sex in the city of Moscow and Moscow Governorate (per 10,000 people of the corresponding group) in 1926. Moscow Moscow Governorate Age M. W. M. W. 0-12 m. ... 48 46 19 11 1-4 y. ... 16 9 10 17 5-9 y. ... 15 20 101 67 10-14 y. ... 30 20 21 18 15-19 y. ... 19 25 27 23 20-29 y. ... 11 11 30-39 y. ... 40-49 y. ... 50-59 y. ... 60 y. and older ... Fig. 6. Mortality from lobar pneumonia by age in Moscow in 1931 (per 100,000 population of the corresponding group). Lobar Pneumonia affects childhood (up to 10 years) most strongly, both in the city of Moscow and in the Moscow Governorate, especially infancy (up to 1 year); some increase is noted in old and senile age. Men in all ages (with the exception of the age up to 1 year in the city of Moscow) fall ill with lobar Pneumonia more often than women. Morbidity among the population of the governorate is higher than in Moscow.
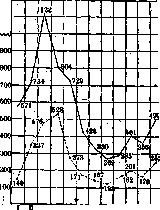
5. Seasonality. The maximum mortality from Pneumonia in most countries falls on the first quarter, as can be seen from Table 11, where the numbers of those who died from pneumonia in some countries and cities for the last three years are summarized by quarters; the minimum falls on the third quarter. The high mortality from pneumonia observed in the first quarter of 1929 in the countries of Europe and the USA finds its explanation in that significant influenza epidemic which these countries experienced at the beginning of 1929. In Fig. 7, the monthly distribution of cases of lobar pneumonia in Moscow and the Moscow Governorate for 1926 is presented. The maximum of cases in the city of Moscow fell on April, and in the Moscow Governorate it falls on March; the minimum of cases of lobar pneumonia in both Moscow and the Moscow Governorate falls on August.
Figure 7. Monthly distribution of cases of lobar pneumonia in 1926.
I. Blokh. Pathological anatomy. From a pathological-anatomical perspective, croupous pneumonia is an acute fibrinous inflammation of the bronchopulmonary tissue with the exudation of abundant masses of fibrin into the air passages (hence the sometimes used synonym - pn. fibrinosa). It is customary to distinguish 4 stages of the pulmonary process: the first - the stage of engorgement - is characterized by sharp hyperemia of the vessels. This hyperemia over significant stretches passes into blood stasis, whereby the very patency of the capillaries of the corresponding sections of the lung sharply decreases, and in places apparently disappears completely. Even at this time, the affected parts of the organ become somewhat dense, darker. The second stage - red hepatization - is characterized by rapidly increasing diapedesis of erythrocytes and the exudation of plasma proteins, especially fibrinogen, into the air-bearing parts of the lung parenchyma. The lung "hepatizes" and clearly increases in volume. Its weight increases significantly - by 2-3 times or more. On section, the lung is red, finely granular, somewhat dry. The granularity is sometimes very fine, sometimes coarse, depending on the size of the alveoli; in croupous pneumonia in an emphysematous patient, the granularity is often particularly coarse. The grains themselves are compact fibrinous-bloody masses of exudate, which like casts fill the alveoli, and often the bronchi. The third stage - gray hepatization - is a direct continuation of the previous one, and the transition itself is either rapid or somewhat drawn out and uneven; that is why they sometimes speak of gray-red hepatization. The essence of the changes in the third period consists in the subsiding of the processes of erythrocyte diapedesis and in the strengthening of desquamative and proliferative phenomena on the part of the alveolar epithelium, and mainly in the emigration of leukocytes, the mass of which, having a gray-greenish color, imparts the corresponding shade to the lung section. The granularity is clear, the hepatization of the lung is sharp, the weight increases. The hepatized lung, especially the gray one, tears easily even with slight force, e.g., during careless puncture with a needle. The fourth stage - the stage of resolution - is characterized by the onset of proteolytic and autolytic processes in the exudate; liquefaction and dissolution of fibrin occur, as well as fatty degeneration, disintegration of leukocytes and desquamated alveolar epithelium. This fatty degeneration can impart a somewhat yellowish shade to the entire section of the affected lung, and then they speak of "gray-yellow hepatization." The granularity weakens or disappears, the phenomenon of hepatization gradually weakens. The lung in consistency and color more resembles a spleen ("splenization"). Finally, complete resorption of the exudate occurs, the organ assumes a soft and even flabby consistency with significantly less elasticity than in the normal state. At the end of the fourth period, the leukocytes finally disintegrate, and they are replaced by cells of the lymphoid type with broad protoplasm, in which it is not difficult to recognize the regenerating alveolar epithelium. This regeneration, however, proceeds unevenly, and along with the restored alveolar structures, it is still possible for quite a long time to discover clusters of free cells in the alveoli here and there. In general, the period of resolution should be viewed as the most drawn out in time; in any case, it extends into the first 5-7 days of the patient's afebrile state.

In the vast majority of cases, the entire exudate is resorbed without a trace; only a comparatively insignificant part of it is expectorated; the lung anatomically returns to normal; true, in a functional respect, it is for some time still devoid of its usual perfect elasticity. Histological, and often already macroscopic, examination reveals in some cases peculiarities in the morphology of the exudative processes or in the succession of individual phenomena. Thus, the diapedesis of erythrocytes in its severity sometimes resembles acute parenchymatous hemorrhage, as if a solid infarct of the lung. In other cases, a weak or extremely uneven fibrinous effusion, negligible granularity of the section, and even its absence are noted. In these cases of so-called smooth pneumonias, the exudate filling the alveoli is mainly serous fluid, alveolar epithelium, leukocytes, and sometimes exclusively the latter, whereby the lung appears as if soaked with liquid pus. Purulent exudate is also removed in large quantities from the section of the organ. It would be incorrect, however, to treat such cases as purulent pneumonias or as an outcome in suppuration, since the melting of lung tissue and the formation of abscesses in this case are by no means mandatory. French authors therefore distinguish two types of "gray hepatization" (see separate table, figure 4): "non suppuree," or ordinary gray hepatization, and "suppuree" - purulent transformation of the intra-alveolar exudate. In these same cases of "purulent" pneumonias, the stage of red hepatization often drops out completely - the general development of the exudate thus proceeds as if along the line of banal catarrhal pneumonias. To all that has been said, it is necessary to add that the development of the pneumonic process in each specific case and even in one and the same lobe of the lung can have its details and peculiarities, and not only in the sense that the very unfolding of changes by stages proceeds in different places at somewhat different times - this is a common phenomenon, but in the sense that in some places the processes generally unfold rapidly and typically, in others - slowly and not quite typically (little or no fibrin, sharp diapedesis of erythrocytes, purulence, massive thrombosis of vessels, etc.). In other words, both the very beginning of the process and its evolution, even in one and the same lobe of the lung, can be different in different places; one cannot help but see in this the premise for one or another focal complications observed not infrequently in croupous pneumonia. As indicated, the exudate usually fills parts of the bronchial tree as well, and cases are not rare when this filling reaches the middle and large bronchi, and it is possible to pull out entire casts of the bronchial path from the lumen of the latter (examine in water). Pneumonia with diffuse effusion into the bronchial tree is also designated as massive pneumonia. On the part of the interstitial tissue of the affected area, phenomena of serous-fibrinous infiltration are also noted, and in the lymphatic vessels, sometimes pictures of lymphangitis and thrombosis. In the greater part of cases, an entire lobe of the lung is subjected to hepatization - hence the synonym "lobar pneumonia." It is not so rare for two and three lobes to be affected, and bilateral pneumonias with hepatization of the main mass of both lungs are also noted. The right lower lobe and lower lobes in general are most frequently affected. Pneumonias of the upper lobes are not so rare; the comparative frequency at autopsies of precisely such upper and even "apical" pneumonias speaks, apparently, of their particular severity (compression of the vagus nerve? phrenic nerve?). Croupous pneumonia is not always lobar in the full sense of the word: individual parts of the lobe often remain non-hepatized, for example, only edematous, but airy or even emphysematous. This lobar principle is especially often violated in childhood and old age. In children, especially small ones (up to 5 years), in the majority of cases there are not even typical lobar pneumonias; this is also often the case in emaciated subjects and marantics. Sometimes the exudate, at different times and with significant intervals, captures individual pieces or entire lobes of the lung - so-called migrating pneumonias (e.g., the upper right lobe has gray hepatization, while the lower left is undergoing only red hepatization, etc.).
Figure 1. Catarrhal pneumonia; a—airless (filled with exudate) parts; b—emphysematously distended area; in the middle and on the right—parts with little air; c—pleura; d—vessel; e—bronchus; f—bronchus blocked by exudate. Figure 2. Interstitial pneumonia (interstitial sclerosis of the lung): a—flattened alveoli with sharply thickened walls. Figure 3. Carnification of the lung in pneumonia as a result of the organization of intra-alveolar exudate (a); b—elastic fibers contouring the alveoli. Figure 4. Croupous pneumonia (gray hepatization) of the lower lobe (a) of the right lung; b—partial airlessness; c—middle lobe; d—upper lobe. Figure 5. Desquamative pneumonia; in the alveoli—an abundant amount of 'thickened epithelium'. Figure 6. Pneumococci. Central pneumonias, i.e., those located deep in the pulmonary parenchyma without the focus reaching under the pleura, are more often noted in children, but in general, they are a rather rare phenomenon; most often we are dealing here with a transitional state, e.g., in the course of the development of ordinary forms, which eventually still reach the surface of the lungs. Deviations in the course of croupous pneumonia are numerous and frequent, and they depend, on the one hand, on the characteristics of the infection, and on the other hand, on the characteristics of the reaction of the pulmonary tissue, previous diseases, and the state of cardiac activity and the entire organism. The above-described classic progression of the periods of hepatization with resolution as an outcome is a property of the majority of pneumonias with pneumococci of types I, II, and IV. Pneumococci of type III are usually found in atypically proceeding cases (absence of lobarity, absence of granularity on the cross-section, purulence of gray hepatization, true suppuration, hemorrhages, sequestra, etc.). In general, these cases have a great similarity to Friedländer's pneumonias. Friedländer's forms of pneumonia almost always reveal significant deviations in terms of morphology and evolution. Lobarity is very often absent in them, although this may be because this form occurs more often in old age and in subjects with impaired nutrition, in alcoholics. Usually, groups of foci of hepatic consistency are observed, and even individual, sometimes completely round, gray-colored nodules scattered in various parts of the lung. Sometimes such nodules merge, and pseudolobar foci arise. Lesions of the upper lobes in Friedländer's forms are especially frequent. The evolution of pneumonic foci of Friedländer's pneumonias is very often atypical: a great tendency toward the formation of necroses and sequestra; on this basis, severe hemorrhages, the development of large cavities with dirty, uneven walls, gangrene of the lung, etc., are possible. The most striking sign of this same pneumonia is the character of the exudate, which can be scraped off and even flows independently from the surface of the cross-section of the foci: it is extremely abundant and has the character of turbid, thick, mucous masses that emit a peculiar smell of burnt meat. Under the microscope, leukocytes, abundant cellular detritus, and masses of mucus with a large number of diplobacilli are discovered [see separate table (to the article Lung), figure 8]; the usually noted weak stainability of the latter depends on their strong envelopment by a powerful mucous capsule, and on the other hand, on the pronounced phenomena of plasmolysis of the bodies of the bacilli themselves. The abundance of bacilli is also striking during histological examination of the lungs; sometimes they are an exclusive constituent part of the intra-alveolar content. Friedländer's 'mucous' pneumonias are distinguished by especially intense toxic, and often septic or pyemic phenomena with septic jaundice, hemorrhages into the skin and mucous membranes, acute serositis, etc. Their mortality is apparently the highest among all pneumonias. All of the above can also be applied to pneumococcal pneumonias of type III; only in the exudate are not bacilli, but chains of pneumococci discovered, usually also weakly stainable due to their envelopment by mucus and plasmolysis. As special microbiological varieties, one should distinguish croupous pneumonias in the exudate of which ordinary or hemolytic streptococcus, staphylococcus, and also mixed infection, especially with the Pfeiffer bacillus, are discovered. In both cases, a feature is the tendency toward hemorrhages: the hepatized lung has a mottled appearance, somewhat resembling variegated grippe pneumonias; by the way, the tendency toward protracted suppuration and carnification (see below) is also significant here. The parts of the lung that remained free from the lesion also undergo certain changes, mainly in the sense of the development of phenomena of acute vicarious emphysema in them. Croupous pneumonia is as a rule accompanied by pleurisy. Pleuritic processes usually arise in the very first days of the disease (parapneumonic pleurisies); less often, the appearance of exudate is noted only in the course of the development of the disease, sometimes at its end as a complication (metapneumonic pleurisies, especially empyemas). The exudate most often has a fibrinous [see separate table (to the article Lung), figure 7] or serofibrinous, less often purulent character. Complications. The wide possibility of the development of various complications in croupous pneumonia follows by itself from a whole series of premises relating to the morphology, dynamics, and microbiology of the process. Of enormous importance, furthermore, are questions of general nutrition, age, and the state of the respiratory tract, especially the lungs, before the onset of pneumonia; pneumonias developing under conditions of stasis in the pulmonary circulation (in heart defects), in various intoxications (alcoholism, uremia), etc., are sometimes very atypical. It is necessary, however, to distinguish the atypical course of pneumonia from complications in them. Only those cases where the course of the disease at one stage or another of its development makes a sharp departure from the essence of the process should be designated as complications. If the essence of the process remains within the limits of the indicated regularities and only features of a topographical character (e.g., upper pneumonias), or of a volumetric character (non-lobar pneumonias), or of a chronological character (rapid or, conversely, slow evolution) are noted, or finally, if there is a falling out of some stages, or the brightness of others—then in all these cases it is more correct to speak not of complications, but of atypical forms of pneumonia. The most important complications of pneumonia are gangrene, abscess (see Lung, abscess, gangrene), purulent lymphangitis, and carnification of the lung. From typical gangrene, one should distinguish its so-called aputrid form (pneumomalacia), when there is no putrid decay and the corresponding odor; in this case, aspergilli and sarcinae are often found in the decay in abundant quantities. Aputrid forms are comparatively frequent in diabetics and in Friedländer's pneumonias. If putrid gangrene of the lung in the overwhelming majority of cases ends in death, this cannot be said about aputrid forms, in which a favorable outcome is sometimes observed, namely the liquefaction of necrotic masses, their removal through the bronchial tree with subsequent epithelialization of the cavity formed at the site of the sequestrum. Such cavities resemble lung cysts, smooth caverns. Purulent lymphangitis of the lung and pleura is a serious complication [see separate table (to the article Lung), fig. 9]. Macroscopically in these cases, a strong thickening and gray-green color of the interstitial tissue of the lung are discovered, and under the microscope, lymphatic vessels strongly distended by purulent exudate and loosened connective tissue. Purulent lymphangitis is usually combined with the development of sequestra, lung abscesses, pleural empyemas, purulent lymphangitis and lymphadenitis of the mediastinum, and mediastinitis; sometimes the process descends down to the peritoneum along the coronary ligament of the liver or along the lymphatic system of the diaphragm, causing peritonitis. Streptococci are a common finding in all these cases. Carnification of the lung is observed in those cases when the usual processes of resorption of fibrinous exudate are weakly expressed or fall out, and the so-called organization of exudate occurs, resembling the organization of a thrombus. Microscopically, the process is expressed first in the ingrowth of the exudate by individual mesenchymal elements, and later by ordinary granulation tissue with vessels; intra-alveolar fibrinous casts gradually turn into dense lumps of fibrous tissue, organically fused both with the walls of the alveoli and with each other through pores and terminal funnels. In the late stages of carnification, the corresponding parts of the lung become almost unrecognizable; true, with the help of staining for elastic tissue, it is possible even at this time to discover elastic fibers, which here and there continue to border the contours of the alveolar parenchyma of the lung, but later even this characteristic detail disappears. Carnified parts of the lungs have the consistency of meat, are airless, and are gray-pink, and later gray, in color [see separate table (pp. 623-624), fig. 3]. Very often, bronchiectases as well as abscesses are found in the same areas; the combination with the latter is a more common than rare phenomenon. Not always, however, is carnification caused by an intra-alveolar process of organization of the effusion. Cases are observed when sclerotic changes proceed predominantly interstitially [see separate table].
(pp. 623-624), figure 2); the entire stroma of the lung becomes sharply coarsened, in particular, the alveolar and interinfundibular septa thicken; the aeration of such a lung also drops sharply. At the basis of interstitial sclerosis of the lung lies usually its lymphangitis, sometimes accompanied by thrombosis of the lymphatic system. About 3% of all croupous pneumonias are complicated by serofibrinous pericarditis. Occasionally, peritonitis is observed, mainly in childhood. The mechanism of development of such peritonitis apparently can be twofold. On one hand, the inflammatory process from the side of the diaphragmatic pleura can deepen along the intermuscular layers of the diaphragm (microperforation) and emerge under the peritoneum; that is why a matte, i.e., fibrin-covered peritoneum in the region of the diaphragm and a matte surface of the liver are not a great rarity in pneumonia, especially on the right. On the other hand, they point to embolism of the vessels of the peritoneum by diplococci (hematogenous peritonitis, see below). Diplococcal purulent metapneumonic peritonitis often proceeds without the usual bright phenomena generally characteristic of peritonitis; that is why the majority of them are only an accidental finding at autopsy. Endocarditis is found in 4-5% of all autopsies in pneumonia; the majority of them, it is true, fall on patients who already had a heart defect (rheumatic) previously, which only exacerbated under the influence of pneumonia. Infarcts of the lungs observed during endocarditis sometimes lead to the development of typical croupous-pneumonic processes. On the other hand, in all such cases, it is necessary to clarify the sequence of events, since infarcts can also arise as a complication of croupous pneumonia. Pneumonias in patients with heart defects are distinguished by certain features of a local and general character. Developing usually against the background of already existing congestion in the lesser circulation, for example, in mitral stenosis, they are often accompanied by violent hemorrhages per diapedesin. An extremely characteristic finding for hearts in pneumonia patients is the finding in the cavities of the heart of powerful light clots of fibrin, emphasizing the hyperfibrinosis of the plasma and increased blood coagulability in these patients. Among the complications of croupous pneumonia, meningitis often figures (about 6% of all cases). Macroscopically, one discovers impregnation of the soft meninges with exudate, especially of the vault of the brain, and the exudate itself can be serous (slightly turbid), seropurulent, and purulent; the yellowish shade of the color of the exudate in diplococcal meningitis draws attention. Upper pneumonias give meningitis especially often. A fairly common phenomenon for pneumonia turns out to be degenerative and inflammatory changes on the part of the sympathetic ganglia, especially the cervical ones. It is possible that these changes have a certain significance for the development of such symptoms as hyperemia and puffiness of the face of pneumonia patients, hyperemia of the brain and its membranes, etc. Childhood pneumonias. The change of phases of hepatization in pneumonia in children proceeds faster, the amount of fibrin is less than in adults, but on the other hand, an abundance of desquamated pulmonary epithelium is always noted, so that sometimes the histological distinction of such pneumonias from banal bronchopneumonias becomes difficult, all the more so because the volume of the foci themselves most often remains lobular. Migratory forms are comparatively frequent. Often in children, the paravertebral sections of the lung parenchyma are preferentially affected (especially in children under 1 year), as well as the upper lobes of the lungs. Statistical observations show that in small children, the right upper and left lower lobes of the lungs are especially predisposed to the disease; they even point to an almost complete immunity of the left upper lobe. Compared to adults, herpes is noted more often in children. Several cases of croupous (lobar) pneumonia in newborns (so-called congenital pneumonias) have been described. In all such cases, croupous pneumonia was also observed in the mothers. I. Davydovsky. Pathogenesis. The pathways of penetration into the pulmonary parenchyma of the pneumococcus or other microorganisms causing croupous pneumonia have not yet been finally clarified. The majority of authors stand on the point of view of bronchogenic penetration of the infection. Besides clinical observations, which will be discussed later, experimental studies speak in favor of this view. As we have already indicated, Blake and Cecil induced in monkeys a disease completely analogous to human croupous pneumonia by intratracheal introduction of small quantities of pneumococcal culture (0.001-0.000001 cm3). The observations of these authors speak for the fact that pneumococci, with the indicated method of introduction into the respiratory tract, do not directly enter the alveoli. Studies of the organs of infected monkeys show that pneumococci penetrate through the walls of bronchi of fairly large caliber into the lung tissue, where they, spreading perivascularly and peribronchially along the lymphatic pathways, cause an interstitial inflammatory process, into which the alveolar epithelium is involved only secondarily. Pneumococci, thus, according to the observations of Blake and Cecil, penetrate into the alveoli not directly through the air passages, but from the lung parenchyma. The described method of penetration and further spread of infection, at the basis of which lies primary infection of the lymphatic pathways, makes partly understandable the "lobar" character of the process, i.e., the tendency to affect entire lobes. A number of authors, especially French ones (Widal, Calmette), stand on another point of view regarding the pathogenesis of croupous pneumonia. They believe that pneumococci penetrate into the lung parenchyma by the hematogenous route and that croupous pneumonia, like typhoid fever, is thus a primary bacteremia. Proponents of this view point to the fact that the pneumococcus can be detected in the blood in the very earliest periods of the disease, when any symptoms (including those observed during X-ray examination) indicating lung damage are still absent. These arguments, however, are not convincing, since the absence of corresponding symptoms during clinical examination by no means excludes the presence of an initial stage of the inflammatory process in the lungs. It has been proven that even X-ray examination does not always catch the first phases of the pneumonic process, especially the stage of hyperemia. Numerous clinical observations speak for the primary localization of the process in the lungs, when croupous pneumonia begins immediately amidst complete health and when immediately following the initial stunning chill or even simultaneously with it, typical stabbing pain in the side and cough appear—symptoms indicating lung damage already at the very beginning of the disease. The cases often observed when croupous pneumonia is preceded for a long or short period by phenomena of catarrh of the upper respiratory tract also speak for the bronchogenic penetration of pneumococci into the lung tissue. Multiple blood cultures in one and the same patient, which showed that regardless of the stage of the disease in the majority of cases it is not possible to detect the pneumococcus in the blood (Ettinger, Viktorov, Mazel), also speak against primary bacteremia. The cases of intrauterine disease of the fetus with croupous pneumonia described in the literature indicate that the hematogenous origin of this infection is nevertheless possible under certain conditions. Rapidly multiplying in the affected lung tissue, the pneumococcus releases toxic substances in the process. The latter, being absorbed and penetrating into the general circulatory system, cause disturbances in different systems of the organism. In a number of cases, the matter is not limited to toxemia alone. From the affected lung tissue, the pneumococcus penetrates in greater or lesser quantity into the circulatory system. As observations by a number of authors have shown, cases with bacteremia proceed especially severely, giving a significantly higher percentage of lethal outcomes in comparison with the average mortality in croupous pneumonia. The pneumococcus circulating in the blood, localizing in different organs, can cause sharp changes in the latter, giving a number of severe, often fatal complications, such as purulent meningitis, ulcerative endocarditis, purulent pericarditis, peritonitis, etc. The respiratory insufficiency (dyspnea, cyanosis) observed in croupous pneumonia is only partly explained by the exclusion of the affected section of lung tissue from the act of breathing. A large role in the origin of anoxemia is played by insufficiency of the heart and especially of the vascular system. As Romberg and Pässler (Romberg, Pässler) showed on the basis of experimental studies, toxins in pneumonia act mainly not on the heart, but on the vasomotor centers. At the basis of the collapse often observed in croupous pneumonia, which often leads to death, lies an acutely occurring sharp decrease in the tone of the vasomotors, leading to the accumulation of blood in the organs of the abdominal cavity and the insufficient blood supply to the central nervous system and heart connected with this. The processes lying at the basis of the cyclic course of croupous pneumonia, in particular the mechanism of the crisis, have not yet been sufficiently clarified.
A number of authors (Klemperer, Romer, Neufeld, Handel) have shown that shortly before the crisis, and especially during and after it, protective bodies appear in the blood of patients with lobar pneumonia, which protect white mice when they are infected with a highly virulent pneumococcal culture in an amount many times exceeding the lethal dose. It has been proven that these protective bodies possess type specificity, protecting mice only when they are infected with a homologous strain, i.e., a pneumococcal culture of the same type with which the given patient is infected. As some authors (Baldwin, Rhoades) have shown, these protective bodies are as a rule absent in blood samples in which pneumococci can be detected. These authors have repeatedly observed the disappearance of pneumococci from the blood upon the appearance of protective bodies. In cases ending lethally, protective bodies are absent in the blood right up until death. In the process of preventing and hindering the generalization of pneumonic infection, these antibodies apparently have great significance. Their significance in the mechanism of the crisis itself cannot, however, be considered finally clarified, since, on the one hand, it is not possible to detect these substances in the blood of all convalescents after lobar pneumonia, and, on the other hand, their appearance does not always coincide with the crisis. Often, a high titer of these substances can be detected even several days before the drop in temperature. In the mechanism of the crisis, besides the appearance of these antibodies, other, little-studied processes, likely of a cellular nature, such as phagocytosis, etc., play a large role. In the process of eliminating the infection, besides the reaction of the macroorganism, the changes that the microorganism undergoes during the pneumonic process undoubtedly also have significance. As Lubarsch has shown, the pneumococcus possesses the greatest virulence in the initial stages of the disease, but as the crisis approaches, its virulence decreases. The parallel processes occurring on the part of the macro- and microorganism are closely linked to each other and constantly influence one another, and at a certain moment of the infection, they cause that turning point which lies at the basis of the crisis. Clinical features. Typical course of lobar pneumonia. In typical cases, lobar pneumonia begins immediately, suddenly, amidst complete health. Patients often fall ill while working. In the anamnesis, there is often an indication even of the hour the disease began. Soon after the appearance of the first painful symptoms in the form of general weakness, malaise, aching in the limbs, and headache, a shaking chill occurs, lasting from 10–15 minutes to 1–2 hours. The temperature rises rapidly and within the first hours after the chill usually reaches 39° and even higher figures. In a number of cases, even during the chill or shortly after it, a stabbing pain in the side appears, which usually intensifies upon inhalation. A cough, painful and consequently suppressed by the patient, also often appears on the very first day of the disease. The patient's well-being worsens more and more, appetite disappears, and thirst appears. Because of the severe headache, general agitation, and painful cough, the patient usually spends the first night without sleep. In typically progressing cases of lobar pneumonia, a number of other characteristic symptoms appear on the first or second day of the disease. A sharp increase in the rate of breathing appears (30–40 and more per minute), which does not correspond to the temperature and pulse; herpes breaks out on the lips or wings of the nose, and a characteristic hyperemia of the cheeks appears. Already at this time, it is often possible to ascertain a lag in the breathing of one half of the chest and the participation of so-called auxiliary muscles in the respiratory movements. Because of the stabbing pain in the side and the painful cough, breathing is superficial and irregular, and speech is difficult. Blood examination usually already in this period reveals neutrophilic leukocytosis, and urine examination reveals a sharp decrease or almost complete disappearance of chlorides. Typical rusty sputum, which finally confirms the diagnosis, only rarely appears before the third day of the disease. Symptoms upon physical examination that definitely indicate the localization of the inflammatory process in the lungs (see below) often appear as early as the 2nd–3rd day of the disease; in a number of cases, however, they can only be detected in subsequent days. Along with phenomena indicating a pneumonic focus, scattered dry and moist rales are often observed as a manifestation of accompanying bronchitis. The temperature curve in typical cases has the character of a continuous fever (see below). In a number of cases, 2–3 days before the crisis, and sometimes in the first days of the disease, a sudden drop in temperature is observed, often by 3–4°, to normal and even subnormal figures. This drop in temperature usually lasts only a few hours, being replaced by a new rise. During such so-called pseudocrises, the patient's well-being often improves, but the breathing and pulse continue to remain frequent, which usually allows one to distinguish these temporary drops in temperature from a true crisis. On the 4th–5th day of the disease, especially in more severe cases, phenomena on the part of the cardiovascular and nervous systems begin to come to the fore. The pulse becomes softer and more frequent, the filling is less, dyspnea intensifies, and cyanosis appears. On the part of the nervous system, various degrees of disorder are observed, ranging from drowsiness and mild delirium to a severe soporous and even comatose state. In typical cases, lobar pneumonia ends in a crisis, which usually occurs at the end of the first or the beginning of the second week of the disease. The temperature drops within 12–24 hours, often reaching subnormal figures. The crisis is usually accompanied by profuse sweating. Within a few hours, a sharp turning point occurs in the patient's condition. Breathing and pulse become less frequent and return to normal figures. During the crisis, the patient often falls into a sleep, from which he wakes up with a normal temperature and a sharp improvement in well-being. In a number of cases, the crisis is immediately preceded by a sharp rise in temperature with a worsening of well-being and general condition. This phenomenon (so-called critical perturbation) contributes to an even greater magnitude of the critical drop in the temperature curve. Far from all cases of lobar pneumonia end in a crisis. A lytic drop in temperature over 2–3 days is often observed. The return of the temperature to normal does not coincide with the disappearance of the inflammatory infiltrate in the lungs. Symptoms upon physical examination indicating consolidation of the lung tissue (dullness of the percussion sound, bronchial breathing, crepitant, resonant moist rales, bronchophony) may persist after the drop in temperature for a week, and sometimes for a longer period, usually having little effect on the patient's well-being and general condition. The duration of the convalescence period and the time for the restoration of working capacity depend on the severity of the disease, the patient's age, and individual reaction. In a number of cases, patients feel completely recovered after 1 1/2–2 weeks. Usually, the convalescence period until the restoration of working capacity lasts no less than a month. In some cases of lobar pneumonia, a few days after the crisis, a new rise in temperature is observed with a new flare-up of the pneumonic process. These so-called recurrences of pneumonia (rekurrierende Pneumonie of German authors, pneumonie à rechute of the French) are observed very rarely, according to the statistics of a number of authors, in less than 1% of all cases. The second inflammatory process may be localized in the site of the first lesion or in a new area of lung tissue.
Special symptomatology. A sudden onset of the disease is observed in far from all cases of lobar pneumonia. Not infrequently, the disease is preceded for several days by more or less pronounced prodromal phenomena—malaise, headache, poor appetite, aching in the back and limbs, and in a number of cases also phenomena of upper respiratory tract catarrh (pharyngitis, laryngitis, rhinitis). Some authors suggest isolating into a separate group of secondary lobar pneumonia those cases which arise against the background of a preceding upper respiratory tract catarrh. Even in cases proceeding with prodromal phenomena, the onset of the pneumonic process is often marked by a shaking chill. The latter, however, is not an obligatory symptom of lobar pneumonia. Not infrequently, patients note only more or less pronounced repeated shivering in the first days of the disease.
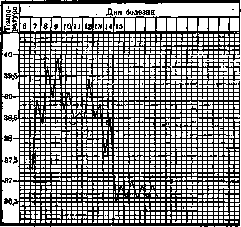
The temperature in lobar pneumonia (Figures 8-10) usually rises rapidly, reaching 39-40° within the first few hours. In cases arising against the background of a preceding influenza infection, the addition of pneumonia usually affects the temperature curve in the form of a more or less sharp rise. The temperature curve in lobar pneumonia in approximately 2/3 of all cases has the character of a continua, while in the remaining cases it shows fluctuations of a remittent and even intermittent type. The character of the temperature curve partly depends on the type of pneumococcus with which the patient is infected. Thus, lobar pneumonia of Type I in more than 70% of all cases proceeds with a temperature curve of the continua type with daily fluctuations of less than one degree. Type III pneumonia, on the contrary, in 2/3 of all cases gives a remittent and intermittent curve. Cases of lobar pneumonia of Type II and Type IV occupy an intermediate position between Type I and Type III in relation to the temperature curve. A fall of the temperature curve down to subnormal figures is observed during the disease in so-called pseudocrises, as well as during collapses. The final fall of temperature in lobar pneumonia in some cases has the character of a crisis, and in others—a protracted crisis or lysis. One speaks of a crisis when the fall of temperature lasts no more than 12-24 hours. With a duration of the temperature fall period from 24 to 48 hours, one speaks of a protracted crisis or accelerated lysis. Even longer periods of temperature fall are referred to as lysis. The study of the clinical picture of lobar pneumonia in connection with the type of pneumococcus shows that the character of the fall of the temperature curve partly depends on the variety of the pathogen. Thus, lobar pneumonia of Type I in approximately 75% of all cases ends with a crisis, while approximately the same percentage of cases of lobar pneumonia of Type III gives a lytic termination of the infection. The second and fourth types occupy an intermediate position between Type I and Type III in relation to the character of the temperature fall (Etinger, Mazel, Viktorov). The period of convalescence usually proceeds with a normal temperature. Only in relatively rare cases is a subfebrile temperature observed, apparently associated with the absorption of the alveolar exudate. A protracted temperature or a new rise of the latter after a crisis is usually caused by those observed in lobar pneumonia.
complications of pneumonia—empyema, abscess—or by the failure of the pneumonic process to resolve (carnification of the lung). In the elderly, as well as in individuals exhausted by severe preceding diseases, croupous pneumonia may proceed with a subfebrile temperature or even with a complete absence of a temperature reaction. General appearance of the patient. Croupous pneumonia often gives the patient's face a certain peculiar, characteristic appearance, so that some authors speak directly of facies pneumonica. Noteworthy is the more or less intense hyperemia of the cheeks with a bluish tint, often more pronounced on the side of the affected lung. The picture of the pneumonic face also includes the participation of the nostrils in respiratory movements, which is often observed. In more severe cases, a sharply pronounced cyanosis of the lips and ears appears as early as the first days of the disease. Herpes is observed in far from all cases of croupous pneumonia (according to data from various authors, the frequency of this symptom fluctuates from 13% to 43%). Most often it erupts on the lips or nostrils, less often on the neck and earlobe, and very rarely on the external genitalia or in the area of the anus. Some authors view herpes as a toxic phenomenon associated with damage to the corresponding nerve elements. Other authors, on the basis that in some cases it is possible to isolate the pneumococcus from the vesicles, speak of the localization of the pneumonic infection in the skin tissue. From the point of view of authors who adhere to the view of herpes as a manifestation of a special filterable virus, croupous pneumonia should be considered one of the infections that activate this virus under certain conditions. A number of authors consider the eruption of herpes to be a prognostically favorable symptom. Cases proceeding without herpes supposedly yield a higher percentage of mortality.
Pain in the side, associated with the involvement of the pleura in the inflammatory process, is observed in the vast majority of cases of croupous pneumonia and is often one of the patient's main complaints. Pain in the side, which usually intensifies during deep inspiration and coughing, is especially intense in the first 2–3 days of the disease and then gradually weakens. It is usually localized at the level of the nipple on the affected side. In some cases, the pain radiates into the abdominal cavity or is concentrated exclusively there, which can simulate an acute disease of the abdominal cavity (appendicitis, cholecystitis, perforated peritonitis). In rare cases, patients feel pain not on the affected side, but on the healthy side. Some authors explain this paradoxical phenomenon by the anastomoses between the intercostal nerves present in these cases. Cough is often an early symptom, arising as early as the first day of the disease. In a number of cases, however, it appears later. Expectoration of sputum in croupous pneumonia is usually difficult due to its viscous consistency. As the crisis approaches, the sputum becomes more liquid, which facilitates its discharge. In senile and asthenic pneumonia and in the pneumonia of alcoholics, which proceeds with delirium tremens, cough is often absent. Sputum in croupous pneumonia is extremely typical. Its quantity is usually small. In different cases, fluctuations are observed from 2–3 tablespoons to 200 cm3 per day. The coloration of the sputum can have different shades (brick-red, yellowish, yellowish-green, the color of prune decoction), which depends on the nature and degree of change in the leached hemoglobin. The brownish-red shade observed in the overwhelming majority of cases, resembling the color of rusty iron, is so characteristic that it is almost pathognomonic for croupous pneumonia. This so-called rusty sputum is usually not an early symptom. In the first days of the disease, the patient either does not produce sputum at all or the latter has a mucopurulent character. In the days preceding the crisis, the rusty color of the sputum often disappears. The latter then becomes completely discolored or acquires a yellowish-greenish tint. Sputum has an especially sharply pronounced green tint in so-called bilious pneumonia (proceeding with jaundice), as well as in cases of croupous pneumonia resulting in abscess formation or carnification. In all phases of the disease, the sputum often contains an admixture of red, unchanged blood in the form of separate spits. More profuse hemoptysis is not characteristic of croupous pneumonia. It is observed only in the so-called variegated pneumonia of the Spanish flu, as well as in some severe cases of Friedländer's pneumonia. Pneumonic sputum in some cases contains macroscopically visible, dichotomously branched casts of small bronchi consisting of fibrin. Sputum, both in the first days of the disease, when it usually does not yet have a characteristic color, and at the height of the disease, is distinguished by viscosity, is expectorated with difficulty, and adheres tightly to the walls of the vessel containing it. During convalescence, the discharge of sputum continues for a more or less prolonged period. At this time, it is usually no longer colored, has a mucopurulent character, and is expectorated more easily. Sputum contains proteins and nucleins in solution. The latter are mainly responsible for the viscous nature of the secretions. Under a microscope, in addition to erythrocytes, partly unchanged and partly leached, it is possible to detect Fraenkel's diplococci in the sputum of patients with croupous pneumonia with appropriate staining. The latter are usually observed in large numbers at the height of the disease, decreasing as the crisis approaches. In those cases where pneumonia is caused by the Friedländer bacillus, the latter can also usually be detected during microscopic examination. Sputum in croupous pneumonia may be completely absent; this is observed especially often in children, the elderly, or in individuals exhausted by severe preceding diseases. In relatively rare cases, even with common forms of croupous pneumonia, sputum is completely absent during the entire time of the disease, which complicates or makes it completely impossible to determine the type of pneumococcus with which the given patient is infected. In some cases of croupous pneumonia, the sputum has a bronchitic, mucopurulent character during the entire time of the disease.
Phenomena from the lungs during physical examination have been linked to anatomical stages since the time of Laennec. Already in the period of engorgement, it is usually possible to detect a slight dullness of the percussion sound with a peculiar tympanic tint. These percussion changes are apparently associated with a decrease in the elasticity of the hyperemic lung tissue. The respiratory sound in this period usually retains its vesicular character, but due to the sparing of the affected side, it is often weakened. A characteristic auscultatory symptom of the stage of engorgement is fine crepitant rales, most clearly audible at the height of inspiration (so-called crepitatio indux). Often, crepitation clearly appears only after cough impulses. In a number of cases of croupous pneumonia, the phenomenon of crepitatio indux cannot be detected even with careful daily examination of the patient. Along with typical crepitation, scattered dry and moist rales associated with concomitant bronchitis are often heard in a limited area. As the process transitions into the stage of hepatization, the dullness becomes increasingly intense, usually, however, not acquiring the character of the femoral tone characteristic of exudative pleurisy. Even at the height of the disease, the dull sound usually retains a tympanic tint. Auscultation in this period yields typical bronchial breathing and increased bronchophony. Simultaneously, increased vocal fremitus usually appears over the surface of the consolidated lung tissue. The latter phenomenon is not
Pneumonia
constant in lobar pneumonia. In a number of cases, vocal fremitus is even weakened. This is observed especially often in so-called massive pneumonia, when the inflammatory exudate fills not only the alveoli but also the supplying bronchi. The intensity of bronchial breathing in lobar pneumonia can be very diverse. In cases where, due to severe pain, sparing of the affected side is sharply pronounced, or in cases of so-called massive pneumonia, the respiratory noise over the consolidated area may be sharply weakened, while still usually retaining a shade of bronchial breathing. The latter in these cases sounds as if from afar. Bronchial breathing is often more clearly revealed by direct auscultation. Crepitant rales, associated with the presence of liquid exudate in the alveoli, usually1 disappear during this period. They may appear in neighboring areas later involved in the inflammatory process. Over the affected pulmonary lobe, along with bronchial breathing, dry and moist resonant rales of various calibers are usually heard, which is a reflection of the accompanying catarrhal process in the bronchi surrounded by consolidated lung tissue. At the height of the disease, in the period of hepatization, rales may, however, be completely absent, so that the only auscultatory symptom is bronchial breathing and increased bronchophony. In the days preceding the crisis, the number of moist rales usually becomes more abundant. Along with the indicated auscultatory phenomena, a pleural friction rub is often heard, indicating accompanying pleurisy. The beginning of resolution of pneumonia and the associated thinning of the inflammatory exudate in the alveoli is noted during auscultation by the new appearance of crepitation (so-called crepitatio redux). Crepitant rales in this period are usually more abundant and have a coarser character in comparison with the similar phenomenon of the stage of engorgement. As the exudate is resorbed, bronchial breathing gradually changes to vesicular. In parallel, the intensity of bronchophony and vocal fremitus decreases. Dullness of the percussion sound also gradually disappears. It should be borne in mind that from a clinical point of view, drawing a sharp distinction between the three Laennec stages is usually not possible, since individual areas of the affected lung tissue are often at different stages of inflammation, as a result of which the picture during physical examination has a variegated character. In the blood in lobar pneumonia, in the majority of cases, a sharply pronounced neutrophilic leukocytosis is found. The number of leukocytes often reaches 30,000–40,000, and in some cases even higher figures. Neutrophils usually make up 80–90% of the total number of white blood cells. Eosinophils are almost always absent, especially in severe cases. A weak leukocyte reaction or even its complete absence is observed, on the one hand, in a very severe course of infection, and on the other, in very mild cases. As Chatard showed on the basis of a large amount of material, cases of lobar pneumonia proceeding with leukocytosis below 10,000 yield a huge mortality—55–60%. According to the observations of Norris and Farley, out of 108 cases of lobar pneumonia that proceeded without a leukocyte reaction, 94 ended lethally. A single blood test, however, can be misleading regarding the prognosis of the disease. Thus, during the transition of the process from one lobe to another, a temporary drop in the number of leukocytes is often observed, which, however, is not a prognostically unfavorable symptom. A gradual and steady increase in leukocytes during the course of the disease usually indicates a favorable course of the process. After the crisis, the number of leukocytes quickly returns to normal. Prolonged leukocytosis after the elimination of acute phenomena from the lungs usually indicates a complication with a purulent process (empyema, lung abscess, etc.). In the recovery period, proceeding without complications, an increase in the number of lymphocytes is often observed (so-called post-infectious lymphocytosis). At the height of the disease, the number of platelets usually falls. After the crisis, on the contrary, an increase in their number is observed. The erythrocyte sedimentation reaction in patients with lobar pneumonia is as a rule accelerated. It returns to normal only after a more or less long period after the crisis. In rare cases, normal erythrocyte sedimentation is observed throughout the entire disease. The amount of fibrinogen in the blood is in almost all cases more or less sharply increased. Blood coagulability is usually lowered. The accelerated erythrocyte sedimentation reaction, along with decreased blood coagulability and an increase in the amount of fibrinogen and the number of leukocytes, lies at the basis of the formation of the so-called crusta phlogistica phenomenon, well known to old authors who widely used bloodletting in lobar pneumonia. In a number of cases, especially with a severe course, it is possible to isolate a culture of pneumococcus from the blood, and in cases ending lethally, the number of microorganisms in 1 cm3 increases until death. The number of cases of lobar pneumonia proceeding with bacteremia, according to the data of various authors, ranges from 25% to 80%. Lobar pneumonia is accompanied by sharply pronounced metabolic disturbances, with the most characteristic disorder being the retention of sodium chloride in the body. Usually, from the very beginning of the disease, the amount of NaCl excreted in the urine drops sharply. Its daily amount reaches 1 g and less instead of the usual 10–15 g. A solution of silver nitrate, added to the urine, gives insignificant turbidity or even a complete absence of reaction. Chloride retention in the body, although observed in some other infectious diseases, is more constant and very sharply pronounced in lobar pneumonia, as a result of which it has a definite diagnostic significance. It is not possible to explain the retention of NaCl in the body exclusively by its accumulation in the inflammatory exudate, since the NaCl content in the affected pulmonary lobes is not sharply increased. All tissues take part in the retention of NaCl. In the first days after the crisis, its excretion in the urine increases sharply, reaching 30–35 g per day. NaCl retention in the body in lobar pneumonia is not accompanied by edema (so-called dry retention). In lobar pneumonia, protein and purine metabolism is as a rule increased. During the illness and in the first days after the crisis, the amount of excreted urea and uric acid is sharply increased. In the stage of resolution, the increased excretion of the end products of nitrogen metabolism is associated with autolytic processes occurring in the alveolar exudate. As Fr. Müller showed, enzymes with trypsin-like action, apparently originating from leukocytes, play a large role in the process of exudate resorption. The autolysate contains amino acids (leucine, tyrosine, lysine, histidine, etc.), as well as purine bases (xanthine and hypoxanthine). The appearance in some cases of albumoses in the urine after the crisis is also associated with the indicated enzymatic processes. The urine is usually concentrated, has a high specific gravity, and contains an increased amount of urobilin, urea, and uric acid. A positive diazo reaction, a small amount of protein, and also individual casts are often observed. This so-called febrile albuminuria has an innocent character and does not affect the prognosis of the disease. More sharply pronounced phenomena from the kidneys, allowing one to speak of nephritis or nephroso-nephritis, are observed rarely and are classified as complications. In a large percentage of cases of lobar pneumonia, a substance of pneumococcal origin appears in the urine, giving a precipitation reaction with specific pneumococcal serum. This reaction is distinguished by strict type specificity, i.e., it is obtained only with the antipneumococcal serum of the type with which the given patient is infected. This substance often appears only shortly before the crisis or even after it; in a number of cases, however, it can be detected already in the first stage of the disease, even 12 hours after the initial chill. This reaction has a certain practical significance, as it makes it possible to quickly determine the type of pneumococcus with which the patient is infected, which is a necessary prerequisite for rational serum treatment. The described specific substance of pneumococcal origin is excreted in the urine even after the crisis, usually for 2–3 weeks, sometimes for a longer time (Etinger, Viktorov, Mazel). The precipitation reaction with urine can thus have a certain significance for the retrospective diagnosis of lobar pneumonia. Cardiovascular system. In cases of mild or moderate severity, the pulse rate usually ranges from 100 to 120 beats per minute. Prolonged pulse acceleration over 120 per minute almost always indicates a severe form of the disease. Starting from the 3rd–4th day of the disease, especially in cases with a severe course, a more or less sharply pronounced drop in blood pressure is usually observed. The pulse at this time becomes softer, the filling worse. In some severe cases, a disturbance of the heart rhythm is observed in the form of extrasystoles or individual dropped ventricular contractions on the basis of partial block.
Often in croupous pneumonia, both by percussion and X-ray, it is possible to detect an expansion of the heart borders, especially to the right, which is apparently connected with the difficulty of blood circulation in the lesser circulation. This is also indicated by the accent on the second tone of the pulmonary artery observed in a number of cases. Often a systolic murmur appears at the apex and at the base of the heart, which has no special significance and usually disappears after the crisis. The collapse often observed in croupous pneumonia, which is based on toxic paresis of the vasomotor system, is clinically manifested by a sharp general decline in strength, a drop in temperature, increased shortness of breath, sharp cyanosis, cooling of the extremities, a frequent and small pulse, as well as poor filling of the peripheral veins, up to their complete collapse (in cases of circulatory insufficiency caused by primary weakness of the heart muscle, the peripheral veins, on the contrary, usually swell). Collapse can occur both at the height of the disease and during or after the crisis. The immediate cause of death in croupous pneumonia is usually pulmonary edema. The latter in most cases occurs as a result of progressive deterioration of blood circulation. In rarer cases, pulmonary edema occurs unexpectedly with a relatively good general condition of the patient. The nervous system is affected to a greater or lesser degree in almost all cases of croupous pneumonia. Patients usually complain of headache and insomnia from the beginning of the disease. The agitated state of the patient is noteworthy. The sensorium may remain clear throughout the entire disease. Often, however, even in cases with a relatively mild course, delirium is observed, especially in the evening hours and at night. In severe cases, violent delirium is observed, with a sharply pronounced disorder of consciousness, up to a soporous and comatose state. Croupous pneumonia of the upper lobes, according to the observations of a number of authors, is more often accompanied by sharply pronounced phenomena from the nervous system. In alcoholics, delirium often takes on the character of delirium tremens from the beginning of the disease. In relatively rare cases, pneumonia begins with violent meningeal phenomena. The entire picture of meningitis may be present (stiffness of the neck, Kernig's sign, sharply pronounced skin hyperesthesia, etc.). The cerebrospinal fluid, flowing out during a puncture of the spinal canal under increased pressure, is in these cases transparent and does not contain pneumococci. These phenomena of meningism usually decrease in their intensity or disappear altogether in the second half of the disease, when pneumonic symptoms appear. Some authors have described the absence of pupillary and patellar reflexes as a transient phenomenon in croupous pneumonia. Gastrointestinal tract. At the beginning of the disease in adults, vomiting is sometimes observed. The appetite is usually sharply reduced, the tongue is coated and dry. In most cases, constipation is observed, in rare cases—persistent diarrhea, which greatly exhausts the patient. In cases proceeding with symptoms of circulatory insufficiency, meteorism is often observed. The latter may be the first symptom indicating impending heart failure. The high standing of the diaphragm associated with meteorism in turn adversely affects the activity of the heart and lungs. Some authors attribute the occurrence of meteorism not to heart failure, but to the direct effect of toxins on the intestine. According to data from Norris and McCrae, from 3% to 4% of cases of croupous pneumonia proceed with jaundice (so-called bilious pneumonia—pneumonia biliosa). If the jaundice is not sharply pronounced, it usually does not have serious prognostic significance. The liver in croupous pneumonia is often enlarged and sensitive to palpation. Acute swelling of the spleen can be clinically detected only in rare cases. Croupous pneumonia usually affects large areas of lung tissue. The process has a tendency to spread to entire lobes, but still, this is far from always observed. Often the process captures only part of a lobe, or along with the lesion of an entire lobe, an inflammatory consolidation of part of the adjacent lobe is observed. Statistical observations of a number of authors indicate that the right lung is affected more often than the left. Thus, on the basis of a large summary statistic by de la Camp, an isolated lesion of the right lung is observed in 52.3% of all cases, of the left lung in 33.3%, and bilateral lesions in 14.1% (pathological-anatomical statistics give a higher percentage of bilateral processes). The lower lobes are affected more often than the upper ones. The upper lobe of the left lung is particularly rarely affected. The prevalence of diseases of the right lung is explained, in addition to the lesion of its middle lobe observed in a number of cases, by the more frequent lesion of the upper right lobe in comparison with the upper left. The lower lobes of the right and left lungs are affected equally often. The febrile period of croupous pneumonia usually lasts about a week. Often, however, cases are observed, on the one hand, with a longer febrile period, and on the other hand, with an early drop in temperature. Old authors somewhat overestimated the frequency of the drop in temperature on the seventh day of the disease. Statistics covering a large number of cases show that on the seventh day the temperature drops in approximately only 1/7 of all cases, although among other days the seventh day usually occupies first place. Thus, according to the statistics of Wells, covering 3,312 cases of croupous pneumonia, a disease duration of 7 days is observed in 20.7%, 5 days in 13.6%, 8 days in 12.1%, 9 days in 9.5%, and 12 or more days in 10% of all cases. According to the statistics of Norris and Farley, covering 1,987 cases, the crisis falls on the 7th day of the disease in 17.4% of all cases, on the 8th day in 14.1%, on the 9th day in 10.2%, on the 6th day in 10%, on the 5th in 8.9%, and on the 10th day in 9.2%. These authors observed croupous pneumonia lasting more than 2 weeks in 8.7% of all cases. Cases with an abortive course lasting 4 days or less are often observed. The pathological process in these cases may not reach the stage of consolidation of lung tissue, stopping at the stage of hyperemia. On the other hand, in a number of cases, croupous pneumonia takes a protracted course—lasting 2 weeks or more. In addition to cases proceeding with complications, this is observed in so-called migrating pneumonia (pneumonia migrans), when the inflammatory process has a tendency to pass from one lobe to another and, in connection with this, the cycle of infection is prolonged.
Clinical forms with a special course. Croupous pneumonia often deviates from the usual clinical picture. The atypical course of the infection is caused by various factors. The age of the patient, his constitutional characteristics, preceding diseases and intoxications, etc., are of great importance. Along with these properties of the macroorganism, one cannot, however, ignore the role of the pathogen. The species and type of microorganism, as well as its virulence, undoubtedly also influence the course of pneumonia. In pneumonia in old age, the history often lacks any indication of a sudden onset and shaking chills. The temperature may rise only slightly during the entire disease, often remaining at subfebrile levels. In some cases, a temperature reaction is entirely absent. Stabbing pain in the side, cough, expectoration of typical sputum, and other symptoms characteristic of the usual forms of croupous pneumonia may also be poorly expressed or entirely absent. As for the findings during physical examination of the lungs, due to the superficial breathing common in these cases, associated with general adynamia, and also due to often accompanying emphysema, they are often poorly expressed. The picture of the lungs often resembles a banal bronchitis rather. A blurred, atypical clinical picture is a common phenomenon for croupous pneumonia of old age, which explains the frequent failure to recognize the disease in these cases. In old age, the sudden appearance of severe weakness, inexplicable by any definite causes, especially if it is accompanied by even a slight rise in temperature, should always raise suspicion of the possibility of an inflammatory process in the lungs. In an unclear clinical picture, the patient is often betrayed by his general appearance, especially flushing of the cheeks, a dry coated tongue, rapid breathing, participation of accessory muscles in respiratory movements, etc. The general reaction of the organism in senile pneumonia can be so weakly expressed that patients endure the infection on their feet. Death in such cases often occurs unexpectedly for those around, with symptoms of acute heart failure and pulmonary edema, and only an autopsy reveals the true nature of the disease. Asthenic and terminal pneumonia. In individuals exhausted by chronic diseases (malignant neoplasms, severe cardiopathies and nephropathies, arteriosclerosis, diabetes), pneumonia also often proceeds in the absence of a sharply expressed reaction from the organism. The course of pneumonia in cachectic patients resembles the already described senile pneumonia. The infection may proceed with a subfebrile or even normal temperature. Cough and sputum production may be completely absent. Due to superficial breathing, auscultatory findings are usually poorly expressed. The existing dullness is often attributed to hydrothorax or some old pleural adhesions. The so-called asthenic pneumonia (p. asthenica), which in some cases has a croupous character, in others a catarrhal one, is often a terminal process ending the life of the indicated chronic patients. Terminal asthenic pneumonia is often not clinically recognized and is discovered only on the autopsy table. In the clinical picture of pneumonia in alcoholics, from the very beginning of the disease, symptoms of delirium tremens often predominate. Subjective complaints and general symptoms indicating lung involvement (stabbing pain in the side, cough, etc.) are usually poorly expressed or completely absent. The same applies to the temperature reaction. A thorough physical examination of the lungs usually reveals the diagnosis. Correct recognition of these cases and the prescription of appropriate treatment (cardiaca, analeptica) is of great importance, because these patients are constantly under the threat of sudden collapse. Croupous pneumonia in alcoholics generally proceeds very severely and has a high mortality rate. Croupous pneumonia in pregnant women, especially in the last months of pregnancy, proceeds severely and has a very high mortality rate. As a rule, pneumonia causes premature labor. In cases where the pneumonic focus is located deep, in the region of the hilus (central pneumonia), the findings during physical examination indicating inflammatory consolidation of the lung tissue appear late, sometimes only at the end of the disease. The nature of the process in such cases, especially if typical sputum is absent, is often revealed only just before the crisis, when the inflammatory focus approaches the surface of the chest wall and when, in a limited area, often in the axillary region, crepitant rales, bronchial breathing, and bronchophony appear. In rare cases, the inflammatory focus remains deep the entire time, does not reach the surface, does not manifest itself during the entire disease by means of physical examination methods, and yields corresponding changes only upon X-ray examination. Cases with a very mild course, lasting 2-3 days (abortive or ephemeral pneumonia), are observed. Early symptoms may be clearly expressed, but the process does not go beyond the stage of engorgement. Some authors have even described cases of one-day pneumonia. Pneumonia in some cases has a tendency to successively move from one lobe to another (migratory pneumonia). The disease consequently usually assumes a protracted character and has a more severe course. The transition of the process to a new lobe is usually accompanied by a deterioration in the general condition and a more or less sharp rise in the temperature curve. Cases are observed where the infection ends only after the inflammatory process has gone through the greater part of the parenchyma of both lungs. Migratory pneumonia usually ends by lysis. Friedländer pneumonia. Cases of pneumonia caused by the Friedländer bacillus often have a severe course and have a high mortality rate. The often observed abundant admixture of blood in the sputum is a reflection of the destructive process in the lungs. The sputum usually contains Friedländer bacilli in large quantities. Due to the sharply expressed viscosity of the inflammatory exudate, the latter is difficult to expel from the bronchi. Obstruction of the latter often causes symptoms of so-called massive pneumonia. The picture during physical examination can thus simulate exudative pleurisy. Cases of Friedländer pneumonia often proceed with sharply expressed adynamia, cyanosis, and general septic symptoms. Complications. In the vast majority of cases of croupous pneumonia, there are anatomically inflammatory changes in the pleura in the form of clouding of its surface and deposition of fibrin. The almost constant complaint of patients of stabbing pain in the side is associated with these changes in the pleura. A reflection of this dry pleurisy during physical examination is the friction rub often detected in croupous pneumonia. This inflammatory-fibrinous process in the pleura is an almost constant phenomenon in croupous pneumonia and therefore cannot be classified as a complication. The latter usually include only exudative pleurisies — serofibrinous or purulent. A clearly expressed pleural effusion is observed in 6-8% of all cases of croupous pneumonia. In approximately half of these cases, the effusion is purulent in nature. The exudate in some cases contains pneumococci, in others — streptococci or other microorganisms. In rare cases, the exudate turns out to be sterile. Purulent exudate in some cases can be detected already at the height of the disease; more often it is revealed only in the period of resolution of the pneumonic process. These so-called parapneumonic and metapneumonic empyemas prolong the disease process and are a serious complication that worsens the prognosis. Empyemas complicating croupous pneumonia often have an encysted character, being located parietally, between the lobes, or above the diaphragm. Due to the thickness of the pus, often mixed with a large amount of fibrin, as well as the deep location of the corresponding foci (interlobar, supradiaphragmatic empyemas), even multiple trial punctures often yield a negative result. Correct recognition of these cases is of very great practical importance. Metapneumonic empyemas only in relatively rare cases end in spontaneous recovery, being absorbed or emptied through a bronchus. In the vast majority of cases, surgical intervention is required. Failure to recognize this complication, often observed after croupous pneumonia, and untimely measures to drain the purulent effusion can have fatal consequences for the patient, as protracted empyema usually causes cachexia and is often complicated by amyloidosis of the kidneys and other organs. There is also a danger of generalization of the process with transition to septicopyemia. Cases operated on in a timely manner usually have a favorable prognosis. One can refrain from surgical intervention only in those cases where the purulent exudate turns out to be sterile and the patient's general condition remains good. In these cases, resorption of the exudate is often observed with conservative treatment (see Pleurisy). Abscess and gangrene of the lung are observed as a complication in approximately 1% of all cases of croupous pneumonia.
For details, see Lung-abscess. A severe complication of croupous pneumonia, which yields a high mortality rate, is pericarditis. Anatomically, it is discovered more often than it is diagnosed clinically. The exudate may have a fibrinous, serofibrinous, or purulent character. Pneumococcal pericarditis is almost always combined with unilateral or bilateral exudative pleurisy. Clinically, this complication is recognized mainly on the basis of a pericardial friction rub. The typical configuration of the heart shadow for pericarditis usually appears indistinctly due to its fusion with the shadow of the pulmonary inflammatory infiltrate and also the very frequent in these cases unilateral or even bilateral pleural effusion. Cases with fibrinous or serofibrinous exudate may end in spontaneous recovery. In cases of purulent exudate, surgical intervention is indicated. Endocarditis as a complication of croupous pneumonia is observed not infrequently in cases ending lethally. The changes usually have the character of verrucous endocarditis, with the vegetations often reaching large sizes. In rarer cases, ulcerative endocarditis is observed with perforation of the valves, detachment of the chordae tendineae, etc. Pneumococcal endocarditis in the majority of cases affects valves already altered by a preceding sclerotic process of rheumatic or other origin. Less frequently, involvement of normal valves is observed. As a rule, inflammatory changes are limited to the valvular apparatus of the left ventricle. Only in exceptional cases is the tricuspid valve affected. The aortic valves are apparently affected more often than the bicuspid valves. This applies in particular to malignant ulcerative forms of pneumococcal endocarditis. From the inflammatory deposits of the endocardium, as a rule, the pneumococcus of the same type with which the given patient is infected is isolated. The diagnosis of endocarditis complicating croupous pneumonia usually presents great difficulties and succeeds only in rare cases. An increase in the size of the heart has a very relative significance, as it is also observed in cases of croupous pneumonia not complicated by endocarditis. The same applies to the appearance of a systolic murmur—a sound phenomenon often observed in croupous pneumonia, as well as in other infectious diseases. The recognition of this complication of croupous pneumonia is further complicated by the fact that we are usually dealing with so-called recurrent endocarditis, localized on already altered valves with corresponding auscultatory and other symptoms of a preceding valvular defect. The appearance of arrhythmia (extrasystoles, partial block) is not connected with changes on the part of the endocardium, but indicates an infectious-toxic lesion of the myocardium and its specific conduction system. Antemortem recognition of endocarditis as a complication of croupous pneumonia usually succeeds only in those cases when, during the illness, a diastolic murmur appears at the site of auscultation of the aortic valves. Its occurrence in a previously unchanged heart definitely indicates an acute lesion of the endocardium of the aortic valves.
In some cases of croupous pneumonia, already at the very beginning of the disease, phenomena of meningism are observed. The changes on the part of the meninges have a toxic character. The cerebrospinal fluid in these cases remains transparent and does not contain pneumococci. Although the phenomena of meningism, at least in adults, usually accompany severe forms of croupous pneumonia, cases of recovery are nevertheless observed not infrequently. A completely different significance has the complication of croupous pneumonia with purulent meningitis, which is usually a terminal process and one of the manifestations of general severe pneumococcal sepsis. Purulent meningitis is often combined with pneumococcal endocarditis. Lumbar puncture reveals cloudy cerebrospinal fluid containing a large number of pus corpuscles, as well as pneumococci of the same type with which the given patient is infected. Purulent meningitis represents an absolutely fatal complication. In rare cases, the process has the character of meningoencephalitis. Depending on the localization of the inflammatory focus in the cerebral substance, corresponding focal phenomena are observed, such as hemiplegia, aphasia, etc. Purulent meningitis complicating croupous pneumonia is not always diagnosed clinically, because against the background of the general severe condition, meningeal symptoms are often smoothed out. Peritonitis as a complication of croupous pneumonia is observed rarely. In some cases, it appears at the height of the disease, in others already in the period of resolution of the pneumonia; it is often combined with purulent pleurisy and pericarditis. From the pus, in some cases, the pneumococcus of the same type with which the given patient is infected is isolated, in other cases—streptococcus. Peritonitis, therefore, can be the result of a concomitant streptococcal infection. Arthritis belongs to rarely observed complications of croupous pneumonia. It usually has the character of monoarthritis and most often is localized in the knee or shoulder joints. The effusion, containing pneumococci, usually has a purulent character. Arthritis, complicating only severe forms of croupous pneumonia, usually appears not at the height of the disease, but already in the period of resolution of the process. Recovery with full restoration of the functions of the affected joints is observed not infrequently. Inflammation of the middle ear as a complication of croupous pneumonia in adults is observed relatively rarely. Otitis is often bilateral. In cases of croupous pneumonia with a protracted course, one must always keep in mind the possibility of complication by purulent otitis. The latter usually has a benign character; only in very rare cases are further complications observed (mastoiditis, sinus thrombosis, etc.). Rare complications of croupous pneumonia include thrombophlebitis and pulmonary embolisms with sudden death. True nephritis as a complication of croupous pneumonia is observed rarely, if one does not count the already mentioned febrile albuminuria. Some authors have described cases of the occurrence of lipoid nephrosis after croupous pneumonia.
Outcome. In cases of croupous pneumonia proceeding without complications and ending in recovery, the pathological process usually leaves no traces. In those cases where death from croupous pneumonia occurs at the height of the disease, it is usually caused by general intoxication and circulatory failure. In the majority of these cases, general pneumococcal sepsis is observed: besides the lungs, the pneumococcus can be detected in large quantities in the blood and various organs. In later stages of the disease, death often occurs from complications (meningitis, ulcerative endocarditis, empyema, etc.). In a number of cases, pneumonia does not resolve. Instead of the absorption of the alveolar exudate, its ingrowth with connective tissue occurs. These cases of the outcome of croupous pneumonia into carnification of the lung tissue have the most diverse clinical course. Sometimes the process takes on a malignant character, combining with lung abscesses and bronchiectasis. With the development of sclerosis, in the majority of cases, the process takes a benign course, dragging on for many years.
Diagnosis. Already at the very beginning of the disease, when local pulmonary symptoms are still absent, a number of general phenomena usually make it possible to recognize croupous pneumonia, if not with complete certainty, then with a high degree of probability. At the first glance at the patient, one's attention is drawn to the hyperemia of the cheeks, often more sharply pronounced on the side where the pneumonic process is localized. In a large part of cases, already on the first day of the disease, there is an increase in the respiratory rate that does not correspond to the rise in temperature and pulse rate, indicating lung involvement. While in infectious diseases not associated with an inflammatory process in the lungs, the ratio of the number of breaths to the number of heartbeats is usually 1:4, croupous pneumonia often gives a ratio of 1:3 or even 1:2 already at the very beginning of the disease. The increase in respiratory rate is usually associated with the participation of accessory respiratory muscles. Already in this early period, it is often possible to establish a more or less sharply pronounced neutrophilic leukocytosis in the blood, as well as a sharp decrease in chlorides in the urine—symptoms that, in the presence of the indicated general phenomena and a corresponding anamnesis (sudden onset of the disease with a shaking chill and subsequent rapid rise in temperature), make it possible to recognize croupous pneumonia with a high degree of probability. The diagnosis is revealed more definitely with the appearance of direct symptoms indicating the localization of the inflammatory process in the lungs, such as sharp pain in the side, lagging of one half of the chest during breathing, dullness of the percussion sound, crepitant and resonant moist rales, bronchial breathing, etc. Typical rusty sputum, which usually finally clarifies the nature of the disease, in some cases represents an early symptom, appearing in the period when physical examination still gives a negative result. It should, however, be borne in mind that the so-called rusty sputum is not a symptom absolutely pathognomonic for croupous pneumonia. Cardiac patients with phenomena of stasis in the lesser circulation, especially with pulmonary infarctions, as well as in rare cases, hemoptysing tuberculous patients, may produce sputum with a rusty shade typical of croupous pneumonia. Physical symptoms often appear only on the 3rd-4th day of the disease or even later. Bronchial breathing and bronchophony in croupous pneumonia are often clearly expressed not throughout the entire affected lobe, but only in certain limited areas, for example, in case of involvement of the lower lobes—in the area directly below the angle of the scapula, where more or less large bronchi approach the surface of the chest most closely. In case of involvement of the upper lobes, phenomena indicating pulmonary tissue consolidation during physical examination usually appear earlier posteriorly (fossa supraspinata) than anteriorly. Often the first pneumonic phenomena (crepitant rales, bronchial breathing, bronchophony) can be detected in the axillary fossa. In case of late appearance of pulmonary symptoms, this area should be examined especially carefully. The area between the IV and VI ribs on the right anteriorly should also be subjected to careful physical examination, since in a number of cases croupous pneumonia is observed as an isolated lesion of the middle lobe of the right lung. In that period of the disease when sharply pronounced percussion and auscultatory phenomena from the lungs are already present, in a number of cases, differential diagnostic difficulties still arise. In the case of so-called massive pneumonia, the picture during physical examination may extremely resemble exudative pleurisy. Upon percussion in these cases, dullness is often femoral, absolute. Upon auscultation, breathing may be sharply weakened, and it is not always possible to catch the bronchial shade. Bronchophony in these cases is not only not increased, as in ordinary forms of croupous pneumonia, but is often weakened in comparison with the symmetrical area on the unaffected side. The same applies to vocal fremitus. Despite the similarity of the picture with exudative pleurisy, the correct recognition of croupous pneumonia in these cases is still usually achieved without special difficulties. The often observed in these cases discharge of rusty sputum, the temporary appearance of bronchial breathing, bronchophony, especially after coughing, usually eliminate diagnostic doubts. The absence of displacement of neighboring organs also has diagnostic significance. Some authors, it is true, point out that even in massive pneumonia, in some cases, displacement of neighboring organs is observed, as well as Rauchfuss's triangle. In any case, these phenomena, in the absence of exudate, represent a rare exception. In doubtful cases, for a final clarification of the diagnosis, one has to resort to trial puncture. In differential recognition between pneumonia and pleurisy, it should be borne in mind that bronchial breathing is also often heard over a pleural effusion, especially at the border of the area of dullness (see Pleurisy). A complex picture during physical examination is often given by those cases where, along with pneumonia, there is a more or less abundant effusion into the pleural cavity. The exudate corresponds to a zone of femoral dullness and weakened breathing. Above this zone, there is usually an area with less absolute dullness, bronchial breathing, increased bronchophony, increased vocal fremitus, resonant moist and crepitant rales. It is not always easy, however, to finally resolve the question of whether the indicated phenomena are caused by pneumonia or by compression of the lung tissue by the exudate. The appearance of typical rusty sputum definitely points to pneumonia. The question of the presence of exudate in these cases, especially if there are no phenomena indicating displacement of neighboring organs, in view of the complexity of the clinical picture, is usually finally resolved only by trial puncture. Compression of lung tissue with corresponding physical phenomena simulating pneumonic consolidation can be caused not only by pleural effusion, but also by a high-standing diaphragm, pericardial effusion, etc. Compression atelectasis of the lower parts of the lungs due to high standing of the diaphragm is not rarely observed in various processes in the abdominal cavity (sharply pronounced meteorism in paretic states of the intestine, ascites, large tumors, subdiaphragmatic abscesses). Lung tissue compressed by a highly located diaphragm, in addition to dullness of the percussion sound, usually gives weakened breathing with a bronchial shade upon auscultation, as well as often atelectatic rales—phenomena that cause suspicion of pneumonia all the more because these cases, in connection...
Pneumonia
[Cases] with an underlying disease often proceed with elevated temperature. Since these cases often require surgical intervention, the decision regarding the presence of pneumonia, which sharply worsens the prognosis of the operation, can have great practical significance. The usual localization of changes in both lungs in these cases, and mainly the corresponding phenomena from the abdominal cavity, explaining the high standing of the diaphragm, speak in favor of compression atelectasis. Large pericardial effusions also often cause compression of the adjacent lung tissue, simulating pneumonia. Dullness of the percussion sound, breathing with a bronchial shade, and atelectatic rales can be detected in this case not only in the area directly adjacent to the cardiac dullness, but in cases with a large pericardial effusion, also posteriorly in the area of the scapular angle. In some cases of croupous pneumonia, irradiation of pain into the abdominal cavity is observed, which can simulate an acute abdominal disease, in particular appendicitis, and even lead to an operation. The area of McBurney's point can be not only sensitive to pressure but also show tension of the abdominal wall. Correct recognition of the nature of the disease in these cases has great practical significance. Careful examination of the patient allows one to exclude appendicitis or another acute abdominal disease. In contrast to true appendicitis, in these cases, the sensitivity of the area of McBurney's point during deep and intense pressure is less sharply expressed than during more superficial pressure. Muscle tension in this area often disappears during the inspiratory phase. Pain and sensitivity in the area of McBurney's point often disappear when the patient holds their breath. All these phenomena, unusual for appendicitis, along with symptoms indicating lung involvement, such as more rapid breathing in comparison with the pulse, lagging of one side of the chest during breathing, the presence of typical sputum, and finally the appearance of corresponding percussion and auscultatory phenomena from the lungs, usually allow for the correct recognition of these cases, preventing unnecessary and dangerous surgical intervention. Cases of so-called central pneumonia usually present diagnostic difficulties. The absence of definite symptoms from the lungs in the presence of a generally severe condition of the patient and high temperature often raises suspicion regarding typhoid, paratyphoid infection, or some septic process. For the correct recognition of these cases, the frequency of respiration and pulse is of great importance. A relative slowing of the pulse in comparison with the temperature speaks more in favor of typhoid. A sharply expressed increase in respiration speaks in favor of pneumonia. Often, the general appearance of the patient directs diagnostic thinking in a certain direction. An excited state, hyperemia of the cheeks, the appearance of herpes, and the participation of auxiliary muscles in respiratory movements speak in favor of pneumonia. A lethargic, apathetic state and pallor of the face speak in favor of typhoid fever. Enlargement of the spleen inclines the diagnosis in favor of typhoid fever or sepsis, but does not speak absolutely against pneumonia. In the latter disease, in a number of cases, especially with a severe course, it is possible to detect acute swelling of the spleen not only anatomically but also clinically. Examination of white blood cells has a certain significance. Leukopenia with relative lymphocytosis speaks in favor of typhoid fever; neutrophilic leukocytosis speaks in favor of croupous pneumonia or a septic process. A sharp decrease in chlorides in the urine also speaks in favor of croupous pneumonia. In a hospital setting, X-ray examination contributes to the clarification of the diagnosis, with the help of which it is often possible to detect a deeply located pneumonic focus. Decisive diagnostic significance in these cases can have bacteriological examination of the blood. In typhoid fever, as is known, during the first week of the disease, in a very large percentage of cases, it is possible to isolate Eberth's bacillus from the blood. Bacteriological examination often also resolves the question regarding the septic nature of the disease. Finally, the isolation of pneumococci from the blood, which is successful in no less than 20% of all cases of croupous pneumonia, decides the diagnosis in favor of this disease. An acutely beginning tuberculous exudative process, often rapidly spreading to an entire lobe, can in its course at the beginning of the disease extremely resemble croupous pneumonia, especially since these forms of so-called caseous pneumonia are usually observed in young age in persons who have not previously shown any signs of tuberculosis. Sputum at the beginning of the disease usually does not contain tubercle bacilli. The greenish tint of sputum often observed in these cases raises suspicion of tuberculosis, although it is not pathognomonic for this disease, since sputum with a greenish tint is also observed in some cases of croupous pneumonia. Percussion and auscultatory phenomena in caseous pneumonia, indicating a compact infiltrate of lung tissue, often occupying an entire lobe, especially the right upper one, extremely resemble the corresponding picture in croupous pneumonia. A protracted course of the process usually raises suspicion of tuberculosis, although the diagnosis is finally clarified only upon the appearance of tubercle bacilli in the sputum in connection with the beginning of cavernous decay. Examination of sputum for pneumococci with the determination of their type can also have differential diagnostic significance. The presence of type IV or III pneumococcus in the sputum does not speak against tuberculosis, since these varieties of pneumococcus are extremely common as saprophytes. The isolation of type I or II pneumococcus almost definitely speaks in favor of croupous pneumonia, since carriers of these types are observed extremely rarely.
Prognosis. The mortality rate from croupous pneumonia shows large fluctuations depending on the contingent of patients covered by the given statistics. Besides age, social and living factors, the simultaneous spread of other infections, especially influenza, and, as recent observations show, the type of pneumococcus with which the patient is infected, influence mortality. In adults, mortality increases with age. Age groups older than 40-50 years show a very high mortality rate. The disease of croupous pneumonia at an age older than 70 years rarely ends in recovery. The increase in mortality in connection with age (starting from the second decade of life) is shown by the following table, based on the statistics of Fränkel and Reiche.
Table 12. Age Mortality (in %) Age Mortality (in %) 11-20 5.0 61-70 63.8 21-30 7.0 71-80 86.7 31-40 24.7 41-60 39.4 The prior state of the organism sharply influences mortality. Patients with chronic diseases of the heart, kidneys, arteriosclerotics, diabetics, the obese, and alcoholics usually endure pneumonia poorly and show a high percentage of mortality. In diabetics, pneumonia often causes diabetic coma. Statistics from American authors convincingly show how much social and living factors influence mortality. Thus, in large city hospitals in the USA, where the majority of patients are recruited from low-paid groups of workers performing heavy physical labor and often abusing alcohol, mortality from lobar pneumonia is 30-50%, while among more affluent segments of the population treated at home, mortality is only 15-20%. Western European hospital statistics show a lower average mortality in comparison with America, namely 20-25%, with large fluctuations in different years.
Authors who have studied lobar pneumonia from the point of view of the pneumococcus type note a dependence between mortality and the type of pneumococcus with which the patient is infected. Thus, almost all relevant statistics note the malignant course of lobar pneumonia caused by type III pneumococcus, which yields a mortality of 40% to 70%. In terms of the severity of the course, according to the data of a number of authors, type II follows type III, yielding a mortality of up to 50%. Type I yields a lower percentage of mortality in comparison with type II. According to the data of most authors, type IV yields the lowest mortality. The indicated connection between mortality and the type of pneumococcus does not, however, have the character of an absolute regularity. Thus, an analysis of a large amount of material from the Medsantrud Hospital in Moscow presents a different picture regarding the connection of mortality with the type of pneumococcus. Only the data regarding type III coincide, which also in the Moscow series yields a high percentage of mortality (26%), exceeding the general average mortality from lobar pneumonia by 2 times. As for type II, considered by American as well as English authors to be the most malignant after type III, in the indicated Moscow series it turned out to be the most benign with a minimal mortality of 3%. In terms of the benignity of the course, type I followed type II, yielding 10% mortality. A somewhat higher percentage of lethal outcomes in the Moscow series was yielded by type IV (12%).
When evaluating statistical data indicating a connection between mortality and the type of pneumococcus, one should take into account the distribution of the corresponding cases among age groups. As observations by a number of authors show, among cases of lobar pneumonia of type III, a large percentage falls on persons of advanced age, often weakened by preceding chronic diseases. Young age is rarely affected by lobar pneumonia of type III, but endures it comparatively easily and does not yield a percentage of mortality higher in comparison with cases of lobar pneumonia caused by other types of pneumococcus.
Pneumonia
[...] with other types. The high mortality rate of croupous pneumonia of type III is explained, therefore, not so much by the malignancy of the microorganism, but by the fact that it often affects subjects weakened by chronic diseases in old age. Croupous pneumonia caused by Friedländer's bacillus, according to the observations of a number of authors, yields a very high mortality rate. In the prognostic evaluation of individual cases, the state of the cardiovascular and nervous systems is of great importance. Persistent tachycardia of over 120 beats per minute, various types of cardiac rhythm disturbances, a sharp drop in blood pressure, and a soporous and especially comatose state indicate severe intoxication and significantly worsen the prognosis. The size of the affected area has only relative significance from the point of view of prognosis. A small inflammatory focus is often accompanied by severe general toxic phenomena. Cases with involvement of a large part of the lung tissue, and especially bilateral processes, admittedly usually have a more severe course and yield a higher mortality rate. Croupous pneumonia of the upper lobes, while often accompanied by sharply pronounced phenomena from the nervous system, does not, however, contrary to popular belief, result in higher mortality. The absence of a leukocyte reaction, with the exception of cases with a very mild course, worsens the prognosis, although the presence of leukocytosis by no means indicates a benign course of the process. Blood culture is of great prognostic significance. Cases proceeding with bacteremia yield a mortality rate many times higher compared to cases with a sterile blood culture. Complications worsen the prognosis. Purulent pneumococcal meningitis and ulcerative endocarditis are absolutely fatal; empyema, pericarditis, and lung abscess significantly increase the mortality rate. Treatment. Since the pathogen of croupous pneumonia was discovered, a number of authors have made attempts to apply causal treatment. Treatment with specific antipneumococcal serum, proposed in its time by Klemperer and Romer and other authors, did not gain wide distribution. Only the establishment of the existence of varieties of pneumococcus, differing in their immuno-biological properties, revived interest in serum treatment. Avery, Cole, and other authors began for the first time to use monovalent sera for therapeutic purposes in relation to individual types of pneumococcus. Observations from the Rockefeller Institute clinic in New York, where the mentioned authors are staff members, showed that only type I antipneumococcal serum has a favorable therapeutic effect in terms of arresting the infection and reducing mortality in relation to cases of croupous pneumonia infected with this type. The effect of type II antipneumococcal serum, according to the same observations, is doubtful. As for type III, it has not yet been possible to obtain a corresponding specific serum with a high titer of antibodies. In view of the collective nature of the so-called type IV pneumococcus, serum treatment possessing type specificity is impossible until this group is split into separate biological varieties. According to the observations of the mentioned authors, the mortality rate in the treatment of cases of type I croupous pneumonia with specific antipneumococcal serum is reduced by more than 2 times. Thus, 495 cases of type I croupous pneumonia treated with serum yielded a mortality rate of 10.5%, while the usual mortality rate in New York from croupous pneumonia is 25-30%. American authors believe that the effect is obtained only with intravenous administration of serum and, moreover, in large quantities. As an initial dose, they usually prescribe 100-150 cm3 and then, until the temperature falls, they repeatedly administer 80-100 cm3 every 8 hours. The total amount of serum administered to the patient thus ranges from 250 to 500 cm3. It is recommended to dilute the serum with an equal amount of physiological NaCl solution. The intravenous injection should be performed slowly over 20-25 minutes. To prevent anaphylactic shock, it is recommended to inject small amounts (from 0.1 to 1 cm3) of the same serum under the skin an hour before the intravenous infusion; since the effect of the serum is most effective when administered early, the rapid determination of the type of pneumococcus with which the given patient is infected is of great importance. At the present time, methods have been developed that allow the type of pneumococcus to be established with certainty within a few hours. Since the administration of the indicated large quantities of serum is not entirely indifferent to the organism (serum sickness, in rare cases shock), American authors recommend using this method of treatment only after it has been definitively established that the given patient is infected with type I pneumococcus and that, consequently, a therapeutic effect can be expected. Observations from the Rockefeller Institute clinic were received in America with great enthusiasm. Serum treatment of type I croupous pneumonia has been used quite widely in America and England over the last 15 years, but it has not yet justified the great hopes placed in it. Large serial observations with corresponding control series have shown that the effect of the serum, even in relation to type I croupous pneumonia, is problematic. The effect of serum administered subcutaneously and in significantly smaller quantities compared to American doses is even more doubtful. Recently, treatment of croupous pneumonia with Felton's concentrated serum and the so-called Huntoon's antibody solution has become increasingly widespread in America. The latter is serum freed from proteins and containing corresponding pneumococcal antibodies in a very concentrated form. There are observations that Huntoon's solution acts more strongly and much more reliably than ordinary antipneumococcal serum. The advantage of this antibody solution is that it is less toxic, as it does not contain serum proteins. Causal therapy for croupous pneumonia is not exhausted by serum treatment. There have been attempts at chemotherapeutic action on the infectious agent. In this regard, the observations of Morgenroth are of particular interest, who showed that optochin possesses the property of arresting pneumococcal septicemia in white mice, which usually proceeds lethally for them. An even more reliable effect in the experiment is provided by the prophylactic administration of this preparation. Optochin was also introduced into the clinic for the treatment of croupous pneumonia. It is usually prescribed in the form of the water-insoluble preparation Optochinum basicum, in doses of 0.2, up to 6 times a day. Authors who have studied the therapeutic effect of optochin in human croupous pneumonia note that the most favorable results are obtained when it is prescribed in the first days of the disease, when it is indeed possible in some cases to arrest the infection. However, optochin has not gained wide clinical use due to its strong toxic effect. A number of cases of amaurosis have been described after treatment with optochin. Damage to the optic nerves is usually temporary, but in individual cases, permanent loss of vision has also been observed. Treatment of croupous pneumonia proposed by Aufrecht with subcutaneous or intramuscular injection of quinine has gained wide clinical use. As the observations of Kahn show, the effect of quinine is most reliable when it is prescribed in the first days of the disease. If this condition is met, it supposedly even surpasses optochin in its arresting effect on the infection. Quinine is usually administered once a day until the temperature falls, 1 cm3 intramuscularly in the following solution: Chinini mur. 0.5, Urethani 0.25, Aq. destill. 50.0. Thus, the possibilities of acting on the infectious agent are limited. The therapy used until now for croupous pneumonia is predominantly symptomatic.
Adherence to an appropriate hygienic and dietary regimen during the disease and in the convalescence period is of great importance. The room in which the patient is located must be aired frequently. In not very severe atmospheric conditions, it is advisable to keep windows open if possible. Maintaining complete rest during the disease, as well as in the initial period after the crisis, is of great importance, since every unnecessary load on the cardiovascular system can have fatal consequences for the patient in the form of an unexpectedly occurring collapse. Medical examination should be performed with appropriate caution and not dragged out for long, and one should especially avoid sudden movements on the part of the patient. Thorough care of the skin and oral cavity is of great importance. The food prescribed to patients must be nutritious and at the same time digestible. A predominantly lacto-vegetarian diet is recommended. It is advisable to limit the amount of animal proteins. As a rule, meat should not be given at all. Food should mainly consist of milk, various dairy products, porridges, mucilaginous soups, soft-boiled eggs, fruit jellies, greens in boiled and chopped form, raw juices, etc. It is also advisable to add flavoring substances such as coffee and cocoa. Special attention should be paid to ensuring that the patient consumes a sufficient amount of liquid. In addition to milk, tea, coffee, and soups, the patient should be given various drinks in cold form more often (lemonades, fruit and mineral waters), and gas should be released from carbonated drinks beforehand. In cases of severe damage to the nervous system, when the patient consumes liquids in limited quantities or does not consume them at all, it is necessary to introduce liquid into the body in the form of drip enemas (up to 1 liter of liquid over 1.5 hours 1-2 times a day) or subcutaneous infusion of a physiological NaCl solution or a 5% glucose solution 1-2 times a day in an amount of 500 cm³. It is necessary to monitor regular bowel movements. In view of the fact that patients with croupous pneumonia often do not have spontaneous bowel movements, one has to resort to enemas or mild laxatives. At one time, alcohol was widely prescribed in large doses to patients with croupous pneumonia, to which, in addition to its nutritional property, stimulating and antipyretic effects were also attributed. At the present time, such routine prescription of alcoholic beverages, and in large doses at that, is considered not only inexpedient but also harmful. This applies in particular to persons not accustomed to alcohol. Exceptions are made only for alcoholics or persons who have regularly consumed alcoholic beverages. Such patients can, and sometimes it is advisable to, be prescribed alcohol, since sudden deprivation of the poison they are accustomed to can cause so-called withdrawal symptoms with a violent reaction from the nervous and cardiovascular systems. The main danger usually threatens a patient with croupous pneumonia from the cardiovascular system. The appearance of symptoms indicating circulatory insufficiency (small, infrequent pulse, cyanosis, drop in blood pressure, sharp increase in breathing, etc.) requires rapid active therapeutic intervention. In these cases, subcutaneous injections of camphor oil are primarily indicated (depending on the patient's condition, 3-4 times a day or more often, 1-2 cm³ of a 20% solution). Some authors believe that camphor, in addition to its stimulating effect on the cardiovascular and nervous systems, possesses a specific influence on pneumonia in the form of local dilation of pulmonary vessels (Liebmann) or a bactericidal effect on pneumococci (Esser, Leo, and others). These authors recommend injections of very large doses of camphor oil (several times a day, 6-10 cm³ of a 20% solution) from the very first days of the disease, when there are still no signs of cardiac weakness. In view of the fact that circulatory insufficiency in croupous pneumonia is caused not so much by heart weakness as by vasomotor paresis of central origin, in recent times, especially great attention in the treatment of croupous pneumonia has been paid to agents that increase the tone of vasoconstrictors. These include caffeine (3-4 times a day, 0.2 g in the form of Coffeinum natro-salicylicum or Coffeinum natro-benzoicum, or in the form of subcutaneous injections of a 20% solution of the same preparations, 2-3 times a day, 1 cm³), strychnine (in the form of subcutaneous injections of a 2:1000 solution in an amount of 1-2 cm³ several times a day), and adrenaline (1/4-1/2-1 cm³ of a 1:1000 solution every 3-5 hours under the skin). During the day, these agents are usually alternated with camphor oil. The question of the effect of digitalis and its preparations in cases of circulatory insufficiency on the basis of infectious diseases, in particular croupous pneumonia, is still controversial. A number of well-known clinicians attach great importance to the "digitalization" of patients with croupous pneumonia. Since circulatory insufficiency in croupous pneumonia often occurs suddenly, without sharply expressed precursors, authors who hold the point of view of the positive effect of digitalis in infectious diseases recommend prescribing it, so to speak, for prophylactic purposes from the very first days of the disease, when signs of circulatory insufficiency are usually still absent. Foxglove, as is known, begins to exert a noticeable effect on the cardiovascular system only after some time; usually a few days after the start of administration. Prescribing foxglove preparations only upon the appearance of symptoms of cardiac weakness may thus turn out to be belated. In cases proceeding with frequent extrasystoles or partial block, digitalis should be prescribed with caution. In cases of threatening or already occurring collapse, heroic measures are indicated, such as intravenous administration of strophanthin (cautiously in case of preliminary digitalization due to the cumulative effect), subcutaneous administration of large doses of camphor oil, strychnine, caffeine, adrenaline, pituitrin, etc. Bloodletting, which was used extremely widely by old doctors in croupous pneumonia, is currently prescribed only rarely. Indications for it are considered to be sharply expressed venous congestion (cyanosis, swelling of the jugular veins, dilation of the borders of the right heart, sharply expressed shortness of breath) and, in particular, incipient pulmonary edema.
Attempting to lower the temperature in croupous pneumonia by prescribing large doses of antipyretic agents or cold baths is inexpedient, as the temperature reaction, according to modern views, represents one of the manifestations of that complex process which leads to the elimination of the infection. The most frequent complaints of patients with croupous pneumonia are pain in the side, often reaching great intensity, as well as painful coughing. Persistent, agonizing insomnia is usually associated with these phenomena. Pain in the side is often relieved by cupping, which is used extremely widely among us, much more often than abroad, as well as by mustard plasters and other so-called counter-irritants. Warming compresses also have a soothing effect on pain and coughing. Of the narcotic agents, codeine, heroin, or dionin are usually prescribed. It is often necessary to resort to morphine or pantopon, especially at night. In cases of persistent insomnia, it is advisable to combine morphine with adalin or other hypnotics. In cases of severe dyspnea and cyanosis, the inhalation of oxygen usually has a beneficial effect. At the height of the disease, it is usually not possible to influence the consistency of the sputum and its discharge from the bronchi with the help of expectorants. The prescription of expectorants is indicated when the discharge of sputum is difficult during the resolution period of pneumonia. The prophylaxis of croupous pneumonia is an extremely complex problem to which little attention has been paid until recently. From the point of view of the view that has prevailed until recently regarding croupous pneumonia as an autogenous infection, prophylaxis could be reduced only to general sanitary and hygienic measures, such as improving working conditions for persons working in unprotected premises or in the open air, who are especially predisposed, as we have seen, to contracting croupous pneumonia, improving housing conditions, combating alcoholism, and training in relation to meteorological fluctuations. Statistical data from American authors, according to which the incidence of croupous pneumonia among the proletarian population is higher in comparison with the wealthy population of better-maintained neighborhoods, indicate the great importance of improving social and living conditions. From the point of view of individual prophylaxis, the attitude toward patients suffering from acute catarrh of the upper respiratory tract is important, especially during a flu epidemic. Such patients, who are predisposed to complications of pneumonia, should be immediately released from work and placed under medical observation while observing bed rest. The range of preventive measures is significantly expanded if one adopts the modern point of view that the majority of cases of croupous pneumonia, namely those caused by pneumococci of types I and II, represent an exogenous infection spread through pneumococcus carriers. Proponents of this view, especially American authors, point to the necessity of a whole series of preventive measures for the successful fight against croupous pneumonia. Considering every patient with croupous pneumonia of types I and II to be dangerous in the sense of scattering and spreading the corresponding pathogens (it has been proven that the dust of a room in which a pneumonia patient is located usually contains a large number of virulent pneumococci of the same type with which the given patient is infected), American authors demand thorough disinfection of sputum and the isolation of such patients as much as possible, especially if it concerns dormitories, barracks, prisons, etc. Under the influence of this new doctrine on the routes of spread of pneumococcal infection, some American cities have passed a resolution on the mandatory registration of all cases of croupous pneumonia with laboratory determination of the pneumococcus type in each individual case. American authors go even further, putting forward the question of registering pneumococcus carriers of types I and II and exerting moral influence on them in the sense of avoiding close contact with others (kissing, etc.). These measures, at least at the present time, are unrealizable if only because the number of healthy carriers of types I and II is too large. Thus, in Moscow, according to an epidemiological survey, the number of healthy carriers of pneumococcus types I and II reaches 0.7% of the entire population (Ettinger, Viktorov, Mazel). As for the fight against pneumococcus carriage in each individual case in the sense of eliminating them from the oral cavity and pharynx, the corresponding possibilities are very limited. Mouthwashes and gargles with solutions of optochin or quinine sulfate in a dilution of 1:10,000, recommended by some authors, do not usually eliminate the carriage. P. Bronchopneumonia. Etiology. Bronchopneumonia is a very frequent pathological process. It joins a whole series of diseases, often being the immediate cause of death. Bronchopneumonia most often affects early childhood and old age. In adults, bronchopneumonia as a primary disease is observed infrequently. It usually joins and complicates other diseases of an infectious and other nature. In cases where bronchopneumonia joins so-called seasonal catarrhs of the respiratory tract, resp. influenza, and when the inflammatory process on the part of the lung tissue appears already at the beginning of the disease and predominates in the clinical picture, one can speak of primary bronchopneumonia. Bronchopneumonia is observed as a companion to a number of infectious diseases. It especially often complicates those infections that have a tendency to proceed with catarrh of the upper respiratory tract. Bronchopneumonia in these cases usually develops against the background of a preceding bronchitis or bronchiolitis. In adults, bronchopneumonia is most often observed in influenza, as well as in typhoid and typhus, and less often in erysipelas and cerebrospinal meningitis. In these infectious diseases, bronchopneumonia often joins already in the period when there are sharply expressed phenomena of circulatory insufficiency. In cardiac patients in the stage of decompensation, especially with congestion in the pulmonary circulation, bronchopneumonias are often observed in the lower posterior parts of the lungs. These hypostatic pneumonias are often the immediate cause of death in cardiac patients. In elderly persons confined to bed for a long time (fractures, etc.), hypostatic pneumonias often arise. Those suffering from pulmonary emphysema and chronic bronchitis, especially in old age, are predisposed to bronchopneumonia. The latter usually proceeds severely in them and often ends lethally. Bronchopneumonia is often a terminal process in persons exhausted by chronic diseases, such as malignant tumors, diabetes, nephropathies, etc. In patients with bronchiectasis, outbreaks of bronchopneumonia are often observed, caused by the entry of infected secretion from the bronchi into neighboring areas. Cases of so-called aspiration pneumonia are usually separated into a separate group. Aspiration pneumonia is especially often observed in persons with a prolonged unconscious state, e.g., in apoplectics, in uremic and diabetic coma, and in rarer cases also with severe intoxication. An increase in temperature in such persons with a deep disorder of consciousness is very often associated with the emergence of a pneumonic focus. A disorder of the innervation of the pharyngeal and laryngeal musculature often entails the entry of infected material into the bronchial tree. Death in bulbar paralysis usually occurs from aspiration pneumonia. Cancer of the larynx and esophagus, as well as surgical intervention on the upper respiratory tract, are also often complicated by aspiration pneumonia due to the entry of septic material into the bronchi. In the mechanism of at least part of the cases of postoperative pneumonia, aspiration of infected material into the bronchi during anesthesia also has significance. Aspiration pneumonia is also observed in those who have drowned. After being pulled from the water, they are often awaited by death from pneumonia. Aspiration pneumonia has a tendency to abscess formation or transition into gangrene and, in general, is distinguished by a severe course. Bronchopneumonias developing on the basis of septic emboli have a special character; they also have a tendency to abscess formation. Bronchopneumonia, with rare exceptions, is an infectious process and is associated with the entry of virulent microorganisms into the corresponding lung area. As experiment shows, strongly irritating chemical substances can cause an inflammatory process in the lungs even in the absence of microorganisms. Pneumonia after the inhalation of strongly irritating gases, smoke, or dust (so-called Thomas slag pneumonia) in the first phases of the disease represents an aseptic process. However, even in these cases, microorganisms soon enter the affected lung foci from the bronchial tree or from the lymphatic and blood vessels, contributing to the further development and spread of the inflammatory process.
In cases of bronchopneumonia, the pneumococcus does not play the predominant etiological role that it has in croupous pneumonia. Among the varieties of pneumococcus in bronchopneumonia, almost exclusively type IV is isolated from both sputum and cadaveric material. Hemolytic and non-hemolytic streptococcus, Pfeiffer's bacillus, golden and white staphylococcus, micrococcus catarrhalis, Escherichia coli, and other microorganisms have a greater etiological significance than in croupous pneumonia. In a significant percentage of cases, bronchopneumonia represents the result of a mixed infection: several of the listed microorganisms are simultaneously isolated from the inflammatory focus. Bronchopneumonia complicating infectious diseases is usually not caused by the corresponding specific pathogen, or at least not exclusively by it. Pneumococcus type IV and streptococcus also have great etiological significance in these cases.
Pathological anatomy. Bronchopneumonia, catarrhal pneumonia, represents a form of inflammation of the lung in which 1) the volume of the lesions usually lies within the limits of a lobule (hence the synonym lobular pneumonia), 2) the inflammatory process in the lung is closely connected with the lesion of the bronchial tree or is even a direct continuation of such a lesion (hence the term bronchopneumonia), 3) the exudate is distinguished by significant diversity and most often resembles various forms of catarrh (hence the synonym catarrhal pneumonia). The site of development of bronchopneumonia is most often the posterior-inferior parts of the lungs; less often the foci are located in the upper-anterior parts. Both lungs are more often affected. The affected parts are more or less dense to the touch, but it is relatively rare to speak of true hepatization. At the beginning of development, the foci can even be easily overlooked or mistaken for edema; the difference is that in the latter, the fluid flowing out under pressure, being foamy, remains completely transparent; at the beginning of bronchopneumonia, there is less foam, and the fluid itself turns out to be already slightly turbid, while the lung tissue is reddened. Around the foci, one often finds a darker zone of some atelectasis, and beyond this zone usually lies a lighter zone of emphysematously inflated parts (vicarious emphysema) [see separate table (art. 623-624), fig. 1]. With the multiplicity of foci, this alternation of dense gray-red pneumonic foci with darker atelectatic and lighter emphysematous zones makes the entire section of the organ variegated, and the anatomical diagnosis itself easy. With simultaneous widespread bronchitis, numerous atelectases often arise, especially in children, which are striking even upon superficial examination of the lung in the form of everywhere scattered lobular and larger airless fleshy areas of blue-red color, sinking from the side of the pleura. In small children, the lower and paravertebral parts of the lungs are especially predisposed to bronchopneumonia, as well as parts corresponding to the ribs; the pneumonias themselves, running along the line of the ribs, are often designated as "striped." Regarding the designations "lobular pneumonia," "bronchopneumonia," "catarrhal pneumonia," one must keep in mind the following: if bronchopneumonia is most often lobular pneumonia, then quite often the lesions are both smaller and larger in their dimensions. Thus, bronchopneumonia is often actually acinous and even miliary. On the other hand, simultaneous or sequential involvement of many lobules can give a picture of confluent bronchopneumonia, simulating lobar forms of croupous pneumonia (pseudolobar pneumonia). In confluent bronchopneumonias, we are still talking about individual foci, which, despite the contact of their boundaries, usually differ slightly from each other in color and consistency; in addition, upon the fusion of foci, one usually discovers in one place or in the same lung or in another, individual small foci with an exudate characteristic of bronchopneumonia. However, sometimes even with the help of a microscope, differentiation in relation to croupous pneumonia becomes impossible, for example, in the late periods of non-lobar forms of croupous pneumonia, when fibrin disappears; in these cases, it is necessary to take into account the entire totality of clinical data. Regarding acinous and miliary forms, it should be pointed out that from the macroscopic side, they sometimes extremely simulate tuberculous lesions (see Measles), especially in late periods, when the exudate undergoes fatty metamorphosis. As for the designation "bronchopneumonia," it should, as it were, indicate the connection and sequence of two phenomena: bronchitis and pneumonia; it is as if we are talking about an aerogenic descending bronchopulmonary process. Such a connection, however, is far from always mandatory; sometimes simultaneous and, moreover, hematogenous involvement of the bronchi and lung parenchyma is assumed as the most probable. Finally, the same term can be applied to the case where primarily arising bronchitis leads to pneumonia not by way of endobronchial spread of infection, but peribronchially along the lymphatic system: involvement of the alveolar parenchyma arises here at the end of approximately the following chain of phenomena: bronchitis, peribronchitis, interstitial pneumonia, alveolar pneumonia. Thus, the term "bronchopneumonia" by no means prejudges the question of the dynamics of the entire phenomenon and of the portal of entry of infection in particular: both the bronchitic and the pneumonic component, together and separately, can be aerogenic, hematogenous, and lymphogenous (see below). The synonym "catarrhal pneumonia" is unfortunate in that the classical idea of "catarrh" as an inflammation of the mucous membrane is not transferable to the alveolar parenchyma of the lung, which is devoid of a mucous membrane in the usual sense of the word. From the histological side, bronchopneumonias present rather variegated pictures. First of all, in contrast to croupous pneumonia, the exudate is least often fibrinous here (see Diphtheria, Influenza); in any case, it is never purely or evenly fibrinous. Usually, one observes serous, "catarrhal," purulent, ichorous, hemorrhagic, mixed exudate. In serous exudate (bronchopneumonia serosa), the picture resembles simple pulmonary edema; true, the presence of cellular elements of alveolar epithelium and leukocytes in the edematous fluid allows one to differentiate both phenomena. Sometimes alveolar epithelium sharply predominates among the cells of the exudate (so-called desquamative pneumonia), e.g., in serous pneumonia in patients with heart defects against the background of brown induration of the lungs, in gas-poisoned patients, in acute lung congestion, etc. The most banal form of exudate is purulent (more correctly, leukocytic); leukocytes by themselves or with an admixture of alveolar and bronchial epithelium fill the entire air-bearing parenchyma and the leading bronchi [see separate table (art. 633-624), fig. 5], and by pressure on such a focus, it is always possible to obtain drops of turbid grayish-green exudate. This is the form of bronchopneumonia that is usually meant when speaking of catarrhal pneumonia. It would be more correct to designate as catarrhal pneumonia only serous-desquamative forms of bronchopneumonia, and to reserve the name "purulent pneumonia" exclusively for those cases where purulent melting of the bronchopneumonic focus and the formation of an abscess occurs (abscessing bronchopneumonia). As chronic catarrhal pneumonias, it is customary to designate cases observed during prolonged edemas of the lung on the basis of circulatory disorders; when the organ or its part becomes dense on section, gelatinous and sharply edematous, and groups of fatty-degenerated alveolar epithelium float in the edematous fluid, giving the surface of the section a special yellowish mottling. Very often, bronchopneumonia turns out to be hemorrhagic; for some acute infections, this is even characteristic (influenza, plague, anthrax, partly streptococcal forms). Often, along with blood-filled parts, one finds other forms of exudate, nests with fibrin (uremia, diphtheria), leukocytes, etc.—mixed forms of bronchopneumonia, distinguished by the extreme variegation of the macroscopic pattern (see Influenza). In small children, the cellular exudate sometimes contains a significant admixture of giant cells (giant-cell pneumonia), and on the part of the small bronchi, they show a tendency to metaplasia of the epithelium—the latter sometimes over extensive extents turns into stratified squamous, and this phenomenon can take place already in the first week of the disease.
Bronchopneumonias, like lobar pneumonias, have a varied course and outcome. Usually, resolution of the process is observed: fatty metamorphosis of cells, absorption of exudate, and restoration of the status quo. In some cases, suppuration occurs, with the formation of an abscess, either single or multiple; the development of gangrenous foci is possible. In both abscess and gangrene, the picture does not differ in essence from that of lobar pneumonia. Suppurative processes sometimes become widely distributed throughout the interstitial tissue of the lung; purulent lymphangitis and purulent interstitial pneumonia arise, whereby entire lobules of the lungs may appear as if isolated (pneumonia dissecans) among the surrounding parenchyma. A special group should be distinguished: necrotizing bronchopneumonias, characterized by the rapid development of necrobiosis of the affected areas, and not only of the alveolar parenchyma, but also of the small bronchi. Classical in this regard are influenzal pneumonias of the "Spanish" type, as well as some cases of measles bronchopneumonias. Unlike ordinary gangrenous forms, there is no putrid decay here and no corresponding bacterial flora; an abundance of streptococci is usually found. Necrotic forms in the later stages of their development usually become abscess-forming. Hypostatic pneumonias arise as a rule in the posterior parts of the lungs; against a dark red background of somewhat consolidated parts, even denser pneumonic areas with a grayish tint are noted, mostly gently contoured. Developing primarily at the end of hopeless cases of various diseases, when patients lie almost motionless for days on their backs, hypostatic pneumonias represent, in essence, one of the specific manifestations of terminal or pre-agonal pathology. Aspiration pneumonias arise mainly also in the posterior-lower regions of the lungs. There are indications, however, that with forced aspirations, foci develop mainly in the upper, and with quiet and weakened breathing, in the lower parts of the lungs. Aspiration bronchopneumonias are characterized by a tendency toward purulent-ichorous and gangrenous decay of the foci (putrid odor). The foci themselves have various shades of gray, appearing either dryish and granular (fibrinous exudate) or soft or smeary and disintegrating. Under the microscope, the picture is one of mixed exudate with an abundance of all kinds of microorganisms and foci of gangrene at the site of their location. In the lumens of the supplying bronchi, pieces of aspirated masses are usually found, e.g., food particles, dental prostheses. Aspiration pneumonias in newborns and stillborns (during intrauterine respiratory movements) are characterized by the presence in the bronchi and lung parenchyma of various parts of amniotic fluid, such as: vernix caseosa, squamous epithelium, lanugo hairs, meconial bodies; these substances can also be detected in smears from the lungs. Atelectatic pneumonias usually arise already in the presence of inflammatory processes along the bronchial tree. Unlike ordinary bronchopneumonias, here at first a collapse of one or another part of the lung occurs, and later the collapsed area is infiltrated with exudate. It is incorrect to think that every atelectasis gives rise to bronchopneumonia. Many of the atelectatic areas (especially in newborns and children) do not undergo such a transformation but acquire the usual properties of lung parenchyma. Sometimes atelectases undergo sclerotic changes, turning into indurative fields. Pathogenesis. The mechanisms of the development of bronchopneumonia have not been sufficiently studied. It is only certain that they are not identical, and this fundamentally distinguishes bronchopneumonia from lobar pneumonia. The most widespread view of bronchopneumonia is as an aerogenic-bronchogenic descending process. Here, consequently, both the portal of entry of the infection and the initial changes, as well as the method of spread, proceed along the air-conducting channels deep into the lung. However, the hematogenic mechanism is no less frequent. In its favor, first of all, are the a priori possibilities, since the lungs are an organ standing primarily in the path of all venous blood, by virtue of which the most varied bacteremias of different origins can find reflection here in the form of focal inflammatory processes. The hematogenic nature is supported by the simultaneous and rapid development of multiple foci in various parts of the lungs, in particular miliary-pneumonic foci, as well as those bronchopneumonias in which the process plays out peribronchially and interstitially. In many cases, the question of the mechanism of development of bronchopneumonia does not find a sufficiently convincing resolution. In particular, even in those seemingly banal cases where the bronchogenic nature of the process is obvious, a hematogenic or mixed mechanism of origin may be assumed. For example, by damaging the blood-air barrier, the hematogenic infection as such may quickly lose its significance, but following this damage to the barrier, the stimulus for development is often received precisely by an aerogenic (nonspecific) infection. It is very likely that such a mixed mechanism is even the primary one for bronchopneumonias arising in the course of acute infections and intoxications, which are so often accompanied by a disturbance of the barrier functions of various organs. Undoubtedly, a number of incidental circumstances, such as disorders of respiration and intrapulmonary circulation, are of great importance for the occurrence of bronchopneumonias. These factors include poor ventilation of the lungs during weak respiratory excursions in severely ill patients, disorders of the coordination of the respiratory movements themselves of a central and peripheral nature, weakening of expiratory, in particular cough, movements, which hinders the clearing of the bronchial tree of secretions and aspirated masses, the development of atelectases, and finally, the general immobility of patients, the occurrence in them of hypostatic phenomena, pulmonary edema, etc. All these very numerous prerequisites, observed in various combinations, explain the enormous frequency of bronchopneumonias in general. On the other hand, the same prerequisites also reveal the difference between bronchopneumonias and lobar pneumonia, for the development of which a state of relative health is rather characteristic; the disease itself arises here unexpectedly, not to mention the fact that in clinical-anatomical terms it is expressed quite vividly. Vivid bronchopneumonias arising in the midst of complete health are almost always an equivalent of lobar pneumonia. Cases of bronchopneumonia on a hypostatic basis are designated as hypostatic pneumonias, on the basis of aspiration as aspiration pneumonias, and on the basis of atelectasis as atelectatic pneumonias.
I. Davydovsky. Clinical picture. The variegated nature of the anatomical process corresponds to the diversity of the clinical symptomatology. Bronchopneumonia, strictly speaking, is not a single disease with a typical clinical picture, but rather represents a collective concept, uniting a number of pathological processes of different etiology and different pathogenetic character. Since bronchopneumonia in adults in most cases does not represent a primary pathological process, but is added to preceding diseases, the onset of the pneumonic process in these cases is usually not marked by as violent a reaction as in lobar pneumonia. In those cases where bronchopneumonia is added to infectious diseases, the emergence of an inflammatory process in the lungs usually still manifests itself by a deterioration of the general condition, a new rise in temperature, the appearance or intensification of a cough, increased respiratory rate, the appearance of cyanosis, etc. The temperature curve in bronchopneumonia, depending on the underlying disease, individual reaction, and also likely the type of pathogen, is distinguished by great variety. A continuous type of fever is rarely observed. Remittent or intermittent fever predominates. In those cases where bronchopneumonia is added to infectious diseases, the temperature curve characteristic of the latter undergoes more or less sharp changes. In old age, as well as in cachectic patients, bronchopneumonia often proceeds with a subfebrile temperature or even with a complete absence of temperature reaction. In some cases, an increase in temperature can be detected only by rectal measurement. Sputum in bronchopneumonia usually has a mucopurulent or purulent character, differing little from the sputum in bronchitis. Often, an admixture of blood in the form of individual streaks can be found in the sputum. In relatively rare cases, the sputum has a rusty hue. Herpes is observed less frequently than in lobar pneumonia. A stabbing pain in the side, which is an almost constant symptom in lobar pneumonia, is relatively rarely observed in cases of bronchopneumonia. Depending on the preceding state of the organism, the nature of the underlying disease, and also to a certain extent on the size of the pneumonic focus, different degrees of involvement of the cardiovascular and nervous systems are observed. Phenomena upon physical examination provide an extremely variegated picture depending on the location, number, and size of the pneumonic foci. Centrally located foci or even foci localized on the surface, if they are small in size, usually do not give noticeable changes in the percussion sound. Bronchopneumonic foci are usually detected earlier by auscultation than by percussion. Over the consolidated areas in a limited place, resonant moist, as well as subcrepitant and crepitant rales appear. Changes in respiratory noise (vesiculobronchial, bronchial breathing), as well as an increase in bronchophony, are observed only over pneumonic foci that have already reached certain sizes. Along with this, areas are observed where breathing is sharply weakened or completely absent (atelectasis). Clear dullness of the percussion sound is given only by compact foci of consolidation of relatively large sizes. In those cases where the bronchopneumonic process becomes more widespread, acquiring a pseudolobar character, physical methods of examination provide a picture analogous to the picture in lobar pneumonia. Along with phenomena indicating pneumonic foci, scattered dry and moist rales are often observed in one or both lungs in bronchopneumonia as a manifestation of concomitant bronchitis or bronchiolitis. Bronchopneumonia is usually localized in the lower lobes. The process is often bilateral. Grippal bronchopneumonia often affects the upper lobes. It is extremely difficult to say anything definite about the duration of bronchopneumonia in adults, given that one is usually dealing with a secondary disease. Bronchopneumonia in these cases often represents an inseparable part of the underlying affliction, as a result of which it is not always possible to establish the beginning and end of the inflammatory process in the lungs. In those cases where bronchopneumonia is added to a grippal infection or to so-called seasonal catarrhs of the upper respiratory tract and clinically has the character of a primary disease, the inflammatory process in the lungs usually lasts from 1 to 3 weeks. Often, however, 4–6 weeks or more pass before the liquidation of the pneumonia. Such a protracted, subacute course is especially often observed in old age, as well as in cases proceeding with complications. The first place among complications is occupied by dry and exudative pleurisies. The effusion may have a serous, serofibrinous, or purulent character. Empyemas, as in lobar pneumonia, are often encapsulated or located between the lobes (interlobitis). Complications with abscess or gangrene of the lung are observed more often than in lobar pneumonia. Aspiration, as well as grippal and septic forms of bronchopneumonia, are especially predisposed to abscess formation. As rarer complications, pericarditis, purulent otitis, and meningitis are observed. In a number of cases, the outcome of the inflammatory process is carnification of the lung tissue, which in turn is often complicated by bronchiectasis. Diagnosis. Foci of small size, especially those located deeply, often do not lend themselves to recognition at all with the help of physical methods of examination. In emphysematous patients, even larger pneumonic foci often do not provide definite percussion and auscultatory data. In cachectic patients and in severe cardiac patients, the recognition of bronchopneumonic foci, in view of frequent and superficial breathing, as well as the presence in a number of cases of congestive bronchitis, which blurs the clinical picture, often presents great difficulties. In infectious diseases, which are often complicated by bronchopneumonia, it is necessary to carefully examine the lungs at each examination of the patient. The first sign upon physical examination (often remaining the only one), indicating an inflammatory focus in the lung tissue, is usually resonant moist and subcrepitant rales, heard in a limited area and persistently holding. Atelectatic rales, often heard in severe patients in the lower posterior parts of the lungs, are usually not persistent and disappear after several deep respiratory movements. Dullness of the percussion sound, a change in respiratory noise, with its approach to a bronchial timbre, and an increase in bronchophony appear far from in all cases of bronchopneumonia, but are observed only in cases of inflammatory pulmonary foci located close to the surface and reaching more or less large sizes. In persons of old age, cachectic patients, and severe cardiac patients, a deterioration of the general condition, the appearance of dyspnea, cyanosis, an increase in pulse rate, and especially respiratory rate, are always suspicious for pneumonia, even if there is no temperature reaction. In cardiac patients, a differential diagnosis between bronchopneumonia and infarction and atelectasis of the lung often presents difficulties, especially since an inflammatory process of the lung tissue is often added to the latter. An abundant amount of blood in the sputum and suddenly appearing pain in the side speak for infarction. Distinguishing bronchopneumonia from lobar pneumonia in most cases does not present difficulties. The nature of the onset of the disease has only relative significance: in so-called primary bronchopneumonia, a sudden onset is often noted, while lobar pneumonia in a number of cases arises without a sharp onset against the background of a preceding catarrh of the respiratory tract. Typical rusty sputum, sharply expressed leukocytosis, a decrease in NaCl in the urine, sharply expressed stabbing pain in the side, and a critical drop in temperature speak for lobar pneumonia. Upon physical examination, the presence of a compact infiltrate coinciding with the boundaries of the corresponding pulmonary lobe is characteristic of lobar pneumonia. In bronchopneumonia, the consolidation of lung tissue usually has a focal, variegated character; the foci are often localized in both lungs. In a number of cases, however, when the bronchopneumonic process has a confluent pseudolobar character, the picture upon physical examination can be completely analogous to that in lobar pneumonia. It is not possible in a number of cases to distinguish such pseudolobar forms of bronchopneumonia from lobar pneumonia during life, especially since transitional forms are also observed anatomically. The determination of the type of pneumococcus isolated from the sputum has greater differential diagnostic significance. As observations by a number of authors show, pneumococci of type I and II cause almost exclusively lobar pneumonia. In the case of a protracted course of the process, it is necessary to exclude tuberculosis. Involvement of the upper lobes only partially speaks for tuberculosis, since grippal bronchopneumonia is also often localized in these sections. In doubtful cases, X-ray examination often has decisive significance.
In a number of cases, the diagnosis is finally revealed only after repeated examinations of sputum for Koch's bacilli. In cases with a protracted course, it is also necessary to exclude actinomycosis (examination of sputum for drusen). Prognosis is closely linked to the underlying disease and also depends on the patient's previous general condition, especially their cardiovascular system; bronchopneumonia proceeds particularly severely and yields a high mortality rate in old age. Its addition to an infectious disease usually worsens the prognosis of the underlying disease. In severe cachectic states, bronchopneumonia is often a terminal disease. Treatment. Bronchopneumonia in those cases where it is a complication of a preceding disease is closely linked to the treatment of the latter. Symptomatic treatment of bronchopneumonia basically coincides with the treatment of croupous pneumonia. In cases with a protracted course, special attention should be paid to the patient's nutrition. The diet should be light but quite sufficient. It is necessary to take care of regular bowel movements. Great importance is attached to the observance of general hygienic conditions (ventilation of the room, care of the oral cavity, skin, etc.), especially in those cases where bronchopneumonia affects subjects exhausted by preceding severe diseases. In cases where there are pronounced bronchitic phenomena, the prescription of expectorants (Ipecac, Senega, etc.) is indicated. Upon the appearance of cardiac weakness, the prescription of cardiaca and analeptica (camphor, caffeine, strychnine, digitalis preparations, etc.) is necessary. For persistent, painful cough and insomnia, the prescription of narcotics and hypnotics (heroin, morphine, pantopon, adalin, luminal, veronal, etc.) is indicated. In cases taking a protracted course, some authors recommend radiotherapy. Prophylaxis. Patients with grippe, or acute catarrh of the respiratory tract, predisposed to complication by bronchopneumonia, should, upon the appearance of the first painful phenomena, be immediately released from work and placed under medical supervision while observing bed rest. In those infectious diseases which are often complicated by bronchopneumonia, it is necessary to ensure that the patient changes their position frequently. Prolonged lying on the back can lead to hypostasis and the subsequent development of pneumonia. In elderly persons confined to bed for a long time (fractures, etc.), it is necessary4 to monitor cardiac activity, as well as frequent changes of position to avoid the development of hypostatic pneumonia.
Pneumonia in children. Pneumonia in children presents many peculiarities compared to pneumonia in adults, especially regarding clinical presentation, prophylaxis, and treatment. The peculiar character of pneumonia is conditioned by the anatomical and physiological peculiarities of the respiratory organs in children, immuno-biological peculiarities, living conditions, and possibly other factors not yet sufficiently known to us. The younger the age of the child, the more differences pneumonia presents. In terms of frequency and dangerous character, this disease occupies one of the first places in the pathology of childhood, especially in infancy. According to American statistics (Sydenstricker), respiratory organs account for more than half of all diseases in early childhood. As is known, among the causes of high mortality in infants, congenital weakness stands in first place, disorders of digestion and nutrition in second, and pneumonia in third. Thanks to the successes of dietotherapy and widely deployed prophylaxis, mortality from disorders of digestion and nutrition has recently decreased sharply, which cannot be said of pneumonia. The maximum of child mortality, which falls in the winter months and depends on pneumonia, currently stands even higher than the maximum which falls in the summer months and is caused by summer diarrheas. Therefore, the problem of pneumonia in children and measures to combat this disease is currently one of the most urgent in the pathology of childhood. There is not yet a satisfactory and universally accepted classification of childhood pneumonia. For practical purposes, it is most expedient to divide them, as with pneumonia in adults, into two large groups: 1) lobar and 2) catarrhal pneumonia. In relation to each of these two forms, it is necessary to distinguish, firstly, pneumonia in infants and young children, and secondly, pneumonia in older children. Lobar pneumonia in typical cases, as in adults, begins suddenly, rapidly, affects an entire lobe with the formation of fibrinous exudate in the pulmonary alveoli, proceeds cyclically in 5-9 days, and ends with a crisis. In children, deviations from the typical course are observed much more often. The influence of age is manifested primarily in the frequency of this type. In infancy, especially up to 6 months, lobar pneumonia is observed extremely rarely. According to Lauche, the earliest reliably established case of lobar pneumonia relates to a 5-month-old child. According to Holt's statistics (500 cases of lobar pneumonia in children), 15% fall in the 1st year, 62% from 2 to 6 years, 21% from 7 to 11 years; starting from 9 years, the frequency of lobar pneumonia is approximately the same across all ages. According to data from the infant ward of the Children's Clinic of the 1st Moscow Medical Institute (150 cases of pneumonia), lobar pneumonia was not encountered a single time in children under 1 year of age, and in 5 cases from 1 to 2 years (Dombrovskaya). True, cases of lobar pneumonia have been described in newborns, but the mothers of all these children were ill with lobar pneumonia during childbirth (Lauche). Some pediatricians (Engel), on the basis of X-ray studies, believe that lobar pneumonia in infancy occurs more often than is commonly thought, but remains unrecognized. In any case, it is undoubtedly established that in infancy, lobar pneumonia is rare; at this age, pneumonia proceeds in the form of lobular pneumonia; after 2 years, the frequency of lobar pneumonia increases sharply. What explains this fact is not exactly known. Many modern pathologists and pediatricians (Beitzke, Aschoff, Loeschke, Heim, Engel, and others) incline toward the view which regards lobar pneumonia as an allergic inflammation, as an inflammation in an organism which has been sensitized by repeated infections with the pneumococcus and responds to a new infection with the same microbe with an extremely strong reaction (see Hyperergy). Objections to the anaphylactic theory of lobar pneumonia are raised by pointing out that in infancy, during repeated infections with the pneumococcus, lobular pneumonia still usually develops. But one must not lose sight of the fact that in a different organism, the production of anaphylactic antibodies generally proceeds very slowly. The question requires further research in any case. Etiology and pathogenesis—see above. There is a certain regularity in the localization of pneumonia. In infancy and early childhood, the right upper lobe is most often affected, followed by the left lower, right lower, and very rarely the left upper lobe. In older children, the lower lobes are almost on a par with the right upper in frequency; the left upper is also affected extremely rarely at this age (Engel, Feer). According to the data of American authors (Holt), the most frequent is the involvement of the right lower, then the left lower and right upper; the left upper is in last place. The reason for such localization lies in the topography of the lymph glands: the glands of the right upper and lower lobes extend deeply into the lung tissue, the glands of the left upper lobe lie outside the lung (Lauche, Engel). Furthermore, it seems that insufficient ventilation of the lower lobes and the right upper lobe due to weaker respiratory excursions of these parts of the lung is of significance. Clinical picture. The onset is sudden, amidst complete health, less often after preliminary catarrhal phenomena from the upper respiratory tract. Unlike pneumonia in adults, cardinal symptoms are very often absent: chills, stabbing pain in the chest, rusty sputum. In older children, there is sometimes a slight shivering, and instead of chills, repeated vomiting is often observed. Children do not know how to localize their painful sensations, and during an inflammatory process in the chest cavity, they often complain of pain not in the chest, but in the abdomen. In lobar pneumonia, a complaint of pain in the middle, sometimes (in inflammation of the right lung) in the right half of the abdomen, is common, which gives rise to an erroneous diagnosis of appendicitis. Children generally do not cough up sputum, especially since in the first days of the disease the cough is negligible, and sometimes absent altogether; rusty sputum can be obtained in rare cases in older children with the help of a cotton swab. The temperature in the first days is 39.5-40°, in typical cases of a constant type. The general condition is severe; lack of appetite, delirious phenomena. Especially noteworthy is the change in breathing: it is frequent, 40-60-80 per minute, the ratio of pulse to respiration decreases from 4-4.5:1 to 2-3:1; breathing is superficial, moaning, with an accent on exhalation; the participation of auxiliary muscles and flaring of the nostrils are noticeable. Upon examination of the chest, it is possible to notice the lagging of the affected half; older children prefer to lie on the affected side. These symptoms, in connection with high, constant-type fever, are very characteristic of the initial stage of lobar pneumonia in children. By percussion and auscultation during the first days, it is often impossible to detect anything pathological or only extremely insignificant changes: a tympanic or dull-tympanic sound, weakened or not so sharply expressed puerile breathing; crepitant rales during superficial breathing in children are rarely detected. Only after 3, and sometimes even 5 days, do the changes usual for lobar pneumonia appear: first of all, bronchophony, bronchial breathing, and then clearly expressed dullness. To avoid errors, it is necessary to perform percussion and auscultation with the precautions usual for childhood: quiet percussion, correct sitting position, calm state, since crying during superficial breathing hinders not only percussion but also auscultation of the child. When auscultating, special attention should be paid to the axillary regions and interscapular spaces: bronchial breathing appears here earlier than in other places. Fremitus pectoralis, even in older children, is not often obtained. At the height of the disease (3rd-7th day), the temperature rises to 40° and higher, nervous phenomena intensify (delirium, unconscious state); herpes labialis, constipation, less often diarrhea (in small children), protein in the urine are often observed; in the blood—hyperleukocytosis (up to 30,000), neutrophilia, shift to the left. The crisis usually occurs around the 7th-11th day, sometimes the 9th or 11th day, and it falls extremely rapidly; strong sweating is observed in older children, but not to the same extent as in adults; collapse also usually does not occur. Resolution of the inflammatory focus occurs with the usual phenomena (crepitation, rales, gradual disappearance of dullness and bronchial breathing); the entire recovery period proceeds very quickly. The usual outcome is complete resolution; in exceptionally rare cases—fibrosis of the lung, abscess, or gangrene. Abnormal forms of lobar pneumonia in children are generally the same as in adults, namely: abortive pneumonia, protracted pneumonia, creeping pneumonia, massive pneumonia (see Tranche disease), central pneumonia (see above), and in addition, cerebral pneumonia, in which three forms can be distinguished: convulsive, typhoid, and meningoid. The meningoid form is encountered more often: vomiting, clouded consciousness, stiffness of the neck, Kernig's and Brudzinski's symptoms. The cerebrospinal fluid is transparent, pressure is increased, the amount of protein may be increased.
The Pandy reaction is positive, the number of formed elements is normal or there is slight pleocytosis; the pneumococcus is absent. The essence of the process boils down either to a weakly expressed toxic change in the substance of the brain and meninges (meningism) or to serous meningitis. Complications in children are observed more often than in adults. Most often, purulent otitis is noted, especially in young children, and pleurisy—fibrinous, serous, and purulent. On the part of the heart—functional disorders (slowed pulse, arrhythmia in the recovery period), rarely pericarditis. On the part of the genitourinary system, pyelitis is distinguished, more rarely hemorrhagic nephritis. On the part of the nervous system—serous meningitis (see above), as well as purulent (pneumococcus in the exudate). In young children, sometimes epiphyseal osteomyelitis occurs, and the matter by no means always leads to suppuration. Complications prolong the course of the disease and worsen the prognosis. The prognosis is more favorable than in adults. The general mortality for all periods of childhood does not exceed 1-5% according to the statistics of various authors. In young children under 2 years of age, in view of their tendency to purulent complications, the prognosis is more serious; mortality reaches 11% (Comby). The main reason for the milder course is the efficiency and endurance of the child's heart. American authors associate the mildness of the course in children with the fact that predominantly type IV pneumococci, which are little pathogenic, are identified in them. The diagnosis is simple in typical cases, with a well-expressed local process in the lungs, but it presents great difficulties in the initial stage, as well as in central pneumonia, when physical examination does not yield definite data. Practically, it is important to differentiate it from typhoid fever and cerebrospinal meningitis. A stormy onset, vomiting, constant temperature, early appearing cough and shortness of breath, and herpes labialis speak for pneumonia and against typhoid. The meningeal form is not easy to distinguish from meningitis; repeated convulsions and sharply expressed and persistently holding meningeal symptoms require the performance of a lumbar puncture. X-ray examination can be of great service for recognition, especially in the initial stage and in central pneumonia. For prophylaxis, see below lobular pneumonia.
Treatment. In typical cases, with the involvement of one lobe, if there are no complications, the disease as a rule ends successfully and does not require energetic intervention. Treatment boils down to placing the organism in the most favorable conditions under which it could cope with the disease itself, i.e., to proper care and hygienic-dietary measures, which are generally applied in infectious diseases in children. In the first place is clean, fresh air (ventilation), abundant frequent drinking; food, sufficient in caloric terms and rich in vitamins, should be given in a convenient, easily digestible form, in small quantities, but more often (cream, broth, egg yolks, fruit jelly, gelatin, fruit and vegetable juices, purees, etc.). Otherwise, the treatment is symptomatic. With a very high temperature—cold to the head, sponging, lukewarm baths; antipyretics are not used. With a frequent painful cough—dry heat to the chest, mustard plasters, or a warming compress; in most cases, one can do without a compress, which in young children only constricts breathing; in older children—codeine, cupping. In case of shortness of breath, cyanosis—oxygen. In case of severe nervous phenomena—bromide preparations, Luminal, baths. Against weakness of cardiac activity—codeine and especially camphor in sufficient doses (3), Digalen, glucose, but in children, threatening collapse is observed rarely, and one does not have to resort to the energetic use of cardiac agents as often as in adults. Lobular (lobular) catarrhal pneumonia, or bronchopneumonia, is most often observed in infancy and early childhood; in older children, it is encountered significantly less often. According to Holt's statistics, out of 426 cases of lobular pneumonia, 222 cases fall on the 1st year, 142 on the 2nd year, 46 on the 3rd year, 10 on the 4th year, and 4 cases on the 5th year. The frequency of pneumonia in infants is explained primarily by the anatomical-physiological features of the respiratory organs, which place the breathing of such children in more unfavorable conditions compared to older age. These features are as follows: almost horizontal position of the ribs, high standing of the diaphragm, weakness of the musculature in general, of the respiratory muscles in particular, weak development of the elastic tissue of the lung, narrowness and shortness of the respiratory tract. As a result—limitation of the respiratory excursions of the chest; weak ventilation of the lungs, a tendency to atelectasis and circulatory disorders, rapid spread of the inflammatory process from the upper sections of the respiratory tract to the lower ones. Unfavorable conditions are further worsened due to the lying position of the child, the frequency of digestive and nutritional disorders, rickets, constitutional anomalies, etc. The absence or weak development of the tonsils and the lymphatic ring in the nasopharynx apparently contributes to the penetration of microbes into the deep sections of the respiratory tract (Meyer). Why in early age pneumonia usually proceeds in a lobular, and not in a lobar form—see above. Primary and secondary catarrhal pneumonias are distinguished, but there is no identical understanding of these names. By primary, one should understand pneumonias that arise as if independently, without preceding diseases. Such pneumonias are encountered very rarely, and some pathologists (Nikolaev) deny their existence altogether, recognizing all lobular pneumonias in children as secondary; indeed, in young children, it is very easy to overlook, for example, an influenza infection in the form of a poorly expressed nasopharyngitis. Secondary pneumonias develop during or after some disease of an infectious or non-infectious nature. Of the infectious diseases, lobular pneumonia is often complicated by those that are accompanied by catarrhs of the respiratory tract—measles, whooping cough, but most often these pneumonias are observed with influenza. To infectious diseases without catarrh of the respiratory tract (typhoid, dysentery, sepsis, etc.), they join much less often. Of the diseases of a non-infectious nature in infants, lobular pneumonia is extremely often added to nutritional disorders; in view of the peculiarities of localization and the mechanism of origin, such pneumonias are called paravertebral or distelectatic. Some authors (Meyer, Nassau, Sadykova, and Lokhov) classify influenza pneumonias as primary, and consider pneumonias with nutritional disorders and with all other infections as secondary, but one cannot agree with such an understanding. Finally, a special position is occupied by aspiration pneumonias.
Etiology. In lobular pneumonia, various microbes are found, either in pure culture or in combination with each other. It is not easy to establish the etiological role of one or another microbe in each individual case. Thus, in diphtheria patients, the pneumococcus and the Loeffler bacillus are usually found. The latter, in some cases, can alone cause inflammation of the lung (true diphtheritic pneumonia according to Loschke); more often, however, Bacillus diphtheriae, by damaging the vessels and lung tissue with its toxins, merely prepares the ground for the pneumococcus. According to Netter, in lobular pneumonia in children, the pneumococcus was found in 40%, streptococcus in 32%, staphylococcus in 20%, and pneumobacillus in 8%. Belikov, Ginzburg, and Dombrovskaya, when examining 87 cases of pneumonia in infants, isolated the pneumococcus in 44 cases (47%), streptococcus in 22 cases (25%), Friedländer's bacillus in 4 cases (3%), and in the remaining 20 cases, influenza bacilli, catarrhal micrococcus, staphylococcus, etc., were isolated. As for the pneumococcus, type IV is encountered more often in children (Adam et al.). Thus, Wollstein and Benson found type I in 8%, II in 20%, III in 12%, and IV in 60%. Belikov, Ginzburg, and Dombrovskaya, out of 25 cases of pneumonia in infants, found type I in 4 cases, type II in 3 cases, type III in 2, and type IV in 16 cases. Establishing a connection between the severity of pneumonia and the type of pneumococcus has not been successful according to their studies (see Pneumococcus). Of great interest for evaluating the etiological role of the pneumococcus are skin reactions with pneumococcal vaccine. Belikov, Ginzburg, and Dombrovskaya in the Children's Clinic of the 1st Moscow Medical Institute obtained the following results: 30 infants suffering from pneumonia, in whom pneumococcus was isolated from the sputum, gave a negative result in 25 cases (87%); 9 children, in whom streptococcus predominated in the sputum, gave a positive result in 8 cases; in 30 children who were in the clinic for other diseases (dyspepsia, meningitis, etc.), the reaction proved positive in all of them. Approximately the same results were obtained by Gutfeld and Nassau. The authors consider the reaction specific and believe that it can also be used for diagnostic purposes. However, the reaction needs further study, and it is still premature to draw final conclusions. Since the most frequent microbes of lobular pneumonia—pneumococcus and streptococcus—are often found in the throat of a child as saprophytes, it is obvious that for the onset of pneumonia, conditions are necessary which either increase the pathogenicity of the microbe or weaken the immunity of the organism. These conditions are partly of an exogenous and partly of an endogenous nature; they have been studied very little. The most important of them are the following: 1) the time of year and meteorological conditions; pneumonias in infants—in the vast majority of influenza origin—are most often encountered in early spring (March-April) and autumn; 2) social and living conditions: overcrowding, poor housing and sanitary conditions, lack of light and air contribute to the development of pneumonias and worsen their course; 3) in the same way, everything that weakens the organism and leads to metabolic disorders and a decrease in immunity acts: prolonged illness, digestive and nutritional disorders, rickets, constitutional anomalies, etc. The clinical picture—symptoms, course, outcome—is extremely varied depending on the age of the child, their constitution, and external living conditions, as well as depending on the underlying disease to which the lobular pneumonia is added. One should distinguish first of all lobular pneumonia in older children—from 2 to 12 years old—and pneumonia in children under 2 years old. Lobular pneumonia in older children is usually observed during infectious diseases which are accompanied by catarrh of the respiratory tract, during measles, whooping cough, and most often during influenza. In these diseases, pneumonia sometimes proceeds according to the lobar or pseudolobar type, but in the vast majority of cases, it has a lobular character. Pneumonia during influenza begins either suddenly or little by little, gradually. The temperature rises to 38-39°; if the child was already feverish, the fever intensifies. The temperature is not of a constant type, but irregular—sometimes remittent, sometimes intermittent. A change in breathing is striking: it becomes more frequent, dyspnea appears, flaring of the nostrils, an accent on exhalation. The cough intensifies, sometimes appears in attacks, and becomes whooping-cough-like (enlargement of bronchial glands?). Upon auscultation, rales, which were previously purely catarrhal and scattered, now concentrate in one place or another, most often in the posterior-lower sections, and become more resonant, but upon percussion, nothing except perhaps a slight tympanic shade can be detected. As small foci merge into larger ones, bronchophony, bronchial breathing, and dullness appear, either in a limited area or over a more extensive space (pseudolobar form). The course is different. In some cases, the general condition is slightly disturbed, the temperature is not high, and the duration is indefinite: after 5-10 days, and sometimes only after 2-4 weeks, all symptoms disappear; the temperature always falls lytically. In other cases, in weakened children, with constitutional anomalies and nutritional disorders (rickets, spasmophilia, etc.), under poor social and living conditions, and perhaps depending on other factors unknown to us, the disease takes a severe course: lack of appetite, sometimes vomiting and diarrhea, sharply pronounced dyspnea, cyanosis, weakening of cardiac activity, sometimes convulsions. The prognosis is very serious. Finally, in some cases, purulent complications are added—purulent otitis, pyelitis, purulent pleurisy, etc., which greatly reduce the chances of recovery. Pneumonia during measles sometimes appears in the rash period, even in the prodromal period, and sometimes in the recovery period. In the first case, the prognosis is significantly worse. During whooping cough, pneumonia develops most often in the convulsive period; with the onset of pneumonia, the typical whooping cough weakens and even disappears, the temperature rises, and dyspnea appears; in measles and whooping cough, the development of interstitial processes (meso-peribronchitis according to M. A. Skvortsov) is very characteristic, in connection with which bronchiectasis often develops after them, and sometimes carnification of the lung. Diphtheritic pneumonia is very often observed in croup patients, especially in those operated on; in view of laryngeal stenosis, the breathing of such patients is heard weakly, rales are absent, and it is very difficult to establish the onset of pneumonia; an unexpected rise in temperature and a sharp increase in the frequency of breathing are always suspicious regarding pneumonia. It sometimes develops during toxic diphtheria in the period of paralysis and disorders of cardiac activity; in such patients, it has partly a hypostatic and partly an aspiration character (see below). The prognosis is extremely poor. In scarlet fever, pneumonia is rarely observed; in septic scarlet fever, it has a septic character; the causative agent is streptococcus. In mild and moderate forms of scarlet fever, it depends on an added influenza (pneumococcal) infection. The prognosis is not so bad. (For details regarding all these pneumonias—clinical picture, complications, outcome, etc.—see the corresponding diseases.) Lobular pneumonia in infants is especially often encountered after influenza, and sometimes arises as if independently (so-called "primary pneumonias" according to Meyer, Nassau, and others). In these pneumonias in infants, general phenomena on the part of the entire organism stand out especially brightly, and very often many organs and systems are involved in the process; often the local process in the lung recedes into the background in the clinical picture before the disease of other organs. The clinical picture is even more variegated and diverse than in older children. Attempts have long been made to create a classification of "primary pneumonias" of infancy and to fit numerous clinical forms into specific types. One of the latest proposed classifications—the Nassau classification—distinguishes 6 forms. 1) Pulmonary form: in the picture of the disease, phenomena on the part of the lungs come to the fore: dyspnea, cough; signs of disorder of other organs are absent or weakly expressed. The prognosis is favorable. 2) Cardiac form: circulatory disorder and decline in cardiac activity are sharply expressed: severe dyspnea, cyanosis, low blood pressure. Mortality is high. 3) Atonic form: resembles the previous one, but from the very beginning, atony of the entire musculature, abdominal wall, and diaphragm is observed. 4) Alimentary form: the most important symptoms are early and sharp weight loss, diarrhea, vomiting, meteorism. 5) Cerebral and convulsive form: clouding of consciousness, convulsions, meningeal symptoms. 6) Toxic and septic form: the most severe: stormy onset, temperature 40-41°, rapidly occurring collapse, cyanosis, intermittent breathing. Death after 48 hours. Mortality 100%. However, in life, one more often encounters not an isolated disorder of one or another organ, but the simultaneous involvement of many organs and systems. Therefore, instead of the fractional Nassau classification, it is more correct to distinguish, depending on the degree of disorder of the general condition, only the main types of the disease.
Molchanov and Dombrovskaya divide pneumonia in infancy into: 1) simple pulmonary, or localized, in which the general condition is disturbed to an insignificant degree; 2) toxic, or toxico-septic, in which disorders of the cardiovascular apparatus, nervous system, gastrointestinal tract, urinary organs, and other systems appear sharply; in some cases these disorders are of a purely toxic nature (toxic pneumonia), in others they are an expression of septicemia or septicopyemia (septic and toxico-septic), and 3) a transitional form (subtoxic), in which the indicated disorders have an unstable, transient character. A special group is represented by fulminant pneumonia. Molchanov and Dombrovskaya, out of 150 cases of pneumonia in infancy, observed the simple pulmonary form in 26 cases, the toxic and toxico-septic in 60 cases (of which 3 were fulminant), and the transitional in 64 cases. It is impossible to draw a conclusion about the frequency of the simple pulmonary form based on the material of inpatient departments; in reality, it occurs more often. Blood. The blood picture in 'primary pneumonia,' like the entire clinical picture, is very diverse and variable. Along with cases in which high leukocytosis (up to 30,000 and higher), neutrophilia, and a shift to the left are noted, there are cases with slight changes in the blood, and it is very often impossible to establish a regular connection with the severity of the course. In contrast to croupous pneumonia, the blood picture in lobular pneumonia in infants cannot serve as a reliable basis for prognosis (Sadykova and Lokhov, Timofeeva). Some authors note toxic changes in neutrophils. Complications. In this form of pneumonia, purulent otitis and purulent pleurisy (sometimes interlobar) are very common. Spontaneous pneumothorax occurs, which often resolves favorably. From the nervous system—serous and purulent meningitis. Epiphyseal osteomyelitis occurs, which can lead to a disorder of joint function (e.g., the hip joint), but sometimes it proceeds favorably and is even overlooked. In infancy, there are other forms of lobular pneumonia, of which the following must be pointed out. So-called capillary bronchitis. In infants, lobular pneumonia sometimes proceeds under the guise of a diffuse catarrh of the smallest bronchi. The onset is acute, high temperature, sharply expressed shortness of breath, cyanosis, general restlessness. Upon percussion, there is tympanitis, and upon auscultation—a large number of moist rales of various calibers. Some consider capillary bronchitis an independent disease, but it is more correct to consider it a variety of lobular pneumonia; on an X-ray (Dombrovskaya and Kudryavtseva), scattered foci are usually found throughout the lung, and at autopsy, it is also possible to discover small pneumonic foci. The prognosis is very serious. Pneumonia in severe nutritional disorders (paravertebral-distelectatic pneumonia according to Engel or striped pneumonia, Streifenpneumonie, according to Steffen). In small infants, emaciated atrophics, pneumonia proceeds atypically, without giving the usual symptoms: the temperature is often not elevated, there is no cough or it is negligible, and upon auscultation, small rales are often heard, meanwhile, at autopsy, foci of lobular pneumonia are discovered in the paravertebral regions, sometimes on both sides. Such pneumonias develop on the basis of atelectasis and circulatory disorders; the participation of microbes is not mandatory (Bartenstein and Tada). Congenital pneumonia and pneumonia of newborns are observed in children whose mothers were ill with pneumonia or sepsis during childbirth; in some cases, the cause is the entry of amniotic fluid into the child's respiratory tract (aspiration pneumonia), as well as a general septic infection of the newborn (septic pneumonia), less often aerogenic infection after a disease of the upper respiratory tract. It occurs more often in premature infants; predisposing moments in such children are atelectasis of the lungs and insufficiently developed reflex excitability, as a result of which amniotic fluid enters the respiratory tract during childbirth and milk during the normal feeding of the newborn in the first days of its life. Phenomena from the lungs are often absent or weakly expressed: there is no cough or it is negligible, dullness is obtained only with extensive infiltrates, rales are heard with difficulty, and an increase in temperature is not always observed. Diagnosis is based mainly on the general picture: irregular breathing, cyanosis, lethargy, drowsiness, refusal of the breast. The prognosis is poor; it is somewhat better in cases of aerogenic infection in full-term children. Finally, aspiration pneumonia occurs especially often in newborns (see above), infants, and in preschool age. The cause is the entry of a foreign body (sunflower seed, ear of grain, etc.), the entry of food particles during paralysis of the soft palate and pharynx (e.g., diphtheritic), and also in children who are in an unconscious state. The onset is acute; the course in children who were previously healthy is protracted; the outcome is sometimes an abscess and gangrene of the lung. The prognosis is serious; with a severe underlying disease, it quickly leads to death. When a foreign body enters, early diagnosis is important for its removal with the help of bronchoscopy. The prognosis in lobular pneumonia depends on age, the form of pneumonia, the child's nutritional status, care, the environment in which the patient is located, and a whole range of other conditions. According to Holt and Nassau, mortality during the first 2 years reaches 50-60%, in the 3rd year it does not exceed 33%, and in the 4th year—16%. Molchanov and Dombrovskaya (150 cases of pneumonia in children under 2 years old) obtained a general mortality of 15%. At the same time, out of 26 patients with the simple pulmonary form, all recovered; out of 64 with the transitional form, 4 died; out of 60 with the toxic and toxico-septic, 18 died. Emaciated, weakened children die quickly even with insignificant changes in the lungs; pneumonia proceeds heavily in rachitic children; exudative children are prone to a protracted course. Tuberculous children tolerate pneumonia relatively well, rarely giving miliary spread of the tuberculous process; characteristic for them is a protracted course. The presence of pneumococci in the blood gives a very poor prognosis (Dombrovskaya and Viktorov). The extent of the process in the lungs is of less importance than the general condition of the patient. Poor social and living conditions undoubtedly worsen the prognosis. Diagnosis in infancy, especially with a stormy onset of the disease, presents great difficulties. As with croupous pneumonia (central), shortness of breath, the patient's habitus, and other general symptoms are of greater importance than the results of percussion and auscultation. In toxic pneumonia with cerebral phenomena, it is often very difficult to exclude cerebrospinal meningitis; the state of the fontanelle does not always help, and only a lumbar puncture decides the matter. X-ray facilitates diagnosis to a significant degree. Regarding the distinction from croupous pneumonia, see above. Treatment depends on the age and form of pneumonia, however, the center of gravity of treatment for all cases of pneumonia, especially in infancy, regardless of the form, lies in nutrition, clean fresh air, and general proper care. Food must be sufficient in caloric terms and contain vitamins. The best food, especially in severe cases, is breast milk. With mixed and artificial feeding, it is necessary to conform to the child's inclination for one food or another, prescribing it in smaller quantities, but more often. With dyspeptic phenomena—mixtures usual for parenteral dyspepsia. Regardless of the type of feeding, it is necessary to take care of a sufficient amount of fluid (tea, boiled water, drip enemas, or subcutaneous infusions of Ringer's solution). Fresh air (ventilation, opening of vents) is of no less importance. In warm weather, the patient should be taken out into the air. In mild cases, patients tolerate staying in the air, even in winter, excellently, but with cyanosis, shortness of breath, and frequent coughing, deterioration is sometimes observed; the use of cold air in our climatic conditions has not yet been sufficiently studied and requires caution (Maslov, Molchanov and Dombrovskaya). One should not forget about turning the child over, carrying them in one's arms; this is especially important in pneumonia with nutritional disorders. Daily hot baths (37-39°) are recommended, but in this regard, it is necessary to conform to the body's reaction: the absence of skin redness, weakening of heart activity, and restlessness are a contraindication to continuing the baths. For older children, baths and warming compresses are prescribed; for infants, compresses are inappropriate (difficulty in breathing), mustard wraps are better. In addition to the indicated treatment common to all cases, for individual forms, the treatment is symptomatic depending on the lesion of one organ or another. Expectorants (ipecacuanha, senega) are used rarely in infancy and only with special indications (many rales, weak infrequent cough). In case of decline in cardiac activity—camphor subcutaneously, adrenaline (0.2-0.5 in 10-15 cm³ of Ringer's solution), intramuscular injection of glucose (5-20 cm³ of a 20% solution). In pneumonia with cerebral phenomena—lumbar punctures; for general restlessness—bromine, luminal, calcium; for convulsions—chloral hydrate.
In severe cases with cyanosis and dyspnea, oxygen and venesection are used. In toxic and toxico-septic forms, hemotherapy (10-30 cm3 of mother's blood) is also applied. Specific treatment (vaccine and serum therapy) is not yet sufficiently studied. French authors widely use anti-diphtheria serum, especially in measles-related pneumonia. Prophylaxis, in view of the high mortality from pneumonia in infancy and early childhood, is of enormous importance. It must be conducted in two directions. Firstly, it is necessary to protect small children from infection, to which pneumonia is especially often added, primarily from whooping cough, measles, and influenza (see prophylaxis of these diseases). In children's institutions and hospitals for infants, pneumonia and influenza patients must be isolated (boxes); precautionary measures are necessary regarding the transmission of infection from mothers and staff caring for small children (prohibition of kissing, masks during feeding). Also of importance are the elimination of overcrowding and overfilling of children's wards, ventilation of wards, and long stays of children in the open air (sleeping on a terrace). During epidemics of measles and influenza, restrictive measures regarding the gathering of children are necessary. The second path is increasing immunity and resistance to infections in general. This is achieved primarily by sufficient and proper nutrition (breast milk, vitamins) and then by wide use of fresh air and reasonably conducted hardening. Special attention should be paid to children with nutritional disorders (hypotrophics and atrophics), rickets, and constitutional anomalies (exudative diathesis, spasmophilia). To avoid atelectasis and hypostasis, it is necessary to eliminate prolonged lying on the back, especially for children with nutritional disorders (turning over, carrying in arms). When such children fall ill with pneumonia, it is desirable, in view of the severe course of this disease in them, to hospitalize them as early as possible. In the fight for the elimination of pneumonia, broad municipal measures play a primary role: city planning (garden cities), increasing living space, rationalization of heating and ventilation. On the other hand, sanitary-educational work among parents must also play a large role (fighting prejudices, overheating the child, fear of colds, etc.). In this area, a huge role belongs to institutions for the protection of motherhood and infancy and for the protection of children's health (consultations, nurseries, etc.). The success of the fight against infant mortality from digestive and nutritional disorders is a guarantee that similar positive results will be obtained on the front of the fight against pneumonia. Specific prophylaxis (pneumococcal vaccine, strepto-, staphylo-, and pneumovaccine) is still in the study period.
V. Molchanov. IV. Postoperative pneumonia. Postoperative pneumonia is one of the most frequent and severe complications of the postoperative period, yielding a very significant percentage of mortality. Thus, in Girgolav's clinic, 38.5% of operated patients contract postoperative pneumonia, and in Fedorov's clinic, 29% of all those operated on the stomach. Mortality from postoperative pneumonia is very high. Petrov indicates that 15% of all postoperative deaths are caused by postoperative pneumonia; in Rubashov's collected statistics, this figure reaches 17%. Among foreign authors, Petren believes that from 1/4 to 1/3 of all operative deaths have postoperative pneumonia as their cause, Guber cites the figure 19%, and Redelius 25%. In any case, his figures for mortality from postoperative pneumonia—1.6% of all operated patients and 5.26% of all who underwent laparotomy—are closest to the truth. These figures raise the question of postoperative pneumonia as a problem of primary importance. Until recently, the following factors were attributed etiological significance in the occurrence of postoperative pneumonia. 1. The harmful effect on lung tissue of the anesthetic substance itself—chloroform and ether (post-anesthetic pneumonia). This version was discarded when, with the introduction of local anesthesia, the number of postoperative pneumonias not only did not decrease but in some places even increased. 2. Cooling of the patient. This view was abandoned when the years of devastation in various countries revealed that during operations in insufficiently heated and even cold operating rooms, postoperative pneumonias were observed no more often than when working in good conditions. 3. Aspiration of vomitus (aspiration pneumonia). The introduction of local anesthesia, in which there is no aspiration of vomitus, proved the untenability of this view as well. 4. Embolism (thrombi, fat, infectious masses) and infections. These etiological moments could not be confirmed experimentally or proven clinically. On the contrary, recently there is experimental evidence that the flora of pulmonary postoperative suppurations coincides with the flora of the oral cavity and upper respiratory tract (canalicular infection), and not with the flora of the surgical wound or the primary process (not metastatic hematogenous or lymphogenous infection). In the pathogenesis of postoperative pneumonia, however, the following clinical facts are indisputable. Men get sick more often than women. In young age, postoperative pneumonias are much rarer, and they proceed significantly easier than in advanced and old age. Most often, postoperative pneumonia is observed after laparotomies, especially in the upper half of the abdomen (operations on the stomach, liver). After heavy, especially long, traumatic, rough operations, postoperative pneumonias occur more often. Cachexia, severe general diseases, heart weakness, lung diseases, and increased nervousness undoubtedly predispose to the disease of postoperative pneumonia. All conditions that reduce the free excursions of the chest, limit lung ventilation, hinder breathing, and increase the standing of the diaphragm contribute to the development of postoperative pneumonia. Such moments include: prolonged lying on the back (the diaphragm in this case stands two intercostal spaces higher, the lungs are compressed), immobility of the patient, meteorism and atony of the stomach and intestine, circular and tight bandages on the chest and abdomen, active breath-holding due to pain after laparotomy and passive, reflex reduction of respiratory excursions, heart weakness as a consequence of the entire surgical intervention with deterioration of blood circulation in the lesser circle, depressed psyche of the patient, exhaustion of the patient (laxatives, hunger, thirst). Complete clarity in the understanding of the pathogenesis, pathological anatomy, and clinical picture of postoperative pneumonia was brought by the research of American scientists in recent years. With the obstruction of a bronchus of any caliber, the air in the entire section of the lung supplied by this bronchus is soon absorbed by the flowing blood without residue, so that in the corresponding area, lung collapse occurs. Depending on the ratio between the size of the obstructing object and the lumen of the bronchus, there may be either clinical well-being, Fig. 1. Jackson's scheme. Parallel lines show the lumen of the bronchus with mucosa; black disk—obstructing object; arrows—direction of air flow during inhalation (down) and during exhalation (up); I—object narrower than the lumen of the bronchus; air enters and exits unimpeded; clinically—complete well-being. II—bronchial system during inhalation and exhalation; left—during inhalation the bronchus expands, the object does not obstruct it, air passes into the lung; right—during exhalation the object fills the entire lumen of the bronchus, air cannot exit; with each inhalation it accumulates; clinically—emphysema. III—object tightly obstructs the lumen of the bronchus; during inhalation air does not pass into the lung; behind the obstruction, air is absorbed by the flowing blood; clinically—atelectasis (collapse) of the lung.
or emphysema, or lung collapse (Figure 11). In the postoperative period, the role of an object obstructing the bronchial lumen can be played by a lump of thick, viscous, purulent mucus, bronchial secretion, edema and swelling of the mucosa itself, etc. Both anesthesia and the surgical trauma itself cause, by reflex, increased secretion and exudation in the bronchi. Furthermore, as a result of operations and anesthesia, which are a severe psychic and somatic trauma, the drainage mechanisms of the lungs, by means of which the obstructing viscous mucus and secretion are removed, suffer, namely: 1) the ciliated epithelium of the tracheobronchial tree, which provides under experimental conditions
the movement of dye up to 1 cm in 20-30 seconds, 2) normal peristalsis of the bronchi (S. Reinberg), and 3) the cough impulse—the latter is the most powerful drainage mechanism of all.
Depending on the size of the obstructed bronchus, the size of the atelectatic area of lung tissue also varies: a lobule, a lobe, an entire lung, etc. Thus, the vast majority of postoperative pneumonias, bronchitis, etc., are considered as lobar, lobular, or focal, disseminated atelectases (collapses). Infection subsequently joins the atelectasis secondarily, usually not from the blood, but from the upper respiratory tract. In the stage of non-infected atelectasis, the process is still reversible (G. Reinberg), i.e., the obstruction can cease spontaneously or under the influence of treatment, and the corresponding area of the lung inflates again (reinflation, reaeration of the lung). These are those short-lived postoperative pneumonias that pass without a trace in a day or two or three. If, however, the bronchus is not cleared and infection joins, then an ordinary, true pneumonia develops with an outcome either 1) in resolution after several days (weeks) or 2) in suppuration, abscess, or gangrene of the lung, depending on the purulent or putrid infection. The pathological-anatomical picture of postoperative pneumonia in its pronounced form does not differ in any way from the corresponding picture in ordinary pneumonia, abscess, or gangrene of the lung (see Lungs, abscess, gangrene). The difference exists only in the first hours and days, when atelectasis develops rapidly within 2–3 hours from the obstruction of the bronchus, and in the case of atelectasis of large sections of the lung, a displacement of the mobile parts and organs of the chest cavity toward the diseased side occurs. In this case, retraction of the intercostal spaces, high standing of the diaphragm, displacement of the mediastinum with the organs and heart, and even scoliotic curvature of the spine with concavity on the affected side are observed. In the unaffected lobes of the same lung and in the other lung, vicarious emphysema inevitably develops. The clinical picture of postoperative pneumonia differs little from the corresponding ordinary pulmonary diseases. Postoperative pneumonia is a summary designation, as this concept encompasses bronchitis, bronchopneumonia, and true lobar pneumonias observed in the postoperative period, sometimes occupying an entire lung, with displacement of the mediastinum and its organs. The clinical manifestations of postoperative pneumonia are as follows: urge to cough, fever, difficulty breathing, circulatory disorder (cyanosis); subsequently, weakening and disappearance of breath sounds, dullness of sound upon percussion if a large or superficially located focus of the lung is atelectatic. The most reliable and accurate data are provided by an X-ray image (not fluoroscopy). Diagnosis of postoperative pneumonia is not difficult. Difficult, shallow breathing, coughing, a rise in temperature on the very first or second day, a frightened, sweaty, cyanotic face—all this makes one think first of all about postoperative pneumonia. Whispered speech should also lead to the thought of changes in the lungs, of their insufficient function, of a developing postoperative pneumonia. Upon auscultation, as well as upon percussion in the first day or two, there are very few changes; only X-ray images show shadowing in the area of the atelectatic foci. The prognosis for developed postoperative pneumonia is always serious. Not to mention the significant mortality, postoperative pneumonias result in a fairly large number of lung abscesses and gangrenes, with a prolonged, severe course and often with an unfavorable outcome. Still, the majority of postoperative pneumonias end in resolution and recovery after several days or, less often, weeks. Postoperative pneumonias proceed differently in very emaciated, weakened, exsanguinated, septic patients and the elderly; they usually die from postoperative pneumonia. As for the treatment of postoperative pneumonia, it does not differ in any way from the treatment of ordinary bronchitis and pneumonia. Cupping, warming compresses, expectorants, analgesics to facilitate expectoration, the injection of ether under the skin proposed by Bier, injection of one's own blood according to Forschütz (autohemotherapy), vaccine therapy, salvarsan for suppurations and especially for gangrene (fusospirillosis), etc.—all these agents are used with some success. But since the causes and mechanism of the occurrence of postoperative pneumonia are now known, unlike the complete helplessness in the relatively recent past, surgeons now possess an extremely successful prophylaxis for postoperative pneumonia. Preventive measures begin long before the operation. They consist of: 1) careful selection of patients for surgery and a well-founded choice of anesthesia method; 2) curing catarrhs of the respiratory tract (influenza) before the operation; 3) preparing the cardiovascular system, where necessary, by digitalization and strychnine injections for major surgical intervention; in more severe cases, blood transfusion is used; 4) cleaning and sanitation of the oral cavity, especially during operations on the upper respiratory and digestive tracts (ascending infection); 5) preparing the patient's psyche for the surgical trauma, especially in cases of Basedow's disease, heart defects, severe nervousness; here, besides bromides and regimen, bed rest before the operation is appropriate; 6) preventing cooling during and immediately after the operation, as cooling lowers the resistance of the patient's organism; 7) improved anesthesia technique and improved operation technique, its speed, and low traumatism. The main and most powerful measures for preventing postoperative pneumonias are: 1) systematic inhalation of carbon dioxide (CO2) after the operation every 1–2 hours for several minutes. Carbon dioxide is given from an ordinary oxygen cushion through a catheter inserted a few centimeters into the nostril. Carbon dioxide is the most powerful stimulant for the respiratory center. 2) Systematic compulsion of the patient by persuasion to cough well and expectorate as soon as he regains consciousness after anesthesia. If the doctor carries this out persistently and systematically, especially in the first hours and days after the operation, the number of postoperative pneumonias drops to negligible figures. 3) Active state of the patient after the operation; the patient should not be kept in a lying position for too long after the operation, but should be sat up as soon as vomiting has ended; the operated patient should be allowed all movements in bed from the day of the operation and—except for rare cases with special contraindications—early permission to sit in a chair and walk a little around the room. When applying preventive measures, it is necessary to consider every operated patient as a candidate for postoperative pneumonia and therefore to carry out all preventive measures in principle for all operated patients. With compliance with these conditions, postoperative pneumonia has become a much rarer phenomenon in surgical departments in the very last years.
G. Reinberg. U. Pneumonia in the tropics. Pneumonia in the tropics (tropical pneumonia) occupies a special place from both an epidemiological and a clinical point of view. In many tropical regions, Pneumonia rages severely among the native population. In Perak (Malay Peninsula) mortality from Pneumonia is higher than from malaria and dysentery combined; in New Orleans it occupies second place among the causes of mortality; on the Caroline Islands—first place. The epidemic character of outbreaks of Pneumonia in the tropics is conditioned predominantly by the lack of immunity among the natives. As the virus spreads in a certain locality or as the colored population, having arrived from an unaffected area to an affected one, becomes acclimatized, the predisposition of the native population to pneumococcal diseases falls, remaining, however, for the most part at higher figures compared to the European population, which may be conditioned by the worse social and living conditions of the natives; Pneumonia epidemics break out among natives crowded in prisons, in the holds of steamships. During the World War, among exhausted porters in East Africa, the epidemics were of such a severe character that many cases were considered suspicious for plague and only upon autopsy and on the basis of bacteriological investigation was the diagnosis of pneumococcal infection made. Fresh contingents of natives, recruited into the army or for work, suffer most from Pneumonia. In the Belgian Congo in 1922, Pneumonia was the cause of 68% of all mortality among newly recruited recruits. Gorgas, in the mines of South Africa in 1912, calculated that among Negroes recruited from remote tropical regions, mortality from Pneumonia amounted to 26.3‰ against 8‰ among Negroes who had lived for some time before that in temperate zones. Authors who have studied the course of pneumonia among the natives of tropical countries note the rarity of classical forms of lobar Pneumonia, the predominance of an atypical course with irregular and prolonged temperature, the frequency of pneumococcal bronchitis, pleurisy, hemorrhagic infarcts, and acute edema of the lung. The infection in a large percentage of cases has a septicemic character. Baermann obtained a positive result from blood cultures in 30-64% of examined cases; other authors had 50% positive findings. A great variety of clinical manifestations is observed—all kinds of organs are affected by the pneumococcus; vesicular dermatitis, subcutaneous abscesses, parotitis, peritonitis, arthritis, meningitis, hypopyon, and panophthalmitis are observed. Heart lesions—effusive pericarditis, myocarditis—present a particular danger. By the sixth day of the disease, symptoms of liver involvement (jaundice) and kidney involvement (uremic phenomena) are often noted, for the most part leading to death. Thus, by the character of its course, pneumococcal infection among the aborigines of the tropics occupies an intermediate position between the lobar form typical for the temperate zone and the experimental pneumonic septicemia obtained under laboratory conditions. In the Belgian Congo, it was noted that among natives living in places where they have long been in contact with whites, i.e., where they had the opportunity to come into contact with the virus and develop a certain degree of immunity, the pneumococcus gives a predominantly pulmonary localization, whereas among newly arriving natives descending from the mountains, generalized forms predominate. According to a number of authors, specific tropical diseases have some influence on the character of the course of pneumococcal infection, and perhaps on its frequency. Sitsen in Batavia points out that the more enlarged the malarial spleen is, the less sharply and less typically the reaction from the lungs to pneumococcal infection is expressed. Other authors point to the role of Schistosomum eggs, which irritate the vessels of the lungs and thereby create a locus minoris resistentiae, and to the role of hookworm larvae migrating through the lungs. The significant spread of syphilis may play a certain role. The distribution of pneumococci of different types in the tropics does not present any regularity. In many tropical localities, approximately the same percentage ratios of the four types have been established as in the temperate zone; for example, on the island of Java, in Singapore, in Madras, and in New Guinea, type I predominates; in the north of India, in Manila, in Panama, and in Kenya, type IV predominates. Specific vaccination of natives was applied on a large scale in South Africa in diamond mines from 1912. The first good results of Wright did not receive confirmation everywhere later on. Vaccination for therapeutic purposes was applied in Antananarivo and Calcutta with good results in those cases where the vaccine was applied in the early period of the disease. Specific serotherapy was also applied in a number of points. Among Senegalese, it gave a reduction in mortality from 30-32% to 8-13%. In Madagascar, mortality among those treated with antipneumococcal serum amounted to 8% against 24% among the untreated. In French East Africa, a reduction in mortality from 50% to 12% was achieved with serotherapy.
Sh. Moshkovski. VI. Pneumonia in animals. Pneumonia in animals, from a pathophysiological point of view, presents in its various forms of manifestation an almost complete analogy with pneumonia in humans; in pathological-anatomical terms, some differences are conditioned by the peculiarities of the macroscopic and histological structure of the lungs in different animals. Significant peculiarities are presented only by etiological factors of an infectious nature. Croupous pneumonia in horses occurs as a primary and, moreover, predominantly epizootic disease, in the form of 'chest plague' or 'contagious pleuropneumonia of horses.' Its causative agent is unknown and likely belongs to ultramicroscopic viruses. In the affected areas of the lung and pleura, various microorganisms can be detected that complicate the process but do not have independent etiological significance (e.g., Streptococcus pyogenes equi, Bacillus bipolaris equisepticus). As a secondary phenomenon, croupous pneumonia is observed in horses during a whole series of acute and chronic diseases: in strangles, in equine influenza, in prolonged gastritis and enteritis, etc. In cattle, there exists an independent lobar disease of the lungs, often affecting the adjacent areas of the pleura as well—'epizootic pneumonia' or 'contagious bovine pleuropneumonia' (pleuropneumonia contagiosa bovum). The causative agent is a microorganism that passes through bacterial filters, stands at the limit of visibility, and grows on special artificial media. Although it also causes a general infection of the organism, its localization under natural conditions occurs almost exclusively in the lungs, giving the impression of primary pneumonia. The inflammatory process begins in the interlobular connective tissue, which is strongly infiltrated with sero-fibrinous exudate; from here, the inflammatory process penetrates into individual lobules, and very unevenly, by virtue of which the affected areas on cross-section have a characteristic 'marbled' appearance. Such areas of varying size can gradually be separated from the surrounding healthy lung by a dense connective tissue capsule, forming freely lying 'sequestra' within it. Some authors (Evtikhiev) recognize the existence in cattle of a second independent genuine form of croupous pneumonia with an unknown causative agent, but the more widespread opinion is that it is of a secondary nature, in particular as a partial manifestation of hemorrhagic septicemia (Bacillus bovisepticus). Aspiration pneumonia can also proceed under the guise of croupous inflammation, although not with a typical clinical course. In sheep, croupous pneumonia is generally a comparatively rare phenomenon; it is encountered during the chronic course of sheep septicemia (Bacillus ovisepticus). In addition, cases of epizootic fibrinous pleuropneumonia in lambs and nursing ewes are described, caused by a diplococcus which grows in cultures into short chains. In pigs, pneumonia appearing in the course of hemorrhagic septicemia also often takes on a croupous character. Cases are observed where Bacillus anthracis causes fibrinous pleuropneumonia in pigs without localization of the microbe in other organs. In carnivores, at the present time, the existence of primary croupous pneumonia is denied by the majority of authors. As a secondary condition, it is observed, although not often, during various infectious diseases, for example, in canine distemper, in pasteurellosis (e.g., in cats). Anatomically typical croupous pneumonia has been described in carnivores in glanders. In rabbits, croupous pneumonia usually occurs as a partial manifestation of general infections, in particular in infectious rhinitis (see Pathology of laboratory animals), but it is also observed as an independent disease caused by specific causative agents from the group of coli-bacteria or bipolar bacilli. In birds, croupous pneumonia sometimes develops as a localization of a general process in fowl cholera. Catarrhal (lobular) pneumonia in animals appears in the majority of sporadic cases as a continuation of inflammatory processes that arose primarily in the bronchi and proceeds under the picture of bronchopneumonia. The infectious agent can be the most diverse microorganisms, many of which act only in connection with harmful physical or chemical factors: inhalation of hot air, irritating and poisonous gases, penetration of foreign bodies (dust, food, medicinal substances, worms, etc.). Mass, epizootic appearance of catarrhal pneumonia is observed as a secondary lesion in many contagious diseases, and it can be caused not by the causative agent of the primary disease, but by extraneous microbes. Very young, elderly, and emaciated animals are especially predisposed to catarrhal pneumonia. In horses, there is encountered, especially in the West, a peculiar 'infectious bronchopneumonia,' described under various names, with an unknown causative agent (possibly a filterable virus). Otherwise, catarrhal pneumonia is observed in horses rarely and, moreover, only as a partial manifestation of a general infection, e.g., in glanders. In cattle, catarrhal pneumonia and bronchopneumonia are not a rare phenomenon both in sporadic and in epizootic form, but it does not constitute a definite independent disease. The pathogenic microbes found in it, such as Bacillus bovisepticus, Bacillus pyogenes, Bacillus necrosis, and especially in calves Bacillus paratyphi, Bacillus Gaertneri, Bacillus pyocyaneus, apparently do not have self-sufficient significance. Sometimes it accompanies general infections: foot-and-mouth disease, malignant catarrhal fever, tuberculosis, actinomycosis, etc. In calves, true epizootics of verminous bronchopneumonia are observed. In sheep, catarrhal pneumonia etiologically differs little from catarrhal pneumonia of cattle, not excluding worm infestation. In the form of a complication, it is also encountered in sheep pox. In pigs, bronchopneumonia is widely prevalent as a partial manifestation or as a companion to various infectious diseases, including 'swine fever.' In paratyphoid, it can prevail over intestinal phenomena to such an extent that it gives the impression of primary localization. Verminous pneumonia is of great importance in piglets as well. In dogs, catarrhal pneumonia, in contrast to croupous pneumonia, is a very frequent phenomenon as a companion to 'canine distemper.' In rabbits, in infectious rhinitis, instead of croupous phenomena, bronchopneumonic foci are encountered in the lungs. In birds, a severe catarrhal pneumonia is described, accompanying infectious catarrh of the upper respiratory tract, as well as bronchopneumonia of verminous origin. Enzootic pneumonia of young animals is distinguished into a special group both from a clinical and an economic point of view. It bears a predominantly catarrhal, but often also a catarrhal-croupous or purely croupous character, causing enormous losses to civilized animal husbandry. Etiologically, it differs little from the corresponding pneumonia of adult animals. The main role is played by Pasteurella with its varieties, such as Bacillus vitelisepticus, ovisepticus, suisepticus, but other microbes from the coli-paratyphoid group, streptococci, and staphylococci, etc., are also encountered. Newborns, sucklings, and more rarely young animals of older age are affected, and moreover, predominantly calves, piglets, and lambs, more rarely kids and foals. Mycotic pneumonia of animals (pneumomycosis), caused by the inhalation of mold fungus spores, rarely bears the character of primary bronchopneumonia developing in weakened animals. In the majority of cases, it represents a secondary development of fungi in pathologically altered tissues, complicating the primary process. Domestic poultry are affected predominantly, much more rarely horses, cows, calves, and sheep. Most often, Aspergillus fumigatus and niger are detected in this disease; Aspergillus glaucus, Mucor racemosus, and Mucor conoideus have also been found. Purulent pneumonia of animals in rare cases develops on the basis of croupous and catarrhal pneumonia, especially with the participation of Bacillus pyogenes (in cattle and pigs) or the causative agent of pseudotuberculosis (see), but usually it bears an embolic character in pyosepticemia of sucklings, septic metritis, ulcerative endocarditis, and all other purulent processes, such as abscesses in strangles, after castration, etc. Interstitial pneumonia (sclerosis pulmonum) is encountered in animals as a consequence of various protracted infectious processes occurring in the lung tissue and in the bronchi, as well as pneumoconiosis. Described as a primary disease in old horses and cattle, sclerotic changes (so-called 'lardaceous pneumonia,' pneumonia lardosa) are apparently also the result of chronic infections, mainly tuberculosis.
Related articles
Mentioned in
Cite this page
“Pneumonia.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/pneumonia/