Letality
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article defines letality (case fatality rate) as the percentage ratio of deaths to the number of people who have contracted a specific disease. It discusses the limitations of calculating this rate using hospital data versus general population statistics and outlines the various factors—such as the nature of the epidemic, age, social conditions, and medical intervention—that influence these rates.
Encyclopedia article (1928–1936)
Letality (French lethalite), or case fatality rate, is the percentage ratio of the number of deaths to the number of people who have contracted the same disease. The letality is calculated for a specific period, usually a year. In Moscow, for example, in 1926, 10,774 cases of scarlet fever were registered; 904 cases of death from scarlet fever; the letality for that year was 8.4%. In Leningrad, for the same year, 9,454 cases were registered and 653 deaths from scarlet fever; the letality was 6.9%. Calculating letality in relation to the number of registered patients does not provide a true indicator of letality, because not all patients are registered; on the other hand, not all death certificates contain an accurate diagnosis (possibility of an erroneous diagnosis, death of a patient without medical supervision, etc.). Another method of calculating letality, which is more accurate, is the use of hospital data. In this case, the number of deaths for a specific period is calculated in relation to the number of patients discharged (recovered and died) from the hospital during the same period. In Leningrad, for example, for the period from 1922 to 1926, 6,192 measles patients were discharged (discharged home and died) from hospitals, of whom 806 died; the letality for measles during this period in Leningrad hospitals was 13%. However, letality calculated from hospital data also does not provide entirely accurate data, because only more severe cases end up in hospitals. It would be, for example, completely incorrect to establish, based only on hospital data, the general letality rate for influenza, measles, whooping cough, and other diseases, since patients are rarely hospitalized for them.
Letality has a specific indicator for each given disease. Below are the letality indicators (per 100 cases) for some acute infectious diseases according to data from Leningrad hospitals for 1886–1926 (according to Binshtok) and Germany for 1889–97 (according to Prinzing). When comparing these indicators, one must remember the difference in the periods to which they refer. Letality for some acute infectious diseases in Leningrad (1886–1926) and Germany (1889–97): Croupous pneumonia (Leningrad 18.2, Germany 19.4); Diphtheria (Leningrad 21.9, Germany 21.4); Smallpox (Leningrad 24.5, Germany 12.2).
The letality indicator is not a constant value. It fluctuates depending on various causes. 1) The nature of the epidemic. Ordinary, so-called endemic influenza gives a negligible percentage of letality. Epidemic influenza, as it was, for example, in 1918, gives an extremely high letality. Letality for malaria, usually very low, rose in the USSR during its pandemic in the period of the Civil War to unprecedentedly high figures: in some places up to 2% and higher. Over many years, diphtheria has produced epidemic waves with sometimes very high and sometimes relatively low mortality. 2) Letality is not the same at the beginning of an epidemic, at its height, and at the end. As a rule, it is higher at the beginning and at the height of the epidemic. 3) At the same time, it is not the same in different countries, for example, letality for smallpox (see). Letality for scarlet fever for the same years (1925–27) was about 1% in England, Germany, Denmark, Sweden, and Switzerland, about 5% in Romania and Japan, and about 10% in Leningrad. 4) Over a long period of years, letality decreases due to the improvement of sanitary conditions of the population, improvement of hospital conditions, and patient care. Thus, in most European countries over the last 50 years, letality for measles, whooping cough, and scarlet fever has noticeably decreased. In Leningrad hospitals, it was over 20% for the latter during the period from 1886 to 1909, and 11% in 1922–26. For croupous pneumonia, it was over 20% in Leningrad hospitals during the period from 1886 to 1900, and 10.6% in 1922–26. 5) It changes in the direction of a decrease due to the introduction of specific treatment methods, as, for example, with diphtheria. Social conditions have a strong influence on letality. For whooping cough, measles, and other diseases, it is higher among the poor segments of the population living in unsanitary conditions than among its affluent groups (see these diseases). 6) Famine and public disasters, by worsening the sanitary well-being of the broad masses of the population and weakening the organism, lead to an increase in letality for a wide variety of diseases. This, in particular, should explain the high letality for malaria during the period of the Civil War and famine, as mentioned above.
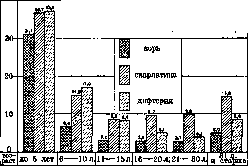
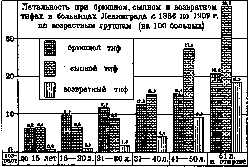
7) The age factor plays a large role in the level of letality. The most striking example is the colossal difference in letality between infants and adults with acute gastroenteritis. In typhoid fever, letality is low among children; it increases with age and reaches a maximum in old age (Figure 1). The same applies to typhus and some other diseases. The opposite picture is observed in so-called 'childhood infections': for measles, scarlet fever, whooping cough, and diphtheria, it is highest at the age of up to 5 years; with increasing age, it decreases, only to rise slightly again at the age of over 30 years (Figure 2). Pneumonia gives high letality in early childhood and old age. 8) Letality is not the same among men and women. According to data from Leningrad hospitals, it is higher among men in all age groups for typhus and, conversely, higher among women for croupous pneumonia. 9) Letality is influenced by the time of seeking medical help (and consequently its accessibility), the timeliness of applying specific treatment (e.g., for diphtheria, anthrax), patient care, the condition of the medical institution where the patient is placed (overcrowding, unsanitary conditions, unqualified personnel—all this worsens the outcome of the disease and increases letality), etc. 10) All other things being equal, the severity of the disease has the strongest influence on letality: at the same time and at the same age, septic forms of scarlet fever give an immeasurably higher letality than toxic ones. Among the causes influencing letality, many remain yet to be clarified. Further accumulation of materials on this issue is necessary, which is of enormous importance in the prognosis of the course of both epidemics as a whole and individual diseases (one should not confuse the terms letality, or 'case fatality rate,' with the term 'mortality'; the latter means the ratio of the number of deaths to the number of the population among whom the deaths occurred).
Related articles
Cite this page
“Letality.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/lethality/