Measles
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia provides a historical overview and etiological discussion of measles. It details the early history of the disease, the 19th-century clinical observations, and the ongoing scientific debate in the early 20th century regarding the causative agent, specifically examining the theories of filterable viruses and bacterial causes.
Encyclopedia article (1928–1936)
MEASLES (Latin: morbilli, French: rugeole, German: Masern, English: measles) is a general acute infectious disease manifested by fever, a characteristic rash on the mucous membranes and skin (enanthema and exanthema), and inflammation of the mucous membranes of the respiratory tract and eyes. History. Based on available historical data, it should be considered that measles has been known to humanity for many centuries before the Christian era. In the 9th century A.D., it was described under the name hash-bah by the Arab physician Rhazes. Physicians of the 14th–16th centuries described it under the names blac-ciae and morbilli. In the second half of the 17th century, Sydenham and Morton provided a detailed description of the clinical picture of measles, but, as before, this disease was very often confused with other eruptive diseases, mainly scarlet fever and smallpox. Only in the second half of the 18th century was measles distinguished as an independent nosological entity. Further in the history of measles, the year 1847 should be noted, when Panum published a report on the measles epidemic in the Faroe Islands, which provided a great deal for the understanding of the clinical features and epidemiology of this disease. The modern era is marked by attempts to find the causative agent of measles and the introduction of prophylactic vaccinations against measles (Weissbecker, 1896; Nicolle and Conseil, 1916; Degkwitz, 1920); the methodology of these vaccinations was developed in detail by Degkwitz. Etiology. The causative agent of measles is unknown to this day. Numerous works carried out in the 19th century and the first decade of the 20th century lead mainly to two conclusions: according to some authors, the causative agent of measles belongs to the group of filterable viruses; another, more numerous group of researchers recognizes various bacteria as the etiological cause of measles. Unfortunately, verification experiments did not confirm the findings made, and therefore, until recently, the essentially poorly substantiated theory of a filterable virus prevailed. The last decade has been marked by a number of new works which, being based on modern achievements in microbiology, are of significant interest. Caronia (1923) described a Gram-negative diplococcus as the causative agent of measles, which he managed to detect in the pharyngeal mucus, blood, and bone marrow of measles patients. A culture of the microorganism was obtained under anaerobic conditions on special 'catalytic' media (ascitic broth with a piece of guinea pig organ or with fresh blood). According to the author's description, this diplococcus undergoes a phase in its development when it becomes ultramicroscopic and, therefore, can be filtered. Caronia believes that he has discovered specific antibodies in the blood of measles patients against the microbe he described. The results of vaccination of healthy children for prophylactic purposes are especially interesting. Thus, Caronia and Sindoni vaccinated 539 children who were in contact with measles patients under various conditions with a vaccine made from their microbe: of the vaccinated, only 9 people fell ill later. Meyer and Nobel, while verifying these observations, could not confirm them. Furthermore, Groer and Redlich, by vaccinating children who were in contact with measles patients with extracts from guinea pig organs, protected them from contracting measles. Burgers and Bachmann showed that even uninoculated Caronia media often yield growth of a microorganism identical to that described as the causative agent. Based on the experiments of Groer and Redlich, it could be admitted that the success of Caronia's vaccination depends on non-specific immunization; but recently, the observations of the Italian authors have received indirect confirmation in the works of Zlatogorov, Nasledysheva, and Burova. The latter authors managed to isolate in 10 cases (out of 24), by culturing the blood and pharyngeal mucus of measles patients, a diplococcus that stains variably by Gram and is strictly anaerobic. With this microbe, the authors performed successful neutralization experiments with serum from those recovering from measles, skin tests, and prophylactic vaccination with good results. Along with this, in a number of works starting from 1917, Tunnicliff describes a Gram-positive diplostreptococcus with a green pigment as the causative agent of measles. Unlike the microbe of the Italian authors, this microorganism is anaerobic only in the first generations. It is isolated on blood agar. With this microbe, Tunnicliff not only performed serological reactions and skin tests with positive results but also obtained, by immunizing goats, a serum that, in the hands of Hoyne and Hasul, gave the same results as vaccination according to Degkwitz. Although Long and Cornwell, applying Tunnicliff's methodology, arrived at negative results, Duval and Hibbard, as well as Belikov and Trushina, partially confirm Tunnicliff's observations. The latter authors managed to isolate from the blood and pharyngeal mucus of measles patients a Gram-positive diplostreptococcus, almost indistinguishable from Tunnicliff's microorganism. Unfortunately, serological reactions, skin tests, and the use of vaccine and serum from immunized goats yielded inconclusive results. Furthermore, inoculations of cultures into rabbits resulted in the same pathological changes in the organs as inoculations of blood and pharyngeal mucus (filtered) directly from patients. Close to those just mentioned are the findings of Ferri, Fischer, Donges, and Thomson, in which the subject is microorganisms of the streptococcus species. In addition, A. Fedorovich, in 52 cases of measles, was able to establish the presence of Tunnicliff's microbe in smears from conjunctival secretions, and this diplococcus was located mostly intracellularly. It should be noted that all the listed authors succeeded in their positive findings only when taking material from the patient during the prodromal period or on the first or second day of the rash. Based on the available data, especially taking into account that all the listed authors isolated microorganisms that do not differ significantly from each other, and that the isolation of microorganisms succeeded only during a certain limited period of the disease, it should be admitted that this microorganism, although it may not be the causative agent of measles, has some close relationship to it and therefore deserves careful study. The theory of a filterable virus has recently been revived in the works of Degkwitz. In his opinion, the virus can be cultivated on a special buffer medium for several generations. In the last generation, the original virus was at a dilution of 1:3,000,000, and yet in an experiment on a human, when a filtrate from a culture containing, along with the virus, also symbiont microbes (cocci with green pigment, Tunnicliff's microorganism, pneumococcus) was inoculated, a positive result was obtained: 10-15 days after the injection, the vaccinated child developed a symptom complex resembling measles, but no typical measles rash was observed. Inoculation of a culture filtrate of only the symbiont microbes did not produce such a reaction. It was also not possible to obtain a typical rash in monkeys. Children vaccinated with the culture filtrate of the virus and symbiont microbes did not react at all to a subsequent inoculation of blood from a measles patient. Degkwitz attempted to prepare immune measles serum in sheep. Released for sale by the Hoechst company, it did not yield positive results when administered to children for prophylactic purposes. In view of the fact that experiments on animals and the use of the serum did not provide any evidence in favor of the specificity of Degkwitz's finding, the existence of this filterable measles virus should be considered unproven for the time being. Despite the fact that, thus, the causative agent of measles is still unknown, experiments on animals, as well as clinical and epidemiological observations, provide sufficient data to judge the properties of the measles virus. Experimental measles. The high infectivity of the blood and secretions of the mucous membranes of a measles patient has been proven repeatedly, starting from 1758, by inoculations of material directly from human to human. This method was even widely used by some physicians for the purpose of preventing natural infection and the disease of measles. Thus, for example, Katona (1842) inoculated 1,122 children with the blood of a measles patient mixed with the discharge from skin vesicles or lacrimal fluid, and obtained a mild but typical disease in 1,115 of them. From the experience of transferring the virus to animals, besides old observations with inconclusive and negative results, the latest works of Goldberger and Anderson, Hektoen and Eggers, and Blake and Trask, performed on monkeys, deserve serious attention. The works of the listed authors provided a number of conclusions important from an epidemiological point of view; thus, it turned out that the blood is infectious shortly before the eruption and during the first day of the rash; however, the measles virus persists longer on the mucous membrane of the respiratory tract—infection of monkeys was successful even 48 hours after the appearance of the rash. The virus was also contained in defibrinated and filtered blood. The virus outside the organism proves to be very unstable: heating to 55° kills it within 15 minutes; it withstands drying at room temperature for only one day.
In the experiments of the authors cited above, it was possible to transmit the virus from monkey to monkey over the course of several passages. At the same time, an animal that had recovered from such an inoculation did not react to a repeated inoculation of infectious material; the scales of the epidermis sloughing off during desquamation proved to be non-infectious, neither in experiments on humans (Mauger, 1848) nor in experiments on monkeys (Goldberger and Anderson). Experiments on monkeys seriously reinforce the existing clinical and epidemiological observations on humans, and this is their main significance. The rabbit, which until recently was considered an animal little suited for experiments with measles, was again used for studying the measles virus thanks to the thorough work of Simon and Scott. These authors, having confirmed the observations on monkeys, proved experimentally that the virus is also unstable in the external environment in natural secretions from the organism—mucus from the nose. Experiments conducted in this same direction by Zlatogorov, Burova, and Nasledysheva, as well as by Belikov, Dvizhkov, and Trushina, showed that infected rabbits exhibit the same changes in organs as monkeys in the experiments of Blake and Trask. Taking into account that Nevin and Bittmann were able to passage the measles virus from a monkey to a rabbit and from the latter back to a monkey, it should be thought that not only monkeys but also rabbits are suitable for experiments with measles. Epidemiology. Location of the measles virus in the organism. The measles virus is undoubtedly present in the blood of a patient and in the secretions of the mucous membranes (pharynx, respiratory tract, and conjunctiva). It is apparently not contained in urine and feces. The scales of the sloughing epidermis are also non-infectious. In the external environment, the measles virus cannot survive for any significant length of time. The measles contagion is distinguished by extreme volatility. The source of infection, as with other diseases, is mainly the sick person in the case of measles. Infection occurs via droplet infection, and in the first days of the incubation period and during the period of the disease from the moment the rash disappears, the patient is not dangerous to those around them. Complications of the primary disease, according to existing clinical and partly bacteriological data, are caused by the introduction of secondary infection microbes, as a result of which they have no significance for the spread of measles. For infection, in the vast majority of cases, direct, even if short-term, contact is necessary (e.g., a kiss, etc.); sometimes even just being in the room with the patient without contact with them is sufficient (Dopter). The spread of infection through the air within the limits of a floor or several floors of the same building appears poorly proven. The frequently cited opinion that measles infection can spread from floor to floor through ventilation ducts should be considered insufficiently substantiated. On the question of the possibility of transmitting infection indirectly through objects used by the patient (bedding, linen, dishes, etc.), there are conflicting opinions. In general, this kind of transmission of infection should be considered doubtful, since in the case of measles, the possibility of the spread of infection by healthy persons or those sick with measles in an abortive form (formes frustes) is not absolutely excluded. Some authors allow for the transmission of the infectious agent through healthy persons or those who have recovered (bacillus carriers). However, there are no corresponding data in favor of this view yet. Susceptibility to measles is universal and total (at all ages). Congenital immunity to this disease does not exist. Rare cases of the absence of measles in the anamnesis of adults can be explained by the presence of active immunity acquired as a result of a previous abortive form of measles or imperceptible spontaneous immunization with the measles virus from patients or carriers. In earlier times, when measles was not yet as widespread among humanity as it is now, entire pandemics and severe epidemics of this disease were described repeatedly: e.g., in Germany in 1823–24 and 1826–28, in Northern and Central Europe in 1834–36, in North America in 1846–47, etc. The susceptibility of all ages to measles is especially well seen in the classic example of the measles epidemic on the Faroe Islands in 1846, described by Panum. On these islands, remote from transport routes, the last measles epidemic before that was observed in 1781. Having been brought to the islands from Copenhagen in 1846, measles achieved extremely wide distribution there: out of 7,782 inhabitants, 6,000 contracted measles. Not a single person who came into contact with the sick escaped infection. Only those people who had previously (in 1781) had measles were spared by the infection. At the same time, people even of advanced age, but who had not yet had measles, endured the disease in the same form of severity as small children. Analogous examples are also presented by the epidemics on the island of Martinique in 1841 and 1851. A disease suffered once leaves behind immunity for life. Cases of repeated measles infections described in the literature appear doubtful, since the accuracy of the primary diagnosis is not very reliable.
P. Belikov. Statistics and geographical distribution. 1. Mortality. Measles is the most common childhood infection. Despite a comparatively low lethality, thanks to its strong spread, it claims many thousands of victims annually. Below, in Table 1, the absolute figures of those who died from measles in some countries of Europe for the last years before the imperialist war and for 1925–1927 are presented. Table 1. Countries 1911 1912 1913 1925 1926 1927 England and Wales 13,128 12,856 11,666 2,389 8,941 6,007 8,380 9,326 1,243 1,163 7,498 5,333 10,581 7,248 3,997 4,949 344 220 923 1,983 3,518 247 3,926 4,455 5,942 132 3,622 582 691 660. Table 2 presents the mortality rates from measles per 100,000 population for some European countries over a period of almost 50 years. A comparison of these indicators allows us to say that for the majority of European countries, there is a tendency toward a decrease in mortality from measles. Over the last decade, it has remained significantly lower than for all previous periods. Table 2. Mortality from measles in European countries (average per year per 100,000 population). Years 1871–80 1881–90 1891–1900 1901–10 1911–13 1914–18 1919–23 1924–28. Figure 1 shows mortality from measles in England over a period of 78 years—from 1851 to 1927. The curve gives an idea of the decrease in mortality from measles over the last decades. Table 2 presents mortality rates from measles for the entire population. The same conclusion—about the decrease in mortality from measles—must be reached when calculating mortality from it for the child population. Per 100,000 children aged up to 15 years, there died: in Bavaria in 1901–1910, 74.1; in Württemberg, 60.7; in 1921–1925 in Bavaria, 48.5; in Württemberg, 23.4. Mortality from measles in the same period is not the same in different countries. Below, in Table 3, the mortality rates from measles in a number of countries for the last (1923–1928) years are presented. Table 3. Mortality from measles in different countries for 1923–28 (per 100,000 population). Countries
1923, 1924, 1925, 1926, 1927, 1928. Austria 13.8, 12.0, 9.9, 4.7, 10.6, 2.3; England 5.3, 18.7, 13.2, 0.3, 1.4, 16.0; Belgium 7.0, 3.7, 2.1, 22.8, 14.1, 56.0; Bulgaria 4.4, 10.8, 4.2, 12.4, 7.0, 5.6; Hungary 5.4, 3.6, 8.6, 20.3, 13.9, 2.9; Holland 3.1, 17.0, 9.8, 1.4, 9.0, 32.6; Greece 1.5, 12.5, 8.8, 8.6, 6.3, 13.7; Denmark 11.0, 16.1, 7.5, 8.2, 1.4, 2.5; Spain 21.9, 21.7, 1.3, 2.1, 18.0, 10.5; Italy 2.4, 1.0, 10.5, 1.9, 42.8, 76.9; Lithuania 2.3, 2.1, 8.9, 9.3, 8.0, 2.9; Norway 12.0, 0.5, 4.2, 20.1, 14.8, 1.0; Northern Ireland 0.3, 25.0, 11.7, 3.3, 19.0, 8.4; Czechoslovakia 63.4, 23.2, 8.2, 5.0, 9.2, 8.6; Switzerland 1.9, 6.2, 13.5, 2.0, 7.9, 13.8; Sweden 7.6, 8.4, 5.0, 5.9, 8.4, 0.6; Scotland 21.2, 1.5, -, 2.0, 17.8, 1.7; Estonia 13.5, 11.5, 26.1, 4.1, 9.9, 5.8; Egypt 20.5, 45.3, 57.0; Mexico; USA. Among European countries, the highest mortality is observed in Spain, Italy, Ireland, and Scotland; the lowest in Greece, Lithuania, Norway, Sweden, and Switzerland. The relatively low mortality from measles in Switzerland compared to other countries is also visible from Table 2. Of the non-European countries listed in Table 3, mortality from measles reaches very high figures in Egypt and Mexico.
Of all childhood infections, the periodicity of epidemic waves is most clearly expressed in measles. This is explained by the high susceptibility to measles. The contagious index for it, according to Gottstein, is equal to 95%, i.e., out of 100 people susceptible to measles who have come into contact with a measles patient, almost all one hundred people fall ill after a certain interval of time equal to the incubation period. With close contact between children in modern conditions, measles covers the entire non-immune population in a short time, its curve rises rapidly, at the same time the combustible material is quickly exhausted, and the epidemic wave declines, only for the epidemic to break out again after a certain interval of time when a new non-immune generation has accumulated. The smaller the populated territory and the less it comes into contact with other populated places, the more clearly this periodicity of measles waves stands out. In Table 3, where mortality from measles is given for a relatively short period (6 years), one can already note large fluctuations in mortality rates by individual years for most countries. This periodicity of measles waves stands out more clearly when comparing mortality by individual years over a long period of time, and it stands out more clearly the smaller the country is.
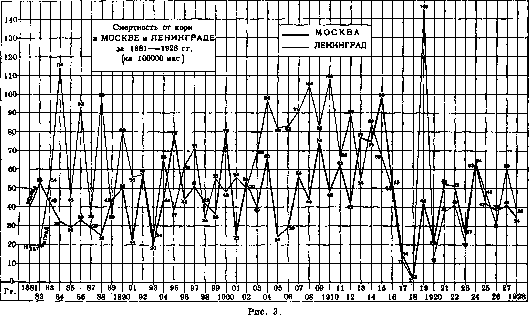
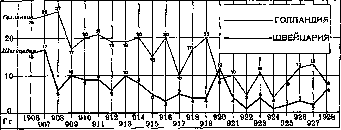
Figure 2 shows the mortality curves for measles by year for the period from 1906 to 1928 for Holland and Switzerland. The periodicity of measles waves is most clearly expressed in small Switzerland. This periodicity stands out even more clearly when comparing mortality by year in individual cities, and here too, the smaller the city, the more clearly it is visible. In small cities and rural areas, the measles wave drops to zero in individual years, only to rise to a great height in the very next years. In large cities, where it drops to such low figures. Growing new generations constantly maintain measles at a certain level in them, but
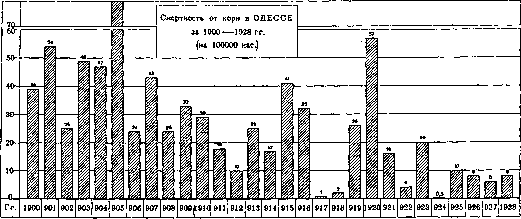
Figure 2. Mortality from measles in Holland and Switzerland from 1906 to 1928 (per 100,000 population). Nevertheless, even in large cities, the fluctuations of measles waves are noticeable quite clearly. Table 4 provides mortality rates from measles for Leningrad, Moscow, and Odessa for the period from 1881 to 1928 (on average per year per 100,000 population). Table 4. Mortality from measles in Leningrad, Moscow, and Odessa. Years 1881-1885, 1886-1890, 1891-1895, 1896-1900, 1901-1905, 1906-1910, 1911-1913, 1914-1918, 1919-1923, 1924-1928. Leningrad: 50.4, 68.6, 47.8, 53.8, 70.6, 93.8, 69.7, 43.0, 51.6. Moscow: 39.2, 36.1, 44.0, 50.6, 41.5, 49.2, 56.2, 49.6, 38.6, 43.4. Odessa: 51.0, 30.6, 51.0, 30.6, 17.8, 18.5, 24.6, 6.5. In Figures 3-5, mortality curves from measles by individual years are given for Moscow, Leningrad
the social composition of the population is very diverse and where an influx of those who have not had measles is constantly observed from outside, measles never
for 1881-1928, for Odessa from 1900 to 1928, for Königsberg from 1885 to 1900, and for Düsseldorf from 1913 to 1928. These curves clearly demonstrate the periodicity of measles waves; they stand out especially clearly on the last two curves, characteristic of Königsberg from 1810 to 1900. For this entire period, the character of the measles waves, according to his data, remains unchanged.
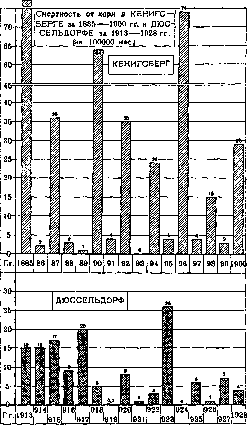
Figure 4.
of the course of measles epidemics in small cities. This wave-like character of measles epidemics remains unchanged throughout
Figure 5.
the entire time accessible to our historical review. Kisskalt collected materials on mortality from measles for Königsberg from 1810 to 1900. For individual periods, the average annual mortality from measles per 100,000 population in Königsberg was: Table 5. Periods 1816-1850, 1851-1863, 1875-1900. Average mortality, Maximum mortality, Years of maximum mortality: 794, 127, 190. Here is noted: a certain tendency towards a decrease in mortality from measles. Large epidemics did not last long—from 1 year to 4-5 years (1828-32, 1860-63). However, Kisskalt is inclined to explain these long epidemics of the 19th century by inaccuracy of diagnosis: it is possible that doctors were dealing with smallpox or varioloid. Materials on mortality from measles in Moscow and Leningrad (Table 4) do not provide an opportunity to speak about a decrease in mortality from it in these cities. When calculating mortality from measles for the city of Moscow per 100,000 children under the age of 14, the following indicators of this mortality are obtained (on average per year): in 1892-1901—214, 1902-05—213, in 1906-09—312, in 1910-13—241, in 1919-21—202, in 1922-24—208, and in 1925-27—165. Table 6 provides mortality indicators from measles over a long period of time in three large cities—Hamburg, London, and Paris. Table 6. Mortality from measles in Hamburg, London, Paris (per 100,000 population). Years: Hamburg, London, Paris. 1851-1860: 123, -, 36; 1861-1870: 31, -, 33; 1871-1880: 21, -, 29; 1881-1890: 23, -, 25; 1891-1900: -, -, 22; 1906-1910: 29; 1911-1913: 29; 1925-1928: 29. Mortality from measles has noticeably decreased in Hamburg; in London, it remained at approximately the same level for 60 years, and only in recent years has a certain decrease been noted; in Paris, it continues to remain high in the current century as well. This table gives an idea of the difference in the height of mortality from measles in one and the same Table 7.
MAP OF MORTALITY FROM MEASLES IN LARGE CITIES OF EUROPE in 1926-28 on average per year per 100,000 population. 0.7-2.0, 2.1-5.0, 5.1-10.0, 10.1-20.0, 20.1-43.1. Fig. 6. of measles (per 100,000 population) for some cities in recent years. Fig.
although somewhat less than in the second half of the 19th century. Compared to other European cities, Moscow and Leningrad have continued until recently to show a very high mortality rate from measles. Table 7 shows the mortality rates for various cities around the world (see also Figure 6). In this same table, which covers a small period of time, one can see, for the majority of cities, the fluctuations in the height of mortality by year that are characteristic of measles. These fluctuations are very weakly expressed in Leningrad and Moscow, which are distinguished by very high mortality rates for all years, as well as in Glasgow, Manchester, and Paris. Extremely sharp fluctuations are noted in some of the non-European cities listed in the table.
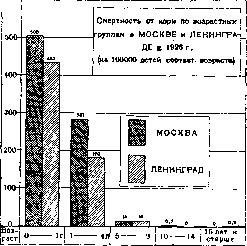
2. Mortality by age and sex. The main mass of those who died from measles falls on the age under 4 years; in the cities of the European part of the USSR in 1926, this age accounted for 96% of all those who died from measles (see Infectious diseases, Table 7, Figure 3). Per 100,000 population of the corresponding age, the number of deaths from measles in Moscow and Leningrad in 1926 was (Table 8, Figure 7):
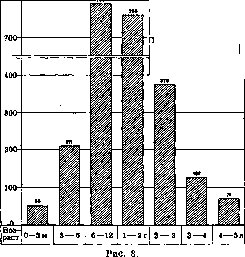
Table 8. Leningrad and Moscow. Age 0-1 year: Leningrad 805.4, Moscow 433.2. 1-4 years: Leningrad 281.7, Moscow 179.1. 5-9 years: Leningrad 14.3, Moscow 15.4. 10-14 years: Leningrad 0.7, Moscow 0.0. 15 years and older: Leningrad 1.1, Moscow 0.2. In relation to the population of the corresponding group, the highest mortality from measles falls on the age under 1 year. In Germany for the years 1925-27, per 100,000 people of the corresponding age and sex, the number of deaths from measles was:
Table 9. Mortality from measles by age and sex in Germany in 1925-27. Age 0-1 year: Men 1925: 128, 1926: 105, 1927: 128; Women 1925: 118, 1926: 105, 1927: 118. Age 1-4 years: Men 1925: 45, 1926: 45, 1927: 45; Women 1925: 43, 1926: 43, 1927: 43. Age 15-30 years: Men 1925: 0.1, 1926: 0.02, 1927: 0.1; Women 1925: 0.1, 1926: 0.1, 1927: 0.1. Age 31-60 years: Men 1925: 0.04, 1926: 0.04, 1927: 0.03; Women 1925: 0.1, 1926: 0.04, 1927: 0.03. Age 61-70 years: Men 1925: 0.1, 1926: 0.1, 1927: 0.1; Women 1925: 0.05, 1926: 0.05, 1927: 0.05. Age 71 years and older: Men 1925: 0.2, 1926: 0.3, 1927: 0.4; Women 1925: 0.2.
Most children die from measles at the age under 1 year. Isolated cases of death are observed even at an advanced age. Table 10 provides mortality rates by age and sex groups in England and Prussia (according to Prinzing) per 100,000 population of the corresponding age and sex.
Table 10. Age 0-1 year: England (1891-1900) Men 292, Women 297; Prussia (1892-1919) Men 119, Women 118. Age 1-2 years: England Men 582, Women 555; Prussia Men 155, Women 154. Age 2-3 years: England Men 94, Women 94; Prussia Men 47, Women 47. Age 3-4 years: England Men 1.7, Women 1.8; Prussia Men 1.7. The highest mortality falls on the age from 1 year to 2 years. At the age under 2 years, boys show a slightly higher mortality rate than girls. Table 11 (Figure 8) provides mortality rates from measles in Paris from 1904 to 1913 by more fractional age groups.
Table 11. Mortality by age in Paris in 1904-13 (average per year per 100,000 children of the corresponding age). Age 0-3 months: 52.6. Age 3-6 months: 210.6. Age 6-12 months: 789.8. Age 1-2 years: 757.5. Age 2-3 years: 376.1. Age 3-4 years: 126.7. Age 4-5 years: 70.7. Age 0-1 year: 427.0. Age 0-3 years: 511.9. Age 3-5 years: 99.1. Age 0-5 years: 348.3. At the age under 3 months, mortality from measles is very low; it is significantly higher at the age from 3 to 6 months, and is highest at the age from 6 months to 2 years; subsequently, with increasing age, it decreases.
3. Case fatality rate for measles. Establishing the case fatality rate for measles is a difficult task. Calculating the case fatality rate in relation to registered patients does not give exact figures, because not all measles patients are registered. Hospital case fatality is higher than the actual one, because only the most severe measles patients are hospitalized. Case fatality rates calculated on the basis of hospital data therefore need a correction in the direction of reduction. Binshok collected materials on case fatality in Leningrad hospitals for the period 1886-1926. The case fatality rate for measles during this period averaged 16%. By five-year periods, it showed the following fluctuations: Table 12. Case fatality for measles in Leningrad hospitals.
Years 1886-1890: 2.7. Years 1891-1895: 5.3. Years 1896-1900: 15.7. Years 1901-1905: 20.8. Years 1906-1909: 17.3. Years 1910-1914: 17.1. Years 1915-1921: 21.3. Years 1922-1926: 13.0. * Without data for 1917 and 1918. The case fatality rate for measles shows large fluctuations depending on the age of the patients. Table 13 (Figure 9) shows the corresponding indicators for St. Petersburg hospitals for 1886-1909.
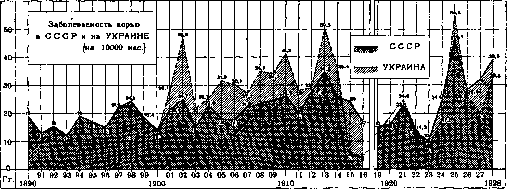
Table 13. Case fatality for measles in St. Petersburg hospitals by age groups. Age: Under 5 years: 1886-90: 14.3, 1891-95: 16.5, 1896-1900: 33.0, 1901-05: 36.7, 1906-09: 28.4. Age 6-10 years: 1886-90: 3.9, 1891-95: 2.3, 1896-1900: 7.6, 1901-05: 10.3, 1906-09: 4.5. Age 11-15 years: 1886-90: 1.6, 1891-95: 1.0, 1896-1900: 3.1, 1901-05: 5.6, 1906-09: 3.8. Age 16-20 years: 1886-90: 1.7, 1891-95: 1.5, 1896-1900: 2.5, 1901-05: 3.3, 1906-09: 4.4. Age 21-30 years: 1886-90: 1.2, 1891-95: 2.0, 1896-1900: 3.2, 1901-05: 2.8, 1906-09: 4.2. Age 31 years and older: 1886-90: 3.3, 1891-95: 3.4, 1896-1900: 4.6, 1901-05: 3.6, 1906-09: 12.0. The highest case fatality for these years was observed in the children's group under 5 years.
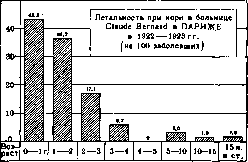
In Table 14, the case fatality by age groups in Paris hospitals is given. The highest case fatality for measles is observed at the age under 1 year, and in individual hospitals, up to 64% of all children of this age died. The case fatality is also very high at the age from 1 year to 2 years, reaching 50 percent of all patients. With increasing age, it noticeably decreases (Figure 10). 4. Morbidity. In the USSR, from 400,000 to 500,000 cases of measles are registered annually, or from 30 to 40 cases per every 10,000 population (see Infectious diseases). Measles is registered at approximately the same level in other countries as well. Thus, in 1926 and 1927, per every 10,000 population, the number of registered measles patients was: in Denmark 37 and 53, in the United States of America 60.1 and 37.6, in Canada 47.3 and 29.6. In absolute figures, the number of registered measles patients by individual countries is shown below in Table 15.
A comparison of the figures of registered patients by individual years also gives a clear idea here of the fluctuation in the height of measles waves. The smaller the country, the more clearly these fluctuations appear. Morbidity in Table 14. Died per 100 patients: Hospitals: Enfants-Malades, St. Louis, Claude Bernard. In all hospitals. Years of observation: 1886-1889, 1893-1898, 1914-1923, 1922-1923, 1912. Age 0-1 year: 43.3. Age 1-2 years: 36.2. Age 2-3 years: 17.1. Age 3-4 years: 5.7. Age 4-5 years: 0. Age 0-2 years: 38. Age 2-5 years: 14. Older than 5 years: 4.183.
1923.
1924. (Asian republics, Dagestan, etc.) follow. Central-Chernozem 9.9. Lower-Volga 20.0. Vyatka-Vetluga 7.5. Bashkir Republic 6.9.
This can perhaps be explained by less complete registration of patients in them. 5. Morbidity by age and sex is illustrated in Table 19 (Fig. 12). Table 19. Morbidity by age and sex in Moscow Governorate and in Moscow in 1926 (per 10,000 population of the corresponding group). Most children contract measles at the age under 5 years; significantly fewer from 5 to 9 years; over 15 years, measles is encountered in isolated cases. However, measles is a "childhood" disease only insofar as almost everyone contracts it in childhood, and subsequently it leaves a lasting immunity. In those places where measles has for some reason been absent for a long time, everyone who has not had it contracts it regardless of age (see above). During the World War, measles caused a fairly significant morbidity in the troops. Thus, in the French army for the period from 1915 to 1918, the number of those who fell ill and died from measles and other "childhood" diseases was: Table 20. Diphtheria; Diseases and mortality Measles Scarlet fever Number of cases... 76,081 35,010 26,065 Number of deaths... 1,470 662 650 Lethality (per 100 cases)... 1.93. More people fell ill and died from measles than from scarlet fever and diphtheria combined. In the army, the number of cases was 5 times higher than among the entire population. This is explained by the large influx into the army of residents from rural areas who had not had measles.
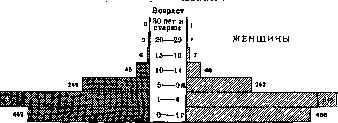
6. Morbidity and mortality from measles in cities and rural areas. Measles is, as a rule, registered in cities higher than in rural areas. Table 21 shows the indicators of measles morbidity in cities and rural areas of the RSFSR for 1924-1927. For comparison, the same indicators for whooping cough are provided. The highest mortality from measles and whooping cough is observed in the poorest families. Bertillon calculated the mortality per 10,000 inhabitants in different parts of Berlin (1886-95), Vienna (1891-97), and Paris (1886-95). For measles and whooping cough, these figures are given in Table 23. Table 21. Per 10,000 population. Years. Measles: Cities, Rural areas. Whooping cough: Cities, Rural areas. The difference in morbidity from both of these infections in cities and rural areas is large. Mortality from measles in cities is also higher than in rural areas. It amounted per 100,000 inhabitants in Württemberg (1899-1902): in cities with a population of over 10,000 inhabitants—23.7, in the rest of the country—21.4; in Upper Bavaria (1899-1902): in cities—34, in rural areas—22; in England (1897-1901) per 100,000 children under 5 years in cities: 388 for boys and 358 for girls, in rural areas—143 and 130. In France (1906-13), deaths from measles per 100,000 inhabitants were: in Paris—23.5, in cities with a population from 30,000 to 1 million—16.4; in cities with a population from 5,000 to 30,000 inhabitants—10.4, in communes with a population below 5,000 inhabitants—6.6. Table 22 provides data on mortality from measles in cities and rural areas of the North American United States (per 100,000 population). Table 22. Populated areas | 1900 | 1905 | 1910 | 1915. Figure 15. Measles morbidity by age and sex in Moscow in 1926 (per 10,000 people of the corresponding group). Cities... 16.4. Rural areas... 9.8, 9.1, 3.4, 13.4: 7.1, 11.6, 3.4. This fact—higher morbidity and mortality from measles in cities than in rural areas—is noted everywhere with rare exceptions.
7. Measles and social factors. Measles, like whooping cough, belongs to those childhood infectious diseases in which the role of the social factor is most strongly expressed. Neefe compared the mortality from childhood infections per 10,000 children under 15 years of age in different parts of Budapest for 1881-90 depending on the average annual income. Table 23. Mortality from measles and whooping cough depending on prosperity in Berlin, Vienna, and Paris (per 10,000 inhabitants). Very poor, Poor, Well-to-do, Very well-to-do, Rich, Very rich. Table 24. Percentage of persons with crowded apartments. Died from measles per 100,000 children under 1 year: in hospitals, at home, total. Rich, Well-to-do, Poor. High lethality. Table 25 shows the lethality from measles in the city of Glasgow for 1893-1912 depending on the number of rooms in apartments. Table 25. Number of rooms in an apartment... 1, 2, 3, 4 and more. Lethality (per 100 cases)... 9.2, 4.6, 2.5, 1.5. Higher lethality in poorer apartments is explained by a lack of air, light, and worse care for the sick and, as a result of all this, more frequent complications from measles. 8. Seasonality of the spread of measles. Figure 13 shows the monthly distribution from March to June, the minimum falls on September and October. For the RSFSR and Ukraine, the minimum also falls on September, the maximum number of cases is noted in the winter-spring period.
I. Dobreytser. Pathological anatomy. Pathological-anatomical changes in measles, if one does not count the skin rash, are concentrated predominantly (often almost exclusively) in the respiratory organs, which are the most vulnerable to this infection. They arise even in the prodromal period in the form of a catarrh of the upper respiratory tract, which is common for this period and which, in cases of moderate severity, lasts until the rash fades or slightly longer. In a more severe course, this catarrh may be accompanied by necrosis of the superficial layers of the mucous membrane, and the process takes on such a necrotic character most often in the larynx (especially in the area of the vocal cords), but it often also captures part or all of the trachea, and sometimes spreads to the large bronchi. The mucosa in this case loses its luster, becomes turbid, rough, and seems as if sprinkled with fine, crumbly gray decay. Where the necrosis goes beyond the limits of the epithelial covering and captures the connective tissue base of the mucosa, ulcers form with the same grayish, uneven necrotic floor. These ulcers are usually not deep and do not go beyond the mucosa, but they can persist for quite a long time (2-3 weeks or more) without changing their necrotic character and showing very little tendency toward cleansing and healing. Often, purulent perichondritis develops on this basis, leading to the necrosis of the underlying cartilage and the formation of purulent cavities of various shapes and sizes in the wall of the larynx. Catarrh of the upper respiratory tract can easily spread down the mucous membrane of the bronchial tree, causing bronchitis, bronchiolitis, and catarrhal bronchopneumonia. However, in their pure form, these forms, apparently due to the relative ease of their course, by no means figure as often as autopsy findings. Pathological-anatomical studies mainly receive more severe cases, where the process quickly takes on those special features that are rightly considered most characteristic of the pathological-anatomical picture of measles. The essence of these features lies in the great tendency of the inflammatory process to penetrate into the depth of the tissues, due to which the inflammatory changes are not limited to the mucous membrane of the bronchus, but also capture its elastic-muscular wall and peribronchial tissue. Thus, in the acute period, in addition to the appearance of catarrhal exudate in the lumen, one can always observe strong dilation of blood vessels here, as well as some edema and a more or less sharp (predominantly round-cell) inflammatory infiltration both of the bronchial wall itself and especially of the tissue surrounding it. And since the penetration of the virus into the depth occurs most easily and quickly where the mucosa is most delicate and permeable, i.e., in the smallest branches of the airways, it is natural that in these latter, inflammatory changes in general, and in particular the formation of infiltrative cellular clusters around the lumens, are most strongly expressed. The development of these infiltrates turns the bronchial wall together with the surrounding tissue into one continuous, wide cellular cuff and leads to the fact that on the cut surface of such a lung, the bronchioles become distinguishable to the naked eye in the form of small grayish spots. Edema and infiltration are usually not limited to the peribronchial tissue but spread further to the adjacent alveolar septa, giving a more or less wide belt of interstitial pneumonia. To the latter, due to the appearance of effusion in the affected alveoli, an exudative one is often added, which usually bears the so-called desquamative or fibrinous, less often catarrhal character. In this way, a new pneumonic cuff forms around the affected bronchus, merging closely with the first and giving on the cut of the lung a larger grayish or yellowish-gray focus (so-called peribronchial pneumonia). With widespread damage to the respiratory tract, such foci can merge with each other, leading to extensive, sometimes lobar and even total consolidation of the lung. A histological feature of these pneumonias is the frequent presence in the affected alveoli (mainly in young children up to 2-3 years old) of multinucleated giant cells, originating from the alveolar epithelium and sometimes very numerous (giant-cell pneumonia). The process just described in the deep layers of the bronchial wall is very prone to taking a protracted course, spreading along the peribronchial lymphatic pathways and gradually capturing larger and larger branches. Where the changes exist for a longer time, the hyperemia gradually subsides, the infiltrate becomes drier, denser, turning first into granulation and then into fibrous connective tissue. Sections of such bronchi on the cut of the lung have a paler, whitish-gray color and stand out even more clearly, very much resembling tubercular tubercles, from which they differ only in that upon careful examination (especially with a magnifying glass) one can almost always notice a central lumen in them; microscopically, in such bronchi, metaplasia of the cylindrical epithelium into stratified squamous epithelium is often observed. Interstitial changes in the adjacent alveolar septa lead to their thickening, and the exudate located in the bronchioles and alveoli often does not resolve but stagnates, undergoing organization over time and causing the collapse and carnification of the corresponding sections of the lung. The course of measles bronchitis and peribronchitis, especially in its acute period, can at any moment be complicated by a necrotic process, similar to that observed in the larynx and trachea, and also localizing predominantly in the smallest bronchial branches. Here, the entire wall of the bronchiole usually undergoes necrosis, and often the peribronchial tissue with a greater or lesser number of adjacent alveoli, especially if there are pneumonic changes in the latter. Thus, in shape, these necrotic foci correspond to the outlines of the peribronchial cuffs and are well distinguished on lung sections due to their dry appearance and pale, sometimes almost white color, and in the latter case, they often strike one with their similarity to tubercular caseous foci (pneumonia morbillosa pseudo-caseosa). If the walls of bronchial branches that are still passable for air undergo necrosis, then bronchiectatic dilations easily develop in them (on the one hand due to the loss of elasticity by the walls, on the other hand under the influence of coughing shocks and the associated frequent and sharp increases in pressure in the airway system), either diffuse or more limited, depending on the spread of the necrotic process. Sometimes foci of necrosis appear in pneumonic areas independently of the bronchial system. Characteristic of measles is the tendency of necrotic masses, wherever they appear, to undergo putrid decay, as a result of which, in severe measles lesions, gangrene of the lungs often develops, and less often gangrenous laryngitis. Similarly, purulent melting of tissue is possible, which almost always begins from the wall of the bronchus and leads to the emergence of sometimes very large abscesses. The outcomes of necrotic and purulent processes are particularly unfavorable in terms of restoring the normal structure and function of the organ. In place of the necrotic bronchial wall, a more or less wide zone of granulation tissue always develops, and if this occurs over a significant extent (which is exactly what happens most often), then epithelialization of the necrotic surface turns out to be very difficult, and such a bronchus in most cases is doomed to obliteration (bronchitis et bronchiolitis obliterans). In this case, the initially hollow granulation cylinder turns into a solid one, the corresponding part of the pulmonary parenchyma collapses, the exudate that was in the alveoli, as well as the necrotic sections of lung tissue, undergoes organization, and in the end, all signs of the former structure disappear without a trace in the resulting scar focus. It should be noted that all the described changes in the respiratory organs in severe, protracted lesions are for the most part combined with each other in the most diverse combinations and varying sequences, creating extremely motley and bizarre pathological-anatomical pictures. The entire process can drag on for months, even years, leading to the development of extensive scars, located mainly along the course of the vascular-bronchial bundles and interlobular pulmonary septa.
Very often, measles lesions of the lungs are complicated by lesions of the pleura in the form of fibrinous, purulent, or productive obliterating pleurisy. In general, diseases of the respiratory organs figure as the cause of death in measles in more than 70% of all cases reaching autopsy. The digestive tract is affected in measles much less intensely and more rarely. True, catarrhal angina and pharyngitis are a fairly common phenomenon, but they take on a necrotic character only as an exception; occasionally, catarrhal, aphthous, or even ulcerative stomatitis are encountered. The reaction on the part of the cervical lymph glands is also moderate. Thanks to this, secondary suppurative processes in the soft tissues of the neck (phlegmons, purulent lymphadenitis, retropharyngeal and lateral pharyngeal abscesses) are not often encountered here. Much more characteristic for measles is the involvement of the large intestine, found in approximately 20% of all measles autopsies. As a rule, these are catarrhal colitis with mucous (much more rarely mucopurulent or bloody) discharge. Their significance lies mainly in the fact that in the case of prolonged existence, they can cause severe exhaustion and intoxication and in this way contribute significantly to a fatal outcome. The presence of a fibrinous or ulcerative process in the intestines should always raise suspicion of a superimposed dysentery, and only after the latter has been excluded can it be attributed to measles. Otitis in measles, in contrast to scarlet fever, almost never leads to damage to the adjacent bone parts (mastoid process, pyramid of the temporal bone)—a circumstance all the more worthy of attention because the causative agent of them (as well as other purulent inflammations in measles) very often turns out to be streptococcus. Among the later measles lesions, it is necessary to mention noma (see). It is usually encountered in children exhausted by prolonged painful processes in the respiratory organs or intestines. Changes in the skin during the measles rash do not present anything specific. This is a focal inflammatory process, expressed in hyperemia, edema, and cellular infiltration of the corresponding sections of the cutis propria, mainly its upper layers. The infiltrates are most strongly expressed around the vessels, less so around the excretory ducts of the sebaceous and sweat glands. In the epidermis, corresponding to the inflammatory foci, edema, leukocyte infiltration, and degenerative changes of the cells are noted, often reaching necrosis (so-called focal necrosis of the epidermis). Subsequently, the altered epithelial cells undergo accelerated and irregular keratinization (parakeratosis), as a result of which the degenerative-necrotic foci turn into horny ones, which are gradually pushed upward by the normal epithelial tissue growing from below and finally are shed in the form of small branny scales. By this time, the inflammatory phenomena in the connective tissue layer of the skin also subside. Filatov-Koplik spots, appearing on the oral mucosa, owe their origin to the same changes that characterize the skin rash. The epithelium of the mucosa here also undergoes degeneration and partial necrosis with subsequent irregular keratinization. And since both necrosis and keratinization deprive the epithelial layer of transparency, the underlying vascular network at the corresponding site ceases to show through, which gives the spots their characteristic whitish color.
M. Skvortsov. Clinical aspects of Measles. The pathogenesis of Measles is still insufficiently studied. The unusual cyclicity of the process, the nature of the skin manifestations, the reaction from the glandular apparatus, the blood picture, the state of the cardiovascular apparatus—all this gives a number of authors the right to consider Measles a "specific reactive (serum-type) disease," similar to smallpox (Moro, Pirquet). The virus (microbe or toxin) has a peculiar elective property of affecting some systems and affecting others very little. The most vulnerable systems are the digestive tract, the respiratory tract, and the glandular apparatus. The cardiovascular apparatus is little affected. Regarding the nervous system, the animal part is affected with moderate intensity; peripheral lesions are a great rarity; on the part of the autonomic nervous system, a peculiar state of increased vagotonia is noted. By this peculiar vagotropic influence of the virus, one can explain to a certain degree both the electivity in the affection of the system (respiratory and digestive tracts, mucous membranes) and the similarity of the picture of skin changes and blood to the manifestations of serum disease (state of vagotonia). In complications, besides the influence of the virus (toxin) on the epithelium of the respiratory and digestive tracts (superficial necrosis) and peribronchial spaces (interstitial processes), a large role is played by the infection of the organism by other microbes—diplococcus, streptococcus, influenza bacillus, as well as the state of reduced resistance of the organism to various microbes, in particular in relation to tbc (anergy according to Pirquet), which is characterized by the fading of the tuberculin skin reaction. Course and symptoms. A typical case of moderate severity. The incubation period is on average 8-10 days. Shorter and longer incubation periods are encountered rarely. Recently, in connection with the use of convalescent serum according to Degkwitz, cases of prolongation of the incubation period (up to 3 weeks) have been described. The incubation period is clinically usually manifested by nothing, although some authors have observed in patients during it instability in weight and some fluctuations in temperature. Most characteristic are the changes in the blood picture; they show that during this period very lively processes occur in the organism, which serve as an indicator of the mutual reactions of the microbe and the human organism. Prodromal period (period of precursors). The first symptoms of this period are: rise in temperature and catarrhs of the mucous membranes. Temperature rises sometimes reach 39° with tenths. Temperature fluctuations are quite significant. Having held at high figures for 1-2, more rarely 3 days, the temperature gives a significant drop, and sometimes even a fall to normal, which usually precedes the beginning of the eruption. With the appearance of the rash, the temperature rises quite high again (Figure 14). This peculiar wave is very typical for the measles process. In a number of cases, especially in small atrophic children and in adults exhausted and weakened by other diseases, the fever may be weakly expressed and proceed atypically (Fig. 15). In parallel with the rise in temperature, a picture of moderate general intoxication appears: lethargy, lack of appetite, headache, in children caprices, restlessness, poor sleep, irritability. Catarrhs of the mucous membranes involve the conjunctiva, nose, and larynx. The conjunctiva reddens, photophobia appears, lacrimation intensifies; the eyelids swell; subsequently, a catarrhal-purulent discharge appears, so that in the mornings the eyelids in children stick together and are glued by purulent secretion. From the nose, at first weak, then abundant mucous, later mucopurulent discharge; sneezing. The face becomes somewhat puffy, and the entire appearance of the patient with red, festering eyes, swollen eyelids, lacrimation and salivation, and discharge from the nose becomes very characteristic. Laryngitis can be very diverse in intensity (see below—complications). Very characteristic and having great diagnostic significance is the symptom described for the first time by N. Filatov in 1895, and later, in 1896, by the American physician Koplik (Filatov-Koplik symptom). This symptom consists of a peculiar bran-like desquamation of the epithelium of the mucous membrane of the lips and cheeks opposite the molars. Upon examination, the mucosa seems as if sprinkled with fine splashes of lime, with small bluish-whitish spots. If one examines them in the early stage, one can notice several small, pinhead-sized, whitish spots, surrounded by a small rim of redness. After a few hours or a day, their number increases, they become coarser, the background merges [see separate table (Vol. XIII, art. 743-744), Fig. 7 and 8]. This is a matter of a peculiar desquamative catarrh of the buccal mucosa. This symptom appears on average 2 days before the rash (Filatov, Molchanov-Bosse, Lautz), but sometimes 4-5-7 days before the eruption. The Filatov-Koplik symptom is unusually specific, is not encountered in other diseases, and sometimes allows for a diagnosis to be made so early that by isolating the patient, one can prevent the infection of other children. Therefore, this symptom has enormous practical significance. The frequency of the symptom is very significant. It may be absent in very small children, especially weak ones, premature infants, atrophic ones, and in the combination of measles with other diseases (e.g., scarlet fever + measles). The presence of stomatitis may obscure it. The Filatov-Koplik symptom can be confused with aphthous stomatitis and thrush (soor); but in the latter case, these spots are white-yellow in color and coarser, there is no rim of redness; in stomatitis, the spots are also coarser and quickly turn into an ulcer. The Filatov-Koplik symptom can last the entire prodromal period, one or two days of the rash, and then disappears. Often its duration is even less. Somewhat later than the Filatov-Koplik symptom, approximately a day before the rash, a spotted-looking redness—enanthema—appears in the throat on the soft and hard palate, which also has great diagnostic significance. Sometimes in the prodromal period, vomiting and loose stools are observed. In some cases, abdominal pain resembling appendicitis, the excretion of pus cells in the urine, yellowish staining of the skin, and early otitis are observed. These phenomena are explained by catarrhs of the mucous membranes of the corresponding organs. Eruption period. At the height of the process, which coincides with the first days of the eruption, there are a number of symptoms typical for Measles, of which 3 are primary: rash, angina, intoxication. Measles rash. The beginning of the eruption coincides with the 12th-14th day from the moment of infection. In rare cases, the rash appears later, on the 16th-17th, or even on the 20th-21st day. The rash appears behind the ears, on the cheeks, on the forehead. At first the eruption is sparse, then within a few hours the rash breaks out more densely all over the face, not sparing the chin and lips, which distinguishes it from the scarlet fever rash, which leaves the lips and chin free of rash ("scarlet fever triangle"). Each rash spot begins with a small papule, especially clearly visible if one looks at the skin under side lighting; in some cases, the papule is quite sharply expressed, clearly protruding above the level of the skin, which is well noticeable if one runs a finger over the skin. Subsequently, the number of individual rash spots increases, each of them becomes larger, flatter, a zone of redness of irregular outline appears around them, and the spots begin to merge. Although so-called confluent Measles is encountered, especially on the back, there is no continuous redness; there always remain free spaces on the affected skin, which, along with the exudative nature of the rash and the affection of the eyes, gives such a characteristic appearance to the face of a measles patient [see separate table (Vol. XIII, art. 743-744), Fig. 6]. The measles rash also breaks out very abundantly on the scalp. By the end of the first to the beginning of the second day, the rash densely covers the face and begins to appear on the torso, where within 1-2 days it undergoes the same process: there is an increase in the number of rash spots and the transformation of papules into maculopapular eruptions merging with each other. The skin between the eruptions, if the rash does not break out very densely, remains unaffected; however, often around the eruptions, the skin has a somewhat cyanotic appearance, and the spot itself is surrounded by a small, peculiar anemic zone.
This is especially sharply noticeable on the extremities and produces a picture very reminiscent of "serum sickness." On the 3rd day from the onset of the eruption, the rash, while remaining very abundant on the face and trunk and often producing entire fields of confluent exudative erythema on the back and chest, begins to involve the extremities, moving from top to bottom and repeating the same cycle of development in each individual rash element. This gradual character of the eruption (from top to bottom: face, trunk, extremities) is very characteristic of measles, just as the cycle of rash development over the course of 3-4 days is characteristic. In this, measles differs from rubella (German measles) and serum sickness, where this gradualness and cyclicity are absent. During the eruption, itching is often observed. In some cases, a day or several hours before the eruption, a so-called "prodromal" rash appears (Vor-exanthem of German authors)—sparse, pale-pink, spotty eruptions on the face, sometimes on the trunk. The measles rash can present many variants, being at times finer or coarser, sometimes merging into entire fields, being colored more palely or more brightly, and being very different in the intensity of exudation into the skin. Often, small and punctate hemorrhages appear on the skin, especially on the flexor surfaces of the extremities. They can sometimes be quite abundant, but if they are not accompanied by severe general symptoms or bleeding from the mucous membranes, they have no particular diagnostic or prognostic significance. The Rumpel-Leede phenomenon is often positive. As rare variants, rashes are observed that take on a pustular character or resemble pemphigus (Heubner). The tendency of the measles rash to erupt in places where there was already hyperemia of the skin, irritation, or any inflammatory skin processes (diaper rash, eczema) is very peculiar. In emaciated subjects, very small children, atrophic infants, in severe states of nutritional decline, and in severe disorders of cardiac activity, the rash may be atypical, sparse, and sometimes cyanotic from the very beginning. French authors describe so-called recurring rashes (recurrent rashes)—eruptions occurring in several stages with intervals of several days.
The skin during measles is usually moist; measles-stricken children are prone to sweating, and the sebaceous glands function normally or with increased activity, which also distinguishes measles from scarlet fever, where the skin is dry and sweating and the function of the sebaceous glands are reduced. As it fades, the rash pigments, leaving behind dark-brown spots of various sizes and intensities at the sites of the eruptions, which can be very valuable for diagnosis in the late stages of the process. The intensity of this process is very diverse; the pigmentation lasts for 1–1 1/2 weeks, sometimes up to 2 weeks. Desquamation is slight, is not observed in all cases, usually has a fine, branny character, and appears more often on the face and trunk; there is no desquamation on the palms and soles, which also distinguishes measles from scarlet fever.
Angina. Changes in the fauces and pharynx appear already at the end of the prodromal period; a few hours or a day before the eruption, it is possible to notice a mild, spotty redness on the soft and hard palate (enanthema). Subsequently, the spots very soon begin to merge, the tonsils swell slightly, and by the moment the rash is in full bloom at the height of the disease, there is a distinct general catarrhal angina. Usually, necrosis is not observed, by which measles sharply differs from scarlet fever. Only in very rare cases in very weakened children and in atrophic infants can one observe phenomena of superficial necrosis of the epithelium, involving the fauces and nasopharynx, sometimes descending into the esophagus and in some cases being the cause of retropharyngeal and lateral abscesses. The tongue is moderately coated, moist, and salivation is increased.
Intoxication. Phenomena of general poisoning are expressed quite distinctly; already in the prodromal period, it is possible to note changes in the patient's mood, restlessness, and irritability. At the height of the disease, these phenomena are even sharper. The child's caprice and restlessness, poor sleep, and sometimes delirium are constant phenomena; in adults, there are complaints of headache and general malaise. However, very severe phenomena with unconsciousness, severe delirium, convulsions, and coma are observed extremely rarely, as are meningeal phenomena. The temperature, in typical cases, gives a very peculiar curve with two rises—at the height of the prodrome and at the beginning of the eruption. During the flowering of the rash, the temperature (remittent) shows quite significant fluctuations, remains as such during the entire time of the eruption, and begins to fall simultaneously with the fading of the rash (4th–5th day from the onset of the eruption), usually critically. However, one can observe many variants in the character of the temperature curve.
Other manifestations of the disease. Peripheral lymph nodes usually do not participate; only in individual cases is it possible to observe moderate general acute lymphadenitis.
Catarrhs of the mucous membranes (conjunctivitis, rhinitis, laryngotracheobronchitis), having begun in the prodromal period, accompany the entire eruptive period and can be expressed very strongly at the height of the disease. However, significant variants are observed here as well. At the beginning of the disease, nosebleeds are not uncommon.
Cough, initially harsh and dry, later becomes moist. It is usually very significant and strongly irritates and disturbs the patient. Upon percussion of the chest, a very characteristic picture of acute emphysema is revealed: the percussion sound is boxy, the heart is covered by the lungs, and their borders are low. The cause of this emphysema has not yet been sufficiently studied. Upon auscultation, there is a significant number of dry rales, and in the period of the height of the disease, often moist rales as well. Stool is usually frequent, of a semi-liquid or liquid consistency, often with an admixture of mucus. This is especially clearly noticeable in infants and small children. The liver is not enlarged and not painful. Rarely, jaundice is noted.
The cardiovascular apparatus is little affected by the measles process. The dimensions of the heart are usually unchanged, the heart sounds are clear, and the pulse at the height of the disease is accelerated in accordance with the temperature. With systematic examination of blood pressure, one can note a certain decrease in pressure in the prodromal period and at the beginning of the eruption, which then levels out. In the convalescence period, arrhythmias are often noted. By this property of relatively sparing the cardiovascular apparatus, measles differs sharply from many infectious diseases in which the cardiovascular apparatus is affected very distinctly (diphtheria, scarlet fever, typhus). And it is these properties that explain the fact that cases of death from uncomplicated measles are almost never observed.
Blood changes are very peculiar (Comby, Hecker, Molchanov-Bosse, Lautz). Already in the incubation period (7 days before the rash), a rise in neutrophils and a fall in the number of lymphocytes begins; soon (6 days before) hyperleukocytosis appears; in the prodromal period, there is leukopenia, eosinopenia, a decrease in the number of neutrophils (4–3 days before), and a shift of the blood to the left according to Arneth-Schilling (4 days). The table below shows how many days before the rash the changes appear.
The table below shows how many days before the rash the changes appear. . ......
The resistance of erythrocytes is not changed (Weil), coagulability
blood is slowed (Gornitskaya). The platelet count is reduced by the time of the eruption and becomes normal by the time the rash fades (Chistovich, Shifer). The blood sugar picture is unchanged. During purulent complications, there is the usual leukocytic-neutrophilic rise, although less sharp than in other infections (e.g., in scarlet fever). The amount of urine at the height of the process is moderately reduced. Sometimes so-called febrile albuminuria appears. A positive diazo reaction is very often found. An increase in urobilin content, in contrast to scarlet fever, is usually not found. The excretion of NaCl is not changed, the ability to concentrate and excrete water is not impaired; in the febrile period, there is some decrease in urea excretion. Phenomena from the central nervous system are moderately expressed. No changes are noted from the peripheral nervous system. The changes in the endocrine-vegetative apparatus are very peculiar. Already in the prodromal period, one can observe a number of symptoms indicating a state of excitation of the parasympathetic division of the autonomic nervous system. These phenomena persist throughout the eruptive period and weaken with the disappearance of the rash. Functional examination of the autonomic nervous system shows that, starting from the prodromal period and at the height of the process, there is a state of active vagotonia, which gradually weakens in parallel with the disappearance of the rash. The adrenal-sympathetic system is weakly affected. Reactions to pilocarpine are sharp, to adrenaline—weakly positive. These data bring measles very close to serum sickness, where a vagotonic syndrome is also seen—a type of disease opposite to that encountered in scarlet fever (Koltypin). When examining the ear with a mirror at the end of the prodromal period and during the eruption, one can find slight hyperemia of the eardrum. In the prodromal period and at the beginning of the eruptive period, photophobia is even sharper in the presence of corneal or conjunctival disease; sometimes there are phenomena of blepharospasm. Course of measles. The duration of the incubation period is on average 8-10 days, the prodromal period 2-4 days (and sometimes even 5-6 days), the eruptive period 3-5 days. Pigmentation lasts 1-1 1/2 weeks. Desquamation is very short-lived. On the 2nd-3rd day of the eruption, all phenomena reach their greatest intensity. With the fading of the rash (4th-5th day), all phenomena begin to subside: the temperature falls, catarrhs weaken, the cough becomes soft, although it may remain for quite a long time; the general condition improves, appetite appears. However, in small children, the lack of appetite persists for a long time, as does the tendency to loose stools and a state of tearfulness and nervous irritability. In the convalescence period, there are mildly expressed disturbances of the heart rhythm. With the fall in temperature, the urine and blood gradually return to normal. In small children, a noticeable weight loss is observed, especially if the process was accompanied by diarrhea, and a state of severe dystrophy often develops as a manifestation of the harmful effect of the pathogen on the tissues of the body and partly of starvation. Forms of measles. From this typical course, measles can show significant deviations. The reasons for this, as in relation to other diseases, remain insufficiently studied: the virulence of the microbe, often associated with the nature of a specific epidemic, sometimes apparently the influence of other microbial groups, then age, constitution, nutrition, and previous illness may play a role here. Measles can present cases of mild and severe courses. The first group includes forms of so-called abortive measles, where all manifestations can be expressed very mildly and the disease ends very quickly. In other cases, the atypicality concerns only one period; e.g., the prodromal period may be expressed very weakly, catarrhs are insignificant, the temperature is not high. Sometimes atypicality concerns the eruptive period—the rash may be very weakly expressed and even absent altogether (measles without rash). Atypical cases are very common in atrophic children and at a very early infant age. These same forms can be observed in adults exhausted by illness or hunger, or in combinations with other infections. In other cases, measles takes a more severe course and can quickly lead to death. A distinction is made between the adynamic, or toxic, form, where phenomena of severe general poisoning and weakness of the cardiovascular apparatus come to the fore; then the pulmonary form, with the very rapid development of severe lesions of the respiratory tract. Very rare are forms of hemorrhagic measles with profuse bleeding from the nose, intestines, and cutaneous hemorrhages, usually ending in death. Death from uncomplicated measles is an exceptional phenomenon. The cause of death is usually complications. Complications. Lesions of the upper respiratory tract (rhinitis, laryngo-tracheo-bronchitis) are constant symptoms of measles. They can be called complications if they take a severe course, become exacerbated, or reappear after disappearance. Rhinitis only in rare cases takes a severe course or produces a necrotic form. In some cases, already in the prodromal period or in the eruptive period, the usual measles laryngitis takes a more severe course: the cough becomes dry and barking, difficult noisy breathing appears, and a picture develops resembling true diphtheritic croup, clinically differing from it only by the more rapid development of all symptoms, the absence of plaques in the throat, and negative data in relation to Bacillus diphtheriae. The process can reach asphyxia and require surgical intervention (intubation, tracheotomy). However, these measures rarely have an effect, as this is a necrotic process in the larynx. Whether the cause of these necroses is the measles pathogen itself, or a toxin, or whether other microbes play a role here, remains insufficiently clarified. As a result of this process, ulcers form in the larynx, which cause reflex spasm (stenosis), and with intubation (as well as with tracheotomy), they cause pressure sores, making extubation and removal impossible. In both cases, pneumonia easily develops, and the matter ends in death. Children are especially prone to this complication at the age of up to 3 years. One must distinguish from it true diphtheritic croup as a secondary, but very common disease in measles, since measles creates an increased susceptibility to diphtheritic infection. This true diphtheritic croup, developing later, usually in the pigmentation period, has a somewhat slower course. Upon inspection of the mucous membranes, one can often note plaques in the throat or nose; a culture yields growth of Bacillus Loffleri. Inflammation of the lungs is one of the most frequent complications. Mortality from measles in children in the vast majority of cases depends on pneumonia. Pneumonia can appear very early, at the very beginning of the eruptive period. These cases are usually the most severe and the most typical in their clinical picture and pathological-anatomical changes. However, pneumonia can join measles also in the pigmentation period, after the fall in temperature. If pneumonia develops early, in the eruptive period, in the presence of high temperature, its recognition can present significant difficulties: pneumonia is indicated here by accompanying shortness of breath, which intensifies with movement, flaring of the nostrils, and sometimes cyanosis of the lips, face, and extremities. Upon percussion, the chest gives a boxy sound (tympany); due to acute emphysema, the heart is covered; upon auscultation, there are many dry, and mainly moist, fine ringing and subcrepitant rales, especially concentrated in the posterior parts of the lungs. Breathing is vesicular. Later, focal phenomena may join in connection with the merging of small foci into larger ones (shortening of the sound, bronchial breathing). In parallel with this, phenomena of cardiac weakness increase—the pulse is frequent and weak. The liver enlarges; the patient may die within 2-4 days from the onset of the disease. Measles pneumonias can, however, have a longer, and sometimes even a very long course (several months) with prolonged irregular fever, further complications (pleurisy, empyema), exhaustion, and again lead to death or cause severe changes in the lung (carnification, abscess, cavity, putrid bronchitis, gangrene). Bacteriologically, various microbes are found, most often the Fraenkel diplococcus and diplostreptococcus. In later periods of measles, pneumonias can proceed in the usual forms—lobular, less often lobar pneumonias. As complications of pneumonia, dry pleurisy, empyemas (diplostreptococcus), lung abscesses, and bronchiectasis are observed. Digestive tract. Complications from the mucous membrane of the mouth are very common. Already at the beginning of the eruption, a peculiar desquamative catarrh can turn into widespread stomatitis of the aphthous, and sometimes ulcerative, type, which makes feeding a small infant very difficult. In atrophic children, one sometimes finds widespread superficial necrosis of the epithelium of the mouth and pharynx. The lips in children often crack and become covered with dirty-colored plaques-necroses (staphylococcus!). Especially dangerous is the complication known by the name of noma (see). Lesions of the gastrointestinal tract in early age very often take a severe course and can be the cause of death.
Dyspepsia in infants and loose stools in older children, and not infrequently in adults, are a very common phenomenon at the beginning of the process. These disorders can sometimes drag on for the entire duration of the disease. Often these diarrheas take on the character of colitis (mucus, tenesmus, sometimes blood); in their course, they differ little from ordinary infectious colitis, increasing the exhaustion of the patient. They last
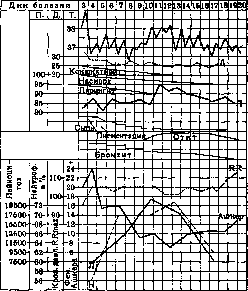
Figure 16. A case of measles complicated by otitis.
a very indefinite time. Bacteriologically, these colitides in some cases are due to infection with the dysentery bacillus; more often, it is obviously a matter of the influence of the measles contagion itself. Complications from the nervous system are quite rare. In recent years, a number of reports have appeared on encephalitis after measles (29 cases collected by Bosse). The process most often develops during the period of fading of the rash, accompanied by new rises in temperature and cerebral phenomena. The cerebrospinal fluid shows no changes and is sterile. In a number of cases, complete recovery was observed; in others, mental retardation developed. Opinions on the genesis differ. It is possible that the process is connected with the effect of the measles poison (toxin) on a particularly vulnerable and prepared soil (Bosse). As very rare phenomena, peripheral paralyses have been observed. Purulent meningitides of otogenic character may be observed. Nephritis is observed very rarely; pyelitis is more frequent, especially in small children. -- Sense organs. A frequent complication is otitis. It can be serous and purulent. Otitis can appear already at the beginning of the eruption period, but more often by the moment of the temperature drop in the pigmentation period (Fig. 16). Otitis is usually accompanied by a sharp rise in temperature, often with pain and shooting sensations in the ear, and leukocytic-neutrophilic shifts in the blood. Unlike scarlatinal otitis, its course is more benign, although streptococci are also often found in the pus. In general, about 60% of otitides in children do not reach suppuration (Polteva); therefore, in exudative acute measles otitis, one should not rush with paracentesis. Mastoiditis is an extremely rare complication. Regarding the eyes--blepharitis, but lesions of the cornea and vascular tunic are rare. The measles poison lowers the general resistance of the organism; therefore, in measles convalescents, various skin lesions (abscesses, furunculosis, phlegmons) are often observed. The influence of the measles poison on chronic infection is very peculiar. Apparently, any acute infectious disease superimposed on a chronic one (tuberculosis, syphilis, malaria, rheumatism) can cause an exacerbation of the chronic process and trigger an outbreak. Measles possesses special properties to cause these exacerbations mainly in relation to tuberculosis (anergy). Outbreaks of miliary process and the appearance of local forms of tuberculosis in children have been described repeatedly after measles. The situation is apparently the same in relation to syphilis, malaria, and gonorrhea (Pirquet, Danilevich). -Mixed infections. Measles, like any other infectious disease, can have a concurrent course with another infection. This is more often observed in conditions of hospital treatment of children. Combinations of measles and scarlet fever, measles and diphtheria, measles and chickenpox, and a number of other rarer, sometimes even triple combinations, are frequently encountered. Usually, such combined cases proceed more severely, as if summing up their harmful effects. The course is especially unfavorable when measles precedes another infection, which is especially noticeable in relation to diphtheria, which usually proceeds more severely in measles patients. Diagnosis. For diagnosis, the incubation period, the presence of prodromes (catarrhs), the character of the rash (maculopapular), the peculiarity of the eruption (three-day cycle), pigmentation, and the absence of necrosis in the throat are of importance. In the blood--leukopenia, slowing of coagulation, thrombocytopenia. Of particular importance in the prodromal period is the Filatov-Koplik symptom, which is not encountered in other infections. Differential diagnosis can present significant difficulties in relation to a number of diseases from the group of so-called acute infectious exanthems. - Rubella (rubeola morbillosa). Differences: the incubation period is longer (17-21 days), there is no prodrome or Filatov symptom; catarrhs are negligible; the character of the rash is small-spotted, the color is more pink, the eruption starts immediately from the trunk; in the throat there is negligible hyperemia, pigmentation is almost absent; swelling of the posterior cervical and occipital glands is typical, there are plasma cells in the blood, there is no thrombocytopenia. The course is benign, usually without complications. - Serum sickness can present significant difficulties for diagnosis. Differences: in the anamnesis, injection of serum, the time of appearance of the serum rash is no later than 3 weeks from the moment of injection, the eruption proceeds from the site of injection, general swelling of the glands; there are no catarrhs, Filatov-Koplik symptom, or angina; the rash is of a more exudative character. -Septic rashes. Presence of a source of sepsis (erysipelas, preceding disease, otitis); temperature of septic type, chills, more often high hyperleukocytosis of neutrophilic character (but leukopenia can also occur), positive data from blood culture from a vein, frequent involvement of joints, septic pyemias, especially in small children, absence of catarrhs. The character of the rash is diverse--the rash is sometimes spotted, sometimes maculopapular, there is no cyclicity of eruption. Initially, measles can be confused with smallpox when papules erupt abundantly on the face and catarrhs are not sharp. Differences: no signs of previously vaccinated smallpox, severe course, enlargement of the spleen, absence of catarrhs and Filatov-Koplik symptom, hyperleukocytosis of monocytic character, drop in temperature at the beginning of the eruption. -In rare cases, measles can be confused with typhus. Prognosis and hospital mortality. The prognosis is determined by age, nutritional status, form of the disease, and the presence or absence of chronic infection. The younger the child, the more serious the prognosis, as mainly small children become victims of complications from the respiratory and digestive organs. Measles in a child younger than 3 years is always a dangerous disease. In older children and adolescents, measles becomes dangerous when it affects a child exhausted and weakened by other infections. It is especially dangerous for the tuberculous. For adults, it can be dangerous during epidemic outbreaks affecting areas where there has been no measles for a long time, and in subjects with nutrition weakened by hunger, diseases, or deprivation. Hospital mortality, which has been more accurately developed among children, is about 15-20%; in children under 2 years, it is significantly higher (40-60%). This high percentage is explained by the fact that almost exclusively severely ill children or those with pulmonary and intestinal complications end up in the hospital. Treatment. General measures of hygiene, care, and dietetics are of enormous importance. The room temperature should be moderate (15-18°); it is necessary to monitor the cleanliness of the air; in summer in warm weather, the patient can be in the open air or with widely opened windows; in cold weather, the room must be thoroughly and systematically ventilated, especially at night. One should by no means darken the light; only in cases of severe photophobia is the patient placed with their head toward the light source, a temporary screen is set up, or an adult is given an eye shade. It is recommended to bathe children daily or every other day, and to wash the face and hands every day. Great importance is attached to the care of the skin and mucous membranes, thorough rinsing of the mouth and throat; the lips are lubricated with boiled vegetable oil; the eyes are washed with 2% boric acid, the eyelids are lubricated with sterile vaseline. - Nutrition of the patient is of great importance in childhood, especially at an early age. For an infant, the most important measure is the preservation of breastfeeding. In the early periods of measles, food should be liquid and semi-liquid. For artificial and mixed feeding--mixtures with carbohydrates (2 parts milk + 1 part rice or oat decoction with 5% sugar); for older ones (after 6-7 months)--tea and coffee with milk, whole milk, kissels; in the presence of intestinal disorders--protein milk with 5-7% sugar, buttermilk with sugar and flour; kefir, concentrated decoction, mixtures of 1/2-2/3 milk with dextrinized flour. For older children--cereals, kissels, broth, cottage cheese, sour milk; abundant drinking. After the temperature drops, one can quickly switch to normal food if there is no liquid stool and appetite appears. In the presence of colitis, it is important not to let the child starve. Food should be wholesome and varied. Diet and treatment--as for ordinary acute colitis (see). Respiratory tract. Clean, fresh room air is of enormous importance. For laryngitis--hot baths (37-40° for 10 min.), for older children--inhalation with a 2% soda solution; in cases of increasing stenosis--bromine preparations, wide ventilation of the room, hot baths, creation of a calm environment around the child. Surgical intervention (intubation, tracheotomy)--only in cases of extreme necessity. In the treatment of pneumonia, the most important thing is to provide the child with the maximum amount of fresh air: constant ventilation of the room with widely opened windows; frequent change of the patient's position is necessary, carrying small children in one's arms. Mechanical cleaning of the oral cavity and throat from mucus is very important in the latter. Hot water procedures [hot baths (40°)] have a good effect; for small children--mustard wraps, for older ones and in cases of vascular disorders--mustard plasters. Compresses that restrict breathing (especially in small children and those with rickets) are not indicated. Internally--alkaline mineral waters (Borjomi), 2% soda solution with milk; in older children with symptoms of dry irritating cough, it is sometimes necessary to use narcotics (Codein, Pulv.
(Doveri). For otitis—5% carbolic glycerin; after paracentesis and in case of spontaneous perforation—standard therapy. Treatment of mastoiditis—according to general rules. Treatment of noma—see Noma. A child may be allowed out of bed, if there are no complications, approximately one week from the onset of the rash. Specific treatment with sera has not yet gained widespread use. Prophylaxis. Prophylactic measures include three tasks: cessation of contact between the sick and the healthy and destruction of the infectious focus (isolation, disinfection), measures to strengthen natural immunity, and measures of specific prophylaxis (active and passive). Regarding the first task, early diagnosis and early isolation of the patient are of great importance. A case removed from a children's group in the early prodromal periods based on the Filatov-Koplik symptom may not entail further illnesses; one removed during the rash period usually leads to the illness of almost all children who have not had measles. Discharge from the hospital without danger to healthy children, according to the rules established by the People's Commissariat of Health, can be carried out after the 7th day from the onset of the rash. Separation of those who have encountered a measles patient is carried out for the incubation period—21 days. For this same period, the admission of children to a group where a quarantine has been declared is stopped. Disinfection is not required; airing and regular cleaning of the premises are sufficient. Measures to strengthen natural immunity include general hygienic and dietary measures. Widespread propaganda of proper hygiene in early childhood is necessary, in particular, the promotion of breastfeeding and the constant stay of children in the open air. However, in view of the insufficiency of all the listed measures, attempts to find ways to create artificial immunity (passive or active) in a child do not cease. This question cannot receive a correct solution until the pathogen is discovered and the nature of immunity is studied. Among the methods of active immunization, it was proposed by Hermann to introduce mucus from the nasal cavity of measles patients into the noses of healthy children; Degkwitz used his culture from the pharynx of patients as a vaccine, and Caronia used a vaccine of the microbe discovered by him. However, these methods have not gained widespread use and cannot be recommended. The Degkwitz method has gained the most widespread use (see Degkwitz vaccinations).
A. Koltypin.
Related articles
Mentioned in
Cite this page
“Measles.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/measles/