Typhus (188 Specific prophylaxis and serotherapy of)
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia defines typhus as an acute, louse-borne infectious disease and details its history, clinical presentation, and the development of experimental models in laboratory animals. It covers the discovery of the infectious agent's presence in the blood and the subsequent use of monkeys, guinea pigs, and other rodents for research.
Encyclopedia article (1928–1936)
188 Specific prophylaxis and serotherapy of typhus. 192 Statistics and geographical distribution of typhus.
Typhus (typhus exanthematicus) (from Greek typhos—smoke, fog, stupor), an acute, louse-borne infectious disease, highly contagious, cyclic, in which the characteristic symptoms are: rapid onset, macular rash, deep lesion of the central nervous and peripheral circulatory systems, constant fever, resolving between the second and third week by shortened lysis or critically. Synonyms: hunger typhus, jail typhus, war typhus. History. The first description of the characteristic signs of typhus belongs to Fracastorius (1483–1553). Next follow the works of Moss, Mantuus, Jordanus, Ambroise Paré, and others, where the distinctive clinical and epidemiological signs of typhus are indicated. However, until the middle of the 19th century, many doctors, including Virchow, denied the existence of typhus as an independent disease. The question was finally resolved thanks to the thorough research of Jenner (1850), Griesinger (1856), Murchison, Wunderlich, Curschmann, and others, who proved by analysis of the clinical picture and epidemiology of typhus that it represents a special specific disease, clearly differing from other typhuses: typhoid and relapsing. Experimental typhus. Mochutkovsky in 1900, having successfully infected himself with the blood of a typhus patient, presented evidence that the infectious agent in typhus is in the blood. The experiment of Mochutkovsky was repeated and confirmed by Otero, Yersin, Vassal, and others. In 1909, Charles Nicolle, Comte, and Conseil in Tunis reproduced experimental typhus in monkeys by infecting them with the blood of typhus patients. The same results were obtained in 1909 by Anderson and Goldberger in Mexico. In 1910–11, Gavino and Girard established that guinea pigs, like monkeys, can be experimentally infected with typhus blood and show a characteristic picture of the disease. The infection in guinea pigs, as in monkeys, is capable of being maintained for an indefinitely long time by passages in fresh animals. The observations of Gavino and Girard were soon confirmed by Charles Nicolle and his colleagues, and developed and deepened by subsequent works of numerous authors. Thus, in the hands of researchers, typhus proved to be a valuable method of studying the nature of this infection on easily accessible material.
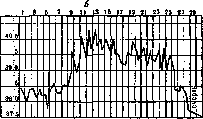
The technique of reproducing experimental typhus in monkeys and guinea pigs consists of injecting them subcutaneously or intraperitoneally with 2–4 cm3 of blood from a typhus patient, taken sterilely from the cubital vein at the height of the disease. The incubation period is on average 8–12 days (fluctuations from 3 to 31 days), the fever period lasts about 1–11/2 weeks (fluctuations from 2 to 16 days). The fever is predominantly of a constant type. It resolves by shortened lysis, with the temperature sometimes falling below normal and returning to normal only after 1–3 days. No other symptoms of the disease, except for fever and a slight drop in weight, are observed in either guinea pigs or monkeys. Experimental typhus in the named animals can be severe, moderate, or mild, as can be seen in the attached temperature curves (Figure 1). Finally, in some cases, the experimental infection can proceed completely asymptomatically in the form of an afebrile sepsis, as was established in 1919 by Ch. Nicolle and Lebailly ('infection inapparente'). The blood of such animals, when inoculated into fresh ones, gives them a typical febrile disease. Monkeys and guinea pigs infected with the blood of typhus patients do not all prove to be susceptible to infection with the human virus. Non-susceptibility in monkeys is sometimes observed in 22% of cases, in guinea pigs—in 44% (Anderson and Goldberger). These figures have relative significance and depend on the origin and individuality of the typhus virus (Barykin and colleagues). Experimental infection of monkeys and guinea pigs is possible not only with typhus blood from human patients but also with organs (especially the brain and spleen) from cadaveric typhus material, which is introduced, in view of its unreliable purity, not into the abdomen but under the skin of the animals.
Experimentally, typhus is capable of being passaged for an indefinitely long time on new animals. The material for passages is blood, brain, or spleen taken at the height of the fever. Usually, for passages, the animal is killed no later than the 3rd–4th day of fever, the sterilely obtained brain (resp. spleen and other organs) is ground in 0.85% NaCl and injected into the abdomen of fresh animals. During passages, the virus adapts to the given animal species, incubation is shortened, the fever becomes more prolonged and higher, the percentage of animals susceptible to the passage virus rises sharply, reaching 90% and higher for monkeys and guinea pigs. Of the internal organs of passage animals, the cerebrum (gray matter) is especially rich in the virus. In some typhus strains, the brain of a passage guinea pig already contains an infectious dose of the virus for fresh guinea pigs. Other strains are less virulent, especially strains isolated from humans during sporadic typhus or obtained in non-epidemic seasons. Such strains, during serial passage through the organism of guinea pigs, not only do not strengthen but gradually fall in their activity, giving an asymptomatic experimental infection by the 5th passage or completely losing the ability to infect guinea pigs. Depending on the individuality of the passaged typhus strain, the mortality among passage animals fluctuates, reaching 18.4% for some strains (Otto and Papamarku strain for guinea pigs). Recent research has established that gophers (Spermophilus) are sensitive to the typhus virus, in which the experimental infection proceeds in the same way as in guinea pigs (Lepine, Grünfeld, Serebryanaya, and Neiman). The study of experimental typhus in monkeys and guinea pigs shows that they are much less susceptible to this infection than humans. Typhus infection in them is reproduced only artificially in a laboratory setting, has a benign course, is accompanied by almost the only symptom—fever, and gives negligible mortality. Experimental typhus proceeds even more easily in rabbits, rats, and mice. In these animals, as shown by the observations of Ch. Nicolle, Comte, and Conseil for rabbits, Doerr, Otto, and Winkler for rats, and Ch. Nicolle for mice, laboratory infection with the typhus virus is expressed in an asymptomatic form of infection. The blood of these animals, taken on the 7th–15th day after their laboratory infection, when introduced into the abdomen of guinea pigs, causes in the latter a typical febrile attack of experimental typhus. Rabbits, when infected with typhus brain, give a positive Weil-Felix reaction. Attempts to infect sheep, goats with typhus...
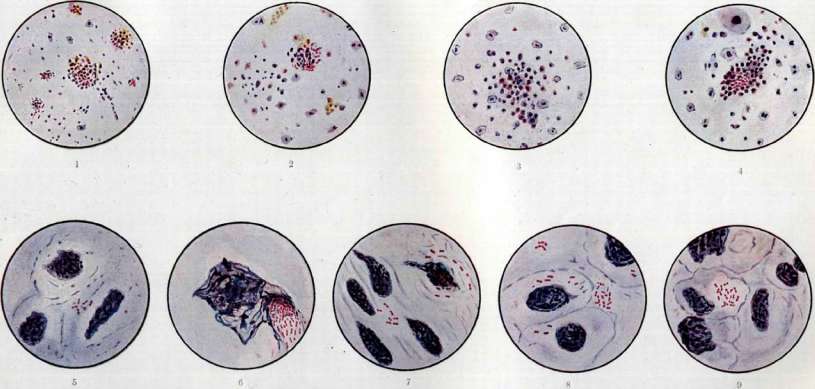
Fig. 1. Granulomas in the brain of a typhus-infected guinea pig. Fig. 1. Low magnification. Granuloma of capillaries and small vessel (in the center). Fig. 2. Medium magnification. Granuloma, proliferation and vascularization in capillaries, scattered glial nodule. Fig. 3. Medium magnification. Typical granuloma at the site of a capillary. Fig. 4. Medium magnification. Cuff around a small vessel. Fig. 5. Rickettsia (Prowazeki).
and organs of animals that died from typhus. Rickettsia prowazekii lie intracellularly. Figure A. Smear from the brain. Figure B. Cell: the protoplasm is stretched, filled with Rickettsia prowazekii arranged as if in a cluster. Figure C. Smear from the spleen. Rickettsia prowazekii scattered in the protoplasm of cells. Figure D. Smear from the plexus chorioideus. Intracellular and extracellular arrangement of Rickettsia prowazekii. Figure E. Smear from the lung. Around the endothelial group, Rickettsia prowazekii are visible. Experiments on donkeys, dogs, and chickens ended in failure. Selivanova in 1924-25 managed to reproduce experimental typhus in chickens, ducks, pigeons, and guinea fowl. Confirmation of these data has not yet followed. As for the pathological anatomy of experimental typhus, it has been thoroughly studied by a number of authors: Levy, Otto and Dietrich, Ritz, Bauer, Barykin and colleagues, Ceelen, Davydovsky (Levy, Dietrich, Ritz, Bauer, Ceelen), and many others. It essentially does not differ from the pathological anatomy of human typhus. Macroscopic changes characteristic of typhus are not observed in experimental infection. Microscopically, it is a universal granulomatosis of small vessels and capillaries, especially of the central nervous system (brain, Ammon's horn) (see separate table, figs. 1-4). Granulomatosis is detected from the 4th-5th day of fever. Involution of granulomas ends in the 2nd-3rd week of apyrexia. The main distinguishing feature of experimental typhus granulomatosis from the same in natural infection in humans should be considered the predominance in the former of proliferative phenomena over destructive ones. The severity and prevalence of experimental typhus granulomatosis depend on: 1) the individuality of the typhus strain with which the infection is reproduced, 2) the dose of infectious material, and 3) the weight and individuality of the infected animal. According to Dürr and Kirschner, in guinea pigs known to be sick with experimental typhus, granulomatosis is not detected in 15-20% of cases; according to Barykin, Kompantsev, Zakharov, and Barykina, in 33%. In mild and abortive forms of experimental typhus, granulomas are extremely rare or completely absent.
Typhus virus. The experimental reproduction of typhus allowed researchers to study the nature and properties of the typhus virus. Thus, it was established that this virus does not belong to the category of filterable ones, although it stands on the border with the latter, passing in some rare cases through Chamberland L2 and Berkefeld V and N candles. Furthermore, it was proven that the typhus virus is extremely unstable. In typhus blood, it dies when heated to 55° for 15 minutes (Anderson and Goldberger, da Rocha-Lima), at room temperature in 2-5 days (Olitzky), upon freezing in 2 days (Hamdi), and according to some authors in 15 days (Goldberger and Anderson). Glycerin 30-80%, saponin, carbolic acid 5%, and mercuric chloride 1‰ quickly kill the typhus virus. Attempts to microscopically detect this virus or obtain its culture for decades proved fruitless. A number of researchers, starting from Haller (1868) to Anigstein and Amzel (1927), described a wide variety of microbes as the causative agents of typhus: Protozoa, cocci, bacilli, spirochetes, etc. Many of these microbes were isolated from typhus blood and gave immunity reactions with it, but none of them, upon subsequent verification, turned out to be the true causative agent of typhus. Such a variety of findings in typhus is explained by the ease with which typhus blood, due to multiple granulomatosis destroying small vessels, is flooded with extraneous microbes (Barykin). The search for the causative agent of typhus was placed on a firmer footing when it was proven that the vector of typhus is the body louse (Ch. Nicolle, 1909). Already in 1910, Ricketts and Wilder discovered in the intestines of body lice infected with Mexican typhus, oval and rod-shaped formations resembling bacteria of hemorrhagic septicemia. Identical formations were found in the typhus louse by Prowazek (Serbia, 1913), Sergent, Foley, and Vialatte (Tunis, 1914). At the end of 1914, da Rocha-Lima, systematically studying under a microscope body lice collected from Russian prisoners of war in the Cottbus camp, established that these formations are found in huge quantities in the intestinal epithelium of lice and are a constant characteristic sign of the infection of the latter with the typhus virus. Rocha-Lima named them Rickettsia prowazekii in honor of the two aforementioned scientists who saw them and died from typhus during their research. According to the description by Rocha-Lima, Rickettsia prowazekii have a basic elliptical shape. Very short, almost round, they grow, stretch in length, and then divide into two new elements. The period of complete separation is preceded by the formation of a constriction, which for some time still connects the young individuals and gives the whole microbe the appearance of a biscuit or a gymnastic weight. Along with such forms, there are rod-shaped ones that stain polarly, and long, elongated specimens. There is nothing characteristic in their arrangement on preparations. Individual formations are sometimes arranged in the form of short chains. A huge number of formations, resembling a pure culture of microbes on smears, is characteristic. Rickettsia prowazekii in size stand at the limit of the resolving power of modern microscopes. Young forms are about 0.3-0.4 μ in length, dividing ones about 0.6-0.9 μ. Their morphology is visible on the microphotogram [see separate table (pp. 199-200), figs. 1 and 2]. Rickettsia prowazekii stain with difficulty and are paler than banal microbes. The most reliable method for them is the Giemsa method, with which they stain a pale pink color with a crimson tint (see separate table, figures 5-9). They do not stain by Gram, do not possess independent movement, and when suspended in a 0.85% sodium chloride solution, they exhibit clear Brownian motion. A capsule has not been found in them, although they often appear surrounded by a transparent zone on Giemsa-stained preparations. The most important distinguishing feature is their localization in the epithelium of the midgut (stomach) of the louse. Invading this epithelium, they multiply vigorously, stretch, and then rupture the epithelial cell, which undergoes deep degenerative changes. Together with cell debris, Rickettsia prowazekii enter the intestinal lumen and are excreted with feces, as can be seen in the attached microphotogram. Sikora found Rickettsia prowazekii in the salivary glands of infected lice.
188 which is disputed by other researchers, Arkwright and Bacot - in the ovaries and eggs of female lice. The most convincing pictures of typhus rickettsiosis in lice are provided by serial sections of their intestine, prepared according to the method of Sikora or Weigl. Rickettsia Prowazeki have been found in the blood and organs of typhus patients and guinea pigs. Thus, Ricketts and Wilder saw them in the blood of sick people, Bessau - in blood plasma, Kuczynski, Jaffe, Barykin and Afanasyeva - in the endothelium of capillaries of internal organs, Wolbach, Todd and Palfrey - in the endothelium of cutaneous granulomas, etc. The intracellular arrangement of Rickettsia Prowazeki and their accumulation in the form of whole groups are characteristic [see separate table (pp. 183-184), figs. 5-9]. Woodcock considers Rickettsia Prowazeki to be non-living formations of the granule, mitochondrion, or cellular decay product type. The entire body of facts proving the living nature of Rickettsia Prowazeki and their close relationship to the etiology of typhus argues against such an interpretation. Rickettsia Prowazeki, unlike granules and cellular decay, are morphologically and tinctorially uniform. They are not destroyed even by strong acetic acid, boiling distilled water, 2% NaCl solution, ether, acetone, toluene, xylene, benzene, and alcohol (Epstein). They are digested by pancreatin. They are complete antigens. In favor of their etiological significance for typhus, a number of weighty and well-verified facts can be presented: 1) Rickettsia Prowazeki, localized in the intestinal epithelium, are found only in lice taken from typhus patients or fed on typhus blood; 2) only lice containing Rickettsia Prowazeki cause experimental typhus with immunity to subsequent infection with typhus blood; 3) Rickettsia Prowazeki, in their size, relation to temperature, and other agents, behave quite identically to the typhus virus; 4) Rickettsia Prowazeki give all immunity reactions with typhus sera of humans and experimental animals; 5) the optimum for the development of Rickettsia Prowazeki, like that of the typhus virus, in the body of the body louse lies at about +32° (da Rocha-Lima); at a temperature of +23°, the development of both Rickettsia Prowazeki and the typhus virus ceases in the louse. On the basis of these facts, the vast majority of researchers consider Rickettsia Prowazeki to be the causative agent of typhus. Unlike banal microbes, Rickettsia Prowazeki is not cultivated on ordinary laboratory media. In 1923, Kuczynski, as well as Krontovsky and Gakh, managed to maintain the typhus virus in one generation in explants of the spleen of a typhus-infected guinea pig according to the Carrel method. Further improvement of this technique as applied to typhus in the hands of Sato Kiyoshi, Nigg and Landsteiner, as well as other authors, led to the final resolution of the problem of cultivating the typhus virus in tissue explants. The authors' methodology ensures the production of a typhus culture in an unlimited number of passages. The culture retains all its virulent, antigenic, and immunological properties completely. Morphologically, it represents a culture of Rickettsia Prowazeki multiplying in the cells of the explant. In some cases, the detection of these formations in tissue cultures requires special processing (Sato Kiyoshi) or they cannot be detected at all. Tissue cultures, however, cannot provide large quantities of typhus virus and therefore cannot serve as material for experiments on the mass preparation of anti-typhus vaccine or serum. An original method for the mass cultivation of the typhus virus was recently proposed by Silber and Dosser, who grow this virus in symbiosis with other microbes, in particular with kefir yeast. The authors obtained 16 generations of the typhus virus, but its biology apparently suffers somewhat, which is expressed by its loss of its antigenic properties (Barykin). It is interesting to note that Rickettsia Prowazeki are not detected in yeast cultures. Since the establishment of the significance of these formations in the etiology of typhus, morphologically identical formations have been found in lice collected both from healthy people (Brumpt) and from people sick with trench fever (Jungmann, Kuczynski) and a number of other infections. At the present time, it has been proven that rickettsioses are widely distributed among blood-sucking and non-blood-sucking insects. They are found in both Insecta and Arachnoidea. However, all these types of rickettsioses ("Rickettsienarten"), by the totality of signs, especially in relation to the intestinal epithelium of the insect, can easily be distinguished from Rickettsia Prowazeki (da Rocha-Lima). The etiological significance of Rickettsia Prowazeki for typhus was disputed by some authors. However, the attempt by Weil and Felix, Friedberger, Kuczynski, Fejgin, and others to link the etiology of typhus with the culture of B. proteus X19, which is specifically agglutinated by typhus sera, proved to be untenable. The following facts argue against the etiological significance of this culture for typhus: 1) its extremely rare isolation from typhus blood, 2) the inability of B. proteus X19 and its variants to cause experimental typhus, 3) its absence in typhus-infected lice, etc. The very ability of X-proteus to enter into specific agglutination with typhus sera is considered by the majority of authors as a property of a para-strain, acquired by it as a result of its cohabitation with the virus, and is qualified as para-agglutination. Thus, summarizing the data on the etiology of typhus, it must be concluded that the causative agent of this infection is Rickettsia Prowazeki, although in some exceptional cases they cannot be detected, which may depend on their ability to produce filterable invisible forms under certain conditions. Ways and methods of spreading typhus. The ways and methods of spreading typhus are predetermined by the fundamental and indisputable position that the transmitter of typhus is the body louse (Pediculus vestimenti). This was first experimentally established on monkeys in 1909 by Ch. Nicolle, Comte, and Conseil, and subsequently found full confirmation both among experimenters and among clinicians and epidemiologists of all countries of the world. Numerous proofs can be cited in favor of the main and decisive role of the louse in the spread of typhus. The most important of them are the following: 1) a deloused typhus patient ceases to be contagious to those around him, 2) the destruction of lice among the population entails the immediate disappearance of typhus, 3) outbreaks of typhus are usually associated with cold seasons of the year, when the population lives more crowdedly, has less opportunity to wash, wears woolen and fur clothing that is difficult to delouse, and when, thanks to all these indicated seasonal and living conditions, lousiness can reach its greatest proportions. The main transmitter of typhus is the body louse, which lives in underwear and moves to a person 3-4 times a day to feed on his blood. Alongside the body louse, the head louse (Pediculus capitis) and possibly the crab louse (Pediculus pubis) play an incomparably less visible, but still indisputable role in the spread of typhus. The transmission of the typhus virus by lice can be carried out in three ways: 1) by means of bites of a healthy person by an infected louse (Ch. Nicolle and colleagues); 2) by means of crushing this louse and rubbing it into the wounds of bites and scratches (Ricketts and Wilder, etc.); 3) by means of the same rubbing in of the feces of this louse (Ch. Nicolle and colleagues, etc.). The question of the ability of typhus-infected lice to transmit their infection by inheritance is not fully clarified. The majority of authors, on the basis of their experiments, deny the hereditary transmission of the typhus virus by lice (Ch. Nicolle, Blanc and Conseil, da Rocha-Lima, Barykin and Kompaneets, etc.). Rickettsia Prowazeki are not found in young lice that are offspring of typhus-infected ones, according to the research of a number of authors. A louse that has sucked typhus blood does not become contagious to humans immediately, but only after 3-5 days. During this period, vigorous multiplication of the typhus virus occurs in the body of the louse, and the amount of this virus reaches the dose that is capable of causing infection in humans (da Rocha-Lima, etc.). The assumption of Ch. Nicolle and colleagues that the typhus virus undergoes a special cycle of development in the body of the louse, characteristic of protozoa, was not confirmed by further research. A louse infected with typhus itself falls ill with it and usually dies from it. The main changes produced by the typhus virus in the body of the louse are concentrated in its intestine, the epithelium of which is destroyed under the influence of the multiplication of this virus (Rickettsia Prowazeki) in it. The lifespan of a louse infected with typhus is reduced due to this infection to 20-25 days, instead of the average lifespan of a healthy louse, which is 30-35 days. A louse infected with typhus remains contagious until the end of its life.
It has not been clarified whether typhus-infected lice can transmit this infection to healthy insects, nor has the method by which such transmission could occur been identified. According to experiments by Barykin and colleagues, healthy lice placed together with typhus-infected ones become infected from the latter in 2% of cases. In Weigl's experiments, no such infection occurred. Pavlovsky's observations establish that the act of copulation between lice, lasting from 20 to 70 minutes, is accompanied by the mixing of the male's and female's feces at the level of the anus. It is possible that this act is significant in the contact transmission of typhus infection among lice. Gakh claims that he succeeded in inducing experimental typhus in guinea pigs by infecting them with lice collected 67-70 days after the last case of typhus in humans. As for other parasites that bite humans, it has already been established on the basis of epidemiological data that these parasites play no role in the development of a typhus outbreak. The season for typhus is the cold time of the year (late autumn, winter, early spring), when mosquitoes are in a state of hibernation, and the number of fleas and ticks drops sharply. According to the observations of C. Nicolle, in some areas of Tunisia, endemic foci of typhus, teeming with lice, are almost completely free of human fleas and bedbugs. Measures aimed at the systematic destruction of lice, as world experience shows, are completely sufficient for the complete liquidation of typhus epidemics and endemic foci. Nevertheless, bedbugs (Barykin and colleagues), fleas, and ticks (Perfiliev) prove to be susceptible to laboratory infection with the typhus epidemic virus and contain it in their bodies for some time (from 4 to 10-20 days). Their infection can be transferred to a guinea pig either by a bite (rarely) or by injection (rubbing in) of crushed insects. Fleas play an important role in the spread of the so-called endemic virus of murine typhus (see below). Thus, from an analysis of the data presented, it is obvious that for the spread of epidemic classical typhus, the decisive importance remains with the human louse. From this follows the main requirement in the fight against this typhus—delousing of the population. The louse becomes infected from an infected person. Consequently, success in the fight against typhus depends on the earliest possible recognition and complete identification of all cases of typhus infection in humans, and thorough delousing of both the patients themselves, who are immediately hospitalized, and those around them, their dwellings, and household items. Along with such clearly expressed cases, during typhus outbreaks, mild, ambulatory, and atypical forms of the disease that proceed without a rash are observed, which are especially frequent among children and in endemic foci. They are sometimes completely inaccessible to clinical recognition. For epidemiologists, they represent a special danger, as they are a source of hidden spread of infection. Finally, cases of so-called typhus virus carriage, proceeding without any symptoms, may be encountered. Such virus carriage by healthy people or those who have previously had typhus was established by the work of Ramsin (1929) in Serbia and, independently of him, in the USSR by the work of Barykin, Minervin and Kompaneyets, Bernhof, Kuteyishchikov, and Dosser (1930). The specific epidemiological weight of typhus virus carriage (frequency, duration, influence on the biology of the virus), although not yet sufficiently clarified, must apparently bring typhus virus carriage closer to mild forms of infection. All these forms can be timely recognized with the help of the Weil-Felix reaction (see). According to recent observations by a number of authors, repeated performance of the Weil-Felix reaction allows one to orient oneself to the degree of hidden and clinically undetectable infection (Durchseuchung) of a typhus focus and, therefore, provides important indications for its complete sanitation. A deloused typhus patient or carrier ceases to be dangerous to those around them. Some researchers assumed that besides lice, typhus infection could be spread by the patient's secretions: sputum, urine, etc. (Zabolotny, Rabinovich, Friedberger, and others). Direct experiments by Anderson and Goldberger and others have proven that the secretions of typhus patients are not infectious, with the exception of those rare cases, which have no epidemiological significance, when the blood of a typhus patient during an operation on him gets into scratches and wounds on the skin and mucous membranes of healthy people (surgeons, nursing staff, etc.). Since typhus is sometimes complicated by pneumonia with the discharge of bloody, infectious sputum, it must be disinfected with disinfectant solutions. Caution is also necessary when performing oral hygiene for a patient with bleeding gums, etc. The earliest possible recognition of typhus, entailing the hospitalization of the deloused patient, is the most important condition for a successful fight against typhus. This condition can be fulfilled with the systematic, mass performance of the Weil-Felix reaction (see), organized according to epidemiological indicators. For epidemiological purposes, this reaction should, according to the observations of Barykin and colleagues, be performed repeatedly; this allows for the identification of its dynamics and to verify whether one is dealing with a positive non-specific and retrospective reaction or with the presence of typhus infection, in whatever hidden form it may be proceeding (virus carriage). With careful selection of B. proteus X19 cultures, among which preference should be given to local strains that are fully valid in a serological sense, and with correct technique, the Weil-Felix reaction provides invaluable services for identifying hidden paths of the spread of typhus. According to experiments by Barykina and Ge, the Weil-Felix reaction is found in only 63% of those who have had typhus after 1 month, and in 54.5% after 1/2 year, sometimes persisting for over 2 years. Thus, in some cases, it is suitable for the retrospective recognition of previously contracted typhus. In order to accelerate the Weil-Felix reaction, one can recommend its modification, proposed by Nobl for the serodiagnosis of the enteric-typhoid group, meningococci, etc., and tested by Bergman and Rabinovich, as well as Mayofis for typhus. Bringing the Weil-Felix reaction to primary rural cells that do not have laboratories is possible by supplying them with killed Weil-Felix cultures in the form of typhus typhus diagnosticum, prepared according to the method of Bien, Sontag, Sacks, and others. Serological recognition of typhus is also successfully carried out with the help of Rickettsia Prowazeki as the causative agent of this infection, which gives specific agglutination, complement fixation, and tropinization (Epshtein and others) with the sera of both typhus-infected human patients and experimental animals. However, the difficulty of obtaining large quantities of Rickettsia Prowazeki makes the test with them little accessible for broad practical purposes. Specific prophylaxis and serotherapy of typhus. Questions of specific prophylaxis and serotherapy of typhus are still in the stage of study. They are closely related to typhus immunity, the nature and mechanism of which have not yet been sufficiently studied. It is known that a successfully recovered case of typhus as a rule leaves behind a strong and long-lasting, although not absolute, immunity to reinfection. In some rare cases, clinicians observe repeated cases of typhus (Pletnev, Flerov, and others). According to systematic observations by Khinskaya, repeated cases of typhus are encountered more often the longer the time that has passed since the first attack of this infection, sometimes reaching 50% of primary cases. Usually, a repeated case of typhus proceeds more easily than the primary one (Moroskin). In experimental animals (guinea pigs), the intensity of immunity is also closely related to the severity of the first recovered disease. Nevertheless, even asymptomatic typhus can sometimes create immunity to subsequent infection. Some authors claim that such immunity appears as a result of any, even the mildest form of primary typhus in animals. Others prove that immunity to typhus in animals that have recovered from it cannot be detected at all, since the brains of these animals contain the virus a long time after their clinical recovery. Sergent distinguishes two stages in the formation of immunity: 1) période de prémunition, occurring immediately after the drop in temperature and characterized by incomplete elimination of the virus from the body (non-sterile immunity), and 2) the subsequent period of sterile immunity, when the virus is no longer in the body. It has been proven that the typhus virus can persist in the brain of a guinea pig after the end of a febrile typhus attack for 24 to 46 days, and in rats—from 9 to 68 days. No less important a moment for clarifying typhus immunity is the question of the very nature of this state. Apparently, the predominant cellular character of the body's defense against the typhus virus is indisputable. This is evidenced by the universal granulomatosis of small vessels characteristic of typhus as a phagocytic reaction to the virus.
But alongside such cellular defense, one cannot ignore the humoral reactions accompanying recovery. Besides serum reactions, such as agglutination, complement fixation, and tropinization, it has been proven that the sera of typhus convalescents, both human and animal, possess preventive and virucidal properties, although they are weakly expressed. Preventive and virucidal properties reach their maximum between the 16th and 23rd days of convalescence, but they are so weak that they are only able to soften the infection, shifting it from a febrile form to an afebrile one.
From what has been said, it is easy to understand what obstacles stand in the way of preparing effective typhus vaccines and sera. The main difficulty in obtaining a reliable typhus vaccine is that even a live typhus virus, which causes a mild disease, usually does not provide immunity. According to Schnabel, Landsteiner, Hausmann, and others, a killed typhus virus loses its immunizing properties. Attempts to use typhus serum or blood as material for a vaccine after inactivating them at 55–60° (serum vaccine of C. Nicolle, blood vaccine of Hamdi) ended in complete failure and currently have only historical interest. The same fate befell vaccines prepared from inactivated typhus leukocytes (Neukirch) or the internal organs of typhus-infected guinea pigs (Blanc), as well as from the intestines of typhus-infected lice (da Rocha-Lima).
Nevertheless, researchers stubbornly continue to look for ways to prepare an effective typhus vaccine. Experiments are proceeding in two main directions. For some researchers, the starting material for preparing the vaccine is the brain and other organs of typhus-infected guinea pigs that have undergone preliminary treatment (avitaminous diet, injection of benzene, irradiation, etc.) with the aim of weakening their natural resistance and causing them to have a severe experimental infection with maximum accumulation of the virus. Other researchers prefer to accumulate the typhus virus in lice and use the intestines of the latter as material for preparing vaccines. Partial successes have been achieved by both groups of researchers; however, these successes are not yet great enough to allow the authors' vaccines to be taken out of laboratories into practice among humans. These vaccines only partially protect a certain percentage of guinea pigs from experimental typhus.
An exception is the Weigl vaccine. As material for his vaccine, Weigl takes the intestines of typhus-infected lice, ground and suspended in a 0.85% NaCl solution. Each intestine contains 10–100 million Rickettsia prowazekii. To inactivate the vaccine, Weigl adds 0.5% Ac. carbolici. The vaccine retains its activity on ice for up to 3 years. The vaccine is administered subcutaneously in doses of 20–40–60 intestines of typhus-infected lice at intervals of 3–5 days. In these doses, it protects guinea pigs and monkeys from several thousand infectious doses of passage typhus virus. To immunize a human, about 120 intestines of typhus-infected lice or about 5 billion Rickettsia prowazekii are required. According to observations by Varela, Parada, and Ramos, the Weigl vaccine causes severe reactions in humans, resembling typhoid vaccine. Its effectiveness for humans is beyond doubt. It has been verified by Weigl himself, as well as by C. Nicolle and Sparrow. During 1931–32, the Weigl vaccine was administered in Poland to 648 medical personnel working in typhus foci and 1,805 people who came into direct contact with typhus patients (family members, etc.). Of the vaccinated, 28 people contracted typhus during the vaccination itself or in the first 2–5 days after its completion; 4 people contracted typhus 2–5 months after the end of the vaccination. In all those who fell ill, the infection had a mild course and ended in recovery. The duration of immunity in vaccinated people is estimated at about 1 year. A significant drawback of the Weigl vaccine is the impossibility, due to the difficulty of preparation, of using it for mass vaccinations.
No fewer difficulties than in the preparation of an anti-typhus vaccine are encountered in attempts to prepare a specific anti-typhus therapeutic serum. The main obstacle here is, as stated above, the very nature of typhus immunity, which is predominantly cellular with weakly expressed serum protective properties. The first experiments in serum treatment of typhus were conducted with the sera of convalescents. These experiments showed that the effect of such sera generally amounts to some softening of the severity of nervous symptoms and an improvement in the patients' well-being. Convalescent sera do not affect either the duration or the outcome of the disease. Therefore, as early as 1916, C. Nicolle and Blaizot undertook the hyperimmunization of a horse and donkeys with the organs of typhus-infected guinea pigs and rabbits. The resulting immune serum, according to the authors' observations, yielded "favorable results" in humans. Upon verification by other researchers, it proved ineffective. Pacevich and Triodin in 1919 performed an experiment on immunizing a horse with the serum of typhus patients. According to reports by these researchers, the serum they obtained showed a good therapeutic effect. However, this was not confirmed subsequently. Finally, Barykin, Klimentova, and Afanasyeva in 1919 subjected 2 horses to hyperimmunization with the organs of typhus-infected guinea pigs. Testing the authors' serum on 30 typhus patients with a control group of 32 typhus patients yielded the following results. In those treated with serum, the duration of the disease was reduced on average by 2 days compared to the untreated; mortality among the treated was 3.3%, and among the untreated 12.5%, i.e., it decreased by almost 4 times. The group treated with serum was older on average (average 28.5 years) than the control group (average 24 years). The modest results obtained regarding the therapeutic effect of the serum are far from those usually observed with specific serotherapy (diphtheria, dysentery, etc.). Recently, Zinsser and Castañeda subjected a horse to prolonged immunization with formalinized Rickettsia prowazekii, accumulated in the bodies of typhus-infected guinea pigs that had been previously benzodized or irradiated with short X-rays. The authors' serum agglutinated Rickettsia prowazekii to a titer of 1:640, and Proteus X19 to a titer of 1:320. When tested, it proved capable of protecting guinea pigs from subsequent or previous (24–43 hours prior) infection with the typhus virus. The therapeutic effect of the serum has not been tested on humans. From what has been stated, it is evident that while there have been certain achievements in the field of specific prophylaxis against typhus in recent years, there are as yet no significant successes in the field of serotherapy. V. Barykin.
Statistics and geographical distribution. In the 19th century, typhus was endemic in most countries of Western Europe. From time to time, under the influence of wars, famine, and other social calamities, typhus took on the character of widespread epidemics. Such were its epidemics during the Napoleonic Wars, which covered a significant part of Western Europe, during the Crimean Campaign (1854–56), in the Russo-Turkish War (1877–78), in connection with the famine in 1846–49 (a significant part of Western Europe), in 1865–70 (Prussia, Sweden, Finland, etc.), and also repeatedly in Tsarist Russia. By the beginning of the World War, typhus remained at more or less high figures in Hungary, the Balkan states, Spain, and Portugal. The World War gave a significant rise to typhus in a number of countries. Among them, one should first of all dwell on Germany. The number of cases on the fronts of the German army rose from 0.03 per 1,000 in 1914 to 0.3 in 1918, i.e., it increased 10-fold; at the same time, on the Turkish front, the incidence reached 10.7, on the Balkan front up to 0.9, and on the Eastern front up to 0.8 per 1,000. In German camps for prisoners of war, over 45,000 cases of typhus were registered during the 4 years of the war. Among the civilian population, more than 2,600 people died from typhus during 1914–19. But an especially strong development of typhus was observed in those countries where it had been endemic before the war. Moreover, in a number of countries, it reached its maximum development after the end of the war in connection with the return of demobilized armies, prisoners, and refugees. On the territory of present-day Yugoslavia, about 675,000 people fell ill with typhus during the first 2 years of the war, and about 135,000 died. Of 534 Serbian doctors, 132 died from typhus, and almost all the rest had the disease. The epidemic continued until 1921. In Bulgaria, in 1917, about 7,000 people fell ill (20 per 10,000); the epidemic continued until 1920. In Austria-Hungary, in 1915, 14,586 patients were registered; epidemics were observed in all the states separated from it (Austria, Hungary, Czechoslovakia). In Romania (Fig. 2), typhus took on the character of a severe epidemic in 1919–20 (over 110,000 cases and about 15,000 deaths in 2 years). Typhus caused a major outbreak in 1919–20 in Latvia, Lithuania, Poland, and Estonia.
A significant increase in it was noted in some states that did not take direct part in the war, for example, in Holland, Greece, Spain, and Portugal. Western European states began to overcome the wartime and postwar epidemics, but Typhus in Western Europe has not yet disappeared completely. In a number of Western European countries, Typhus in recent years not only does not show a tendency to decline, but, on the contrary, shows a noticeable increase (Bulgaria, Poland, Romania, Yugoslavia) (Tables 1–3). Table 1. Incidence of Typhus in some countries in 1933 (abs. figures). In Asia, among those countries where Typhus is subject to mandatory registration, the highest incidence of it is observed in Korea (Table 1). In Japan, Typhus caused a large outbreak in 1914 (7,309 cases). A major outbreak was observed in 1928 in Kwantung (1,709 cases, or 21.5 per 10,000). Foci of Typhus are observed in China and Manchuria. In Iran in 1931, 1,167 cases were registered, in 1932—1,171 cases; in Palestine in recent years, from 30 to 100 cases are registered; in Turkey—from 100 to 300 cases per year. The largest foci of Typhus are in Africa (Table 1). A sharp increase in Typhus in recent years is observed in Algeria, the Union of South Africa, and Egypt (Tables 1 and 4, Fig. 3). In the USA, a noticeable growth of Typhus has been noted in recent years. Permanent foci of Typhus are observed in Mexico (Fig. 4), Chile. In the latter, Typhus in 1933 showed an extremely high rise. Epidemics of Typhus in recent years have been observed in Bolivia and Peru. In Australia, about 50 cases of Typhus are registered annually. The growth of Typhus in a number of foreign countries should be closely linked to the economic crisis in capitalist countries. Table 4. Incidence of Typhus in Egypt in 1927–1934 by quarters of the year (abs. figures).
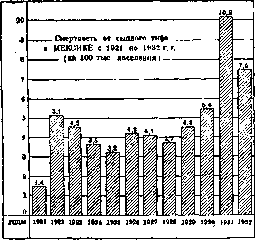
Typhus in the USSR. In pre-war Russia, Typhus was endemic throughout the country. Its largest epidemics were during the Crimean campaign of 1854–56 (in the southern and western armies, 79,533 contracted Typhus and 15,571 lower ranks died) and the Russo-Turkish War of 1877–78 (in the Danube and Caucasian armies, 48,011 contracted it and 16,587 people died). Official data on the incidence of Typhus among the civilian population have been available since 1881. Summarized by five-year periods, they give the following indicators: When analyzing the Typhus curve by individual years (Fig. 5), one can see several sharply pronounced rises. The epidemics of 1881 and 1892–1893 are connected with the famine that gripped the greater part of the country in those years; the epidemic of 1908 and the following years is connected with the overcrowding of prisons in connection with mass repressions after the first revolution. Russia entered the World War heavily affected by Typhus (Fig. 6). It began to develop rapidly in the army, where the incidence rose from 0.13 in 1913 to 2.33 per 1,000 in 1915. From the fronts, Typhus, along with the sick and wounded, prisoners of war, and refugees, began to seep into the interior of the country. Already in 1916, the incidence rate rose throughout Russia to 8.3; in 1917, a significant growth of Typhus was noted in a number of regions (Central Industrial, Ukraine, etc.). The return of troops from the front in 1918 gave a strong impetus to the further development of Typhus. In this year, the incidence rate reached an unprecedented height—up to 21.9. In the following 2 years, in connection with the Civil War and intervention, Typhus took on the character of a severe pandemic. According to far from complete information, over 2 million cases were registered annually in 1919 and 1920, or about 340 per 10,000. All the forces of the country were mobilized to fight it ('Comrades, all attention to this issue. Either lice will defeat socialism, or socialism must defeat the lice!', from a report by V. I. Lenin in December 1919). It was possible to reduce Typhus to 60 per 10,000 in 1921, but in connection with the famine and the migration of starving people, it caused a new explosion in 1922 (158.9 per 10,000). In total, for the period from 1918 to 1922, according to rough estimates, about 20 million people contracted Typhus in the USSR. Only gradually was it possible to eliminate the epidemic, and in 1925 Typhus decreased to 5.2, in 1928–29 to 2.1, and in 1933 to 1.5 per 10,000, i.e., almost 5 times lower than the pre-war level. It decreased especially in the northern and central regions of the RSFSR, the Lower Volga region, the North Caucasus, Crimea, Ukraine, and Transcaucasia (Fig. 7). In recent years, Typhus still causes isolated outbreaks of disease across the country, and the fight for its elimination stands as one of the immediate tasks in the work of public health agencies. Incidence by age and sex. The highest incidence of Typhus is observed in the age group from 15 to 40–50 years. This character of age-specific incidence was preserved during the Typhus pandemic (Table 6). Table 6. Incidence of Typhus in Moscow by age groups (per 10,000 of the corresponding age). Among men, the case fatality rate is higher than among women. During the World War, unequal case fatality rates were noted among different nationalities: in German prisoner-of-war camps, it was 7.5% among Russians who contracted Typhus, and 21.6% among the French. Seasonality of incidence. The monthly distribution of Typhus has clearly expressed seasonal fluctuations. In individual countries, depending on climatic and related living conditions (crowding, lice infestation), the maximum occurs at different times of the year. In the USSR, the maximum incidence occurs in the winter and early spring months (February–March) (Fig. 8). It is characteristic that during the pandemic, Typhus retained the type of its monthly curve. Fig. 3. [Children] contract Typhus significantly more often than is usually registered among them, because at this age it proceeds atypically and is often not diagnosed by doctors. Figure 4.
Mortality in Typhus is not uniform for individual age groups: its rate increases with increasing age, but in younger age groups (up to 10 years) it is higher than in the immediately older groups. Pathological anatomy of typhus. The pathological anatomy of Typhus was developed mainly by the works of E. Fraenkel, I. V. Davydovsky, and Sh. I. Krinitsky. It was established that from a morphological standpoint, Typhus is primarily a disease of the circulatory system as a whole. Upon microscopic examination of this system, especially in the skin and in the nervous system, the following types of changes were discovered (Davydovsky). The first type—verrucous endovasculitis—is characterized by the appearance on the inner surface of vessels, including such vessels as the aorta, of small verrucous deposits consisting of fibrin and often containing an admixture of nuclear detritus, i.e., disintegrated endothelial cells. Essentially, parietal thrombosis of the vessels (see separate table, Fig. 5) occurs here on the basis of the destruction of individual endothelial cells or groups of these cells. In small vessels, thrombi often have an obstructive character, accompanied by a large volume of destructive changes, sometimes with the transformation of the entire mass of the vessel wall into amorphous detritus. This second form can be designated as destructive thrombovasculitis. Either in combination with the previous forms or independently, a third form of vasculitis develops, consisting of a focal proliferative reaction along the peripheral vascular system (capillaries, arterioles, venules) and leading to the development of typhus granulomas around these vessels. Proliferation occurs either at the expense of endothelial and intimal cells or at the expense of adventitial cells, depending on which pictures arise of either proliferative endovasculitis, or perivasculitis (periphlebitis, periarteritis), or, with a combination of both moments, pictures of endoperivasculitis. At the site of granuloma development, the vessel wall loses its contours, becomes fibrillated, and the lumen is often thrombosed. The tissue surrounding the vessel also takes part in the proliferation; in particular, in the nervous system such
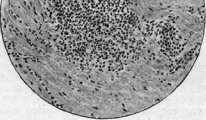
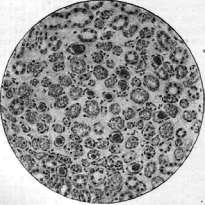
Figure 1. Rickettsia Prowazeki; intracellular location (according to Otto-Munter). Figure 2. Rickettsia Prowazeki; extracellular location (according to Otto-Munter). Figure 3. Myocarditis in typhus. Figure 4. Granuloma in the skin in typhus. Fig. 5. Massive thrombosis of vessels of the medullary substance of the kidney. Figure 6. Encephalitis-granulomas and perivascular cuffs in the medulla oblongata. 20-3
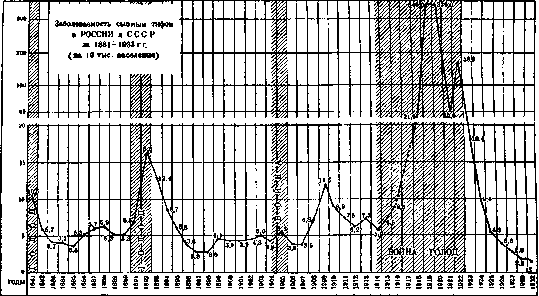
Figure 5.
participation is observed on the part of neuroglial elements. The above-described vascular changes are observed predominantly in the peripheral vascular system and, as a rule, without exception, although with significant qualitative and quantitative variations. Mild and moderate cases (and this was verified by Davydovsky on biopsied exanthema) are characterized by the prevalence of a proliferative reaction, while more severe cases are characterized by the presence of significant, sometimes sharp destructive processes, massive thrombosis of vessels, hemorrhages, etc. As a fourth and, moreover, latest type of vascular change (observed usually no earlier than the 3rd-4th week), one should point to nodular periarteritis, morphologically indistinguishable from the pictures of Kussmaul's periarteritis nodosa. The process involves either the entire circumference or part of the vessel walls and is localized mainly along relatively large muscular-type arteries (e.g., in the area of the adrenal capsule). The regression of vascular changes varies depending on the intensity of the process. Thrombotic (verrucous and obstructive) processes, insofar as they are not accompanied by deep destruction of the wall, apparently do not leave special traces: autolysis of thrombi and regeneration of the endothelium occur. With significant destruction, limited or circular hyalinosis of the wall occurs, and in some places, apparently, complete disappearance of the vessel with the development of fibrous connective tissue in its place. Both the emergence, quantitative increase, and regression of vascular changes in Typhus are often greatly stretched out in time, which is why sometimes 1 1/2-2 months after the onset of the disease, residual processes of incomplete regeneration are still discovered along the vessels; thus, morphological convalescence significantly lags behind clinical convalescence. Upon detailed examination of typhus granulomas in the protoplasm of proliferating cells, in particular in the endothelium, minute coccoid formations resembling rickettsiae were discovered. These findings, however, are inconstant. Whether rickettsia-like formations are parasites or a product of cellular decay—this question also still remains open. In organopathological terms, Typhus is characterized by the following features. The heart almost without exception presents pictures of myocarditis, either in the form of diffuse infiltrates of large and small monocytoid, plasma cells, or in the form of nodules-granulomas. In general, myocarditis has an interstitial character [see separate table (col. 199-200), Fig. 3]. Sometimes inflammatory changes, edema, and thrombosis of vessels are selectively concentrated along the atrioventricular system, which, like myocarditis in general, can serve as a cause of cardiac death sometimes developing in Typhus. Endocarditis is not observed. The most prominent place in the organopathology of Typhus is occupied by the lesion of the nervous system. This lesion is universal, covering the brain, cerebellum, medulla oblongata, spinal cord, sympathetic ganglia, ganglia in general, and peripheral nerves. The type of these changes is twofold. On the one hand, vulgar phenomena are noted, such as: hemorrhages (punctate and large, of an apoplectic nature), degenerative processes in ganglion cells, sharp hyperemia of vessels, dilation of lymphatic spaces, sometimes rupture of the latter. On the other hand, and this is more characteristic, focal inflammatory processes are discovered along the affected vascular system. Every Typhus is an acute encephalitis with predominant involvement of the gray matter of the brain. There are especially many foci of lesions in the medulla oblongata, and specifically in the part of it lying below the level of the striae acusticae, in the olives, and in the area of the nuclei of the X and XII pairs of cranial nerves. The foci have the appearance of rounded granulomas [see separate table (col. 199-200), Fig. 6], in the central parts of which passes an affected vessel in a state of more or less significant destruction; sometimes only
Related articles
Mentioned in
Cite this page
“Typhus (188 Specific prophylaxis and serotherapy of).” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/typhus-fever/