Patient Care
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia outlines the general and specialized principles of patient care in medical institutions, emphasizing hygiene, environmental management, observation, and proper nutrition.
Encyclopedia article (1928–1936)
PATIENT CARE is a whole range of measures aimed at alleviating the patient's condition, eliminating unnecessary suffering, and ensuring the correct course of the disease and the success of treatment. Since the patient's well-being and mental state are of great importance for the success of treatment, care for patients must be viewed as a very essential part of treatment, responsibility for which is also borne by the attending physician and the physician in charge of the institution, whose duty is the proper organization of care. Patient care is divided into general and special. General care includes such measures as can be applied to any patient regardless of the type and nature of their disease. Special care contains measures applied only to patients of a certain type, e.g., gynecological, psychiatric, etc. The correct implementation of patient care is most feasible in a hospital setting, where it is carried out mainly by the nursing and auxiliary medical staff, predominantly intermediate staff, who must be appropriately trained and educated for this. The nursing staff must have appropriate knowledge, skills, familiarity with care techniques and equipment. At the other hand, they must possess patience, the ability to approach the patient, and above all cleanliness. They must be dressed in clean, wrapped-around gowns, the head and obligatorily the hair must be covered with a bandage or cap, and the feet shod in noiseless (but not felt) footwear.
General care of patients. Basically, it consists of the following: 1) creating a hygienic environment for the patient and actual care, i.e., servicing the patient, 2) observation of patients and carrying out preventive measures, and 3) carrying out therapeutic measures. 1. Creation of a hygienic environment and care in the strict sense of the word. The room for the patient must meet certain requirements in terms of its design, dimensions, lighting, heating, ventilation, equipment, furnishings, and cleanliness (see Ward). Cleaning the room and the items of hospital furnishings in it must always be damp, and the walls and windows must also be periodically wiped down. It is especially necessary to monitor the cleanliness of bedside tables, preventing the accumulation and storage of unnecessary things and especially food products in them. Wards must be ventilated at least 3 times a day. The best temperature in the patient's room is 18–20°. For the purpose of refreshing the air, flowers without harsh odors and especially rich in greenery can be allowed in the patient's room, but only for the day. It is extremely important to wage the most energetic struggle against the penetration and accumulation of flies in the room. The patient's bed must consist of a bedstead, a resilient mattress, a pillow, a blanket, and bed linen—pillowcases, sheets, and a duvet cover. For bedridden patients suffering from incontinence of feces or urine, oilcloth must be laid between the sheet and the mattress. For restless patients, beds (resembling children's beds) with side mesh are used. The patient's bed must be neatly and comfortably made; there must be no lumps or depressions on the mattress, the pillows must not be matted down, the blanket must not hang down but must be tucked in at the edges under the mattress, the pillowcase and sheet must not be knocked into a lump or form rough folds, and the duvet cover must be well attached to the blanket. All parts of the bed must be kept in the greatest possible cleanliness. Bed linen must be changed regularly as often as possible, in any case no less than once every 5–7 days, and in the event of contamination with any excretions of the patient, it must be changed immediately. When changing bedding for bedridden patients, the latter are either transferred to another bed or lifted and held in arms. A sheet can be quickly changed for a seriously ill patient without lifting them in the following way: they are turned onto their side towards one edge of the bed, the freed half of the sheet being changed is gathered into a roll toward the patient's back, a clean sheet is laid in its place, half of which is also gathered into a roll, and the rolls of the old and new sheets are placed side by side, then the patient is turned onto the other side onto the clean half of the bed, the old sheet is removed, and the roll of the new one is smoothed out.
The patient's clothing depends on their condition. Bedridden patients are given only underlinen, and seriously ill patients are given only a shirt or, even better, a jacket put on from the front and wrapped back without ties or fasteners. Ambulatory patients are also given a bathrobe, preferably with button-on linen collars, cuffs, stockings, and slippers. All of the patient's clothing must be clean, for which purpose the underlinen as well as the collars and cuffs of bathrobes must be regularly and as frequently as possible changed, and the bathrobes aired and shaken out or beaten and periodically disinfected. It is especially necessary to change linen for sweating patients and obligatorily clean linen, rather than using linen dried after sweat. When changing a shirt for seriously ill patients, it is necessary, having gathered it upwards, to remove it first from the head and then from the arms, and to put it on in the reverse order. In case of diseases of the limbs, linen must be removed first from the healthy limb and then from the sick one, and put on conversely. The changed dirty linen must be stored in a special place completely separate from clean linen. The cleanliness of the patient's body must be a subject of special attention by the nursing staff. The skin must be systematically and thoroughly washed, especially carefully and frequently in the most contaminated places (groin, perineum, armpits, etc.). To wash patients, hygienic baths at 35–36° or showers are usually used, which are given at least once every 5–7 days. In cases where baths or showers cannot be used, recourse is made to wiping down parts of the patient's entire body. After a bath or wiping, the patient must be thoroughly dried with a dry towel or sheet. The bath must also be kept very clean and periodically disinfected. No matter how ill the patient is, it is necessary to wash their face every morning, and even better at night as well, and to monitor their cleanliness throughout the day. But especially carefully must one monitor the cleanliness of the hands, as well as the ears, periodically cleaning them of sulfur. The patient's hair must be combed daily, and for women braided into a braid; bedridden and especially infectious patients must have their hair clipped to the skin.
In order to preserve greater cleanliness in the hospital wards, it is necessary to subject all patients to a thorough sanitary treatment upon their very admission to the hospital. For this purpose, a so-called checkpoint system is usually arranged, in which the patient passes through all its premises in a strictly defined order of increasing purification and under no circumstances should fall back into a premise already passed through. The patient's own clothing goes for storage in a special room, and often it is necessary to subject it to disinfection or disinsection. Visitors should be admitted to patients only at a designated time and in clean, well-wrapped gowns worn obligatorily with sleeves and not as a cape; they must not sit on the patient's bed and under no circumstances bring anything without the permission of the medical staff.
Very great attention on the part of the nursing staff is required by the feeding of patients, which always to one degree or another has the significance of a therapeutic factor (see Dietotherapy). Therefore, the nursing staff must carefully observe the accurate execution of all dietary prescriptions by the patients and the very intake of food by the patients. Ambulatory patients are best fed at a common table in special rooms, while bedridden ones have to be given food in bed, and in many cases it is more convenient to place a special low bench across the bed for eating or to place a special L-shaped table next to it (Fig. 1), the board of which is directed across the bed. Patients who cannot eat by themselves must be fed accurately and timely by the nursing staff (passive feeding), and it is often necessary in one way or another to persuade or coax the patient to eat; under no circumstances should food simply be poured into the patient's mouth if they do not swallow it. Usually, liquid and mushy food is used for passive feeding. Drinking vessels of various shapes are very convenient for the passive feeding of patients with completely liquid food and for drinking (Fig. 2). In some cases, recourse must be made to various types of artificial feeding (see). During passive feeding, it is necessary to monitor the temperature of the food; blowing on food to cool it is under no circumstances permissible.
An extremely large role in the feeding of patients is played by the setting of the meal and the appearance of the food served. Neatly and accurately served and uncooled food, a neatly set table, the cleanliness of tableware and eating utensils stimulate appetite and make eating pleasant, and vice versa. After a meal, dirty dishes must be quickly removed and thoroughly washed with hot water, and in some cases disinfected. Especially important are drinking mugs or feeding cups when they stand near patients, especially severe ones.
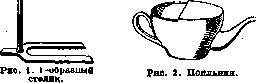
Besides creating a proper hygienic environment for the patient, the duties of the attending staff also include carrying out the regimen necessary for the patient, strictly following the established daily routine, and ensuring both physical and mental rest. In this regard, it is extremely important to maintain the strictest silence in the patient's room and its vicinity. The staff's demeanor toward the patient should be even, calm, soft, and polite. Visitors often have an unsettling effect on patients by talking to them about business and family troubles, and therefore the attending staff must monitor them and bar visitors if they exert a harmful effect on the patient's psyche; special care must be taken with severely ill patients: it is necessary to check on them more frequently, respond quickly to calls, help them change positions, take food, attend to physiological needs, etc. When moving a patient from one place to another, they are carried either in arms or on a stretcher; intra-hospital transport of various kinds is often used for this—wheeled stands for transporting beds, wheeled tables, wheel chairs, etc. Cultural care for the patient is of great importance, and the more so the longer the patient remains in a medical institution. To this end, medical institutions must have libraries for patients with a selection of books corresponding to the cultural demands and level of development of the patients; newspapers and magazines should be subscribed to in sufficient quantities. It goes without saying that reading must be regulated. Reading aloud should as a rule not be permitted. A radio with individual earphones at each bed is very useful. Radios with loudspeakers must not be permitted. Chess and checkers may be permitted in wards for mildly ill patients, and one must prevent excessive absorption in games that fatigue or agitate the patients. 2. Observation of patients and implementation of preventive measures. Being in more prolonged and close contact with patients than physicians, the attending staff must constantly observe the patients' condition, monitor all changes in their condition, take available measures to alleviate the patients' condition, and report everything to the attending physician, or, if necessary, the duty physician. In addition, the duties of the attending staff include the correct and timely collection of materials and preparation of patients for laboratory and other examinations, as well as assisting the physician with various kinds of manipulations. When observing a patient, one must first of all pay attention to the patient's general appearance and body position. The general appearance, especially the face and its expression, as well as the expression of the patient's eyes, along with the patient's position, often already immediately determine the type and severity of the disease (see Habitus). Particularly important are changes in facial expression that occur quickly and sharply, as they sometimes indicate the need for urgent measures. It is very important to observe the patient's skin, its color, the presence of edema, the appearance of rashes, especially those that can disappear quickly (e.g., urticaria), and the intensity, time, and sites of sweating. It is especially necessary to monitor the skin in severely debilitated patients in a passive or forced position, since bedsores can easily form in them (see). To avoid them, it is necessary to keep the skin of such patients particularly clean, wash it more frequently (especially the sacral region), prevent the patient from lying on wet surfaces, carefully smooth out linen folds, periodically change the patient's position, and finally use rubber-inflatable cushion rings (Fig. 3) placed under the sheet or wrapped in it or in special covers. The rings should be inflated with a special pump (and not by mouth), not too tightly, and placed so that the pressure-bearing area falls over the hole in the ring. Sometimes, for greater accuracy in observing the patient's condition, the attending staff must use the simplest anthropometric methods: weighing the patient, measuring height, chest circumference, abdomen, etc. (see Anthropometry). Observation of the patient's temperature consists in its systematic measurement (see Body temperature). Observation of cardiac activity by the attending staff boils down mainly to observing the pulse (see). Patient care for those with weakened heart activity requires the elimination of factors that hinder heart work—all sorts of agitation and the need to perform even minor physical exertion and movements, as well as giving the patient a position that alleviates their condition. Observation of the respiratory organs consists in observing the character of the patient's breathing, cough, and sputum discharged during coughing (see) (see also Hemoptysis). Care for patients with respiratory disorders or coughing consists in giving them a position that alleviates their condition. Sputum discharged during coughing must not be swallowed by patients, but must be spat into special sputum mugs (see). Observation of the digestive organs consists first of all in observing the patient's oral cavity and tongue, since their poor condition not only causes the patient extra suffering, but also threatens unpleasant and sometimes dangerous complications (parotitis, lymphadenitis, and even sepsis). For care of the oral

Figure 3. Under-lay ring.
cavity, more or less frequent antiseptic, refreshing, mucus-removing, and other mouthwashes are used (see), and in severe patients who are unable to rinse their mouths, the oral cavity is carefully wiped several times a day with cotton wool or gauze moistened with these solutions, which are wound around a finger or a notched stick. A heavily coated, dry, and cracked tongue should preferably be smeared several times a day with a mixture of glycerin and a 2% soda solution in equal parts. Furthermore, one must observe the patient's appetite, the onset of dyspeptic phenomena (belching, heartburn, nausea), and mainly vomitus (see Vomiting); the latter should preferably be kept in a special place until examined by a physician. If the patient's vomitus is spewed onto the floor, then before cleaning it up, it must be poured over for some time (half an hour to an hour) with some disinfecting solution. Patients with bloody vomit require special attention and measures: they must be put to bed, given absolute rest, not allowed to eat or drink, and have an ice pack placed on the epigastric region. In many cases, one has to resort to the artificial removal of gastric or duodenal contents (see Stomach, methods of stomach examination, Duodenal tube). Special attention must be paid to the condition and function of the intestine, observing its rumbling and bloating (see Flatulence), passage of gas, character of feces (see) and their frequency (see Constipation, Diarrhea), and the presence of hemorrhoids (see). Care for the patient's intestine consists mainly in ensuring a normal and regular bowel movement and cleanliness of the anal region. It is very important that the patient quickly satisfy the arising urge to defecate and not be forced to hold it in for a long time. For this purpose, severely ill patients are provided at their beds with portable pails with wooden seats or, much better, bedpans. They are usually either iron (enameled) or porcelain and have a round (Fig. 4) or elongated (Fig. 5) shape; for very emaciated patients, it is better to use rubber bedpans with an inflatable ring (Fig. 6). Upon completion of defecation, the bedpan must be immediately removed from the patient's room. If feces have to be Figure 4. Round bedpan.
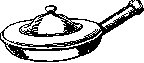

Figure 5. Elongated bedpan Figure 6. Rubber bedpan.
bedpan.
If specimens are to be left for examination or analysis, they are poured into a clean jar, but in no case are they left in the vessel. The area around the anus of the patient after defecation should also be thoroughly cleansed. Special care must be taken to maintain cleanliness in patients with fecal incontinence—their soiled linen should be changed immediately and the soiled areas of skin should be thoroughly washed and dried. In some cases of bowel disorders in patients, it becomes necessary to resort to various types of enemas (see). In cases of severe flatulence, rubber gas tubes with thick elastic walls and a rounded end, which has an opening, are used. This tube is inserted with the rounded end into the rectum as far as possible and left there for several hours. For abdominal pain, the application of heat to the abdomen often brings great relief to the patient. Hemorrhoidal pain in the anus is significantly relieved by applying cold compresses to it. Patients with intestinal bleeding (see Melaena) require special observation; the measures in these cases are the same as for gastric bleeding. When it is necessary to subject the gastrointestinal tract or part of it to X-ray examination, it must be well cleared of gas the day before the examination by giving a laxative and enemas. Observation of urination (see Diuresis) consists in observing the frequency and character of urination (see), the appearance of urine (see), its color, transparency, presence of sediment and impurities, especially blood (see Hematuria), as well as in measuring the daily or half-daily amount of it. Urine is usually collected in graduated glass beakers with lids (Fig. 7), which should be kept in a special place; in seriously ill patients, urine is collected in a special urinal, i.e., a glass bottle with a neck extending from one of its ends sideways and upward, so that urine does not pour out of it despite its recumbent position. In male urinals (Fig. 8), the shape of the neck is round, in female urinals (Fig. 9) it ends in a specially designed funnel, which is pressed against the external genital organs. In case of urinary incontinence in a patient, a urinal is placed under him, with which he lies, or a rubber bedpan is placed under him. Conversely, in cases of urinary retention, heat is applied to the lower abdomen or elastic catheterization (see) is resorted to. For analysis, usually a freshly released morning portion of urine collected in a clean container is sent, but sometimes it is necessary to send both morning and evening urine or different portions of the same urination. In some cases, usually for quantitative analyses, e.g., for sugar, it is necessary to send urine from a well-mixed daily amount of it (see Urine, urine analysis). In women, during menstruation or with leucorrhea, to prevent these impurities from getting into the urine collected for analysis, it is convenient to use glass tubes with fused edges, which are applied to the opening of the urethra so that it faces into the tube; the external genital organs should be washed with warm water beforehand.
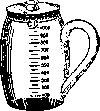

Figure 7. Beaker for measuring urine.

Figure 9. Female urinal.
Observation of the nervous system reduces to observing the sleep (see) of the patient, his mood, state of consciousness, sensitivity, and motor sphere. Care for the nervous system consists mainly in creating for the patient the quietest and most calm environment, protecting his sleep, and calming the patient. In delirium, especially febrile, the application of cold to the head often brings relief. Pain is sometimes relieved by changing the patient's position, or by applying heat or cold. During convulsions, especially clonic ones, the patient should be carefully held so that he does not fall off the bed or injure himself in any way. Dying patients in agony (see) require no less attention and care from the nursing staff. He should be with them as often as possible, in every way helping them and alleviating their condition. After the death of the patient, which in a hospital is usually confirmed by a physician, the body must be undressed, placed in an extended position, eyes closed, the often sagging lower jaw tied up, wrapped in a sheet and left on the bed for 2 hours. Only after this is the body carried out on special stretchers to a special room, where it is kept until autopsy. 3. Carrying out therapeutic measures. The carrying out of the vast majority of all therapeutic measures has to be done by the nursing staff, mainly by nurses. These measures consist in the timely, neat, and precise fulfillment of medical prescriptions and in the thoughtful and skillful carrying out of a whole variety of manipulations. The latter are often associated with the use of various instruments and apparatus, the design of which and handling of which should be well known to the nurse. The carrying out of medical prescriptions to the patient consists in the patient receiving the prescribed medications exactly at the time, in the form, and in the amount as prescribed to him. At this time, it is not only necessary to bring the medication to the patient, but also to make sure that it is taken on time, and even to help him take it. In order to avoid errors in administering medications and possible accidents during this process, it is necessary to keep medications in a large and strictly defined order. All potent substances must be stored in a separate, strictly designated place under lock, external preparations separately from internal ones, and they should have clearly visible labels of different characters. Each medication should always be put back in the same place from which it was taken. Under no circumstances should medications without labels on them be used from memory. It is necessary to develop the habit of carefully checking the correctness of the medication taken by the patient by the label before giving it to him. The majority of various dosage forms (see) are taken internally, but they are very often used otherwise—per rectum (see Enema, Suppositories), by inhalation (see Inhalation), on the skin in the form of rubs (see), mustard plasters (see Mustard), blisters


Figure 10. Ice bags. (see Spanish fly), on mucous membranes in the form of gargles (see), sprays (see Inhalation), cauterizations (see), douches (see Vaginal douches), instillations (see Instillators) and finally under the skin or intramuscularly by injections (see) and infusions (see). Whatever method is used for administering medication, it is necessary to carefully monitor the exact dosage prescribed, especially for potent drugs. In addition to drug therapy, compresses (see) and cups (see) are very often used, as well as local heat in the form of fomentations (see) and hot-water bottles (see), and local cold in the form of wet dressings (see), ice bags (fig. 10), or refrigerators (see Ice). When using ice bags and hot-water bottles, care must be taken that they are tightly closed and do not leak, and especially that they do not cause burns or excessive cooling of the skin. Therefore, a hot-water bottle or ice bag should not be placed directly on the patient's skin, but there should be some padding between them and the skin, for example, a towel, sheet, etc. Sometimes they, especially ice bags, have to be secured in some way on the spot where they should lie. Various physical therapeutic methods play a major role in treating the patient, such as baths (see) in all their forms-water baths, sand baths (see), mud baths (see Mud therapy), air baths (see Aerotherapy), sun baths (see Heliotherapy), light baths (see Phototherapy), then showers (see), douches (see), and wrapping (see). In some cases, it becomes necessary to resort to bloodletting (see), which can be performed by nurses using leeches (see). Sometimes it is necessary to perform stomach lavage; this is done with a thick stomach tube, at the end of which there is a large glass funnel. The tube is inserted into the stomach in the same way as when withdrawing stomach contents, the funnel is filled with the lavage fluid and raised upward; as soon as the liquid entering the stomach flows down to the neck of the funnel, the latter is moved downward, and the liquid flows back from the stomach into the funnel by siphon action; it is poured out, replaced with a new portion, the funnel is raised again, and so on; this is done until the desired goal is achieved. In addition to the stomach, bladder lavage is sometimes necessary (see Bladder, operations). In addition to performing most therapeutic measures independently, nursing staff often have to assist the physician in performing many more complex and dangerous therapeutic and diagnostic procedures. These mainly include various types of punctures (see Puncture)-veins, thoracic and abdominal cavities, lumbar (see Lumbar puncture), etc.-and related procedures-withdrawal of pleural exudates, removal of ascitic fluid, intravenous infusions, etc. For assistance to be effective and meaningful, it is necessary that the staff have a sufficient understanding of the procedure and its technique, be familiar with the necessary instruments and equipment, and know how to properly prepare them. All items for Patient care-drinkers, hot-water bottles, ice bags, bedpans and urinals, urinals, enema bottles and jugs, nozzles for them and for douches, thermometers, measuring cups, etc.-must be kept in impeccable cleanliness and, if possible, be for individual use. Those that are particularly easily soiled, such as bedpans, rings, and urinals, should be periodically disinfected, and some of them, such as nozzles and thermometers, should even be stored in disinfectant solutions. Care must be taken to ensure the cleanliness and proper functioning of instruments and apparatus, especially syringes and needles, by thoroughly cleaning them after use and sterilizing (see) before each use. Special care is required for special types of patients, and each type of care has its own specific characteristics. 1) Care for infectious patients consists first of all in the particularly careful implementation of general care measures, mainly cleanliness, and in carrying out current disinfection (see); this is especially important for patients in a severe unconscious state, as insufficient care can lead to unpleasant and sometimes dangerous complications. In some cases, with severe degrees of infectious intoxication (e.g., typhus), the patient's tongue may fall back, as sometimes occurs under general anesthesia, thereby impeding their breathing: patients turn blue and may even suffocate; in such cases, as with anesthesia, the tongue must be pulled forward, holding it with a gauze at the end-this immediately alleviates the patient's condition. In addition, it is necessary to ensure that there is no possibility of the already weakened patient acquiring any additional infection. In general, the staff caring for infectious patients must constantly be aware of the possibility of spreading infection and carefully monitor the cleanliness of the patient and objects that have been in contact with him, as well as their own body and clothing. The patient himself must be washed as often as possible and his linen changed. All items that have been with the patient, and especially his linen, must be thoroughly washed and disinfected or disinfested. The nursing staff should be dressed in special well-fastened and fully buttoned gowns, have a head covering, wash their hands frequently in disinfectant solutions and hot water with soap. Particular care should be taken to wash before leaving the infectious ward. It is highly desirable that the staff have, in addition to gowns, special clothing made of cotton fabric and wear it upon arrival and remove it when leaving the infectious ward. Patients in delirium, often accompanied by strong excitement, attempts to escape, etc., require special attention and care. Usually, in addition to applying cold to the head and various sedatives, they are placed on beds with side rails or covered with a sheet, the edges of which are attached to the bed. 2) Care for surgical and operated patients-see General anesthesia, Postoperative period, Burns, Wounds, 18 Desmurgy. 3) Care for gynecological patients consists in maintaining the cleanliness of the patient's genital organs and in carrying out special procedures-douches (see Vaginal douches), tampons (see Tamponade, tampons), etc. 4) Care for parturients and puerperal women-see Childbirth, management of labor, Postpartum period. 5) Care for children-see below. 6) Care for mental patients-see Mental patients.
A. Molchanov. Patient care for a sick child is a matter of paramount importance, determining the outcome of every disease. And the younger the child, the greater the importance of care for him. The significance of patient care is determined, on the one hand, by the special reactivity of the child to all external stimuli, whatever their nature (nutritional, microbial, thermal or mechanical), and on the other hand, by the enormous influence that all these stimuli have on the general somatic and psych. development of the child, especially in early childhood (see Infant). The uniqueness of patient care is inversely proportional to age: patient care for adolescents and schoolchildren differs little from patient care for adult patients (see above), whereas patient care for premature and newborn infants constitutes a special chapter in pediatrics (see Prematurity and Newborn). Age differences in patient care concern the qualitative and quantitative composition and number of personnel, certain specific features of the organization of the hygienic environment, direct observation of the sick child, the method of collecting material for laboratory research, and finally the method of carrying out therapeutic measures. In addition to the general requirements for medical personnel (see above), a nurse in charge of a sick child must meet the following requirements: to know well patient care for a healthy child and its dietetics, to master elementary pedagogy, to be able to organize the child's life, and finally to have an understanding of acute infections and measures to combat them. In addition, the nurse must be very observant, impeccably honest, accurate, and truthful in her answers to the doctor. The latter requirement stems from the absence of complaints from the patient, which sometimes have decisive importance in diagnosis and treatment. Without accurate and truthful information from the nurse, the doctor cannot give a correct assessment of the patient's condition or judge the effectiveness of the treatment being carried out. The role of the nurse is also important in relations with parents, especially with the mother. Often when a child is admitted to the hospital, the mother is separated from him for the first time. This often leads to her irritability and nervousness. Therefore, communication with parents should be calm and composed, answers should be brief, clear, and not go beyond the nurse's competence. When parents visit the child, the nurse ensures that they do not violate the prescribed regimen for the child. The requirements presented require the services of special nursing staff for sick children, requiring special training in courses on patient care for children. The number of sick children per nurse should not exceed 7-8 on average in infancy and 10-12 in older children. The question of direct admission of the mother to patient care for a sick child in the hospital has not found a uniform solution and depends on a number of conditions (the number of personnel, their authority and the culture of the mother). Taking into account the importance of emotional factors affecting the nervous trophism of the patient and the great labor intensity of patient care, it is desirable to admit the mother, with appropriate selection, to care for seriously ill patients under the supervision of authoritative nurses. The mother is thus given to help the nurse, not to replace her; thus, observations, weighing, collection of laboratory material, carrying out therapeutic measures and recording in the logbook should be done by the nurse. The creation of a hygienic environment for a sick child consists of general hygienic requirements for hospital premises (see Hospital, hospital equipment), the peculiarities of organizing the child's life (see Infant, hygiene), and finally the specific requirements for the organization of pediatric departments. After preliminary sanitary treatment (bath, hair and nail cutting, disinsection, etc.; see Sanitary treatment), the sick child needs maximum individual isolation and individual care (see Hospital-acquired infections). Therefore, when organizing a department for young sick children, the need for small rooms and extensive boxing in larger ones should be taken into account, and both open and closed boxes are permissible (see Boxes). The same isolation should be applied to children who suddenly fall ill in a group. For this purpose, an isolation ward with special equipment should be organized in the system of every children's institution (see Isolation Ward, Nursery). For mothers hospitalized with children, a separate room (bedroom, dining room) should be allocated. For walks, which are of great importance for the effectiveness of treatment, special rooms with constantly open windows or a space in the garden with a closed veranda are allocated. The uniqueness of nutrition for a sick infant and young child, requiring skillful preparation of various nutritious milk mixtures (see), necessitates the organization of a milk kitchen (see) and a complementary food kitchen in hospital departments with appropriate age portions and menus (see Child Nutrition). The equipment of wards for sick infants does not differ from the equipment for healthy children in children's groups. The equipment for older children has some peculiarities. Beds should be equipped with high, drop-down or fold-down sides that protect the child from falling. Hooks for hanging an individual chamber pot are installed on the lower surface of the bed. This hanging eliminates the possibility of soiling the crib with a chamber pot standing on the floor. In addition, in boxes, fold-down tables with sides are desirable for placing the child during bed-making. An indispensable accessory for each ward should also be cold and hot water. For feeding a child lying in bed, hanging tables are adapted, and for convalescent children, appropriate furniture (table, chairs or armchairs). Increasing the nervous tone is of very great importance for the convalescent child, so in addition to the regular nurse, a teacher is needed who knows how to organize activities. This is especially important for children with chronic illnesses. For proper observation of the sick child and assessment of his condition, records and information about the child in a certain form are necessary. Records and explanations of the caring personnel, along with objective examinations of the child, are the basis for diagnosis and treatment. All indicators of the child's condition should be recorded in the records: temperature, weight, quality and quantity of excreta (see), regurgitation (see Vomiting in children), vomiting (see), as well as unexpected changes in the child's condition: attacks of asphyxia (see), convulsions (see), convulsive cough (see Whooping cough) and others. Medical orders given are also noted here. - The presence in children of a number of pathological processes in the oral cavity (thrush, stomatitis, scarlet fever, diphtheria) makes it necessary to examine the pharynx of the sick child daily, both by the doctor and by the caring nurse. Collecting materials for laboratory research presents certain difficulties and requires special technique. Collecting sputum from children who cannot cough up sputum is done as follows: at the moment when the child coughs, the root of the tongue is held with a spatula and the sputum is removed with a sterile swab. The swab is carefully inserted into a sterile test tube. In infants, sputum is obtained with the help of a probe, one end of which is inserted into the stomach (on an empty stomach), while the other is attached to a syringe. One can also first introduce 100 cm3 of sterile physiological solution through the probe into the stomach and then withdraw the liquid, in which there will also be sputum. The method of collecting urine is as follows: the girl is placed on a clean rubber circle, under which a clean plate or basin is placed; for a boy, a tube is attached to the pubic area with adhesive tape, into which the penis is inserted. To preserve the urine in the tube, the upper part of the child's body is raised and the legs are tied with a diaper to the side of the bed. For collecting excreta, a glass tube, melted at both ends, is necessary. Such a tube is sterilized and inserted into the anus, where it is immediately filled with excreta. It is closed at both ends with sterile cotton wool, lowered into a test tube, and sent to the laboratory. For gastric lavage, a soft catheter, a short piece of glass tube connecting the catheter to a long rubber tube fitted on a funnel, is needed. Taking blood is easiest from the heel. After preliminary treatment (with alcohol and ether), two oblique incisions are made at an angle to each other with a Jenner needle or scalpel. The drops of blood that emerge are collected in a test tube in an amount of 30-35. If the drops come out slowly and the blood clots, the heel should be wiped and slight pressure applied to the entire foot. Puncture for taking blood is done where the vein is most visible: at the bend of the elbow, on the skull; sometimes it is most convenient to do this on the jugular vein, which clearly stands out on the neck above the sternocleidomastoid muscle, after the child has been placed on his back on a table so that the shoulders are at the level of the edge of the table and the head, supported by the nurse, hangs. The needle, fitted tightly on the syringe and not too thin, should be inserted in the direction of blood flow, after thoroughly disinfecting the puncture site.
After drawing blood into a syringe, in order to prevent clotting, the needle should be removed from the syringe and the blood quickly released into a test tube. After removing the needle from the vein, the latter should be pressed with a cotton tampon for a minute. Usually there is no bleeding in the surrounding cellular tissue. In children with an open fontanelle, the longitudinal sinus is punctured. Preparation for this operation consists of shaving the hair at the injection site and disinfecting the skin. For puncture, either an ordinary, not too thin Rekord needle is used, but if possible not with such a blunt tip as usual, or special needles: a short one, 6-7 mm long, or one with a thickening near the tip. The puncture is made from front to back in the posterior corner of the fontanelle along the midline with the needle tilted at approximately 40°. The child at this time lies on his back with his head fixed by the assistant's hands. After removing the needle, there is usually no bleeding; if blood does appear, the child should be quickly brought to a sitting position. For the technique of obtaining cerebrospinal fluid, see Lumbar puncture and Puncture. The carrying out of therapeutic measures should be closely linked to the general regimen (see Infant, hygiene). The main therapeutic factor--dietotherapy--requires from the nursing staff exceptional clarity, endurance, and technical skill. Errors in the quantity and quality of food prescribed by the doctor lead to a sharp worsening of the disease. Technical difficulties in feeding arise from the child's inability to suck due to underdevelopment of sucking reflexes (see Prematurity), from the impossibility of sucking due to congenital deformity (see Hare lip, Cleft palate), or from the child's refusal of food (lesion of the oral mucosa, loss of appetite, severe and unconscious state, manifestation of neuropathy) (see Anorexia). Methods of forced feeding: through a gastric tube, through a pipette (see Prematurity) and with a spoon. The latter is carried out as follows: the nurse presses the child's cheeks with two fingers of her hand, forcing the jaws to separate; a few drops of milk or nutrient mixture are poured into the thus open mouth, and the mouth is kept open until the child swallows the food. After that, the next spoonful is given. Refusal of food in neuropathic children is eliminated by creating the correct pedagogical environment and placing the child in a group (see Anorexia). The physical therapeutic methods widely used in pediatric practice require certain technical devices and very careful observation of the child's condition and reactivity, since often even a short stay outdoors in spring days is enough to cause burns. The use of prolonged heat--see Incubators, Hot water bottles; hydrotherapy--see Baths, Hydrotherapy; heliotherapy--see Heliotherapy; mercury-quartz therapy--see Light therapy, Mercury-quartz lamp. Features of P. C. in individual types of diseases: in skin diseases, it is necessary to create conditions that protect the skin from contamination, excessive pressure, and scratching. Baths used should be made of boiled water, linen should be sterilized and ironed. At points of great pressure (occiput, sacrum), rubber circles or specially made soft ones (from cotton and gauze) of appropriate size are placed. In cases of extensive skin lesions, a hammock is arranged. The walls of the crib on which the hammock is suspended are covered with a blanket in cold weather, and hot water bottles are placed under the hammock inside the crib. To prevent scratching, splints are applied to the child's elbow bends. P. C. in mouth diseases--see Thrush, Stomatitis; in diarrhea--see Atrophy, Dyspepsia; in respiratory tract diseases--see Pleurisy, Pneumonia, Grip, in childhood; in ear diseases--see Otitis. In P. C. for surgical patients, the necessary postoperative position is achieved by fixing the child in bed with special suspenders, with which he is tied to the mattress, or even more simply with armlets and leglets made of cotton and soft bandage and towel. Specific features of care--see Cleft palate, Pylorospasm. P. C. in infectious diseases--see the respective diseases.
Related articles
Mentioned in
Cite this page
“Patient Care.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/patient-care/