Prematurity
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Prematurity refers to birth before full term, defined as infants weighing less than 2,500 grams at birth. The article discusses the challenges in defining prematurity, distinguishing it from debility, and presents statistical data on its occurrence.
Encyclopedia article (1928–1936)
Prematurity (praematuritas, Frühgeburt), in the common understanding, the birth of a child before the full term of pregnancy. Such a definition, however, is theoretically and practically unsatisfactory, since first, the moment of conception, i.e., the beginning and consequently the duration of pregnancy cannot always be firmly established, second, a significant percentage of children that are undoubtedly full-term by time possess all the external and internal signs described below for premature infants and share their fate, and third, reverse cases are not uncommon—the birth of fully mature children in premature labor. Premature infants are children who differ from mature newborns by a specific external appearance and a certain underdevelopment of the most important internal organs and functions. In the overwhelming majority of cases, their initial weight does not exceed 2,500 g. This externally easily and unmistakably established sign of prematurity is therefore accepted for the definition of the concept itself: premature infants are children whose weight at birth does not exceed 2,500 g. Usually this weight is accompanied by a body length not exceeding 45 cm. Premature infants should be distinguished from weak-born children, or debiliacs. Congenital weakness (debilitas vitae congenita), or inferiority (Minderwertigkeit), is as it were an intermediate state between health and disease. It manifests itself in the low stability of the organism and low resistance to the external environment and various harmful influences, especially infections. The cause of debility in most cases is illness of the parents, especially the mother, most often chronic infections and toxicoses (syphilis, tbc, etc.). A large part of premature infants (but not all) are simultaneously debiliacs (see Congenital, congenital weakness). In the literature there is not yet complete clarity in the concept of prematurity. The French school, represented by Pinard, considers premature infants as debiliacs, whose congenital weakness is the result of incomplete development of the fetus. Tarnier and Budin, on the contrary, believe that "not all premature infants are debiliacs and not all debiliacs are premature infants." Pfaundler, without attaching importance to the initial weight of the fetus, distinguishes: a) immaturity of the fetus in a healthy mother during premature labor (for example, due to physical trauma or surgical intervention); b) reduced size—weight, length—in fully mature twins due to purely mechanical reasons constraining their development in the uterus; c) congenital weakness due to illness of the parents (see Congenital), especially the mother. In this last case, often but not always, the debilitated child is simultaneously premature, since the cause that damaged the fetus's organism also led to interruption of pregnancy before term. But Pfaundler himself and his followers recognize the difficulty, and often the impossibility, of differential diagnosis in each individual case. Finally, Ylppo, on the basis of his extensive material, does not assign decisive importance to parental illnesses and harmful influences on intrauterine life and defines prematurity depending on the degree of maturity of the fetus at the moment of birth; he considers weight the main indicator of this maturity and sets the boundary for it in prematurity not higher than 2,500 g. Most recent works adhere to this definition; it is theoretically correct and practically most convenient. Systematic statistics on the birth rate of premature infants do not exist. In the literature there is only fragmentary material from individual institutions in large cities for different periods. For example, in the Paris Maternité and Bodelot clinic for the period 1822-99, out of 188,204 infants, 29,071 were premature, or 15%; in Germany, Berlin, Chemnitz, and Opeln, with less statistical material, gave 10.3% (12,377 infants, of which 1,282 were premature). These figures should be considered rather exaggerated and not reflecting the true frequency of prematurity. For the USSR in the old literature there is only a report by Miller that out of 121,626 infants admitted to the former Moscow Foundling Home in 1809-80, 6,036, or less than 5%, had a weight less than 2,500 g. Recent data from 8 Moscow maternity homes and clinics for 1907-26 cover 127,028 births, of which 10,177 were premature, or 8% (Ivanskaya). In relation to live-born infants, premature infants constitute only 6.2%. Neither the war period nor the reduced nutrition of the population in 1918-20 had a noticeable effect on prematurity. Regarding the weight of premature infants, it is interesting to compare data on 6,196 premature infants in Moscow maternity homes with the material of Cherny (971 cases) and Ylppo (700 cases) (Table 1). These data show that about half of premature infants are born with a weight from 2,001-2,500 g. Table 1. Weight (in grams) Under 1,000..... From 1,001 to 1,500 From 1,501 to 2,000 From 2,001 TO 2,500 Moscow Germany (6,196 prema- (1,671 prema- ture infants) ture infants) in percent 17.5 7.0 12.7 19.0 21.6 27.0 48.2 47.0 It should be noted that the number of twins, which is less than 1% of the total number of births, reaches among premature infants in the USSR 19.6%, and in the West 19%. Etiology. Despite such prevalence of prematurity, its causes are still insufficiently studied, since the problems of biochemical processes in fetal development, as well as the factors causing the onset of labor, in particular—premature termination of pregnancy (see Antenatal protection of infancy), remain unclear. Therefore, the study of the etiology of prematurity still largely proceeds according to external signs, and in a large number of cases it remains completely unexplained (Table 2). The causes of premature birth may lie either in the fetus itself, or more often, in diseases and anomalies of the maternal organism, or in the mentioned, still unexplained biochemical processes of pregnancy and its termination, or finally in mechanical external influences. The significance of each of these factors as an etiological moment in prematurity is evident from Table 2. It systematizes the results of many years of observations in Okhrmatmlad NKZdr. For comparison, 47ft Causes of prematurity in 333 cases investigated by Group 1 in the premature and obstetric departments of the State scientific
institute for the protection of motherhood and infancy of the People's Commissariat of Health in Moscow Maternal diseases Syphilis ................ ............. Tuberculosis ....................................... Acute infections (angina, influenza, pneumonia, typhoid, erysipelas, colitis, malaria, pyelitis, cystitis)............... Eclampsia ............................ Chronic and subacute albuminuria.............. General diseases weakening the maternal organism (heart defect, diabetes, acute anemia, liver diseases) . . . Mental and nervous diseases (hystero-neurasthenia, epilepsy, mental disorders, deficiency, deaf-mutism)...... Toxicosis of pregnancy (intractable vomiting, rashes, itching, jaundice)............................. Insufficient nutrition of the mother during pregnancy (qualitative and quantitative). Avitaminosis........ Anomalies and diseases of the sex organs and birth canal of the mother Inflammation of tubes, ovaries, uterus, vagina (gonorrhea). Bleeding ............................ New growths of the sex organs (fibroma, cyst) . . . . Anomalies of uterine position .................. Infantilism of the mother-general and of the birth canal (narrow pelvis); uterine infantilism ...................... Professional hazards in the mother Including: ballerina, surveyor-working on knees; laboratory assistant-gas poisoning; overwork with strenuous housework..................... Maternal traumas Physical (fall accompanied by rupture of the membranes, bruises, concussions, heavy lifting)........ . . . Mental (fright, emotional stress, etc.)............ Disruption of pregnancy due to anomalies and diseases of the fetus and placenta From the placenta (premature detachment, placenta accreta) ........................ From the fetus (tumor of the lumbar region, cord prolapse, abnormal fetal position)......... Multiple births Twins ............................. Triplets .............................. Habitual familial miscarriages............... Artificial premature births............... Causes unclear . . ................... Total............. [Table data translated contextually according to medical statistics] ... Comparison in the same table with the frequency of the same diseases at the birth of normal children shows to what extent the listed factors can be considered specific for premature infants. Anomalies and diseases of the birth canal and eclampsia, along with placental anomalies and fetal position, occupy first place in the etiology of prematurity. Syphilis, contrary to the previously prevailing opinion, by no means inevitably causes prematurity and has a relatively small specific weight among its causes (according to Reiche's observations - 5%, Ilpe - 3.9%, and only 1.2% according to the State Scientific Institute material; Ivenskaya). Maternal tuberculosis can be considered a direct cause of prematurity only in the active stage with elevated temperature, cough, and impaired gas exchange. Also, the toxicoses of the maternal organism that are frequent during pregnancy become etiological factors only in cases of sharp exacerbation. Finally, contrary to common notions, physical and especially psychological traumas of the mother are only in particularly rare cases the actual cause of prematurity. The majority of twins and all triplets are born premature. The direct cause of their low weight is purely mechanical: insufficient dimensions of the uterus and intrauterine nutrition for multiple fetuses. The study of occupational hazards and occupational diseases as etiological factors of prematurity was not previously given due attention. The few observations and recent works so far indicate their influence through mechanical action (for example, prolonged work in a bent position) or chemical action (poisoning of the organism in chemical industries and laboratories). There are no mass statistics on the mortality of premature infants, but observations collected in the literature on small material (at most 668 premature infants according to Ilpe) show that the lower the initial weight of the premature infant, the higher the mortality. At the same time, premature infants die most of all in the first hours and days after birth. In this regard, Ilpe's material is particularly indicative (Table 3). [Table 3 data] Mortality of premature infants. Contrary to the widespread opinion about the weak viability of premature infants, many years of study at the Moscow State Scientific Institute for the Protection of Motherhood and Infancy and literary data indicate that even very premature infants can survive with proper care and protection from birth and external traumas. Premature infants with an initial weight of 800 g have been observed who survived and overcame the specific dangers inherent in prematurity. However, in the mass, premature infants naturally yield an incomparably higher mortality than full-term children. The main reason for this is the immaturity and underdevelopment of the most important life centers and organ functions of the premature infant. Therefore, the mortality of premature infants is higher the lower their initial birth weight. Twin premature infants show greater resilience than weak-born ones and those originating from sick mothers. Mortality in children with a burdened heredity (syphilis, tuberculosis, etc.) is significantly higher than in children of healthy parents. Pfaundler cites premature mortality figures from healthy mothers reaching up to 27%, versus 82% mortality for children from sick mothers with weakened nutrition. A significant portion of premature infants perish due to unskilled or insufficient care in the first hours and days after birth, which are extremely dangerous for premature infants (physiological weight loss, trauma, especially cooling). Therefore, for premature infants even more than for normal children, it remains true that their mortality coefficient depends on social conditions. Proper establishment of prematurity wards, children's rooms in maternity hospitals, widespread awareness in consultations for pregnant women and children, training of midwives and other medical personnel in the care of premature infants can and indeed do reduce premature mortality. Mass statistics show that almost 10% of premature infants die on the very first day and half of them do not survive to 1 year. But at the same time, out of 36 premature infants up to 1,000 g in weight, only two remained alive, and in groups with higher weight, mortality rapidly drops from 65% for 1,001-1,500 g to 33.5% for premature infants over 2,000 g. The external signs of prematurity, like the internal ones, appear stronger the smaller the weight and height of the premature infant. Emaciation is particularly sharp due to the almost complete absence of the subcutaneous fat layer (since fat deposition occurs in the very last months of intrauterine life), the skin is especially thin and gathers into folds, wrinkled on the face, which gives the premature infant an senile appearance; the entire skin, not excluding the face, is abundantly covered with downy hair and often has a dark red color. A large head with a high forehead, narrow chest, and short limbs, low-lying navel. The auricles due to cartilage underdevelopment hang like shapeless rags (Fig. 1). Ossification centers are usually absent in the epiphyseal parts of long bones, while the nails (contrary to common opinion) are often fully developed. The scrotum in boys is empty, the testicles are either still in the abdomen or stand high in the inguinal canal; in girls, the genital slit is open, and the labia minora protrude from under the labia majora. Characteristic of the entire appearance of these children is deep hibernation, complete immobility, a thin squeaky voice, shallow breathing, general weak manifestations of life. Features of the clinical behavior of premature infants. A. Temperature and thermoregulation. More essential than the external symptoms of fetal immaturity are the defects in the functioning of internal organs. They are especially significant in the area of heat production and regulation. Unlike a normal newborn with a stable temperature, in a premature infant it drops immediately after birth to 35° and below and remains within these limits for a long time (which in itself does not yet pose a danger to life; cases of survival even at temperatures below 30° have been noted in literature). One of the causes of hypothermia is increased heat loss, as
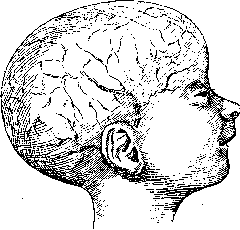
Figure 1.
The head of a premature infant with visible vessels. - The surface area of their skin, which emits heat, is relatively much larger than that of a normal child, while the body weight, i.e., the muscle tissue that generates heat, is poorly developed; furthermore, the fatty layer, which conserves the body's thermal energy, is absent in premature infants. The thermoregulatory centers are underdeveloped. Therefore, the temperature curve in them often has an erratic character: low temperature alternates with very high temperature, followed by a new sharp drop, often without apparent causes. Such an increase in t° can occur from many other causes, for example, from the absorption of sterile blood from foci of internal hemorrhages, to which premature infants are prone; infection, however—the most frequent cause of increased t° in normal children—in weak premature infants often occurs at low temperatures (Figure 2). B. Edemas and hardenings of the skin. Low body t° in premature infants is associated with a tendency toward edemas and hardenings of the skin and subcutaneous tissue, appearing from the first days of life on the limbs and genital parts. At autopsy, edemas of internal organs (brain, lungs) are often observed. The causes of this phenomenon are weakness of blood circulation due to general cardiac weakness, greater water content in the tissues of premature infants, and permeability of the walls of blood and lymphatic vessels. Special mention should be made of sclerema—hardenings of the subcutaneous fat layer. Sclerema most often affects areas with the greatest fat deposition—calves, thighs, cheeks. In more severe cases, the upper extremities and finally the face (cheeks) are affected, which further impairs the already weak sucking ability. Tissues affected by sclerema are hard to the touch, the skin is taut, as if fused, and does not form folds. Conditions favoring the development of sclerema are a) significant fluid loss, b) decreased t°, and c) primarily the special chemical composition of infant fat and the incompleteness of physicochemical processes in the body of a premature infant. According to Langer, in premature infants, easily solidifying fatty acids (stearic and palmitic) predominate over oleic. Treatment of sclerema should be directed toward eliminating the conditions causing this condition and consists of 1) supplying the body with sufficient fluid both by drinking and subcutaneous injection, 2) warming the body with hot water bottles or in a bath at 37-38°, and 3) stimulating cardiac activity—injection of a 10% solution of caffeine subcutaneously. C. An extremely characteristic and important feature of premature infants is hemorrhage, especially in the first days of life, when the immediate external trigger for them is trauma during the birth process, with forceps, turns, etc. Hemorrhages occur in premature infants in the skin (sometimes occupying very large areas), in the lungs, kidneys, and intestines. But the most dangerous for them are hemorrhages into the brain and cranial cavity, caused by rupture of the tentorium cerebelli, especially with rapid compression of the head and the overlapping of cranial bones (Beneke), or by venous congestion in the brain. According to Ilpe, hemorrhages are most common in the area of the sinus longitudinalis, at the point where veins empty into it. According to materials from the Moscow State Scientific Institute for the Protection of Motherhood and Infancy, brain hemorrhages were found at autopsy in 86% of premature infants with an initial weight of up to 1,500 g. Even in the highest group (2,000-2,500 g), Ilpe found them in 26% of all cases at autopsy. Meanwhile, it is extremely difficult to clinically diagnose brain hemorrhages in premature infants, because due to underdevelopment of the brain, the usual clinical symptoms—convulsions, paralysis, etc.—are often absent. - The relationship of premature infants to infection. The literature has established the view of greater susceptibility of premature infants to all infections and their lower resistance, or even complete helplessness against bacteria, which develop unimpeded in the imperfect body of a premature infant. However, long-term observations of the premature infant department of the aforementioned institute allow for more favorable conclusions, indicating that in this respect premature infants differ little from full-term infants (Ivinskaya). In diseases in the first weeks of life, premature infants often become ill at normal or even low t°, while in older premature infants, infections proceed without any peculiarities. D. Asphyxia. Breathing in premature infants is extremely shallow, often invisible to the eye, irregular, and not rhythmic (close to the Cheyne-Stokes type). The highest degree of its disorder are asphyxia attacks, characteristic only of these children. They consist of the premature infant suddenly stopping breathing, turning blue or even black, respiratory movements cease, and although the heartbeat continues, the child appears dead. Such attacks more often develop after or during feeding and last for a minute or two. Return to life sometimes occurs spontaneously, but usually the premature infant is brought out of such a dangerous state with hot baths at 40-42°, alternating hot and cold showers at 40-22°, rubbing the entire body, subcutaneous injection (10% caffeine), and artificial respiration with careful techniques; the revival method according to Schulze is unacceptable due to the possibility of hemorrhages. The causes of asphyxia are controversial. Older authors attribute it to poor expansion of the lungs during birth, Birk to overfeeding, French scientists to underfeeding, and Finkelstein to carbon dioxide intoxication due to the shallowness of breathing and narrowness of the respiratory tract. Closer to the truth is probably the hypothesis of the influence of underdevelopment of brain centers. In many cases of severe asphyxia, the cause is hemorrhage into the respiratory center (Ilpe). Secondary signs develop in premature infants at 3-4 months. These include: peculiarities of appearance, rickets, anemia, hernias, tetany. -1. Particularly characteristic is the asymmetrical head of a premature infant: the bones of the skull are so soft that they are easily cut with scissors at autopsy. Between the 4th and 8th months, bulges appear on the head, which sometimes remain until the second year of life. In the first weeks, the bones of the skull overlap each other, but later, conversely, with a disproportionate increase in the head relative to the body, all sutures widely diverge (megacephalus according to Ilpe) (Figure 3). The body of a premature infant is thin, the trunk is long and narrow, the chest is especially narrow; the arms and legs are thin, the entire figure has a fragile appearance. As weight increases, the forms become rounded, but in the general build, the characteristic appearance of a premature infant with severe underdevelopment of the bony part remains for a long time.

The head of a premature infant with visible vessels. - The surface area of their skin, which emits heat, is relatively much larger than that of a normal child, while the body weight, i.e., the muscle tissue that generates heat, is poorly developed; furthermore, the fatty layer, which conserves the body's thermal energy, is absent in premature infants. The thermoregulatory centers are underdeveloped. Therefore, the temperature curve in them often has an erratic character: low temperature alternates with very high temperature, followed by a new sharp drop, often without apparent causes. Such an increase in t° can occur from many other causes, for example, from the absorption of sterile blood from foci of internal hemorrhages, to which premature infants are prone; infection, however—the most frequent cause of increased t° in normal children—in weak premature infants often occurs at low temperatures (Figure 2). B. Edemas and hardenings of the skin. Low body t° in premature infants is associated with a tendency toward edemas and hardenings of the skin and subcutaneous tissue, appearing from the first days of life on the limbs and genital parts. At autopsy, edemas of internal organs (brain, lungs) are often observed. The causes of this phenomenon are weakness of blood circulation due to general cardiac weakness, greater water content in the tissues of premature infants, and permeability of the walls of blood and lymphatic vessels. Special mention should be made of sclerema—hardenings of the subcutaneous fat layer. Sclerema most often affects areas with the greatest fat deposition—calves, thighs, cheeks. In more severe cases, the upper extremities and finally the face (cheeks) are affected, which further impairs the already weak sucking ability. Tissues affected by sclerema are hard to the touch, the skin is taut, as if fused, and does not form folds. Conditions favoring the development of sclerema are a) significant fluid loss, b) decreased t°, and c) primarily the special chemical composition of infant fat and the incompleteness of physicochemical processes in the body of a premature infant. According to Langer, in premature infants, easily solidifying fatty acids (stearic and palmitic) predominate over oleic. Treatment of sclerema should be directed toward eliminating the conditions causing this condition and consists of 1) supplying the body with sufficient fluid both by drinking and subcutaneous injection, 2) warming the body with hot water bottles or in a bath at 37-38°, and 3) stimulating cardiac activity—injection of a 10% solution of caffeine subcutaneously. C. An extremely characteristic and important feature of premature infants is hemorrhage, especially in the first days of life, when the immediate external trigger for them is trauma during the birth process, with forceps, turns, etc. Hemorrhages occur in premature infants in the skin (sometimes occupying very large areas), in the lungs, kidneys, and intestines. But the most dangerous for them are hemorrhages into the brain and cranial cavity, caused by rupture of the tentorium cerebelli, especially with rapid compression of the head and the overlapping of cranial bones (Beneke), or by venous congestion in the brain. According to Ilpe, hemorrhages are most common in the area of the sinus longitudinalis, at the point where veins empty into it. According to materials from the Moscow State Scientific Institute for the Protection of Motherhood and Infancy, brain hemorrhages were found at autopsy in 86% of premature infants with an initial weight of up to 1,500 g. Even in the highest group (2,000-2,500 g), Ilpe found them in 26% of all cases at autopsy. Meanwhile, it is extremely difficult to clinically diagnose brain hemorrhages in premature infants, because due to underdevelopment of the brain, the usual clinical symptoms—convulsions, paralysis, etc.—are often absent. - The relationship of premature infants to infection. The literature has established the view of greater susceptibility of premature infants to all infections and their lower resistance, or even complete helplessness against bacteria, which develop unimpeded in the imperfect body of a premature infant. However, long-term observations of the premature infant department of the aforementioned institute allow for more favorable conclusions, indicating that in this respect premature infants differ little from full-term infants (Ivinskaya). In diseases in the first weeks of life, premature infants often become ill at normal or even low t°, while in older premature infants, infections proceed without any peculiarities. D. Asphyxia. Breathing in premature infants is extremely shallow, often invisible to the eye, irregular, and not rhythmic (close to the Cheyne-Stokes type). The highest degree of its disorder are asphyxia attacks, characteristic only of these children. They consist of the premature infant suddenly stopping breathing, turning blue or even black, respiratory movements cease, and although the heartbeat continues, the child appears dead. Such attacks more often develop after or during feeding and last for a minute or two. Return to life sometimes occurs spontaneously, but usually the premature infant is brought out of such a dangerous state with hot baths at 40-42°, alternating hot and cold showers at 40-22°, rubbing the entire body, subcutaneous injection (10% caffeine), and artificial respiration with careful techniques; the revival method according to Schulze is unacceptable due to the possibility of hemorrhages. The causes of asphyxia are controversial. Older authors attribute it to poor expansion of the lungs during birth, Birk to overfeeding, French scientists to underfeeding, and Finkelstein to carbon dioxide intoxication due to the shallowness of breathing and narrowness of the respiratory tract. Closer to the truth is probably the hypothesis of the influence of underdevelopment of brain centers. In many cases of severe asphyxia, the cause is hemorrhage into the respiratory center (Ilpe). Secondary signs develop in premature infants at 3-4 months. These include: peculiarities of appearance, rickets, anemia, hernias, tetany. -1. Particularly characteristic is the asymmetrical head of a premature infant: the bones of the skull are so soft that they are easily cut with scissors at autopsy. Between the 4th and 8th months, bulges appear on the head, which sometimes remain until the second year of life. In the first weeks, the bones of the skull overlap each other, but later, conversely, with a disproportionate increase in the head relative to the body, all sutures widely diverge (megacephalus according to Ilpe) (Figure 3). The body of a premature infant is thin, the trunk is long and narrow, the chest is especially narrow; the arms and legs are thin, the entire figure has a fragile appearance. As weight increases, the forms become rounded, but in the general build, the characteristic appearance of a premature infant with severe underdevelopment of the bony part remains for a long time.
Physical features—a wide, distended abdomen, very often with an umbilical hernia, a pyramidal chest with soft and pliable ribs during breathing (a consequence of rickets), a large head, a short neck, a long trunk on short legs, uneven fat deposition, which gives premature infants even in later months a 'family resemblance' (Rosenstern).-2. Rickets is a very early (often by the 2nd month) and constant companion of premature infants. Besides its duration, it takes on an especially pronounced expression in premature infants not only in the softening of the skull bones and bosses, but also in the extreme softness of the ribs, due to which they retract with every inhalation and form a transverse groove at the lower edge of the ribs. The prognosis for rickets in premature infants is poor: it persists for a long time in them and severely affects the already slow growth of the child; therefore, it is necessary to begin and vigorously carry out the usual treatment very early (see Rickets).-3. Anemia. Hyperglobulinia with a red blood cell count up to 6,000,000 and hemoglobin up to 120-130 (according to Sahli), which is usually observed in newborns, turns into anemia in premature infants from the 2nd-3rd week, reaching its greatest strength between the 4th-6th month and often occurring in very severe forms. The cause of anemia in premature infants is the insufficient activity of blood-forming organs, as well as to some extent the insufficient deposition of iron during the fetal period. Improvement in blood composition occurs very slowly, and even in the second, or even third, year of life, premature infants show a reduced percentage of hemoglobin. Treatment: fresh air, early supplementary feeding with vitamin-rich food, and especially the administration of large doses of iron (Ferrum reductum up to 1.5 g per day) (see Anemia).

-4. Hernias. Umbilical and inguinal hernias are especially common in premature infants with low weight. Hernias form more often in the first months and sometimes reach considerable size. The special predisposition of premature infants to hernias depends on the weak development and frequent separation of the abdominal muscles, and also plays some role the later falling off of the umbilical cord (sometimes on the 3rd week). Umbilical hernias usually have little effect on the condition of the children, and in later months they most often disappear spontaneously and require no intervention (in extreme cases, strips of adhesive plaster are applied).-5. Spasmophilia—increased excitability of the peripheral nervous system—is observed in premature infants more often and earlier than in full-term children and manifests in them not only in convulsions, but is especially common in a latent state. It is not noticeably associated with artificial feeding in them (as in normal children). Their predisposition to spasmophilia can be explained by their inherent deficiency of salts in the body, as well as the underdevelopment and impaired function of the endocrine glands. It often passes in them without any therapy with the general strengthening of the premature infant's body (see Spasmophilia). Care. A significant feature of the care of premature infants is the measures to raise the body temperature and protect from cooling, as this often determines the life of premature infants. For this, since ancient times, all sorts of methods have been used, from completely unhygienic and unacceptable wrapping in furs to the most complex devices-incubators-and the construction of special warming rooms (for their design and use-see Incubators). Incubators are not applicable in a home setting, but even in an institution they can be replaced by an individual thermal regimen. To raise and maintain the temperature of a premature infant, it is necessary to maintain 22-23° in the room (or ward), wrap the premature infant in hot water bottles, not allow cooling during turning, bathing, etc. As desirable as it is to achieve a normal temperature in the premature infant as soon as possible, it is necessary to be extremely cautious in dosing heat to avoid dangerous overheating, which sometimes manifests as a sharp drop in weight, restlessness, and refusal to suckle.
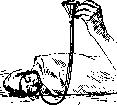
In all other respects, the usual rules for caring for infants should be applied (see Infant) with double caution in handling the especially fragile body of the premature infant. In particular, to soften the dry skin of the premature infant, it is lubricated, especially after bathing, with petrolatum, and the softest, flannel fabrics are used for clothing (wrapping a premature infant in cotton wool impedes skin respiration). The first bath is given after the umbilical wound has completely healed (bath temperature not below 37-40°). With regard to walks in cold weather, great caution should be exercised. Children can be taken out starting from two months and when weight reaches 2,000 g at an air temperature not more than 7-8° below zero, and mainly in the absence of wind; for the smallest children in winter, it is recommended to place one or two hot water bottles in the blanket. The duration of the stay outdoors initially does not exceed 5-10 minutes (Figure 4). The features of feeding premature infants lie both in the technique of feeding and in other quantitative and qualitative requirements for nutrition. Serious difficulties arise already in the first hours after birth due to the weakness of the body, extreme passivity during feeding, and poor sucking ability, 'Figure 4. Warming a premature infant.', 'Figure 5. Artificial feeding of a premature infant.'
the strength of the premature infant, creating a danger of underfeeding. On the other hand, underdevelopment and small capacity of the gastrointestinal tract more easily lead to indigestion, regurgitation, and vomiting. Meanwhile, the premature infant, losing more heat per unit of weight than a normal child, needs a relatively larger amount of food. At the same time, premature infants in the first months of life experience an increased need for proteins and salts compared to normal children, which are necessary for more intensive development. Therefore, the quantitative food requirement of premature infants depends on the composition and correlation of food substances. On breast milk alone, it should not be below 140-150 calories per 1 kg of weight, but when breast milk is supplemented with salts and proteins, it can be limited to 120-130 calories. Good results are obtained by adding 2-3% plasmon (milk protein - a German patented product) or curdled milk or buttermilk that is quite equivalent to it in digestibility and stimulating effect on the child's development, in an amount of 4-5% to breast milk. Fatty mixtures, in particular Cherny's mixture, give less satisfactory results, especially if they are introduced into the diet in a ratio exceeding 1:3 or 1:2 to breast milk. Even less useful are mixtures that increase only the caloric value of food but do not increase the protein and salt content (for example, adding sugar to milk). Breastfeeding encounters significant technical difficulties with premature infants. Especially weak premature infants are unable to suck even minimal amounts of milk from the breast. The cause is a small mouth, weakness of the muscles, and sometimes underdevelopment of the brain centers. Moreover, the lactational ability in women who have given birth before the physiological term is usually reduced, and milk production develops gradually, later than usual. The premature infant, however, is unable to serve as a developing force for the mother's breast. In such cases, the premature infant is given expressed breast milk, and to develop the mother's lactational ability, massage of the breast and expression of milk every 2 hours is performed, both manually and with a breast pump. In more difficult cases, it is necessary to resort to feeding from a very small nipple or a curved spoon, a pipette, and finally a tube. The tube should be soft, thin (catheter No. 14), its tip is lubricated with sterile oil and is inserted through the nose or mouth into the child lying on their back or side (Fig. 5). The first feeding must be established already 3-4 hours after birth in order to minimize the dangerous for the premature infant physiological weight loss in the first days. The number of feedings per day ranges from 7 to 12 times (every 1½-2 hours). Attempts to pour a large amount of milk at once (which would be necessary with normal 6-7 feedings) increase the tendency of premature infants to profuse regurgitation and vomiting. The six-hour night break for very small children has to be reduced to 4 hours. The further fate of the premature infant who has survived the dangers of the first 2-3 months of life, and in particular his mental development, is evaluated differently in the literature. Some (e.g. Finkelstein) believe that by the end of the first year of life the premature infant catches up with a normal child. However, the pessimistic prognosis of others (Ilpe) is more justified, who believe that the premature infant lags behind both physically and mentally for a long time. As long-term observations at the Moscow State Scientific Institute for the Protection of Motherhood and Infancy show, however, it is necessary to distinguish two groups: premature infants with an initial weight of up to 1,500 g give a sluggish weight and growth curve with long pauses and still at the age of 5-7 years show underdevelopment in weight, height, and chest volume. All the main dates of their physical and mental development are significantly delayed. For example, they are delayed in teething, walking, speech; speech defects are observed more frequently in them. The main cause of this backwardness lies in the immaturity of their organism, the imperfection of the major internal systems (respiration, digestion), underdevelopment of the endocrine glands, the inevitable rickets and anemia for them. The prognosis is significantly more favorable for children with a larger birth weight (close to 2,000 g and higher), especially for twins, whose development is incomparably better - they relatively quickly make up for the defects of birth and indeed often catch up in their development with a normal child by the age of one year.
Related articles
Mentioned in
Cite this page
“Prematurity.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/prematurity/