Ovariotomy
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia discusses the history, abdominal and vaginal techniques, and complications of ovariotomy—the surgical removal of the ovary. It details methods for managing cyst contents, vascular pedicles, and adhesions, reflecting surgical practices of the early 20th century.
Encyclopedia article (1928–1936)
OVARIOTOMY, a general term for all operations associated with the removal of the ovary. The removal of the ovary while preserving at least a small portion of its tissue is called ovarian resection. (According to Gubarev, it is more correct to say "ovariectomy," since almost the entire ovary is always removed, whereas the term ovariotomy indicates only its incision.) The first ovariotomy was performed in 1809 by McDowell in Kentucky.
OVARIOTOMY
In subsequent years, the development of technique and the clarification of details were advanced by Spencer Wells, Koeberle, Olshausen, Schroder, Krassovsky, Rein, and Slavyansky. In Russia, Severin Galenzovsky (Vilna; 1827) first attempted to perform an ovariotomy, but the operation was not completed due to extensive adhesions; the first successful ovariotomy was performed by Krassovsky in 1862 (St. Petersburg). Ovariotomy can be performed by two routes: abdominal and vaginal. In
the abdominal method, the skin incision is made along the midline, paramedians, or transversely. Upon opening the abdominal cavity, the surgeon orients themselves in the anatomical relationships. If the ovarian tumor is on a pedicle and free of adhesions, the operation is very simple: the tumor is easily extracted through the abdominal wound; preliminarily, if necessary, the tumor is emptied using a trocar (Figures 1 and 2) fitted with a long sterilized gutta-percha tube. Evacuation of the cyst is performed while the patient is in a horizontal position. The assistant grasps the abdomen of the patient
Figure 2. Nasse's trocar.
from the sides with both palms, compresses it, and thereby presses the cyst against the parietal layer of the incised peritoneum. At this time, the operator punctures the tumor with the trocar, and the fluid flows out of the cyst through the side outlet of the trocar; the walls of the cyst begin to collapse, the surgeon quickly fixes them with two Nelaton forceps (Figure 3), and the reduced tumor is brought out of the abdominal cavity through a small incision. Multilocular cysts are punctured
Figure 3. Nelaton's forceps.
sequentially. Then the pedicle is found, ligated, and the tumor attached to it is severed along with the adjacent part of the fallopian tube. When ligating, one should not use a simple ligature, but it is recommended to pierce the pedicle in the middle with a Deschamps needle bearing a double ligature; thus, two ligatures are obtained, upper and lower, which are tied in turn. Recently, most surgeons operate generally without mass ligatures (Fig. 4); the tumor pedicle is fixed with Kocher forceps, then transected, while the bleeding vessels are caught with hemostatic forceps and ligated individually (testicular artery, artery of the round ligament, and the terminal branch of the uterine artery); subsequently, both layers of the peritoneum covering
Figure 4. Ligation of the pedicle.
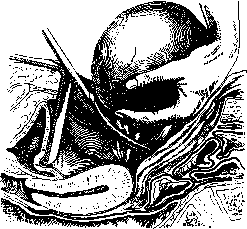
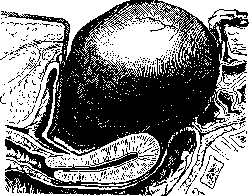
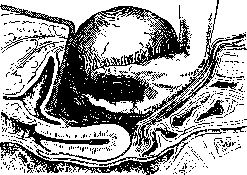
the pedicle are sutured. Such peritonealization excludes the possibility of adhesions between the intestines and the surgical stump, which prevents the occurrence of mechanical ileus. After treating the tumor pedicle, the abdominal cavity is toilet-cleaned: any cyst contents that accidentally entered the abdominal cavity are thoroughly removed (with gauze sponges), bleeding sites are inspected once more, and the abdominal wound is closed. At present, most surgeons consider it unnecessary to use the instruments proposed at the time for treating the cyst pedicle—Figure 5. Staffordshire knot (diagram); on the right—Gubarev's modification. [Karavaev's clamp, angiotribe (Tuffier, Doyen)] or searing the pedicle with the Paquelin cautery; neither is the ligation with the so-called Staffordshire knot performed anymore (Fig. 5). The suture material is catgut. The most frequent complication in ovariotomy is the presence of adhesions with adjacent organs, most often with the intestines (Fig. 6) (especially in the case of so-called giant tumors) (Fig. 7). In such cases, it is recommended to open the abdominal cavity near the umbilical ring, because here the peritoneum is most firmly fused with the underlying layers of the abdominal wall; a cautious, layered incision of the abdominal wall excludes the possibility of detachment of the parietal peritoneum from the abdominal wall. If the separation of intestinal adhesions presents great difficulties, it is better to leave a layer of the cyst wall on the intestine (Olshausen) than to worsen the prognosis of the operation by violating the integrity of the intestine in one or several places; the remaining inner layer of the cyst wall must be removed or burned off with the Paquelin cautery. In cases of extensive adhesions (rarely), one has to
Figure 6. Adhesion of the cyst to the intestine.
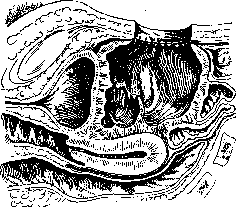
abandon the enucleation of the entire tumor and use so-called marsupialization (see). The omentum most frequently adheres to the cyst; it is usually easily separated by blunt dissection, and bleeding sites must be ligated. If there is a suppurating or dermoid cyst, the tumor must be removed entirely. If the latter fails, one must immediately perform a toilet, disinfect the contaminated areas (rivanol, ether); some in such cases drain the abdominal cavity. A further complication is the twisting of the cyst pedicle. The technical feature of the operation in these cases is as follows: the pedicle should not be untwisted, because untwisting disrupts thrombosed vessels and embolism can occur. If the pedicle is elongated, it should be ligated with a mass ligature above the thrombi located within it; if it is short, then a wedge-shaped excision of the pedicle is performed together with a part of the uterine angle. After ligating the bleeding arteries individually, the edges of the wound are brought together with sutures. There are so-called interligamentous ovarian tumors that have absolutely no pedicle and grow between the leaves of the broad ligament. In addition to true interligamentous ovarian tumors, there are also so-called pseudointerligamentous cysts. There is no uniform technique for removing interligamentous tumors. The most accepted technique: the peritoneum is dissected at the border of the implantation of the interligamentous cyst into the broad ligament, the serous cover is separated, and, adhering to the cyst wall, enucleation is begun (Fig. 8). When enucleating the tumor, one must be extremely careful not to injure the ureter. Upon
Figure 7. Huge ovarian cyst.
enucleation of the cyst and after the arrest of hemorrhage, the resulting cavity is closed with tight sutures. If it is not possible to entirely remove the cyst wall due to its thinness or previous inflammation, marsupialization is initiated (Fig. 9). Since statistics show that bilateral involvement of the ovary is very common (51.8%, and according to Döderlein, 90.9%), in cases of unquestionable malignancy of the tumor of one ovary, the other ovary should be removed even in young subjects. Ovariotomy can also be performed by the vaginal route—by incision of the anterior or posterior fornix. Posterior colpotomy was practiced by American surgeons
Figure 8. Enucleation of the cyst.
(Battey, Atlee, Byford), in Russia—by Lvov (Kazan; 1892), and was significantly improved by Ott (Leningrad). Anterior colpotomy was practiced by German surgeons led by Dührssen and Martin (Duhrssen, Martin). By the vaginal route, it is possible to recommend the removal of small mobile cystic tumors, and the choice of anterior or posterior colpotomy depends on the anatomical and topographical location of the tumor itself.

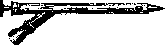
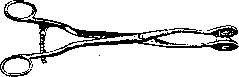

Performance of the operation - see Colpotomy. - The age of the patient is not a contraindication to O. The operation is successfully performed both at the very youngest age and in old age - in 80-year-old old women. In case of severe exhaustion of patients, O. is recommended to be performed under spinal anesthesia. In addition to impeccable surgical technique and strict adherence to asepsis, the prognosis depends especially on whether complications were present. According to the material of the gynecological clinic in Giessen, the mortality rate after O., excluding cancers and complicated cases, was 2%, and after ovariectomies performed for benign ovarian tumors, the mortality rate is only 0.7%. O. in complicated cases gives a much higher mortality rate (according to some statistics up to 15% and even 20%). Ovariectomy during pregnancy. Despite the fact that the childbearing function in ovarian tumors is reduced, the onset of pregnancy with them is not excluded: according to Martin, out of 1,732 deliveries, ovarian tumors were found in 20 cases (1.5%), according to Ols-hausen - in 3.9% of cases, according to the statistics of the Berlin obstetric clinic - in 0.1% of cases. Collective statistics show that out of 100 ovariectomies, 3 are during pregnancy; according to Yartsev's statistics, out of 2,000 ovariectomies - 68 ovariectomies complicated by pregnancy (3.4%); according to Lebedev's material, out of 412 ovariectomies - 28 cases (6.8%). Pregnancy can occur with both benign and malignant tumors. - The effect of ovarian tumors on the normal course of pregnancy and delivery depends on their anatomical location and size. Small cysts without adhesions, located in the small pelvis and having a long stalk, usually rise from the small pelvis to the large one as the pregnant uterus grows; but if the cyst lies interligamentary or is fixed in the small pelvis, then it is a mechanical obstacle during delivery. Pregnancy and delivery in the presence of an ovarian neoplasm can proceed normally, but complications can occur. A very serious complication during pregnancy, delivery, and in the postpartum period is twisting of the tumor stalk, rupture of the cyst due to compression, hemorrhage into the tumor, and finally suppuration. Recognition of an ovarian tumor in the first months of pregnancy presents no difficulty; it is much more difficult to diagnose a cyst at the end of pregnancy. - The question of indications for surgical intervention for ovarian tumors during pregnancy has not yet been finally resolved. Some authors object to performing O., based on the fact that in many cases of complications of pregnancy with ovarian tumors, delivery ends successfully, and after O., pregnancy is often interrupted (on average from 5% to 15%). In more recent data, this percentage is even lower. Therefore, the danger of interruption of pregnancy after operations is unfounded. It is better to operate in the first months of pregnancy despite the possibility of removal of the corpus luteum. The latter circumstance does not lead to interruption of pregnancy, as can be concluded from the observations of Essen-Moller, Ruge, and others. Even Veit pointed out that 'the prognosis of O. intra graviditatem is not only not worse than the prognosis of O. extra graviditatem, but even significantly more favorable'. This is because such operations are mostly performed on young patients whose bodies have greater resistance. Thus, as soon as an ovarian tumor is determined during pregnancy, its treatment should consist of surgical removal. Some recommend colpotomy, but most prefer laparotomy. In rarer cases, when the cyst is attached in the small pelvis or lies interligamentary and the pregnant uterus interferes with approaching the removal of the tumor, it is necessary to empty the uterus beforehand by means of the so-called small cesarean section.
Related articles
Mentioned in
Cite this page
“Ovariotomy.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/ovariotomy/