Evacuation
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
An overview of sanitary evacuation principles during wartime and mass disasters from the 1928-1936 Great Medical Encyclopedia, detailing the collection, sorting, transport, and staged medical care of the wounded and sick.
Encyclopedia article (1928–1936)
EVACUATION (from Latin evacuatio - removal, emptying). By sanitary evacuation is meant the removal of contingents in need of treatment, with their simultaneous placement in conditions most favorable for the promptest recovery and restoration of working capacity. Sanitary evacuation represents a complex system of measures for collecting evacuees, providing them with initial medical aid, preparing them for transport, sorting, rendering medical aid en route, and placing them in special medical institutions. Sanitary evacuation is used in all cases when treatment on the spot proves impossible for various reasons. This happens most often during mass casualties, during war and national disasters (earthquakes, floods, famine, etc.). In wartime, sanitary evacuation pursues two goals: 1) the removal from the active forces of the wounded, those affected by chemical warfare agents, and the sick, who restrict the maneuverability of military units and formations; 2) the restoration of the combat capability of the evacuated by organizing their most rational treatment in combination with the evacuation process. The provision of initial medical aid, the determination of indications for sanitary evacuation, the collection of evacuees, and their preparation for transportation are in the army the duty of the medical service of military units. The removal of evacuees from the forward area and the provision of qualified medical aid to them, as a rule, is carried out by the medical service of military formations (divisions), while the placement of the wounded and sick for special treatment in stationary medical institutions of the army rear and the internal region is usually entrusted to the sanitary service of large military associations (armies, fronts, and military districts). Evacuees use various types of sanitary transport (see Sanitary transport) and pass along their way through a series of intermediate medical institutions where they are given medical aid, sorted, and provided with rest. Such medical institutions or groups of them (hospital bases) are called stages of sanitary evacuation, and sanitary evacuation itself is identified by some authors with so-called staged treatment. Stages of sanitary evacuation, as a rule, are usually located at places of transfer from one type of transport to another. In addition, stages of sanitary evacuation have to be deployed on evacuation routes of considerable length to provide medical aid and treatment to contingents incapable of enduring prolonged transportation. The segment of the evacuation route between the stages of sanitary evacuation with the transport serving it is called a link of sanitary evacuation. Since the removal of evacuees by each stage of sanitary evacuation is carried out "toward oneself," sanitary transport vehicles operating in one or another link of sanitary evacuation are attached to the rear stage of sanitary evacuation and are sent forward to work. The path of sanitary evacuation with all the sanitary assets located on it, leading to the rear from any military formation, is called the axis of sanitary evacuation of this formation. The equipment of the axes of sanitary evacuation is carried out along evacuation directions, differing from one another in the intensity of the flow of evacuees. Evacuation routes and directions by type of communication means are divided into dirt, railway, water, and air. Dirt routes of sanitary evacuation provided for sanitary evacuation may coincide with roads intended for the supply of provisions to the troops, or are allocated separately. In this case, to ensure unidirectional movement, which has significant advantages with an intensive flow of transport vehicles, empty sanitary transport moves along the supply routes, and empty vehicles freed from cargo return to the rear along roads designated for sanitary evacuation. Even greater conveniences for the movement of wagon trains are created by the allocation of parallel roads for horse-, motor-, and tractor-drawn transports, which differ in various speeds of movement and require different construction of the roadbed. The coincidence of evacuation routes with the return routes of empty return military (non-sanitary) transports makes it possible to use the latter for the transportation of the wounded and sick evacuated to the rear. However, practical difficulties in adapting such empty vehicles for the transportation of severely wounded persons in need of special rest, as well as the discrepancy between the return points of freight transport and the stages of sanitary evacuation, compel the medical service to have its own special sanitary transport in its organizational system. Modern regulations of the Workers' and Peasants' Red Army resolve the issue of the organized use of return empty freight transport for sanitary evacuation purposes by allocating two streams of evacuees along dirt roads: a) the severely wounded and sick are transported from forward medical aid points to that stage of sanitary evacuation where they can most likely be provided with the required medical aid and treatment appropriate to their health—on sanitary carts and automobiles; b) the lightly wounded and sick, sent from forward medical aid points to the area of transshipment of property brought up to the troops from the wagon trains of one supply link to the transport of another link—by return empty vehicles. Such places (areas) of transshipment are called exchange points (division collection points—DCP, corps collection points—CCP) and are distinguished by the type of cargo (artillery, transport). Collection points for the lightly wounded (CPL) are deployed at the DCP, and field evacuation reception points (FEP) are deployed at the CCP, where the wounded easily evacuated by return empty freight transport are provided with medical aid, as well as short-term rest and food. Return empty railway freight cars are included in temporary sanitary trains (TST) and are more easily adapted for the transportation of evacuees. The greatest difficulties in evacuation are presented by the task of ensuring the approximation of qualified medical aid to the evacuees in accordance with the type and nature of the lesion or disease. In contrast to the transportation of cargo and the organization of the transportation of healthy people, in the composition of evacuated contingents we have very different groups, the state of which is subject to sharp fluctuations during the transportation process, in accordance with which the attitude toward these groups also constantly changes. Sanitary evacuation must be accompanied by sorting at each stage, which leads to a constant change in evacuation groupings. The latter, in turn, must provide for: a) the method of transportation (sitting, lying, walking); b) the type of transport (sanitary cart, sanitary automobile, sanitary airplane, unadapted freight transport cart, etc.); c) the destination (address) of the transport (to which stage, to which medical institution directed) and d) the urgency of the transport. The combat situation, the availability of transport resources, and the capacity of the stages of sanitary evacuation exert a significant influence on the evacuation grouping. Under the real threat of the impact of enemy combat assets, the indications for leaving in place and the volume of medical aid at the stages of sanitary evacuation are significantly reduced. The organization of the evacuation apparatus and its management require the greatest operational efficiency, anticipation of various kinds of possibilities, and the availability of reserve funds to parry any contingencies. The distribution of treatment and evacuation resources can be more or less stable only in the internal region, in the territory of military districts of the country's rear, where hospital bases consisting of medical institutions of various specialties are deployed in large populated areas according to a pre-planned plan. According to modern views (Schickele, 1934), at least 60% of all beds available to the army evacuation apparatus must be concentrated here. Each internal district, depending on the network of communication routes, is expediently divided into sectors (regions) with the consolidation of hospital bases and separate hospitals located in such a sector under the management of the chief of the district or distribution evacuation point (Fig. 1). Hospitals located in one populated area in the territory of the internal military district are part of the local evacuation point. Within the evacuation points, the bed apparatus can be grouped into two large groups: a) therapeutic, consisting of hospitals for the treatment of the sick, those affected by chemical warfare agents, and contagious patients, and b) surgical—for the treatment of the wounded and the sick with diseases of the eyes, ear, throat, and nose. Individual hospitals included in or assigned to a particular evacuation point may be located at some distance from the main hospital base as branches. Each district evacuation point must have special hospitals or departments for the treatment of fractures, foot, skin-venereal, nervous, psychiatric, cardiac, and dental diseases, as well as for X-ray therapy. Urological, jaw departments and hospitals, for special bone surgery and for surgical tuberculosis, as well as sanatoriums, may not be allocated in every district evacuation point, but serve several regions, since the deployment of hospital units with a capacity of less than 200 beds turns out to be uneconomical. In frontline, army, and troop hospitals, only lightly sick and wounded are detained until complete recovery in the presence of vacant places. In addition, severely wounded and sick persons who do not tolerate transportation at all settle on evacuation beds. The percentage of wounded and sick detained...
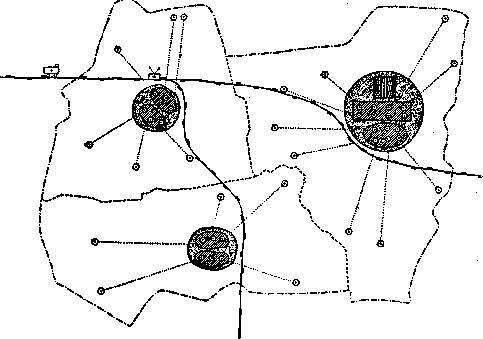
Legend: --.. Conventional signs: boundaries of the inner district; boundaries of a region (sector); railway; sanitary train; distributors of a district evacuation point; local evacuation point; group of surgical hospitals; group of therapeutic hospitals; group of special hospitals of district (regional) significance; group of special hospitals of interdistrict significance; individual hospitals assigned to the evacuation point. Figure 1. Scheme of sanitary evacuation and hospitalization in the inner region. EVIPAN of those accommodated on evacuation beds depends primarily on the combat situation; the largest number is evacuated during periods of intense combat, when the troop and army stages of sanitary evacuation are forced to pass through themselves such a quantity of evacuees within a single 24-hour period that it often exceeds the capacity of their bed apparatus. On average, at least 60% of the wounded and sick are evacuated to the inner region (Toubert). The total number of evacuees in wartime is calculated in millions; thus, from the beginning of the World War until October 1, 1916, about 4,000,000 people were evacuated in the Russian army; the number of admissions to hospitals during 4 years of war in the French army reaches 9,000,000, and in the German army it equals 10,080,470 people. The "rhythm" of evacuation is shown in the diagram (Fig. 2), from which it can be seen that the largest number of evacuees falls on the summer months, when combat operations were more intensive. The ratio of evacuated wounded and sick is given in the diagram (Fig. 3), relating to one of the distribution evacuation points. This diagram shows that at the beginning of the war, combat casualties predominated in the Russian army, and towards the end, the loss due to illness increased. The unevenness of the flow of evacuees in qualitative and quantitative terms is most pronounced in the troop and army regions, where the load on both the transport and bed apparatus is subject to constant and sharp fluctuations. In order to be able to provide transport and beds for the flow of evacuees to the rear under all conditions, it is necessary to have a powerful reserve of flexible and maneuverable means distributed along individual evacuation routes. Communication is hampered, and on individual routes may be completely disrupted by enemy air operations. To monitor the condition of evacuees on the way at intermediate in thousand, 800
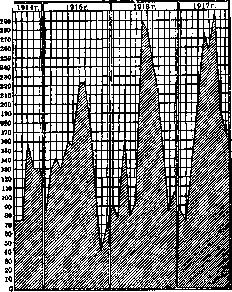
army in the World War of 1914-1917 by months with the stages of sanitary evacuation and a smoothly operating "reporting service" based on constant (dispatching) accounting of the state and work of the entire evacuation apparatus plays an exceptionally important role in managing sanitary evacuation. Under conditions of modern warfare, sanitary evacuation sharply ) ieur o 5r. 1 1918 1917 =- =2»55=;«;-==>;;=» 4- i -|- Oo 11» > t - £» _... __Lj- -X- 44- £. ____i / l j -3-iI ' t __l±., __L_\_____j T_ I-iv-4-j--t:ii: l-* -I-I* ::> i,' i J V L ,„ 4- l - X %- J' t 4 „L 15^y-'$/ i-H I^ t „-/-11--- _ x "J and /E o-----.-------------------------~i. "=T^ x- Figure 3. Admission of evacuees to the Moscow distribution evacuation point in the World War of 1914-1917. station control and evacuation points are opened with a small number of beds to accommodate those unable to endure further transportation. The entire organization and deployment of sanitary and evacuation work is built according to a plan. The basis for drawing up the evacuation plan is preliminary calculations of the number of expected casualties, data on communication routes, and areas where stages of sanitary evacuation can be opened. In accordance with these calculations, hospital, transport, and other sanitary facilities are distributed, and the necessary reserve of these facilities is created at the disposal of senior sanitary commanders. The evacuation plan indicates the deadlines for deploying the stages of sanitary evacuation, the scope of medical work for each of them, and simultaneously outlines assumptions about sanitary and evacuation maneuvers depending on the tasks assigned to the troops provided for in terms of medical and evacuation treatment. The mass nature of the contingents requiring treatment in wartime makes the doctrine of sanitary evacuation one of the most important sections of sanitary tactics (see). B. Leonardov.
EVIPAN, N-methyl-C-C-cyclohexenyl-methyl-barbituric acid, a white crystalline tasteless powder with a melting point of 143-150°. Sparingly soluble in water. A hypnotic drug possessing an extremely rapid, deep, but short-lived action. Well tolerated by the stomach and produces no side effects. Due to the short duration of the effect, it is almost never used. Of much greater importance has become the sodium salt of Evipan—Evipan-sodium—as an agent for general anesthesia. Weese and Scharf noted in animal experiments the onset of anesthesia already during the injection of 25 mg per kg of body weight. The hypnotic and narcotic doses lie very close, while the lethal dose is 4 times greater than the narcotic dose. In humans, the intravenous administration of a freshly prepared 10% solution of Evipan-sodium produces deep sleep after approximately 30 seconds, passing without a period of excitation into complete anesthesia (after 1-3 minutes), lasting 15-25 minutes. Recommended dosage: up to 50 kg of the patient's weight—7 cm3, for every subsequent 5 kg—0.3-0.5 cm3 more, but not more than 10 cm3 in total. Most authors point to the need for individual dosage, depending on the state of the patient's strength and the reaction to the drug. It should be injected very slowly, at a rate of approx. 15 seconds for each cm3, and no more than is necessary to achieve complete anesthesia occurring during the injection itself. With such administration, after only 3 cm3, deep sleep ensues, which can be used as basal anesthesia or preliminary before ether or chloroform anesthesia, as well as before local anesthesia (Frigyesi). Already 50-60 seconds after the start of the injection, the corneal reflex disappears, breathing becomes deeper and slower, the pulse quickens by 10-30 beats per minute, and blood pressure drops by 5-20 mm. After 15 minutes, the corneal reflexes return, and after 20-25 minutes, the reaction to a call returns. Among side effects, at the beginning of falling asleep, frequent small tonic twitches of the entire body and extremities are noted. Sometimes at the beginning of deep anesthesia, strong twitches are observed. Upon awakening, there is complete amnesia, mild headache, and in 5% of cases, vomiting. With rapid administration, collapse occurs. Out of over 100,000 cases of evipan anesthesia described in the literature, 29 deaths have been published. To a significant extent, they can be attributed to overdose and too rapid administration, but in some cases, like with Weese (Redman, a case of death with 4 cm3 of Evipan-sodium), it falls to the share of the drug itself. In view of the fact that the drug is decomposed by the liver during evipan anesthesia, mild jaundice was observed in a small percentage of cases. A contraindication to its use is liver disease. Evipan is also poorly tolerated by patients with bronchial asthma (paralysis of the respiratory center) and with a tendency to collapse (lability of the autonomic nervous system).
Related articles
Mentioned in
- Ampoule and Ampullitis
- Anus
- Audiometer and Auditorium
- Boris Weisbrod
- Brephotomy
- Constipation (Constipation is generally defined as stool that)
- Diarrhea
- Dressing Squad
- Eructation
- Graphical Representations (GRAPHICAL REPRESENTATIONS)
- Hospital
- Isolation-Transit Points
- Kitasato Filter
- Kuchaidze
- Larrey
- Maneuvers
- Market
- Medical Aid Station
- Meteorism
- Mikhnov
Cite this page
“Evacuation.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/evacuation/