Sanatorium
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
A Soviet sanatorium is a type of medical institution that differs from hospitals in patient composition and treatment methods, focusing on natural healing factors, diet therapy, physical therapy, and work therapy. The article describes the historical development of sanatoriums in the Soviet Union, their organization, types, medical services, and the importance of sanatorium regime in patient recovery.
Encyclopedia article (1928–1936)
SANATORIUM, a type of therapeutic and preventive institution, differing from hospitals in the composition of patients and methods of therapeutic and preventive impact. The contingent of S. consists mainly of convalescents after severe diseases and operations, as well as patients with not too advanced forms of certain chronic diseases. In S., natural healing factors, diet therapy, physiotherapy, physical culture, work therapy, sanatorium regime, etc. are widely applied; drug treatment, unlike in hospitals, is applied on a limited scale. However, under Soviet conditions, there is no major fundamental difference between S. and other inpatient institutions. The boundaries between the hospital and S. are gradually blurring, as all methods of hospital treatment are applied in S. when necessary. Historical data. Sanatoriums arose in the first half of the 19th century in Western Europe as highly qualified institutions intended for serving the wealthy classes of society. Only with the development of social insurance and national associations for the fight against tuberculosis did S. begin to open for the poor as well. But even now, most S. in the West are expensive institutions serving mainly wealthy people. In pre-revolutionary Russia, there were few S. During the war, the Union of Cities opened S. for convalescents after wounds and severe diseases of participants in active armies. The October Revolution gave a powerful impetus to the broad development of sanatorium construction, primarily at state resorts. In addition, former palaces, villas, dachas, and estates of landowners in various corners of the Soviet Union were adapted for S. and rest homes. This network proved to be clearly insufficient and poorly suited for the purposes of sanatorium work, and at present new construction of S. (mainly by social insurance bodies) is being carried out taking into account the latest achievements of medicine and technology. Network of S. The largest number of S. is concentrated at state resorts of Crimea, Caucasian mineral waters, Black Sea coast, etc. [see separate tables (art. 551-552)]. In addition to resort S., the USSR has a significant network of so-called local S., managed by health authorities, the All-Union Central Council of Trade Unions, and other departments and organizations. Moscow and Leningrad regions possess especially large and highly qualified networks of local S. The number of sanatorium beds increased from 26,372 in 1928 to 66,339 beds in 1932, the network of local S. reached 20,000 beds. In 1933, the network of sanatoriums of social insurance bodies alone reached 9,410 beds. Types of sanatoriums. S. at resorts are built according to the specialization of the resort and in accordance with the contingent of patients by type of disease. Thus, at balneological resorts, S. function specifically for gastroenterological patients and patients with metabolic diseases (Essentuki), cardiological (Kislovodsk), gynecological (Pyatigorsk), renal (Zheleznovodsk); at climatic resorts - tuberculosis S., sanatoriums for neurotics, etc. Local S. are usually differentiated by the nature of the diseases to be treated - tuberculosis, bone-tuberculosis, therapeutic, neuropsychiatric, as well as by the contingent of patients - children and for adults. (For indications for sanatorium treatment of tuberculosis patients - see Tuberculosis of the lungs.) In therapeutic S. (for patients with cardiovascular diseases, respiratory organs of non-tuberculous nature, digestive organs, movement organs, blood diseases), patients with temporary impairment of general or professional working capacity are directed. A special type of physiodietetic S. sets as its task the treatment of patients suffering from metabolic disorders and endocrine system diseases, diseases of the gastrointestinal tract and blood diseases, by diet, hormone therapy, physiotherapy, mineral waters and drug therapy. - Open neuropsychiatric sanatoriums can only admit those patients who in a relatively short time can fully or to a large extent restore their neuropsychological balance and professional working capacity. Organization of medical services. Depending on the profile and medical indications, the entire organization of medical work in S. is built - treatment methods, medical services, personnel, regime, nutrition, etc. Sanatoriums at resorts use general resort balneo-physiotherapy installations (bathhouses, mud therapy facilities, mineral water drinking pavilions, air-solariums, medical beaches, physio-mechanotherapy cabinets, etc.) and diagnostic institutions (laboratories, X-ray, electrocardiograph, etc.) for carrying out the treatment plan. Local S. usually have air-solariums, verandas for lying in the open air (Liegehalle), swimming pools, physiotherapy cabinets, water treatment facilities, laboratory and X-ray. Recently, the use of mud therapy in non-resort conditions (mud and peat), as well as the use of artificial mineral baths outside the resort - carbonic and hydrogen sulfide - has been introduced into sanatorium practice. Night S. are urban S. of open type and their task is to combine the treatment of the patient with continuing professional activities with the aim of preventing loss of working capacity. The patient during his stay in the night S., without being separated from production, is in hygienic housing conditions, receives additional nutrition, follows the established regime, undergoes sanitary-educational processing, acquires necessary hygienic skills and receives necessary treatment. In night S., in addition to those in need of preventive treatment methods without being separated from production, patients discharged from closed S. or hospitals are also directed with the aim of consolidating the effectiveness of inpatient treatment. On the other hand, the first group of patients undergoes observation with the aim of clarifying the diagnosis and, if necessary, directing them to closed treatment institutions and for special treatment with the aim of establishing the need to change profession, etc. Night S. are usually organized at hospitals, prophylactoriums, dispensaries. In the latter cases, they use the physiotherapeutic, diagnostic and other installations available in these institutions. Usually, male and female night sanatoriums are organized separately, or male and female groups alternate at certain intervals. Night sanatoriums are attached to specific enterprises, and individual shifts of patients are usually composed of workers from specific shops. Therefore, the regime of the night S., first of all, the hours of arrival and morning rising, vary depending on the working hours and shift work of the workers of this shop and enterprise. Management of S. is entrusted to chief physicians, the household-administrative work is carried out by the manager of the S. household. At present, at a number of resorts, managers (directors) of S. are administrators, to whom managers of the medical part of S. are appointed, responsible for the organization of treatment work and being chairmen of the so-called sanatorium treatment consultation, which includes the physicians of the S. The staff of S. varies depending on specialization and capacity. The staffing norms in S. (the number of patients per 1 member of staff) are as follows: Positions In S. at resorts and therapeutic local S. In S. for tuberculosis and severe patients Physician 40-50 25-30 16-18 20-40 40-50 35-40 18-20 10-12 20-25 40-50 Junior care personnel Sanatorium regime covers the entire daily routine of the patient; it should be built in accordance with the profile of the S. (different at drinking, mud, climatic resorts and local S.) and be strictly individualized. For the convenience of organizing the regime and monitoring it in S., several regime schemes are established, containing different ratios of rest and load (see Resorts, resorts of the USSR). Nutrition of patients in sanatoriums is under the supervision of a physician specially designated for this purpose. The total caloricity of food varies from 3,000 to 4,000 calories per day. In special sanatoriums, depending on their purpose, diet tables have been introduced, and the general management of diet nutrition is entrusted to a dietitian. Physical culture and sanitary-educational work. Physical culture in S. is applied in the broad sense of the word, starting with body hygiene, morning cold rubdowns, douches and showers, physical culture exercises, exercises for individual systems and organs, teaching proper breathing, walking, rest, and ending with all kinds of games, excursions, etc. The task of the treating physician - together with the physical culture physician or instructor - is to dose it depending on the severity of cases, age composition, profession, etc., and to choose the most suitable complex, establishing a gradual increase in physical culture exercises. Cultural-sanitary-educational work should be dosed along with other treatment methods, for which schemes for the assignment of cultural-sanitary-educational work are established, providing for both quantity and duration. - A completely new and therefore very difficult, but also extremely important task is the introduction of the element of dosed therapeutic labor into the everyday life of S., which beneficially affects the mental state of patients.
Work therapy, by placing certain demands on the body's load, serves as a training and strengthening medium, helping the attending physician to precisely control the patient's work capacity, and facilitates the patient's transition to normal professional life. By instilling in the broad masses the concept of labor as a health-improving life factor, work therapy also has educational significance. Dispensary care of sanatorium patients. Referral of patients to S. is carried out by sanatorium selection commissions existing at large enterprises and medical-prophylactic institutions. Candidates to be sent to sanatoriums are identified by the attending physician at the place of residence or place of work of the patient during the course of daily observation and treatment. In the first instance, workers in the main branches of industry are directed to sanatoriums, with the allocation of places by factories and enterprises being determined by regional and provincial trade union councils in accordance with the directives of the All-Union Central Council of Trade Unions. The number of workers in S. averages around 70%, with the remaining places being provided to employees, students, disabled persons, family members of workers, etc. The sanatorium selection commission, in addition to medical indications, is also guided by the production value of the worker (shock work, Socialist competition), his living and domestic conditions, etc., when selecting candidates. Preparation of the patient for sanatorium-resort treatment (carrying out necessary analyses, sanitation of the oral cavity, removal of tonsils, etc.) is of very great importance, enhancing the effectiveness of treatment; no less important is consolidation of the achieved treatment results through examination of the patient by the attending physician of the outpatient clinic after the completion of sanatorium-resort treatment and, if necessary, the establishment of appropriate additional treatment (mainly physiotherapeutic), work and rest regimens, etc. (For the accounting of sanatorium treatment results - see Balneology.)
L. Goldfayd. The construction of sanatoriums in pre-revolutionary Russia was a rare phenomenon. Even at the largest resorts, sanatoriums that were even slightly well-equipped could be counted on one's fingers, and the majority of them were organized during the imperialist war in connection with the need to treat sick and wounded officers. As the territory of the resorts was liberated from the White Guards and interventionists, extensive work was launched to adapt privately owned property at the resorts for use as sanatoriums. Individual estates and palaces, hotels, mansions, and dachas were rebuilt into sanatoriums in accordance with a specific system of medical-sanitary and cultural-domestic services for the patient and the vacationer. In the process and based on the experience of this work, the basic requirements currently imposed on the construction of Soviet sanatoriums, intended for the health improvement of the broad masses of the working people of the Union, gradually emerged. New sanatorium construction began somewhat later, as old resources were mastered, and received its greatest development in connection with the industrialization of the country and the collectivization of agriculture, which opened the widest prospects for the sanatorium-resort business as one of the links in the general system of cultural-domestic services for the working class. In this regard, data on the development of new sanatorium construction in the Sochi-Matsesta resort area are characteristic. Here, during the 1932 construction season, about 3,500 sanatorium beds were in the process of being built, which constitutes over 50% of the existing sanatorium fund. About 20 million rubles were allocated for the construction of new sanatoriums that year. It is also well known that there was great development of sanatorium construction at the Caucasian Mineral Waters (especially in Kislovodsk). The rapid growth of industrial construction in various parts of our Union caused, along with the expansion of the sanatorium fund at resorts of national importance, the development of local sanatorium construction in the regions of new industrial centers and new construction projects. New construction of sanatoriums in the USSR is characterized by a whole series of achievements. Even now, one can cite examples of very successful resolution of the requirements imposed on a Soviet sanatorium, both from the medical-organizational and architectural sides. At the same time, new sanatorium construction is often guilty of a whole series of major shortcomings—until very recently, a great discrepancy in the principles and norms of design had not yet been eradicated; quite often, the architectural design also does not correspond to the ever-increasing cultural demands. In this regard, the work of the State Central Institute of Balneology in the field of planning, standardization, and also the typification of sanatorium construction (begun in 1931-32) is acquiring great practical significance. The basic principles of organization and design norms are being subjected to scientific research: 1) territory, 2) buildings and structures, 3) equipment. The territory of a sanatorium is of decisive importance in the organization of sanatorium services and must serve as an object of special attention during the construction of a sanatorium. The choice of a site must ensure the unconditional fulfillment of a number of sanitary requirements, which are elevated in comparison with other populated areas, and must be in strict accordance with the purpose, volume, and type of the sanatorium intended for construction. One of the decisive factors in choosing a site is the climate and microclimate conditions (winds, temperature data, relative humidity, conditions of insolation and aeration). In a number of cases, the requirements for the most favorable microclimatic conditions must be combined with the need to bring the sanatorium closer to therapeutic springs, the sea, or another therapeutic factor. In any case, a sanatorium must be located in a healthy area on a well-drained site, favorable—according to soil conditions and orographic data—for the implementation of the basic elements of improvement, as well as for the allocation of a special zone of mining-sanitary protection (see). Special attention when choosing a site must be paid to the sufficient isolation of the sanatorium from populated areas, industrial enterprises, transport hubs, transit roads, as well as to the location of the territory on the windward side in relation to possible sources of air pollution. The organization of the territory is carried out by developing a general plan. The general plan must show the lands of the sanatorium and those adjacent to it, with the designation of the boundaries of the sanatorium and the mining-sanitary protection zone, the topographic features of the area, and lands of agricultural significance with an indication of the boundaries of individual plots. The plan must also show all artificial structures, road profiles, all residential and non-residential buildings (subdivided by type of building materials), both existing and those proposed for construction. The general plan of a sanatorium is a necessary and basic document when resolving issues related to the territory and is an integral part of the planning project for the given populated place and the district as a whole. The general plan is developed for a period of at least 15 years and provides not only for construction and expansion on the given territory but also for the sequence of work over time. The organization of the sanatorium territory must provide for a clear definition of individual districts (zones) and their functional connection with each other. The interdependence, size, and proportions of the dimensions of individual zones must be determined in each specific case on the basis of special medical-organizational and technical-economic calculations, depending on the features of the given territory, the type, composition, and volume of the sanatorium, the adopted system of organizing patient services, and at a resort—also the coordination of the given sanatorium with the general resort economy, etc. In any case, the allocation of zones must be provided for: 1) direct patient service—medical and cultural-domestic, including special areas for physical culture, labor processes, aero- and heliotherapy, passive rest (the so-called "quiet zone"), 2) economic-technical institutions, 3) housing for service personnel, 4) auxiliary agriculture, etc. At the same time, both proper isolation and connection between individual zones must be ensured. The dimensions of the sanatorium territory, varying within significant limits depending on specific conditions, should nevertheless not be less than 250 m2 per 1 bed for the zone of direct patient service, so that the percentage of development of this zone does not exceed 7-10% in two- or three-story construction. Green spaces are planned in close dependence on the general system of medical-preventive measures in the sanatorium. Besides preventive tasks and decorative design, green spaces must contribute to the replenishment of the sanatorium's food funds (gardening, vegetable growing, greenhouse, hothouse farming, etc.) and must also be adapted for the purposes of occupational therapy. The norm for greening can be accepted as 60-70% of the sanatorium territory. Green spaces must be developed in the form of a unified system, uniting the sanatorium with the nearest green massifs so that protection of the sanatorium from strong winds and other unfavorable climatic factors is ensured. Plots of green spaces must separate individual zones, while at the same time not hindering sufficient ventilation of the territory and proper insolation. The optimal number of beds in a sanatorium for patients, as shown by studies of the State Central Institute of Balneology, can be accepted as 200-300. The construction of a sanatorium with over 300 beds may prove acceptable in the presence of special conditions; over 500 beds usually finds no justification. The arrangement of buildings on the site (with a correct system, see below) must ensure convenient communication between individual groups of premises, with the distances (the so-called service radii) established depending on the contingents of patients served and not exceeding 300 m. Orientation by cardinal points for the sleeping quarters of sanatoriums is most favorable toward the southern half of the horizon, in particular toward the southeast. Orientation toward the southwest should be avoided (especially in the south) due to significant overheating of the premises in the afternoon hours. For operating rooms, doctors' offices, and the kitchen, orientation toward the northern half of the horizon is desirable. The gaps between buildings depend on their number of stories and must be established at no less than 40 m for the long sides, and no less than 10 m for the ends; a setback of the building from the boundaries of the site must also be provided, guaranteeing the building against dust and noise. The kitchen and other economic and technical premises in relation to housing must be located on the leeward side, keeping in mind the prevailing winds in the summer time. When designing the entire sanatorium in one building, the entrance to the dining room should be located primarily in the direction of the sleeping blocks, with the calculation of avoiding the passage of patients past the entrance to the kitchen and the territory of the utility yard adjacent to the kitchen. Kitchen windows and kitchen entrances must not be located opposite the premises for cultural-domestic and medical-diagnostic service of patients and vacationers.
The communication routes of the kitchen and the utility yard must be coordinated with the system of utility roads and designed in such a way as to make it possible to deliver products, remove garbage, waste, etc., bypassing the buildings that directly serve the patients. The composition and volume of the premises of a Sanatorium can be characterized by approximately the following data (in m3) (art. 553):

Figure 1. Lenin Cardiological Sanatorium in Kislovodsk.

Fig. ~ First Sanatorium in Kislovodsk "For Industrialization" ; - ,*M Figure 3. "Red Banner" Sanatorium in Miskhor. l

Figure 1. Sanatorium No. 7 in Novaya Matsesta.

Figure 2. Sanatorium No. 7 in Novaya Matsesta.

Figure 3. Semashko Sanatorium in Simeiz.

Fig. 4. Peasant Sanatorium in Livadia.
Number of beds in the sanatorium Name of premises Sleeping quarters . Kitchen and dining room . . Administrative-reception Medical section.... Club section: a) club primitive 9 25 8 22 b) club and theater . . . c) administration premises .... 3.5 Total on average per bed: a) with a club primitive . . 141.5 b) with a club and theater .... 158.5 The accommodation of the service staff should be provided for, if possible, outside
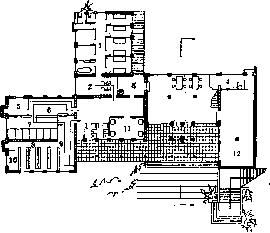
Figure 1. Administrative building with a filter station and isolation ward. 1st floor: 1-filter station; 2-doctor; 3-registration; 4-buffet; 5-dirty linen; 6-undressing room; 7-showers; 8-linen room; 9-dressing room; 10-repair shop; 11-barbershop; 12-storeroom.
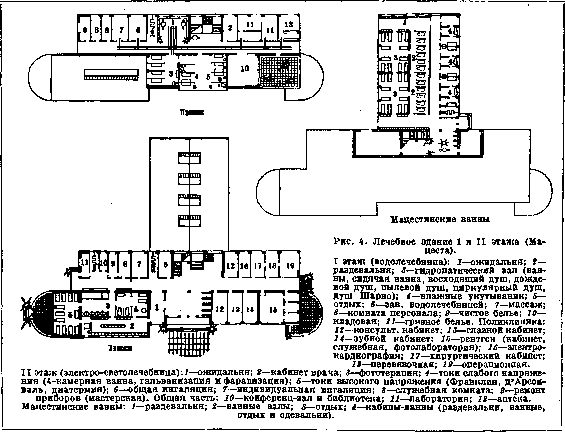
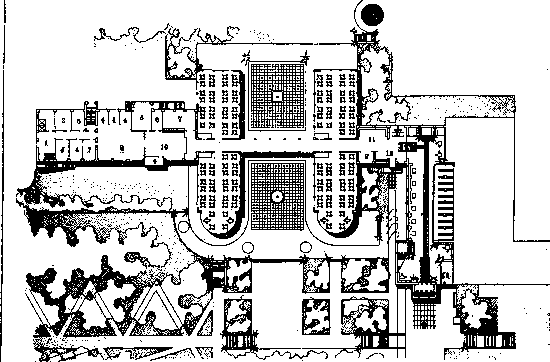
the territory of the Sanatorium. On average, for rough calculations, the number of service personnel with families can be taken as 1.3-1.5 inhabitants per bed, which requires from 80 to 100 m3 of premises (including cultural and domestic service premises) per sanatorium bed. Premises intended for the economic and technical maintenance of the Sanatorium account for about 15-20 m3 per bed (this includes warehouses, a bathhouse, a laundry, and transport premises). A complete, finished Sanatorium includes the following groups of premises: A. Administrative premises with a filter station and isolation ward (Figs. 1 and 2). B. Sleeping quarters (Fig. 3). C. Medical premises (Fig. 4). D. Premises for the cultural and domestic service of patients (Figs. 5-7). E. Premises of a cultural and recreational nature. F. Service and utility premises and staff housing. The first 5 groups of premises (A, B, C, D, E) can be located either in one building (sometimes two or more buildings connected by covered heated passages, i.e., in one block) or in separate buildings located on the site of the Sanatorium in a certain way (the so-called pavilion type). The first type, i.e., the Sanatorium in one block, can be recommended for small Sanatoriums—not exceeding 150-200 beds, operating all year round and intended for patients with limited mobility. In all other cases, the pavilion type can be recommended. The choice between these two types of Sanatoriums depends, of course, also on a number of local conditions—the size of the site, its relief, basic building materials, etc. The advantages of the first type are greater compactness of the Sanatorium, greater ease of serving patients, the absence of the need to duplicate auxiliary premises (e.g., vestibules, cloakrooms), and the accessibility of all Sanatorium premises without the need for outerwear, which is especially important in the rainy and cold seasons. The pavilion type lacks these advantages, but it allows for better placement of patients, eliminates their crowding and the associated noise in the Sanatorium, and allows for better development of the territory. With the first type of Sanatorium, usually one vestibule with a cloakroom is built (in the north, also with a dryer for felt boots), calculated for the total number of beds in the Sanatorium, the service staff, and possible visitors. With the second, pavilion type, vestibules are provided in each building and are calculated for the maximum possible simultaneous load. The area of vestibules and cloakrooms at the sleeping quarters is determined according to slightly higher than usual standards (simultaneous use in connection with the regimen). The composition and areas of individual premises of the Sanatorium (all numbers, areas, etc., are given approximately in relation to a Sanatorium of the normal type for 150-300 beds). Administrative premises with a filter station and isolation ward. The administrative part consists of an entrance hall with a cloakroom with a total area of 20-25 m2, an office of 18-20 m2, an accounting and cash office of 18-20 m2, a post office and savings bank of 15 m2,
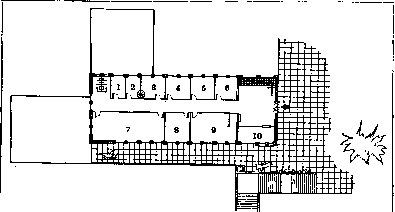
Figure 2. Administrative building with a filter station and isolation ward. II floor: 1-battery room; 2-utility room; 3-archive; 4-reserve room; 5-head of household; 6-head of the sanatorium; 7-red corner; 8-office; 9-accounting; 10-post office.
director's office of 15 m2, office of the head of household of 12 m2, room for the VKP(b) cell of 15 m2, local committee (also known as the red corner) of 30-35 m2, cleaner's room of 8 m2, switchboard (internal telephone) of 8 m2 and 2 toilets (male and female). The filter station consists of a shower room with benches and one bathtub of 0.11-0.15 m2 per bed, an undressing room (with a window to the dirty linen room) of 0.05-0.06 m2 per bed, a dressing room (with a window to the clean linen room) of 0.06-0.08 m2 per bed, a dirty linen room with a separate exit to the outside of 8-10 m2, a clean linen room with a separate exit to the outside of 10-12 m2, a storeroom for patients' belongings of 0.20-0.30 m2 per bed, a disinfestation chamber (its area is determined depending on the chosen system and local conditions). The isolation ward consists of two or three single-bed hospital-type wards with an area of 10.5 m2 each, a duty room for the nurse (with a box for heating food) of 15 m2, a toilet, a bathroom of 10 m2 and an exit to the outside. In individual cases, depending on local conditions, a temporary reception ward is provided at the filter station (in case of arrival of patients at night, in case of the need for re-evacuation of incorrectly sent patients, etc.) consisting of a vestibule with a cloakroom, a box for a barber and a place fenced off by a barrier for receiving the belongings of arriving patients, with a total area
of 0.17-0.18 m2 per Sanatorium bed, 2 toilets (male
and female), a registration desk of 12 m2, a room
for staff of 12 m2, a doctor's examination room with
2 boxes for patients to change clothes and an entrance to
the dining room with a box for heating food of 20-25 m2, a room
for visitors of 12-15 m2 and two toilets (male and female); the entrance hall of the temporary reception ward can simultaneously serve as an exit from the filter station. The width of the corridors in these premises is provided at 1.8 m; the height of the premises is 3.0-3.2 m. The total useful area of all premises (excluding auxiliary area-corridors) is between 2.3 and 3.2 m2 per bed. Sleeping quarters are built in 2, less often in 3 and 4 stories (in the latter case, an elevator is provided) and consist of bedroom wards, common areas, auxiliary medical, service, and auxiliary premises. Bedroom wards are built for 1, 2, and 4 beds. The ratio between the number of these wards is different for different Sanatoriums. In some—general
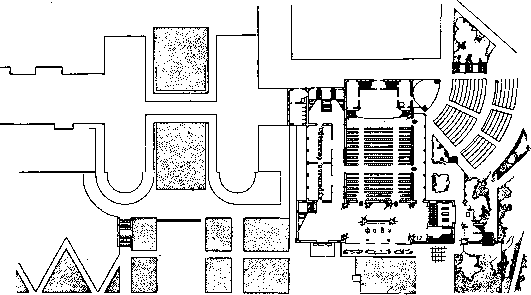
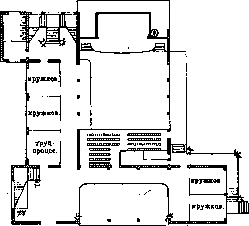
Figure 5. Dining room and club building (1st floor-dining room): 1-staff room; 2-confectionery; 3-provision storage room; 4-preparation rooms; 5-dining room; 6-boiler room; 7-washing room; 8-kitchen; 9-nurse; 10-serving room; 11-washroom; 12-galoshes; 13-head of the club.
Figure 6. Dining room and club building (II floor-club).
type, for gastrointestinal patients—four-bed wards may predominate, in others—for neurotics—on the contrary, one- and two-bed wards. The number of patients placed in one-, two-, and four-bed wards varies depending on the purpose of the Sanatorium within the following limits: in one-bed wards—from 6 to 20%, in two-bed wards—from 30 to 80%, in four-bed wards—from 0 to 60%. The number of beds (patients) in one department is on average 50 and varies depending on the purpose of the Sanatorium and the doctor's workload in it from 25-30 to 60. For greater convenience in placing patients, each department is divided into 2 groups (sections) with their own service premises, while all other premises are common to the whole department or even a wing of the building. The area of a one-bed ward is provided at 9-10.5 m2, a two-bed ward—at 13-15 m2, a four-bed ward—at 24-26 m2. The wards are oriented to the southern half of the horizon—the closer to the south, the more one should avoid orienting the wards to the southwest. Types of wards are shown in Fig. 8. Common areas serve for rest and daytime stay of patients. In each department, 2 rooms with a total area of 45-50 m2 and one smoking room (where it is not contraindicated) of 15-20 m2 are provided.—Auxiliary medical premises. In each department pre
A doctor's office of 9-11 m2, a treatment room which is also the nurse's station, in 18-20 m2, are provided. In each building or wing of the building, in addition, for special examinations, an anthropometry office for determining basal metabolism, etc. (on average one for every 100 patients) in 16 m2 is provided. In sanatoriums for tuberculosis patients in the corresponding departments, in addition, a room for pneumothorax induction (one is sufficient for every 2 departments) in 16-20 m2, a laryngology office in 18-20 m2, an inhalatorium in 18-20 m2, a dressing room (in the surgical department) in 15 m2 are provided. In case of deterioration in the condition of any of the patients in each department of a tuberculosis sanatorium, one spare single-bed room should be provided.-Relaxation rooms. Toilets are provided at 2 per department at the rate of 1 toilet for every 8 beds; in men's toilets, in addition, urinals are provided, in women's toilets - bidets; next to one of the toilets, sometimes a room of 6-8 m2 for enemas and for storing items for the sanitary-hygienic care of patients is placed. Washrooms are also provided at 2 per department at the rate of 1 faucet for every 5 beds and one foot bath for every 10-15 beds; next to each washroom, rooms for cleaning clothes and footwear in 8-10 m2 are provided;
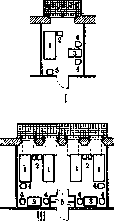
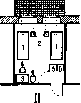
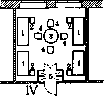
Figure 8. -I-IV-types of rooms: 1-bed; 2-bedside table; 3-table; I-chair; 5-closet. Balconies are desirable for these rooms. A bathroom is provided for one ward (depending on local conditions, 1 or 2 bathtubs). A doctor's duty room of 9-10 m2 is provided in one of the wards for the entire S. A nurse's duty room of 9-10 m2 is provided for each building or wing of a building (on average for every 100 patients). A nurse's aide duty room is provided in each ward and consists of 3 parts: 1) the duty room proper, 2) for heating water, food, etc., and 3) for storing cleaning items, small equipment, etc.; the total area of the entire room is 22-26 m2 on the upper floors and 30-36 m2 on the ground floor (in the latter, a room for collecting dirty linen from all floors and an exit from this room to the outside are also provided). In individual cases, with a large number of bedridden patients, a buffet of 8-10 m2 is also provided for each building or wing of a building. Auxiliary rooms. Corridors, depending on local conditions, possible and desirable orientation of the building and its individual rooms, are built on one or both sides. With two-sided construction of corridors, the latter is allowed within up to 60% of their length. The width of corridors is taken as 2-2.5 m. The staircase is usually located between two wards or groups of rooms. In front of the doctor's office and treatment room, corridors are usually somewhat widened, forming small waiting rooms. Depending on the type of S. and the adopted heating and ventilation system, each building also provides rooms for a boiler room, fuel storage, ventilation chambers, etc. Terraces, verandas, and balconies for general use are provided near sleeping quarters, and depending on the purpose of the S. and local conditions, individual balconies or common verandas for therapeutic purposes (Liegehalle) are also provided; the latter are provided at a rate of 3.7-3.8 m2 per bed. The total useful area of all rooms, depending on the type of S., its purpose, layout of rooms, and architectural solution, ranges from 17 to 21 m2 per bed. The height of sleeping rooms is taken as 3.2-3.5 m; in auxiliary and some service rooms, this height can be reduced to 2.8 m. The total volume of a sleeping building, depending on its number of floors, height of rooms, and useful area, is about 80 m3 per bed. Treatment rooms constitute the medical center of the S., in which all treatment facilities, special doctor's offices, special diagnostic offices, laboratories, pharmacy, and conference hall are located. These rooms are usually located on 2 floors: on the lower floor - water and mud treatment room, X-ray, operating room, most frequently visited patient offices, on the second floor - electro-light therapy room, laboratories, pharmacy, conference hall. The nomenclature and number of treatment facilities here depend more than in any other rooms on the purpose of the S., the contingent, and the number of patients in it. The treatment rooms include: head office of 15 m2, dental office of 15 m2, eye, also laryngological, office of 18-20 m2, 2-3 consultant offices of 15 m2 each, medical office of 15-18 m2, conference hall (and medical library) of 30-50 m2. Water and mud treatment department consisting of waiting rooms, changing rooms, rooms for baths, showers, mud treatment, poliotherapy, wraps, rest after procedures, and a number of service rooms (doctor's office, staff room, linen rooms, drying rooms, restrooms, storerooms, etc.). The area of this department depends on its throughput and ranges in S. in one building from 0.5 m2 (in tuberculous S.) to 1.1 m2 (in S. for nervous patients); in pavilion-type S. - from 0.6 m2 (in tuberculous S.) to 1.8 m2 (in S. for cardiovascular patients) per bed of S. Electro-light therapy department consisting of waiting rooms, rooms for electrical equipment and service rooms (doctor's office, staff rooms, restrooms, workshop, service room, rectifier room, etc.). The area of the department ranges from 0.6 m2 (in tuberculosis sanatoriums) to 0.9 m2 (in S. for nervous patients) per bed of the sanatorium. Operating room consisting of a dressing room of 15 m2, preoperative room of 12-15 m2, anteroom of 4-5 m2, operating room of 30 m2, and a room for sterilization and instruments of 12-15 m2. Massage department of 8-10 m2 per couch. In individual S., depending on their purpose and contingent of patients, inhalation rooms of 15-16 m2 for general inhalations and 18-20 m2 for individual inhalations, a room for electrocardiograph of 20-22 m2, a room for determining basal metabolism of 18-20 m2 are also provided. Rooms of the X-ray office with a total area of 70-75 m2. Laboratory - its area ranges from 0.2 m2 (in S. for nervous patients) to 0.25 m2 (in tuberculous S.) per bed in S. Pharmacy of 30-32 m2, household storerooms, linen rooms, equipment rooms, restrooms. - The total useful area of all the listed rooms (without vestibules, corridors, staircases, etc.) ranges in S. in one building from 2.4 m2 (in tuberculous S.) to 4.5 m2 (in S. for nervous patients). Corridors in treatment rooms have a width of 1.8 m (service) to 2.5 m. In front of special offices, X-ray, and in other places where a gathering of waiting patients can be anticipated, corridors are widened. Height of rooms: water-mud-electro-light therapy - 4-4.5 m, other rooms - 3.2-3.5 m; height of service rooms can be reduced to 2.8 m. Cultural and domestic service rooms are divided into dining rooms and club rooms. Dining rooms include: dining hall (depending on the number of patients, one or several halls) of 1.35-1.40 m2 per bed, buffet-distribution kitchen, cooking room, washroom, storeroom, sister-in-charge room, staff room, restrooms, washrooms. The area of the listed rooms (without the dining hall) is determined at 0.55-0.75 m2 per bed (the more beds, the relatively smaller the area per bed). Kitchen consisting of cooking hall, cold shop, pastry section, preparation rooms, washroom, storeroom, equipment room, head chef's room, and rooms for kitchen staff is provided with an area of 0.85-1.0 m2 per bed. A bakery is provided if required by local conditions, with an area of 0.24-0.28 m2 per bed. Club rooms include: auditorium of 0.7 m2 per placeu, foyer (several rooms serving also as living rooms, reading rooms, quiet game rooms) of 0.5 m2 per place, smoking room of 0.10 m2 per place, stage of 60 m2, artist rooms (male and female) of 12 m2 each, artist restrooms, prop room of 25-30 m2, film booth, book storage room, rooms for literary circle and wall newspaper, photo circle of 18-20 m2 each, cultural worker room of 10-12 m2, service room of 6-8 m2, restrooms (according to standard norms). In the vestibule or hall adjacent to the cultural and domestic service rooms, a barber shop and post office kiosk are also provided. The auditorium is optional. The stage with adjacent service rooms can be attached to the dining hall. The total area of club rooms (without vestibule, corridors, staircases, etc.) averages 2.5-3.0 m2 per bed. The width and height of corridors are usual for club-theater rooms. The visual part of club rooms, consisting of an open platform, stage, artist rooms, restrooms, and prop room, is also provided in the park in the open air for warm weather. Rooms (structures) of cultural and health-improving nature consist of rooms (structures) for physical education, medical gymnastics, sports, and rooms for labor processes. The former rooms include: gymnasiums (covered - insulated terraces) of 11x18 or 12x24 m (depending on the contingent and number of patients, maximum percentage of their coverage by physical education, medical gymnastics, mass games, etc., and possible number of shifts according to the regime of S., both size and number of halls are determined); leader's office of 12 m2 and equipment room of 15 m2. To avoid the need for a separate vestibule and other service rooms, it is desirable to connect the halls with club, sleeping, or treatment rooms. In addition to halls for summer time, similar open-air platforms for physical education are provided, as well as platforms for volleyball of 13x22 m, for tennis of 20x40 m, for croquet of 9x18 m, for city games of 13x25 m, for jumps of 20x40 m, running track of 130x3.6 m, shooting gallery of 50x10 m, etc.
If water basins are present, provisions are made for a boat dock, bathing facilities, a beach with a solarium and open-air sunbathing area (the latter are also provided in the absence of a water basin) at a rate of 15 m2 per place. For winter sports, a winter station for skiers and skaters is provided. In the sanatorium park, gazebos-verandas for reading (3-3.5 m2 per place), quiet games and activities (2-2.5 m2 per place), and rest (4.5-6.0 m2 per place) are also provided. The premises for work processes consist of several workshops with a total area of from 1 to 2 m2 per bed in the sanatorium, an inventory and material storage, a warehouse for finished products, auxiliary premises, an instructors' room, washrooms and toilets with a total area of from 0.45 to 0.55 m2 per bed. The number of workshops and their dimensions are determined depending on the purpose of the sanatorium, the contingent and the number of patients in it, the percentage of patient coverage and the regime of the sanatorium. For work processes in the open air, in addition, vegetable gardens, a fruit orchard, an area for sawing and chopping wood, etc., are provided on the sanatorium grounds. Service and household premises are provided depending on local conditions and consist of warehouses for fuel, a fire brigade cart, equipment and other materials, a garage, stables, repair workshops, a laundry, vegetable and ice storage sheds, guardhouses and sentry boxes. Housing for sanatorium personnel is provided depending on local conditions.
Related articles
Mentioned in
Cite this page
“Sanatorium.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/sanatorium/