Splints
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia provides a historical overview of splints used for immobilization in fracture treatment and transport. It details the evolution of various splint designs, from ancient Egyptian wooden boards to specialized wire and metal apparatuses used during the First World War.
Encyclopedia article (1928–1936)
SPLINTS, a device used to create immobility (immobilization), most often in fractures of the long bones of the limbs, jaws, and in joint injuries, for the purpose of providing first aid, for transport, and for treatment. Excavations of Egyptian tombs testify that 4,000–5,000 years B.C., Egyptians were already using various kinds of splints for fractures, albeit very simplified ones—in the form of small boards made of wood, bark, or even dried animal skin—for the purpose of fixing the fracture site. At the present time, one can count hundreds of different kinds of simple fixation splints made of various materials: cardboard, splint-wood, wood, metal, plate-like, wire, mesh, sometimes prepared in advance for various parts of the body. The most common fixation splints used for "setting" the upper and lower limbs were the wire or mesh splints of Mayor—wide, suitable for any arm bent at a right angle or an extended leg (Figs. 1 and 2), and the tin, gutter-shaped splint for the lower leg with a foot piece—the splints of Volkmann and Cabot (Figs. 3 and 4). In order for the fixation splint to
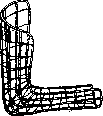
Figure 1. Mayor's wire splint for the arm. So that it was easy to fit to one or another part of the body and to the curves of the joints, Cramer proposed the use of strips of "wire ladder" (Fig. 5), and Filbry—a metal
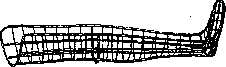
Figure 2.
Mayor's wire splint for the leg.
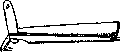
Figure 3. Volkmann's splint.
mesh fabric (Figs. 6 and 7), obtained by stretching sheets of aluminum or galvanized iron that had been punched frequently and in a specific order. When used, strips of the necessary length and width are cut from them, to which the necessary curves are given. When bandaged with a soft bandage, they, thanks to their springiness (especially during transport, during shaking), gradually loosen the bandage, and fixation is not achieved. More satisfactory fixation is obtained by well-fitting these splints to the curves of the body with reinforcement by starch or plaster bandages. The enormous experience with the treatment of fractures in the imperialist war added a large number of new variations of fixation splints to the abundant splint inventory that entered the textbooks. For example, among Russian splints, the wire splint of Sapezhko is known, then the sliding wire splint with support under the pelvis of Kravz-Tarnovsky (Fig. 8), the splint of Faltin, Sozon-Yaroshevich, and others. Like most old ones, they proved to be little effective. The rich museum collection composed of them, as this, for example, takes place in the Military-Sanitary Museum of the Military Medical Academy (from where some objects for the accompanying figures were taken), has more historical than practical interest, since the vast majority of this arsenal of splints cannot fulfill the requirements of rational immobilization during first aid, transport, and treatment of fractures. Even less suitable, even if only for primary immobilization of a fracture, are primitive improvisations from one or another material found under hand in various conditions (rifle, sticks, boards, splint-wood, plywood, tied twigs, bundles of straw,
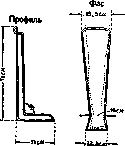
Figure 4. Cabot's posterior wire splint; Figure 5. Cramer's splint. sandbag, etc.). Such primitive immobilizations are permissible for use only in extreme cases of a hopeless situation. But even in such cases they

Figure 6. Sheets
of Filbry metal fabric—stretched. can provide a certain service in the matter of immobilization only in combination with a plaster or starch bandage. The imperialist war clarified that the best immobilization means for first aid and for transport is a plaster bandage, correctly applied, with preliminary setting of the fragments by means of forced traction in the middle, so-called physiological position. But in the conditions of first aid, not only in war but also in peacetime, a plaster bandage is difficult to make, and in view of possible complications (hematomas, infections), it is also risky. It is recognized that its replacement should be a splint, but not a simple fixation splint, but a splint that ideally performs fixation together with traction. The principle of fixation with traction in the treatment of a fracture is a fairly old principle, known since antiquity—from the time of Hippocrates. Its wider practical application was realized 200 years ago in the form of a double inclined plane, when Petit (1719) demonstrated it at the Paris Academy of Sciences (Fig. 9) and recommended it for the treatment of leg fractures. With muscles relaxed by rest, the lower leg and thigh, by virtue of their weight, are passively pulled on the movable bend of the inclined plane. The idea of the Zuppinger apparatus (1905) (Fig. 10) repeats the idea of Petit's double inclined plane for passive traction by the limb's own weight while the knee is semi-flexed. Later, Zuppinger himself abandoned the idea of treating fractures by passive traction. On these same apparatuses in a position of semi-flexion, but with active adhesive plaster traction according to the Bardenheuer principle, with early active movements and massage, Zuppinger tried to realize the so-called Fig. 7. Sheets of Filbry metal fabric—punched.
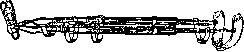
Figure 8. Kravz-Tarnovsky's splint.
functional treatment, the principle of which was proclaimed by Hennequin. According to the Zuppinger type, the Heusner splint was also built, who, instead of plaster for active traction, recommended the use of cotton strips with the help of glue (see Traction). Wegner performed active traction of the lower leg bent at the knee instead of a splint on pillows (Fig. 11). Codivilla and Steinmann replaced plaster traction with nail traction: the former—through the heel, the latter—through the femoral condyles. However, the idea of a double inclined plane with
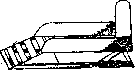
Figure 9. Petit's splint.
passive traction did not die, but, having undergone significant modification, played a role in the imperialist war not only in treatment hospitals but also at the front—on evacuation routes. Thus, for a fracture of the femur, Fritz Lange proposed for transport a rather cumbersome splint-sleeve apparatus on a metal base with a cardboard sleeve on straps. Criticizing this splint in a post-war report, K. Franz says that the cardboard becomes soggy from pus and moisture, and the splint did not enjoy success among German surgeons. A similar splint bandage, built on the principle of a double inclined plane with fixation and passive traction on a bent knee, Rummel proposed to make by bending its frame from three Cramer splints. K. Franz warns against using it during transport, as, not being reinforced with plaster, the Cramer strips are very springy, loosen the bandages, and the whole bandage falls apart. Thus, fixation with passive traction did not justify itself in the transport of the imperialist war on any of the splints used. A significantly greater role during transport was played during the last war by fixation with active traction by the most varied methods. For example, Weissenstein (Fig. 12) in Austria, for this purpose, in cases of femoral fractures, adapted
ordinary stretchers, and in winter, ski stretchers (Fig. 13). In the foot half on each side, along the sides of the poles, 6 slits the length of a palm's width are made in the canvas of the stretcher, through which the leg and pelvis are secured to the pole with circular turns of a bandage. The foot is bandaged to the crossbar of the stretcher. Counter-traction is carried out through the groin and

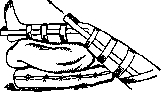
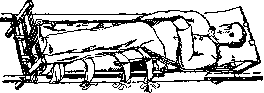
Figure 12. Stretcher-splint for femoral fracture (according to Weissenstein).
is secured at the head end. These stretchers went with the wounded person to the place of his stationary treatment. An obstacle to the wide application of Weissenstein's interesting idea in Austria was the insufficient quantity and bulkiness of the stretchers used as a splint. The old Liston-Esmarch splint (Fig. 14) also served the idea of fixation with traction. The leg, fixed by circular turns of a bandage through the holes of a long wooden board, was pulled by the movable foot part, which is fixed to the side splint with the help of a screw. Counter-traction is provided by an elastic pull,
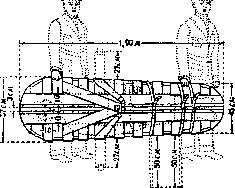
Figure 13. Ski stretchers (manual on U.S. Army splints).
passed through the groin, secured at the upper end of the side board. The Liston-Esmarch splint, which was widely, almost exclusively, used in the first year of the war by the British for femoral fractures,
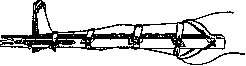
Figure 14. Liston-Esmarch splint.
received full condemnation later on all fronts when a huge mortality rate was discovered among the wounded with femoral fractures. "The rifle gave better results," says
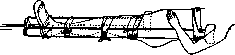
Figure 15. Dietrichs' splint.
Bowlby. Based on the idea of the Liston-Esmarch splint, the Dieterichs splint (Fig. 15) was also constructed, with two lateral wooden strips and a movable foot piece. In its weight and bulkiness, it can compete only with the wooden Volkovich splint (Fig. 16), which is intended by the author also for walking in case of a femoral fracture. Based on the idea of fixation with active traction, the Stubenrauch splint was constructed in Germany, consisting of two Kramer splints: a posterior one, embracing the area under the knee, the lower leg, and the sole, and an outer one, extending to the foot from the lateral surface of the torso and pelvis. The extra 12 cm of the foot end of the outer splint were bent for the purpose of attaching to it the traction applied to the skin along the sides of the knee and lower leg. As in the above-described splints, elastic counter-traction was also carried out through the groin. All these splints, however, do not sufficiently implement the principle of "fixation and active traction." The latter is insufficient due to the small weight that such splint dressings allow. This circumstance prompted the search for combinations of plaster and traction. The so-called Lange extension plaster cast appeared; however, plaster and traction have completely opposite effects. Plastered extension straps stop the action of traction and lose their meaning. Of all the methods of splinting, the idea of a double inclined plane with active traction survived the imperialist war. But not in first aid and not in transport, but in treatment in a hospital, the idea of a double inclined plane developed into a separate method and entered the post-war environment of treating fractures in peacetime. Even during the war (in Germany), so-called positioning splints with active adhesive or nail traction appeared. Braun (Fig. 17) was the first during the war, in 1916, to propose an iron frame for the treatment of femoral fractures, into which the thigh and lower leg are placed with the hip and knee joints bent. Later, during the war, the Viennese surgeon Böhler (Fig. 18) improved it by adapting the pulleys for active traction of the thigh and lower leg, which are usually located on the bed, onto the splint itself. For this purpose, Böhler attached several metal arches to the splint: one arch as a continuation of the upper horizontal strip of the frame for traction of the lower leg, and two arches for the thigh bent at different angles at the knee. Thanks to the work of Böhler during and after the war, positioning splints
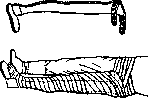
Fig. 16. Volkovich splints. an splints

Figure 17. Braun splint. traction, made by the skin along the sides of the knee and lower leg. As in the above-described splints, elastic counter-traction was also carried out through the groin. All these splints, however, do not sufficiently implement the principle of "fixation and active traction." The latter is insufficient due to the small weight that such splint dressings allow. This circumstance prompted the search for combinations of plaster and traction. The so-called Lange extension plaster cast appeared; however, plaster and traction have completely opposite effects. Plastered extension straps stop the action of traction and lose their meaning. Of all the methods of splinting, the idea of a double inclined plane with active traction survived the imperialist war. But not in first aid and not in transport, but in treatment in a hospital, the idea of a double inclined plane developed into a separate method and entered the post-war environment of treating fractures in peacetime. Even during the war (in Germany), so-called positioning splints with active adhesive or nail traction appeared. Braun (Fig. 17) was the first during the war, in 1916, to propose an iron frame for the treatment of femoral fractures, into which the thigh and lower leg are placed with the hip and knee joints bent. Later, during the war, the Viennese surgeon Böhler (Fig. 18) improved it by adapting the pulleys for active traction of the thigh and lower leg, which are usually located on the bed, onto the splint itself. For this purpose, Böhler attached several metal arches to the splint: one arch as a continuation of the upper horizontal strip of the frame for traction of the lower leg, and two arches for the thigh bent at different angles at the knee. Thanks to the work of Böhler during and after the war, positioning splints
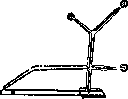
Figure 18. Böhler splint.
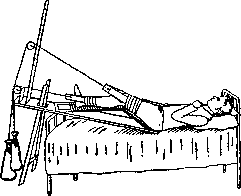
Figure 19. Tikhomirov and Anzin splint.
gained great popularity for hospital treatment of femoral and lower leg fractures. In addition to the Braun and Böhler splints, other modifications of positioning splints appeared—Bayer, Schede, completely similar to the Braun positioning splint for the leg, as well as more complex and bulky apparatuses by Tikhomirov and Anzin (Fig. 19) with traction and simultaneous movement in the joints. Worthy of attention is the folding positioning (for transport) splint by Osten-Sacken (Fig. 20) and two wooden triangles by Colmers (Fig. 21), placed under the bent knee; when dressing the wound, one of the triangles is removed. For hospital treatment, a number of authors have also proposed so-called suspension splints, e.g., the Smith splint; traction when suspending the leg on slings to a long crossbar of a wooden frame, for example, the Florschütz method. Only one or two
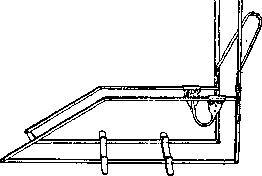
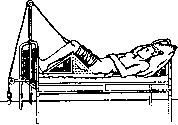
Figure 20. Folding—for transport and treatment—Osten-Sacken splint.
of the many slings are removed during dressing, and the limb continues to hang on the others. Suspension splints were used in all countries during the war. English authors called this method a hammock. However, in cases of severe fractures and infections, suspension splints, or the method of air suspension, are of little use in terms of fixation, since it creates a certain mobility of the broken infected limb. But still, the suspension method has to be used, and mainly in cases of severely lacerated wounds, which hinder not only the application of a plaster cast but also a permanent splint. The suspension itself is best carried out using the so-called Balkan frame, which is also good for suspending various kinds of extension splints. Of all the splints that create fixation and traction and are suitable for first aid and transport in cases of femoral and lower leg fractures, only one splint survived the imperialist war—the Thomas splint (Fig. 22). The latter was designed by Thomas shortly
Figure 21. Colmers triangles.
before the Franco-Prussian War of 1870/71 and was proposed by him at that time to the French army; however, the French refused this proposal at the time. For half a century, the Thomas splint was included in surgical manuals, finding little practical application among surgeons. It was used in the form of the so-called Thomas apparatus mainly by prosthetists, wishing to provide unloading to one or another of the 3 large joints of the lower limb (Fig. 23, 24). Seeing the horrific mortality from complications in gunshot fractures of the femur in the 1st year
Figure 22. Thomas splint and one of its modifications—for first aid and transport in femoral fractures.
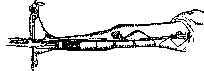
Figure 23. Thomas splint during hospital treatment for a wounded person with a femoral fracture.
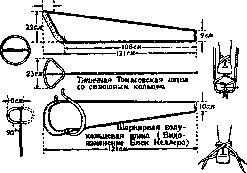
Figure 24. Two types of Thomas leg splint for first aid (manual on US army splints).
of the imperialist war, the leading English orthopedist R. Jones persistently recommended the use of the Thomas splint at the site
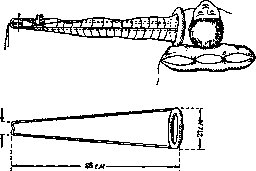
Figure 25. Thomas hand splint.
where the wounded person was found—over the trouser leg and boot—with traction by a pin inserted through a cut in the boot along the inner plane of the sole. In the second half of the war, the Thomas splint became mandatory for first aid and transport in femoral fractures not only in the English but also in the American army. A number of authors, such as Sinclair, having modified the Thomas splint, used it also for further treatment of fractures of the femur and lower leg, as well as

Detail
With subsequent adduction of the shoulder
Figure 26. Hinged Thomas transport hand splint (Murray modification).
in fractures of the upper limb (Fig. 25, 26). Thus, for English and
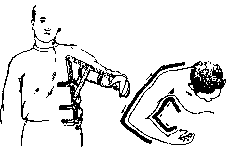
Figure 27. Turner metal splint—for shoulder fractures.
American orthopedists, it is now to a certain extent universal. The arm needs splinting significantly less often than the leg, since in many cases of first aid and transport, the torso, to which the arm is bandaged, can serve as a replacement for a splint. For the splinting of fractures of the upper limb, there are many variations of the method built on the principle of a double inclined plane. Thus, Middeldorf, in case of a humeral fracture, proposed fixing the lowered arm, abducted at the shoulder and bent at the elbow, on a triangle. However, this position of the arm with sharp internal rotation of the shoulder cannot provide the correct alignment
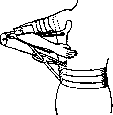
Figure 28. Tikhomirov-Petrov splint.
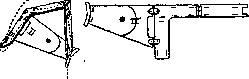
Figure 29. Splint for the shoulder by Sitenko.
of the humeral fragments. Based on the same principle, but with a more correct physiological position of the shoulder and forearm, the cardboard triangular Faltin splint is also constructed. In addition, there is a folding metal Turner splint (Fig. 27) and the so-called ambulatory crutch splint by Borchgrevink, used
Figure 30. Rectangular extension splint for the shoulder. (According to Zuppinger)
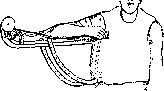
on the type of the Thomas extension splint for the treatment of a shoulder fracture while walking. The upper end of the splint, the "fork," is inserted under the support in the armpit. The shoulder and forearm hang down and rest on the plane of the splint. Adhesive tape applied along the length of the shoulder and forearm produces traction with the help of a rubber tube. Tikhomirov and N. N. Petrov added shoulder abduction to the Borchgrevink splint (Fig. 28). In M. I. Sitenko's version, this splint with abduction is made foldable (Fig. 29). Of the extension splints used in Germany in the imperialist war for shoulder fractures, Müller notes in particular the improvised splint by Porzelt, which was bandaged to the torso along its length when the shoulder was extended. When the Kramer splint appeared, the rectangular extension splint by Zuppinger (Fig. 30) gained wide use. Furthermore, by Müller's admission, the adjustable angular extension Braun splint with a spring and screw (Fig. 31) proved to be very rational. For fixation of a limb after joint resection, various kinds of so-called resection splints are used. The 2 parts of the splint, usually wooden, bandaged to the limb above and below the diseased joint, are connected by a "bridge"—a metal arch thrown over the site of the joint resection—for dressing the wound (Fig. 32). For jaw fractures, at the present time, splints of the Tigerstedt type are most often used, consisting of a main aluminum wire 2 2/3 mm thick. Each tooth is individually
Figure 31. Braun extension splint for the shoulder with an adjustable angle.
Fig. 32.
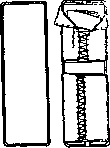
Figure 34.
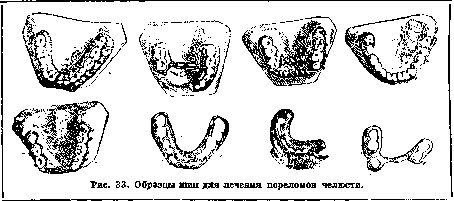
is tied to it with thin ligature wire 0.3-0.4 mm in diameter. The difference between Sauer's dental splints is only that they are made not of aluminum, but of nickel silver. Schroeder's dental splints are distinguished by the fact that they have metal rings soldered to the splint on the end teeth, which are fixed to the teeth with cement. The rest of the splint is fixed to the teeth with thin ligature wire (Fig. 33).
If the historical development of the idea of fracture splinting for first aid led to traction on a splint, then the development of this principle based on the experience of the Imperialist War and the modern stage leads to the use of frame-type splints—both for treatment and for first aid and transport. Modern requirements for a field splint are as follows: 1) the splint must be portable, cheap, simple, and convenient to use; it must perform both fixation and traction, allow for dressing the wound without removing the splint, and in an emergency, it must serve not only for first aid and transport but also during treatment, and be suitable for decontamination. The Imperialist War proved the necessity for the standardization of splints with a limitation of types for all these purposes. In this regard, 5-7 types of army metal frame splints were chosen in the USA: 1. Thomas arm splint of two types: one (Fig. 25) with a fixed ring, the other—modified by Murray, hinged—for fractures of the humerus, elbow, and forearm (Fig. 26). 2. Thomas leg splint also of two types: one with a full fixed ring (Fig. 24), the other—with a movable (180° pivoting) half-ring—for fractures of the thigh, knee, and lower leg (Fig. 24). 3. Cabot posterior frame—for injuries of the lower end of the lower leg and foot (Fig. 4). 4. Bradford frame (Fig. 34), representing convenience and facilitating care for fractures of the spine and pelvis, i.e., for the most severe and most painful fractures, serves as that necessary stable surface on which the corresponding wounded can be transported without being moved until reaching the place of treatment. The ideal transport means for these fractures, according to Wilson, during the Imperialist War were stretcher-litters (Fig. 13); in them, the wounded can be tied (swaddled) so tightly that during narrow turns in trenches, they can be placed on their side—on edge. 5. In addition to these metal frame splints, the long wooden Liston splint (Fig. 14) is recommended among US army splints—only for cases of injury to the hip joint area, in which the ring of the Thomas splint cannot find support in the pelvis.
Related articles
Mentioned in
- Bandages (a269)
- Corsets
- Dental Prostheses
- Dental Technical Instrumentation
- Dupuytren's Fracture
- First Aid Kit
- Hammond Splint and Gamomania
- Hessing Apparatus
- Immobilization
- Injuries
- Kienböck's Disease
- Orthopedic Appliances
- Plaster Casts, Corsets, and Beds
- Sanitary Orderly
- Sanitary Transport
- Sphygmograph
- Stomatology
- Traumatology
- Vladimirov-Mikulicz Operation
- Volkmann
Cite this page
“Splints.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/splints/