First Aid Kit
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
A first aid kit is a piece of equipment containing bandages and other supplies for providing initial medical assistance at the scene. In the Red Army, it was standardized with specific contents including bandages, tourniquets, scissors, and specialized tools for emergency care.
Encyclopedia article (1928–1936)
First Aid Kit, an item of equipment for a medic, containing bandaging material and other means for providing first aid at the scene. In the Red Army, the first aid kit is made of dense canvas. It can be worn over the shoulder (usually on the right side), for which it has a strap (or wide tape) consisting of 2 parts. When a medic needs to have their hands free and a hanging bag on the side should not restrict movement (e.g., when crawling, when carrying stretchers), the bag is worn on the shoulders like a backpack (see illustration). For this purpose, the back of the bag has 3 metal rings through which both parts of the shoulder strap or tape are threaded separately. The contents of the military first aid kit are standardized and determined by the table of property placed in it. Inside the first aid kit there are 2 compartments and a number of pockets (nests) for individual items. The large compartment is filled with bandaging material: individual or antiseptic first aid bandage packages, triangular bandages, safety pins. A skein of coarse thread and several needles for securing bandages and torn clothing rendered during aid are also placed here. For applying immobilizing bandages, splints are in the first aid kit: mesh, of the Filby type, or bast. To stop bleeding, a rubber tourniquet or special tape with a lock is in the first aid kit. For hand care, soap, a towel, and a grass brush for washing hands are carried in the first aid kit. Of individual items, scissors and a garden knife (with a curved blade) are mandatory accessories of the first aid kit for removing clothing before bandaging, for making splints from available materials, etc. For first aid to victims of persistent chemical warfare agents, a supply of tampons and a vial of decontaminating liquid are placed in the first aid kit. Bags with which medical instructors in military units are supplied are made according to the same type, but have a wider assortment of items contained in them. In addition to the items mentioned, a thermometer, a set of medical instructor's tools, a syringe, and some medications necessary in cases of emergency medical aid are placed in them: camphor oil and caffeine solution in ampoules, tincture of iodine, ammonia spirits, ether-valerian drops, as well as tablets with opium, codeine, aspirin, etc. If the medical instructor has an oxygen inhaler with them, then the tag from it, the oxygen cushion, and the corrugated tube can also be placed in the medical instructor's bag. First aid kits with which medics in Red Cross and Red Crescent teams are supplied are made according to the general army model, but their contents sometimes deviate from the inventory of items adopted in the Red Army.
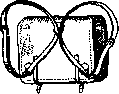
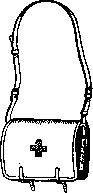
Red Army first aid kit.
For applying immobilizing bandages, splints are in the first aid kit: mesh, of the Filby type, or bast. To stop bleeding, a rubber tourniquet or special tape with a lock is in the first aid kit. For hand care, soap, a towel, and a grass brush for washing hands are carried in the first aid kit. Of individual items, scissors and a garden knife (with a curved blade) are mandatory accessories of the first aid kit for removing clothing before bandaging, for making splints from available materials, etc. For first aid to victims of persistent chemical warfare agents, a supply of tampons and a vial of decontaminating liquid are placed in the first aid kit. Bags with which medical instructors in military units are supplied are made according to the same type, but have a wider assortment of items contained in them. In addition to the items mentioned, a thermometer, a set of medical instructor's tools, a syringe, and some medications necessary in cases of emergency medical aid are placed in them: camphor oil and caffeine solution in ampoules, tincture of iodine, ammonia spirits, ether-valerian drops, as well as tablets with opium, codeine, aspirin, etc. If the medical instructor has an oxygen inhaler with them, then the tag from it, the oxygen cushion, and the corrugated tube can also be placed in the medical instructor's bag. First aid kits with which medics in Red Cross and Red Crescent teams are supplied are made according to the general army model, but their contents sometimes deviate from the inventory of items adopted in the Red Army.
V. Leonardov—SANITARY TACTICS, the study of the most effective use of the resources of the army medical service in wartime. Since the task of the medical service in a combat situation is to "be the strongest at the right time and in the proper place," which is connected with the movement of medical resources (personnel, medical equipment, individual medical institutions), sanitary tactics is defined otherwise as the study of sanitary maneuvering. The most extensive and most developed chapter of sanitary tactics is the study of medical evacuation. At the present time, the content of sanitary tactics has been significantly expanded by information on medical reconnaissance and data on maneuvering with medical preventive resources (laboratories, sanitary inspection stations, vaccination detachments, etc.). Sanitary tactics as one of the military disciplines subject to study by medical personnel was first named as such by the senior physician of a Finnish rifle battalion, Wahlberg, who published an article in 1889 on the tactics of sanitary troops. In 1890, Wahlberg wrote a brochure, "Experience of a Brief Guide to the Tactics of Sanitary Troops," published first in Swedish and only later in Russian (St. Petersburg, 1890). In the introduction to this work, the author says that sanitary troops, which until that time had been "in neglect and almost in humiliation," must "like all other troops in peacetime in the field learn what they will have to do in war." Despite the fact that before this N. I. Pirogov had written much about the combat work of the medical service, emphasizing the exceptional importance of the ability to distribute medical resources and manage the medical service apparatus ("in war, administration is above all"), Wahlberg's appeal in Tsarist Russia of the late 19th and early 20th centuries did not receive a response, and his brochure was for a long time almost the only manual on sanitary tactics. The results of this did not fail to affect the sanitary consequences of the Russo-Japanese War of 1904-05, after which the first and last sanitary-tactical dissertation in the Russian language in the pre-revolutionary period was published by P. P. Potiralovsky, for which the author was awarded the degree of Doctor of Medicine: "Tyurenchen-Wafangou-Liaoyang in a Sanitary-Tactical Respect." Uncovering the root causes of the failure of the medical service in this war, Potiralovsky notes that "we saw preparation mainly in the scientific education of medical personnel, but we had to come to the conclusion that for the successful use of medical institutions during the war, the ability to direct the movement of the latter is necessary." Potiralovsky, based on an analysis of the experience of the Russo-Japanese War, comes to the conclusion that "sanitary tactics should be studied not only by field surgeons, but by all military doctors." In 1908, Unterberger came to essentially the same conclusions, pointing out the defects of the military-medical education of doctors at that time. Sanitary-tactical training of military doctors in the old army was first introduced in 1907. From this time, sanitary-tactical literature began to appear (Gerikh, Zaglukhinsky, Potiralovsky, Pruss, Timofeevsky, and others). During the imperialist war, the vast majority of Russian military doctors did not know sanitary tactics, and commanders had no idea about it. In the works of Burdenko, Oppel, Timofeevsky, and a number of other authors that appeared during and after the World War, one can find many concrete figures and examples testifying to the consequences of the sanitary-tactical illiteracy of medical chiefs in the World War. The percentage of those returned to the ranks from hospitals after treatment in the Russian army was significantly lower compared to the armies of France, England, the USA, Germany, and other states that took part in this war, not because Russian doctors were medically insufficiently prepared or because there were no medical resources, but mainly due to the unskilled use of the medical apparatus and its management. In the first years of the Civil War, the Red Army received from the past a medical staff with extremely low theoretical qualifications in sanitary tactics, but with some practical experience. New revolutionary methods of organization and work of the military-medical service in the active army and in the rear of the Soviet Republic, surrounded by an iron ring of fronts, emerged. This experience has not yet been sufficiently accounted for and studied to date. Systematic sanitary-tactical training of medical personnel for the Workers' and Peasants' Red Army began during the Civil War and has been improving to the present time. In 1922, sanitary tactics was introduced as an independent subject for study by military doctors, and from 1924 it became a mandatory discipline, taken at medical faculties (in medical institutes) as part of higher pre-conscription training; at the Military Medical Academy of the Workers' and Peasants' Red Army, an independent course in sanitary tactics was established in 1923, which was subsequently expanded into an independent department. The dissemination of sanitary-tactical information was facilitated by the organization and work of the sanitary section of the Military Scientific Society, which existed until 1928. Sanitary-tactical questions are widely covered in the periodical press (Military-Sanitary Collections of 1924-28, the journal "Military-Sanitary Affairs"). A number of official sanitary-tactical manuals and instructions have appeared in the Red Army. In the training of the modern Red Army doctor—a medical commander—sanitary tactics occupies a central place, combined with the entire system of constant improvement of his special medical qualifications. Research work in the field of sanitary tactics is proceeding in the direction of finding the best sanitary support for special branches of the armed forces. Sanitary resources studied by sanitary tactics are viewed by it from the point of view of technical properties and work standards. Methods of the medical service that provide for troops in a preventive respect, such as: preventive vaccinations, preventive quinine treatment, sanitary processing, disinfection and degassing measures, are characterized by duration of action, time for execution, expenditure of material resources, calculation of medical personnel output, and equipment productivity. Sanitary-preventive institutions are studied by sanitary tactics in relation to their throughput capacity, mobility, calculations of technical equipment, weight and volume tonnage, timeframes for deployment, folding, bringing to operational readiness, etc. Medical institutions are also considered from the point of view of their medical specialization, capacity (number of beds, calculation of patients and those wounded in battle received per unit of time), and work standards of individual subdivisions (dressing station, operating room, diagnostic offices, etc.). Sanitary transport is characterized by technical properties—cross-country ability, speed of movement, turning radius, load capacity—and tactical calculations of operation—capacity for sitting and lying evacuees, productivity of daily work, etc. External conditions affecting the morbidity and combat casualty rate of the manpower of troops, as well as determining the situation in which the activities of the medical service are deployed, are the subject of medical reconnaissance (see). Troops provided for in a sanitary respect are studied by sanitary tactics in relation to the standards of their physiological load, useful work (e.g., time of a daily march of infantry, cavalry units, mechanized troops, flight work in aviation, ski runs, etc.), provision with everything vital (clothing, footwear, housing, food, sanitary-technical devices and installations), labor and living regime, as well as morbidity (outpatient and hospital). Mainly on the basis of the experience of past wars, average figures for losses in troops due to illness and combat wounds are established for sanitary-tactical calculations. These contingents are called sanitary losses and represent the object of medical-evacuation support for troops. The norms of sanitary losses are only very approximate guidelines for building plans for the sanitary support of troops (calculations of the need for resources and the work of the medical apparatus), giving sharp deviations in examples of individual concrete episodes and requiring a multitude of corrections. The most common, empirically derived average calculation of combat losses is the Benesch calculation, which establishes combat losses for 3 days of battle for an infantry (rifle) division at 25% of the number of its active fighters, of which 1/5 (5%) falls to the share of the killed, and the remaining 4/5 (20%) constitute the contingent of sanitary losses. Corresponding figures for an infantry regiment for just 1 day of battle increase to 40%, and for a corps for 4-5 days of battle decrease to 20%. Many authors (e.g., Ritchie) believe that an army as an operational formation of corps and individual divisions loses about 15% of its numerical strength during a 7-10-day combat operation. French and Polish manuals use an even rougher calculation, suggesting a norm of combat sanitary losses for an infantry division in the first 2 days of battle of 600 people each, and in the following 2 days of 200 each. More stable are the average figures for losses due to illness in wartime, taken at 3-3.5 per thousand per day in relation to the total number of troops ("eaters").
The distribution of military casualties by type of combat weapon indicates a decrease in the number of bullet wounds in the total mass of those hit in battle (from 75-80% in the Russo-Japanese War to 9% in the American army in the World War), an increase in the number of artillery casualties (up to 55-60%), and the appearance in the composition of medical casualties of a new category—those hit by chemical warfare agents. For training purposes, most armies assume the number of the latter contingents to be equal to 1/3 of the total number of those hit in battle. All these 'average figures' can claim some approximation to the expected actual reality in modern war only in calculations covering significant intervals of time, a large number of battles, and various conditions of the combat situation. The range of deviations in specific cases increases with a decrease in their number
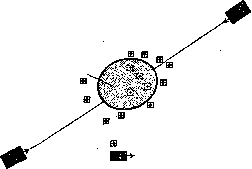
field of battle
field hospitals
armies of opponents Figure 1. Scheme of the organization of treatment on the spot after a decisive battle in the era of the strategy of one point (1st half of the 19th century). Depending on the effectiveness of treatment methods and the successes of the organization of medical evacuation, the average periods of stay in a bed change, assumed for the sick to be 2-3 weeks and for the wounded-1.5-2 months. The most stable remain the calculations of the localization of gunshot wounds due to the constancy of the ratio of the projection of human organs, which gives grounds to assume the injury of organs of movement in 2/3 of traumatic injuries. In connection with this stands the evacuation calculation of the grouping of the wounded in the forward area, according to which it is assumed that 1/3 accounts for lightly wounded, walking, capable of walking evacuation, 1/3-for wounded of medium severity with limited ability to move, requiring transport sitting, sitting, and 1/3-for heavily wounded, stretcher-bearers, completely incapable of independent movement and transported in a lying position. These ratios change as time passes from the moment of wounding in the direction of a relative increase/
in the number of lying /
and sitting, until in their condition a change for the better occurs. / field
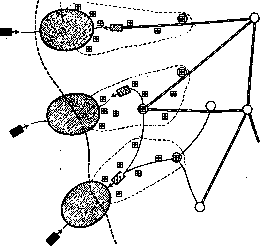
battle
_____state, border railways O cities S hospitals \ armies of opponents s U dispersion zone Figure 2. Scheme of dispersion of the wounded after battles in the era of the strategy of a series of points (2nd half of the 19th century). changes for the better. The evacuation-transport grouping of those hit by chemical warfare agents depends on the type of chemical warfare agent that caused the injury. Those hit by suffocating agents and chemical warfare agents of the phosgene type require maximum rest in the first 24 hours after the injury as a prophylaxis of pulmonary edema. The volume and nature of the task arising before the medical service in each individual battle (operation), determined by the calculation of medical-preventive work and the calculation of expected losses, the assessment of available medical resources on the basis of their quantitative accounting and tactical-technical properties, the characterization of external conditions according to the data of medical reconnaissance-give the medical commander the opportunity to propose the most grounded plan of action for the medical service apparatus subordinate to him. The goal of these actions in all cases is the medical support of the greatest success of the troops operating in battle; therefore, the preliminary decision of the medical commander is in its main features approved by the command of military units or formations, and the plan itself is built on the basis of corresponding instructions of the staff, given to all 'services' (engineering, communications, supply, veterinary), including the medical one. Upon approval by the command of the plan for medical support of the battle (operation), the plan is carried out i ii.P Russo-Jap. Amer. Eng. Fr. Germ. 1870-71 1904-05 I
1914-18
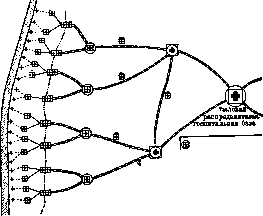
I Figure 3. Comparative size of armies in the 19th and 20th centuries. by the medical commander, coordinating the details of execution with the staff of his military unit (formation). In urgent cases, medical commanders are obliged to make independent decisions with a subsequent report to the command. The methodology of operational and staff work of medical commanders in our country also enters as one of the sections of medical tactics. A medical maneuver in battle, pursuing the same goals that stand before the entire military unit (formation) as a whole, must reflect in its plan the main intent (decision) of the command. As a general rule, medical resources before a battle are massed (accumulated) in the direction of the main attack. During an offensive, the bed (treatment) apparatus is brought as close as possible to the troops in order to fully reduce evacuation routes and thereby increase the productivity of the work of medical transport. During a retreat, the most cumbersome medical resources are withdrawn in advance to the rear, and on the paths of retreat, the most mobile resources and the largest possible amount of medical transport are delayed until the last moment. In a stable defense, approaching the conditions of positional warfare, the first medical aid is brought as far forward as possible, into shelters specially constructed for this purpose, and communication trenches are adapted for the purposes of medical evacuation. In a meeting engagement, medical resources are echeloned in the marching column so as to ensure the most rapid deployment of medical institutions and the equipment of evacuation routes. But these are only very general rules, far from exhausting the details when establishing the order of work of the medical service. The latter is established in relation to the protection and preservation of the health of troops by the plan of their medical-preventive support, and in relation to those who have left the ranks of the troops due to the loss of health-by the evacuation plan or the plan of medical evacuation. Medical evacuation over the last century has undergone significant evolution. The operational (military) art of the Napoleonic era, characterized by Clausewitz as the 'strategy of one point,' boiled down to bringing the strongest possible army to the same army of the opponent. The battle that arose in the place (point) of the meeting usually decided the fate of the entire war, giving on such a field of decisive battle the largest number of combat casualties for the entire war. The medical service in these conditions organized the treatment of the wounded 'on the spot,' i.e., in the villages, hamlets, and cities closest to the battlefield (Fig. 1). But as soon as 50 years later military technology grew and the rifle began to shoot not at 200 m, but at 1,000-1,300 m, and the cannon not at 1 km, but at 3.5 km, the tactics of battle and the art of leading armies changed. Moltke in 1866 deploys against Austria not one, but three whole armies, which is facilitated by the appearance of railways leading to the borders of the state (Isserson). A 'strategy of a series of points' arises. The system of treatment on the spot ceases to satisfy at this time and is supplemented by the dispersion of the wounded to populated areas, more distant from the fields of battle (Fig. 2). Medical transport is carried out along dirt and railway roads, for which special medical transport is created. By the moment of the outbreak of the World War, military technology develops to such an extent that artillery begins to hit closed targets located 6-11 and more km away. The range of the rifle increases to 3-4 km and its rate of fire; next to it, an automatic machine-gun begins to operate, giving up to 500 bullets per minute. Armies strive to disperse to the sides; the most dangerous blow becomes a blow to the flank. At the beginning of the World War, the so-called 'race to the sea' begins. The era of linear strategy of 1914-18 gives classic examples of wide fronts along the entire length of the continent. At this time, treatment on the spot becomes already impossible, battles last for weeks, the size of the army increases (Fig. 3), and the number of wounded at the same time reaches such sizes that mere dispersion of them in the immediate rear turns out to be insufficient. A period of the evacuation system arrives, when the basis of aid to those hit in battle and the sick is their removal to the deep rear and the systematic 'drainage' of the active army to remove non-combat-ready contingents from its composition (Fig. 4), but pre-\ front-line hospital base
hospital base army hospital base. (field evacuation point) Hospital No. 3 of the 1st line. Hospital No. 2 of the 2nd line. intermediate hospital medical aid points. boundary of the troop district Figure 4. Diagram of sanitary evacuation in the era of linear strategy (at the beginning of the world war). On the left (shaded strip) - the combat zone on a continuous front line. Neglect of the basic principles of treatment - timeliness of medical care, its continuity, and rest for those in need - sharply negatively affects the results of treatment. As a result of the experience of the world war of 1914-1918, a new system of 'stage treatment' (Oppel), or 'echeloned treatment' (French authors), emerges, which seeks to combine the transportation of evacuees with the provision of medical aid at the stages of evacuation in the same sequence as is carried out in a stationary medical institution, where the wounded or patient undergoes the entire course of treatment until the moment of one or another outcome of their illness (fig. 5) (see Field Surgery).

Under the conditions of modern war, characterized by the possibility of damaging armies not only along the front but also in the depth of their deployment, the stage treatment system, with its continuous flow of evacuees to the rear, encounters great difficulties. A blow on the main direction from the depth of one's deployment into the depth of the enemy's troop deployment, the commitment of motor-mechanized units to break through the front line with a simultaneous air raid on the rear to defeat the enemy's reserves [------------], dressing room, operating room, reception ward, rest ward for those undergoing surgery,
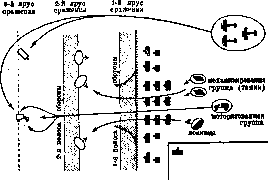
Figure 5. Plan of a hospital with a diagram of the stages of sanitary evacuation drawn into it (diagram of stage or echeloned treatment). (fig. 6) places the sanitary service of both the attacking and defending armies in conditions of a very complex combat situation and requires the equipment of new sanitary technology. In relation to sanitary transport, first place is taken by the high-cross-country sanitary vehicle (sanitary transporter) and the sanitary airplane, which frees it from dependence on non-rail (earth and highway) and rail (railway) routes. The motorization and mechanization of sanitary troops inevitably change their tactics, which in the first place must ensure the exploitation of all the advantages (speed of movement, range of action, mobility, etc.) of the latest technical means. Accordingly, sanitary tactics are significantly complicated. Reconnaissance, correct assessment of the situation, decisiveness and resourcefulness of the sanitary commander, his organizational skills, and precise calculation and coordination of the actions of the entire sanitary apparatus become the basic conditions for the success of combat sanitary work.
The plan for sanitary evacuation finds its expression in the form of a sanitary evacuation diagram and in the form of a planning table, where in the horizontal columns the troop units provided with sanitary support are indicated, and in the vertical column - the time and the expected place of development of their combat actions. Sanitary tactics, while remaining a medical discipline in its content, in the methods of its study is increasingly approaching the military sciences. Hence the requirements for the organization of sanitary-tactical training, which should: a) be conducted with contingents having medical education and who have passed a preliminary course in military disciplines (organization of troops, their tactics, familiarity with the basic combat regulations), b) be practical, i.e., conducted not only by the book and in the classroom, but carried out mainly in the field by solving typical sanitary-tactical problems and military-sanitary games, first on a map without real means, and as operational skills are acquired (organization of reconnaissance, assessment of the situation, decision-making, planning, maintaining communications, working with a map, etc.) - with field sanitary equipment and with sanitary troops.
In full, the verification of sanitary-tactical training can be achieved in combined arms exercises, in which the sanitary service participates.
Related articles
Mentioned in
Cite this page
“First Aid Kit.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/first-aid-kit/