Muscles
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia provides a detailed histological overview of muscle tissue, distinguishing between smooth and striated muscle. It describes the morphological and functional characteristics of muscle fibers, myofibrils, and their structural components, including the Z-discs and various bands observed under microscopy.
Encyclopedia article (1928–1936)
MUSCLES. I. Histology. From a general morphological perspective, the tissue of contractile substance is characterized by the presence of differentiation in the protoplasm of its elements into a specific fibrillar structure; the latter are spatially oriented in the direction of their contraction and serve as the morphological substrate for the specific contractile function of muscles. Located parallel to one another, the visible elements of this structure, so-called myofibrils, appear in the form of extremely thin (up to 0.2 μ in diameter) filaments, distinguished by their characteristic property of true positive uniaxial anisotropy. Depending on whether the myofibrils are optically homogeneous or constructed of fragments of optically heterogeneous substance alternating along their length, two main types of musculature are distinguished: smooth muscles and striated muscle tissue.
1. The morphological and functional unit of smooth muscle tissue—the smooth muscle fiber (cell-fiber)—is an elongated (in vertebrates), spindle-shaped, somewhat flattened along the long axis, single-nucleated formation, on average 100-200 μ in length and 4-8 μ in width (limiting dimensions: 24-500 μ in length, 4-13 μ in width). Fibers branched in a fork-like manner at one or both ends are encountered. The elongated, so-called 'rod-shaped' nucleus is located somewhat eccentrically in the middle of the cell length. The protoplasm of the cell-fiber appears delicately striated due to the presence within it of extremely thin homogeneous myofibrils, located parallel to the long cell axis. The nucleus is surrounded by a certain amount of sarcoplasm (protoplasm, fibrillarly undifferentiated), which accumulates at its poles and forms extremely thin layers between the bundles of fibrils; within it, a 'cell center' is discovered, located next to the nucleus, and chondriosomes scattered throughout the cell body. In the composition of the tissue complex, the elements of smooth musculature are connected to each other by small fibers, so-called myoglia, which have the character of 'reticular' fibers of connective tissue, sometimes assuming a collagenous type and forming net-like sheaths on the surface of each muscle cell. Architecturally, human smooth muscles appear either in the form of thin, individual strands embedded in connective tissue or in the form of continuous contractile membranes; in the latter case, the fibers within the muscle layer are either located parallel to each other or form net-like plexuses of muscle strands. Functionally, human smooth muscle tissue is the so-called musculature of involuntary movement of internal organs, the vascular system, and the integument, and is always innervated directly by the peripheral neuron of the autonomic nervous system. 2. Striated muscle tissue is optically heterogeneous due to the structure of the myofibrils that compose it; in the vertebrate organism, it is represented either by morphologically individualized entities (skeletal musculature) or by a syncytially connected system of muscle cross-beams (the type of cardiac muscle). The structural unit of 'skeletal' musculature is the so-called striated muscle fiber, a multi-nucleated, strongly elongated cylindrical formation with pointed or rounded ends. The average size of a fiber in humans is from 4 to 8 cm in length with a diameter of 40 to 50 μ (the smallest observed length is 2 mm, the largest is about 12.7 cm; the smallest diameter is 9 μ, the largest is 150 μ). The myofibrils within the fiber are arranged in the form of columns separated by a greater or lesser amount of sarcoplasm, which on its cross-sections give the appearance of so-called Cohnheim's fields. Numerous nuclei are distributed along the entire length of the muscle element; in the sarcoplasm-poor muscles of mammals, they are located in its peripheral, sub-membrane layer. The entire fiber is covered by a sarcolemma, a membrane previously homologous to cell membranes, but now recognized as a connective tissue formation; it is intimately connected with the substance of the muscle fiber on one side and with the tissue of the perimysium on the other, by means of the small fibers that are part of its composition. The characteristic transverse striation observed during microscopic examination of a striated muscle fiber is conditioned by the heterogeneity of the optical structure of its myofibrils on one side and the presence of transverse, extremely thin membranes (inofragms) crossing the entire fiber on the other. Located along the length of the muscle fiber strictly at the same levels, identical iso- or anisotropic sections of adjacent myofibrils produce the optical phenomenon of alternating, parallel light and dark bands, as if cutting through the entire fiber in the transverse direction (so-called discs); this picture is further complicated by the lines of optical sections of the inofragms, which also cross the muscle element in the transverse direction at specific intervals of its extent. Alternating in a specific section of the muscle fiber, the discs form so-called muscle segments, characterized by the same sequence of discs included in each of them. The scheme of transverse striation within one segment: The boundary of two adjacent segments is generally considered to be the inofragm cutting the fiber between two isotropic discs, connected at its periphery to the sarcolemma (Z-disc of modern nomenclature, Heidenhain's telophragm, thin dark disc of French authors, Amici-Krause band of old nomenclature); adjacent to it is the isotropic disc (I of modern nomenclature, light disc of French authors); next follows the wide anisotropic disc (Q of modern nomenclature, thick dark disc of French authors). In ordinary transmitted light, with a stretched fiber, the middle part of Q appears lighter, forming a light band (h of modern nomenclature, Hensen's band), cut in the middle by the extremely thin M-inofragm (Heidenhain's mesophragm, Merkel's band); then follows again the isotropic disc I, and finally, the segment is closed by the next Z-inofragm. Thus, in letter expression, the scheme has the form: z + i + (Q + h + M + h + Q) + i + z. The Q-disc, which appears continuous in polarized light, possesses true positive anisotropy, while the anisotropy of Z is explained by the phenomenon of so-called depolarization. The fibrillar discs Q and I, besides their metamicroscopic structure, differ in their ability to adsorb light, density, and probably chemical composition. The properties of the M-mesophragm are almost unknown: this disc is little accessible to observation and is clearly visible only on fixed preparations of a maximally contracted fiber. The average height of the entire segment in vertebrates is about 2.5 μ. The sarcoplasm of the striated muscle fiber is characterized by the presence within it of granular formations of various morphological significance: along with true sarcosomes, which represent the chondriomes of the fiber and are arranged in regular rows between the fibrils at the levels of the I-disc (I-Q grains), droplets of lipoids and clumps of glycogen are also found here. Interesting are the argentophilic transverse networks of fibers discovered by Veratti, located at the level of the I-discs on both sides of Z and possibly identical to Holmgren's trophospongium. In the composition of the muscle complex, the 'muscle', striated muscle fibers are connected by means of the fibrous connective tissue of the perimysium, the small fibers of which transition into the fibrous framework of the sarcolemma. The question of the connection of the fibers with the corresponding tendon is currently a matter of debate: while according to the opinion prevailing in modern literature, this connection is entirely carried out through the mediation of the perimysium fibers, a number of researchers insist on the presence of a direct transition of myofibrils in the region of the tendinous end of the muscle fiber into the collagenous fibrils of the tendon bundles. Unlike skeletal musculature, striated cardiac muscle is characterized by a) the syncytial arrangement of the muscle cross-beams included in its composition, b) the axial arrangement of nuclei in connection with the presence of an accumulation of sarcoplasm in the axial region of these cross-beams, and c) the presence of special bands crossing the latter at indefinite distances, so-called 'intercalated discs'; the morphological and functional significance of the latter is still controversial. Previously homologized with cell boundaries, these formations are currently considered either as growth points of the cardiac-muscle syncytium or are assigned the significance of microscopic intermediate tendons, which serve as a supporting element during the contraction of the latter. Literary data on the morphology of the contraction of striated muscle are to this day extremely incomplete and contradictory: it can be considered generally accepted that the morphological substrate of contraction is precisely the myofibrils, but even the question of which of the myofibrillar discs the shortening of each myofibril predominantly occurs at the expense of is a subject of debate. Also not finally clarified is the morphological significance of the so-called...
"contraction bands" (CS in modern nomenclature), observed in fixed preparations of maximally contracted striated muscle fiber instead of its normal striation. Due to what was said above, modern theories of muscle contraction have long been constructed without close connection to the morphological data of the finest microstructure of muscle tissue. All these theories, starting from Engelmann's, recognize as the immediate cause of fibril shortening the property of a colloidal protein gel (in this case, the substance of the muscle fibrils) to change its external form under the influence of energy changes in its surrounding environment (resp. sarcoplasm). These changes, according to the generally accepted view, are in turn due to chemical processes arising in the muscle fiber at the moment of its excitation. The very mechanism of the indicated change in the shape of contractile fibrils is explained either by 1) an increase in the osmotic tension of their substance depending on the appearance at the moment of excitation of new cleavage products (so-called osmotic theories of McDougall and Zuntz), or 2) a change in surface tension on the surfaces separating the fibrils and sarcoplasm (d'Arsonval-Bernstein theory), or finally 3) by the swelling of the anisotropic substance of the muscle fibrils during the hydration of the proteins included in its composition that occurs at the moment of contraction (theory of Engelmann, Pauli, Fürth). This swelling must occur either at the expense of water coming from isotropic fibrillar sections (Engelmann), or from the surrounding sarcoplasm, or at the expense of water from the anisotropic sections themselves; the latter in this case must be constructed from ultramicroscopic granules of ellipsoidal shape suspended in a liquid medium; their long diameter is parallel to the direction of contraction. Changes in the hydration capacity of the protein gel were explained by Engelmann as the influence of the significant increase in the temperature of the muscle fiber observed during contraction, which is the result of oxidative processes arising at the moment of excitation. In contrast to this "thermodynamic" theory of Engelmann, modern "chemodynamic" theories of muscle contraction accept the indicated hydration as the result of a change in the reaction of the muscle element's substance arising at the moment of excitation. At the same time, according to Fürth and Pauli (see also the data of Meyerhof and Hill), the moment triggering contraction is the appearance of acidic cleavage products in the muscle; Embden, however, believes that here, on the contrary, alkaline products play a role. Carefully conducted observations by Hill on the course of heat production of striated muscle in various stages of its activity refute the classical theory of Engelmann; in connection with the latest research by Meyerhof and Embden, Hill's experiments provide a foundation for "chemodynamic" theories. Functionally, the skeletal striated musculature of vertebrates is, as a rule, musculature of voluntary movement and is innervated by a motor neuron of the cerebrospinal nervous system. The automatically working cardiac muscle is innervated according to the type of smooth muscle tissue.
A. Mislavsky. II. Physiology. Functions of the muscle. The main function of the muscle organ is to set in motion and mutually displace individual links and parts of the body. At the basis of these movements lie the processes of muscle contraction, with the consideration of which it is more convenient to begin an acquaintance with the physiology of muscular activity. A muscle can be forced to contract by acting upon it with various agents: mechanical influences, chemical reagents, heat, and finally, electric current. When experimenting with a muscle, it is desirable to take as a stimulus a factor which 1) would not damage the muscle, 2) would act on the whole muscle at once, 3) would be amenable to dosage, and 4) the action of which could be quickly turned on and off. Mechanical influence is usually accompanied by damage to the surface fibers. This, however, can be avoided if one stimulates the muscle from its nerve (indirect stimulation). In this case, a small device is used, the so-called tetanomotor, consisting of an electromagnet and a movable armature, brought into vibrational trembling, which is transmitted in the form of light blows to the motor nerve of the muscle. Thermal influence on the muscle can be carried out if one quickly changes the temperature of the muscle; this is usually accompanied by some damage to the muscle. Chemical irritation (acids, citrates and oxalates of sodium, alcohol, chloroform) brings into action in the first place (and this is understandable) the surface fibers. The most convenient and satisfying all the requirements given above is stimulation with the help of an induction current. The source of the latter is usually the so-called Du Bois-Reymond sled apparatus (see Du Bois-Reymond sled apparatus), in which it is possible, by sliding the primary and secondary coils together and apart, to change the voltage of the induction current. This type of current, in contrast to direct current, does not produce polarization. For the study of muscle contractions, the muscle is placed in a so-called myograph. The gastrocnemius muscle (m. gastrocnemius) of a frog is fixed immovably in the upper part. Upon contraction of the muscle, its lower end (Achilles tendon) lifts a lever, which is equipped with a stylus writing on a smoked tape of a kymograph. Since the muscle pull acts on the short arm of a lever of the 2nd kind, and the recording is produced by the long arm, the myograms are obtained as many times larger than the actual contractions as the long arm is larger than the short one. A very weak shock of current is not able to cause a muscle contraction. The moment when the muscle first contracts is called the threshold of excitation. With further strengthening of the stimulating current, the single contractions of the muscle also strengthen, but this increase occurs only up to a certain maximum limit, upon reaching which the contractions of the muscle no longer increase. Between the moment of receiving a single stimulus by the muscle and the moment of the beginning of contraction, a certain interval of time passes, equal for the frog muscle on average to 0.01 seconds and named by Helmholtz the period of latent excitation, or latent period. The phases of contraction and relaxation usually last 0.05 seconds each. In the case that the muscle is fatigued, the total time of a single muscle contraction increases mainly due to the lengthening of the relaxation phase. A stimulus falling on the muscle before the latter has managed to come into a state of relaxation gives a so-called summation of muscle contractions. With sufficiently frequent stimuli, the muscle does not manage to relax and comes into a state of prolonged, so-called tetanic contraction, or tetanus (Helmholtz). The longer a single contraction of the muscle lasts in a given species of animal, the lower the frequency of stimuli at which tetanus can be obtained; with short single contractions of the muscle, even very frequent stimuli can cause only single muscle contractions, but not give tetanus. Thus, the gastrocnemius muscle of a frog comes into a state of tetanic contraction already at 20 shocks of induction current per second (the duration of its single contraction is equal to 0.1 seconds), while the wing muscles of an insect do not give tetanus even at 200 stimuli per second (the duration of a single contraction is equal to 0.003-0.040 seconds). The Russian scientist N. E. Vvedensky proposed his theory to explain the deviations in the magnitude of tetanus, calculated as the result of a simple superposition (summation) of muscle contractions equal in magnitude. According to Vvedensky, there exist optimal tempos (frequencies) and strengths of stimulation that give the maximum tetanic contraction. In these cases, the stimulation not only causes a single contraction but also increases the susceptibility of the muscle tissue to subsequent stimuli, as a result of which the tetanus turns out to be larger than in the case where all contractions would be completely identical. Excessively strong or excessively frequent stimuli—pessimum (see)—give a smaller effect than weaker or less frequent stimuli—optimal. The cardiac muscle, as is known, does not give a tetanic contraction, but can only rhythmically contract. The latter is conditioned by the presence in it of a so-called refractory phase, when the cardiac muscle becomes inexcitable, insusceptible to stimuli falling upon it. Questions related to the reaction of the muscle to one and two subminimal, i.e., lying below the threshold of excitation, and supermaximal stimuli, have been studied in detail by Vvedensky and his students (see Parabiosis, Pessimum). One subthreshold stimulus of the muscle is not capable of causing its contraction, but, as we saw above, it can increase the excitability of the muscle and, at a certain frequency of such stimuli, cause a maximum contraction. Two maximum stimuli following one after another give a completely different effect depending on what the duration of the interval between them was. With a more or less significant interval, the amplitude of contraction turns out to be very large; with a very small interval (e.g., in a thousandth of a second), two maximum stimuli act as one supermaximal, and the contraction turns out not larger, but, on the contrary, smaller (stages of parabiosis). Contraction wave. Upon stimulation of a muscle that has been subjected to the action of curare poison, its contraction is observed not immediately along the entire length, but first at one point—the place of application of the stimulus (in case of indirect stimulation through the motor nerve—at the place of location of the end plates of the nerve). The contraction of the muscle from this place occurs immediately in both directions, in the direction of both its ends. The speed of this contraction wave (Kontraktionswelle) in different animals turned out, according to the studies of Bernstein and Hermann (Bernstein, Hermann), to be different: in the frog about 3 m/sec., in the rabbit 5-10 m/sec., in man 10-15 m/sec. For smooth muscles, the speed of propagation of the excitation wave is less than for striated ones. Law of average load and tempo. Mechanical work is expressed, as is known, by the product of force and path. In the case of lifting a load, we can substitute the weight of the load for force. The question naturally arises about the dependence existing between the weight of the lifted load and the mechanical work performed during this. This dependence is easy to detect if one takes a nerve-muscle preparation or a frog muscle without a nerve and records the heights of lifting the load with different weights. Experiments of this kind have been set up many times and have already become classic; they showed that with an increase in the load, the mechanical work grows, but only up to a certain limit; having reached it, it begins to decrease and at a certain limiting load falls to zero. Mechanical work is expressed in this case in gram-centimeters (g/cm) or kilogram-meters (kg/m). This dependence is usually called the law of average load. A similar dependence can be detected also regarding the tempo (speed) of work. At a certain average tempo, the mechanical work turns out to be the greatest. These two dependencies cannot be applied indiscriminately and uncritically to the whole organism, where the connection of the muscle with the circulatory system ensures the supply of oxygen to the muscle tissue and the removal from it of certain substances formed as a result of muscle work. The participation of the nervous system in muscle contractions also changes the process of muscle work so much in comparison with the contractions of a nerve-muscle preparation that the dependencies observed in the latter are significantly complicated. This is especially true in relation to the law of average speed (tempo). Fatigue of the muscle. Under the influence of prolonged work, a number of changes occur in the state and functioning of the muscle, usually designated as fatigue. This term is one of the most indefinite and imprecise in physiological terminology, and different authors understand far from the same thing by it (See Fatigue). In its simplest form, the phenomena of fatigue manifest themselves in the work of an isolated muscle periodically stimulated by an induction electric current (stimuli of maximum strength). At the beginning, the contractions of the muscle almost do not change in their height, and then the decrease becomes noticeable and continues to progress until finally the muscle completely ceases to contract. The more the muscle is loaded and the more frequent the stimuli, the sooner its fatigue sets in. The total duration of contraction during fatigue increases mainly due to the lengthening in time of the relaxation phase.
A highly fatigued muscle may not even provide complete relaxation (residual contraction or contracture). Along with the slowing of the entire process of muscle contraction, the speed of the contraction wave also decreases. During fatigue, the contraction wave may even stop at the site of stimulation, and an so-called idiomuscular swelling then forms there. Finally, during fatigue, the strength of the muscle decreases and the threshold of stimulation increases. A muscle that has reached a state of complete fatigue and does not respond to any stimulation can—even outside the organism—return to a functional state, albeit to a far from complete extent. This phenomenon still has no scientific explanation. A muscle that is in connection with the circulatory system of the organism, and even better, a muscle that has not been removed from its place and has preserved all its nervous and vascular connections, resists fatigue significantly longer than an isolated muscle. At the present time, a very primitive concept of fatigue is widespread in physiology, reducing almost all phenomena to the accumulation in the tissues of a working muscle of some kind of 'fatigue substances.' With the connection to the vascular system preserved, these substances are supposedly quickly washed out of the fatigued muscle, and it regains its working capacity. In an isolated muscle, there is no washing out, and the hypothetical substances are oxidized by oxygen from the air diffusing into the muscle. Of course, the phenomena of muscle fatigue are much more complex than many modern scientists imagine. There are many reasons to assume that fatigue is connected with processes of a colloid-chemical nature and proceeds with the direct participation of the autonomic and cerebral nervous systems. If even the phenomena of fatigue in an individual muscle have not yet been scientifically explained, then it is understandable that the much more complex process of fatigue of the whole organism is far from its scientific interpretation. Fatigue of human muscles is usually studied with the help of an ergograph (see Ergography). The load lifted and lowered thanks to the flexion and extension of a finger or arm can be of different weights. The tempo can also vary. By selecting different values for both, one can find on the work of the finger the same laws of average tempo and load that were considered for an isolated muscle, but from this, one should by no means draw broad generalizations concerning the whole organism. Ergograms have an individual character: in some, the decrease in amplitude occurs slowly; in others, on the contrary, almost immediately after the start of work. One should not think that ergograms reflect only the fatigue of the muscles of the working finger; despite the fixation of the forearm, the work of lifting the load is not limited to the participation of only the finger flexors, but as fatigue progresses, more and more new muscles are involved in the work. The ergograph is often used to assess human working capacity, and attempts have even been made to use it in industry. Such attempts must be treated with great caution. The magnitude of working capacity in professional labor is determined by a whole range of factors, including factors of a psychological nature (interest in the work, competition, shock-work). After all, labor differs from work precisely in that it represents a phenomenon of a bio-social nature. By assigning a worker a task on an ergograph, the researcher excludes this element and studies the working capacity of the subject not in relation to the professional labor performed by the subject, but in relation to uninteresting and meaningless work involving lifting a load with a finger or arm. The total amount of energy released by a muscle strictly corresponds to the work that it performs. This has recently been proven by precise experiments by Hill's students—Azuma and Fenn. Meyerhof, Embden, and their students established that the greater part of the decomposed hexosephosphoric acid is restored again in the stage of muscle relaxation. In a fatigued state, the processes of resynthesis occur half as energetically as in a fresh state, and the muscle loses much valuable substance—a source of energy—in the process. It has been proven that the smaller the part of the initial substances that finally burns in the muscle, the higher its efficiency. Hill compares a muscle to an accumulator that recharges itself after each partial discharge. Elsewhere, he draws an analogy between a muscle, in which hexosephosphoric acid alternately breaks down into lactic and phosphoric acids and is then resynthesized, and a self-winding spring. Muscle as a receptor. Usually, the muscle is considered as an organ of movement, and another role of the muscle—the role of a receptor apparatus—is pushed into the background. Inside the muscle tissue, and especially in the muscle tendons, there is a huge number of nerve endings that signal to the central nervous system about the degree of muscle tension and, consequently, about the position of the body's segments at various moments of movement, and about the direction and speed of the latter. The muscle is thus an organ with a dual role—receptor and effector. Since the impulses traveling centripetally from the endings in the muscle provide information about the internal state of the organism and its parts, the English physiologist C. Sherrington called these endings proprioceptive. However, objections are raised against this term, since in a number of cases, receptor endings also provide an idea of the properties of objects in the external world. Thus, for example, a person holding a stone in an outstretched hand and thereby assessing its weight is undoubtedly using data on the degree of contraction of their muscles for this, data obtained from proprioceptive elements. Long before Sherrington, the famous Russian physiologist I. M. Sechenov gave another name to the sensations we receive from our muscles. He called these sensations 'dark muscular sense,' thereby emphasizing the difference between them and sensations received from the sense organs. The muscle and its relation to the nervous system. The muscle, as is known, is part of a reflex arc. Numerous experimental studies have shown that the muscles of some animals can sometimes function without the participation of the nervous system and that, apparently, the early link of the reflex arc was precisely the muscle, and only then, in the order of phylogenetic development, did the muscle cause the appearance and improvement of the sense organs and the central nervous system (Samoilov). The muscle brought the central nervous system to life, this most complex formation that we know, and then, in the process of evolution, this system began to perform a number of new independent functions; the muscle, meanwhile, shifted to the role of an executive organ. According to the views of I. M. Sechenov, the muscle was precisely that formation which significantly influenced the function of certain sense organs. If the human ear can assess the duration of various sounds, it is completely incapable of assessing the duration of pauses—soundless intervals of time. The latter could be accomplished, according to Sechenov's thought, only if the pauses were filled with muscular sense with its characteristic viscosity. This circumstance indeed takes place during walking. 'In view of the fact that every placing of the foot on the ground is accompanied by a sound, walking at various speeds is for consciousness a periodic series of short sounds, the intervals of which are filled with viscous elements of muscular sense. This is, therefore, the school in which hearing could learn to assess the various duration of intervals within the limits of acceleration or deceleration of the step during walking' (Sechenov, 'Elements of Thought'). On the other hand, the assessment of distances with the help of the eye is also accomplished thanks to the muscular sense. The complex of impulses traveling from the endings located in the six muscles of the eye to the brain gives us an idea of the shape of objects, their distance from us and from each other, and the direction, character, and speed of their movements, which is significantly more complete than in the case of a stationary eye. As a result of a whole series of ingenious examples and constructions, I. M. Sechenov comes to the conclusion that the muscular sense was and is an analyzer of time and space. Muscular work. There is not a single professional job where one muscle or an isolated group of muscles participates. As a rule, many muscles take part in work, and the longer the work is performed and fatigue progresses, the greater the number of muscles involved in it. Part of the musculature performs the function of fixing certain joints or parts of the body in a given position, while another part directly participates in the work. The tension of a muscle that is not accompanied by further approximation of its ends and those segments of the body to which it is attached by means of tendons, we conventionally call static work. This term, which has taken root in physiology, is from a physical point of view incorrect, since mechanical work presupposes the presence of some displacement caused by the action of a force applied to the body. The term 'static,' however, points precisely to the absence of movement. However, since this name for the isometric tension of a muscle when holding a load, fixing parts of the body, etc., has not been replaced by another more rational one, it must be preserved and used.
The activity of muscles, the ends of which move the links of our body and foreign objects connected to them (tools, loads), relates to dynamic work. The organism as a whole does not remain indifferent to the activity of its own musculature. The main factor in this regard is the increasing need of active muscles for nutrients and, primarily, for oxygen. Usually, any more or less significant muscular work is accompanied by a general increase in blood pressure in the cardiovascular system, a redistribution of blood in the organism in the sense of a greater supply to the active part of its musculature, and the dilation of capillaries and an increase in their number in working muscles. According to data by A. Krogh, the number of open capillaries in 1 mm2 of the cross-section of a working muscle increases by 10-100 times compared to the resting state, and the total surface area of the capillary network in 1 mm3 of muscle tissue increases by 12-130 times. There is a hypothesis that the local dilation of blood vessels in working muscles is caused by an increase in the active reaction in the muscles. Atzler and Lehmann found that the pH in a working muscle decreases by 0.2 and that even such a weak acid as carbonic acid can cause vasodilation. The latter leads immediately to two consequences: an increase in blood inflow and an increase in the outflow of venous blood and lymph. As for the redistribution of blood in the organism, it is accomplished by the constriction of the lumen of the vessels of internal organs and the corresponding dilation of the vessels of active muscles. Weber, and after him Lehmann, showed that the blood supply to muscle groups increases even before the start of work, already at the mere thought of possible work. Static work, in contrast to dynamic work, is characterized precisely by the fact that the vessels of isometrically tensed muscles are compressed by the latter; blood supply to muscle tissue during static work is much worse than during dynamic work, in which muscle contractions are rhythmically replaced by their relaxations. It is possible that this is the reason for the greater fatigability of muscles during static work. Poor blood supply, difficult washing out of metabolic products from tensed muscles, and, in the case of fixation of the chest, also a disturbance of respiration and blood circulation in the whole organism—this is what, as a rule, characterizes static work. The increase in pressure in the arterial system during muscular work is conditioned, on one hand, by the periodically occurring difficulty in blood outflow through active muscles, and on the other, by an increase in the frequency of heart contractions and an increase in the volume of an individual systole. This pressure (maximum) can reach very high values (up to 200 mm and higher). Therefore, in cases of advanced arteriosclerosis, muscular work is contraindicated. The following table gives an idea of the relationship between the power (intensity) of work and the volume of blood ejected by the heart in one minute: Relationship between work power and minute volume. State of the organism | Work power (in kg.m/min) | Minute blood volume (in l) | Rest | 0 | 3.0 | Work I | 180 | 8.5 | Work II | 500 | 12.5 | Work III | 700 | 14.0 | Work IV | 900 | 16.0 | Work V | 1100 | 21.6. Venous circulation also does not remain unchanged during muscular work. During dynamic work, increased excursions of the chest contribute to the inflow of venous blood from the venae cavae into the right atrium, as intrathoracic pressure decreases during this. Thanks to more energetic heart activity, blood passes through the capillary network with greater force and enters the venous system under higher pressure. Finally, contractions of the leg muscles squeeze blood out of the veins in the direction of the heart (venous valves prevent it from flowing back), and thanks to all these factors, the blood filling of the right heart during diastole increases significantly. This same circumstance, according to the well-known "law of the heart" of E. Starling, entails an increase in the systolic volume and leads to an increase in the supply of blood and oxygen to active muscles. Something different happens during static work. A fixed chest (when lifting or carrying weights, when moving carts, trolleys, wheelbarrows, etc.) prevents, due to the high air pressure created within it, the inflow of blood from the venous system into the right heart. If, in addition, the huge muscle masses of the legs are in a tensed state, then the conditions for the movement of blood along the veins of the legs upward to the heart become very difficult. All this leads to blood stasis in the legs (occupational dilation of skin veins) and (during the static work itself) in the veins of the face and head. The harmful effect of static work on the organism has been repeatedly emphasized by many researchers, and it is undoubtedly the case that the most important factor here was disturbances in blood circulation. The effect of muscular work on human respiratory activity is enormous. Even with small muscle work, breathing becomes rapid and uneven. Without touching on the question of what exactly is the stimulant of the respiratory center—carbonic, lactic, or other acids formed during muscle work—it is necessary to note that there is a definite and (within certain limits) linear relationship between the power of the work performed and the magnitude of pulmonary ventilation, as the following table shows (compiled according to data by Boothby). Relationship of pulmonary ventilation to work power. State of the organism | Work power (in %) | Ventilation | Rest | 182 | 100 | Work II | 256 | 178 | Work III | 320 | 283 | Work IV | 347 | 288 | Work V | 521 | 306 | 438. As we can see, the relationship in this case has a linear character. Research by Hill and other physiologists and biochemists has established a number of extremely curious facts relating to the role of lactic acid in the process of respiration. As is known, the organism, after more or less difficult work, does not immediately return to its normal resting state. Pulmonary ventilation and the amount of absorbed O2 are elevated, and the ratio of CO2:O2 in the exhaled air, or the so-called respiratory quotient (RQ), also remains increased for some time, indicating the predominant combustion of carbohydrates. Chemical analysis of the blood in this period (recovery or reparative period) shows a higher content of lactic acid than at rest. By the end of the recovery period, pulmonary ventilation and the volume of absorbed oxygen return to normal. The same happens with the RQ and the lactic acid content. Barr and Himwich established that in the recovery period, the oxidation of lactic acid released into the blood occurs in the tissue of non-working muscles. Having compared a number of experimentally established facts, Hill and his colleagues came to the conclusion that the O2 excessively absorbed in the recovery period goes to the oxidation of a part (approximately 1/5-1/6) of the lactic acid; the other, larger part of it, as was discussed above, is resynthesized again into hexosephosphoric acid. The CO2 formed as a result of the oxidation of lactic acid is not completely excreted with exhaled air, but enters into a compound with that alkali of the blood which has just been freed from lactic acid. Consequently, during work, lactic acid, entering the blood in excess, binds part of the alkali and thereby forces a greater amount of CO2 to leave with exhaled air than is formed at any given moment. Conversely, in the recovery period, the disappearance of lactic acid from the blood due to its oxidation and resynthesis leads to a smaller excretion of CO2 into the air ("retained" carbon dioxide). All this, of course, affects the fluctuations of the respiratory quotient. The release of lactic acid into the blood during heavy muscular work is of enormous importance, and without this, a person could not perform any significant muscular work at all. For every organism, there is a certain limit for oxygen absorption; if the work is light, then the "oxygen requirement" (according to Hill's terminology) is below this limit, and the organism easily copes with the work. The same approximately happens if the requirement is very close to the limit. In the third case, however, when the oxygen requirement exceeds this limit, the "oxygen intake" proves to be insufficient, and a certain "oxygen debt" is formed, which is repaid with the help of the release of lactic acid into the blood only during the recovery period. After heavy work, as is known, oxygen absorption remains elevated for a long time. The changes occurring in the organism during muscular work have been studied very little, but even what is known now allows us to think about the significant participation of the endocrine system and both components of the autonomic nervous system. Experiments point to an increased-above-normal influx of adrenaline into the blood during muscular work and to an increase in the percentage of sugar content in the blood.
It has not been possible to establish a direct correlation between the power of work and the amount of sugar in the blood. By examining urine, an increase in the excretion of various nitrogen- and phosphorus-containing chemical substances was established, but, of course, all this is clearly insufficient to clearly visualize the course of intermediate metabolism in relation to even the main substances (proteins, carbohydrates, and fats) during and after muscular work. Physiologists are accustomed to that amazing coordination which manifests itself in the human body at rest; during work, however, especially in a trained person, the coordination of the activities of various body systems reaches a very high degree of perfection thanks to the activity of a number of coordination mechanisms. Coordination is carried out with the help of the cerebral and autonomic nervous systems and the accessory apparatuses of the latter (the endocrine system). One can rightfully say that the organism as a whole appears with particular vividness precisely when performing complex and difficult muscular work.
K. Kekcheev. Basic mechanical phenomena in muscles, methods of their registration and imaging. The basic mechanical property observed in a muscle is the variability of its length, which represents the basis of all its motor properties. Upon closer examination of this phenomenon, it turns out that the length of a muscle changes as a result of very numerous and diverse causes of both a purely physical and physiological nature. These causes and their effects have not yet been reduced to any coherent theory, and muscle mechanics continues to be the subject of numerous experimental investigations. Changes in muscle length are studied mostly in frog muscles (usually m. sartorius or m. gastrocnemius), which, depending on the experimental setup, are either completely isolated, or dissected together with the n. ischiadicus, or finally preserved in situ, with only the distal end being dissected and connected to a recording device. The recording of changes in muscle length is usually carried out using a myograph, which is a stand with two hooks or clamps to which the ends of the muscle being studied are attached. One of the hooks is fixed, while the other is connected in one way or another
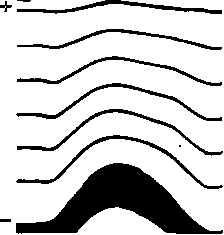
Figure 1. Photomyogram of a single muscle twitch of a frog muscle (Bethe and Happel). The signs + and - denote the points of application of the electrodes. The upper broken line is the moment of stimulation. In the image, it is clearly visible that the excitation of the muscle (the increase in elastic properties) begins at the lower end of the muscle, near the cathode: the lower segments begin to contract first and pull the upper segments toward them, temporarily stretching them.
with a pen writing on a smoked drum (kymograph). In some varieties of the myograph (Schenck, Blix, Kries), both ends of the muscle are connected to movable recording devices. A. Bethe used an extremely subtle method of optical recording for the analysis of changes in muscle length, which is interesting in that it registers not only the total length of the entire muscle but also the changes in the lengths of individual successive segments of the muscle. Bethe places the muscle, divided along its length into a number of segments by attached black silk threads, in the focal plane of a projection apparatus and casts its translucent image onto the slit of a photokymograph, in which the displacements of each of the silk threads are depicted in the form of curves (Fig. 1). Along with changes in length, a muscle is also capable of undergoing changes in tension, i.e., the force tending to bring its ends together. Since there is no action without reaction, the tension of a muscle not loaded with any stretching force is always equal to zero, whatever its physiological state may be. Tension arises in a muscle only in the presence of a stretching force (while a change in length may not require any external force) and is always determined in magnitude by the magnitude of this external force, although the cause of the tension's emergence may have nothing in common with the given force. Muscle tension is measured by the most diverse dynamometers (see Dynamometry). As a dynamometer for frog muscle, modifications of the myograph are used. In cases where one wants to register changes in muscle tension at a constant length (isometric processes in muscle, see below), it is fixed between two almost immobile clamps, one of which is connected to a low-compliance dynamometric spring and a recording pen. If it is desired to record both changes in length and changes in muscle tension simultaneously, it is loaded at the movable end either 1) with a weight or a lever with a large moment of inertia, with tensions being calculated from the acceleration imparted to the muscle by these attachments, or 2) with a compliant spring (auxotonic process, see below), the resistance of which is accounted for by the degree of stretching it has undergone, or finally 3) with a significant weight that the muscle can lift only relatively slowly, so that the weight acts on it mainly by its mass, and not by inertia (isotonic process, see below). In addition to changes in length and tension, a muscle also undergoes changes in cross-section and transverse hardness. The cross-section of a muscle increases when it shortens and decreases when it lengthens, since the volume of the muscle does not change during these processes. Transverse hardness changes in parallel with the change in the longitudinal tension of the muscle. Indeed, if a muscle overcomes an external stretching force, this means that it tends to shorten with an equal and opposite force. Meanwhile, simultaneous transverse compression by another external force reduces its cross-section, i.e., tends to lengthen the muscle; consequently, such compression meets with resistance in the muscle's tension. Both these phenomena are thus derivative, secondary manifestations of both basic processes and therefore present
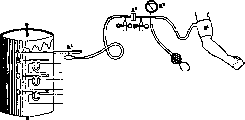
Figure 2. Diagram of the Brugsch myographic setup: a1 - air cuff on a human arm; a2 - manometer; a3 - chamber with an elastic partition for equalizing pressures; a4 - Marey capsule; A - recording pen; B, C, D - electromagnetic markers.
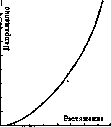
little theoretical interest; however, since a muscle in an intact organism is much more accessible to transverse influences than to longitudinal ones, both mentioned phenomena are widely used to assess the state of muscles in humans. The registration of transverse expansions of muscles, which should testify to their contractions, was carried out on humans by Brugsch and Johnen and applied by them to the study of labor processes; the diagram of the Brugsch setup is given in Fig. 2. The registration of transverse hardness (sclerometry) has found wide application for an approximate assessment of longitudinal muscle tension in humans (Noyons, Uexküll, Exner and Tandler, Mangold) and boils down to measuring the depth to which a weight placed on the muscle (more precisely, on the skin above it) sinks into it. This static sclerometry has in the present time given way to a more perfect dynamic (ballistic) one, which measures the elastic recoil exerted by the muscle on a hammer striking it (Noyons, Gildemeister, Bethe, Steinhausen, Richter). The hammer is suspended like a pendulum and strikes with a perfectly defined force on a plate applied to the skin over the muscle, with the duration of its contact with the plate being measured. The two main variables of muscle mechanics—length and tension—are connected by a close internal dependence. If one studies both these variables in parallel on an unexcited (resting) muscle, it will turn out that the muscle's tension increases with an increase in its length (stretching) and falls with the shortening of the muscle. The dependence between both variables can be depicted graphically in the form of a so-called length-tension diagram (Längen-Spannungsdiagramm, L.-T. diagram) (see, for example, Fig. 3). A more careful study of the L.-T. diagram of passive stretching of a resting muscle shows that even in this particular case, the dependence between both quantities is not constant: the L.-T. diagram changes depending on the speed of stretching and on the biochemical state (e.g., the degree of fatigue) of the muscle, and on whether it is recorded during gradual stretching or, conversely, during gradual shortening of the muscle. The point of intersection of the L.-T. diagram curve with the abscissa axis obviously depicts the state of the muscle in which its tension is equal to zero, i.e., the state into which the muscle comes when no external forces act on it. The length of the muscle in this state is designated as the resting length (Ruhelänge), or the natural length of the muscle. Both these names are not entirely successful, since the rest of a muscle is usually contrasted with its excitation, and contrasting the same word with tension can lead to errors; as for natural length, there is no reason to speak of it once we cannot recognize other lengths of the muscle as unnatural. It would be most correct to call this length the unstressed, or free, length of the muscle. The dependence between length and tension is even more complex and peculiar if one turns to its study in a muscle excited to one degree or another. Here there is such a chaotic variety of experimental material that to sort out
it is
It is currently impossible to determine the length-tension relationship of a muscle with sufficient certainty. (See below for the basic theoretical premises for the analysis of these facts.) Measurement of the dependence between the length and tension of a muscle can be performed both on an excised muscle and on a living subject (a human). On a frog muscle, such a measurement is feasible in two ways. The first method, introduced by Weber and used by Marey, Haycraft, Wertheim, Christen, and others, consists of the gradual loading or unloading of a resting or tetanized muscle with weights, whereby the tip of the muscle, connected to a writing stylus, records on a kymograph the changes in its length caused by various loads (i.e., tensions). The curves obtained by these methods have been subjected to theoretical analysis more than once, but these analytical attempts have not yet led to consistent results. In any case, it can be considered a fact that the length-tension diagram of passive stretching is undoubtedly not a straight line, i.e., that there is no proportionality between the increase in length and the increase in tension, which is characteristic within wide limits of unorganized elastic bodies and is known as Hooke's law. As can be seen from Figure 3, the length-tension diagram is a curved line (Wertheim incorrectly assumed it to be a hyperbola), which, with an increase in muscle length, goes ever more steeply upward. This means that the more strongly the muscle is stretched, the more strongly it resists further stretching. If an increase in load of 1 g is sufficient to lengthen a muscle by 1 mm, then to lengthen it by another 1 mm, a further increase in load of not 1, but 1.2 or 1.5 g will be required. True, these experiments on an isolated muscle are performed within much wider limits of stretching than is feasible in a living organism, and it is certain that in this latter case, the deviations of the muscle from Hooke's law during passive stretching are small. Experiments allowing for the obtaining of a length-tension diagram of a muscle are also feasible on a living human. Spiegel balanced the lower leg of the raised leg of a person lying on their back using a lever with weights, and by then hanging weights on the lower leg itself, he caused passive flexion of the knee and, consequently, stretching of the m. quadriceps femoris, the tension of which was evaluated by the weight of the suspended weights. By this method, it was possible to bring the tension of the muscle under study up to 8-9 kg. Vereshchagin used a similar setup but much more successfully chose as the test muscles the group of posterior thigh muscles (mm. biceps femoris, semitendinosus, and semimembranosus), taking advantage of the fact that these muscles, crossing two joints at once, can be passively stretched with a flexed hip joint to incomparably greater values: up to 115% of the initial length (taken as 100%) and up to 70-80 kg of tension. The setup of this author is shown in Figure 4a. The setups of Spiegel and Vereshchagin were applied by the authors to the study of muscle tone (see Tone)—a phenomenon understood very differently by various researchers, but in recent times increasingly identified with the elastic state of an unexcited muscle, i.e., with a syndrome characterized precisely by the length-tension diagram of the longitudinal extensibility of the muscle. It is necessary to emphasize that the similarity between the length-tension diagram of a living tonized muscle (Fig. 4b) and the same diagram of an isolated muscle (Fig. 6) should not be understood in the sense of complete identity. An isolated muscle does not experience any nervous influences, while in the whole organism, the muscle is continuously under the influence of the central and autonomic nervous system, and its length-tension diagram reflects a synthesis of local (purely muscular) and central phenomena. Among such central, tonic phenomena is, for example, the hump of initial inhibition (Bremsung) in Fig. 4b, which is absent in an isolated muscle. The methods of both authors have found wide application in clinical neurology, allowing for a reliable quantitative assessment of pathological muscle tone. The second method for the quantitative determination of the elastic properties of a muscle, applied so far only to the frog muscle, was developed by Bethe, Steinhausen, and Richter and is based on the aforementioned ballistic principle. In Richter's ballistic elastometer (Fig. 5), the muscle is attached at one end to a stationary clamp and at the other to the hook of pendulum B, which is struck by hammer A. The blow of the hammer deflects the pendulum and thereby suddenly stretches the muscle; following this, the hammer flies back, and the pendulum, pulled by the stretched muscle, performs one or two swings and then comes to rest. The duration of the first swing, as Steinhausen showed, stands in a very simple dependence on the measure of elasticity (the so-called modulus of elasticity) of the muscle; the difference between the duration of the first deflection of the pendulum and the duration of its return is just as closely related to the internal friction of the muscle, or muscle viscosity (see below). The advantage of the ballistic method over the method of gradual loading is that with sudden, jerky stretching of the muscle, the influence of the previous long-term stretched state, which very noticeably changes the character of the length-tension diagram, is excluded. Theoretical premises for muscle mechanics. Any body that produces a length-tension diagram in which (as can be seen in Fig. 3) an increase in length is accompanied by an increase in tension is classified by mechanics as a longitudinally elastic body. A muscle is a longitudinally elastic body, although, as indicated above, it is not subject to Hooke's law of proportionality. The degree of elasticity of a body is usually characterized by the modulus of elasticity, or Hooke's modulus. The modulus of elasticity is the ratio of the increase in tension per unit of cross-section (in kg per cm2 of the body's cross-section) to the relative increase in length accompanying this tension. If a muscle, stretched by 1/10 of its initial (unstressed) length, exhibits a longitudinal tension of 0.8 kg per cm2, then the modulus of elasticity (more precisely, the average value of the modulus) of this muscle is equal to 0.8 : 1/10 = 8 kg/cm2. As indicated above, this ratio, which determines the modulus of elasticity, is not the same for different stretches of the muscle; the more the muscle is stretched, the higher the value of the modulus. Therefore, the modulus of elasticity of a muscle cannot be expressed by a single number, as is possible, for example, for steel or rubber. At best, one can speak of an average value of the modulus, but even for this value, due to a multitude of extraneous factors, different authors have obtained figures that agree very poorly with each other. Wundt gives values for the muscle of an adult human from 35 to 86 kg/cm2, for the m. sterno-cleido-mast. of a dog—142 kg/cm2, for a frog muscle—9.4 kg/cm2. Richter, using the ballistic method, found values for the m. sartorius of a frog from 5.2 to 9.4 kg/cm2. Measurements of the tone of human muscles, performed by Vereshchagin, give figures approaching those of Richter—10-12 kg/cm2. Stretching a muscle requires the expenditure of work not only to overcome the rapidly increasing tension but also to overcome the internal friction in the muscle substance. The work expended on overcoming tension is returned by the muscle upon its shortening (just as the spring of a clockwork mechanism returns the work spent on its winding) and is therefore called the reversible part of the work, while the expenditures on overcoming friction irreversibly turn into heat. The internal friction of a muscle, or muscle viscosity, depends on the speed of stretching or shortening of the muscle: the faster the length of the muscle changes, the more significant the friction. Experiments on determining the coefficient of muscle viscosity (Steinhausen, Richter), i.e., the ratio between the speed of stretching and the force of frictional resistance, have not yet led to reliable results.
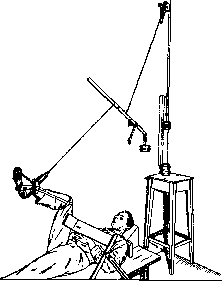
Figure 4a. Vereshchagin's setup for measuring muscle tone.
Figure 4b. Length-tension diagram of a human tonized muscle according to Vereshchagin.
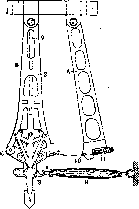
* Very recently (1931), a very valuable interpretation of the indicated curve was given, considering it as an exponential function of the form l=lm~ he-aj>.
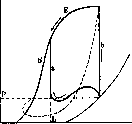
Figure 5. Richter's ballistic elastometer: A—hammer; B—pendulum; M—muscle; S—writing pen. The hammer strikes plate v against plate l. Muscle viscosity significantly affects the Length-Tension diagram of the muscle. Let line I (Figure 6) be the Length-Tension diagram of a very slow stretching of the muscle, at which the resistance of viscosity is negligible. Then, when stretching the same muscle at a noticeable speed, the Length-Tension diagram will follow line II, and during the reverse elastic contraction, the muscle will return to zero along line III. Indeed, if static stretching of the muscle to magnitude A corresponds to a static tension Aa, then when stretching the muscle to the same magnitude at a noticeable speed, we will experience 1) the same static resistance Aa and 2) friction resistance ab, or in total a resistance Ab, greater than Aa. During the reverse contraction of the muscle, internal friction will resist the shortening of the muscle and thereby weaken its force; therefore, passing through length A during contraction, the muscle will exhibit a tension which will be less than the static tension Aa by the magnitude ac, i.e., it will be equal to Ac. From the nature of the Length-Tension diagram, it follows that the area of the figure bounded by curves II and III depicts, on the scale of the drawing, the irreversible work spent on overcoming internal friction during the forward and reverse stroke of the muscle; all the work spent on stretching the muscle will be depicted by the area between curve II, the abscissa axis, and the extreme ordinate Bd, and the reversible part of the work (returned by the muscle during contraction)—by the area between curve III, the abscissa axis, and the ordinate Bd. The work of the muscle, like that of any elastic body, is performed in the form of two successive phases. In the 1st phase, the accumulation of potential energy by the muscle takes place, in the second—the conversion of the latter into mechanical work. The sources of energy for the first phase can be different: elastic potential energy can accumulate in the muscle both at the expense of preceding passive stretching and at the expense of an internal chemodynamic process occurring during the excitation of the muscle and releasing a certain portion of mechanical energy. Conversely, the source of energy for the second phase is in all cases one and the same—the elastic potential energy of the muscle. In other words, under identical external conditions, the course of muscle contraction will be completely identical, whatever the sources that charged the muscle with energy in the first phase; the observed enormous variety of forms of this course is determined exclusively by the variety of external conditions accompanying the activity of the muscle (see below). Between an unexcited muscle, charged with energy at the expense of preliminary passive stretching, and a muscle that is excited, having received a charge of energy via a chemodynamic path, there is, however, a significant quantitative difference. Both the unexcited and excited muscle are elastic bodies, quite similar in their mechanical properties; however, the quantitative characteristics of the elastic properties of both these states of the muscle are different: 1) the free, or unstressed, length of the muscle decreases upon excitation. If one immerses a non-loaded frog muscle in a Ringer-Locke solution to free it from the influence of its own weight, and through a nerve subjects it to tetanization, it will shorten. 2) The modulus of elasticity increases upon excitation. As in the unexcited muscle, it is different at different degrees of muscle stretching, so that in this case too, the Length-Tension diagram has the form of a curve, but unlike the resting muscle, this curve bends upwards only to a certain limit, after which it begins to go more and more gently. The Length-Tension diagrams of the excited (I) and resting (II) muscle are depicted semi-schematically in Fig. 7. The free length of the excited muscle is depicted by point A, that of the resting one—by point a. Up to point B, the steepness of curve I (i.e., the modulus of elasticity of the excited muscle) increases, then begins to fall. At point C, it already equals the steepness (c) of curve II, and at point D (the existence of this latter cannot be considered strictly proven) it becomes zero, i.e., the excited muscle, having been stretched to length D, loses its elastic properties. Figure 6.
Figure 7. Figure 6. Length-Tension diagram of passive stretching and reverse shortening of an isolated muscle. Figure 7. Length-Tension diagram of an excited (I) and unexcited (II) muscle: A—free length of the excited; a—the same of the unexcited muscle. To this day, a heated discussion is being conducted between the defenders and opponents of the "all-or-nothing" law (see) about whether the transition of the elastic properties of the muscle from state II to state I occurs suddenly (by a jump) or gradually, in other words, whether intermediate states like curve III (Fig. 7) take place, even if only for a very short time each time. This dispute has not yet received an experimental solution, although indirectly many facts speak in favor of a jump-like change. It should be noted that only experiments on a microscopically small section of a single fiber can be decisive in this dispute. If one observes a whole multi-fiber muscle along its entire length, then even if the change of states of each of the fibers occurs suddenly, it will inevitably be masked by the non-simultaneity of the entry of individual fibers, as well as by the fact that both the excitation wave and the elastic wave propagate along the muscle not instantaneously. During tetanization of the muscle, each new stimulus of excitation transfers the muscle from state II to state I, following which, together with the fall of the action current wave, the muscle obviously immediately returns to state II. Thus, at a tetanization frequency of 50 impulses per second, the muscle changes the elastic state II to I and back as many times per second. The fact that the length of the muscle does not manage to change as many times per second (at least in a way noticeable to the eye) is explained exclusively by the internal friction of the muscle, its viscosity, which does not allow the length of the muscle to change at the required speed and thus is an extremely useful property for the feasibility of tetanus. In Fig. 8, it is very clearly visible how tetanization of the same frequency acts on a muscle with high viscosity (above) and with low viscosity (below). The curves of changes in length and tension during tetanus (Length-Tension diagrams) for both cases of Fig. 8 are given schematically in Fig. 9 next to the main curves of passive stretching I and II; a—tetanus of a viscous muscle; the area of the oval—work of one impulse; b—tremor of a less viscous muscle; the area of the oval—work of lifting and lowering the load. The influence of external conditions on muscle contraction. Relying on the main Length-Tension diagram of Fig. 7, one can trace with great clarity the features of the course of muscle contraction under diverse conditions. Graphic
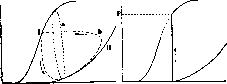
Figure 9.
Figure 10. Figure 9. Length-Tension diagrams of incomplete tetanus of a viscous muscle (a) and a less viscous one (b). Cf. with Fig. 8. Figure 10. Length-Tension diagram of isometric tension of a muscle. The graphic representation of all these processes in the form of Length-Tension diagrams represents the best way to sort out, at least in the most general terms, the chaotic abundance of experiments conducted on muscle contraction.—Figure 10 depicts the isometric tension of the muscle (the phrase "isometric contraction" obviously makes no sense). In the unexcited state, the tension is equal to zero; in the excited state, it reaches the magnitude P. Various cases of auxotonic contractions, i.e., those in which tension increases as the muscle contracts (for example, when a muscle stretches a spring), are presented in Fig. 11. Line a depicts a strictly auxotonic (ideal) case; line b—a case of auxotonic contraction of a muscle possessing high viscosity. Since the increase in the static tension of the spring in this case also follows line a, the excess of b over a is obviously quite analogous to the excess of II over I (Fig. 6), and the area between b and a depicts the work of overcoming the internal friction of the muscle.—Cases of isotonic contractions are depicted in Fig. 12. Curve a—slow (almost strictly isotonic) lifting of a heavy load P; b—faster lifting of a medium load Q. From the figure, it is clear that this lifting is "isotonic" only in name. At the beginning of the lifting, the muscle has to overcome 1) the weight of the load Q=lm, 2) its inertia st, proportional to the acceleration, and 3) its own internal friction rs, depending on the speed of contraction. Additives (2) and (3) raise the initial tensi
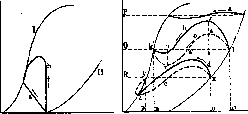
Figure 11.
Figure 12. Figure 11. L.-T. diagrams of auxotonic muscle tensions. Figure 12. L.-T. diagrams of so-called isotonic muscle contractions. The tension of the M. by the amount rt above the tension sufficient for statically supporting the load Q. By the end of the lift, the movement of the load upward slows down, and it pulls on the M. with a force that is less than its own weight by the amount uv. In connection with this, despite the friction and the general tension of the muscle, b decreases. The useful work expended on the lift is measured by the rectangle mlkn or the area mlswvkn, which is equal to it; the expenditure on internal friction is determined by the area Irkvwsl. Curve c depicts the changes in the inertial resistance of the load Q. Curve d in Fig. 12 corresponds to the case of throwing the load R, which, during the rapid contraction of the M., flies past the equilibrium position and then performs one or two damped oscillations around this position. The useful work of the lift is the rectangle oxur, the work of friction is the area between the solid curve d and the dashed curve e. Figure 13 characterizes contractions in which a previously supported load can be lifted only when the excited M. has already developed a tension equal to its weight. These contractions proceed at first, obviously, strictly isometrically, and then according to the type of curves in Fig. 12. Line a—lifting of load P, the viscosity of the M. is high; b—lifting of a larger load Q, the viscosity is low (throwing); c—an impossible load R (isometric tension). In Fig. 14
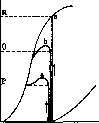
Author Henke and Knorz Hermann Rosenthal Franke. . Beck . . . Rosenthal Camarero Figure 13.
Figure 14. Figure 13. L.-T. diagrams of muscle contractions with a previously supported load. Figure 14. L.-T. diagrams: a—contraction with impact; b—contraction with initial delay. Shown are a—contraction with impact (Anschlagszuckung), in which a lightly loaded muscle contracts first to a certain length L, at which it hits an obstacle that forces it to further tense isometrically (Schenck, B. I.); b—contraction with initial delay (Anfangshemmung): the M. is held until the full development of tension, and then released into flight with load P. The area between part b' of this curve and the dashed curve is the expenditure on friction. Experiments of this type were performed by A. Fick. M. as an organ and as an element of the bone-muscular skeleton. Individual working elements of the skeletal M. are of the same type and obey the same laws in any M., but a whole M. is not a simple bundle of fibrils: it is an organ in which the arrangement, connection, and cumulative effect of the action of the fibrils can be very diverse depending on the function that the given M. has to perform. Since the modulus of elasticity determines the relationship between tensions and relative stretches of the M., it is obvious that with given elastic properties, the absolute excursion of the end of the M. will be greater the longer its fibers are. On the other hand, again, with given elastic properties, the total tension of the muscle must change in proportion to the cross-section (the number of fibers working in parallel). Thus, the excursions of the end of the M. are proportional to its length, and the tensions are proportional to the cross-section. Consequently, the work of the M., measured by the product of tension and the distance traveled, is proportional to the product of the cross-section of the M. and its length, i.e., the volume of the M. or the amount of contractile substance contained in it. Figure 15 depicts schematically two fully equivalent M. of different shapes. Both these M. have the same volume, consequently—the same power, and furthermore, the moment of their action on the joint is the same, since the three times stronger M. is applied to a three times shorter lever arm. As an attempt to estimate the force of the M. per unit of cross-section, one should mention the experiments on the so-called absolute force of the M. According to Franke, the absolute force of the M. is the greatest tension per 1 cm2 of cross-section that the M. can develop due to tetanus under the most favorable conditions (i.e., at length B, Fig. 7). The imperfection of the methods and a certain vagueness of the definition led to not very consistent results among different authors (for the main data, see the table). One and the same total work (determined, as stated, by the volume, and not the shape of the muscle) can, however, be performed in different ways: either as overcoming a small force over a long path or, conversely, as movement against a larger force over a short path. M. with long fibers, usually spindle-shaped (e.g., m. biceps br.) or fan-shaped (e.g., m. temporalis), are adapted to the first type of work; to the second type—short-fibered M. with a large cross-section: parallel-fibered (e.g., m. rhomboideus) or pinnate (e.g., m. rectus femoris). Figure 16 shows very clearly that the work performed by a pinnate M. (lifting a large load to a small height) and a spindle-shaped one equivalent to it (lifting a small load to a large height) is the same. Indeed, if the weight of the pinnate M. consisted of two parts A and B, then the work of lifting the entire weight to the dashed position would not differ from the work of lifting only piece B and placing it on the upper side of part A, which remained in its former place, and this is exactly what the second muscle does. The mentioned various basic forms of "cut" of the M. are found in the organism in infinitely diverse combinations and variations (see Muscular system). Here one should turn to the general typical conditions of the work of the M. in the skeletal system. In the overwhelming majority of cases, the M. of the skeleton have to perform the rotation of one skeletal part relative to another. Therefore, as in the mechanics of any rotation in general, the action of the M. has to be characterized not by its tension itself, but by the so-called moment of tension relative to the axis of the joint it serves. The moment of tension is measured as the product of the longitudinal tension F (Fig. 17) and the lever arm of its action, i.e., the length of the perpendicular R dropped from the center of the joint to the longitudinal axis of the M. With a complex shape of the M. and diverse directions of its fibers, one has to take the resultant of the tensions of all its parts as the tension of the M., and the line of action of this resultant as the longitudinal axis of the M. From Fig. 17, it is easy to see that with different positions of the links, the moment of the M. can turn out to be different even with one and the same longitudinal tension F, because the length of the lever arm R changes due to the displacement of the links. Usually, the greatest value of the arm R corresponds approximately to a right angle between the links, and in this position, the M. can develop the greatest moment (and not the "greatest force," as is usually said).
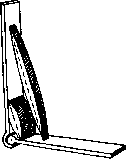
Figure 15. Scheme of two equal-power muscles with the same moments, with different shapes and arrangements.
Muscle Triceps surae Flexores brachii Triceps surae Mm. masticatorii Biceps brachii Brachialis int. Triceps brachii Object of study Abs. force in kg/cm2 Human 5.9 » 8.1 » 6.2 » 10.0 » 11.4 » 12.1 » 16.8 Frog 1.8 » 2.8 Crustacea (crustaceans) 1.8-3.2 Coleoptera (beetles) 3.4-6.9 Lamellibranch. (bivalves) 12.4
The law of equality of action and reaction also extends to moments. According to this law, the moment of action of a muscle on link B (Fig. 17) is equal and opposite to the moment of its action on link A. Therefore, the tension of one muscle cannot yet determine which of the links will begin to move upon its tension: for A to move, it is necessary to fix B, and vice versa (by an external force or by some other muscle); otherwise, both links will move towards each other. It is very important to understand this for the case of a muscle overcoming external forces. Let a load P be placed on the hand, with the forearm horizontal (Fig. 18), which must be held. The moments of two external forces act on the elbow joint: the moment of the load + PR and the moment of the weight of the forearm itself with the hand + pr. For equilibrium, the moment of the muscle (elbow flexor) must be equal and opposite to their sum, +(PR+pr). But since, according to what was said above, the moment of a muscle is bilateral, it will not only support the loaded forearm with a moment -(PR+pr), which is directly expedient, but will also pull the shoulder forward in the direction of flexion with the same moment +(PR+pr). This is not only unnecessary, but also harmful, since for maintaining equilibrium the shoulder must be motionless, but this muscle is powerless to help the matter in any way. To hold the shoulder, it is necessary to apply to it from the outside the same moment -(PR+pr); this has to be done by the muscular system of the scapula and the shoulder girdle. But the action of these latter muscles is again bilateral and in turn needs external support; furthermore, besides the moment PR+pr, originating from the forearm and hand with the load, the weight moment of the shoulder p'r' also acts on them, and for the equilibrium of the entire system, a moment -(PR + pr + p'r') must act on these muscles from the outside. Reasoning in this way, it is easy to be convinced that when holding a load on the hand, not only the muscles closest to it are tensed, but also a multitude of muscles throughout the body—from the place of application of the external force of the load and up to the nearest external point of support (for example, the resting of the feet on the ground). The same thing and in the same order is observed during movement, when muscles overcome not the static force of gravity, but dynamic forces (friction, inertia, etc.). In this case, in all instances, the moments of the muscles increase from the periphery to the center due to the imposition of ever new additional external moments p'r', p''r'', etc. We present some figures representing the moments of muscles of different joints during some simplest processes, taking the moment of the wrist muscle as a unit (Bernstein, Popova). Moment Processes in wrist in elbow in shoulder joint 22.0 16.7 7.6 9.3 Holding a horizontally extended arm . . . Holding arm, semi-flexed . . . Piano strike . . . Postal stamping . . . 1 1 1 6.8 6.7 4.6 5.4 The table shows that during wrist movements (piano strike, stamping) the relative role of the wrist muscle increases, but still far yields to the load of distant muscles, having
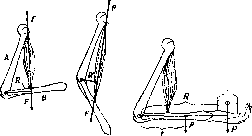
Figure 17.
Figure 18. Figure 17. Moment of a muscle at various positions of the joint. Figure 18. Moments of external forces (weight of the forearm with the hand and the load) acting on the flexors of the elbow. no direct relation to the given movement. The application of the law of action and reaction just described is also used for measuring muscle moments in humans (Bernstein). For this, the sum of the moments of all external forces is measured on one side of the joint being studied. According to what has been said, the resultant of the moments of all muscles of this joint must be equal and opposite to the measured sum of external moments.
N. Bernstein. Electrical phenomena in Muscles. Processes occurring in a Muscle in the conditions of its active state are accompanied by electrical phenomena, as was firmly established by Matteucci and du Bois-Reymond (see Bioelectric currents, Animal electricity). Electrical currents arising in a Muscle during its contraction have received the name of action currents, in contrast to the resting current appearing in a resting Muscle when its damaged part is connected through a galvanometer with its unchanged points (see Animal electricity). As is known, the action currents arising during tetanic contraction are so strong that with their help one can irritate a second muscle if its motor nerve is placed on the first. This phenomenon has received the name of secondary contraction. When a capillary electrometer and a string galvanometer were applied for the investigation of electrical phenomena in a Muscle, it was possible to show that during a single contraction, a single electrical oscillation takes place corresponding to the emergence of a single wave of excitation, e.g., under conditions of irritation of the nerve of a given muscle by a single make or break induction shock. The photographic images obtained during this, or so-called electrograms, give the possibility to approach more closely the study of single electrical oscillations in a Muscle. The electrical process during a single impulse has a wave-like course. The descending part of the electrical oscillation is somewhat more stretched in comparison with the ascending part. The length of the electrical wave is less than the contractile wave and changes under the influence of temperature. As for the latent period of the electrical effect following the application of irritation, it passes very quickly. Some authors consider it equal to zero. It is easier to reveal the latent period during the cooling of muscles. In the isometric regime of a muscle, a steeper fall of the electrical curve is observed than in the isotonic one. In the opinion of Samoylov, contraction in the isotonic regime produces an inhibitory influence on the magnitude of the electrical oscillation. Further, it was found that the height of the electrical oscillation increases up to known limits corresponding to the loading of the Muscle with a weight. During tetanus, although the mechanical effect of contraction is continuous, nevertheless, a telephone and a string galvanometer can easily detect the intermittent nature of this contraction. Namely, corresponding to the frequency of impulses arriving in the muscle and causing tetanic contraction, in a telephone connected by means of special electrodes to the muscle, we have a corresponding number of membrane oscillations. In connection with this, Vvedensky established the concept of lability, by which he understood the ability of a Muscle to give a certain number of electrical oscillations (action currents) per unit of time at a known rhythm of irritation. Exciting a Muscle from a nerve with an intermittent current with a period of 100 per second, Vvedensky established that the muscle gives 100 electrical oscillations only for a short time, and then it begins to transform the impulses arriving in it to a smaller number. Corresponding to this, instead of a given tone from 100 irritations per second (in the tuning fork-current interrupter circuit), we begin to hear a lower tone in the telephone. At a comparatively higher frequency of irritation, almost immediately in the telephone one gets not a musical tone, but a noise, replaced by a rumble, which depends on the annulment by the muscle through transformation (in the physiological sense) of a whole series of impulses arriving from the nerve. Partial blocking of excitation waves occurs, according to Vvedensky, in the myoneural transmission, in the endings of the motor nerve. Undoubtedly, the amplitude and frequency of electrical oscillations in a muscle change together with a change in the lability of the muscle or, which is the same, together with an increase or decrease in the speed of processes occurring in a Muscle. Since as fatigue increases, the lability of the muscle falls, then at the same time the ability of the muscle to reproduce this or that frequency of irritation in the form of electrical oscillations also falls. The data obtained by Vvedensky with the help of a telephone then received brilliant confirmation during work with a string galvanometer, which gives the possibility to photograph action currents. The ability of a muscle to transform indicates the revelation of the muscle's own rhythm. The latter is easy to detect during irritation of a muscle with a constant current. An electrogram shows a series of electrical oscillations in a muscle in response to the passage of current through it. In the muscle of a turtle, the own rhythm of excitation is slower than in a frog. In a turtle, it is easy to observe at this rhythm the so-called absolute refractoriness, falling on the ascending part of the electrical curve, and a relative refractory stage during its descending part. As was to be expected, in the muscles of warm-blooded animals, the own rhythm is faster in comparison with cold-blooded ones. The study of action currents of skeletal musculature during voluntary movement has received great importance. It sheds light on the rhythm of the central nervous system and in any case gives the possibility to penetrate more deeply into the activity of the centers. The main complicating moments here are the above-noted processes of transformation during the transmission of impulses from one physiological apparatus to another and the difference in lability. From Vvedensky's data, it is known that the nerve possesses the highest lability, or the ability to reproduce the rhythm of irritation; it is followed by the muscle. As for the centers and the endings of the motor nerve, they show a known similarity between themselves in their lability and stand lower than the nerve and muscle. This means that the phenomena of transformation, the remaking of the rhythm for passing impulses, can most likely take place in the centers and in myoneural transmissions. The law of relative lability, established by Vvedensky during work with a telephone, can have a guiding significance in the study of the rhythm of the most diverse physiological apparatuses, up to and including the rhythm of the centers. Further, it should be kept in mind that proprioceptive nerves must also exert their influence on the electrogram. Upon their exclusion, a lower frequency of electrical oscillations and greater regularity in their succession are usually observed in muscles. The study of action currents of a muscle during voluntary contraction showed that voluntary contraction gives intermittent action currents of different periodicity, which is explained by the fact that "during voluntary contraction, muscle fibers receive impulses not simultaneously, but some earlier, others later, as if the nerve centers are firing at random." Such is the characteristic comparison of Brücke. Leading action currents from the human forearm to a string galvanometer during voluntary contraction, Piper found the main rhythm to be equal to 50 per second, with additional oscillations (Nebenzacken) being added to the main oscillations. Upon fatigue, the number of main waves decreases to 25-35 per second. Cobb and Forbes studied fatigue while working with an ergograph and observed a decrease in the number of main waves to 9-20 per second with an increase in their amplitude. The study of electrical phenomena during pathological states of the musculature showed the following. In Wilson's disease, a Muscle in a state of rigidity shows very insignificant action currents, which apparently do not stand in any relation to the intensity of the contraction. In Thomsen's disease, after the cessation of voluntary contraction, the muscle still remains in a state of tension for some time, with oscillating action currents being observed, as if voluntary innervation were still continuing. Weizsäcker, while studying ataxia in humans, found a known decrease in the frequency of electrical oscillations during voluntary movement in comparison with the norm. As for tonic contractions, in contrast to tetanus, they are apparently not accompanied by intermittent action currents. Thus, Wachholder, during the development of narcosis in cats, failed to observe action currents during tonus. Whether a prolonged negative oscillation takes place during tonus remains for now unclarified. Under conditions of maintaining tension in a human muscle, significantly smaller action currents are observed than during the most insignificant movement. With small tensions, the action currents are strikingly small. For the theory of electrical phenomena in a muscle, the question of in what relation the electrical phenomenon stands to the mechanical effect of contraction is of deep interest. It should be noted that this question has still not been resolved to this day. There are only the following data: when the action current of a muscle captured by a string galvanometer is registered photographically together with the curve of a single muscle contraction, then in rough experimental conditions, it is observed that the electrical effect precedes the muscle contraction and falls on its latent period. One could think that the electrical process is the result of preparatory chemical processes, which then cause the muscle contraction itself. However, registering the mechanical effect of contraction by an improved method, Einthoven found that the latter almost coincides with the beginning of the electrical one. On this basis, Einthoven believes that the action current is connected with the contractile process itself.
Later, Bishop and Gilson, using cathode rays and an oscilloscope, found that only the descending part of the electrical monophasic curve coincides with the mechanical effect of a single contraction. The authors believe that only this part of the curve is due to the contractile process itself, whereas its ascending part is caused by the wave of excitation. Since the magnitude of the action current does not always change in parallel with the contraction, Beritov believes that the electrical effect is caused by the emergence of other chemical substances, and not those upon which the contraction of the myofibrils directly depends. In connection with the issue raised, the electrical phenomena during poisoning of a muscle with veratrine are of particular interest. As is known, upon the action of this poison, a prolonged shortening of the muscle occurs following the usual contraction. At the same time, it is evident from the experiments of Garten that the prolonged contraction is accompanied by a prolonged action current. Under conditions of severe poisoning, indeed, no oscillatory currents are observed in the muscle. If the above data of Samoilov are compared with the data of Bishop and Gilson, it can be assumed that the contractile process is a kind of compensatory process aimed at restoring the disturbed equilibrium in the muscle cell. And thus, the electrical and contractile processes are in the closest connection with each other under normal conditions. N. Rezvyakov. III. Chemical statics and dynamics of Muscles. I. Chemical composition of Muscles. Striated and smooth Muscles differ in their composition, and these differences are more of a quantitative than a qualitative nature. The composition of striated Muscles has been better studied, while comparatively less attention has been paid to the chemistry of smooth musculature. Composition of striated Muscles. Muscles contain proteins, fats, carbohydrates, a number of extractive nitrogenous and non-nitrogenous substances, and inorganic substances. Protein substances. Striated Muscles contain several protein substances, to which various authors have given various names. These proteins take part in the process of coagulation of muscle plasma, which various authors have also explained differently. The proteins of Muscles and their participation in coagulation were ultimately most fully studied by Fürth, whose nomenclature is now the most widespread. Muscle plasma can be squeezed out with the help of a press from fresh Muscles just cut from an animal's body in the form of a yellowish liquid. This muscle plasma, like blood plasma, coagulates, with the muscle plasma of cold-blooded animals coagulating quickly, while the plasma of the muscles of warm-blooded animals coagulates slowly; after the coagulation of the plasma, muscle serum remains, which has an acidic reaction to litmus. The coagulation of muscle plasma depends on the transformations of two proteins contained in the plasma, named by Fürth myosin and myogen; they pass into insoluble protein substances myosin-fibrin and myogen-fibrin, of which the clot formed during the coagulation of muscle plasma consists. According to Fürth, during the coagulation of myogen, a soluble myogen-fibrin is first formed, which then turns into an insoluble myogen-fibrin; therefore, coagulation can be represented by the following scheme: Myogen Myosin
♦ ^ 4.
Soluble myogen-fibrin Myosin-fibrin
I. Insoluble myogen-fibrin. When juice is squeezed from dead muscles, muscle serum is obtained immediately. Myogen (myosinogen, myoprotein) does not precipitate upon dialysis of its solution in a solution of neutral salt. Myogen, especially in the presence of salts and with an increase in temperature, converts into soluble myogen-fibrin, and then into insoluble myogen-fibrin. Myogen is the main protein of muscle plasma (70-80% of all proteins). The plasma of frog and fish muscles contains a lot of soluble myogen-fibrin. Myosin is a typical globulin; it dissolves in solutions of neutral salts and precipitates upon dilution of its solutions with water. The usual method of obtaining myosin from dead muscles is extraction with a 5-10% solution of ammonium chloride and precipitation from the solution by diluting it with water. Muscle stroma. After removing all proteins soluble in water and in a solution of ammonium chloride, a residue remains—muscle stroma, consisting mainly of insoluble proteins, so-called myostromin. Fat is always contained in muscles, albeit in small quantities (about 1%). The fat content in some animals can reach up to 30% (eel). It also increases strongly during fatty degeneration of muscles. Of the phosphatides, lecithin is contained in muscles mainly. In heart muscles, there are more phosphatides (lecithin and cephalin) than in limb muscles. Cholesterol is also always present in muscles (from 0.03% to 0.23%). Phosphatides and cholesterol are part of the sarcoplasm. According to Embden, red muscles are richer in phosphatides and cholesterol, as well as sarcoplasm, than white muscles, which are capable of faster contractions but at the same time tire more quickly. Glycogen is the reserve carbohydrate of muscles. Its reserves are different and depend on a number of conditions, primarily on food and the physical work performed by the animals; with good nutrition and at rest, there is a lot of glycogen in muscles; during starvation or heavy muscle work, its content decreases sharply. In humans, muscles contain on average 0.4% glycogen. Lactacidogen (see) is an intermediate product of carbohydrate metabolism in muscles. Striated muscles, different in their function, contain different amounts of lactacidogen: white muscles contain more of it, red ones—less. Inositol (see) is contained in muscles in small quantities; its role has not been clarified. One of the intermediate products of the conversion of hexose, which splits off from lactacidogen, is lactic acid, which can be detected in muscles in greater or lesser quantities depending on its functional state. Extractive nitrogenous substances of muscles. Striated muscles contain various non-protein (extractive) nitrogenous substances; specifically, according to Fürth and Schwarz, in 100 g of muscle there is from 0.327 to 0.328 g of these extractive substances. Of this amount, ammonia accounts for 4.5-7%, purine substances—6.1-11.1%, creatine and creatinine—26.5-37.1%, carnosine fraction—30.3-36.3%, carnitine, methylguanidine and other similar bases—8.2-15.3%, urea, polypeptides, amino acids—8.3-16%. Creatine (see) is contained in various quantities in different muscles; limb muscles are richer in it than the heart. Furthermore, white limb muscles are richer in creatine than red muscles, e.g., m. biceps femoris of a rabbit is richer in creatine than m. semitendinosus (Table 1). Muscles of the same name in different animals (dogs, rabbits) are also different in creatine content. But if one takes muscles of the same name or groups of muscles of the same name from different individuals of the same species (e.g., different rabbits), then provided that both nutrition and all other living conditions are normal, the creatine content in them is distinguished by great constancy. Therefore, for example, various researchers, determining the creatine content in the muscles of the hind limb of rabbits, always found the same value—0.522%. The creatine content in muscles can increase under the influence of a whole series of causes, e.g., during starvation (at the beginning of it), during avitaminosis, after severe cooling, after poisoning with phosphorus, guanidine, after extirpation of the parathyroid glands, during tetany, during training, etc. The content of creatinephosphoric acid (see Creatine) increases in acute forms of polyneuritis, during training, during poisoning with phosphorus and tetrahydro-beta-naphthylamine, etc. Creatinine (see) is contained in muscles in very small quantities: e.g., in human muscles only 0.003-0.007%. Carnosine (see) is contained in the muscles of different animals in fairly large quantities, namely—from 0.05% to 0.3%. Regarding changes in the carnosine content in muscles under different conditions, there are only initial indicative indications, e.g., an indication of a decrease in content according to studies by the Ukrainian Biochemical Institute during starvation and an increase during training. Table 1. Content of total (i.e., free and bound) creatine, creatinephosphoric and hexosemonophosphoric acids in white and red muscles and in heart muscles (in percentages of fresh muscle substance). Rabbit: White muscles (m. biceps femoris)—creatine 0.526, creatinephosphoric acid 0.279, hexosemonophosphoric acid 0.420; Red muscles (m. semitendinosus)—creatine 0.261, creatinephosphoric acid 0.286, hexosemonophosphoric acid 0.235; Heart muscles—creatine 0.170, creatinephosphoric acid 0.134, hexosemonophosphoric acid 0.070. Rooster: White (pectoral)—creatine 0.084, creatinephosphoric acid 0.251, hexosemonophosphoric acid 0.235; Red (m. soleus)—creatine 0.109, creatinephosphoric acid 0.126, hexosemonophosphoric acid 0.070; Heart muscles—creatine 0.092. Carnitine (see Meat extract) is contained in muscles in small quantities (from 0% to 0.03%). Adenosine phosphoric acid, or adenylic acid (Embden), upon deamination, which occurs, e.g., during muscle contraction, turns into inosinic acid; the latter was isolated from meat extract by Liebig. Table 2. Content of various anions and cations in muscles. Ions: K 2.5-4.0%, Na 0.6-1.6%, Mg 0.2-0.3%, Ca 0.02-0.2%, Fe 0.04-0.2%, Cl 0.4-0.8%. Inorganic substances. Of the inorganic substances of muscles, the greatest interest regarding their role in muscle dynamics is represented by salts of orthophosphoric acid (H3PO4) and salts of pyrophosphoric acid (H4P2O7), the presence of which in muscles was recently established by Lohmann. Pyrophosphoric acid is found in muscles in combination with adenylic acid in the form of adenylyl-pyrophosphoric acid. In addition to these, muscles contain Cl and SO4 among anions, and K, Na, Mg, Ca, Fe among cations (Table 2). Table 3 provides data on the content of the aforementioned substances in the muscles of different animals. The chemical composition of smooth muscles has been studied less well than that of striated muscles, and the available data concern mainly the muscles of the stomach and urinary bladder. Smooth muscles contain protein substances similar to myosin and myogen, and also nucleoprotein. Furthermore, glycogen, lactacidogen, inositol, creatine, creatinephosphoric acid, creatinine, purine bases, and lactic acid have been found in their composition. There is much less creatine, creatinephosphoric acid, and lactacidogen in smooth muscles than in striated muscles (Table 4). Table 4. Content of creatinephosphoric acid and lactacidogen in smooth muscles (in percentages of fresh muscle substance). Rabbit uterus: creatinephosphoric acid 0.034, hexosemonophosphoric acid 0.100. Rooster muscular stomach: creatinephosphoric acid 0.047, hexosemonophosphoric acid 0.064. Regarding inorganic substances, one can note a higher chlorine content in smooth muscles compared to striated muscles. II. Rigor of muscles. Cadaveric rigor of muscles occurs upon the cessation of blood access to muscles either after the death of the animal, or after cutting the muscles out of the animal's body, or as a result of ligation of the corresponding artery. During cadaveric rigor, lactic acid accumulates in muscles, and their reaction becomes acidic. Under the influence of lactic acid, due to the swelling of the colloidal anisotropic substance of the muscle fibers, muscles shorten, become hard and opaque. Subsequently, the stiffened muscles become soft again; this can be explained by the fact that a further increase in the lactic acid content causes the coagulation of proteins, and this entails a decrease in the ability of colloids to bind water and their release of water. Some authors hold other views on the phenomena that occur during cadaveric rigor. Thermal rigor develops under the influence of high temperature; in the muscles of warm-blooded animals, it occurs at 50°, and in frog muscles—at 40°. Chemical rigor occurs upon immersing isolated muscles in distilled water and upon the action of acids, chloroform, ether, alcohol, many alkaloids, etc., on them.
Characteristic of rigor mortis is not only the formation of lactic acid, but also the conversion of pyrophosphoric acid into orthophosphoric acid (Lohmann). III. Metabolism and energy in Muscles. The beginning of work on the chemistry of muscle contraction was laid by the studies of Fletcher and Hopkins (Fletcher, Hopkins), who established that the activity of Muscles is always accompanied by the formation of lactic acid in them, which, as Meyerhof later showed, disappears during the relaxation of Muscles. Then Embden showed that this process proceeds through the stage of the formation of lactacidogen. Until recently, when studying the chemical dynamics of Muscles, almost exclusive attention was paid to carbohydrate metabolism, attributing the main role to them. Glucose, formed in Muscles from glycogen, before turning into lactic acid, enters into a compound with phosphoric acid, forming lactacidogen (see), which is thus an intermediate product of carbohydrate metabolism in Muscles. From it, during further transformations, lactic acid is formed [lactacidogen splits into glucose and phosphoric acid, and glucose, passing through further intermediate stages (see Carbohydrate metabolism), turns into lactic acid]. The formation of lactic acid occurs under anaerobic conditions: the contraction of Muscles is not associated with the consumption of oxygen; the period of recovery of Muscles (rest) is associated with the consumption of oxygen. During recovery, the lactic acid formed during contraction disappears in such a way that a part of it (1/4) is oxidized further to CO2 and H2O, and a part (3/4) is again converted into glucose and glycogen. Thus, in working Muscles, the formation of lactic acid and its disappearance occur. [This process of the disappearance of lactic acid is also the result of two opposite processes (see below).] As work continues, there is a struggle between these two opposite processes; during intense work, the second process does not keep up with the first, and the content of lactic acid in Muscles increases. The Muscle becomes fatigued, but its working capacity is still preserved. Upon the accumulation of a certain amount of lactic acid, complete fatigue sets in, and the Muscles cease to work. During the ensuing rest period of the Muscle, lactic acid disappears from it as a result of two opposite, mutually related processes: at the expense of the oxidation of two molecules of lactic acid, the conversion of its other six molecules into glycogen occurs. After rest, working capacity returns to the muscle, but the rested Muscle is no longer the same muscle that it was at the beginning of its work. If isolated Muscles work in an oxygen-free environment, they quickly reach a state of complete exhaustion, simultaneously with the accumulation of large amounts of lactic acid in them; the restoration of the working capacity of Muscles is possible only in the presence of oxygen, because only under aerobic conditions does the oxidation of lactic acid occur. The ratio between the total amount of lactic acid disappearing during rest and the amount of lactic acid oxidized during the same period does not represent a constant value; this coefficient... depends...
The oxidized lactic acid depends on the state of the muscles, their fatigue, training, etc., and can fluctuate within the range of 6/1 to 3/g. Carbohydrate metabolism in muscles consists, according to Meyerhof, of two phases: the first phase is anaerobic (the work phase); during it, glycogen, passing through the stage of lactacidogen formation, decomposes into molecules of lactic acid: 4/n (C6H10O5)n + 4H2O + 4H3PO4 -> 4C6H11O6.H2PO4 + 4H2O -> 8C3H6O3 + 4H3PO4; the second phase is aerobic (the recovery phase); during it, all 8 molecules of lactic acid disappear (2 of its molecules are oxidized to CO2 and H2O, and 6 molecules are again converted into lactacidogen and glycogen): 8C3H6O3 + 3H3PO4 + 6O2 -> 3C6H11O6.H2PO4 + 6CO2 + 9H2O -> 3/n (C6H10O5)n + 3H3PO4 + 6CO2 + 9H2O. Thus, during muscle contraction, exothermic processes of carbohydrate metabolism occur, and during their rest, endothermic phases occur. Meyerhof and Hill (Hill) describe energy metabolism in connection with these carbohydrate metabolism processes as follows: heat production occurs both during contraction and during rest, with 50% of the energy accounting for the contraction period and 50% for the recovery period. The heat of contraction, released during the period of work, is not generated immediately at the beginning of contraction, but in 3 phases: the first phase of heat production coincides with the beginning of contraction, the second phase of less significant heat generation with the period of maintaining the achieved tension (shortening), and the third phase (the phase of more significant heat generation) with the period of relaxation. Only after this, in the presence of oxygen, does heat production associated with muscle recovery begin, extending over a longer period of time. Meyerhof believes that lactic acid is formed during muscle contraction. Embden thinks that a significant part of the lactic acid formed during muscular activity arises after muscle contraction, and therefore views it as a substance that causes muscle relaxation. The role of creatine phosphoric acid in muscle dynamics. Recent studies have shown that not only carbohydrates participate in energy metabolism in muscles. Meyerhof previously recognized that the exothermic process of converting carbohydrates into lactic acid provides only the greater part of the energy released (in the form of work and heat) during muscle contraction, and after the discovery of creatine phosphoric acid, he thought that the rest of the energy is provided by the process of its decomposition. Indeed, according to the latest data, an important role in the chemistry of muscular activity must be attributed to creatine phosphoric acid; during muscle contraction, it decomposes into creatine and orthophosphoric acid and is synthesized again after this; this synthesis can also proceed under anaerobic conditions, meaning it can occur during the first phase of contraction. The decomposition of creatine phosphoric acid is an exothermic reaction, with 110-120 calories released for every gram of phosphoric acid split off. Rapidly contracting (white) muscles contain more creatine phosphoric acid than slowly working (red) ones; when training muscles, which is associated with an increase in their performance, the content of creatine phosphoric acid in them increases; these facts indicate a definite role for creatine phosphoric acid in the chemical dynamics of muscles. If one makes the formation of lactic acid during muscle contraction impossible (for example, by the action of mono-iodoacetic acid on the muscle), then all energy is generated at the expense of the decomposition of creatine phosphoric acid; it is even assumed that under normal conditions in muscles, the decomposition of creatine phosphoric acid occurs during contraction, providing energy for it, and carbohydrate metabolism processes may participate indirectly (for example, by providing energy for reverse synthesis). In any case, the process of creatine phosphoric acid decomposition and the process of glucose conversion into lactic acid should be considered important processes in muscles from an energetic standpoint. Conversely, the processes of glycogen decomposition, the decomposition of lactacidogen into glucose and phosphoric acid, as well as the processes of conversion of other phosphorus compounds—adenosine phosphoric and pyrophosphoric acids—occurring in muscles, do not play an energetic role. Transformations of adenylic acid in muscles. Adenosine phosphoric acid is also a substance whose decomposition is associated with muscle work; during muscle contraction (at the beginning of contraction), ammonia is split off from adenosine phosphoric acid, and as a result of such deamination, it is converted into hypoxanthosine phosphoric or inosinic acid. During muscle relaxation, the reverse synthesis of adenosine phosphoric acid occurs by the reverse addition of ammonia to inosinic acid. During the reverse synthesis of adenylic acid, according to Parnas, it is not the ammonia that was released during the deamination of adenylic acid that is added to inosinic acid, but the ammonia formed in the muscle during the deamination of amino acids. Pyrophosphoric acid is found in muscles in combination with adenylic acid in the form of adenylphosphoric acid. Pyrophosphoric acid can be enzymatically split into two molecules of orthophosphoric acid: H4P2O7 + H2O -> 2H3PO4; such decomposition takes place during prolonged work, during rigor mortis, and during autolysis. The role of pyrophosphoric acid during muscle contraction has not yet been clarified; it is assumed that during contraction, the synthesis of pyrophosphoric acid occurs, and during rest, its decomposition. Regarding the role of lactacidogen, see Lactacidogen. Thus, the following chemical processes occur in a working muscle: the decomposition of creatine phosphoric acid into creatine and phosphoric acid, the decomposition of carbohydrates with the formation of lactic acid, passing through the stage of lactacidogen formation and its decomposition into glucose and phosphoric acid; the oxidation of lactic acid; the deamination of adenylpyrophosphoric acid and the reverse amination of inosinic acid, and probably other, as yet unknown, processes. All these processes do not proceed in isolation, but are undoubtedly connected to each other; it is quite likely that the endothermic processes of synthesis of one substance proceed at the expense of the exothermic decomposition of another substance. The orthophosphoric acid formed in muscles during their contraction as a result of the splitting of creatine phosphoric and hexose phosphoric acids does not all go to the reverse synthesis of these substances; part of it passes from the muscle into the blood and further into the urine. For muscular activity, as is evident from the above, not only carbohydrates and nitrogenous substances are necessary, but also phosphoric acid; it is therefore understandable that the supply of phosphoric acid from the outside, especially during heavy physical work, has a favorable effect on muscle performance. All the chemical processes described above cause a number of physicochemical changes in the muscles. First of all, the beginning of muscle shortening is characterized by a change in the concentration of hydrogen ions; specifically, the splitting of lactacidogen, as well as the splitting of creatine phosphoric acid and the deamination of adenylic acid, cause a decrease in the concentration of hydrogen ions, i.e., they shift the reaction in the direction of alkalinity at the site of these processes (apparently in the interfibrillar colloids). Embden considers this decrease in the concentration of hydrogen ions to be the moment that triggers contraction, and the subsequent increase in the concentration of hydrogen ions due (mainly) to the formation of lactic acid to be the moment that causes muscle relaxation. Embden considers a sudden increase in the permeability of the boundary layer of muscle fibers to be the second characteristic physicochemical process during muscle contraction. Both of these processes are closely related to each other. The influence of training on the chemical composition of muscles. Training, which increases muscle performance, causes certain changes in their chemistry. Trained muscles are found to contain more glycogen, creatine, and creatine phosphoric acid. Training, on the other hand, has no effect on the content of lactacidogen.
A. Palladii. (Continuation of the article Muscles—see p. 735.) Muscles No. Latin and Russian Name. Synonyms. Form and Position. Origin and Insertion. Innervation and Relation to Segments. Abductor digiti minimi longus manus (long abductor of the little finger of the hand). [Rare variation.] A long, flat ribbon, which can even reach the humerus, to the lateral epicondyle, lying along the medial surface of the forearm. See abductor digiti quinti manus. Abductor digiti quinti manus (abductor of the little finger of the hand). Syn.: abductor digiti minimi manus. The largest of all the muscles of the hypothenar, located in the form of a flat ribbon, lies most laterally and superficially under the skin, covered only by the palmaris brevis muscle. Origin: pisiform bone, tendon of the flexor carpi ulnaris muscle, piso-hamate ligament, sometimes the transverse carpal ligament. Insertion: proximal phalanx, ulnar edge of its base. Ulnar nerve—deep branch. Cviii, VIII and Di. Abductor digiti quinti pedis (abductor of the fifth toe of the foot). Syn.: abductor digiti minimi pedis. Represents a comparatively thick and long bundle, located immediately under the skin along the lateral and plantar edge of the foot; it is this that mainly forms the relief of the lateral edge of the foot. Origin: calcaneus—lateral process of the calcaneal tuberosity and its plantar surface, fifth metatarsal bone—tuberosity of the fifth metatarsal bone, plantar aponeurosis. Insertion: proximal phalanx of the 5th toe. Medial plantar nerve. Lv and Si. Abductor hallucis (abductor of the big toe of the foot). Syn.: pollicem abducens. The largest muscle of the foot, in the form of a thick prismatic muscle bundle with a strong tendon, lies along the medial edge of the foot under the skin and fascia, covers the tendons, joint, and bones of the medial edge, and forms the pad of the big toe of the foot. Origin: calcaneus—medial process of the calcaneal tuberosity, laciniate ligament, and plantar aponeurosis. Insertion: proximal phalanx of the big toe, medial sesamoid bone, and capsule of the metatarsophalangeal joint. Medial plantar nerve. Lv and Si. Abductor pollicis brevis: radial head and ulnar head (short abductor of the big toe of the hand). Syn.: abductor internus pollicis (Cruveilhier), s. externus (Soemmering). Consists of two small folds, bundles, converging to the point of insertion, lying immediately under the skin in the lateral part of the thenar eminence, which it mainly outlines; the muscle covers the opponens pollicis muscle, as well as the entire deep head of the flexor pollicis brevis muscle. Origin: radial head: terminal tendon of the abductor pollicis longus muscle, volar forearm fascia; ulnar head: navicular bone—tuberosity of the navicular bone and transverse carpal ligament, sometimes up to the pisiform bone itself and the site of origin of the muscles of the hypothenar eminence. Insertion: proximal phalanx of the big toe—its base and radial sesamoid bone. Median nerve. Cvi, Vii. Abductor pollicis intermedius (Frohse and Frankel) (intermediate abductor of the big toe of the hand). [Variation.] See abductor pollicis longus muscle. Abductor pollicis longus (long abductor of the big toe of the hand). Syn.: abductor pollicis major, s. internus, s. bicornis, s. m. extensor ossis metacarpi pollicis, s. m. abductor carpi. Represents a large, flat, bipennate muscle belly, passing into a thin, long tendon; it is located on the distal half of the forearm along its dorsal surface and partly along its radial edge; in the proximal half, it is covered by the extensor carpi radialis brevis and extensor digitorum communis muscles; in the distal half, it lies immediately under the forearm fascia and skin; its tendon is clearly visible under the skin, especially sharply protruding during abduction of the big toe, and constitutes the radial border of the "snuffbox." Origin: ulna—its dorsal surface, interosseous membrane; radius—dorsal surface of the radius. Insertion: first metacarpal bone—its base—its lateral part. Radial nerve—deep branch. Cvi, Vii (viii). Accessorius ad digastricum (accessory to the digastric muscle of the lower jaw). [Rare variation.] A small bundle from the angle of the lower jaw to the lateral edge of the anterior belly of the digastric muscle. See digastric muscle of man. Blood supply. Action. Variations. Ulnar artery—deep volar branch. Abduction of the little finger. 1) Absent rarely; 2) often fuses with the flexor brevis digiti quinti muscle; 3) may have two or three heads; 4) one of the heads may originate above the pisiform bone, i.e., a) from the transverse carpal ligament, b) from the forearm fascia, c) from the flexor digitorum sublimis muscle, d) from the flexor carpi ulnaris muscle, e) from the ulna, f) from the humerus or from its middle or even from the medial epicondyle of the humerus—this is the abductor digiti minimi longus muscle. Medial plantar artery. Abduction and flexion of the fifth toe. One of the most variable muscles of the human body; in connection with the various places of its insertion to the proximal phalanx, it can be divided into two more or less independent layers; Le Double described three cases of accessory muscles (accessory abductor of the little toe), located outwardly and above the normal muscle. Plantar arch, perforating branches from the arcuate artery and metatarsal arteries. Strengthens the medial part of the arch of the foot and thereby shortens it; flexes and abducts the big toe. 1) The muscle often, if not always, consists of two portions: deep and superficial, as indicated by their independent innervation by separate branches of the medial plantar nerve; 2) there is often a tendon to the second toe, and not only to the medial side, but also to the lateral. Radial artery—superficial volar branch. Abduction of the big toe of the hand and partly its opposition; Volar and dorsal interosseous arteries. Abduction not only of the big toe, but mainly of the entire hand; besides that, its volar flexion helps the flexor carpi ulnaris and radialis muscles. Variations of this muscle are very frequent and diverse. 1) The muscle belly may be absent altogether due to its complete fusion with the extensor pollicis longus or brevis muscles; 2) it can often be double even throughout its entire length; 3) it is less often triple; 4) as a norm, its tendon can divide into two, less often into three and four; 5) one of them can fuse with the abductor pollicis brevis muscle (its radial head)—this is the abductor pollicis intermedius muscle; 6) accessory tendons can attach: a) to the first metacarpal bone, b) to the transverse carpal ligament, c) to the muscles of the thenar eminence: flexor pollicis brevis, abductor pollicis brevis, opponens; the latter connection sometimes gives the form of a digastric muscle; 7) the most interesting is the connection with the trapezius muscle, existing in all monkeys; 8) more complex combinations of the above-described variations between themselves are possible. Latin and Russian Name. Synonyms. Form and Position. Origin and Insertion. Innervation and Relation to Segments. Acromio-clavicularis profundus (Tisne and Rousseau) (deep acromioclavicular muscle). [Once-found variation.] A small muscle between the clavicle and the scapula, covered by the deltoid muscle. Origin: clavicle—at the border of the middle and lateral third. Insertion: scapula—acromial process. Acromio-clavicularis superficialis (Gruber) (superficial acromioclavicular muscle). See infraclavicularis muscle and lateral praeclavicularis muscle. [Very rare variation.] A small muscle bundle located between the clavicle and the scapula under the deltoid muscle. Origin: clavicle—at the border of the middle and lateral third. Insertion: scapula—acromial process, its apex. Adductor brevis (short adductor muscle of the thigh). Syn.: adductor parvus, s. profundus parvus femoris, s. femoris brevis, s. sub-pubio-femoralis, s. caput profundum m. tricipitis. The muscle has a flat, long belly with parallel fibers; it is located on the medial surface of the thigh: on the anterior surface of the adductor magnus and minimus muscles, covered in front by the superficial pectineus and adductor longus muscles; it is separated from the other adductors due to the fact that on its anterior surface lies the anterior branch of the obturator nerve, and on the posterior—its posterior branch. Origin: pubic bone—anterior surface, covered by the origin of the adductor longus and gracilis muscles. Insertion: thigh—linea aspera of the femur (upper third of the medial lip) behind the adductor longus and pectineus muscles, fusing with the tendon of the adductor magnus muscle. Obturator nerve—anterior branch. Lii-iv. Adductor hallucis: oblique head and transverse head (adductor of the big toe of the foot). Syn.: abductor hallucis (Cruveilhier). Transverse head = transversalis pedis muscle, s. plantae. Oblique head = interosseus ad indicem pertingens muscle. Represents two independent bundles, which have a completely different direction at an angle close to a right angle; between them is a large gap for all arterial branches emerging from the deep volar arch; the muscle belly lies in the depression on the middle and lateral toes, and only its insertion falls on the first toe.
The muscle is covered by the m. flexor digitorum brevis and the tendon of the m. flexor digitorum longus. Origin: caput obliquum: cuboid and III cuneiform bones, lig. calcaneocuboideum plantare, lig. plantare longum, II-IV metatarsal bones - basis ossis metatarsalis II-IV; caput transversum: capsule of the articulation of the proximal phalanges of the III-V toes and lig. transversa capitulorum. Insertion: proximal phalanx of the big toe and the lateral sesamoid bone. N. plantaris lateralis - r. profundus; it often also anastomoses with the n. plantaris medialis. SI and SII. Adductor longus (long adductor of the thigh). Syn.: adductor magnus, s. superficialis, s. secundus femoris, s. m. pubiofemoralis, s. m. adductor pectinealis. A flat, irregularly triangular plate of muscle fibers, which begins and ends with tendons, lies on the medial surface of the thigh between the m. pectineus on the lateral side and the m. gracilis on the medial side, in front of the mm. adductor brevis and magnus, and is covered anteriorly by the m. sartorius. Origin: pubic bone - below the tuberculum pubicum and the fibrous cartilage of the symphysis ossium pubis. Insertion: thigh - linea aspera femoris (middle third of the medial lip), fusing with the tendon of the mm. adductoris magni and brevis and with the aponeurosis of the m. vastus medialis. N. obturatorius - r. anterior. LII and LIII. Adductor magnus: portio flexoria and portio adductoria (great adductor of the thigh). Syn.: adductor profundus magnus femoris, s. m. custos virginum, s. m. ischiofemoralis, caput tertium tricipitis. This is one of the largest muscles of the human body; it has the shape of a thick, wide, more or less triangular plate located on the medial surface of the thigh between it and the pelvis; it lies on the m. semimembranosus and m. glutaeus maximus, is covered anteriorly by the m. vastus medialis, m. sartorius, and m. adductor longus, and on the medial side it is adjacent to the m. gracilis, which also covers it; thus, only a small middle section of the muscle on the medial surface of the thigh is not covered by muscles and is adjacent to the superficial fascia and the skin. Origin: ischium - tuber ischiadicum. Insertion: portio adductoria: thigh - linea aspera femoris (medial lip) by means of tendinous arches extending from the tuberositas glutaea to the distal third of the thigh, fusing with the tendons of the superficial adductors; portio flexoria: thigh - epicondylus medialis by means of a strong tendon and fusing with the aponeurosis of the m. vastus medialis. N. obturatorius - r. posterior for the portio adductoria and n. ischiadicus - branch of the n. tibialis for the portio flexoria. LIII and LIV - portio adductoria and LIV and LV - portio flexoria.
MUSCLES OF MAN
474 Blood supply: 1 Action: Variations: 1, A. obturatoria and aa. perforantes. Adducts the thigh and rotates it outward. 1) Very often the muscle consists of two parts, separated by a slit in which one a. perforans lies; 2) once, a division into three bundles was observed. Arcus plantaris and a. arcuata-rr. perforantes, and aa. metatarseae. Mainly strengthens the arch of the foot, but in addition, the caput transversum narrows, and the caput obliquum shortens the arch; partly also adducts the big toe and flexes it plantarly. Caput obliquum: 1) may also send a tendon to the second toe and originate from os metatarsale I; 2) may attach to the tendon or belly of m. flexor hallucis brevis; 3) may originate with one bundle only from one of the bones; 4) may have additional bundles along its lateral edge to the first phalanx of the second toe. Caput transversum: 1) may be absent entirely; 2) may originate only from the IV and V metatarsophalangeal joints or from the III and IV, or finally from the III, IV, and V; 3) very often there is an additional muscle bundle in the first interosseous space between m. interosseus dorsalis I and the caput obliquum of this muscle, which is directed toward the caput transversum and ends in it by means of a tendon. A. femoralis (a. profunda femoris and a. pudenda externa) and a. hypogastrica (a. obturatoria). Adducts the thigh and rotates it outward. 1) sometimes it may double; 2) its attachment may descend to the knees and to the condylus medialis; 3) sometimes it may fuse more or less completely with m. adductor brevis or m. pectineus. A. obturatoria and aa. perforantes. Adducts the thigh-portio adductoria and flexes it at the knee-portio flexoria. 1) Often, duplication is observed with the formation of independent portio adductoria and portio flexoria; 2) may fuse at the tuber ischiadicum with m. semimembranosus; 3) once, an origin by two heads near the origin of m. semimembranosus was observed; 4) in one case, an additional belly of m. semimembranosus ran from the fascia of m. adductor magnus, and then in the middle of the thigh it connected with the general mass of the muscle; 5) the caput breve of m. bicipitis femoris may connect with m. adductor magnus by means of a thin bundle. No. Name (Latin and Russian). Synonyms. Form and position. Innervation and relation to segments. Origin and attachment. Adductor minimus (small adductor of the thigh). Syn.: adductor quadratus, s. adductor femoris (cruris) minimus, s. adductor tertius femoris. Represents the uppermost part of m. adductor magnus and has the form of a rather wide triangular plate, located between the pelvis and the upper third of the medial surface of the thigh and lies adjacent to the lateral edge of m. adductor magnus; the fibers of both muscles have different directions and cross in the upper parts. Origin: ischium-ramus inferior (anterior surface) and pubis-synostosis ischio-pubica. Attachment: thigh-linea aspera femoris (its proximal third), starting from the trochanter minor. N. obturatorius-r. anterior. Adductor pollicis: caput obliquum and caput transversum (adductor of the thumb). Syn.: mesothenar, pars profunda hypothenaris pollicis. The largest and deepest of the muscles of the thenar eminence; consists of two heads in the form of a muscle band, arranged at an angle to each other; between them there is a slit through which the arcus volaris profundus and the deep branch of the n. ulnaris pass. The muscle is to a significant extent covered by m. flexor pollicis brevis, its superficial head, the tendon of m. flexor digitorum sublimis and profundus, and m. lumbricalis I and II, and only its final distal part is not covered by muscles; the muscle itself covers m. interossei externi I and II. Origin: caput obliquum: II and III metacarpal bones-their base, capitate bone, and lig. radiatum; caput transversum: II and III metacarpal bones, their heads, and facies volaris of the III metacarpal. Attachment: proximal phalanx of the thumb-its base, medial sesamoid bone of the artic. metacarpo-phalangeae. N. ulnaris-r. profundus and in 10% of cases also a small branch of the n. medianus. Cvii (D1), and also sometimes Cvi and Cvii (n. medianus). Adductor prostatae. Fibers of m. levator ani, which are directed toward the prostate gland. Alaris (M. of the nasal wings). Syn.: alaris major, dilatator pinnarum proprius, myrtiformis, depressor alae nasi, dilatator narium proprius+levator alae narium proprius, levator proprius alae nasi, dilatator nasi. A small fan-shaped muscle bundle on the wings of the nose. Origin: maxilla-edges of the apertura piriformis nasi. Attachment: skin of the wings of the nose. N. facialis-r. infraorbitalis. Anconaeus (elbow muscle). Syn.: anconaeus quartus, s. posterior, s. parvus, s. m. brachialis posterior, s. m. epicondylo-cubitalis. A small muscle in the form of a pyramid, attaching by its apex to the arm-epicondylus lateralis humeri, and by its base to the olecranon; located just under the skin. Origin: arm-epicondylus lateralis humeri, lig. collaterale laterale, tendinous plate between m. extensor carpi ulnaris and m. extensor digitorum communis. Attachment: ulna-margo dorsalis, its proximal quarter. N. radialis. Cvii and Cviii. Anomalus maxillae (Albinus) (anomalous muscle of the maxilla). Syn.: rhomboideus + lateralis narium. A flat muscle ribbon or a cylindrical or spindle-shaped bundle on the anterior surface of the maxilla under m. quadratus labii superioris. Origin: maxilla-its processus naso-frontalis. Attachment: maxilla-fossa canina. Antitragicus (antitragus muscle). A small muscle plate on the antitragus. Origin: auricle-antitragus and up to the cauda helicis. Attachment: skin of the auricle-incisura antitragica. N. facialis. Apicis nasi (muscle of the nasal tip). Syn.: levator nasi proprius, compressor narium minor. [Inconstant muscle.] A small bundle on the lower half of the crus laterale cartilaginis alaris majoris. Origin: wing of the nose-cartilago alaris nasi major, its crus laterale. Attachment: skin of the nasal tip. N. facialis. Arrectores pilorum (muscles raising the hairs). Syn.: pili, s. expressores sebi. Smooth muscle fibers of the upper layer of the dermis proper, directed toward the hair follicles and sebaceous glands. Sympathetic nervous system. Blood supply: A. obturatoria. Action: Adducts the thigh and rotates it outward. Variations: According to some anatomists, this is only a variation of m. adductor magnus, with which it can fuse to varying degrees, up to the complete loss of its independence. Arcus volaris profundus. Action: Caput obliquum-flexion of the thumb and caput transversum-its adduction. Variations: A more complete separation of both heads into independent muscles is possible; in that case, the caput transversum is called m. transversus manus (Halette). A. angularis, a. maxillaris externa, and a. ethmoidalis ant. from a. ophthalmica. Action: Dilates the wings of the nose. Variations: 1) The development of the muscle is quite different; 2) sometimes it is absent entirely; 3) the anterior bundle may originate from the upper edge of the cartilage of the wings of the nose and be directed toward the tip of the nose-this is m. levator alae proprius (Arnold), or m. dilatator anterior (Theile); 4) at the anterior edge there may be a small bundle-this is m. alaris minor; it departs from the anterior edge of the cartilage of the wing of the nose. A. interossea recurrens from a. interossea dorsalis. Action: Extends the arm at the elbow joint and tenses the joint capsule. Variations: A very constant muscle, the rare variations of which boil down to a closer connection with neighboring muscles: with m. triceps brachii (its caput laterale), with m. extensor carpi ulnaris, and sometimes to its duplication or division into two by means of a connective tissue layer. Action: Attaching to parts of immovably connected bones, it is apparently devoid of function. Variations: 1) May be absent entirely; 2) may vary in size from 5 to 20 mm; 3) may consist of several portions; 4) may give bundles to m. nasalis, m. caninus, caput infraorbitale, and caput zygomaticum of m. quadratus labii superioris. Action: Pulls the antitragus. Variations: 1) May break up into two crossing bundles; 2) individual fibers may reach the apex of the cauda helicis-these are mm. caudae helicis. Action: Lowers the tip of the nose. Variations: Often may be absent or be developed differently. Action: Raises the hairs and makes the skin "gooseflesh." Articularis genu (more correctly genus) (muscle of the knee joint). Syn.: subcruralis externus and internus. A flat muscle plate on the anterior surface of the thigh, lying on the bone itself under m. vastus intermedius. Origin: thigh-facies anterior. Attachment: articular capsule of the knee joint, its anterior and lateral surface. N. cruralis. Articularis humeri novus (Gfantzer) (new muscle of the shoulder joint). [Variation.] See m. tensor semivaginae articulationis humero-scapularis. Ary-epiglotticus (arytenoid-epiglottic muscle). Syn.: epiglottideo-arytaenoideus, depressor epiglottidis, Hiltoni. See m. arytaenoideus obliquus. Arytaenoideus obliquus (oblique arytenoid muscle).
Syn.: ary-corniculatus, s. ary-taenoideo-corniculatus, s. interarytaenoideus obliquus. A small muscle bundle on the dorsal surface of the arytenoid cartilages. Origin: arytenoid cartilage-muscular process. Insertion: opposite cartilage, and its continuation along the lateral wall of the laryngeal vestibule to the epiglottis is the aryepiglottic muscle. Vagus nerve-inferior laryngeal nerve, its posterior branch. Transverse arytenoid muscle (transverse arytenoid M.). Syn.: interarytaenoideus proprius. A small muscular plate located on the dorsal surface of the arytenoid cartilages. An unpaired muscle lying on the posterior surface of both arytenoid cartilages. Vagus nerve-inferior laryngeal nerve, its posterior branch. Atlantico-basilaris internus (Gruber) (atlanto-basilar M.). [Rare variation (3-4%).] A spindle-shaped, triangular, or prismatic bundle located on the anterior atlanto-occipital membrane, medial to the longus capitis muscle. Origin: atlas-anterior tubercle, less often somewhat lower-to the anterior longitudinal ligament and the axis. Insertion: base of the skull-base of the occipital bone. Atlantico-mastoideus (Gruber). [Rare variation (1 in 33 or 1 in 5).] A spindle-shaped or triangular bundle between the atlas and the occipital bone laterally. Origin: atlas-transverse process. Cervical nerves I and II. Insertion: temporal bone-mastoid process. Anterior auricular muscle (anterior muscle of the auricle). Syn.: auricularis anticus, s. attrahens auriculae, s. epicranius superficialis, s. temporalis superficialis, s. protrahens auriculae, s. novus conchae proprius. A very small bundle of diverging short muscle fibers located in front of the auricle somewhat above the zygomatic arch in the superficial fascia of the temple. Origin: galea aponeurotica and superficial temporal fascia together with fibers of the auriculo-frontal muscle. Insertion: auricle-spine of the helix and spine and eminence of the concha. Facial nerve-temporal branch. Deep anterior auricular muscle (Cruveilhier) (deep anterior muscle of the auricle). Part of the fibers of the anterior auricular muscle. Auricularis anticus profundus (Cruveilhier). Fibers extending from the zygomatic arch to the tragus. Inferior auricular muscle (inferior muscle of the auricle). [Very rare variation.] Represents several muscle fibers lying in the subcutaneous fat layer above the parotid fascia. Origin: parotideo-masseteric fascia. Facial nerve-posterior auricular nerve. Insertion: auricle-eminence of the concha. Posterior auricular muscle (posterior muscle of the auricle). Syn.: auricularis posticus, retrahens auriculae, epicranius auricularis posterior. Represents a fairly significant (3-4 cm) muscle bundle located across the mastoid process on the bone itself just under the skin. Origin: temporal bone-mastoid process (with two teeth) and occipital bone-superior nuchal line. Insertion: auricle-its posterior surface, eminence of the concha. Facial nerve-posterior auricular nerve. Blood supply. Action. Variations. Tenses the knee capsule. Superior laryngeal nerve and cricothyroid branch from the superior thyroid artery. Constricts the entrance to the larynx. Superior laryngeal nerve from the cricoarytenoid artery from the superior thyroid artery. Constricts the posterior part of the glottis. Superficial temporal artery. Pulls the auricle forward. 1) Sometimes absent; 2) changes consist in the elongation of the muscle forward, so that the lower bundles can be parallel to the zygomatic arch. Posterior auricular artery. Pulls the auricle backward. 1) May be absent; 2) may consist of separate portions (up to 5-6); 3) their origin: external occipital protuberance, superficial cervical fascia, tendon of the trapezius muscle; with the transverse nuchal muscle it can form a digastric muscle; 4) its lower bundles often reach the parotideo-masseteric fascia; the upper fibers of the platysma can extend backward to it and lie against it.
B. M. E. Vol. XIX. No. Name in Latin and Russian. Synonyms. Form and position. Origin and insertion. Innervation and relation to segments. 36 Superior auricular muscle (superior muscle of the auricle). Syn.: attollens auriculae, attentionis, epicranius auricularis superior. Represents a thin layer of separate, fairly long muscle fibers, having different shapes and sizes; lies just under the skin on the galea aponeurotica, which separates it from the temporal fascia. Origin: galea aponeurotica and superficial temporal fascia. Facial nerve-temporal branch (its anterior surface) and posterior auricular nerve (posterior). Insertion: auricle-its posterior surface-eminence of the scapha and triangular fossa and spine of the helix. 37 Auriculo-frontalis (Gegenbaur) (auriculo-frontal M.). Syn.: epicranius temporalis, orbito-auricularis. [Variation.] In a well-developed state, it represents a quadrangular plate of thin muscle fibers located in the temple region between the lateral edge of the frontal muscle and the medial edge of the superior auricular muscle, on the galea aponeurotica, just under the skin. Fibers of the epicranius muscle, which in full development represent a quadrangular plate between the frontal muscle on one side and the superior and anterior auricular muscles on the other. Facial nerve-temporal branch. Auriculo-iniacus (Hamy). [Rare variation.] Muscle fibers of the fused transverse nuchal muscle and the posterior auricular muscle. A small digastric muscle located on the occipital bone along the nuchal line.
superior just under the skin. Auriculo-styloideus (Duverney) (auriculo-styloid M.). Syn.: stilo-auricularis, auriculo-glossus, depressor auriculae. [Rare variation.] A small muscle bundle in the space between the auricle and the styloid process. Origin: external auditory canal-cartilage of the external meatus. Insertion: temporal bone-styloid process. Azygos pharyngis (unpaired muscle of the pharynx). A small muscle bundle along the posterior wall of the pharynx. Origin: occipital bone-pharyngeal tubercle. Insertion: pharynx-pharyngeal raphe. Biceps brachii: long head and short head (biceps muscle of the arm). Syn.: flexor antibrachii radialis, flexor biceps internus, quadri-.
geminis brachii. The muscle has two heads, starting with long ribbon-shaped tendons; they transition into spindle-shaped muscle bellies and merge more or less completely into one large muscle mass, which transitions into a strong, cord-shaped tendon; from it, a tendinous plate (lacertus fibrosus) extends medially. The muscle is located on the anterior surface of the arm under the superficial fascia of the arm and under the skin; it borders laterally on the m. triceps brachii-caput laterale, and medially on its caput mediale, the tendon of the m. latissimus dorsi, the m. coraco-brachialis, and the m. brachialis, being separated from them by the septi intermuscularis lateralis and medialis. Origin: caput longum: scapula-tuber-ositas supraglenoidalis scapulae; caput breve: scapula-processus coracoideus scapulae, its apex. Insertion: radius-tuberositas radii, fascia antibrachii-lacertus fibrosus. Musculo-cutaneus, Cv and Cvi. Blood supply: Action: Variations: A. temporalis superficialis, a. auricularis posterior, and a. occipitalis. Pulls the auricle upward. 1) May be absent; 2) may break up into separate bundles; 3) its dimensions may vary; 4) the entire muscle may attach to the fascia temporalis and not reach the auricle; 5) may consist of two layers; 6) may have an inscriptio tendinea; 7) may fuse with the m. helicis major. Various forms of muscle fibers from single ones to a complete quadrangular plate; approximately the same thickness as the m. frontalis. 1) This small muscle has diverse forms: it may consist of one belly or be digastric, with an intermediate tendon; 2) sometimes divided into two parallel bellies (biceps) either along the entire length or only at its end; 3) may attach: a) to the processus styloideus; b) to the m. stylo-glossus; c) to the cervical aponeurosis. Observed several times, but Le Double believes that it should occur much more often than is commonly thought. A. axillaris-rr. musculares and a. brachialis-rr. musculares. Flexes the arm at the elbow joint and supinates the forearm; in the shoulder joint, it participates in the abduction of the arm (abductio)-long head, and in the adduction of the arm into a flexed position (anteversio)-both heads. This muscle is subject to the most frequent variations. 1) Cases of the absence of one or another head are very rare, and the absence of both heads is completely singular; 2) cases of additional starting heads of the muscle are frequent, which may depart: laterally from the processus coracoideus, from the shoulder capsule, from the tendon of the m. pectoralis majoris, from the upper and even middle part of the humerus, directly above the m. brachialis (caput access., s. tertium-10%), from the septum intermusculare med.; 3) cases of enlargement of attachment sites are frequent, which may reach the ulna (m. coraco-ulnaris), to neighboring muscles: m. pronator teres, flexor carpi rad., m. brachio-radialis; 4) both heads may be completely separated up to the tendon, in this case, one portion is called the m. coraco-radialis, and the other the m. gleno-radialis; 5) in case of underdevelopment of the first of them, the muscle is reduced to the m. gleno-radialis; 6) with underdevelopment of the m. gleno-radialis, the muscle is reduced to a form with one belly-the m. coraco-radialis; 7) the muscle may be three-headed in the following combinations: a) an additional one from the humerus, from its middle or lower third, joins the normal heads; b) a third one joins the normal heads either from the tendon of the m. pectoralis majoris, or from the upper part of the humerus, or from the articular capsule; c) a doubled head of the m. coraco-radialis joins the normal m. gleno-coracoideus; 8) the muscle may have four heads in the following forms: a) a third from the middle third of the humerus and a fourth from the tuberculum majus humeri join the two normal ones; b) two portions from the humerus, originating at the level of the upper tendon of the m. brachialis, join the two normal heads; c) in the absence of the caput longum, there may be a double caput coraco-radiale, a third head from the medial surface of the humerus, and a fourth from the tuberculum majus; d) with normal heads, the third originates from the medial surface of the arm, and the fourth from the outer lip of the sulci intertubercularis; e) similar to the previous one, but with a fourth head from the tendon of the m. pectoralis; f) caput longum, a bifurcated caput breve, and a fourth from the tendon of the m. pectoralis; g) caput longum. 16. No. Name (Latin and Russian). Synonyms. Form and position. Origin and insertion. Innervation and relation to segments. Biceps femoris: caput longum and caput breve (biceps muscle of the thigh). Syn.: biceps cruris, flexor cruris externus, flexor cruris fibularis, flexor cruris tibialis. The muscle has two heads-a long one, which starts with a tendon from the pelvis, and a short one from the thigh; each of them has a flat, wide, plate-like belly, which merge together and transition into a narrow, short tendon; the muscle lies superficially under the skin on the lateral part of the posterior surface of the thigh and borders laterally on the m. tensor fasciae latae and the tractus ilio-tibialis, and medially on the m. semitendinosus. Origin: caput longum: ischium-tuber ischiadicum, together with the m. semitendinosus; caput breve: thigh-linea aspera femoris, middle third of the lateral lip, septum intermusculare. Insertion: fibula-capitulum fib., tibia-condylus lateralis tibiae and fascia cruris. N. peronaeus communis-caput breve and n. tibialis-caput longum. Liv-V and Si-caput breve; Si and Cii-caput longum. Brachialis (brachial muscle). Syn.: brachialis anterior, s. internus, brachiaeus internus, flexor antibrachii ulnaris, flexor cubitalis internus. A large fleshy muscle covering the entire anterior surface of the humerus in its lower half and itself covered by the biceps muscle along almost its entire extent, except for the lower part of the medial half. Origin: humerus-facies anterior from the tuberositas deltoidea to the capsule of the elbow joint and septa intermuscularia laterale and mediale. Insertion: ulna-tuberositas ulnae and fuses with the capsule of the elbow joint. N. radialis (in 75% of cases), n. musculo-cutaneus, very often also the n. medianus. Cv and Cvi. Brachio-radialis (brachio-radial muscle). Syn.: regulator radii, supinator longus, s. primus, satelles a. radialis, pauperum, mendicantium. The muscle represents a long, spindle-shaped, somewhat flattened ribbon, lying along the lateral edge of the forearm in its upper half; in the lower half, it transitions into a long, narrowing tendon; it is located just under the superficial fascia of the forearm and the skin; its belly borders on the dorsal side with the mm. extensor carpi radialis longus and brevis, and on the volar side with the m. pronator teres and m. flexor carpi radialis. Origin: humerus-margo lateralis humeri above the epicondylus lateralis, septum intermusculare laterale. Insertion: radius-facies lateralis proximally from the processus styloideus radii. N. radialis. Cv and Cvi. Broncho-oesophageus (broncho-esophageal muscle). [Frequent muscle.] A thin triangular muscle plate that goes from the posterior wall of the left bronchus to the longitudinal muscles of the esophagus. Buccinator (buccal muscle or trumpeter's muscle). Syn.: buccae, buccinatorius, contrahens communis buccarum labiorumque. Represents a thin plate woven from muscle bundles, the greater part of which is directed, crossing at an acute angle, either from the upper jaw into the lower lip or from the lower jaw into the upper lip, and only the marginal fibers go without crossing from the upper jaw into the upper lip, and from the lower jaw into the lower lip; the muscle lies in the depth of the cheek under the layer of the fat pad of the cheeks. Origin: upper jaw-processus alveolaris maxillae, tendinous arch between the processus pyramidalis ossis palatini and the hamulus pterygoideus, raphe pterygo-mandibularis, crista buccinatoria and lower jaw-processus alveolaris mandibulae.
Ex.: skin of the angle of the mouth and m. orbicularis oris. N. facialis-rr. buccales, plexus buccinatorius. Blood supply. Action. Variations: doubled, caput breve and a fourth from the humerus; 9) M. may have five heads in the following forms: a) besides the normal ones, a third from the humerus, a fourth from m. deltoideus, a fifth from the lip of the sulcus bicipitalis; b) besides the normal M., a second biceps with its own tendon and with three heads: two from the humerus, and the last from the short head of the biceps M.; c) besides the normal ones, a third head from the humerus, a fourth from the processus coracoideus, and a fifth from the capsula articularis. A. circumflexa femoris medialis, aa. perforantes and branches of a. poplitea. Caput breve-flexes the leg at the knee joint and, with the knee bent, rotates the lower leg outward; caput longum-additionally rotates the thigh outward, flexes the leg backward at the hip joint (retroversio), and strengthens it when standing. M. is distinguished by frequent and diverse variations. 1) Caput breve may originate: from fascia lata, linea aspera medialis, epicondylus lateralis, m. adductor magnus, vastus lateralis and even lig. sacro-tuberosum; 2) caput breve may connect with the portio flexoria (longitudinalis) of m. adductor magnus; 3) caput longum may originate: from the sacrum, coccyx, lig. sacro-tuberosum and m. glutaeus maximus; 4) caput longum may connect with m. semitendinosus by an intermediate muscular bundle; 5) caput longum may connect with m. adductor magnus; 6) M. may give a bundle to the fascia cruris-this is m. tensor fasciae cruris; 7) both heads may be completely independent; 8) caput breve may be completely absent; 9) on the other hand, caput breve may divide into several bundles; 10) there may be additional bundles from the thigh or pelvic bones. A. brachialis, aa. collaterales ulnaris superior and inferior and a. radialis-a. recurrens. Flexes the arm at the elbow joint. Variations of this M. are comparatively few. 1) Cases of division of the M. into two heads on both sides of the tuberositas deltoidea are quite frequent; 2) there is an additional bundle from the septum intermusculare mediale; 3) it may have close relations with mm. deltoideus, coraco-brachialis, pronator teres, supinator longus, biceps; 4) additional bundles may attach to the radius, to the chorda obliqua, to the fascia antibrachii, to the elbow joint, to the tendon of m. bicipitis; 5) there may be muscular bundles to m. flexor pollicis longus; 6) absence of the M. was once observed with underdevelopment of the radii. Aa. collaterales et recurrens radiales. Flexes the arm at the elbow joint, weakly supinates (up to 20° and only in those cases when supination begins from a position of extreme pronation) and pronates significantly more strongly (up to 100°). 1) Several cases of absence of the M. on one, and once on both sides, were observed; 2) the origin may rise to the tuberositas deltoidea and enter into connection with m. deltoideus and m. brachialis; 3) the point of attachment may also shift; on one side it may reach only to the upper edge of m. pronator quadratus, and on the other descend below the processus styloideus to the os lunatum and to the base of the os metacarpalis III; 4) cases of splitting off of a thin bundle from it were also observed, which attached near m. pronator teres to the radius-this is m. supinator verus; 5) the tendon often splits into two, and very rarely the entire M. may divide into two bundles. Aa. labiales superior et inferior from a. maxillaris externa, a. transversa faciei from a. temporalis superficialis and aa. buccinatoria, alveolaris superior posterior, mentalis and infraorbitalis from a. maxillaris interna. Compresses the cheeks during blowing or spitting, protects the mucosa from being bitten during chewing. 1) Division of the M. into two layers; 2) a defect or thinning in the middle part is observed; 3) the origin of the M. on both the upper and lower jaws may be reduced; 4) there may be an additional bundle from the tendinous arch from the fascia buccalis; 5) a small bundle from the lower portion may attach to the lower jaw near the tuber mentale or together with m. mentalis to the skin of the chin; 6) a separate small bundle may pass to the ductus parotideus; 7) M. may have close relations with m. masseter, with m. constrictor pharyngis superior (m. bucco-pharyngeus), with m. zygomaticus. No. Name in Latin and Russian. Synonyms. Form and position. Origin and attachment. Innervation and relation to segments. Bucco-labialis (bucco-labial M.). Fibers of m. buccinator for the lips. N. glosso-pharyngeus. Bucco-pharyngeus (bucco-pharyngeal M.). See constrictor pharyngeus superior and m. buccinator. A small bundle of m. constrictor pharyngeus superior, which originates from the raphe pterygo-mandibularis. Bulbo-cavernosus (bulbo-cavernosus M.). Syn.: accelerator urinae, compressor bulbi (muliebris), s. bulbi urethrae, constrictor sphincter ani externus, in men, lower surface of bulbi urethrae. Att.: in men: bulbus urethrae, corpora cavernosa urethrae and penis; in women: lower surface of clitoridis, bulbus vestibuli, its dorsal surface and the mucous membrane of the vestibuli vaginae. N. pudendus. Caninus (canine M.). Syn.: levator angularis (anguli) oris superior, levator labiorum communis, triangularis superior, elevator labiorum communis. A small muscular ribbon on the upper jaw itself, covered by a cluster of fat, m. quadratus labii superioris and m. zygomaticus. Orig.: upper jaw-fossa canina below the foramen infraorbitale. Att.: skin of the angle of the mouth and weaves with tendinous fibers into m. triangularis and orbicularis oris of the lower lip. N. facialis-r. zygomaticus. Cephalo-pharyngeus (cephalo-pharyngeal M.). Syn.: occipito-pharyngeus. A small ribbon or cord between the base of the skull and the pharynx; located on its posterior surface. Orig.: occipital bone-pars basilaris in front of the condylus occipitalis. Att.: pharynx, its posterior wall. N. vagus-rr. pharyngei. Cerato-arytaenoideus (Gruber) (cerato-arytenoid M.). [Rare variation.] Muscular fibers on the posterior surface of the laryngeal cartilages between the lateral edge of m. crico-arytaenoideus posterior and the cartilago thyreoidea. Orig.: arytenoid cartilage-processus muscularis. Att.: thyroid cartilage-cornu inferius. Cerato-cricoideus (Tourtual C.) (cerato-cricoid M.). Syn.: kerato-cricoideus, crico-corniculatus, crico-thyreoideus posticus. [Variation.] A small muscular bundle located on the posterior surface of the laryngeal cartilages, having a direction of fibers opposite to m. crico-thyreoideus and different innervation. Orig.: cricoid cartilage-lamina cartilaginis cricoideae and m. crico-arytaenoideus posterior. Att.: thyroid cartilage-cornu inferius. N. laryngeus inferior-its small branch. Cerato-glossus (cerato-glossus M.). Posterior bundles of m. hyo-glossus. Orig.: hyoid bone-cornu majus. Att.: mass of the tongue. N. hypoglossus. Cerato-pharyngeus (cerato-pharyngeal M.). Syn.: hyo-cerato-pharyngeus. Part of the fibers of m. constrictor pharyngeus medius. Between the hyoid bone and the pharynx. Orig.: hyoid bone-cornu majus ossis hyoidei. Att.: lateral wall of the pharynx. N. vagus-rr. pharyngei. Cervico-costo-humeralis (Gruber) (cervico-costo-humeral M.). [Once observed variation.] A muscular belly (11 cm) that originated with two tendons lay dorsally to the clavicle and m. subclavius, ventrally to the vena subclavia and plexus brachialis, directed dorsally to m. pectoralis minor and ventrally to the attachment of m. subscapularis and attached tendinously to the humerus. Orig.: VI cervical vertebra-processus transversus and I rib.
Insertion: humerus - crista tuberculi minoris near the attachment of m. latissimus dorsi. Unknown 404: Blood supply Action Variations. Compresses the urethra in men and the vestibulum vaginae in women. Infraorbital artery and buccal artery from the internal maxillary artery and branches of the external maxillary artery. 1) The origin medially can reach the m. nasalis and in such a case the Muscle seems to be adjacent to the m. incisivus superior; 2) give bundles to the pars transversa of the m. nasalis; 3) connect with the m. anomalus maxillae, with the caput infraorbitale and zygomaticum of the m. quadratus labii superioris, with the m. orbicularis oris and incisivus superior; 4) divide into two portions - lateral and medial or superficial and deep, and even into three completely equal bundles. Pharyngeal branch from the ascending pharyngeal artery (external carotid artery). Elevates the pharynx. 1) Absent very rarely; 2) segmentation of this Muscle was observed; 3) its origin can shift: a) to the lower surface of the pyramid of the temporal bone - m. petro-pharyngeus - ends in the m. pterygo-pharyngeus (part of the m. constrictor pharyngis superior); b) to the lower surface of the auditory tube - m. salpingo-pharyngeus (see m. constrictor pharyngis superior); c) to the sphenoid bone from its small tubercle or ligamentum Civinini - m. spheno-pharyngeus; 4) can receive an additional small bundle from the aponeurosis of the soft palate. According to Fürbringer, it occurs much more often than is indicated, and represents a part of the fibers of the m. crico-arytenoideus posticus, which attach to the thyroid cartilage. Very often absent entirely, found on 33 cadavers - 7 times, on 26 cadavers - 5 times, on 28 cadavers - 5 times; can be only on one side. Depresses the root of the tongue. Compresses the pharynx. 1) Close to it is the m. cervico-humeralis (Ranson); it starts from the VI cervical vertebra - processus transversus and attaches to the tuberculum minus humeri. 49ti No. Name Latin and Russian. Synonyms. Form and position. Innervation and relation to segments. Origin and insertion. Cervico-hyoideus (Le Double) (cervico-hyoid Muscle). [Rare variation, see m. omo-hyoideus.] Origin: VI and VII cervical vertebrae - processus transversalis. Insertion: os hyoideum. Chondro-coracoideus. [Variation.] See m. pectoralis major. Chondro-epitrochlearis. [Variation.] See m. pectoralis major. Chondro-glossus (hyo-glossal Muscle). [Variation.] Middle fibers of m. hyo-glossus. Origin: hyoid bone - cornu minus ossis hyoidei. Insertion: root of the tongue - passes into the m. longitudinalis linguae superior. Nerve: N. hypoglossus. Chondro-pharyngeus (middle constrictor of the pharynx). Represents a separated upper bundle of the middle constrictor of the pharynx. Origin: hyoid bone - cornu minus ossis hyoidei. Insertion: lateral wall of the pharynx. Nerve: N. vagus - rr. pharyngei. Ciliaris: fibrae meridionales, radiales and circulares (ciliary Muscle). Syn.: lig. ciliare, tensor chorioideae - fibrae meridionales and radiales (m. Bruckii), - m. Mulleri - fibrae circulares, compressor lentis. Smooth muscle fibers located on the outer surface of the orbiculus ciliaris and coronae ciliaris; consists of three groups of fibers: meridional fibers (fibrae meridionales, s. Bruckii) go from the border between the sclera and cornea to the orbiculus ciliaris, radial fibers (f. radiales) go more inward and circular fibers (f. circulares, s. Mulleri) surround the ciliary edge of the iris. Nerve: N. oculomotorius - through ganglion ciliare - nervi ciliares. Ciliaris Riolani (muscle of the eyelashes). Syn.: sub-tarsalis. Thin bundle of muscle fibers located along the edge of the eyelids, around the ducts of the tarsal glands. 64 Clavicularis novus (Gantzer). [Atypical muscle.] See m. infraclavicularis. Cleido-cervicalis (cleido-cervical Muscle). [Variation.] See m. omo-hyoideus. 66 Cleido-hyoideus (Cruveilhier) (cleido-hyoid Muscle). [Variation.] See m. omo-hyoideus. Cleido-mastoideo-occipitalis (cleido-mastoid-occipital Muscle). [Variation.] See m. sterno-cleido-mastoideus. Cleido-mastoideus (cleido-mastoid Muscle). [Variation.] See m. sterno-cleido-mastoideus. Cleido-fascialis (Macalister) (cleido-fascial Muscle). [Variation.] See m. omo-hyoideus. Cleido-occipitalis (cleido-occipital Muscle). [Variation.] See m. sterno-cleido-mastoideus. Coangustator labii inferioris (Merkel). Part of m. orbicularis oris. 72 Coccygeus (coccygeal Muscle). Syn.: abductor coccygis (ventralis), s. caudae anterior, levator coccygis, ilio-coccygeus, ischio-coccygeus, ischio-caudalis, triangularis coccygis, spino-caudalis. Origin: ischium - spina ischiadica. Insertion: IV and V sacral vertebrae and coccyx, their lateral edges and ligamentum sacro-spinosum. Nerve: Plexus pudendus. S(n)i III, IV (V). Blood supply: Branch of a. glutaea inferior, a. haemorrhoidalis inferior and a. sacralis lateralis. Action: Compresses the pharynx. Variations: 1) The Muscle is absent very often; 2) The Muscle consists of muscular and tendinous layers, which are in various relative quantities, and on most cadavers the latter dominate, but sometimes it can be the reverse; 3) cases of doubling and tripling of the Muscle are possible; 4) its connection with m. levator ani is possible. Complexus major (greater complex muscle). Under this name the French understand the entire triangular mass of muscle bundles between the transverse processes of the 6-thoracic vertebrae and the four lower cervical, and also often the spinous processes of the VII cervical and I thoracic vertebrae on one side and the occipital bone on the other (=m. semispinalis capitis); some German anatomists call only the lateral part of this Muscle so. See m. semispinalis. Origin: 1) 5-7 upper thoracic vertebrae and VII cervical vertebra - their processus transversus; 2) 4 lower cervical vertebrae - their processus articulares and base of processus transversus; 3) VII cervical and I thoracic vertebrae - their processus spinosus. Insertion: occipital bone between linea nuchae superior and inferior. Nerve: The first three cervical nerves - rami posteriores. Complexus minor (of French authors) (lesser complex Muscle). Syn.: complexus parvus, trachelo-mastoideus, mastoideus lateralis. Flat, narrow, long muscle ribbon on the lateral surface of the neck in front of the m. complexus major. Origin: lower cervical and upper thoracic vertebrae - processus transversus. Insertion: temporal bone - processus mastoideus, its posterior edge and apex. Nerve: N. occipitalis major, and also III and IV cervical nerves - their rami posteriores. Complexus profundus (Testut) (deep complex Muscle). Rarely occurring thin muscle bundle located under the m. complexus major. See m. semispinalis. Origin: II thoracic vertebra - processus transversus. Insertion: occipital bone. Compressor bulbi proprius (proper compressor of the bulb of the urethra). Posterior and deep layer of m. bulbo-cavernosus (virilis). 77 Compressor narium minor (Arnold) (lesser compressor of the nostrils). See m. apicis nasi. 78 Compressor prostatae (compressor of the prostate gland). Bundle of m. levator ani, which goes to the prostate gland. Compressor sacci lacrimalis (compressor of the lacrimal sac). Part of the bundles of m. orbicularis oculi. Compressor urethrae (Guthrie) (compressor of the urethra). Syn.: transverso-urethralis. Circular fibers of the urethra of women. 81 Compressor vesiculae et ductus seminis (Viner Ellis) (compressor of the seminal vesicle and duct). Muscle fibers between both seminal vesicles. Constrictor cunni profundus, s. vestibuli. The most anterior bundles of m. transversus perinei profundi in women. Constrictor isthmi faucium superior, s. posterior (constrictor of the fauces). Part of the fibers of m. pharyngo-palatinus. Constrictor pharyngis inferior: m. thyreo-pharyngeus + m. crico-pharyngeus (inferior constrictor of the pharynx). Syn.: laryngo-pharyngeus. Thin muscle layer in the lower part of the pharynx. Origin: by two bundles: a) thyreo-pharyngeus - thyroid cartilage; b) crico-pharyngeus - cricoid cartilage. Insertion: posterior wall of the pharynx. Nerve: N. vagus - rr. pharyngei. Constrictor pharyngis medius: m. chondro-pharyngeus + m. cerato-pharyngeus (middle constrictor of the pharynx). Syn.: hyo-pharyngeus. Thin muscle layer in the middle part of the pharynx. Origin: by two bundles: a) m. chondro-pharyngeus - hyoid bone - cornu minus and lig. stylo-hyoideum; b) m. cerato-pharyngeus - hyoid bone - cornu majus.
Ins.: posterior wall of the pharynx. N. vagus-rr. pharyngei. Blood supply. Action. Variations. Raises the head and tilts it slightly to its side. 1) Most often consists of two or three portions: medial-m. biventer cervicis, middle-complexus major in the narrow sense, and m. trachelo-occipitalis; 2) m. biventer may have three bellies; 3) the origin may descend to the VIII thoracic and rise to the I cervical vertebrae-their transverse processes; 4) in the same way, the origin from the spinous processes may either be absent entirely or descend to the V thoracic vertebra; 5) may fuse with m. longissimus dorsi and m. complexus minor. Raises the head and tilts it slightly to its side. 1) May be absent entirely; 2) may originate only from the VI and VII cervical vertebrae; 3) may consist of two independent bundles: one from the five lower cervical, and the other from the five upper thoracic; 4) may be a digastric bundle from the junction of m. complexus major and minor; 5) the insertion may extend to the occipital bone-linea nuchae superior. R. pharyngeus from a. pharyngea ascendens (a. carotis externa). Constricts the pharynx. 1) Individual bundles may extend into the wall of the esophagus-m. oesophageus (Meckel and Winslow) and into the thyroid gland (m. thyreo-adenoideus); 2) may be connected by additional small bundles with mm. sterno-hyoideus, thyreo-hyoideus, crico-thyreoideus, crico-arytaenoideus posterior, and with the trachea. R. pharyngeus from a. pharyngea ascendens (a. carotis externa). Constricts the pharynx. 1) Both bundles may be independent; 2) m. cerato-pharyngeus may be absent entirely; 3) there may be an accessory bundle from the cartilago triticea; 4) may be inseparable from m. constrictor pharyngis inferior, exchanging fibers with m. stylo-glossus and m. thyreo-hyoideus. No. Name in Latin and Russian. Synonyms. Form and position. Origin and insertion. Innervation and relation to segments. Constrictor pharyngis superior: mm. salpingo-pharyngeus, pterygo-pharyngeus, bucco-pharyngeus, mylo-pharyngeus, and glosso-pharyngeus (superior pharyngeal constrictor). Syn.: cephalo-pharyngeus, gnatho-pharyngeus. A thin layer of muscle bundles in the upper part of the pharynx, originating from various points. Orig.: salpingo-pharyngeus-auditory tube; pterygo-pharyngeus-sphenoid bone-processus pterygoideus; bucco-pharyngeus-fascia bucco-pharyngea and raphe pterygo-mandibularis; mylo-pharyngeus-lower jaw-linea mylo-hyoidea; glosso-pharyngeus-tongue-m. transversus linguae. Ins.: posterior wall of the pharynx. N. vagus-rr. pharyngei. Coraco-brachialis (coracobrachial M.). Syn.: coracoideus, perforatus, levator humeri internus. Represents a more or less prismatic muscle bundle between the coracoid process of the scapula and the medial surface of the humerus; anteriorly it is to a significant degree covered by m. biceps. Orig.: scapula-processus coracoideus, its apex, together with the tendon of m. pectoralis minor and m. bicipitis brachii-caput coracoideum. Ins.: humerus-facies medialis humeri along the line of cristae tuberculi minoris, septum intermusculare mediale. N. musculo-cutaneus. CVI and VII. Coraco-brachialis inferior (inferior coracobrachial M.). [Variation.] See m. coraco-brachialis. Coraco-brachialis longus (long coracobrachial M.). [Variation.] See m. coraco-brachialis. Coraco-brachialis minor (short coracobrachial M.). Syn.: coraco-brachialis superior. [Variation.] See m. coraco-brachialis. Coraco-cervicalis (coracocervical M.). See m. omo-hyoideus. [Variation.] Coraco-clavicularis singularis anterior (Gruber). [Variation.] See m. pectoralis minimus. Coraco-radialis (Krause) (coracoradial M.). [Variation.] Orig.: scapula-processus coracoideus. Ins.: radius. See m. biceps brachii. Coraco-ulnaris (Krause) (coracoulnar M.). [Variation.] See m. biceps brachii. Orig.: scapula-processus coracoideus. Ins.: ulna. Corrugator labii inferioris (Santorini) (M. wrinkling the lower lip). Syn.: protrusor labii inferioris. Fibers which run from the skin of the chin or the fascia of m. quadratus labii inferioris to the medial edge of m. triangularis. Corrugator supercilii (M. wrinkling the eyebrow). Syn.: corrugator glabellae, frontalis verus, corrugator Coiteri. A small muscle bundle in the medial half of the eyebrows, located just under the skin. Orig.: frontal bone-sutura fronto-maxillaris, glabella, and arcus superciliaris. Ins.: skin of the eyebrow (caput supercilii) and galea aponeurotica. N. facialis-r. temporalis. Costo-deltoideus (costodeltoid M.). Syn.: acromio-clavicularis lateralis, costo-acromio-clavicularis, tensor fasciae deltoideae a margine axillare scapulae. [Variation.] Orig.: scapula-margo axillaris. Ins.: m. deltoideus or its aponeurosis. Blood supply. Action. Variations. R. pharyngeus from a. pharyngea ascendens (a. carotis externa). Constricts the pharynx. 1) Individual bundles may be more or less independent; 2) bundles of mm. mylo-pharyngei and bucco-pharyngei may be rudimentary; 3) the points of origin of individual bundles may shift: a) pterygo-pharyngeus may originate only along the upper or lower edge of the laminae internae processus pterygoidei or even only on the hamulus pterygoideus; this last one may be independent (m. pterygo-pharyngeus extrinseque-Cruveilhier); mylo-pharyngeus may represent the most external fibers of m. mylo-hyoideus; glosso-pharyngeus-continuation of m. hyo-glossus, m. genio-glossus, and m. transversus linguae. Aa. circumflexae humeri anterior and posterior. Moves the arm forward, upward, and [medially].
of the midline, from the axillary artery: 1) Very rarely absent entirely; 2) the attachment may begin from the shoulder joint; 3) the upper part of the muscle may be independent—this is the m. coraco-brachialis minor or superior; its shape, size, and attachment may vary; it may attach: a) to the surgical neck; b) to the crest of the lesser tubercle; c) to the medial intermuscular septum; d) to the tendon of the m. latissimus dorsi (m. levator tendinis m. latissimi dorsi—Gruber); e) to the tendon of the m. subscapularis; f) to the capsule of the shoulder joint; 4) the middle part of the muscle may be independent—this is the m. coraco-brachialis medius; it may very rarely be absent entirely, be pierced by the musculocutaneous nerve or be divided by it into two portions, and it may merge with the m. brachialis, its medial part; 5) the lower part of the muscle may be independent—this is the m. coraco-brachialis inferior or longus; it may reach the medial epicondyle of the humerus. The angular artery from the axillary artery, the frontal branch from the superficial temporal artery, and the supraorbital artery from the ophthalmic artery. Wrinkles the brow: 1) Not very rarely absent; 2) often not sharply separated from the m. orbicularis oculi; 3) the origin may vary along the extent up to the trochlear fovea and up to the supraorbital foramen; 4) a tendinous connection of both antimers has been observed. Described by several anatomists, this muscle varies in its shape (round or flat), in its composition (many or few muscle fibers), in its distinctness, in its origin along the axillary margin, and in its attachment (sometimes up to the scapula and to the outer edge of the clavicle).
No. Name in Latin and Russian. Synonyms. Shape and position. Origin and attachment. Innervation and relation to segments. Costo-coracoideus (costo-coracoid muscle). [Variation.] See m. latissimus dorsi. Costo-fascialis (Quain) (costo-fascial muscle). [Variation.] A bundle which goes from the m. sterno-hyoideus to the cervical fascia. Costo-fascialis cervicalis (Macalister) (cervical costo-fascial muscle). [Variation.] Origin: first rib. Attachment: endothoracic fascia. Cremaster (muscle raising the testicle). Synonyms: cremaster externus, suspensorium testis, tunica carnea testis, s. cremasterica, s. erythroides, s. vasculosa, s. virilis testis musculus, suspensorius. Origin: separate bundles from the m. transversus abdominis and m. obliquus abdominis internus, from the upper edge of the inguinal ligament, and from the anterior wall of the sheath of the m. rectus abdominis. Attachment: around the testicle. Innervation: genitofemoral nerve—external spermatic nerve, L1 and L2. Cremaster internus (internal muscle raising the testicle). Name for the smooth muscle fibers of the tunica vaginalis communis. Crico-arytaenoideus lateralis (lateral crico-arytenoid muscle). A small, more or less triangular bundle on the lateral wall of the larynx. Origin: cricoid cartilage—arch of the cricoid cartilage and the median cricothyroid ligament. Attachment: arytenoid cartilage—muscular process of the arytenoid cartilage. Innervation: vagus nerve—inferior laryngeal nerve (anterior branch). Crico-arytaenoideus posterior (posterior crico-arytenoid muscle). Synonym: crico-arytaenoideus posticus. A small fan-shaped muscle on the posterior surface of the cricoid cartilage. Origin: cricoid cartilage—lamina of the cricoid cartilage. Attachment: arytenoid cartilage—muscular process of the arytenoid cartilage. Innervation: vagus nerve—inferior laryngeal nerve (posterior branch). Crico-hyoideus (crico-hyoid muscle). [Variation.] See m. thyreo-hyoideus. Crico-oesophageus anterior, medius and lateralis (crico-esophageal muscles). Muscle fibers to the esophagus. Crico-thyreoideus: pars recta and pars obliqua (cricothyroid muscle). Synonym: crico-thyreoideus anticus. A relatively large muscle, consisting of two bundles and located on the lateral surface of the thyroid cartilage. Origin: cricoid cartilage—arch of the cricoid cartilage. Attachment: thyroid cartilage—thyroid lamina in two portions. Innervation: vagus nerve—superior laryngeal nerve (external branch). Crico-thyreoideus internus (internal cricothyroid muscle). Synonym: crico-thyreoideus superior. A small muscle bundle located medial to the m. crico-thyreoideus. Origin: cricoid cartilage—external surface of its arch. Attachment: thyroid cartilage—its inferior margin. Innervation: vagus nerve—superior laryngeal nerve (external branch). Deltoideus: portio clavicularis, portio acromialis, portio spinata (deltoid muscle). Synonyms: deltoides, elevator, s. extensor, s. attollens humeri. The muscle has a triangular outline, the base of the triangle begins from the girdle of the upper limb (clavicle and scapula), and the apex of the triangle attaches to the humerus; the entire mass of the muscle represents a semi-cone consisting of interlacing muscle bundles; it covers the shoulder joint and lies on the mm. supraspinatus, infraspinatus, teres major, biceps brachii, and coraco-brachialis, partially covering them, and is covered from the outside only by the superficial fascia of the arm and the skin. It usually consists of three more or less independently originating portions, then merging into one muscle. Origin: portio clavicularis: clavicle—acromial extremity, its anterior edge; portio acromialis: scapula—acromial process; portio spinata: scapula—spine of the scapula, its lower edge and sometimes the infraspinatus fascia. Attachment: humerus—deltoid tuberosity. Innervation: axillary nerve, C(IV), V and VI. Blood supply: posterior circumflex humeral artery and thoraco-acromial artery from the axillary artery, deltoid branch of the deep artery of the arm from the brachial artery. Action: All three portions together abduct the arm to a horizontal position (abduction); the portio clavicularis abducts forward (anteversion) and rotates slightly inward (pronation); the portio acromialis abducts outward (abduction); the portio spinata abducts the arm backward, but only to 45° (according to Duchenne) (retroversion) and rotates outward (supination). Variations: 1) The portio clavicularis and portio acromialis may be partially or completely absent: Gruber once saw a gap four fingers long and two fingers wide instead of the portio acromialis; 2) Very often the portio clavicularis is independent—m. delto-clavicularis; less often the portio spinata is isolated—m. delto-spinalis, s. deltoideus posterior; cases of division of the muscle into a larger number of bundles have been observed; 3) sometimes an additional bundle exists along the posterior edge: from the infraspinatus fascia—m. infraspinatus deltoideus, from the vertebral margin of the scapula—m. basio-deltoideus, or from the axillary margin—m. costo-deltoideus; in one case such a bundle went over the portio spinata to the superficial deltoid fascia; 4) connections with neighboring muscles are observed; usually—a close connection of its terminal tendon with the tendon of the m. pectoralis major and m. brachialis, less often with the m. trapezius; occasionally the m. brachio-radialis may reach the deltoid tuberosity and connect with the m. deltoideus by means of muscle or tendinous fibers; 5) in isolated cases, the following were observed: an additional bundle from the spine of the scapula to the middle third of the brachial fascia; a bundle from the musculus...
Latin and Russian name. Synonyms. Form and position. Origin and insertion. Innervation and relation to segments. Blood supply. Action. Variations. Depressor auriculae (Lauth) (M., depressing the auricle). Syn.: stylo-auricularis, auriculo-glossus. A small muscle bundle, described several times. Origin: cartilaginous part of the external auditory canal. Insertion: temporal bone - processus styloideus or m. stylo-glossus or cervical fascia. Depressor septi nasi (M., depressing the nasal septum). Syn.: depressor septi mobilis narium, s. apicis naris, m. nasalis labii superioris, naso-labialis. Origin: m. orbicularis oris. Insertion: skin of the nasal septum. Innervation: N. facialis. Depressor supercilii (Lesshaft) (M., depressing the eyebrow). Syn.: depressor palpebrarum, s. capitis supercilii, dilatator superior sacci lacrimalis, m. superciliaris medialis. Medial fibers of pars palpebralis superioris, which rise upward to the root of the eyebrow. Innervation: N. facialis. Depressor supercilii lateralis (lateral M., depressing the eyebrow). [Variation.] Isolated fibers of m. orbicularis oculi, departing from the lateral side of pars palpebralis. Depressor urethrae muliebris (Santorini). Part of the fibers of m. transversus perinei profundus. Dermo-scrotalis (Sebileau). Part of the muscle fibers of the scrotum. Detrusor urinae (constrictor of the urinary bladder). Outer layer of tunicae muscularis vesicae urinariae. Innervation: Plexus sacralis. Diaphragma: pars sternalis, pars costalis, pars lumbalis (diaphragm or thoraco-abdominal M.). Syn.: diaphragmaticus, phrenicus, septum transversum, interseptum. It is a thin muscle plate, in the center of which is a tendinous plate; muscle fibers are divided according to their origin into sternal, costal, and lumbar parts; the lumbar part consists on each side of three crura: medial, intermediate, and lateral; the diaphragm has the shape of an irregular dome, with a somewhat lowered tendinous center, located between the thoracic and abdominal cavities, with its convexity facing the thoracic cavity. Origin: pars sternalis - sternum - processus xiphoideus, its posterior surface; pars costalis: from the VII to the XII rib - their inner surface; pars lumbalis: crus mediale - XII thoracic and lumbar vertebrae (up to III on the right and up to IV on the left) - their bodies and lig. longitudinale anterius; crus intermedium - II lumbar vertebra, its body; crus laterale - from the arcuate ligaments of Haller. Insertion: tendinous center - centrum tendineum diaphragmatis. Innervation: Nn. phrenici and nn. intercostales (VII-XII). CIV and V. Blood supply: Aa. vesicales superiores and inferiores. Action: Depresses the tendinous center of the thoraco-abdominal barrier. Variations: 1) Complete absence of the diaphragm was observed only in severe deformities, most often in anencephalia; occasionally partial developmental defects are observed in the form of non-fusion of parts (asyntaxia) between pars lumbalis and costalis; 2) lumbar bundles can descend lower and pass into the fascia of mm. psoatis and quadrati lumborum, reach the crista iliaca, to the aponeurosis of m. transversi abdominis; 3) aberrant bundles are very often observed: to the duodenum - m. suspensorius duodeni (Treitz), to the stomach - m. phreno-gastricus, to the flexura duodeno-jejunalis, to the peritoneum (faisceaux peritoneo-diaphragmatiques), to the tissue around the aorta, spleen, to the liver (m. diaphragmatico-hepaticus), to the esophagus (m. diaphragmatico-oesophageus), to the posterior mediastinum (m. diaphragmatico-retromediastinalis); 4) atypical muscle bundles are often observed in the tendinous center of the diaphragm, running in different directions. Diaphragmatico-hepaticus (diaphragmo-hepatic M.). [Rare variation.] See m. diaphragma. Diaphragmatico-oesophageus (diaphragmo-esophageal M.). [Very rare variation.] See m. diaphragma. Diaphragmatico-retromediastinalis (diaphragmo-posterior mediastinal M.). [Very rare variation.] See m. diaphragma. Digastricus mandibulae: venter anterior and venter posterior (digastric M. of the lower jaw). Syn.: digastricus maxillae inferioris, s. ossis hyoidei, digastrico-myloideus, biventer mandibulae, s. ossis hyoidei, deprimens biventer. The M. consists of two more or less cylindrical bellies, connected to each other at an angle by means of an intermediate tendon, which is connected to the hyoid bone. The M. is located between the lower jaw, the hyoid bone, and the mastoid process of the temporal bone; the posterior belly touches m. stylo-hyoideus, m. stylo-glossus, nn. glosso-pharyngeus, vagus and hypoglossus, a. carotis and v. jugularis interna; the M. lies on m. mylo-hyoideus and is covered by m. platysma, fascia superficialis and skin. Origin: venter anterior: lower jaw - fossa digastrica; venter posterior: temporal bone - incisura mastoidea. Insertion: hyoid bone - corpus and cornu majus ossis hyoidei. Innervation: Venter anterior: n. trigeminus, n. mandibularis (its r. mylo-hyoideus); venter posterior: n. facialis, its r. digastricus. Dilatator ani (M., dilating the anal opening). Lower medial bundles of the lower end of the longitudinal muscle layer of the rectum. Dilatator ani internus (internal M., dilating the anal opening). Lower end of laminae mucosae of the rectum. Dilatator canaliculorum lacrimalium (dilator of the lacrimal canaliculi). Muscle fibers of partis lacrimalis m. orbicularis oculi, which end in the lacrimal canaliculi. Dilatator pupillae (dilator of the pupil). Syn.: membrana pigmenti iridis, lamina pigmenti iridis. Radially arranged smooth muscle fibers of the iris. Innervation: Plexus ciliaris sympathicus. Dilatator pylori (dilator of the stomach outlet). Muscle fibers of the longitudinal muscles of tunicae muscularis ventriculi. Dorsi-axillaris (Macalister) (dorso-axillary M.). Muscle fibers in the axillary cavity, see m. latissimus. Dorso-epitrochlearis (fourth ulnar M.). Syn.: latissimo-condyloideus, anconaeus quintus. [Rare M.] See m. latissimus. Dorso-fascialis (dorso-fascial M.). [Rare variation.] See m. trapezius. Epicranius (cutaneous M. of the head). Syn.: cranii cutaneus, occipitofrontalis, capitis. Consists of a tendinous plate - galea aponeurotica, into which muscle bundles are woven: m. frontalis, proceri, occipitalis, auricularis superioris and auriculo-frontalis (see these muscles). Innervation: N. facialis. Epistropheo-basilaris (epistropheo-occipital M.). [Variation.] See m. longus capitis. Epitrochleo-anconaeus (Gruber) (brachio-ulnar M.). [Not rare variation (1:4)]. Syn.: epitrochleo-cubitalis, epitrochleo-olecranius, olecrano-epitrochlearis, anconaeus trochlearis, s. quintus, s. sextus, s. minimus, s. parvus. Insignificant muscle fibers, on the medial half of the posterior surface of the elbow joint under the skin, under an accumulation of fat and under the superficial aponeurosis. Origin: humerus - epicondylus medialis humeri.
Att.: ulna-olecranon ulnae N. ulnaris-its branch Blood supply j Action Variations A. lingualis and a. submentalis (anterior belly), a. occipitalis and a. auricularis posterior (posterior belly) Raises the hyoid bone The M. is subject to very frequent and diverse variations. 1) Venter anterior may be absent; 2) between both anterior bellies there may be various accessory bundles: mm. mentohyoideus, digastricomyloideus, interdigastricus; 3) from the angle of the mandible an additional bundle may run to the lateral edge of the venter anterior or to the fascia suprahyalis or to the intermediate tendon-this is m. accessorius ad digastricum; 4) venter anterior may consist of two layers: superficial and deep; this is m. trigastricus; it may end in the fossa digastrica of its own or the opposite side, in the aponeurosis of m. mylohyoideus, on the os hyoideum; 5) the anterior bellies may fuse with each other; 6) venter posterior may originate from the processus styloideus, linea nuchae superior, from m. splenius, m. trapezius; 7) it may not cross m. stylohyoideus; 8) there may be an inscriptio tendinea on the M.; 9) it may attach to the angle of the jaw-m. mastoideomaxillaris; 10) there are cases of duplication; 11) a bundle may run from the M. to m. stylopharyngeus; 12) if only tendinous fibers remain from the venter posterior, then this is m. mentohyoideus transversus Circulus arteriosus iridis-anastomosis of the branches of aa. ciliares posteriores longae and anteriores Dilates the pupil [ j Blood supply, see individual muscles Moves the hairy part of the scalp (see individual muscles) i i Brings the olecranon closer to the medial epicondyle of the humerus The M. is variable in its shape (a ribbon, or a small cylinder, or spindle-shaped, or triangular, or even digastric), in its dimensions (up to 55 mm), in the proportions between muscular and tendinous elements, but it is always well separated from neighboring muscles No. Latin and Russian name. Synonyms. Shape and position Origin and attachment Innervation and relation to segments Extensor carpi radialis brevis (short radial extensor of the wrist). Syn.: extensor carpi rectus, radialis externus brevis, s. secundus. Prismatic belly of the M. on the dorsal surface of the forearm along its lateral edge, partly immediately under the skin, partly covered by mm. extensor carpi radialis longus; its tendon on the forearm is covered by m. abductor pollicis longus and extensor pollicis longus Orig.: humerus-epicondylus lateralis humeri, lig. collaterale laterale and lig. annulare radii. Att.: III metacarpal bone, its base, also sometimes II N. radialis-r. profundus. C(v), VI and VII Extensor carpi radialis longus (long radial extensor of the wrist). Syn.: extensor adductoris, radialis externus longus, s. primus. The M. has a rather large flat spindle-shaped belly and a very long tendon; the belly is located immediately under the skin along the lateral edge of the elbow on the dorsal side, lying adjacent to m. brachioradialis and covered partly by m. extensor carpi radialis brevis; the tendon on the forearm is covered by mm. brachioradialis, abductor pollicis longus and extensor pollicis longus Orig.: humerus-margo lateralis humeri, epicondylus lateralis and septum intermusculare laterale. Att.: II metacarpal bone, its base N. radialis, r. profundus. C(V), VI and VII Extensor carpi ulnaris (ulnar extensor of the wrist). Syn.: extensor adductorius, s. cubitalis posterior, s. epicondylicus, s. ulnaris externus. The long spindle-shaped belly of the M. lies along the medial edge of the dorsal surface of the forearm immediately under the skin and lies adjacent on the lateral side to m. extensor digiti minimi proprius, covering partly the origin of both it and m. extensor indicis proprii; its short tendon is visible under the skin along the medial edge of the back of the hand Orig.: humerus-epicondylus lateralis humeri, lig. collaterale, ulna-margo dorsalis ulnae and fascia antibrachii. Att.: V metacarpal bone-tuberositas ossis metacarpalis V N. radialis-r. profundus. C(VI), VII and C(VIII) Extensor digiti minimi proprius (proper extensor of the little finger of the hand). Syn.: extensor digiti quinti proprius. The elongated spindle-shaped belly lies on the dorsal surface of the forearm in its lower half, between m. extensor carpi ulnaris and m. extensor digitorum communis, immediately under the skin; its tendon lies along the medial edge of the dorsal surface of the hand Orig.: humerus-epicondylus lateralis humeri, lig. collaterale laterale, lig. annulare radii and fascia antibrachii. Att.: dorsal aponeurosis of the fifth finger N. radialis-r. profundus. Cv, VI and VII Extensor digitorum brevis manus (Gruber) (short extensor of the fingers of the hand). Syn.: maniaeus, extensor brevis digiti indicis, vel medii, indicator anomalus brevis et extensor brevis anomalus medii digiti, pediaeus manus, extensor brevis digitorum, extensor brevis proprius s. lateralis medii digiti. Not a very rare muscle (1 in 10 or 1 in 15), of diverse shape Orig.: radius. Att.: most often to the index finger, and also to the middle and fourth fingers N. radialis-r. profundus Extensor digitorum communis (manus) (common extensor of the fingers of the hand). Syn.: extensor digitorum radialis. The large spindle-shaped bipennate belly of this M. lies in the middle part of the dorsal surface of the forearm between m. extensor carpi ulnaris and extensor digiti minimi proprius on the medial side and mm. extensores carpi radiales longus and brevis on the lateral side, immediately under the fascia antibrachii and the skin; its tendon in the lower part is covered by m. abductor pollicis longus and m. extensor pollicis brevis Orig.: humerus-epicondylus lateralis humeri, lig. collaterale laterale, lig. annulare radii and fascia antibrachii. Att.: II-V fingers, their dorsal aponeurosis N. radialis-r. profundus. C(VI), VII and VIII Extensor digitorum longus (pedis) (long extensor of the fingers of the foot). Syn.: extensor digitorum communis longus pedis, Orig.: tibia-condylus lateralis tibiae and fibula-capitulum and crista N. ischiadicus-n. peronaeus profundus Liv and V and Si Blood supply Action Variations A. collateralis radialis from a. profunda brachii and a. recurrens from a. radialis Dorsal extension of the wrist 1) An accessory tendon may depart from the muscle tendon to m. extensor carpi radialis longus, i.e., the muscle also attaches to the base of the II metacarpal bone; 2) cases of intermediate fibers to m. extensor carpi radialis longus are possible-this is m. extensor carpi radialis intermedius (Wood); 3) usually the M. originates together with m. extensor carpi radialis longus, but cases of fusion of both M. are observed to a greater or lesser extent up to complete fusion into one M.: the described cases of absence of this M. are explained by their complete fusion; 4) cases of duplication have been observed A. collateralis radialis from a. profunda brachii and a. recurrens from a. radialis Extends the wrist and abducts it in the radial direction, and in addition flexes the arm at the elbow joint 1) Accessory tendons are frequent: to mm. abductor pollicis brevis, interosseus dorsalis and volaris I, to the base of the first metacarpal bone, to os multangulum majus; 2) cases are possible when five heads of m. extensoris radialis are present; 3) a case of the formation of an intermediate tendinous connection with m. abductor pollicis longus is known.
For other variations, see musculus extensor carpi radialis brevis. Arteria interossea dorsalis. Slight dorsal flexion (extension) of the hand, but mainly abduction to the ulnar side, and in addition flexion of the arm at the elbow joint. 1) Partial fusion with musculus triceps brachii, anconaeus, extensor digiti quinti, and abductor digiti quinti is observed; 2) there may be a doubling of the muscle belly and attachment to the IV and V metacarpals; 3) often (1:8) there exists a dorsal accessory tendon, which attaches to the articulatio metacarpo-phalangea V—musculus ulnaris digiti quinti (Macalister). Arteria interossea dorsalis. Extension of the little finger. 1) Complete absence is apparently possible; 2) an additional origin from the dorsal surface of the ulna has been observed; 3) rarely, there is a division of the tendon into two, three, or four heads; even more rarely, a doubling of the muscle belly along its entire length is encountered; 4) fusion with the tendon to this finger from musculus extensor digitorum communis is observed; 5) attachment to the radius is observed (1 time per 10 cadavers). The form of the muscle is very diverse: 1) once, 4 tendons were observed—to the II, III, and IV fingers and to the dorsal surface of the fifth metacarpal bone; 2) cases with three tendons have been described; 3) more often, two tendons were observed—to the II and III fingers; 4) finally, a single tendon may go either to the II, or to the III, or to the IV fingers. Arteria interossea dorsalis. Dorsal flexion (extension) of the fingers and hand. 1) The number of tendons is very variable; usually 4, but it can rise to 12 and fall to 3 due to the absence of a tendon for the index finger or for the little finger; 2) there may also be an accessory tendon for the thumb; 3) the muscle belly for the index finger may have greater independence; 4) the belly for the little finger may be absent; 5) division of the muscle belly into two, three, and even four independent bundles is possible; 6) variations of the connecting tendons are very frequent. Arteria tibialis anterior. Dorsal flexion (extension) of the entire foot rather than of individual toes. 1) The number of tendons and their attachment sites on the dorsal surface can significantly increase and even double; in places 523
HUMAN MUSCLES
Latin and Russian name. Synonyms. Form and position. Origin and insertion. Innervation and relation to segments. Blood supply. Action. Variations. Extensor digitorum pedis longus (long extensor of the toes). Syn.: extensor digitorum pedis sublimis, s. digitorum tibialis. The long muscle belly lies on the lateral-anterior surface of the lower leg in a narrow space between m. tibialis anterior on the medial side and m. peronaeus longus on the lateral side, covered anteriorly by fascia cruris and skin; the tendon, having started along the anterior surface of the muscle, divides on the foot in the form of an aponeurotic plate into four terminal tendons. Origin: fibula, membrana interossea, its upper quarter, septum intermusculare anterius and fascia cruris. Insertion: II-V toes, their dorsal aponeurosis and os metatarsale V and IV in the form of m. peronaeus tertius. Extensor digitorum pedis brevis (short extensor of the toes). Syn.: pediaeus, pedilus. A small common belly lies on the lateral part of the dorsum of the foot immediately under the skin, crossed only by the tendons of m. extensor digitorum longus; its tendons are also covered by the tendons of the long extensor of the toes. In the closest connection with it stands m. extensor hallucis brevis. Origin: calcaneus-corpus calcanei, its dorsal surface, before the entrance to sinus tarsi and lig. cruciatum, its lateral part. Insertion: by three tendons to the dorsal aponeuroses of the II-IV toes. Innervation: n. peronaeus profundus. LIV and V and SI. Extensor hallucis brevis (short extensor of the big toe). Syn.: extensor primi internodii hallucis. Represents a medial bundle of m. extensor digitorum brevis that has become more or less independent. Origin: calcaneus-corpus calcanei, its dorsal surface, before the entrance to sinus tarsi, and lig. cruciatum, its lateral part. Insertion: big toe-proximal phalanx. Innervation: n. ischiadicus-n. peronaeus profundus. LIV and V and SI. Extensor hallucis intermedius (intermediate extensor of the big toe). [Variation.] Origin: fibula, membrana interossea, distal to the origin of m. extensoris hallucis longi. Insertion: tendinous to m. extensor hallucis brevis at the level of articul. cuneo-metatarsalis I. Extensor hallucis longus (long extensor of the big toe). A small muscle belly lies in the middle and lower third of the lower leg between m. tibialis anterior and m. extensor digitorum longus; its tendon on the dorsum of the foot is clearly visible under the skin along the medial edge of the foot. Origin: fibula-facies medialis, its two middle quarters and membrana interossea. Insertion: first toe-its distal phalanx. Innervation: n. ischiadicus-n. peronaeus profundus. LIV, V (SI). Extensor indicis proprius (proper extensor of the index finger). Syn.: extensor digitorum manus profundus, indicator, indicatorius, abductor indicis. A narrow, long, spindle-shaped belly located on the forearm under m. extensor digitorum communis, next to m. extensor pollicis longus, and the long tendon passes along the back of the hand in a transverse direction. Origin: ulna-facies dorsalis ulnae, its distal third. Insertion: index finger, its dorsal aponeurosis. Innervation: n. radialis-r. profundus. CVI, VII and VIII. Extensor pollicis brevis (short extensor of the thumb). Syn.: extensor pollicis minor, s. primi internodii pollicis. A small muscle ribbon located in the lower part of the forearm along its lateral edge of the dorsal surface, partly covered by superficial extensors, partly directly under the skin; its tendon forms the radial border of the "snuffbox" together with m. abductor pollicis longus. Origin: ulna-crista ulnae and membrana interossea, radius-facies dorsalis radii. Insertion: first toe-its proximal phalanx. Innervation: n. radialis-r. profundus. C(VI), VII and CVIII. Extensor pollicis longus (long extensor of the thumb). Syn.: extensor pollicis major, s. tertius, s. secundi internodii pollicis. Origin: ulna-crista ulnae, membrana interossea and radius-facies dorsalis radii. Insertion: big toe-distal phalanx by means of the dorsal aponeurosis. Innervation: n. radialis-r. profundus. C(VI), VII and VIII. Blood supply: a. tarsea lateralis from a. dorsalis pedis and r. perforans from a. peronaea. Action: dorsal flexion (extension) of the II-IV toes at the articulatio metatarso-phalangea. Variations: 1) ossa metatarsalia and articulationes metatarso-phalangeae can serve as insertion; 2) division of the muscle was observed: a) into two parts: medial-for the II and III toes and lateral for the IV and V toes; b) into two parts: one for the II, III and IV toes, and the other merged with m. peronaeus tertius; c) into four independent bundles; 3) m. peronaeus tertius represents an independent part of this muscle, attaching to os metatarsale IV and V; 4) tendons from m. extensor digitorum to m. extensor hallucis longus were observed; 5) fusions with m. extensor hallucis longus are possible; intermediate bundles to m. tibialis anterior, to m. extensor hallucis brevis, to m. extensor digitorum brevis pedis; 6) aponeurotic bridges between the tendons of the muscle were observed. Blood supply: a. tarsea lateralis from a. dorsalis pedis and r. perforans from a. peronaea. Action: dorsal flexion of the big toe (extension). Variations: 1) Very rarely may be absent; 2) may rarely have five tendons; 3) more often there are four tendons; 4) rarely cases with two and one tendons were observed; 5) closer relations with the tendon of m. extensoris digitorum communis and with mm. interossei are possible; 6) displacements are often observed: a) of the origin to one of the ossa cuneiformia, cuboideum or the proximal ends of the ossa metatarsalia; b) insertion not to the aponeuroses, but to the phalanges; c) simultaneously both origin and insertion-various cases of underdevelopment of the muscle. Blood supply: a. tibialis anterior. Action: dorsal flexion (extension) of the big toe, but also extension of the entire foot and its pronation. Variations: Sometimes sends a small bundle to os metatarsale I. Blood supply: a. interossea dorsalis. Action: extends the index finger. Variations: 1) Rarely may be absent; 2) the muscle belly may be doubled; 3) the tendon may be double and triple; 4) the tendon may go to the III and IV fingers; 5) tendinous connections with the thumb or its extensor are possible. Blood supply: aa. interosseae volaris et dorsalis. Action: extends, and partly abducts the thumb. Variations: 1) May be absent altogether; 2) start only from the radius; 3) grow together with m. abductor pollicis longus; 4) the tendon may be double and head towards the distal phalanx. Blood supply: aa. interosseae volaris et dorsalis. Action: extends, and partly abducts the thumb. Variations: 1) The tendon of the muscle may receive an additional tendon from m. extensor digitorum communis, which can be considered more or less normal-m. ypsiloformis; 2) the tendon may give an additional tendon to the index finger. Latin and Russian name. Synonyms. Form and position. Origin and insertion. Innervation and relation to segments. A long muscle ribbon located in the lower part of the forearm, deep between m. extensor indicis proprius on the medial side and m. abductor pollicis longus on the lateral, under m. extensor digitorum longus; its tendon forms the ulnar border of the "snuffbox". Fixator baseos stapedis (muscle strengthening the base of the stapes). A microscopic muscle reinforcing the lig. annulare baseos stapedis. Origin: temporal bone-cavum tympani of its pyramid, fenestra vestibuli. Insertion: stapes-crus posterius stapedis. Flexor carpi radialis (radial flexor of the hand). Syn.: radialis internus, anterior, anticus, flexor manus radialis, palmaris major. A bipennate long flat muscle belly lies in the middle of the palmar surface of the forearm, covered only at the proximal end by lacertus fibrosus and m. palmaris longus, and further only by fascia antibrachii and skin; the long tendon in the distal third of the forearm is located most radially of all flexors. Origin: humerus-epicondylus medialis humeri, septa intermuscularia and fascia superficialis antibrachii. Insertion: second metacarpal bone, the palmar surface of its base. Innervation: n. medianus. CVI, VII and C(VIII). Flexor carpi radialis brevis (Wood) (short radial flexor of the hand). Syn.: radialis internus brevis, profundus, minor. [Not an infrequent variation (1 in 20).] The shape, size and position are very variable. Origin: radius-facies lateralis or anterior in the middle third. Insertion: bones of the metacarpus or carpus or ligamentum carpi transversum. Flexor carpi ulnaris; caput humerale and caput ulnare (ulnar flexor of the hand). Syn.: ulnaris internus, cubitalis internus. The muscle, starting with two heads, represents a long muscle belly with a strong terminal tendon; it occupies the ulnar edge of the forearm, lying under fascia antibrachii and skin; it borders m. flexor digitorum sublimis on the lateral side and covers m. flexor digitorum profundus. Origin: caput humerale: humerus-epicondylus medialis humeri, septum intermusculare; caput ulnare: ulna-olecranon, facies dorsalis ulnae, its upper two thirds, and fascia antibrachii.
Ex.: pisiform bone and by means of the lig. piso-hamatum and piso-metacarpeum—the hamate and V metacarpal bones, N. ulnaris, and also sometimes the n. medianus. C(vii), VIII and Di Flexor digastricus indicis (digastric flexor of the index finger). [Variation.] See flexor digitorum sublimis and profundus Flexor digiti quinti brevis accessorius pedis (accessory short flexor of the fifth toe). See m. flexor digiti quinti brevis Flexor digiti quinti brevis manus (short flexor of the fifth finger). Syn.: flexor digiti minimi manus, s. proprius. A small flat muscular ribbon along the palmar surface of the hand next to the m. abductor digiti minimi on the medial side and the m. opponens digiti quinti on the lateral side, and immediately under the m. palmaris brevis and the skin. Origin: hamate bone—hamulus ossis hamati and lig. carpi transversum. Insertion: fifth finger, its proximal phalanx from the palmar surface. N. ulnaris. C(vii), VIII and Di Flexor digiti quinti brevis pedis (short flexor of the fifth toe). Syn.: flexor digiti minimi brevis. A small spindle-shaped bundle on the sole next to the m. abductor digiti V near the lateral edge of the foot. Origin: fifth metatarsal bone, its base, lig. plantare longum and the tendon sheath of the m. peronaei longi. Insertion: V toe, first phalanx, its base. N. plantaris lateralis. Si and II Flexor digitorum brevis pedis (short flexor of the toes). Syn.: flexor digitorum perforatus, s. sublimis, s. pediaeus, s. pedilus internus, pterno-dactyleus. Origin: calcaneus—tuber calcaneum, its lower surface and plantar aponeurosis, its proximal end. N. plantaris medialis. Lv and Si Blood supply Action Variations to the first phalanx of the thumb; once four tendons were observed: two to the ungual phalanx of the first finger and two to the lig. annulare; 3) closer relationships are possible: with the m. extensor indicis proprius—this is the m. extensor pollicis indicisque, m. extensor pollicis brevis, abductor pollicis longus; 4) duplications of the M. were observed. Branches of the a. radialis Flexes the hand and turns it inward (pronates). 1) Variations of the attachment site are most frequent: a) lig. carpi transversum; b) os naviculare; c) os multangulum majus; d) metacarpale II, III and IV; e) combinations of the previous; 2) the origin of the M. can be on the radius and ulna; 3) there may be additional bundles from the mm. biceps and brachialis; 4) it may be fused to a greater or lesser extent with the m. palmaris longus, pronator teres, flexor digitorum superficialis; 5) once an M. was observed with three origins: from the m. biceps, epicondylus medialis and processus coronoideus. Flexion of the hand. 1) The origin of the M. occupies different places on the radius, but in addition, individual fibers may originate: a) from the m. pronator teres; b) from the fascia antibrachii; c) from the m. flexor pollicis longus; d) from the ulna; e) from the epicondylus medialis; 2) the attachment may be: a) on the os carpi—m. radio-carpeus (Gruber); b) on the os metacarpi—m. radio-metacarpeus (Gruber); c) on the ossa carpi and metacarpi—m. radio-carpo-metacarpeus (Gruber); d) on the ligaments of the wrist or the palmar aponeurosis—m. carpo-palmaris (LeDouble). Aa. collateralis from the a. brachialis and a. ulnaris. Palmar and ulnar flexion. 1) Part of the fibers may be innervated from the n. medianus and constitute an additional belly, but the general mass of the M. may also have a double innervation; 2) the M. may attach to the lig. carpi volare, lig. carpi transversum, os metacarpale IV or III or to the articulatio metacarpo-phalangea digiti V, to the m. abductor digiti V; 3) absence of the caput ulnaris on both hands was observed once; 4) closer relationships with the m. palmaris longus and with the caput mediale m. tricipitis brachii are observed. R. volaris profundus from the a. ulnaris. Flexes the proximal phalanx of the little finger. 1) It may be completely absent; 2) it may fuse with the m. abductor and opponens digiti quinti; 3) it may have an additional tendon to the head of the metacarpalis V; 4) under the name m. flexor brevis digiti minimi accessorius, a small bundle has been described several times, located above the M. and originating from the aponeurosis of the forearm. A. plantaris lateralis. Flexes the little finger in the plantar direction and strengthens the longitudinal arch of the foot. 1) It may often be absent; 2) an additional belly from the lig. talo-naviculare was observed—m. flexor digiti quinti accessorius; 3) in the opinion of Le Double, incomplete and even complete fusion with the m. opponens digiti V is possible. A. tibialis posterior and a. plantaris lateralis and medialis. Plantar flexion of the toes. 1) Rarely, the M. may be absent; 2) closer relationships with neighboring M. are observed: a) with the m. adductor hallucis—pars obliqua; b) with the m. opponens hallucis; 3) there are additional [entries]. Name in Latin and Russian. Synonyms. Form and position. Innervation and relation to segments. Origin and attachment. A fairly thick muscular plate located on the arch of the foot directly above the aponeurosis plantaris; three or four terminal tendons split, allowing the tendons of the m. flexoris digitorum longi to pass through. Insertion: II, III and IV (V) toes, their middle phalanges. Flexor digitorum longus pedis (long flexor of the toes). Syn.: flexor digitorum profundus, s. perforans pedis, flexor tibialis. A unipennate long muscle belly lies on the entire medial surface of the lower leg along the posterior surface of the tibia, having the m. tibialis posterior on the lateral side, and the m. soleus behind and on the medial side. The tendon of the M., which began already in the lower third of the lower leg, crosses the tendon of the m. flexoris hallucis longi and m. tibialis posterioris on the foot, lies on the m. flexor digitorum brevis and divides into its 4 terminal tendons. Origin: tibia—facies posterior, from the linea poplitea to the epiphysis of the fibula, and the membranous arch between both bones. Insertion: II-V toes—their terminal phalanges. N. tibialis. Lv and Si. Flexor digitorum profundus (manus) (deep flexor of the fingers). Syn.: flexor digitorum perforans, s. communis profundus. A large, wide, but flat muscle belly lies on the entire palmar surface of the ulna and the interosseous membrane, and below also on the m. pronator quadratus, soon passing into a wide tendon, which divides on the palm into 4 terminal tendons; on the lateral side, the M. adjoins the m. flexor pollicis longus, and from above it is completely covered by the m. flexor digitorum sublimis. Origin: ulna—facies volaris ulnae, its proximal two-thirds, and membrana interossea, curves around the tuberositas ulnae and margo dorsalis ulnae, reaches the origin of the m. flexoris carpi ulnaris. Insertion: II-V fingers—terminal phalanges, their bases. N. medianus and n. ulnaris. Cvii, VIII and Di. Flexor digitorum sublimis: caput humerale and caput radiale (superficial flexor of the fingers). Syn.: flexor digitorum superficialis, s. perforatus, flexor digitorum secundi internodii. The peculiar form of this M. is due to the fact that, firstly, it merges from two heads—a long, humeral one for the III-V fingers and a shorter but wider, radial one for the index finger, that, secondly, individual muscle bundles lie in two layers: the outer for the III and IV and the deep for the II and V, and that, thirdly, there are beds on the M.: one for the m. palmaris longus, and the other for the m. flexor carpi radialis: both these M. almost completely cover it. The two tendons that began already on the forearm each divide on the hand into two (bifurcation); the terminal tendons allow the tendons of the m. flexoris digitorum profundi to pass through. Origin: caput humerale: humerus—epicondylus medialis humeri and ulna—processus coronoideus ulnae; caput radiale: radius along the oblique line medially and proximally from the attachment site of the m. pronator teres. Insertion: II-V fingers, middle phalanges, their lateral edges. N. medianus. Cvii, Cviii and Di. Flexor hallucis brevis: caput laterale and caput mediale (short flexor of the big toe). Syn.: flexor brevis pollicis pedis. Two small muscle ribbons on the os metatarsale I, adjoin the m. abductor hallucis on the lateral side and form a bed for the tendon of the m. flexoris hallucis longi. Origin: I (II and III) cuneiform bone, lig. calcaneo-cuboideum plantare, often also the tendon of the m. tibialis posterioris and the plantar aponeurosis. Insertion: caput laterale: big toe, its proximal phalanx, lateral sesamoid bone, tendon of the m. abductoris hallucis; caput mediale: big toe, its proximal phalanx, medial sesamoid bone, tendon of the m. abductoris hallucis. Caput laterale—n. plantaris lateralis; Si and II, Caput mediale—n. plantaris medialis;
Ly and Si Blood supply Action ch [ Variations bundles: a) tendinous bundle to os cuneiforme primum; b) to the first phalanx of the second toe A. tibialis posterior Flexes the toes, but also flexes, supinates, and adducts the entire foot This M. is subject to numerous variations, depending on its common origin with m. flexor hallucis longus and reducing to the following groups: 1) both M. can receive additional bundles: a) from m. flexor tibialis posticus; b) from fibula; c) from tibia; d) from fascia cruris; e) from condylus lateralis femoris; f) from the ligaments of the knee joint- m. accessorius longus; g) from os calcaneum-m. accessorius brevis; 2) various degrees of connection of these M. among themselves-not only their muscle bodies, but especially their terminal tendons; 3) isolation of certain bundles-m. flexor digiti secundi proprius for the second toe and m. flexor digiti V proprius for the fifth toe R. muscularis from a. ulnaris and a. interossea volaris Flexes the terminal phalanges of the II-V fingers 1) Independent bundles can be isolated for one or another finger, most often for the index finger (see m. flexor digastricus indicis), the latter bundle can be independent until its origin at the tuberositas ulnae: 2) separate bundles for the III-V fingers are often connected among themselves by thin long tendons, sometimes they serve for the origin of mm. lumbricalium; 3) there can be closer relations with mm. palmaris longus, flexor pollicis longus, flexor digitorum sublimis, lumbricales; 4) there can be an additional bundle: a) from processus coronoideus-m. accessorius ad flexorem profundum digitorum (Gantzer); b) from the radius below the attachment of m. pronator teres Branches of aa. radialis and ulnaris Flexes the middle phalanges of the II-V fingers 1) Absence of one or another head is observed, especially often for the little finger; 2) tendons may not split, but attach only to the radial edge of the middle phalanx; 3) caput radiale can have different degrees of development, can even be completely absent or go only to the IV-II fingers; 4) can merge with the more superficial layer; merge or replace m. palmaris longus, i.e., reach the aponeurosis palmaris, or with fascia antibrachii; or connect with mm. pronator teres, flexor carpi radialis, brachioradialis and very often with M. of the deeper layer: with m. flexor digitorum profundus or with m. flexor pollicis longus or with mm. lumbricales; 5) very often there exists an intermediate tendon to the head of m. flexoris digitorum profundi to the II finger-this is m. flexor digastricus indicis; 6) M. can rarely be divided into 4 separate bundles; 7) the tendon to the V finger can be absent and then a separate tendon for it continues into a muscle belly, originating from different places: ulna, m. flexor digitorum profundus, lig. carpi transversum, aponeurosis palmaris, etc.; 8) the tendon to the IV finger can be absent; 9) can be divided into 4 independent bundles along the entire length of the M.; 10) an independent bundle for the II or III or IV fingers can be isolated A. plantaris medialis and arcus plantaris Plantar flexion of the big toe 1) Often M. originates from the sheath of the tendon of m. tibialis posterioris No. Latin and Russian name. Synonyms. Form and position Origin and attachment Innervation and relation to segments Flexor hallucis intermedius (Frohse and Frankel) {intermediate flexor of the big toe}. [Variation.] Orig.: lower leg at the level on one side of lig. laciniatum, on the other- fascia profunda m. abductoris hallucis, calcaneus (by two separate bellies). Att.: sesamoid bones of the big toe Flexor hallucis longus (long flexor of the big toe). Syn. flexor digitorum fibularis, flexor digitorum pedis peronaeus, caput fibulare m. flexoris hallucis communis. A strong, rather large and long muscle belly lies on the posterior surface of the lower leg between m. tibialis posterior and mm. peronaei, in the depth it is covered by m. soleus; its tendon on the sole lies in the very depth under m. flexor digitorum brevis and between two layers of m. flexoris hallucis brevis Orig.: fibula-facies posterior, its lower two thirds, membrana interossea and septum intermusculare posterius. Att.: big toe, terminal phalanx, its base N. tibialis. Ly and Si and Sn Flexor pollicis brevis: caput superficiale and caput profundum (short flexor of the thumb). Syn.: caput superficiale-abductor internus; caput profundum-caput superficiale (Henle). M. consists of two small flat muscle ribbons, lying one above the other, separated from each other by the tendon of m. flexoris pollicis longi and forming the distal part of the elevation of the thumb (eminentia thenar) Orig.: caput superficiale: lig. carpi transversum; caput profundum: greater and lesser multangular and capitate bones and the first metacarpal bone, its base. Att.: articulatio metacarpo-phalangea pollicis and radial sesamoid bone Caput superficiale-n. medianus; caput profundum - n. ulnaris. CVI and VII Flexor pollicis longus: caput radiale and caput humerale (long flexor of the thumb). Syn.: flexor pollicis proprius longus, longissimus pollicis. A long unipennate flat M.-caput radiale, with a small narrow accessory ribbon-caput humerale, lies along the lateral edge of the forearm in the same layer as m. flexor digitorum profundus, covered from above by superficial flexors; its tendon, which began already on the forearm, passes on the palm between two layers of m. flexoris pollicis brevis Orig.: caput radiale: radius-facies volaris radii from tuberositas to the beginning of m. pronator quadratus and membrana interossea; caput humerale: humerus-epicondylus medialis humeri. Att.: thumb, terminal phalanx, its base N. medianus-n. interosseus volaris. Cvi, Frontalis (frontal M.). Syn.: epicranius frontalis, frontis Orig.: skin of the eyebrow and with the help of neighboring muscles os frontale, below the place of attachment of m. corrugatoris supercilii. Att.: galea aponeurotica N. facialis-rr. temporales Galea aponeurotica (tendinous helmet of the head). Syn.: galea tendinea aponeurotica, pericranium. Tendinous plate under the hairy part of the skin of the head, with which mm. frontalis, occipitalis, auricularis superior, auriculo-frontalis are connected Gastrocnemius: caput mediale and caput laterale (gastrocnemius M.). Syn.: gemelli surae, biceps surae. Two large fleshy heads-medial and lateral, of semi-oval shape, lie on the posterior surface of the lower leg, in its upper half, directly under the skin and fascia cruris and cover mm. plantaris, popliteus, soleus, and under the latter also mm. flexor digitorum longus, flexor hallucis longus and tibialis posterior; a long, thick, wide at the top and narrowing downwards tendon lies in the lower half of the lower leg just under the skin and fascia cruris Orig.: caput mediale: thigh-planum popliteum femoris, condylus medialis and the bursa of the knee joint; caput laterale: thigh-planum popliteum femoris, condylus lateralis and the bursa of the knee joint. Att.: calcaneus-tuber calcaneum-tendo calcaneus Achilli, together with m. soleus and m. plantaris N. tibialis. L(iv),v and Si and u Blood supply Action Variations A. peronea Flexes the big toe, in addition flexes the entire foot in the plantar direction, supinates and adducts it 1) From the tendon of the M. very often, on the foot at the place of its crossing with the tendon of m. flex. dig. longi (chiasma plantare), tendinous branches depart, heading along the course of the tendons of m. flexoris digitorum longi to the terminal phalanges of the II, III and (IV) toes, which is even considered the norm, and the description given above-a variation; 2) in case of absence of a bundle from m. flexor digitorum longus to the second toe, m. flexor hallucis longus gives a significant tendon to this toe; 3) rarely there is m. tensor vaginae mucosae m. flexoris hallucis longi, which departs from sustentaculum tali R. volaris superficialis and r. princeps pollicis from a. radialis and arcus volaris profundus Flexes the thumb 1) Cases of underdevelopment of one or another head are possible; 2) caput profundum can merge with m. adductor pollicis, abductor brevis and opponens Branches of a. radialis, ulnaris and interossea volaris Flexes the terminal phalanx of the thumb 1) Can merge: a) with m. flexor digitorum profundus; b) with m. sublimis; c) with both at once; d) with pronator teres; e) with m. brachialis; 2) not infrequently under it there is a special M.-m. radialis internus (Gruber) or m. flexor carpi radialis brevis (Frohse and Frankel), which attaches either to os carpale I or to os metacarpale I; 3) an additional bundle can exist from processus coronoideus- m. accessorius ad pollicem (Gantzer), which is closely connected with m. pronator teres; this additional bundle can vary in its development and in its relations with neighboring M.
A. supraorbitalis and a. lacrimalis from a. ophthalmica, r. frontalis from a. temporalis superficialis and a. angularis from a. maxillaris externa. Raises the skin above the eyebrows and the eyebrows themselves upwards. 1) Extremely rare complete underdevelopment of the M.; 2) various degrees of development of the M.; 3) various forms of its fusion with mm. corrugator supercilii, depressor supercilii and procerus are observed; 4) between m. frontalis and m. auricularis superior there may be muscle fibers—m. auriculo-frontalis; 5) once a muscular connection with m. occipitalis was observed (possibly via m. auriculo-frontalis); 6) a case of inscriptio tendinea in the muscle was observed. Aa. surales from a. poplitea. Flexes the foot in the plantar direction and supinates it; furthermore, it flexes the leg at the knee joint; with a fixed foot, it flexes the thigh backward (e.g., when sitting down on a chair). 1) The lateral head is occasionally absent or is rudimentary; 2) both heads may be separated from each other throughout their entire length; 3) they may have a tendon separate from m. soleus even along its entire length; 4) an os sesamoideum is observed in the caput mediale in isolated cases and in the caput laterale somewhat more often (1:6); 5) sometimes an additional bundle, m. gastrocnemius tertius, is observed, see below; 6) the medial head may give a bundle to the fascia cruris—m. tensor fasciae cruris. Name (Latin and Russian). Synonyms. Form and position. Origin and insertion. Innervation and relation to segments. Gastrocnemius tertius (third gastrocnemius M.). [Variation.] A small muscle bundle on the posterior surface of the thigh and under m. gastrocnemius on the lower leg. Origin: in various places—thigh—planum popliteum femoris or labium internum lineae asperae femoris or the sheath of the vasorum popliteorum and n. ischiadicus. Insertion: heel bone—tuber calcaneum—tendo calcaneus. Gemelli: superior and inferior (twin M.). Syn.: secundus and tertius quadrigemini, marsupium carneum, marsupiales externi. Two tiny spindle-shaped bundles above and below m. obturator internus. Origin: ischium—tuber ischiadicum. Insertion: thigh—fossa trochanterica. Branches from plexus sacralis. Liv and V and Si and II. Genio-epiglotticus (genio-epiglottic M.). Syn.: glosso-epiglotticus, elevator epiglottidis. Fibers of m. genio-glossus, which go to the base of the epiglottis. N. hypoglossus. Genio-glossus (genio-glossus M.). Syn.: expulsor linguae. Origin: lower jaw—spina mentalis mandibulae. Insertion: root of the tongue. N. hypoglossus. Genio-hyoideus (genio-hyoid M.). Syn.: geniohyalis. A small, spindle-shaped, but somewhat flattened bundle, located next to its pair on the neck under the chin, covered by skin and m. mylo-hyoideus and covering m. genio-glossus. Origin: lower jaw—spina mentalis mandibulae. Insertion: hyoid bone—corpus ossis hyoidei. N. hypoglossus. Genio-hyoideus superior (Ferrein) (superior genio-hyoid M.). The most posterior bundles of m. transversi linguae. Genio-pharyngeus (Winslow) (genio-pharyngeal M.). Part of the fibers of m. constrictoris pharyngis superioris. Glosso-palatinus (glosso-palatine M.). Syn.: palato-glossus, glosso-staphylinus, constrictor isthmi palatini. Origin: lateral edges of the base of the tongue. Insertion: merges with its antimere at the base of the uvula. N. vagus—rr. pharyngei. Glutaeus maximus (gluteus maximus M.). Syn.: glutaeus magnus, major. Represents one of the most massive M. of the body, which is surpassed only by a few M. (m. quadriceps cruris); it consists of coarse, more or less parallel bundles separated by connective tissue layers and has the shape of a wide, thick, but flattened rhombus: the M. continues on the posterolateral surface of the gluteal region into a wide aponeurotic plate, continuing into the broad ligament of the thigh; the M. lies in the gluteal region under the skin with a fat layer and fascia coxae, s. glutaea, covering all M. of this region, except for part of m. glutaei medii. Origin: ilium—below linea glutaea superior, sacrum—its lateral edge, coccyx, fascia lumbo-dorsalis and lig. sacro-tuberosum. Insertion: upper bundles: fascia lata, continue into tractus ilio-tibialis; lower bundles: thigh—tuberositas glutaea femoris. N. glutaeus inferior. Lv and Si and II. Glutaeus medius: pars superficialis and pars profunda (gluteus medius M.). Syn.: glutaeus secundus, iliacus externus. The M. consists of two layers—superficial and deep, having in general the shape of a flat, rather voluminous triangle, with the base facing the iliac crest and the apex directed toward the greater trochanter; the fibers converge into a tendon that is short on the outside and long on the inside. The M. is almost entirely covered by m. glutaeus maximus; only the upper part of the aponeurotic plate of the pars superficialis lies under the skin and fascia glutaea; in turn, the M. covers m. glutaeus minimus. Origin: pars superficialis: crista iliaca, fascia coxae; pars profunda: ilium—its outer surface between linea glutaea anterior and posterior. Insertion: thigh—trochanter major, its lateral and upper surface. N. glutaeus superior. LiV, V and Si. Blood supply. Action. Variations. 1) The M. may end in different places: a) in the medial, b) in the lateral head, c) in both heads of m. gastrocnemii, d) in its tendon; 2) it may originate from m. biceps femoris, m. semitendinosus, m. adductor magnus. A. glutaeus inferior. Rotates the thigh outward. 1) Often one or the other, less often both together, are absent; 2) gemellus inferior may sometimes be doubled; 3) gemellus superior may attach to the articulatio coxae; 4) the tendon of m. gemelli superioris may merge with the tendon of m. piriformis and m. obturator internus. Pulls the epiglottis upward and forward. Pulls the tongue forward. May send fibers: 1) to the epiglottis—m. genio-epiglotticus; 2) to the pharynx—in the space between os hyoideum and m. stylo-glossus; 3) to lig. stylo-hyoideum; 4) m. genio-glossus accessorius (Luschka)—a bundle from the very lowest part of the spina mentalis into the thickness of the muscle. A. thyreoidea superior and r. hyoideus from a. lingualis. Pulls the hyoid bone upward and forward. 1) Both antimeres may be fused; 2) very often there is an auxiliary bundle to the cornu majus; 3) there may be a fusion: a) with venter anterior m. digastrici; b) with m. mylo-hyoideus; c) with m. genio-glossus and m. hyo-glossus. A. glutaeus inferior from a. hypogastrica, a. circumflexa femoris medialis from a. femoralis and a. perforans prima from a. profunda femoris. Tenses the broad ligament of the thigh, abducts and extends the leg at the hip joint—when standing, it straightens the torso bent forward. No significant variations were observed. 1) Once, a division into two layers was observed along the entire length and once in its lower part; 2) the anterior edge of the M. rarely merges with m. tensor fasciae latae; 3) posteriorly, the M. sometimes also originates from the spinous processes of the lower lumbar vertebrae; 4) posteriorly, the M. may not have an origin on the lig. sacro-tuberosum or os sacrum or os coccygis; 5) the number of bundles constituting the M. is individually very variable. A. glutaeus superior from a. hypogastrica and a. circumflexa femoris lateralis from a. femoralis. When standing, it tilts the torso to its side. Abducts the free leg, but in addition, the anterior bundles rotate the thigh inward, and the posterior ones—outward. 1) It may fuse anteriorly: a) with m. glutaeus minimus; b) with m. piriformis, either in the form of intermediate bundles or in the form of complete fusion along the entire length; 2) several times a division into two layers was observed. Name (Latin and Russian). Synonyms. Form and position. Origin and insertion. Innervation and relation to segments. 177 Glutaeus minimus (gluteus minimus M.). Syn.: glutaeus minor, s. profundus, s. tertius. Represents a relatively thin muscular layer approximately in the shape of a triangle, with the base facing upward toward the iliac crest, and the apex downward, toward the greater trochanter; it lies on the ilium on the lateral part of its wing, adjoining m. piriformis posteriorly, covered partially by m. glutaeus medius and entirely by m. glutaeus maximus and tensor fasciae latae. Origin: ilium—its outer surface between linea glutaea anterior and inferior. Insertion: thigh—trochanter major, its anterior and upper surface. N. glutaeus superior. Liv, V and Si. Glutaeus quartus (fourth gluteal M.). Syn.: invector femoris, scansorius. A wide bundle near the anterior edge of m. glutaei minimi. Origin: ilium, near spina iliaca anterior superior. Insertion: thigh—trochanter major, anterior edge. Gracillimus oculi (Bochdalek) (delicate M. of the eye). Syn.: gracillimus orbitae, orbitalis, obliquus accessorius oculi. A thin small bundle, which sometimes accompanies the belly of m. obliqui superioris oculi and attaches in various places. 180 Gracilis (gracilis M.). Syn.: gracilis, internus, adductor gracilis, femoris internus. Represents a long, thin, narrow muscle ribbon, located on the medial surface of the thigh just under the skin and fascia lata; it covers all the adductor M. and lies anteriorly next to m. sartorius, and posteriorly next to m. semimembranosus. Origin: pubic bone—ramus descendens, its anterior surface, near symphysis ossium pubis.
Ex.: tibia-tuberositas tibiae and fascia cruris. N. obturatorius-anterior branch. L(n)in IV and V 1 181 Harlingi (Harling's muscle). [Variation.] A bundle from m. semimembranosus, which goes to m. adductor magnus. Helicis major (greater muscle of the helix of the ear). A long but narrow muscle bundle under the skin on the helix. Origin: auricle-helix-spina helicis. Insertion: auricle-eminentia fossae triangularis. N. facialis. Helicis minor (lesser muscle of the helix of the ear). A very small muscle bundle under the skin on the helix. Origin: auricle-helix, its rima helicis. Insertion: auricle-helix, its spina helicis. N. facialis. Hyo-fascialis (Gruber) (hyo-fascial muscle). [Variation.] See m. omo-hyoideus. Hyo-glossus: m. basio-glossus, cerato-glossus and chondro-glossus (hyo-glossal muscle). Three small bundles (the widest is basio-glossus), located between the hyoid bone and the root of the tongue on the sides of the neck, deep under the venter posterior of m. digastrici, m. mylo-hyoideus and on m. constrictor pharyngis superior. Origin: a) basio-hyoideus-hyoid bone-basis; b) cerato-hyoideus-cornu majus and c) chondro-glossus-cornu minus. Insertion: thickness of the tongue. N. hypoglossus. Hyo-trachealis (hyo-tracheal muscle). [Variation.] See m. thyreo-hyoideus. Iliacus: caput internum and externum (iliac muscle). Syn.: iliacus internus. A wide muscle layer along the entire inner surface of the iliac wings (caput internum) and from the anterior superior and inferior iliac spines to the medial surface of the upper part of the thigh. Here it is partly covered from the lateral side by m. sartorius, partly only by skin and fascia cruris; from the medial side it lies adjacent to m. pectineus. Origin: a) caput internum: ilium-fossa iliaca up to the linea terminalis; caput externum-spina iliaca anterior superior and inferior. Insertion: thigh-trochanter minor femoris and adjacent parts of the femoral shaft-linea aspera. Branches of the plexus lumbalis. LII and LIV. Ilio-appendicularis (Jonnesco and Juvara). Smooth muscle fibers of the plica ileo-caecalis. Blood supply. Action. Variations. A. glutaea superior from a. hypogastrica and a. circumflexa femoris lateralis from a. femoralis. Abducts the thigh. When standing, it tilts the pelvis, and consequently the torso, to its side. 1) Between m. glutaeus medius and minimus there may be a portion which is called m. invector femoris; 2) The muscle very rarely divides into two bundles: anterior and posterior; 3) the muscle often merges with m. piriformis; see glutaeus medius; 4) very rarely, additional bundles to mm. tensor fasciae latae and vastus externus have been observed; 5) several anatomists have observed an independent muscle under m. glutaeus minimus, attaching to the capsule of the hip joint-m. glutaeus quintus (Macalister). The muscle is met with not infrequently, but is variable in its relation to m. glutaeus minimus, in its dimensions and in its attachment: a) to trochanter major; b) to capsula articularis; c) to trochanter minor. A. pudenda externa and a. profunda femoris from a. femoralis and a. obturatoria from a. hypogastrica. Adducts the thigh; furthermore, it flexes the leg at the knee joint, and when flexed, rotates it outward. 1) It may sometimes send a tendon to the fascia lata in the distal third of the thigh; 2) it may be completely inseparable from mm. sartorius and vastus medialis in its lower part; 3) it may divide into several bundles at its origin; 4) the length and width of the muscle may vary individually. 1) It may sometimes be absent; 2) it may merge: a) with m. helicis minor; b) with m. tragi. It may merge with m. helicis major. A. pharyngea ascendens and branches of a. lingualis from a. carotis externa. Pulls the tongue downward (depresses the root). 1) All three of its main bundles may be independent; 2) a fourth from the cartilago triticea may join them-m. triticeo-glossus; 3) there is sometimes an additional bundle to m. sterno-thyreoideus. A. ilio-lumbalis from a. hypogastrica and a. circumflexa ilium profunda from a. iliaca externa. Flexes the thigh at the hip joint and rotates it outward; with a fixed thigh, it flexes the torso forward. 1) It may have a connecting bundle with m. psoas major at the place where the n. femoralis passes between them; 2) a separate superficial bundle has been observed occasionally; 3) the caput externum may also sometimes represent an independent muscle-m. iliacus minor or ilio-capsularis or ilio-capsulo-trochantericus. B. M. E. Vol. XIX. No. No. Latin and Russian name. Synonyms. Form and position. Origin and insertion. Innervation and relation to segments. Ilio-costalis: pars lumbalis, pars thoracalis (dorsi) and pars cervicalis (ilio-costal muscle). Syn.: sacro-lumbus, sacro-lumbalis; ilio-costalis lumborum, lumbo-costalis; ilio-costalis dorsi-accessorius ad m. ilio-costalem, costalis dorsi; ilio-costalis cervicis-cervicalis descendens et ascendens. The most lateral of the long muscles of the back; it represents a voluminous muscle mass which begins from the sacrum and the ilium and continues, becoming thinner, up to the lower cervical vertebrae; the muscle consists of bundles which attach to the ribs near their angles; auxiliary bundles begin medially from these same places; along the entire length of the back, these bundles are divided into three parts: lumbar, thoracic, and cervical. Origin: pars lumbalis: sacrum-crista sacralis lateralis and fascia lumbo-dorsalis, ilium-crista iliaca-dorsal part; pars thoracalis (dorsi): from XII to VII ribs-angulus costae, medially from the attachment of the previous portion; pars cervicalis: from VI to III ribs-angulus costae, medially from the attachment of the previous portion. Insertion: pars lumbalis: lumbar vertebrae-processus laterales, deep layer of fasciae lumbo-dorsalis and lower VI-IX ribs-angulus costarum; pars thoracalis: 6 or 5 upper ribs-angulus costae; pars cervicalis: from VI to IV (III) cervical vertebra-tuberculum posterius processus costo-transversarii. Spinal nerves-their posterior branches: of the first lumbar, all thoracic and cervical up to CIV. LI to CIV. Ilio-costalis cervicis. See m. ilio-costalis. Ilio-costalis dorsi. See m. ilio-costalis. Ilio-costalis lumborum. See m. ilio-costalis. Ilio-lumbalis (ilio-lumbar muscle). Fibers of m. quadrati lumborum, which go from the ilium-crista iliaca to the lumbar vertebrae. Ilio-psoas. See m. iliacus and m. psoas. Incisivi labii superioris and inferioris (upper and lower incisive muscles). Syn.: incisivi inferiores and superiores, accessorii buccinatoris, s. orbiculares, adductores, adductores anguli oris, protractores anguli oris, protrusores. Small but rather long ribbons which, having started from the bones of the upper and lower jaws close to the midline, are directed obliquely to the outer edges of the lips: the upper muscle to the upper lip, the lower muscle to the lower lip; they lie under the mucosa and weave into the fibers of m. orbicularis oris. Origin: upper and lower jaw-juga alveolaria dentium caninorum superiora et inferiora. Insertion: mucous membrane of the lips at the corners of the mouth in the mass of m. orbicularis oris. N. facialis-rr. buccales. Incisurae helicis (muscle of the helix notch of the auricle). [Rare muscle.] Syn.: incisurae auriculae, s. majoris auriculae, cartilaginis meatus acustici externi, dilatator conchae auriculae, intertragicus. Origin: cartilage of the external auditory canal-cartilago meatus acustici externi. Insertion: tragus of the auricle-facies anterior tragi. Infraclavicularis (Bardeleben) (subclavicular muscle). A rare atypical muscle, it represents a flat muscle bundle in the region of m. pectoralis majoris and deltoidei in the fascia superficialis. Origin: above pars clavicularis m. pectoralis majoris.
Attachment: disperses in the fascia above the pectoralis major muscle and deltoid muscle. Branch of the anterior thoracic nerve. Infrascapularis minor (Gruber). Lower bundle of the subscapularis muscle. Blood supply. Action. Variations. Unilateral contraction helps to bend the torso and neck to its side; bilateral contraction straightens the torso and neck bent forward. 1) Variations reduce to a reduction or increase in the number of points of origin and attachment of the bundles; 2) the lumbar part can be attached by one deep bundle to the lumbo-costal ligament; 3) the first bundle of the thoracic part can also sometimes originate there; 4) the sequence of bundles can be disrupted due to the loss of some of them; 5) the attachment of the dorsal part is often limited only to the second rib; 6) the cervical part can be attached only to the V-VII vertebrae; 7) closer relationships with neighboring muscles are possible. Superior and inferior labial arteries from the external maxillary artery, from the infraorbital artery, and also branches from the ophthalmic artery - superior; mental artery and submental artery - inferior. Pull the lips forward during sucking, whistling, kissing. Superior incisive muscle: 1) can be reduced to several small bundles or even to complete absence; 2) on the other hand, it can increase and occupy the space up to the canine fossa and up to the origin of the canine muscle or rise along the nasal muscle, or reach the skin of the nasal wings, or connect with the superficial bundles of the transverse part of the nasal muscle, or with the lower end of the anomalous maxillary muscle; 3) the attachment can also vary: it can end in a fan shape in the mucosa of the cheeks up to the very beginning of the buccinator muscle or adjoin the medial edge of the canine muscle or some fibers can pass through the canine muscle into the nasolabial fold. Inferior incisive muscle: 1) can also be reduced up to disappearance; 2) the bundles may not lie adjacent to each other, but diverge laterally, with the lower ones even being able to attach to the lower jaw above the oval foramen; 3) the attachment of the bundles often merges with the mentalis muscle; 4) sometimes the bundles can lie closely adjacent to the platysma muscle, the inferior quadratus labii muscle, and the triangular muscle. Also included here are rare variations: 1) new clavicular muscle (Gantzer), which departs tendinously from the sternal edge of the clavicle and passes over the deltoid muscle into the fascia of the arm; 2) supraclavicular muscle (Luschka) - departs from the sterno-clavicular joint and passes into the fascia of the deltoid muscle; 3) lateral pre-clavicular muscle (Gruber) or acromio-clavicular muscle (superficial) - departs from the clavicle at the border of its lateral and middle thirds, crosses the origin of the deltoid muscle and attaches to the tip of the acromion. 18 No. Name, Latin and Russian. Synonyms. Form and position. Origin and attachment. Innervation and relation to segments. Infraspinatus: superior portion, intermediate portion, and inferior portion (infraspinatus muscle). Syn.: rotator humeri posticus. A flat triangular mass of muscle fibers occupying the entire infraspinatus fossa; it is divided by its origin and the direction of the fibers into three portions: the upper with parallel fibers, the middle with converging fibers, and the lower with parallel fibers; the muscle is covered: from above in the lateral part by the deltoid muscle, from above in the medial part by the trapezius muscle, and from below by the latissimus dorsi muscle and teres major muscle; only the middle part of the muscle is covered only by superficial fascia and skin. Origin: superior portion: scapula - spine of the scapula; intermediate portion: scapula - surface of the entire infraspinatus fossa; inferior portion: scapula - axillary margin directly near the teres minor muscle. Attachment: humerus - greater tubercle of the humerus, its middle facet. Suprascapular nerve. Cv and VI. 200 Intercartilagineus (intercostal-cartilaginous muscle). Fibers from the internal intercostal muscles, located between the costal cartilages. Anterior digastric interclavicular muscle (Gruber) (anterior digastric interclavicular muscle). [Very rare variation.] See anterior sterno-clavicular muscle. A case where a bilaterally developed muscle begins with one common median tendon above the manubrium of the sternum. Superior interclavicular muscle (Hyrtl) (interclavicular muscle). [Rare variation.] Fibers directed between the sternal ends of the clavicles ventrally from the interclavicular ligament. External intercostal muscles (external intercostal muscles). Syn.: inspiratory. Represent layers of muscle fibers that fill all eleven intercostal spaces; the fibers run from above and behind forward and downward, starting from the costal crest outward from the inferior costal groove of the overlying rib to the nearest underlying one; the muscles leave unfilled: a) a small triangular space behind and at the dorsal edge of the rib, where the levator costarum muscles lie adjacent to them, and b) the anterior parts, where they are replaced by shiny tendinous fibers - shimmering ligaments, or external intercostal fascia. Adjacent ribs from the costal tubercle to the beginning of the costal cartilages, and further up to the sternum itself, the muscle fibers are more often replaced by tendinous ones. Spinal nerves from Di to Dxi, their anterior branches. Di-Dxi. Intermediate intercostal muscles (Eisler) (intermediate intercostal muscles). Muscle bundles described by Eisler, which are located between the external and internal intercostal muscles; they differ from the former in direction (from top to bottom and from the midline outward) and are separated by a long thin nerve, and from the latter they are separated by the trunk of the intercostal nerve itself and the intercostal vessels; the muscle is located in the space up to the costal angle. Internal intercostal muscles (internal intercostal muscles). Syn.: expiratory. Represent a layer of muscle fibers filling all 11 intercostal spaces; their fibers run from below and behind upward and forward, starting from the upper edge of the ribs and attaching to the lower edge of the overlying rib inward from the inferior costal groove; the muscle fibers are thickest in the anterior parts and become thinner towards the dorsal edge, being replaced there by tendinous fibers - internal intercostal fascia. Adjacent ribs from the sternum to the costal angle, and closer to the sternum, the muscle fibers can be replaced by tendinous ones. Spinal nerves from Di to Dxi, their anterior branches. Di-Dxi. Interdigastricus (Bianchi) (interdigastric muscle). [Variation.] See digastric muscle of the mandible. 55$ Blood supply. Action. Variations. Transverse scapular artery from the subclavian artery and circumflex scapular artery from the axillary artery. Rotates the humerus outward, and abducts the raised arm backward. 1) Close relationships with the teres minor muscle are frequent; 2) cases of connection of the lower portion with the deltoid muscle are rare; 3) separation of the upper bundles into an independent muscle is possible - minor infraspinatus muscle (Knott); 4) isolated superficial bundles have been observed - superficial infraspinatus muscle (Thomas). \ i, Posterior intercostal arteries from the subclavian artery and thoracic aorta and anterior intercostal arteries from the internal mammary artery and musculophrenic artery. Takes part (according to different authors, differently) in the process of breathing. 1) Some bundles may be absent, but all may also be absent and replaced entirely by tendinous fibers; 2) starting from the eighth intercostal space, the bundles may end at the place of exit of the lateral branches of the intercostal nerves; on the IX-XI intercostal spaces, the bundles may be interrupted at the place of departure from the ribs of the posterior serratus muscle and the external oblique abdominal muscle; 3) one or several bundles can ventrally extend to the sternum; 4) the number of muscles can increase in the presence of a cervical or thirteenth thoracic rib; 5) exchanges of fibers with the anterior serratus muscle, internal intercostal muscles, and external oblique abdominal muscle are sometimes observed. Posterior intercostal arteries from the subclavian artery and thoracic aorta, anterior intercostal arteries from the internal mammary artery and musculophrenic artery. Takes part (according to different authors, differently) in the process of breathing. 1) The three upper muscles sometimes extend to the spine itself, often merging with the subcostal muscles; 2) near the sternum, portions from the intermediate intercostal muscles sometimes weave into this muscle; 3) in the ventral region, tendinous continuations of the X, XI, and XII ribs into the external oblique abdominal muscle (tendinous inscriptions) are frequent, and muscle fibers (intermediate intercostal muscles) continue accordingly; 4) ventral bundles often have a direction parallel to the ribs; 5) intercartilaginous muscles - layers of muscle fibers, often sharply separated from the internal intercostal muscles or even representing a kind of independent muscle; 6) in different places, defects of muscle fibers are sometimes observed. No. Name, Latin and Russian. Synonyms. Form and position. Origin and attachment. Innervation and relation to segments. Interfoveolaris (Hofmann). [Variation.] Syn.: pubo-transversalis, pubio-peritonaealis, tensor of the posterior lamina of the rectus abdominis muscle sheath, pubo-rectalis. See transversus abdominis muscle. First intermetacarpal muscle (Frobse and Prankel) (first intermetacarpal muscle). [Rare variation.] Muscle bundle between the first and second metacarpal bones. Dorsal interosseous muscles of the hand (dorsal interosseous muscles of the hand). Syn.: external interosseous muscles of the hand, posterior, extensor interosseous, bicipitis of the hand, external metacarpal; first dorsal interosseous muscle = abductor of the index finger.
They represent four elongated spindle-shaped pennate muscle bundles with two heads, located in the spaces between the metacarpal bones and extending with their tendons to the base of the first phalanges. Origin: I-IV metacarpal bones - dorsal surfaces of two adjacent fingers. Insertion: II, III, and IV fingers - first phalanges of their basis, articulationes metacarpo-phalangeae, their dorsal aponeurosis and tendons of m. extensoris digitorum; int. I origin: from Mtc. I and Mtc. II and insertion: to the II finger; int. II origin: Mtc. II (dorsal head) and Mtc. III (dorso-volar head) and insertion: to the III finger; int. III origin: Mtc. III (dorso-volar head) and Mtc. IV (dorsal head) and insertion: to the III finger; int. IV origin: Mtc. IV (dorso-volar head) and Mtc. V (dorsal head) and insertion: to the IV finger. N. ulnaris - r. profundus. CVIII and DI. Interossei dorsales pedis (dorsal interosseous muscles of the foot). Syn.: interossei externi pedis, s. superiores, bicipitis pedis, metatarsales externi, s. superiores. They represent four muscle bundles, having a prismatic and triangular shape in cross-section, and if looked at in their natural position - flat bipennate muscles, filling the entire space between the metatarsal bones on the dorsal side; in this space they form an aponeurotic plate, which passes into a cylindrical tendon. Origin: by two heads from all metatarsal bones, from their sides directed toward each other and lig. plantare longum. Insertion: II-IV fingers - their main phalanges (basis), its lateral edges, and also lig. accessoria plantaria. M. int. I - origin: Mtt. I - lateral surface only at the base (caput med.) and Mtt. II - entire medial surface (caput lat.) and a small tendon from os cuneiforme I and insertion: to the second finger (medial surface of the base of the 1st phalanx); int. II - origin: Mtt. II - entire lateral surface (caput med.) and Mtt. III - entire medial surface (caput lat.) and insertion: to the II finger (lateral surface of the base of the first phalanx); int. III - origin: Mtt. III - entire lateral surface (caput med.) and Mtt. IV - entire medial surface (caput lat.) and insertion: to the III finger (lateral surface of the base of the first phalanx); int. IV - origin: Mtt. IV - entire lateral surface (caput med.) and Mtt. V - entire medial surface (caput lat.) and insertion: IV finger (lateral surface of the base of the first phalanx). N. plantaris lateralis. SI and SII. Interossei plantares (plantar interosseous muscles). Syn.: interossei pedis inferiores, metatarsales interni. Three small muscle bundles in the second, third, and fourth intermetatarsal spaces, on the medial surfaces of the third, fourth, and fifth metatarsal bones; cylindrical tendons attach from the medial side. Origin: III-V metatarsal bones - their base and plantar surface (upper third) and lig. plantare longum. Insertion: to their own fingers (III-V) main phalanges, medial surface of their bases. M. int. I origin: Mtt. III - plantar surface of the base and proximal third and insertion: III finger; int. II origin: Mtt. IV, as the previous one and insertion: IV finger; int. III origin: Mtt. V, as the previous ones and insertion: V finger. N. plantaris lateralis. SI and SII. Interossei volares (palmar interosseous muscles). Syn.: interossei interni manus, s. simplices, flexores breves profundi manus, digitorum manus profundi, metacarpales interni, palmares. They represent four spindle-shaped muscle bundles, located in the interosseous spaces on four metacarpal bones, except the third, on their sides facing this third finger - the axis of the hand. The first interosseous represents an easily separable bundle - m. adductor pollicis. Origin: II metacarpal - ulnar edge and IV and V metacarpal bones - radial edge. Insertion: I, II, IV, and V fingers - main phalanges, articulationes metacarpo-phalangeae and dorsal aponeurosis. M. int. I - origin: Mtc. I - ulnar edge and Mtc. II - base of the radial edge and insertion: I finger; int. II - origin: Mtc. II - ulnar edge and insertion: II finger; int. III - origin: Mtc. IV - radial edge and insertion: IV finger; int. IV - origin: Mtc. V - radial edge and insertion: V finger. N. ulnaris - r. profundus. CVIII and DI. Blood supply: Arcus volaris profundus. Action: Abduct the II and IV fingers from the axis, i.e., from the III finger (adductors), flex the fingers at the metacarpo-phalangeal joint (main phalanx) and extend at the articulationes interphalangeae (middle and nail phalanges). Variations: 1) Some of the muscles may be absent; 2) may be double; 3) m. interosseus II may attach to the index finger, which then becomes the axis of the hand instead of the third finger; 4) m. intermetacarpalis I (see No. 208). Blood supply: Arcus plantaris and aa. metatarseae plantares. Action: Flex the fingers at the phalangometatarsal joints (flex the main phalanx) and extend the middle and nail phalanges, and besides that, abduct the fingers from the axis of the foot, which passes through the second (and not the third, as on the hand) finger (abduction in an adult is negligible). Participate in strengthening the arch of the foot. Ruge noted the movement of muscles from the plantar side to the dorsal side as the child develops; likewise, he pointed out that in the human embryo, the muscles have only one head and are not bipennate. Blood supply: Arcus plantaris and aa. metatarseae plantares. Action: Flex the III-V fingers only at the articulatio metatarso-phalangea, bring them closer to the II finger and insignificantly participate in the formation of the arch of the foot. Blood supply: Arcus volaris profundus. Action: Adduct the II, IV, and V fingers to the axis of the hand, which passes through the III finger (mm. adductores), and besides that, flex the fingers at the metacarpo-phalangeal joint and extend at the interphalangeal joints. Bundles may be double - all or only some of them, repeating the shape of the main muscle. Interspinales (interspinal muscles). Small muscle bundles between the spinous processes. Origin: Between the spinous processes of all vertebrae except IV-X thoracic. Innervation: Spinal nerves, their posterior branches. Intertransversarii anteriores longi (Testut) (anterior long intertransverse muscles). [Variation.] See m. intertransversarii ventrales. Intertransversarii dorsales: cervicales, thoracales and lumbales (dorsal intertransverse muscles). Syn.: intertransversarii posteriores; intertransversarii lumbales = intertransversarii posteriores mediales, interaccessorii, interobliqui, interarticulares lumborum. Quite tiny muscle bundles, lying deeply on the dorsal surface between adjacent transverse processes and having preserved the original segmental arrangement; they are separated from the ventral intertransverse muscles not only topographically, but also by their innervation from the posterior branches of the spinal nerves. Cervicales: origin: all cervical vertebrae - processus transversus - their facies caudalis and insertion: cervical vertebrae from II to VII - processus transversus (tuberculum posterius), first rib - tuberculum and collum costae I and first thoracic vertebra - processus transversus. Thoracales: 1) origin: first thoracic vertebra - processus transversus and insertion: second thoracic vertebra at the same place; 2) origin: X vertebra at the same place and insertion: XI vertebra at the same place; 3) origin: XI vertebra and insertion: XII - processus mamillaris and accessorius. Lumbales: origin: all lumbar vertebrae - processus mamillaris and insertion: all lumbar vertebrae - processus mamillaris and accessorius. Innervation: Spinal nerves of the corresponding segments, their posterior branches. Intertransversarii laterales: cervicales and lumbales (lateral cervical and lumbar intertransverse muscles). Lateral parts from mm. intertransversarii dorsales, which separate from the latter muscle when the musculature is well developed. Innervation: Spinal nerves of the corresponding segments, their posterior branches. Intertransversarii longi (long intertransverse muscles). [Variation.] See mm. intertransversarii dorsales. Intertransversarii ventrales: cervicales and lumbales (ventral intertransverse muscles). Syn.: intertransversarii anteriores. Small muscle bundles between the transverse processes, located on the ventral side in the cervical and lumbar regions. Cervicales: all cervical vertebrae - processus costo-transversarius - their tuberculum anterius; lumbales: all lumbar vertebrae - processus lateralis. Innervation: Spinal nerves of the corresponding segments, their anterior branches. Intertransversarius lateralis longus. See mm. intertransversarii ventrales (cervicales) and scalenus medius. Ischio-bulbosus (Macalister) (ischio-bulbar muscle).
Syn.: constrictor, s. depressor urethrae et vaginae, dilatator, s. retractor urethrae, erector accessorius. Anterior bundles of m. transversus perinaei profundi in women. Ischio-calcaneus (Hinterstoisser) (ischio-calcaneal M.). [Variation.] A bundle of muscle fibers from m. biceps femoris or m. semitendinosus. Blood supply. Action. Variations. Extend the forward-bent spine. Flex the spine to its side. 1) Bundles transitioning to adjacent muscles are observed quite often: ilio-costalis, longissimus, and splenius cervicis; 2) mm. intertransversarii longi are often formed, passing over one or several vertebrae; 3) these or other bundles may be absent. i Flex the spine to its side! 1) The last bundle can often be absent; 2) between the IV and V lumbar vertebrae, the M. can also be reduced to a small oblique strip attaching to the lig. ilio-lumbale. Flex the spine to its side. 1) Sometimes some of them are very weakly developed or even absent altogether; 2) the bundle between the atlas and the epistropheus can be very small, and may be absent altogether; 3) sometimes directly laterally from them are bundles that pass over the nearest processes and, becoming longer, attach to the overlying vertebrae—mm. intertransversarii anteriores longi (Testut); in the cervical region, this is m. transversalis cervicis anticus (Luschka) or m. singularis in collo (Albinus), or mm. transversarii cervicis anteriores (Retzius), or m. intertransversarius lateralis longus, s. transversarius cervicis medius (Tornblom). No. No. Latin and Russian name. Synonyms. Form and position. Origin and insertion. Innervation and relation to segments. 223 Ischio-cavernosus (ischio-cavernous M.). Syn.: depressor, s. erector clitoridis, sustentator, s. director, s. erector penis. Orig.: ischium—tuber ischiadicum and ramus ascendens ossis ischii. Ins.: tunica albuginea at the root of the corpus cavernosum penis or clitoridis. N. perinaeus. 224 Ischio-coccygeus (Browning) (ischio-coccygeal M.). Syn.: obturato-coccygeus (Savage). Posterior bundles of m. levatoris ani, which go from the ischium—spina ischiadica to the coccyx. 225 Labii proprius (proper M. of the lip). Syn.: labii externus, s. rectus, compressor labii, suctionis, cutaneo-mucosus. See m. orbicularis oris. Muscle fibers that are found in each lip separately in the form of round or flat bundles located along the edges of the lips under the mucous membrane; they are not macroscopically distinguishable. Latissimo-condyloideus. Syn.: anconaeus quintus. [Variation.] See m. latissimus dorsi. 227 Latissimus dorsi: pars scapularis, vertebralis, iliaca, and costalis (broad M. of the back). Syn.: dorsalis maximus, aniscalptor, anitensor. The largest M. of the body; it has the shape of a wide, flat triangular plate, with the base along the midline of the body on the back and the apex facing the humerus; it lies immediately under the superficial fascia and skin, and only the upper angle of the pars vertebralis is covered by the m. trapezius; the M. in turn covers the m. serratus posterior inferior, superficial dorsal M., m. rhomboideus, m. obliquus abdominis externus, m. serratus anterior (partially); the upper edge is in contact with the m. rhomboideus, and its tendon adjoins the m. teres major. Orig.: pars scapularis: scapula—angulus inferior; pars vertebralis: VII-XII thoracic vertebrae—processus spinosus, fascia lumbo-dorsalis; pars iliaca: ilium—crista iliaca, its inner third; pars costalis: (IX) X-XII ribs. Ins.: humerus—crista tuberculi minoris humeri. N. subscapularis—r. thoraco-dorsalis. (Cyi) yii and VIII. 228 Levator alae narium major (major M. elevating the wing of the nose). Syn.: levator posterior. [Variation.] Medial position of the capitis angularis m. quadrati superioris. 229 Levator ani: pars anterior and posterior (M. elevating the anus). Syn.: levator intestini recti, sedem attollens, diaphragma pelvis; pars anterior—m. pubo-coccygeus; pars posterior—m. iliaco-coccygeus. A wide flat plate of funnel-like shape. Orig.: pars anterior: pubic bone—ramus horizontalis, its posterior surface; pars posterior: fascia obturatoria and arcus tendineus fasciae pelvis. Ins.: ischium—spina ischiadica. N. pudendus. 56 5 Blood supply. Action. Variations. Compresses the cavernous body of the penis and clitoris and thereby compresses the v. dorsalis. 1) It can sometimes give bundles to the mm. bulbo-cavernosus, sphincter ani, and transversus perinaei; 2) Houston described a small bundle heading from both antimeres to the dorsal surface of the penis to the vena dorsalis penis—m. compressor venae dorsalis penis. A. thoraco-dorsalis from the a. subscapularis and branches of the a. circumflexa humeri anterior and posterior. Rotates the shoulder inward, lowers the raised arm, and throws it onto the back with the palm outward. 1) Once, complete absence of the pars vertebralis, iliacae, and scapularis was observed; the M. attached only to the VIII-XI ribs; 2) the origin can descend to the I lumbar vertebra; 3) rise to the V-IV thoracic vertebrae; 4) the origin on the crista iliaca can either extend far ventrally, so that the trigonum lumbale is absent, or be reduced up to the absence of this part JH.; 5) the costal origin can be limited to the X and XI ribs; 6) very often an additional bundle departs from the fascia teretis majoris near the angulus inferior scapulae; 7) the terminal tendon can merge with the tendon of the m. teretis majoris along its entire length or partially; 8) once, in the absence of the m. teretis majoris, the tendon of the m. latissimi was split into two leaves; 9) from the costal part, larger or smaller bundles pass to the fascia axillaris; sometimes these bundles can be separated from the m. latissimus to a greater extent—this is the m. costo-coracoideus; the tendon of such a bundle can reach the processus coracoideus or the capsule of the shoulder joint through the gap between the lateral and medial trunks of the plexus brachialis; it can also be called the "muscular axillary arch"; 10) in connection with the tendon of the m. latissimi there can be: a) a "muscular axillary arch," which is connected with the m. pectoralis major; b) occasionally near the tendon there may be a bundle either heading into the long head of the m. tricipitis or maintaining independence—this is the m. dorso-epitrochlearis, s. latissimo-condyloideus, s. anconaeus quintus; it heads to the septum intermusculare mediale humeri; c) from the processus coracoideus, bundles occasionally go to the dorsal and ventral surfaces of the tendon of the m. latissimi—this is the m. coraco-brachialis minor, s. secundus, s. brevis; if this M. goes medially from the axillary nerve and vascular bundle, it is called the m. levator tendinis latissimi; 11) very rarely there is a bundle from the processus spinosus of the VI thoracic vertebra, adjoining the cranial edge of the m. latissimi dorsi and reaching the angulus inferior of the scapula; Hofmann calls it rhomboideus minimus (but this is incorrect, as it has a common innervation with the m. latissimus). A. pudenda. Elevates the perineum and the anus and narrows it. Part of the fibers passes by the prostata, tightly adhering to it—m. compressor prostatae; part attaches to the urinary bladder; in women, this muscle passes near the vagina and enters into connection with its muscle fibers. No. No. Latin and Russian name. Synonyms. Form and position. Origin and insertion. Innervation and relation to segments. Levator oesophagi (M. elevating the esophagus). Longitudinal muscle fibers of the esophagus, which go from the cricoid cartilage. Levator palpebrae superioris (M. elevating the upper eyelid). Syn.: orbito-palpebralis, tarsalis superior. A wide triangular muscle bundle just under the upper wall of the orbit. Orig.: sphenoid bone, around the foramen opticum and the sheath of the n. opticus. Ins.: upper eyelid—tarsus palpebrae superioris. N. oculomotorius. Levator prostatae. See m. pubo-vesicalis. Levator scapulae (M. elevating the scapula). Syn.: levator, s. elevator anguli scapulae, rhomboideus anterior, patientiae, adjutor splenii. Represents a large muscle layer located on the posterior and lateral surface of the neck in the same plane as the mm. scaleni between the transverse processes of the lower cervical vertebrae and the dorsal angle of the scapula; it adjoins the m. scalenus in front, and the m. splenius behind; almost the entire m. trapezius is covered, only the origin of the M. lies directly under the skin. Orig.: IV-VII cervical vertebrae—processus costo-transversarius—their tuberculum posterius. Ins.: scapula—angulus medialis to the spina scapulae. N. dorsalis scapulae and branches from the plexus cervicalis. C IV and C V. Levator tendinis latissimi (Gruber) (M. elevating the tendon of the broad M. of the back). [Variation not very rare.] See m. latissimus dorsi. Levator urethrae (M. elevating the urethra). Anterior, medial bundle of the m. levatoris ani. Levator vaginae (Luschka) (M. elevating the vagina). Outer, longitudinal layer of the tunica muscularis vaginae. Levator veli palatini (M. elevating the soft palate). Syn.: levator palati mollis, petro-salpingo-staphylinus, compressor tubae Eustachii.
A small round bundle between the soft palate and the temporal bone, located laterally from the choanae and medially and behind the tensor veli palatini muscle. Origin: temporal bone—inferior surface of the petrous part of the temporal bone and the cartilaginous part of the auditory tube. Insertion: converges with its antimere on the midline of the soft palate. Facial nerve. Longissimus: part of the lumborum, part of the thoracis, part of the cervicis, and part of the capitis (long muscle of the back). Synonyms: semispinatus, transversalis; longissimus thoracis = longissimus dorsi; longissimus cervicis = transversalis, or posterior major; longissimus capitis = complexus minor, trachelo-mastoideus, transversalis capitis. It forms the middle part of the sacrospinalis muscle, the lateral part of which is the iliocostalis muscle, and the medial part is the spinalis muscle; it represents initially a wide and thick muscular mass, which gradually decreases in volume and can be compared to a long pyramid with the apex directed toward the skull; a peculiarity of the muscle lies in the fact that it receives auxiliary bundles, varying in number and in their places of origin. Origin of the pars lumborum: sacrum—lateral sacral crest, long posterior sacroiliac ligament, iliac bone—iliac crest in the posterior part; insertion of the pars lumborum: lateral bundles: lumbar vertebrae—lateral process and lumbodorsal fascia, deep layer; medial bundles: lumbar vertebrae—accessory tubercle. Origin of the pars thoracis: superficial aponeurosis, upper sacral, lumbar, and lower thoracic vertebrae—spinous process, as well as the accessory tubercle and mamillary tubercle; insertion of the pars thoracis: lateral fibers: from the 12th to the 2nd rib—angle of the rib; medial fibers: all thoracic vertebrae—transverse processes. Origin of the pars cervicalis: upper thoracic (IV–VI) and lower cervical vertebrae—transverse processes; insertion of the pars cervicalis: cervical vertebrae (V–II)—costotransverse process, its posterior tubercle. Origin of the pars capitis: lower cervical vertebrae (VII–III)—costotransverse process; insertion of the pars capitis: temporal bone—mastoid process. Spinal nerves of all cervical, thoracic, and lumbar segments, their posterior branches. Blood supply. Action. Variations. Ophthalmic artery. Raises the upper eyelid. Ascending cervical artery, vertebral artery, and transverse cervical artery from the subclavian artery. Raises the scapula and brings it closer to the midline; with a fixed scapula, it tilts the neck to its side. 1) Complete absence is very rare; 2) greater or lesser independence of individual bundles, especially the bundle from the atlas; 3) decrease or increase of the initial bundles or their aberration are very frequent; the greatest constancy is shown by the two upper bundles; bundles can originate from all cervical and even from the first thoracic vertebrae; 4) additional bundles can originate from the trapezius muscle, splenius capitis muscle, longissimus cervicis muscle, from the fascia of the splenius muscle, from the tendinous arch above the occipital nerves and vessels in the region of the origin of the trapezius muscle and the sternocleidomastoid muscle from the dorsal edge of the latter, from the superior nuchal line (from the squamous part of the temporal bone in monsters), from the mastoid process, from the aponeurosis of the posterior superior serratus muscle, from the lower surface of the rhomboid muscles, from the I or II or from both ribs; 5) variations in the region of insertion are insignificant: the bundle from the atlas can attach to the I or II ribs, to the cranial edge of the first bundle of the anterior serratus muscle; it can be independent; 6) this aberrant bundle dorsally can attach to the tendon of the minor rhomboid muscle, to the fascia or tendon of the posterior superior serratus muscle, or to the spinous process of the VII cervical vertebra; it is called: rhombo-atloides, adjutor splenii, singularis splenii accessorius, splenius accessorius. Raises the soft palate, expands the fauces, and compresses the auditory tube. With unilateral contraction, it turns to its side; with bilateral contraction, it straightens the forward-bent spine. 1) A contraction of the lateral points of attachment of the longissimus dorsi muscle to the ribs is often observed: the upper bundles can be absent up to the V rib; the medial ones can reach the VII cervical vertebra; 2) the longissimus cervicis muscle can on one side reach the X–XI thoracic vertebrae, on the other—attach only to three; its superficial bundles can reach beyond the atlas to the posterior edge of the mastoid process; with strong development, this is the minor trachelo-mastoideus muscle, or accessorius (Luschka); 3) the longissimus capitis muscle can be completely absent; on the other hand, it can descend caudally to the VIII thoracic vertebra; in length, the muscle can break down into two bellies: one on the five lower cervical vertebrae, the other—on the five upper thoracic vertebrae. The muscle lies just under the latissimus dorsi, trapezius, rhomboid, and posterior superior and inferior scalene muscles and covers part of the short muscles of the back. Inferior longitudinal muscle of the tongue. Synonyms: lingualis inferior, or profundus, muscular layer of the tongue—longitudinal. Muscle fibers that run in the sagittal direction on the lower part of the tongue on both sides of the midline. Hypoglossal nerve. Blood supply: deep lingual artery. Action: shortens the tongue and makes it thicker. Superior longitudinal muscle of the tongue. Synonyms: lingualis longitudinalis superior, notoglossus. Muscle fibers that run in the sagittal direction along the upper part of the tongue from its root to the tip. Hypoglossal nerve. Blood supply: dorsal lingual artery. Action: shortens the tongue and bends its surface in the sagittal direction. Longus capitis muscle (long muscle of the head). Synonyms: rectus capitis internus major, anticus major. A small mass of muscle bundles located on the bodies of the anterior cervical vertebrae and their costotransverse processes; they partially cover the upper bundles of the longus colli muscle. Origin: III–VI cervical vertebrae—costotransverse process, its anterior tubercle. Insertion: occipital bone—basilar part of the occipital bone on the sides of the pharyngeal tubercle. Spinal nerves—their anterior branches. Ci–iv, and according to others Cii–iv or Ciii–v. Blood supply: ascending cervical artery and vertebral artery from the subclavian artery and ascending pharyngeal artery from the external carotid artery. Action: with bilateral contraction, it tilts the head forward. 1) The number of initial bundles can decrease to three due to the absence of the bundle from the VI vertebra and increase to seven due to the origin from the epistropheus and atlas; 2) cases of division into two layers or even into two independent muscles have been described; 3) a transition of bundles from one side to the other at the place of their attachment was observed once, more often a connection with the longus colli muscle is encountered; 4) in 4% of cases, the atlanto-basilaris internus muscle (Gruber) is encountered, which is a spindle-shaped muscle starting from the anterior tubercle of the atlas and attaching near the longus capitis muscle; 5) the origin of this muscle can shift to the epistropheus or to the anterior longitudinal ligament—this is the epistropheo-basilaris muscle (Gruber), or rectus capitis anticus medius muscle (Walsham); 6) in one case, the tendon of this muscle fused with the tendon of the detached bundle of the longus colli muscle. Longus colli: medial vertical part, superior oblique part, and inferior oblique part (long muscle of the neck). Synonyms: longus colli + longus atlantis muscle (Henle), rectus colli + superior and inferior oblique colli (Luschka). An elongated triangular mass of muscle bundles; the wide base of the triangle is located on the spine, and the apex on the transverse process of the fifth cervical vertebra—its anterior tubercle; it is only partially covered by the longus capitis muscle, and mainly by the pharynx, esophagus, and vessels of the neck. Origin: medial part: III–I thoracic vertebrae and VII–V cervical—vertebral body, their ventral surface; superior oblique part: V–II cervical vertebrae—costotransverse process, its anterior tubercle; inferior oblique part: upper thoracic vertebrae—their bodies. Insertion: medial part: (IV) III–I cervical vertebrae—vertebral body, their ventral surface; superior oblique part: atlas—anterior tubercle and epistropheus—body; inferior oblique part: VII and VI (V) cervical vertebrae—anterior tubercle. Spinal nerves from II to VI, their anterior branches. Ciii–viii. Lumbo-styloideus (Broca). Part of the fibers of the longissimus dorsi muscle on the lumbar vertebrae. Lumbricales of the hand (lumbrical muscles of the hand). Synonyms: fidicinales, fidicini, flectantes primum internodium. Four small spindle-shaped muscle bundles, extending from the tendons of the flexor digitorum profundus muscle in the region of the metacarpal bones to the radial edge of the bases of the first phalanges of the II–V fingers. Origin: tendons of the flexor digitorum profundus muscle. Insertion: II–V fingers—dorsal aponeurosis, its radial surface. Median nerve—I and II muscles, and ulnar nerve—III and IV muscles. Cviii and Di. Lumbricales of the foot (lumbrical muscles of the foot). Four small spindle-shaped muscle bundles. Origin: tendons of the flexor digitorum longus muscle. Medial plantar nerve for the I and (II) muscles, plantar nerve.
A. vertebralis, a. cervicalis ascendens and profunda from a. subclavia, as well as the upper aa. intercostales posteriores. Turn to their side, and with bilateral contraction, tilt the neck (and head) forward. 1) Lengthening of the muscle to the IV vertebra; 2) attachment to the heads of the I, II, and III ribs; 3) often a tendinous ligament with m. longus capitis; 4) often M. can be in the form of independent M.; 5) pars obliqua superior can merge with m. scalenus anterior and m. longus capitis; 6) pars obliqua inferior can merge with mm. intertransversarii ventrales; 7) pars medialis can merge with its antimere. Arcus volaris sublimis. Flexes the fingers at the metacarpophalangeal joint. Variations are encountered more often than the normal form (45%, according to Froment, and 61%, according to Kopsch, though according to other authors much more rarely): 1) all may be absent; 2) may originate: m. lumbricalis I additionally from the tendon of m. flexor pollicis longus, flexor digitorum sublimis; m. lumbricalis III from lig. carpi transversum; m. lumbricalis III and IV by means of special tendons from m. flexor digitorum profundus; 3) often (35%) m. lumbricalis I, II and IV attach to the radial surface of the corresponding fingers, i.e., II, III and V, and m. lumbricalis III splits and attaches with one tendon to the ulnar edge of III, and with the other to the radial edge of IV; 4) may double. Aa. plantaris lateralis and medialis. Flexes the fingers in the plantar direction. 1) Their muscular and tendinous parts can double; 2) m. lumbricalis IV can originate. No. Name Latin and Russian. Synonyms. Form and position. Origin and attachment. Innervation and relation to segments. 245 - (Continued) muscular bundles, directed from the tendons of m. flexor digitorum longus in the region of the metatarsal bones to the medial edge of the bases of the first phalanges of the II-V fingers. Att.: II-V fingers - main phalanx, its medial edge, and from here also the dorsal aponeurosis... taris lateralis for (II) III and IV M.L. ... Masseter: portio superficialis and portio profunda (masticatory M.). Syn.: masseterus, mansorius, masticatorius, mandicatorius, massiter, mandibularis externus, jugo-maxillaris. A short but powerful quadrilateral muscular layer, consisting of two layers - superficial and deep, more independent in the anterior part and more fused in the posterior, but distinguishable from each other by the somewhat different direction of the fibers; M. is located in the space between the zygomatic arch and the angle of the mandible, covered from above by skin, fascia parotideo-masseterica, partly by the parotid gland, m. platysma and m. risorius, and in its turn covers m. buccinator, the tendon of m. temporalis and m. pterygoideus externus. Orig.: portio superficialis: zygomatic arch - its lower edge; portio profunda: zygomatic bone - its inner surface and fascia temporalis. Att.: mandible - tuberositas masseterica. N. mandibularis - r. massetericus. I - mandibular arch. 247 Masto-carotideus fasciculus (mastoid-carotid M.). [Extremely rare M.] Orig.: temporal bone - processus mastoideus. Att.: sheath of a. carotis at the level of the thyroid cartilage. Mastoideo-triticeus (Westarini Kresi). [Once encountered variation.] Orig.: medial surface of m. sterno-cleido-mastoidei. Att.: corpusculum triticeum in lig. thyreo-hyoideum laterale. Mentalis (mental M.). Syn.: levator menti, s. labii inferioris, elevator labii inf. proprius, incisivus, s. incisorius inferior, superbus, corrugator menti, conscripens. A small muscular bundle of conical shape with the apex on the mandible and the base in the skin of the chin. Orig.: mandible - juga alveolaria of the incisors and canines. Att.: skin of the chin. N. facialis - r. marginalis mandibulae. Mento-hyoideus (Macalister) (mental-hyoid M.). [Variation.] See m. digastricus mandibulae. Additional bundle of venter anterior m. digastrici, which goes from os hyoideum to the chin, not merging with m. digastricus. Mento-hyoideus (Gruber) (mental-hyoid M.). [Variation of m. digastricus mandibulae.] Variation when the venter anterior does not merge with the venter posterior, but attaches to the os hyoideum. Mento-hyoideus transversus (Schwegel, H. Virchow) (transverse mental-hyoid M.). [Variation of m. digastricus.] A transverse bundle, located medially from the venter anterior and passing in the transverse direction to the other side. Multifidus: longus and brevis (multifidus M.). Syn.: multifidi, multifidus spinae; for the cervical part - transversalis colli; for the thoracic - semispinatus, transversalis dorsi interiores; for the lumbar - sacer, transversalis lumborum. Represents separate muscular bundles, located along the entire vertebral column between the transverse processes or their derivatives, deep under m. semispinalis and the long dorsal M.; at the same time, the bundles of mult. longus skip three vertebrae, and the breves only two. Orig.: sacrum - facies posterior to the IV foramen sacrale posterius, lig. sacro-iliacum posterius, ilium - crista iliaca, fascia lumbo-dorsalis, lumbar vertebrae - processus mamillaris, thoracic - processus transversus, VII-IV cervical - processus articularis. Att.: all vertebrae to the IV cervical - processus spinosus. Spinal nerves to the III cervical - their posterior branches. Mylo-hyoideus (mylohyoid M.). Syn.: diaphragma oris, transversus mandibulae, mylo-glossus, mylo-hyalis. Represents a not very thick muscular plate, consisting of two symmetrical halves, stretched between both halves of the mandible in the space between the hyoid bone and the chin; M. is covered by skin, fascia superficialis with m. platysma and on the sides by the venter anterior m. digastrici, and itself in turn covers mm. genio-hyoideus and genio-glossus. Orig.: mandible - linea mylo-hyoidea. Att.: hyoid bone - corpus ossis hyoidei and raphe between spina mentalis and os hyoideum. N. mandibularis - n. mylo-hyoideus. Mandibular arch. Blood supply. Action. Variations. from m. interosseus dorsalis IV; 3) m. lumbricalis I can originate from the tendon of m. tibialis postici or m. flexoris hallucis; 4) rarely this or that or even all may be absent. A. masseterica from a. maxillaris interna, branch of a. maxillaris externae, transversa faciei, a. buccinatoria and a. alveolaris superior posterior. Elevates the mandible. 1) Once complete absence was observed (phocomelia); 2) a more or less complete separation of both portions is possible; 3) fusion of the deep portion with m. temporalis and m. buccinator happens; 4) additional bundles: from lig. temporo-mandibulare, behind from m. zygomaticus; from maxilla to the anterior edge of masseteris; between both portions to the posterior edge of arcus zygomatici near the tuberculum articulare; 5) superficial bundles were observed from fascia colli superficialis near angulus mandibulae; 6) once both portions attached above the angle of the jaw to a special ridge, which went in an arc from the processus condyloideus through the outer surface of rami mandibulae to the anterior edge of the processus coronoidei (Fleissig). A. labialis inferior and a. submentalis from a. maxillaris externa and a. mentalis from a. maxillaris interna. Elevates the skin of the chin. 1) Different degrees of its development are observed and accordingly different sizes of the place of its origin; 2) it can very rarely split into two parallel portions. Unilateral contraction rotates, bilateral straightens the spine. Possible absence of individual muscular bundles. R. mylo-hyoideus from a. maxillaris interna, a. submentalis from a. maxillaris externa and a. sublingualis. Elevates the hyoid bone. 1) Complete absence is possible; 2) fusion of both antimeres into one; 3) attachment to os hyoideum can be extremely insignificant; 4) can divide into several bundles; 5) can divide into two bundles, between which m. stylo-hyoideus can pass; 6) can merge with... Mylo-pharyngeus (mylo-pharyngeal M.). Syn.: mylo-glossus (Douglas). Lower portion of m. constrictor pharyngis superioris, which goes from the posterior part of lineae mylo-hyoideae and under the last posterior molars. Nasalis: pars alaris (inferior) and pars transversa (superior) (M. of the nose). Syn.: pars alaris: myrtiformis, depressor alae nasi, s. labii superioris proprius, s. labii superioris et pinnarum nasi, s. alae nasi et septi mobilis, depressor labii superioris et constrictor alae nasi; pars transversa: elevator alae nasi, transversus and dilatator pinnae proprius, compressor naris, s. nasi major, s. naris, triangularis nasi, attrahens, compressor naris. A delicate flat triangular plate, located on the nose under the skin directly above the upper border of the wings of the nose; with the base, the triangles of one and the other side converge on the bridge of the nose. Orig.: maxilla - fossa canina to the jugum alveolare of the outer incisor and canine. Att.: pars alaris - skin of the wings of the nose and nasal septum; pars transversa: through the cartilaginous bridge of the nose to the common aponeurosis between the M. of both sides. N. facialis. Naso-labialis (naso-labial M.).
Syn.: nasalis labii superioris, depressor narium, s. septi mobilis narium, s. apicis nasi. The uppermost bundles of the outer zone of the m. orbicularis oris, which are directed toward the skin of the nostrils and the nasal septum. Obliquus auriculae (oblique muscle of the auricle). A small group of separate short muscle fibers on the posterior surface of the auricle. Origin: auricle-eminentia fossae triangularis. Insertion: auricle-eminentia conchae. N. facialis. Obliquus capitis inferior (inferior oblique muscle of the head). Syn.: obliquus capitis major. A spindle-shaped muscle bundle located obliquely between the first and second vertebrae on the arches themselves, deep beneath the more superficial cervical muscles: m. semispinalis capitis and m. splenius. Origin: II cervical vertebra-processus spinosus epistrophei. Insertion: I cervical vertebra-processus transversus atlantis. N. suboccipitalis-r. posterior and a branch of the n. occipitalis majoris. CI and (II). Obliquus capitis superior (superior oblique muscle of the head). Syn.: obliquus capitis minor. A flat muscle ribbon located obliquely on the lateral and posterior surface of the neck between the occipital bone and the atlas; it lies adjacent to the m. rectus capitis major and is covered by the mm. complexus, splenius, and partly by the m. sterno-cleido-mastoideus. Origin: I cervical vertebra-processus transversus atlantis. Insertion: occipital bone-linea nuchae inferior, its lateral part. N. suboccipitalis-r. posterior. CI. Obliquus externus abdominis (external oblique muscle of the abdomen). Syn.: obliquus superficialis, s. descendens, s. major. The largest and most superficial muscle of the abdominal wall, consisting of muscular and tendinous parts. The muscular plate has the shape of a more or less irregular rectangle and is formed by 7-8 muscle bundles starting with digitations on the 7-8 lower ribs between the digitations of the m. serratus anterior; the base of the triangle touches the iliac crest, the other leg runs approximately along the linea mamillaris, and the hypotenuse lies on the ribs. The tendinous plate lines the entire anterior abdominal wall from the arcus costarum above to the spina iliaca anterior superior and the symphysis ossium pubis. Origin: V-XII (bony) ribs, their outer surface. Insertion: iliac bone-labium externum cristae iliacae, lig. inguinale, pubic bone-tuberculum pubicum, linea alba. Nn. intercostales V-XII thoracic and I lumbar, nn. ilio-hypogastricus and ilio-inguinalis. D. xin k. (LI). Blood supply: nearby muscles: m. digastricus, m. sterno-hyoideus, m. omo-hyoideus, m. stylo-hyoideus, m. genio-hyoideus. A. angularis-r. nasalis and a. labialis superior from the a. maxillaris externa and a. ethmoidalis anterior from the a. ophthalmica. Pars alaris brings the wings of the nose together and narrows the nasal opening; pars transversa pulls the soft parts of the nose backward (Braus). 1) Pars alaris may attach only to the septum mobile nasi; 2) pars transversa may vary in its dimensions to a great degree; 3) pars transversa may send a bundle to the inner surface of the m. procerus of its side and to the outer surface of the opposite side; 4) there may be additional bundles; 5) it may be absent; 6) it may be inseparable from the m. orbicularis oris. A. occipitalis and a. vertebralis. Rotates the atlas and the head toward its side, and with bilateral action, tilts the head backward. 1) Occasionally it may double; 2) along the lateral edge, a bundle may run to the processus mastoideus or to the incisura mastoidea; 3) once a bundle was observed which ran from the processus spinosus epistrophei to its transverse process, bent over it as if over a pulley, was directed caudally, and attached to the transverse process of the III cervical vertebra. A. occipitalis and a. vertebralis. Rotates the head to the opposite side, tilts the head backward with bilateral action. Only one variation is known-division of the muscle into two layers (doubling). A. circumflexa ilium interna and a. epigastrica inferior from the a. iliaca externa, a. musculo-phrenica and a. epigastrica superior from the a. mammaria interna, aa. intercostales and a. thoraco-lateralis from the a. axillaris. With bilateral action, it lowers the rib cage, brings it closer to the pelvis, and tilts the torso forward. It takes part in the formation of the abdominal press. Unilateral contraction flexes and rotates (torsio) the trunk to the opposite side. 1) Complete absence has not been observed, but bundles from the VIII and IX ribs may be partially absent; once the muscle started from the VII-XII ribs between the angulus costae and the costal cartilages and from the VIII costal cartilage and, becoming tendinous at the level of the navel, attached only to the pelvis; 2) the number of bundles may vary: the bundle from the V and XII ribs is often absent; in the latter case, the muscle dorsally starts from the lig. lumbo-costale; an increase in the number of bundles occurs either due to starting from the IV rib or a doubling of their number (different according to various authors: on VII-VIII, VIII-IX, VIII-X and X-XI); 3) the length of the attachment site to the crista iliaca may change, so that the trigonum lumbale (Petiti) may be absent; 4) there may be a tendinous connection with the m. serratus ant. (quite often), m. latissimus dorsi, m. serratus below. The muscle lies immediately under the skin and superficial fascia, is in contact with the mm. pectoralis major and serratus anterior above, the m. latissimus dorsi-posteriorly (except for the trigonum Petiti), and covers the m. obliquus abdominis internus and mm. intercostales externi. The tendinous plate participates in the formation of the laminae externae vaginae m. recti, and its lower edge in the space between the spina iliaca anterior superior on one side and the tuberculum pubicum and symphysis ossium pubis on the other forms the Poupart's ligament-lig. inguinale. Obliquus externus abdominis secundus (second external oblique muscle of the abdomen). Syn.: obliquus ext. accessorius, s. profundus, s. minor. [Variation.] A case of complete doubling of the m. obliquus externus abdominis, see m. obliquus externus abdominis. Obliquus inferior oculi (inferior oblique muscle of the eye). A long, narrow muscle ribbon located in the lower part of the orbit between its floor and the m. rectus inferior in the mass of the corpus adiposi orbitae, bypasses the eyeball in an arc from the medial to the lateral side, and attaches tendinously to the eyeball. Origin: upper jaw-margo infraorbitalis, laterally from the lower edge of the crista lacrimalis of the lacrimal bone. Insertion: eyeball-its lateral surface posterior to the equator. N. oculomotorius. Obliquus internus abdominis (internal oblique muscle of the abdomen). Syn.: obliquus ascendens, s. alter, s. interior, s. profundus. A wide, flat plate consisting of muscular and tendinous parts. The muscular part consists of fan-shaped diverging muscle fibers and is located on the sides of the abdomen in the space between the costal arch and the iliac crest, as if in a bony frame; the tendinous part occupies the anterior abdominal wall from the lineae mamillaris to the midline of the abdomen. The muscle is covered by the m. obliquus externus abdominis, and it itself covers the m. transversus abdominis. Origin: fascia lumbo-dorsalis-outer layer, iliac bone-linea intermedia cristae iliacae, lig. inguinale. Insertion: XII-X(IX) ribs-their lower edge and linea alba. Nn. intercostales (VIII, IX, X) XI and XII, n. ilio-hypogastricus and n. ilio-inguinalis. D(VIII-X), XI-XII and LI. Obliquus superior oculi (superior oblique muscle of the eyeball, or trochlear muscle). Syn.: obliquus longus, patheticus, trochlearis. A long muscle belly lies in the upper medial corner of the orbit medial and superior to the m. rectus oculi medialis, has a long, narrow, round tendon, which bends over a pulley, changes its sagittal direction to lateral and dorsal at an acute angle, and attaches to the eyeball with an expanded tendon. Origin: sphenoid bone-around the foramen opticum, from the common tendinous ring around the n. opticus shared with all other eye muscles-annulus tendineus communis (Zinni). Insertion: eyeball, its upper surface posterior to the equator. N. oculomotorius. Obturator externus (external obturator muscle). Syn.: flexor cruris fibularis. The most hidden and inaccessible muscle of the entire body, located deep to the adductor muscles of the thigh, under the m. ilio-psoas, m. pectineus and m. adductor minimus, and occupies the space between the pelvis and the thigh; the muscle has the appearance of a flat triangular mass and consists of three bundles: the upper-from the ramus horizontalis ossis pubis, the middle-from the ramus descendens of it, and the lower-from the corpus and ramus ascendens of the ischium. Origin: innominate bone-facies externa, edges of the foramen obturati and membrana obturatoria. Insertion: thigh-fossa trochanterica and capsule of the hip joint. N. obturatorius-r. posterior. L (II), III and IV. Obturator internus (internal obturator muscle). Syn.: marsupialis, bursalis. A fan-shaped muscle of muscle fibers converging into a flat, long tendon; it bends at a right or acute angle over the incisura ischiadica minor; the muscle fibers lie in the pelvis, and the tendon lies outside between the pelvis and the greater trochanter.
In the pelvis, the muscle comes into contact with the levator ani muscle, and the tendon is surrounded by the gemelli muscles and covered by the gluteus maximus muscle. Origin: innominate bone-pelvic surface, around the obturator foramen and obturator membrane. Insertion: femur-trochanteric fossa. A branch from the sacral plexus directly or through the pudendal nerve. LIV, V and SI, II (III). Blood supply. Action. Variations: posterior inferior, external intercostal muscles; 5) under the name of duplication-external oblique muscle second, or accessory, or deep, or minor-frequent descriptions of bundles lying between the external and internal oblique muscles are included; the lateral rectus muscle of the abdomen (Kelch) also belongs here, which ran from the middle of the caudal edge of the 10th rib to the middle of the external lip of the iliac crest; standing apart is the protractor muscle of the crural arch (Gruber), which ran between the aponeurosis of the external and internal oblique muscles and attached to the superior ramus of the pubic bone dorsally from the site of attachment of the rectus muscle; 6) additional bundles from the 5th-7th ribs are quite frequent, which run in a transverse direction to the ventral surface of the sheath of the rectus abdominis muscle; 7) very rarely, tendinous intersections are found in the muscle. Ophthalmic artery-muscular branch. Rotates the eyeball upward and to the side. Internal circumflex iliac artery and inferior epigastric artery from the external iliac artery, musculo-phrenic artery and superior epigastric artery from the internal mammary artery, as well as the lower intercostal arteries. Takes part in the formation of the abdominal press (see external oblique muscle); with unilateral contraction, it flexes and rotates the trunk in the lumbar region to its side (torsion). 1) Absence of the inguinal portion was observed once, defects in the cranial and ventral parts of the muscle; 2) the muscle is occasionally attached to the 9th and even 8th ribs, but in exceptional cases can rise to the 5th-4th and even to the 3rd ribs; 3) tendinous intersections are sometimes described, more often one, but their number can reach 3-6; 4) fusion with the transversus abdominis muscle has been described by several authors. Ophthalmic artery-muscular branch. Rotates the eyeball downward and to the side. Fibers that attach to the trochlea are called the tensor trochleae muscle. Obturator artery and medial circumflex femoral artery. Rotates the thigh outward. 1) May fuse with the pectineus muscle; 2) the tendon of the muscle may fuse with the tendon of the piriformis muscle; 3) the upper bundle may sometimes be separated by the obturator nerve from the remaining bundles; 4) a case of an additional bundle of the adductor brevis muscle was observed; inferior gluteal artery, obturator artery and internal pudendal artery. Rotates the thigh outward. 1) The muscle was once reduced to a flat, translucent plate; 2) the number of aponeurotic layers in the muscle mass can vary from 3 to 6; 3) there may be an independent part of the muscle from fibers starting from the outer surface of the pelvis; 4) the muscle may fuse with the piriformis muscle; 5) the muscle may receive additional bundles from various points: a) iliopectineal eminence; b) tendon of the psoas minor muscle; c) pelvic fascia; d) sacrotuberous ligament; e) ischial spine; f) 3rd sacral vertebra; g) pubic bone. No. Name in Latin and Russian. Synonyms. Form and position. Origin and insertion. Innervation and relation to segments. 268 Occipitalis (occipital muscle). Syn.: occipiti, epicranius occipitalis. A flat, thin plate of muscle fibers on the occipital bone just under the skin and superficial fascia. Origin: occipital bone-highest nuchal line. Insertion: galea aponeurotica. Facial nerve-posterior auricular branch. 269 Occipito-hyoideus (occipito-hyoid muscle). Syn.: occipito-pharyngeus. [Rare muscle.] Origin: occipital fascia near the external occipital protuberance. Insertion: hyoid bone-horns of the hyoid bone, sometimes also the pharyngeal muscle. Occipito-parotideus (occipito-parotid muscle). [Rare variation.] See transverse nuchal muscle. Omo-cervicalis (scapulo-occipital muscle). Syn.: levator claviculae, or cinguli, or scapulae anterior, or major, omo-cleido-transversarius, acromio-basilaris, atlanto-acromialis, atlanto-scapularis, basio-humeralis, cervico-humeralis, trachelo-clavicularis, trachelo-scapularis, cleido-omo-atlanticus, cleido-epistrophicus, trachelo-clavicularis imus, omo-atlanticus. [Rare muscle (2%).] Origin: atlas-posterior or anterior tubercle, or atlas and axis, or 3rd vertebra-its transverse process, or fascia of the levator scapulae muscle, or tendon of the longus capitis muscle. Insertion: clavicle-acromial extremity of the clavicle. Third cervical nerve-its posterior branch. See Omo-hyoideus: superior belly and inferior belly (omohyoid muscle). Syn.: omo-hyalis, coraco-hyoideus, costo-hyoideus, scapulo-hyoideus. A long, thin muscle ribbon with a tendinous part in the middle-digastric muscle. It is located in an arc along the lateral side of the neck and is covered differently in different parts of its extent: close to the midline only by skin, superficial fascia and platysma muscle, further outward the sternocleidomastoid muscle is added here; in the middle third lateral to this muscle (subclavian triangle) again only skin, superficial fascia and platysma muscle, in the posterior third-skin, superficial cervical fascia and trapezius muscle. In turn, the muscle covers: in the anterior part the thyrohyoid and sternothyroid muscles, further-the larynx, thyroid gland and vessels and nerves of the neck, in the posterior part the scalene muscles and the upper edge of the serratus anterior muscle. Origin: scapula-superior margin of the scapula around the notch and superior transverse scapular ligament. Insertion: hyoid bone-body of the hyoid bone, its lower edge. Ansa hypoglossi. Opponens digiti quinti manus (muscle opposing the little finger of the hand). Syn.: opponens digiti minimi, adductor digiti minimi, or of the fifth metacarpal bone of the hand. A wide, flat triangular muscle, covered by the abductor and flexor digiti minimi brevis muscles and in turn covers the origin of the 4th palmar interosseous muscle. Origin: pisiform bone-hook of the hamate bone, transverse carpal ligament. Insertion: 5th metacarpal bone, its ulnar edge. Ulnar nerve-deep branch. CVIII and DI. Blood supply. Action. Variations: Posterior auricular artery and occipital artery. Pulls the scalp backward. 1) May be absent altogether; 2) dimensions may increase until joining posteriorly to the midline with its antimere, and laterally to the mastoid process and to the posterior auricular muscle; 3) may fuse with the posterior auricular muscle and with the superior auricular muscle; 4) may break up into portions; 5) may attach to the auricle. Transverse cervical artery. Superior thyroid artery, hyoid branch from the lingual artery, superficial cervical artery, transverse cervical artery and transverse scapular artery. Depresses the hyoid bone. 1) May be absent on one or both sides; 2) the inferior belly may either be reduced altogether or replaced by a tendon; 3) the superior belly may also be absent and then a tendon goes from the inferior belly to the hyoid bone or into the supraclavicular fascia, while the superior belly may pass and disperse into the fascia of the neck-this is the hyo-fascialis muscle (Gruber); 4) the superior belly may divide into 2 or 3 bundles, which attach fan-shaped to the hyoid bone, or to it and to the thyroid cartilage, or to the greater horn, or to the hyoglossus muscle, or to the sheath of the neck vessels, or to the geniohyoid muscle, or fuse with the sternothyroid muscle; 5) the inferior belly may double or a small bundle may split off from it to the sternohyoid muscle or sternocleidomastoid muscle or go partially to the transverse process of the 6th cervical vertebra, partly into the anterior scalene muscle; 6) the entire muscle may double-another omohyoid muscle; 7) the tendinous intersection may vary in its length and form; 8) the origin at the scapula varies in its extent from the superior transverse scapular ligament to the length of almost the entire superior margin, may pass to the coracoid process, coracoclavicular ligament, to the acromial edge of the clavicle, acromial process or, losing connection with the scapula, attach to the first rib or dorsal surface of the clavicle-cleidohyoid muscle; 9) there may exist an additional portion from the clavicle-cleido-omohyoid muscle in various forms and relationships with neighboring muscles, tendons and bones; 10) the muscle may pierce the sternothyroid muscle; 11) other atypical forms may be observed, such as the sternoscapularis muscle-from the cranial edge of the scapula, supraspinatus fascia-into the fascia and tendon of the sternothyroid muscle; coracocervicalis muscle-a rudimentary form when the tendon is lost in the supraclavicular fossa; cleidocervicalis or cleidofascialis muscle: from the middle of the dorsal surface of the clavicle or from its medial third passes into the fascia of the sternohyoid muscle. Deep volar branch from the ulnar artery. Opposes the little finger to the other fingers. 1) May be absent altogether; 2) have an additional head from the forearm aponeurosis; 3) may divide into two bundles; 4) may be more or less closely connected with the flexor brevis and abductor pollicis muscles. No. Name in Latin and Russian. Synonyms. Form and position. Origin and insertion. Innervation and relation to segments. Opponens digiti quinti pedis (muscle opposing the little finger of the foot). Syn.: opponens digiti minimi.
Short triangular M., covered by m. abductor digiti quinti and covers m. flexor brevis. Origin: lig. plantare longum and the tendon sheath of m. peronaei longi. Insertion: V metatarsal bone. N. plantaris lateralis. Si and II. Opponens pollicis (M. opposing the thumb). A thin (two-layered) muscle plate of more or less triangular shape, covered by m. abductor pollicis brevis and covers in its turn m. adductor pollicis and the deep head of m. flexoris pollicis brevis, as well as partly the tendon of m. abductoris pollicis longi. Origin: greater multangular bone-tuberositas ossis multanguli majoris and lig. carpi transversum. Insertion: I metacarpal bone. N. medianus. Cvi and VII. Orbicularis oculi: pars orbitalis, pars palpebralis, pars lacrimalis and pars superciliaris (circular M. of the eye). Syn.: palpebrarum, palpebrarum primus, orbicularis palpebrarum, m. supercilii, orbicularis latus + ciliaris, palpebras claudentes, semicircularis, sphincter oculi; pars superciliaris-depressor supercilii, s. capitis supercilii, superciliaris medians; pars lacrimalis-sacci lacrimalis Horneri, tensor tarsi, lacrimalis posterior. A flat, thin elliptical mass of muscle fibers located along the edge of the orbit and the upper part of the cheek and cheekbone (pars orbitalis) and along the edge of the eyelids (pars palpebralis); pars orbitalis is closely fused with the fascia superficialis and with the skin and its fatty layer by means of tendinous plates and covers the origin of m. zygomatici and m. quadrati labii superioris; pars palpebralis is separated by loose tissue from the skin and from the cartilago tarsi. Origin: pars orbitalis: maxilla-processus nasalis and crista lacrimalis, frontal bone-pars nasalis ossis frontalis and lig. palpebrale mediale; pars palpebralis: lig. palpebrale mediale and saccus lacrimalis; pars lacrimalis: lacrimal bone-crista lacrimalis; pars superciliaris: lacrimal bone-facies orbitalis. Insertion: pars orbitalis: outer corner of the orbit (Poirier denies this attachment), where the upper and lower M. merge into each other; pars palpebralis: lig. palpebrale laterale; pars lacrimalis: continues along the edges of both eyelids into m. ciliaris (Riolani); pars superciliaris: skin of the medial part of the eyebrow. N. facialis-rr. temporales and zygomatici. Orbicularis oris (circular M. of the mouth). Syn.: sphincter oris, s. labiorum, constrictor labiorum, s. prolabiorum, constringens, osculatorius. Represents fibers, for the most part originating from mm. buccinator, caninus, triangularis, zygomaticus, risorius and incisivi superior and inferior-these are fibres radiees Poirier. But besides that, there exist also circular fibers-fibres circulaires (Poirier), representing one unpaired M. in his opinion, and in the opinion of Brans consisting of two semicircular M.-of the upper and lower lip, because in the opinion of the latter, at the corners of the mouth there exists under the mucous membrane a tendinous layer, something like an inscriptio tendinea, to which the fibers of m. orbicularis oris and part of the fibers of m. buccinatoris are attached; these fibers represent as it were a constrictor or sphincter oris. Finally, there exist anterior-posterior fibers-compressor oris. N. facialis-rr. buccales. Orbicularis malaris (Henle) (circular cheek M.). [Variation.] See m. orbicularis oculi. Orbitalis (Mulleri). [Müller's (orbital) M.] Smooth muscle fibers located in the depth of the orbit around the fissura orbitalis inferior in the so-called membrana orbitalis, which closes this fissure. N. sympathicus. Palmaris brevis (short palmar M.). Syn.: carpicus, cutaneus manus, caro quaedam quadrata. A flat trapezoidal plate consisting of separate muscle fibers running parallel just under the skin of the ulnar part of the hand in its proximal half. Origin: palmar aponeurosis-its ulnar edge, lig. carpi transversum. Insertion: skin of the pad of the little finger. N. ulnaris-r. superficialis. Cvii and VIII and Di. Blood supply: A. plantaris lateralis. Action: Plantar flexion of the V metatarsal bone and strengthening of the arch of the foot. Variations: Very often absent (about half of the cases according to Le Double). Blood supply: R. volaris superficialis and a. princeps pollicis from a. radialis, arcus volaris profundus. Action: Opposes the thumb to the whole hand. Variations: 1) May be completely absent; 2) may merge with m. abductor or flexor pollicis brevis; 3) once consisted of two portions along its entire length. Blood supply: A. angularis from a. maxillaris externa, a. frontalis and a. transversa faciei from a. temporalis superficialis, a. infraorbitalis from a. maxillaris interna and a. supraorbitalis from a. ophthalmica. Action: Pars orbitalis-squints and closes the eye; pars palpebralis-closes the eyelids; pars lacrimalis-dilates the lacrimal sac; pars superciliaris-lowers the medial end of the eyelids. Variations: 1) A diversity is observed in the extent of the M.; thus, lateral parts can adjoin bundles running from the fascia temporalis, on the other hand, in the peripheral part of the pars orbitalis inferioris there may be a gap between the outer and inner segments of the M.; 2) close relationships are possible between pars orbitalis inferior and m. depressor supercilii; sometimes a bundle of varying thickness is encountered, which begins at the medial corner of the eye and is directed to the os zygomaticum or margo infraorbitalis near the caput infraorbitale m. quadrati labii sup.; a bundle to m. levator palpebrae superioris was even observed (Knott); 3) cases of variations of medial and lateral connections of the upper and lower bundles of the pars palpebralis are very frequent; among them one can note: the transition of the medial ends across the midline and the connection of the antimeres in the region of the glabella-m. transversus glabellae (Ruge); Eisler observed m. transversus radicis nasi, when fibers from both sides went from a straight line between the crista lacrimalis and arcus superciliaris and, crossing to the opposite side, wove into the skin of the beginning of the eyebrows and the side of the nose; 4) sometimes some fibers of the pars orbitalis are directed into the skin of the cheeks-this is m. orbicularis malaris. Blood supply: Aa. labiales superior and inferior from a. maxillaris externa, as well as branches from a. infraorbitalis (upper lip) from a. maxillaris interna and a. submentalis from a. max. ext. and a. mentalis from a. max. int. (lower lip). Action: Compresses the lips and closes the mouth. Variations: In each lip there are macroscopically indistinguishable fibers, which receive various names: m. suctionis, compressor labii, rectus labii, labii proprius, cutaneo-mucosus. Blood supply: A. ulnaris. Action: Tenses the skin of the eminence of the little finger. Variations: 1) Apparently the absence of the M. is very rare; 2) sometimes it begins from the os hamatum and os triquetrum. [Table columns: No. | Latin and Russian Name. Synonyms. | Form and Position | Origin and Insertion | Innervation and relation to segments]. 281 Palmaris longus (long palmar M.). Syn.: flexor manus medius. A spindle-shaped muscle belly of highly variable size passes into a very long cord-like tendon, which on the palm passes into a wide palmar aponeurosis; the M. lies on the forearm superficially, just under the skin and fascia superficialis, between m. flexor carpi radialis and flexor digitorum sublimis, which it partly covers. Origin: humerus-epicondylus medialis humeri, septum and fascia antibrachii. Insertion: aponeurosis palmaris. N. medianus. C(vii), VIII and Di. Papillares valvulae bi- et tricuspidalis (papillary M. of the heart valves). Syn.: contractors chordae vaginae. Origin: inner surface of the wall of the ventricles of the heart. Insertion: by means of heart strings-chordae tendineae-to the atrioventricular valves. Pectinati (pectinate M.). Muscle fibers of the auricle of the atria. 284 Pectineus (pectineal M.). Syn.: pectinalis, adductor superficialis, primus femoris, lividus. A small flat muscle plate of quadrangular shape between the os pubis and the most proximal part of the medial surface of the thigh; part of the M. lies directly against the skin and fascia cruris (trigonum Scarpae), and itself covers m. obturator externus and the upper part of m. adductoris minimi. Origin: pubic bone-pecten ossis pubis, tuberculum pubicum, lig. pubicum superius. Insertion: thigh-linea aspera femoris below the trochanter minor (linea pectinea). N. obturatorius-r. anterior (often absent) and n. femoralis. Lii and III. Pectoralis intermedius (intermediate pectoral M.). [Rare M.] Origin: III and IV ribs at the border of the cartilaginous and bony parts and the third intercostal space. Insertion: fascia of the arm above mm. biceps and coraco-brachialis. 286 Pectoralis major: pars clavicularis, pars sterno-costalis (superior and inferior) and pars abdominalis (greater pectoral M.). Syn.: portio clavicularis-m. cleido-brachialis. The M. represents a large mass of muscle bundles located on the anterior-upper part of the chest, between the clavicle, sternum and upper six ribs on one side and the humerus on the other. These bundles, according to the place of their origin, are divided into three or four more or less independent parts: upper, or clavicular, middle-sterno-clavicular (upper and lower) and lower-abdominal. All these bundles converge radially, become tendinous, whereby the tendon of the clavicular portion becomes superficial, and the tendons of the remaining portions pass under it; thus the tendon has the shape of a very narrow bag, open towards the shoulder joint and filled with fatty tissue.
The shape of the muscle changes depending on the position of the arm. The muscle is covered in its upper part by skin, the superficial fascia, and the platysma; in the middle part by skin, the superficial fascia, and the mammary gland; and in the lower part only by skin and the superficial fascia. In turn, the muscle covers the pectoralis minor, subclavius, and intercostal muscles. Finally, the muscle is in contact along its upper edge with the deltoid muscle, and along its lower edge with the external oblique abdominal and serratus anterior muscles. Origin: clavicular part: clavicle—its medial half or even two-thirds; sterno-costal part: sternum—sternal membrane and II-VI (VII) ribs—their cartilaginous parts; abdominal part: sheath of the rectus abdominis muscle—its anterior leaf. Insertion: humerus—crest of the greater tubercle of the humerus. Anterior thoracic nerves I and II. C(V), VI, VII and D1. Blood supply. Action. Variations. Branches of the ulnar artery. Palmar flexion of the hand. Variations are so frequent that it is difficult to determine the typical form of the muscle: 1) Complete absence is frequent (22-27%, according to other authors less often; Le Double accepts an average of 11.2%); 2) the entire muscle may be fleshy, or only the middle part, or, conversely, only its upper or lower part may be digastric, or the whole thing may be tendinous; 3) it may originate from the antebrachial fascia, from the lacertus fibrosus, from the flexor carpi ulnaris or radialis, from the humerus, radius, and ulna; 4) it may attach to the antebrachial fascia, thenar, carpus, or abductor pollicis longus muscle; 5) the muscle may be double, or only the tendon, or the entire muscle; both parts may attach to different points or originate from different places, e.g., one on the ulna, the other on the radius. External pudendal and medial circumflex femoral arteries from the femoral artery and obturator artery from the hypogastric artery. Raises the thigh, rotates it outward, and adducts it. 1) Occasionally it may be absent altogether; 2) it may originate from the hip joint; 3) it may attach to the lesser trochanter; 4) it may fuse with the obturator externus muscle or with the adductor longus muscle; 5) it is frequently doubled; 6) it may have accessory bundles: a) from the iliacus muscle; b) from the obturator externus muscle. Lateral coraco-acromial artery from the axillary artery and branches from the intercostal arteries. Adducts and rotates the arm inward; in a horizontal position of the arm, it adducts it in the sagittal direction (anteversion); it lowers a raised arm; the clavicular part can raise the shoulder ("shrug the shoulders"). With a fixed limb, movements of the chest (deep breathing) and the whole body (climbing with the help of the arms) are possible. 1) Isolated from other anomalies of the muscular system, complete absence of the muscle is extremely rare; more often there is complete or partial underdevelopment of one or another part: only the clavicular part may remain, or the clavicular and abdominal parts, or the sterno-costal and abdominal parts; 2) partial defects of the sterno-costal part are frequent in the presence of the sternalis muscle; the abdominal part is especially often reduced; 3) sharp demarcations of individual parts are not uncommon; 4) the origin of the clavicular part may be insignificant and limited only to the sternal end of the clavicle, but more often, conversely, the clavicular part extends to the deltoid muscle, from which it is difficult to separate in such a case; 5) the sterno-costal part may originate from the tendon of the sternocleidomastoid muscle or cross with its antimere; fusion of both antimeres along the midline and transition into each other without a boundary is possible; 6) the origin of the abdominal part may descend to the first tendinous intersection; connection with the rectus muscle, origin from the fascia of the external oblique abdominal and serratus anterior muscles, and even from the IX intercostal space between the teeth of the serratus anterior muscle is possible; 7) often the superficial bundles of the sterno-costal and clavicular parts send their tendinous fibers into the fascia of the arm—tensor fasciae brachialis muscle—along the medial bicipital groove to the medial epicondyle, and even through the deltoid muscle into its fascia; 8) occasionally the terminal tendon splits and allows the tendon of the biceps muscle (long head) to pass through; this split bundle attaches to the crest of the greater or lesser tubercle; splitting can occur with each of the three portions; the tendon of the abdominal part often transitions into the coracobrachialis fascia (chondro-coracoideus muscle), into the capsule of the shoulder joint, the subdeltoid bursa, and the tendon of the supraspinatus muscle; in the presence of an "axillary muscular arch," its tendinous attachment often adjoins the aberrant tendon of the pectoralis major muscle. Name in Latin and Russian. Synonyms. Form and position. Innervation and relation to segments. Origin and insertion. Pectoralis minimus (Gruber) (least pectoral muscle). Syn.: chondro-coracoideus ventralis. [Very rare muscle.] Origin: first costal cartilage. Insertion: scapula—coracoid process, its ventro-medial edge. Branch of the anterior thoracic nerve. Pectoralis minor (lesser pectoral muscle). Syn.: coraco-pectoralis, serratus anticus minor, axillaris. A more or less triangular mass consisting of three to five large serrated bundles and located on the antero-lateral part of the chest wall between the III, IV, and V ribs on one side and the coracoid process of the scapula on the other. The muscle is covered by the pectoralis major muscle and in turn covers the intercostal muscles and partly the serratus anterior muscle. The terminal tendon of the muscle is in close contact with the tendon of the coracobrachialis muscle and the coracoid head of the biceps brachii muscle. Origin: III-V ribs and the aponeurosis of the external intercostal muscles. Insertion: scapula—coracoid process and coracobrachialis fascia. Anterior thoracic nerves. C VII and VIII. Pectoralis quartus (Macalister) (fourth pectoral muscle). [Not uncommon variation.] A not uncommon variation occurring in various forms; when well-developed, it originates from the V rib and the fascia of the first tooth of the external oblique abdominal muscle or the sheath of the rectus abdominis muscle and attaches to the tendon of the pectoralis major muscle or to the coracobrachialis fascia and the biceps brachii muscle. Anterior thoracic nerves. Peronaeo-tibialis (Pürst) (peroneo-tibial muscle). [Variation (8% according to Krause and 15% according to Gruber).] A muscular plate at the proximal end of the interosseous space below the proximal articulation of the tibia and fibula. Origin: fibula—head of the fibula. Insertion: tibia—popliteal line of the tibia. Peronaeus brevis (short peroneal muscle). Syn.: peronaeus anticus, s. medius, s. secundus, s. sextus, peronaeo-calcaneus externus, fibularis, semifibularis, semifibulaeus. A thin, pinnate, long muscle, located on the lateral surface of the lower leg between the extensor digitorum longus in front and the peronaeus longus behind; the latter muscle covers it almost completely. The long tendon passes behind and below the lateral malleolus and runs along the lateral edge of the foot. Origin: fibula—lateral surface of the fibula, from its second third to the lateral malleolus and the anterior and posterior intermuscular septa. Insertion: fifth metatarsal bone—tuberosity of the fifth metatarsal and, by means of a thin tendon, to the V toe. Superficial peroneal nerve.
L(iv), v and Si 602 Blood supply Action Variations: on the sides, these muscle bundles sometimes extend distally along the medial edge of the m. bicipitis to the septum intermusculare mediale, to the m. brachialis, to the epicondylus—m. chondro-epitrochlearis and to the fascia of the forearm; the m. sterno-chondro-epitrochlearis differs from the previous one only in that it starts from the middle of the costal teeth; it attaches with a tendinous arch to the fascia of the arm, near the tendon of the m. pectoralis major or the capsule of the shoulder joint. A modification of the muscle is the m. coraco-clavicularis singularis anterior, which starts from the bursa of the sternoclavicular joint and from the sternal edge of the clavicle and attaches to the processus coracoideus. A. thoraco-acromialis from the a. axillaris and aa. intercostales. Lowers and moves the girdle of the upper limb forward; with a fixed scapula, it raises the chest wall. 1) Isolated from other anomalies in the muscular system, complete absence of the muscle was observed, apparently, once; together with defects of other muscles—more often: 2) division into 2 layers was described several times: m. axillaris is the second layer, consisting of three teeth along the I and II ribs; m. pectoralis minor secundus from the II and III ribs or from the IV or from the V and VI ribs; 3) division into two portions is possible, due to the absence of the middle part; once one of these portions went from the III and IV ribs to the processus coracoideus, and the other from the V and VI ribs to the tuberculum majus humeri; 4) variations of the origin are very frequent: from the II-IV ribs, or II-V, or III-VI, or IV and V, or only from the IV rib; 5) attachment to the processus coracoideus can be partial or even absent altogether; part of the tendon can pass through a gap in the lig. coraco-acromiale, into the lig. coraco-humerale, into the tendon of the m. supraspinatus, can attach to the tuberculum majus humeri, to the capsule of the shoulder joint, to the collum scapulae; it can pass into the initial tendon of the m. coraco-brachialis, bicipitis brachii (caput breve), lig. coraco-acromiale, fascia coraco-brachialis, the tendon of the m. pectoralis major, rarely into the fascia coraco-clavicularis and attach to the crista tuberculi majoris or even to the clavicle; 6) connections of the deep bundles of the m. pectoralis major from the V rib and the m. pectoralis minor are observed. The shape of the muscle can vary from spindle-shaped, cylindrical, quadrangular to triangular. A. peronaea and a. tibialis anterior. Flexes the foot in the plantar direction, pronates and abducts it. An accessory tendon (m. peronaeus digiti quinti Wood) can attach in various places: a) distal end of the first phalanx of the V digit—usual location; b) aponeurotic expansion of the tendon of the m. extensor digitorum to the V digit; c) to this tendon itself; d) to the tendon of this muscle to the IV digit; e) to the body or head of the metatarsalis V; f) to the IV metatarsale; g) to the os cuboideum; h) to the m. abductor digiti V. 604: No. Name Latin and Russian. Synonyms. Shape and position. Origin and attachment. Innervation and relation to segments. Peronaeus longus (long peroneal muscle). Syn.: peronaeus posticus, s. primus, s. fibularis, s. fibulaeus primus longus. A large, bipennate, prismatic-shaped muscle located on the lateral surface of the lower leg in the peroneal osteomuscular bed, formed in front by the m. extensor digitorum longus, inside by the fibula, behind by the m. soleus and outside by the fascia cruris. A thin, long tendon, which began with a wide aponeurotic plate on the outer surface of the muscle in its lower half, bypasses the malleolus lateralis from behind and below (first bend), passes under the processus trochlearis ossis calcanei and the tuberositas ossis cuboidei and bends onto the dorsal surface of the foot (second bend). Origin: tibia—condylus lateralis tibiae, bursa articulationis tibiofibularis, fibula—capitulum fibulae, upper third of the crista anterioris and lateralis fibulae and septa intermuscularia anterius and posterius. Attachment: 1) first metatarsal bone—tuberositas ossis metatarsalis I (II), 2) its distal end and 3) first cuneiform bone—its plantar surface. N. peronaeus superficialis. L(iv), v and Si. Peronaeus parvus (small peroneal muscle). [Variation (norm in most monkeys).] Origin: fibula, between both peroneal muscles. Attachment: to the fifth digit together with the tendon of the m. extensor longus. Peronaeus quartus (fourth peroneal muscle). Syn.: sextus, calcaneus externus, accessorius, medius. [Variation.] When fully developed, the belly lies on the lower part of the fibula, and its tendon passes to the plantar surface of the foot. Origin: fibula—facies posterior in its lower part, between the m. peronaeus brevis and the m. flexor hallucis longus. Attachment: tendon of the m. extensor digitorum longus or one of the phalanges of the V digit. Peronaeus tertius (third peroneal muscle). Syn.: peronaeus parvus, adductor digiti quinti pedis longus, s. fibularis. Represents a part of the m. extensor digitorum longus. Origin: together with the m. extensor digitorum longus. Attachment: os metatarsale V (and IV). N. peronaeus profundus. L(iv) and v and Si. Pharyngo-epiglotticus (Tourtual) (pharyngo-epiglottic muscle). Bundle of the m. stylo-pharyngei under the plica stylo-pharyngea. Pharyngo-palatinus (pharyngo-palatine muscle). Syn.: palato-pharyngeus, levator pharyngis internus, pharyngo-staphylinus, thyreo-pharyngo-palatinus, constrictor isthmi pharyngo-nasalis. Origin: lateral wall of the pharynx, as well as the thyroid cartilage—lamina thyreoidea (its posterior surface) and cornu inferius. Attachment: aponeurosis of the soft palate (its posterior surface), where the opposite bundles converge, as well as to the cartilaginous part of the auditory tube and the sphenoid bone—hamulus pterygoideus and lamina medialis. N. vagus—rr. pharyngei. Piriformis (piriform muscle). Syn.: primus quadrigeminus, iliacus externus piriformis, quadrigeminus, pyramidalis. A flattened-piriform or triangular-pyramidal muscle, lies partly in the pelvis on the anterior surface of the sacrum, partly outside the pelvis between it and the thigh; here it is located between the m. glutaeus medius and the m. gemellus superior and is covered by the m. glutaeus maximus. Origin: sacrum—facies pelvina laterally from the foramina sacralia anteriora (II-IV), bursa articulationis sacro-iliacae, hip bone—upper edge of the incisura ischiadica majoris. Attachment: thigh—trochanter major, its inner surface. Branches from the plexus sacralis. Si, ii (iii). Plantaris (plantar muscle, or muscle tensing the plantar aponeurosis, or small calcaneal). Syn.: extensor pedis minor, s. tarsi minor, s. gracilis, s. gracillimus surae. A very small elongated-piriform muscle body lies in the popliteal fossa between the m. popliteus and is covered by the m. soleus and gastrocnemius; a long thin tendon first lies against the medial edge of the m. soleus, and then lies between them m. gastrocnemius. Origin: thigh—planum popliteum femoris above the condylus lateralis and bursa of the knee joint. Attachment: calcaneus—tuber calcaneum, medially from the tendo calcaneus (and aponeurosis plantaris). N. tibialis.
Blood supply, action, variations: A. genu inferior lateralis, a. peronea, tibialis anterior. Flexes the foot in the plantar direction, pronates and abducts it outward. 1) The muscle may start with two heads; 2) the attachment of the tendon may be limited to two or even one of its usual attachment sites; 3) it may attach to the second metatarsal, to the m. tibialis posticus; 4) fusion with the m. peronaeus brevis at the upper end and fusion of their tendons has been observed once; 5) attachment to the malleolus lateralis has been observed once. The muscle more often atrophies at its distal end and may attach: a) to the os cuboideum—this is the m. peronaeo-cuboideus of Chudzinski or m. peronaeus accessorius of Henle; b) to the os calcaneum—facies lateralis—this is the m. peronaeus calcaneus externus or peronaeus sextus. A. tibialis anterior. Flexes the foot in the dorsal direction and raises its lateral edge (pronation). 1) The muscle represents all stages from complete independence of the muscle belly and tendon to complete fusion with the m. extensor digitorum longus; 2) it may occasionally (8.2%) be absent altogether; 3) it may provide an additional tendon to the fifth toe, to the base of the fourth metatarsal bone, to other neighboring parts. The posterior palatine arch constricts the fauces. Aa. glutaea superior and inferior from the a. hypogastrica. Rotates the thigh outward. 1) It may start from all sacral vertebrae and down to the coccyx; 2) the absence of the muscle has been noted in the literature, which Le Double, however, considers a fusion with neighboring muscles; 3) it may start only from the second and third or third and fourth sacral vertebrae; 4) the tendon of the muscle may fuse with the tendon of the m. gemellus superior and the mm. obturator internus, gluteus medius and minimus; 5) the muscle may be divided into two or three portions. A. poplitea. Takes part in the plantar flexion of the foot, and furthermore, it tenses the capsule of the knee joint (it can also tense the plantar aponeurosis). Variations of this muscle are most frequent; they concern primarily the size of the muscle; 1) the muscle may not develop at all; 2) on the other hand, it may have a second belly in the distal part—this is the m. digastricus surae; 3) it may start: a) mainly on the tibia; b) from the lig. posterius of the knee joint; c) from the aponeurosis of the m. popliteus; d) from the beginning of the lateral head of the m. gastrocnemius; e) from the fibula—between the m. peronaeus longus and flexor hallucis longus; f) from the aponeurosis of the thigh; 4) there may be additional muscle bundles from the aponeurosis of the m. soleus, from the fascia cruris, from the femur and fibula simultaneously; 5) with one origin, a double attachment is possible: medially to the Achilles tendon, and laterally to the lig. laciniatum. Name (Latin and Russian). Synonyms. Form and position. Origin and attachment. Innervation and relation to segments. Platysma myoides (subcutaneous muscle of the neck). Syn.: subcutaneus colli, latissimus colli, quadratus genae, detrahens quadratus communis buccarum labiorumque. The muscle is a very thin plate of muscle fibers, which are sometimes separated from each other, maintaining their parallel direction to each other from top to bottom and in the lateral direction; in its lower part, the muscle fibers diverge more widely, and at the top they converge. The muscle occupies the lower part of the face in front (from the corner of the mouth to the m. masseter), the entire anterolateral surface of the neck, except for a small triangle from the incisura sterni to the chin, part of the region above the m. pectoralis to the level of the second to fourth ribs and above the deltoideus to the processus acromialis. The muscle lies between two layers of the fascia superficialis colli and covers the deeper muscles of the neck and partly the mm. pectoralis and deltoideus. Origin: lower jaw—margo inferior from the level of the foramen mentale to the height of the first molar tooth and the fascia parotideo-masseterica. Attachment: skin of the second to fourth intercostal spaces and to the processus acromialis behind and from the side. N. facialis—r. colli. Platysma risorius. Syn.: risorius platysma. See m. platysma. Popliteus (popliteal muscle). Syn.: subpopliteus, in poplite occultus, oblique movens tibiam. A small triangular muscle, located obliquely in the depth of the popliteal fossa and covered by the m. plantaris and m. gastrocnemius. Origin: thigh—fossa, condylus and epicondylus lateralis femoris and the articular capsule of the knee joint (lig. arcuatum). Attachment: tibia—linea poplitea tibiae. N. tibialis. Praeclavicularis lateralis (Gruber) (lateral preclavicular muscle). Syn.: acromio-clavicularis superficialis. [A not infrequent atypical muscle (1:140).] See m. infraclavicularis. Praeclavicularis subcutaneus (Gruber) (subcutaneous preclavicular muscle). [Variation.] See m. platysma. Praerectalis (Henle) (prerectal muscle). Anterior medial bundles of the longitudinal muscle layer of the rectum. Procerus (muscle of the proud). Syn.: dorsalis narium, pyramidalis nasi, Santorini, nasium dilatans, depressor glabellae nasi. A small muscle band on the bridge of the nose, located immediately under the superficial fascia and skin on the bones. Origin: bony bridge of the nose and aponeurosis of the pars transversa of the m. nasalis. Attachment: skin over the glabella and continues into the m. frontalis. N. facialis. Pronator quadratus (square pronator). Syn.: pronator inferior, s. parvus, s. transversus, quadratus antibrachii, cubito-radialis. A thin, irregularly quadrilateral plate of muscle fibers, transversely located in the distal part of the forearm, on the bones themselves under all the flexors of the hand and fingers, directly covered by the m. flexor digitorum profundus and flexor pollicis longus. Origin: ulna—facies volaris, its distal quarter. Attachment: radius—facies volaris, its distal quarter. N. medianus—r. interosseus volaris. C(VI), VII and VIII and D1. Blood supply, action, variations: R. submentalis from the a. maxillaris externa and a. cervicalis superficialis and ascendens from the a. subclavia. Raises the skin of the neck. 1) Complete absence is possible; 2) lengthening to the level of the fourth rib or shortening to the clavicle is observed; 3) it extends from one side to the other; 4) it is divided into separate bundles; 5) the m. transversus nuchae is isolated—transverse bundles in the region of the neck behind; 6) platysma-risorius—bundles going radially to the corner of the mouth; 7) bundles are possible that pass from one or both sides into the m. triangularis; it may adjoin the m. transversus menti and strengthen it; some fibers may go in the direction of the deep bundle of the m. mentalis and attach to the lower jaw; 8) deviations in the direction of some bundles from the general direction of the muscle are quite frequent; 9) deviations of individual portions were observed both along the edges of the muscle and on its surface, of quite significant size: a) along the dorsal edge near the ear, bundles may start tendinously in the fascia of the m. sternocleidomastoideus or in the region of the processus mastoideus and end in the fascia parotidea or on the surface of the platysma above or below the edge of the jaw; along the medial edge, the fibers may cross and descend to the second and third costal cartilages or form arcuate bundles located between the clavicles and on the sternum; b) aberrant bundles on the surface of the muscle may have longitudinal and transverse directions; the latter is more frequent in the region of the jaw, less frequent in the caudal parts of the muscle; such is the m. praeclavicularis subcutaneus (Gruber), which in the form of a thin triangular plate departed from the articulatio sternoclavicularis and along the beginning of the m. pectoralis and deltoideus and went to the processus acromialis; such is also the character of the m. tensor fasciae brachii; c) deeper changes are relatively rarer; these include: division into two layers—superficial and deep; division into independent—caudal and cranial segments of the muscle (Seydel); a case where there were two layers and of them the deep one disintegrated into cranial and caudal segments; the transverse deep layer corresponds to the m. sphincter colli of animals. Branch of the a. poplitea and a. genu medialis. Flexes the leg at the knee joint, rotates the bent knee outward. 1) Very rarely it may be absent altogether; 2) a second head was observed by several anatomists, starting from the sesamoid bone of the lateral head of the m. gastrocnemius—this is the m. popliteus biceps (Gruber), popliteus geminus (Fabricius ab Aquapendente) and others. A. angularis from the a. maxillaris externa and a. ethmoidalis anterior from the a. ophthalmica. Pulls the skin over the bridge of the nose downward. 1) It may be absent on one or both sides; 2) complete separation from the m. frontalis is possible; 3) it may start only from the bony bridge of the nose; 4) occasionally it connects with the caput angulare of the m. quadratus labii superioris and more often with the m. corrugator supercilii. A. interossea volaris. Pronates the forearm. 1) It may be absent altogether; 2) it may extend over a larger space than usual; 3) the shape may not be square, but different, even triangular; 4) the direction of the fibers may be different; 5) sometimes the muscle does not end at the level of the radiocarpal joint, but continues onto the capsule of the articulatio radiocarpea, onto the os naviculare and multangulum majus and even further distally.
Syn.: pronator magnus, s. obliquus, s. rotundus. The muscle has a somewhat flattened belly from front to back, transitioning into an even flatter tendon; the muscle lies in the proximal part of the forearm obliquely from inside to outside, between the m. flexor carpi radialis on the inside and the m. brachio-radialis on the lateral side, covered besides the skin and fascia superficialis also by the lacertus fibrosus, and it covers the attachment of the m. brachialis, m. flexoris digitorum sublimis, and the m. supinatoris. Origin: caput humerale: humerus-epicondylus medialis humeri, septum intermusculare mediale (processus supracondyloideus); caput ulnare: ulna-tuberositas ulnae, its medial edge. Insertion: radius-facies lateralis radii in the middle of its length (tuberositas radii). N. medianus. Cvi and VII. Prostaticus superior (Winslow): Middle part of the m. levatoris ani. Protractor arcus cruralis (Gruber) (Muscle tightening the femoral arch). [Variation.] See m. obliquus externus abdominis. Psoas major (greater psoas muscle). Syn.: psoas magnus, lumbalis, s. lumbalis internus. The muscle represents a large, long, spindle-shaped mass located on the lateral surfaces of the vertebral bodies and lateral processes, on the medial part of the fossae iliacae, along the lateral edge of the horizontal branch of the pubic bone, and on the anterior surface of the hip joint. Origin: XII thoracic and I-IV lumbar vertebrae, lateral surface of the body and processus lateralis. Insertion: femur-trochanter minor femoris. Branch from plexus lumbalis. Psoas minor (lesser psoas muscle). Syn.: psoas parvus. [Inconstant muscle.] A thin, spindle-shaped muscle located on the m. psoas major in the lumbar region. Origin: XI thoracic and I lumbar vertebrae-lateral surface of the body. Insertion: pubic bone-pecten ossis pubis, transitions into the fascia of the m. psoatis majoris (ligamentum ilio-pectineum) and fascia iliaca. Branch from plexus lumbalis. L(I), and (II and III and IV). Pterygoideus externus: caput, s. fasciculus superior, s. sphenoidalis and fasciculus inferior, s. pterygoideus (external pterygoid muscle). Syn.: pterygoideus minor, s. exterior, s. abducens, alaris externus. A small, short, but strong muscle consisting of two more or less independent bundles located in the sagittal plane between the pterygoid processes of the os sphenoidei and the articular process of the mandibulae. It is in contact with its medial surface with the m. pterygoideus internus, and laterally partially with the m. masseter. Origin: caput superius: sphenoid bone-planum infratemporale alae majoris; caput inferius: lamina externa processus pterygoidei. Insertion: lower jaw-fovea pterygoidea processus articularis, capsula articularis and discus articularis. N. mandibularis-r. pterygoideus. (I mandibular arch). Pterygoideus internus (internal pterygoid muscle). Syn.: pterygoideus major, masseter internus, alaris internus. A fairly large muscle in the form of a quadrilateral plate, lying between the pterygoid processes of the os sphenoidei and the lower jaw. Origin: pterygoid bone-fossa pterygoidea ossis sphenoidalis. Insertion: lower jaw-angulus mandibulae, tuberositas pterygoidea. N. mandibularis-n. pterygoideus. (I mandibular arch). Pterygoideus proprius (proper pterygoid muscle). [Variation.] See m. pterygoideus externus. Pterygo-fascialis (Poland) (pterygoid-fascial muscle). See m. pterygoideus internus. Pterygo-pharyngeus (pterygoid-pharyngeal muscle). The first bundle of the m. constrictoris pharyngis superioris (see above), which departs from the hamulus pterygoideus and lamina medialis processus pterigoidei. Blood supply: Branches of the aa. brachialis, radialis, and ulnaris. Action: Pronates the forearm. Variations: 1) The origin of the capitis humeralis is variable, which can reach up to half the length of the humerus; 2) there may be additional bundles or heads: from the septum intermusculare mediale, m. brachialis, fascia brachii, aponeurosis antibrachii; 3) thanks to this, there may be a doubling of the capitis humeralis; 4) in the presence of an independent caput ulnare, the muscle may consist of three or four heads; 5) the attachment may also occupy a larger or smaller space. A. subcostalis and aa. lumbales from the aorta abdominalis, a. ilio-lumbalis from the a. hypogastrica, and branches of the a. femoralis. Flexes the thigh at the hip joint and rotates it outward. When the thigh is fixed, it flexes the trunk at the hip joint forward. 1) There may be connecting bundles between the muscle and a) m. psoas minor; b) m. iliacus; 2) the m. psoas and m. iliacus may completely merge; 3) it may be divided into several bundles. R. lumbalis from the aorta abdominalis. Tightens the fascia iliaca. 1) It is more often absent than present; 2) it may originate even from the XII thoracic vertebra; 3) there may be an additional muscle above the m. psoas major, which originates from the III lumbar vertebra and attaches either to the eminentia ilio-pectinea or to the trochanter minor; 4) the muscle may attach: a) to the os femur between the trochanter minor and caput femoris; b) to the trochanter minor. Branch of the a. maxillaris internae. Simultaneous contraction of both muscles moves the lower jaw forward; contraction of one side shifts the jaw to the opposite side. 1) The caput superius may be absent; 2) the caput superius may be tendinous; 3) the same may be partially true for the lateral part of the capitis inferioris; 4) individual bundles may separate and attach to the capsula articularis; 5) m. pterygoideus proprius-these are muscle bundles that originate in different places of the crista infratemporalis and attach: to the lower edge of the laminae lateralis processus pterygoidei or processus pyramidalis, processus alveolaris of the upper jaw, raphe pterygo-mandibularis, tuber maxillare; its fibers may transition into the m. buccinator, pterygoideus internus, tendon of the m. temporalis; 6) Bradley found one time on both sides a muscle that went from the processus styloideus to the posterior edge of the meniscus of the jaw joint, but due to the lack of indication of innervation, it is impossible to establish whether it belongs here. Branch of the a. alveolaris superioris, a. buccinator, a. alveolaris inferior. Elevates the lower jaw. 1) Sometimes there is a bundle connecting the muscle with the m. tensor veli palatini; 2) the medial bundle may depart from the tendinous arch between the foramen caroticum and the raphe pterygo-mandibularis; 3) m. pterygo-spinosus s.-these are muscle fibers parallel to the lig. pterygo-spinosum (Civinini); 4) m. pterygo-fascialis-a muscle bundle that originates from the lig. spheno-mandibulare. Pterygo-spinosus (Thane) (pterygoid-spinous muscle). See m. pterygoideus internus. Pubo-prostaticus (Velpeau) (puboprostatic muscle). Anterior medial bundle of the m. levatoris ani. Pubo-uretralis (pubourethral muscle). Anterior medial bundle of the m. levatoris ani. Pubo-vesicalis (pubovesical muscle). Syn.: depressor vesicalis, s. vesicae urinariae, levator prostatae. Origin: pubic bone-symphysis ossium pubis. Insertion: orificium urethrae internum. Pyramidalis abdominis (pyramidal muscle). Syn.: pyramidalis pelvis, triangularis, succenturiatus, iliacus externus, rectus abdominis anticus minor. A small triangular muscle located on the sides of the linea alba, with its base adjacent to the os pubis, and its apex facing cranially; it is covered by the outer layer of the vaginae m. recti abdominis and is adjacent to the m. rectus abdominis. Origin: pubic bone-symphysis ossium pubis. Insertion: linea alba. N. thoracalis XII. ThXII and (LI). Pyramidalis auriculae (Jungi) (pyramidal muscle of the auricle). Syn.: fasciculus accessorius m. tragici, superficialis tragici. [Rare muscle.] Origin: auricle-tragus. Insertion: auricle-spina helicis. N. facialis. Quadratus femoris (quadrate muscle of the thigh). Syn.: quadratus cruris, quadrigeminus quartus. A rectangular muscle plate, only in a contracted state taking the form of a square, located between the ischial tuberosity and the thigh in the frontal plane, i.e., the plane of the adductors below them and the mm. gemelli and m. obturator externus, above it; it is in contact with them, and posteriorly it is covered by the m. glutaeus maximus. Origin: ischial bone-tuber ischiadicum, its lateral surface. Insertion: thigh-from the crista intertrochanterica to the tuberositas glutaea. Branch from the n. ischiadicus (n. tibialis). LIV, V and SI. Quadratus labii inferioris (quadrate muscle of the lower lip). Syn.: quadratus inferior, s. menti, depressor labii inferioris proprius, mento-labialis. An oblique plate of muscle fibers located on the lateral parts of the chin between the lower edge of the mandibulae in the region of the canine and three premolars on one side and the lower lip on the other; the muscle represents a direct continuation of the platysmatis, interrupted by the attachment of fibers to the lower jaw; in front it is covered partly by the m. triangularis, and then by the fascia superficialis and skin. Origin: lower jaw-its lower edge, outside the tuberculum mentale, platysma. Insertion: skin of the entire lower lip. N. facialis-r. marginalis mandibulae. Quadratus labii superioris: caput angulare, caput infraorbitale and caput zygomaticum (quadrate muscle of the upper lip).
Syn.: levator alae nasi et labii superioris, levator labii superioris proprius, zygomaticus minor of earlier anatomists. Caput angulare = m. retractor, s. dilatator nasi et elevator labii superioris pyramidalis, levator labii superioris alaeque nasi, levator alae nasi labiique superioris; caput infraorbitale = elevator labii superioris, s. proprius, incisorius (superior), levator labii superioris proprius; caput zygomaticum = zygomaticus minor. The muscle consists, strictly speaking, of three separate muscles; at the point of attachment they may fuse together, but the points of origin form, as it were, a single line, while at the same time all three heads prove to be more or less independent. This applies especially to the middle head, caput infraorbitale, which lies deeper than the other two. Thus, the entire muscle represents a peculiar conglomerate. Origin: caput angulare: upper jaw—processus frontalis and margo orbitalis; caput infraorbitale: upper jaw—margo orbitalis to processus zygomaticus; caput zygomaticum: zygomatic bone—m. orbicularis oculi. Insertion: caput angulare: skin of the cheek, upper lip, and wings of the nose; caput infraorbitale: skin of the upper lip; caput zygomaticum: skin of the cheek near the corner of the mouth. N. facialis—rr. zygomatici. Blood supply. Action. Variations: 1) May be absent on both sides (in Europeans on average 16.8%, in Japanese 3.3%), less often on one side, in which case more often on the left, most frequently in female cadavers; 2) the size of the muscle varies even in antimers, generally the left is more often smaller than the right; it may reach the navel; 3) rarely—inscriptio tendinea; 4) division into 2, 3, and 4 bundles has been described, apparently from the ingrowth of fibers of the rectus abdominis muscle sheath. A. epigastrica inferior. Tenses the linea alba. A. glutaea inferior, circumflexa femoris medialis and a. obturatoria. Rotates the thigh outward. 1) Rarely (2.4%) may be absent entirely; 2) may be inseparable from m. gemellus inferior or m. adductor minimus; 3) may divide into two layers. A. labialis inferior and a. submentalis from a. maxillaris externa, a. mentalis from a. maxillaris interna. Pulls the lower lip downward. 1) Cases of splitting into two portions have been observed; 2) various degrees of development are possible, from very strong with one extending across the midline into the region of the antimer, to very weak, when only an insignificant part of the chin is covered; 3) various degrees of proximity to m. platysma are observed. A. infraorbitalis from a. maxillaris interna, a. labialis superior and a. angularis from a. maxillaris externa. Raises the entire upper lip and the wing of the nose. 1) The muscle varies from complete fusion of all portions into a single muscle to distinct separation along the entire length into three muscles; 2) caput angulare fuses with caput infraorbitale, is reinforced and even doubled by bundles from m. orbicularis oculi, continues into m. frontalis and reaches m. depressor supercilii; on the other hand, bundles of the muscle may rise to the origin of m. procerus, running transversely across the bridge of the nose; the anterior bundle, which attaches to the wings of the nose, may be sharply separated or absent; it may be perforated by caput transversum m. nasalis; 3) caput infraorbitale may be absent entirely on one side, on the other it may be doubled, divided into two or three portions; the origin may fuse medially with the origin of the capitis angularis, laterally reaching the os zygomaticum; lateral bundles may adjoin m. caninus; 4) caput zygomaticum may be absent on one or both sides, may be reduced to a few bundles or be very wide and fuse with m. zygomaticus; the origin may extend to the fascia temporalis, may partially close with lateral bundles of m. orbicularis oculi: medial bundles may extend through caput infraorbitale to the wings of the nose, lateral ones—pass into m. zygomaticus and m. caninus. A. subcostalis and aa. lumbales from aorta abdominalis and a. [The table columns are: No., Latin and Russian Name, Synonyms, Form and Position, Origin and Insertion, Innervation and relation to segments, Blood supply, Action, Variations]. Quadratus lumborum: pars ventralis (interna), pars dorsalis (externa) and pars intermedia (quadrate muscle of the loin). Syn.: rectus abdominis posticus, scalenus lumborum et ilio-lumbalis, transversalis lumborum—pars dorsalis. A muscle mass filling the quadrangular space between the last rib above, the bodies of the lumbar vertebrae and their transverse processes on the medial side, and the posterior half of the iliac crest below. Ventrally it adjoins m. psoas, and dorsally it is covered by fascia lumbo-costalis. Origin: pars ventralis: iliac bone—crista iliaca, its labium mediale, lig. ilio-lumbale; pars dorsalis: iliac bone—crista iliaca, lig. ilio-lumbale; pars intermedia (variable): lumbar vertebrae—transverse processes. Insertion: pars ventralis: XII vertebra and XII rib, lig. lumbo-costale; pars dorsalis: I-IV lumbar vertebrae—processus lateralis and XII rib; pars intermedia: XII rib. Segmental nerves of the lumbar region. Dxii, Li, Lii and Liii. Quadratus plantae: caput externum and internum (quadrate muscle of the sole). Syn.: caro quadrata, caput plantare (quadratum) m. flexoris digitorum pedis longi, accessorius perforantis, flexor accessorius pedis. A flat, elongated quadrangular muscle lying on the plantar surface of the foot on lig. calcaneo-cuboideum plantare and covered from below by m. flexor digitorum brevis, from which it is separated by a layer of loose connective tissue. Origin: by two heads from the calcaneus, from the lateral and medial edges of the plantar surface. Insertion: m. flexor digitorum longus—its lateral edge. N. plantaris lateralis. Si and Sii. Quadriceps cruris (quadriceps muscle of the thigh). Syn.: extensor cruris quadriceps, triceps femoris, quadriceps femoris. See m. rectus femoris and vasti intermedius, lateralis and medialis. Radialis internus brevis (Gruber) (short, internal radial muscle). Syn.: flexor carpi radialis brevis. [Variation] A special muscle of small size, which is found under m. flexor pollicis longus. Origin: radius. Insertion: os multangulum majus. Recti labiorum (Aeby) (straight muscles of the lips). Part of the fibers of m. orbicularis oris, which run in a sagittal direction into the skin of the lips. Recto-coccygeus (muscle, retracting the rectum). Syn.: retractor recti. A small paired muscle, which runs from the II and III coccygeal vertebrae into the longitudinal muscle layer of the rectum. Recto-uterinus (muscle, retracting the uterus), see retractor uteri. A bundle of smooth muscle fibers, which run from the rectum to the outer muscle layer of the uterus and vagina. Recto-vesicalis. A bundle of smooth muscle fibers, which run from the rectum to the urinary bladder. Rectus abdominis (straight muscle of the abdomen). Syn.: rectus anticus major, s. anterior abdominis. Represents a long, but relatively thin muscle band, divided along its length into parts by means of (2) 3-5 tendinous intersections (inscriptio tendinea), running transversely. The muscle is located on the anterior part of the abdominal wall, on the sides of the midline of the body (linea alba), in the space between the sternum and cartilaginous ribs above and the pubic bone below. The muscle lies in a sheath (vagina m. recti abdominis), formed by the tendinous plates of the oblique and transverse muscles of the abdomen. Origin: V-VII costal cartilages, sternum—corpus and processus xiphoideus. Insertion: pubic bone from symphysis ossium pubis to tuberculum pubicum. Spinal nerves VII-XII, as an exception also IV-VI, and I lumbar. D(iv-vi) vii-xii, Li.
Psoas lumbalis from the lumbar artery. Flexes the lumbar part of the spine to its side; both together straighten it; lower the XII rib and the entire thoracic cage. 1) The width and thickness of the muscle vary strongly, as does the development of individual parts and the number of teeth; thus, on one side the attachment can rise to the XI vertebra and the XI rib, while on the other, the attachment to the XII vertebra turns out to be inconstant; 2) pars ventralis sometimes reduces so much that it becomes less noticeable than pars intermedia; 3) pars intermedia is the most variable in its development. M. quadratus plantae. Changes (corrects) the direction of action of m. flexor digitorum longus in the lateral direction. 1) Caput externum may be absent more often than caput internum, very rarely both heads may be absent; 2) tendons to the V digit, to flexor digitorum brevis, m. tibialis posticus, m. peronaeus are encountered occasionally; 3) additional bundles were observed: a) from m. peronaeus; b) from the lower third of the tibia; c) from the aponeurosis of m. flexor hallucis longus; d) simultaneously two bundles: one from the tibia, the other from m. tibialis posticus—this is m. peronaeo-calcaneus internus; e) from m. soleus; f) from m. peronaeus brevis; g) from the fibula; h) from the os calcaneum; i) from the ligamentum calcaneo-cuboideum. M. rectus abdominis. Takes part in the tension of the abdominal press; brings the thoracic cage closer to the pelvis; flexes the trunk forward. 1) Complete and partial absence was observed simultaneously with other deformities; 2) the width of the muscle varies quite significantly; 3) the bundle from the V rib may be absent; 4) the muscle may begin: from the VII rib, if it reaches the sternum, from the IV, III, II and even I rib (more often with the help of a tendon) and from the clavicle; 5) the caudal attachment can be up to 7 cm wide; it can consist of two layers, divide into bundles and attach to the tendon of m. transversus abdominis; 6) an additional bundle from the VI rib to the VIII costal cartilage was also observed under the normal muscle; 7) inscriptiones tendineae can increase in number up to 5 and extremely rarely up to 6 and decrease to 2 and even (very rarely) one; they can be of various shapes. Rectus capitis anterior (anterior straight muscle of the head). Syn.: rectus anticus minor, s. internus minor. Short, wide muscle plate on the very midline between the occipital bone and the I vertebra on its body, covered in front by m. longus capitis. Origin: I cervical vertebra—massa lateralis atlantis. Insertion: occipital bone—pars basilaris ossis occipitalis, in front of foramen magnum. Innervation: First cervical nerve—anterior branch, sometimes anastomosis with the second. Ci. Blood supply: Branch of a. vertebralis from a. subclavia and a. pharyngea ascendens from a. carotis externa. Action: Tilts the head forward. Variations: 1) May be completely absent or reduced to several bundles; 2) may not reach the base of the skull, but end in the membrana atlanto-occipitalis anterior; 3) may double; 4) the medial portion may be independent—m. rectus capitis anterior medius, s. minimus. Rectus capitis lateralis (lateral straight muscle of the head). Very small muscle bundle between the skull and the first vertebra on the side. Origin: I cervical vertebra—processus transversus atlantis. Insertion: occipital bone—pars lateralis ossis occipitalis. Innervation: First cervical nerve—anterior branch and anastomosis with the second. Ci and II. Blood supply: Branches of a. vertebralis from a. subclavia and a. occipitalis from a. carotis externa. Action: Tilts the head to the side. Variations: 1) Absence is extremely rare; 2) apparently, doubling is possible; 3) an additional bundle from the processus costo-transversalis of the epistropheus to the occipital bone is observed—this is m. rectus capitis lateralis longus. Rectus capitis posticus major (large posterior straight muscle of the head). Syn.: rectus capitis posterior major. More or less triangular bundle on the dorsal side of the neck between the occipital bone (base of the triangle) and the second vertebra, along the midline of the body, on the bones themselves between m. rectus capitis posticus minor on the medial side and mm. obliqui capitis superior and inferior on the lateral side, under m. biventer capitis. Origin: II cervical vertebra—processus spinosus epistrophei. Insertion: occipital bone—planum nuchale. Innervation: N. suboccipitalis—r. posterior. Ci. Blood supply: A. vertebralis. Action: Rotates the head to its side; with bilateral contraction tilts the head backward. Variations: 1) Absence of the muscle is rare; separation into two parallel bundles is observed; 2) there is an additional bundle under the normal one, which goes from the processus spinosus of the II and III vertebrae and lig. nuchae; 3) a bundle to the posterior atlanto-occipital ligament—is called m. tensor membranae atlanto-occipitalis posterioris. Rectus capitis posticus minor (small posterior straight muscle of the head). Syn.: rectus capitis posticus profundus. Very small triangular muscle along the midline of the body on the dorsal side of the neck between the occipital bone and the first vertebra, medially from m. rectus capitis posticus major and under m. biventer capitis. Origin: I cervical vertebra—tuberculum posterius atlantis. Insertion: occipital bone—planum nuchale under linea nuchae inferior. Innervation: N. suboccipitalis—r. posterior. Ci. Blood supply: A. vertebralis. Action: Rotates the head to its side; with bilateral action tilts the head backward. Variations: 1) May be absent altogether; 2) may double. Rectus femoris: two independent tendons: tendo verticalis and tendo transversa (straight muscle of the thigh). Syn.: rectus cruris, s. gracilis, nonus tibiam moventium, nonus tibiae musculus, extendentium tibiam secundus. Long, bipennate muscle, starting with two separate tendons, has the shape of a spindle flattened from front to back, tapering like a lance at both ends. Lies between m. vastus medialis and lateralis superficially under the skin and fascia lata cruris, only partially covered on the lateral side by m. tensor fasciae latae and m. sartorius, which bypasses it in a spiral; in turn, the muscle covers m. vastus intermedius and m. articularis genu. Origin: tendo verticalis: ilium—spina iliaca anterior inferior; tendo transversa: upper edge of the lip of the fossa acetabuli. Insertion: tibia, through the medium of lig. patellae proprium to tuberositas tibiae. Innervation: N. femoralis. Blood supply: A. circumflexa femoris lateralis and rr. perforantes from a. profunda femoris. Action: Extends the leg in the knee joint and flexes the thigh in the hip joint. Variations: 1) Very rarely is the origin of the tendo transversae from the acetabulum absent; 2) doubling of the origin from the spina iliaca anterior inferior was observed—double tendo verticalis; 3) there may be an additional tendon from the spina iliaca anterior superior. Rectus inferior oculi (inferior straight muscle of the eyeball). Syn.: deprimens, humilis. The tendon-muscle belly starting in the form of a thin long plate ends with a tendon (4-8 mm long) on the lower surface of the eyeball, firmly intertwining with the fibrous bundles of the sclera, due to which an anterior thickening of the sclera is formed. Origin: sphenoid bone—edge of fissura orbitalis superioris—annulus tendineus communis (Zinni). Insertion: eyeball in front of the equator—attachment belt (anterior thickening of the sclera), its lower part. Innervation: N. oculomotorius. Blood supply: A. ophthalmica—r. muscularis. Action: Rotates the eyeball downward. Rectus lateralis oculi (external straight muscle of the eyeball). Syn.: rectus oculi externus, abducens, indignatorius. In everything similar to m. rectus inferior oculi, but located on the lateral surface of the eyeball. Origin: sphenoid bone—by two tendons—one from the root of the alae parvae ossis sphenoidalis, the other from the annulus tendineus communis (Zinni). Insertion: eyeball in front of the equator—attachment belt (anterior thickening of the sclera), its lateral part. Innervation: N. abducens. Rectus medialis oculi (internal straight muscle of the eyeball). Syn.: rectus internus, amatorius. In everything similar to the two previous ones, but located on the medial surface of the eye, laterally from m. obliquus oculi superior. Origin: sphenoid bone—dorsally from fissura orbitalis superior—annulus tendineus communis (Zinni). Insertion: eyeball in front of the equator—attachment belt—its medial part. Innervation: N. oculomotorius. Rectus superior oculi (superior straight muscle of the eyeball). Syn.: rectus oculi major, attollens oculi, sublimis, superbus.
Similar in all respects to the previous ones, but lies on the upper surface of the eyeball and is partially covered by the m. levator palpebrae superioris, with which it is connected by tendinous bands. Origin: sphenoid bone, dorsally from the fissura orbitalis superior and from the foramen opticum. Insertion: eyeball in front of the equator—zone of attachment (anterior thickening of the sclera), its upper part. N. oculomotorius. Reisseisen's (M. of the smallest bronchi). Microscopic smooth muscle fibers of the smallest bronchi. 1. Retractor glottidis. Fibers of the m. genio-glossi, which extend to the epiglottis. Retroclavicularis (Weber) (retroclavicular M.). Syn.: sterno-clavicularis posterior. [Rare.] Origin: sternum—facies dorsalis manubrii. Insertion: clavicle—facies dorsalis claviculae. Retroclavicularis proprius (Gruber) (proper retroclavicular M.). Syn.: tensor laminae profundae fasciae colli. A muscle encountered once. Origin: clavicle—dorsal surface near the sterno-clavicular joint. Insertion: near the articulatio acromio-clavicularis. Rhomboideus: major and minor (rhomboid M.: major and minor). Syn.: rhomboideus; major—inferior; minor—superior. The M. is a truly regular rhomboid, thin plate of muscle fibers having a more or less parallel direction from top to bottom and from inside to outside. The M. is covered almost throughout its entire extent by the m. trapezius, except for the lower-outer triangular part, which is covered only by skin with superficial fascia; with its upper edge, the M. is in contact with the m. serratus posterior superior and levator scapulae and lies on the m. longissimus, ilio-costalis, and mm. intercostales. Origin: major: I-IV (V) thoracic vertebrae—processus spinosus; minor: VI-VII cervical vertebrae—processus spinosus and lig. nuchae. Insertion: scapula—margo vertebralis scapulae. N. dorsalis scapulae. Civ and v. Rhomboideus capitis (Gegenbaur) (rhomboid M. of the head). Syn.: occipito-scapularis. [Variation.] Blood supply: A. ophthalmica—r. muscularis. Action: Rotates the eyeball outward. A. ophthalmica—r. muscularis. Action: Rotates the eyeball inward. A. ophthalmica—r. muscularis. Action: Rotates the eyeball upward and simultaneously causes the lifting of the upper eyelid due to the tendinous connection with the m. levator palpebrae superioris. R. descendens a. transversae colli from the a. subclavia and branches of the aa. intercostales. Action: Raises and brings the scapulae together. 1) The M. caudally can become very thin or disintegrate into parallel bundles; 2) the initial tendon can also be quite thin in the caudal part and pass without a boundary into the aponeurosis of the m. latissimi; 3) the m. rhomboideus minor at the place of attachment can overlap the m. rhomboideus major; from the latter, superficial tendinous bundles can go into the fascia infra-spinata, into the teres major, and into the scapular part of the m. latissimi; 4) splitting of the M. into two layers has been observed; 5) the origin cranially can rise to the IV cervical vertebra or descend to the VII cervical vertebra, caudally reaching only to the III thoracic, rarely it can descend to the VI thoracic; in this case, the caudal part from the V thoracic vertebra can be an independent M.; 6) a very rare but interesting variation is the m. occipito-scapularis, s. rhomboideus capitis, which begins from the occipital bone on the dorsal continuation of the m. splenii capitis and attaches to the basis spinae scapulae or, beginning from the processus costo-transversalis atlantis, also attaches to the basis spinae scapulae; finally, it can begin from the fascia of the m. splenii capitis and attach to the scapula; the m. subcutaneus nuchae also belongs here, which begins from the lateral edge of the lineae nuchae superioris and disappears in the fascia covering the m. serratus posterior superior.
Risorius (M. of the smile). Syn.: novus (Santorini), zygomatico-risorius. Represents a triangular plate of thin muscle fibers, converging fan-like with its apex to the corner of the mouth; lies in the middle part of the cheek superficially under the skin, more superficially than the fibers of the m. platysmatis, if they extend so high onto the face. Origin: fascia parotideo-masseterica. Insertion: skin of the corner of the mouth. N. facialis—r. buccalis. Rotatores dorsi: breves and longi (rotators of the spine: short and long). Syn.: rotatores spinae, spino-transversales brevissimi. Small, metamerically arranged bundles in the thoracic region represent short rotators; long rotators represent fused adjacent metameres, passing through one vertebra and located along the entire spine. Origin: breves: thoracic vertebrae—processus transversus; longi: all vertebrae, except the atlas, processus transversus and sacrum—posterior surface. Insertion: breves: thoracic vertebrae (adjacent) arcus vertebrae, their outer surface; longi: vertebrae—processus spinosus (skipping one vertebra). Spinal nerves—their posterior branches. Sacro-coccygeus anterior (Meckel) (anterior sacro-coccygeal M.). Syn.: sacro-coccygeus inferior, curvator, s. extensor, s. levator coccygis, depressor, s. flexor caudae, tenuis. Individual muscle fibers on the anterior surface of the last sacral and first coccygeal vertebrae. Origin: sacrum—from the III foramen sacrale anterius to the coccyx. Insertion: lig. sacro-coccygeum anterius and to the II-IV coccygeal vertebrae—anterior surface. Spinal nerves from Siv and V and Coi. Sacro-coccygeus posterior (posterior sacro-coccygeal M.). Syn.: sacro-coccygeus posticus, curvator, s. levator coccygis. [Rare rudimentary M.] A small number of muscle fibers on the posterior surface of the last two sacral vertebrae. Remains of the mm. interspinales, am. b. and others between the os sacrum and os coccygis, which begin from the last sacral vertebrae or even from the spina iliaca posterior inferior or lig. sacro-tuberosum and attach to the coccyx. Plexus sacralis. Salpingo-pharyngeus. Syn.: retrahens tubae. Fibers of the m. constrictoris pharyngis superioris, which go to the tuba auditiva. Sartorius (tailor's M.). Syn.: sutorius, fascialis, longus. One of the longest M. of the entire body, it represents a thin, varying in width (up to 10 cm) ribbon, beginning and ending with tendons; the M. lies just under the skin and fascia lata femoris in a double aponeurotic plate (vagina m. sartorii), in the form of a spiral ribbon, enveloping the anterior and medial surface of the thigh from the ilium to the lower leg; the M. crosses: mm. rectus femoris, ilio-psoas, pectineus, adductor longus, and vastus medialis. Origin: ilium—spina iliaca anterior superior and adjacent parts of the incisura iliaca. Insertion: tibia—tuberositas tibiae, crista anterior, and fascia cruris. N. femoralis. Lii and III. Scalenus anterior (anterior scalene M.). Syn.: scalenus anticus, s. prius, s. prior, s. triangularis. Three or four separate bundles, which merge into a flat-spindle-shaped belly between the lower cervical vertebrae and the first rib on the lateral surface of the neck, medial to the other scalene M., from which it is separated by a gap—spatium interscalenium; it is crossed in front by the m. sterno-cleido-mastoideus and the m. omo-hyoideus, and only a small part of the M. below is covered by skin, fascia superficialis with platysma, and adipose tissue. Origin: IV-VI cervical vertebrae—tuberculum anterius and sulcus spinalis of the VI vertebra. Insertion: first rib—tuberculum scaleni (Lisfranci). Spinal nerves from V to VII—anterior branches. Civ-VII. Scalenus lateralis (Albinus) (lateral scalene M.). [Variation.] See m. scalenus medius.
Blood supply, Action, Variations. Pulls the corner of the mouth outward. 1) Sometimes absent on one or both sides; 2) varies generally from weak bundles to significant size; 3) may sometimes split into 2-3 portions; 4) may connect with m. zygomaticus—this is m. zygomatico-risorius; 5) may originate: from arcus zygomaticus, from tragus auriculae, from fascia colli covering m. sterno-cleido-mastoideus; 6) sometimes fibers of m. platysma reach the corner of the mouth, taking the place of m. risorius—this is m. platysma-risorius. Rotate the spine. Very often absent or replaced by a bundle of tendinous fibers. 1) Quite often complete absence of the muscle; 2) often replaced by tendinous fibers between the sacrum and coccyx; 3) sometimes may originate from spina iliaca posterior inferior. R. muscularis from a. femoralis and a. circumflexa femoris lateralis. Flexes the thigh at the hip joint and the lower leg at the knee, and rotates the flexed knee outward. 1) Meckel noted the absence of the muscle; the volume of the muscle often varies greatly; 2) the muscle may double, with Le Double noting three possibilities: a) doubling by splitting along the entire length into two similar bundles; b) doubling due to a second additional muscle located above or below the normal muscle; c) doubling, but both muscles are fused to some extent; 3) may give a bundle to fascia cruris—m. tensor fasciae cruris; 4) may attach to lig. patellae; 5) in the middle of the length, the muscle may have an inscriptio tendinea; 6) may receive an additional bundle: a) from the pelvis—m. sartorius biceps (Gruber); b) from parts adjacent to the knee joint—m. sartorius bicaudatus (Gruber); 7) the muscle may end at only one of its three usual points of attachment. A. cervicalis ascendens, a. vertebralis, a. thyreoidea inferior and a. cervicalis profunda from a. subclavia. Raises the first rib and consequently the chest; flexes the neck to its side, and upon contraction of both sides—forward. 1) Complete absence was observed; 2) may attach dorsally to a. subclavia or be pierced by it or by n. phrenicus; 3) may split at its attachment; 4) in one case of a cervical rib, the muscle attached on the right with three bundles (a. subclavia passed through the ventral slit, and a nerve through the dorsal), on the left—with two bundles; 5) may originate from the III and II cervical vertebrae and from the VII; 6) occasionally additional small bundles were observed: a) to clavicula; b) to m. scalenus posterior. No. 362. Latin and Russian name. Synonyms. Form and position. Origin and attachment. Innervation and relation to segments. Scalenus medius (middle scalene muscle). Syn.: scalenus minor, s. secundus, s. pleurae, pleuro-transversarius, suspensor pleurae, transversalis pleurae. The largest of all scalene muscles; it represents 6-7 muscle bundles, merging into a muscle belly of a flat-spindle shape; the muscle lies between all cervical vertebrae and the first rib, on the lateral surface of the neck between m. scalenus anterior, partly m. scalenus posterior and levator scapulae, covered partly in its medial-upper third by m. sterno-cleido-mastoideus, in the lateral-lower corner by m. trapezius, crossed by m. omo-hyoideus, and in the remaining space it lies adjacent to the skin, fascia superficialis colli and platysma. Origin: all cervical vertebrae—tuberculum anterius and lateral edges of sulcus n. spinalis. Attachment: first rib—behind sulcus subclavius and second rib. Spinal nerves II-VIII, their anterior branches. CII-CVIII. Scalenus minimus (smallest scalene muscle). Syn.: pleuro-transversarius, pleuralis. A small spindle-shaped bundle, not always present, the most medial and deep of all scalene muscles between the last cervical vertebra and the dome of the pleura and the first rib. Origin: VII cervical vertebra, its processus costo-transversalis. Attachment: I rib—inner edge and dome of the pleura. Eighth cervical nerve. CVIII. Scalenus posterior (posterior scalene muscle). Syn.: scalenus posticus, s. tertius. Two or three tendinous-muscular bundles, which merge into a muscle belly of a more or less flat shape, located between the lower cervical vertebrae and the second rib on the lateral surface of the neck, lateral and dorsal to m. scalenus medius, partly covered by it, posteriorly it is covered by m. levator scapulae and m. trapezius. Origin: (IV), V and VI cervical vertebrae—tuberculum posterius. Attachment: II (and III) ribs—their lateral surface. Spinal nerves—their anterior branches. C(VII)-CVIII. Scansorius. Syn.: glutaeus quartus, invector femoris. [Variation.] See m. glutaeus minimus, the anterior, separated bundle of which constitutes this muscle. Scapulo-clavicularis (Wood) (scapulo-clavicular muscle). Syn.: coraco-clavicularis, omo-clavicularis. [Rare variation.] Origin: scapula—processus coracoideus scapulae, its root, or lig. transversum scapulae superius, or margo superior—its middle third, or angulus superior scapulae. Attachment: clavicle—facies dorsalis, its lateral edge and fascia of m. subclavius. Scapulo-costalis (Gruber) (scapulo-costal muscle). [Variation.] See m. subclavius. Scapulo-costo-clavicularis (Gruber) (scapulo-costo-clavicular muscle). [Variation.] See m. subclavius posticus. Semimembranosus (semimembranosus muscle). Syn.: flexor cruris tibialis. A peculiar muscle, as it begins tendinously, ends also tendinously (pes anserinus profundus) and only its 2nd and 3rd quarters represent a muscle belly in the form of a rhomboid mass of transverse parallel muscle fibers; the muscle is located on the posterior surface of the thigh; on the medial side it lies adjacent to m. gracilis and adductor magnus (partly covered by it above), and on the lateral side to m. semitendinosus (partly covered by it); in the remaining space it is covered only by the sheath and fascia superficialis, except for the origin, which is also hidden by m. glutaeus maximus. Origin: ischium—tuber ischiadicum, laterally and proximally from m. semitendinosus, between m. biceps and quadratus femoris. Attachment: tibia—condylus medialis tibiae, knee joint capsule, its posterior wall (lig. popliteum obliquum) and fascia of m. poplitei. N. tibialis. LIV, V and SI. Blood supply. Action. Variations. [For Scalenus posterior:] A. cervicalis ascendens profunda, a. vertebralis and a. thyreoidea inferior from a. subclavia. Raises the first and second ribs, and with them the entire chest; flexes the neck to its side, and upon contraction of both, bends the neck and head forward. 1) Complete absence was observed only 1 time; 2) a decrease in the number of bundles to five is very common; 3) the muscle sometimes attaches to the III and even IV rib; 4) converging bundles with m. scalenus anterior are observed; 5) there is a connecting bundle with m. levator scapulae; 6) very often or even constantly the muscle has ventral and dorsal teeth, between them there may be a middle bundle—this is m. intertransversarius lateralis longus, s. transversalis cervicis medius (Tornblom)—it varies very strongly: it may start from the VI transverse process and go together with m. serratus to the atlas or start from the VII-IV transverse processes and I-II (II and III) transverse processes and is always closely connected with m. scalenus; the dorsal portion can also be called scalenus lateralis—it starts from the IV-VI vertebrae and attaches to the I or II ribs. [For Scalenus minimus:] Branches of a. cervicalis profundae and a. vertebralis from a. subclavia. Holds the dome of the pleura. 1) Attachment to the rib may be absent; 2) the muscle may be double; 3) may start from the transverse processes of the VI and VII vertebrae and from the neck of the first rib; 4) the muscle is generally constant, but may sometimes be replaced by a tendon. [For Scalenus medius:] Aa. cervicalis ascendens and profunda, a. vertebralis and a. thyreoidea inferior from a. subclavia. Raises the ribs, and with them the entire chest; tilts the neck and head to its side, and upon contraction of both, tilts the neck and head forward. 1) Absent quite often; 2) may start from the IV and V vertebrae; 3) the origin may rise to the IV vertebra; 4) attachment may be only on the III or only on the IV rib; 5) may split into 2 or even 3 bundles, more or less independent for two or three ribs; 6) may be a connecting bundle to m. scalenus medius. Besides the variations indicated above in the sense of the origin of the muscle, its attachment to m. subclavius is also possible; in this case, it is also possible that the appearance of this muscle coincides with the absence of m. subclavii. It is possible that m. coraco-cervicalis (Krause) is only a variant of this muscle. [For Semimembranosus:] Rr. perforantes from a. profunda femoris and a. circumflexa femoris medialis from a. femoris. Flexes the leg at the knee joint, rotates the lower leg outward and strengthens the leg at the hip joint.
(during standing) ralis, as well as branches of the a. popliteae 1) Occasionally it may be absent entirely; 2) a bundle may depart from the muscle into the fascia of the thigh—this is the m. tensor fasciae cruralis; 3) the muscle may double along its entire length; 4) the relationships between the muscular and tendinous parts may be different; 5) there may be additional bundles: a) from the lig. sacro-tuberosum, b) from the spina ischiadica. No. Name (Latin and Russian). Synonyms. Form and Position. Origin and Insertion. Innervation and relation to segments. 370 Semispinales: lumborum (variation), thoracis, s. dorsi, cervicis, capitis [Semispinal muscle: of the loins (variation), of the back, of the neck, and of the head]. Synonyms: semispinalis cervicis = spinalis colli, s. cervicis; semispinalis capitis = complexus, trigeminus, biventer cervicis + complexus major, transverso-occipitalis. See m. complexus major (of French authors). The muscle represents a tendinous-muscular mass consisting of a whole series of separate bundles, starting from the transverse processes and attaching, after passing more than four vertebrae, to the spinous processes of the vertebrae located above; this entire mass is located in the groove between the transverse and spinous processes, starting from the level of the XI thoracic vertebra to the occipital bone; it covers the more deeply located mm. multifidi brevis and longus, mm. rotatores breves and longi, and mm. interspinales; in turn, this mass is covered by the long muscles of the back: m. longissimus and m. spinalis. Origin: pars thoracis: (XII) XI-VII (VI) thoracic vertebrae-processus transversus; pars cervicis: (VII) VI-III (II) thoracic vertebrae-processus transversus; pars capitis: VI-I thoracic-processus transversus and VII-IV cervical vertebrae-processus articularis. Insertion: pars thoracis: IV-I thoracic and VII-VI cervical vertebrae-their processus spinosus; pars cervicis: VI-II cervical vertebrae-processus spinosus; pars capitis: occipital bone-between the linea nuchae superior and inferior. Innervation: Spinal nerves of the corresponding segments—their posterior branches. Ci to Dvi. Blood Supply: Branches from the aa. lumbales, intercostales, and a. cervicalis profunda, ascendens, and vertebralis from the a. subclavia and a. occipitalis from the a. carotis externa. Action: Rotates the spine during unilateral contraction and straightens it during bilateral. Variations: 1) Additional bundles may be in the lumbar region—from the II-V lumbar (processus mammillaris) and I sacral vertebra to the VI-XII thoracic and I lumbar vertebrae-processus spinosus—this is the m. semispinalis lumborum—a rare muscle; 2) semispinalis thoracis may have a different number of starting points (from 4 to 7) and attachment points (from 2 to 8); 3) semispinalis cervicis may also have a different number of starting places (4-7) and may attach cranially up to VII; 4) semispinalis capitis may start only from the IV cervical and reach the atlas; often there are little bundles from the processus spinosus of the V-I thoracic vertebrae (perhaps a hint of the m. spinalis); connective bundles with the m. longissimus dorsi and spinalis dorsi are encountered; 5) cases of doubling of the muscle have been observed, with the deeper muscle going from the I, from the I and II, from the III, from the III-I thoracic vertebrae (pr. spinosus) to the occipital bone independently of the superficial layer; 6) a muscular bundle in the nuchal ligament has been observed; 7) sometimes encountered: a) a little bundle from the II thoracic vertebra, processus transversus to the scale of the occipital bone—this is the m. complexus profundus; b) a little bundle from the transverse process of the epistropheus to the scale of the occipital bone; c) a little bundle on the upper surface of the muscle, having a lateral direction; d) a muscular plate from the linea nuchae sup. into the m. semispinalis capitis. 371 Semitendinosus (semitendinous muscle). Synonyms: seminervosus. The muscle consists of a flat-conical muscular belly with an inscriptio tendinea in its middle part and a very long spindle-shaped tendon; the muscle is located on the posterior surface of the thigh lateral to the m. semimembranosus, in the depression of which it partly lies, and medial to the long head of the m. bicipitis femoris; under it is also located the m. adductor minimus at the top and the adductor magnus in the middle and lower parts; in the upper parts the muscle is covered by the m. glutaeus maximus, and in all the rest of the space—only by skin and fascia superficialis. The terminal tendon of the muscle is in contact with the origin of the medial head of the m. gastrocnemii. Origin: ischium-tuber ischiadicum, its medial surface, together with the caput longum bicipitis femoris. Insertion: tibia-facies medialis tibiae to the crista and fascia cruris. Innervation: N. tibialis. LIV, V and SI (II). Blood Supply: Rr. perforantes from the a. profunda femoris. Action: Flexes the leg at the knee joint, rotates the lower leg outward, flexes at the hip joint, and strengthens during standing. Variations: 1) May start on the tuber ischiadicum separately from the long head of the bicipitis femoris; 2) may also start: from a) os coccygis; b) os ischii; c) linea aspera femoris; d) lig. sacro-tuberosum; 3) the inscriptio tendinea can vary very strongly in its dimensions, shape, and can be double; 4) may have close relationships with neighboring muscles: a) m. semimembranosus; b) m. biceps femoris—with the short head; c) with its long head; 5) there may be additional bundles: a) from the m. coccygeus; b) from the lig. sacro-tuberosum; c) from the linea aspera femoris. 372 Serratus anterior: pars superior, pars intermedia and pars inferior (anterior serrated muscle). Synonyms: serratus anticus, s. major, s. magnus. One of the widest muscles of the body, it represents a mass of fan-shaped diverging muscular bundles, located on the lateral surface of the thoracic cage, partly between it and the costal surface of the scapula; in this mass, upper, middle, and lower parts are distinguished, separated from each other by loose cellular tissue. The muscle in the lower half is covered from behind by the m. latissimus dorsi, and from the front in its lower part only by skin and superficial fascia; in the upper half from behind it is adjacent to the mm. subscapularis, teres major and minor—it constitutes the medial wall of the cavum axillaris, and from the front it is covered by the mm. pectoralis major and minor. With its anterior edge in the lower part, it enters the teeth of the m. obliquus abdominis externus. Origin: pars superior: I and II ribs and the tendinous arch between them; pars intermedia: II, III and IV ribs, their lateral surface; pars inferior: V-IX ribs, their lateral surface. Insertion: pars superior: scapula-angulus medialis; pars intermedia: margo vertebralis; pars inferior: angulus inferior scapulae. Innervation: N. thoracalis longus. CV-VII (VIII). Blood Supply: A. thoracalis lateralis, a. thoracalis dorsalis from the a. subscapularis, a. thoracalis suprema from the a. axillaris, branches from the aa. intercostales and p. descendens from the a. transversa colli. Action: Fixes the scapula on the chest, acting with its other muscles; pulls the scapula forward and to the side; pars inferior rotates the scapula, pulling the lower angle forward and to the side. Variations: 1) The number of starting points changes: it may reach only to the VII rib or start from the II rib only with one bundle, more often the upper bundles are absent, very rarely the middle ones; 2) often there is a division into three independent muscles or the isolation of the cranial portion or, even more often, the caudal one; 3) not infrequently a deep layer of the muscle is encountered, departing most often from the second rib, less often from the first or both together, and attaching to the margo vertebralis, sometimes along the extent from the basis spinae to the angulus inferior; 4) occasionally the muscle is reduced to the presence of only the upper bundles, which happens simultaneously with other anomalies; 5) often additional portions are added to the caudal edge, starting from the VIII, IX and X ribs and innervated by the intercostal nerves; 6) cases of connection with the m. levator scapulae, continuation into the mm. intercostales externi, obliquus abd. ext. are very rare. 373 Serratus posterior inferior (lower posterior serrated muscle). Synonyms: serratus posticus inferior, spino-costalis longus, dentatus posticus inferior. A rather large, but thin quadrilateral (rhomboid) plate, consisting of partly tendinous, partly muscular flat ribbon-like bundles, directed obliquely from below and behind upward and forward; it lies on the lower part of the back and the upper part of the loins between the lumbar vertebrae and the lower ribs, covering the mm. intercostales, longissimus and ilio-costalis and in turn covered by the m. latissimus dorsi. Origin: fascia lumbo-dorsalis at the height of the upper lumbar and lower thoracic vertebrae. Insertion: XII-IX (X) ribs. Innervation: Lower intercostal nerves—their ventral branches. DIX-XII.
Branches of the intercostal arteries. It pulls the ribs downward, and when acting simultaneously with the m. serratus posterior superior, it stretches the thoracic cage like an accordion (Braus), i.e., it is an inspiratory muscle. 1) Complete absence of the entire muscle is extremely rare; in such cases, it is replaced by tendinous fibers; 2) partial absence of individual bundles occurs, with the bundles of the X and XI ribs being the most constant, but even they can be very weakly developed; 3) an increase in the number of serrations up to 5 is possible, especially in the presence of a XIII rib; 4) other irregularities are also encountered, observed more often than in the m. serratus posterior superior: a) cranially there may be an additional muscle plate to the IX and X ribs (parallel to them); b) only one, but well-developed bundle on the IX rib; c) it divides into separate parts; d) it may be connected by muscle or tendon to the m. obliquus externus abdominis or intercostalis externus. Great Medical Encyclopedia, Vol. XIX. Name (Latin and Russian). Synonyms. Shape and position. Origin and insertion. Innervation and relation to segments. Serratus posterior superior (upper posterior serrated muscle). Syn.: serratus posticus superior, spino-costalis longus, dentatus posterior superior. A small and very thin rhomboid plate, consisting of narrow but long semi-tendinous, semi-muscular ribbons, having an oblique direction from behind and above downward and forward; it lies on the upper part of the back, covering the mm. semispinalis capitis, splenius, longissimus, ilio-costalis and intercostales and in turn covered by the mm. rhomboideus and trapezius. Origin: VI and VII cervical and I and II thoracic vertebrae - processus spinosus and lig. nuchae. Insertion: II-IV (V) ribs. Intercostal nerves - their ventral branches DI-IV. Singularis in collo (Albinus). [Variation.] See mm. intertransversarii ventrales. Singularis splenii accessorius (Walter). [Variation.] See m. levator scapulae. Soleus; caput peronaeale and caput tibiale [heel (soleus) muscle]. Syn.: solaeus, gastrocnemius internus. Starting with two tendinous plates, the muscle has a large, thick, but flat, flounder-like muscle belly, which is covered from the dorsal side by a wide aponeurotic plate, merging with the main tendon of the m. tricipitis surae; the muscle consists of two layers: dorsal and ventral, separated from each other by an aponeurosis; the muscle is covered from the dorsal side by the m. gastrocnemius, and from the ventral side it lies adjacent, starting from the medial side: to the mm. flexor hallucis longus, flexor digitorum longus, tibialis posticus and peronaeus longus; at the place of its origin it touches the m. popliteus and m. plantaris. Origin: caput peronaeale: fibula - capitulum and facies lateralis and posterior fibulae; caput tibiale: tibia - facies posterior tibiae, its two middle thirds, and arcus solei. Insertion: calcaneus - tuber calcanei (tendo calcaneus Achillis). N. tibialis. L(IV) V and SI(II). Sphincter ani externus (external sphincter of the anus). Syn.: Sphincter ani cutaneus, s. superficialis, constrictor ani, orbicularis ani. Origin: coccyx - apex coccygis, lig. ano-coccygeum and skin. Insertion: raphe bulbi cavernosi, partly in the skin of the perineum and centrum perinaeale. N. pudendus - nn. haemorrhoidales inferiores. Sphincter ani internus (internal sphincter of the anus). A more thickened part of the smooth circular muscle fibers of the lower part of the rectum. Sphincter ani tertius (third sphincter of the anus). Syn.: sphincter superior, s. O'Beirne. Thickening of the smooth circular muscle fibers in the region of the plicae transversalis recti. Sphincter colli [Variation.] See m. platysma. Sphincter orificii uteri interni et externi (sphincter of the cervix of the uterus). Syn.: sphincter uteri. Inner layer of the tunica muscularis cervicis uteri. Sphincter praeputii penis (Sappey). Fascia penis. Sphincter pupillae (muscle constricting the pupil). Syn.: m. iridis major. Circular smooth fibers in the iris - stroma iridis, near its pupillary margin. Plexus ciliaris. Sphincter pylori (muscle of the pyloric orifice of the stomach). Circular smooth muscle fibers of the tunica muscularis pylori, which form the valvula pylori. Blood supply. Action. Variations. Branches from the aa. intercostales. Raises the upper ribs, and with simultaneous action of the m. serratus posterior inferior pulls the ribs in opposite directions, i.e., serves for inspiration. 1) Absent extremely rarely and then it is replaced by an aponeurosis; 2) the origin of the insertion can reach the IV thoracic and descend to the VII cervical and I thoracic vertebrae; 3) the number of serrations can fall to two (II and III ribs) and increase to six (ending at the seventh rib); 4) some bundles can pass into the m. latissimus dorsi; 5) very rarely several small muscle bundles were observed. A. tibialis posterior and a. peronaea. Flexes the foot in the plantar direction. 1) Once its complete absence was observed; 2) the muscle belly can rarely double; 3) an additional belly of the m. plantaris can depart from the muscle; 4) once the entire m. plantaris started from the inner surface of the m. solei; 5) there may be a muscle-tendon bundle reaching the os calcaneum independently. Constricts the pupil. Sphincter urethrae membranaceae (sphincter of the urethra). Syn.: sphincter prostaticus, s. externus, constrictor isthmi urethralis, s. urethrae, s. urethrae membranaceae, orbicularis urethrae membranaceae, ischio-urethralis, ischio-rectalis, pubio-prostaticus, transverso-urethralis, stratum circulare, s. internum, s. musculare horizontale transversum, s. musculare superius isthmi urethrae, m. Wilsoni. Arched transverse fibers of the m. transversi perinei profundi, which surround the membranous part of the urethra. N. pudendus. Sphincter vesicae (sphincter of the urinary bladder). Stratum medium tunicae muscularis of the urinary bladder of men and stratum musculare circulare urethrae of women. Spinales: thoracis, s. dorsi, cervicis (capitis, lumborum - variation) (spinal muscles). Syn.: spinales cervicis - spinales colli, superspinales colli, interspinales supernumerarii, interspinales cervicis longi, spinatus, semispinosus. Represents a spindle-shaped long mass, consisting of semi-muscular, semi-tendinous bundles, located on the lateral surfaces of the spinous processes in two places of the vertebral column: below in the lumbar-thoracic region and above in the cervical-thoracic region. Origin: pars thoracis: III-I lumbar and XII-X thoracic vertebrae - processus spinosus; pars cervicis: II-I thoracic and VII-VI cervical vertebrae - processus spinosus. Insertion: pars thoracis: VIII-II thoracic vertebrae - processus spinosus; pars cervicis: IV-II cervical vertebrae - processus spinosus. Spinal nerves of the corresponding segments. Splenius: capitis and cervicis (triangular, or bandage muscle). Syn.: triangularis, spino-transversalis. The muscle represents a large muscle mass of irregular shape, located on the lateral parts of the neck, between the lower cervical and upper thoracic vertebrae on one side and the occipital bone on the other in an oblique direction. The muscle is covered above by the m. sternocleidomastoideus, and below by the mm. trapezius, rhomboideus and serratus posterior superior, and only its part between these muscles lies immediately under the skin and fascia superficialis; in turn, it covers the mm. semispinalis capitis, longissimus, as well as the mm. obliquus capitis superior and inferior and m. rectus capitis posticus major. Origin: pars capitis: III-I thoracic vertebrae and VII cervical - processus spinosus and lig. nuchae; pars cervicis: (VI) V-III thoracic vertebrae - processus spinosus. Insertion: pars capitis: occipital bone - linea nuchae superior and temporal bone - processus mastoideus; pars cervicis: upper cervical vertebrae - tuberculum posterius, processus costo-transversarius. Spinal nerves - their posterior branches. Splenius accessorius (Krause) (accessory bandage muscle). Syn.: rhombo-atloideus, adjutor splenii, singularis splenii accessorius. [Variation.] See m. levator scapulae. Stapedius (muscle of the stapes). Syn.: pyramido-stapedis. Origin: eminentia pyramidalis. Insertion: stapes - capitulum stapedis. N. facialis. Sternalis (sternal muscle). Syn.: sternalis brutorum, thoracicus, accessorius ad rectum, anomalus sterni, episternalis, praesternalis, sterno-costalis, rectus abdominis superficialis, s. thoracis, triangularis anterior, pectoralis rectus. The shape of this rare muscle can be very diverse, the muscle lies on the anterior surface of the chest. Origin: fascia in the region of the xiphoid process of the sternum.
Insertion: superficial fascia in the region of the pectoralis major muscle. Anterior thoracic nerve or anterior branches of the III-VI intercostal nerves or from both sources. Blood supply. Action. Variations. Branches of the internal pudendal artery from the hypogastric artery. Extend the spine. 1) Complete absence of the muscle is very rare; 2) the thoracic part may contract to the three middle or reach even to the VII cervical vertebra; 3) cervical part—symmetry between antimeres is very rare; antimeres may fuse into an unpaired muscle or divide only cranially; a case of attachment of the upper bundle to the superior nuchal line was observed; 4) spinalis capitis—muscle bundles, rare and varying in shape and place of origin and insertion, starting from the upper thoracic (up to IV) and lower cervical and attaching together with the semispinalis capitis muscle or rectus capitis posterior major or minor muscle to the nuchal line, or even to the external occipital protuberance; 5) spinalis lumborum as a rare variation—small muscle bundles from the IV and V or III and IV lumbar vertebrae together with the semispinalis muscle or multifidus muscle to the IX and X thoracic vertebrae—spinous process. Occipital artery from the external carotid artery and superficial and deep cervical, transverse cervical, vertebral from the subclavian artery. Turns the head to its side, with bilateral contraction tilts the head backward. 1) Complete absence is extremely rare; 2) quite often fusion of both portions by means of an intermediate bundle, reaching with its tendon to the mastoid process and pharyngeal tubercle or ending earlier in the fascia of the rectus capitis lateralis or obliquus capitis superior muscles; 3) less often, a more sharp separation of both portions; 4) sometimes a division of the capitis part into two portions is observed, with one attaching to the mastoid process and the other to the superior nuchal line; 5) the serratus posterior superior muscle may wedge between both portions with the help of its tendon; 6) the origin of the muscle may also vary, decreasing cranially for the capitis part to the atlas, for the cervical part caudally to the VI thoracic vertebra; 7) the attachment of the capitis part may be limited to the mastoid process, the cervical part—to the IV cervical vertebra; 8) occasionally, connecting bundles to the levator scapulae and longissimus capitis muscles are observed. This atypical muscle is found in very diverse forms. In the simplest case, the muscle starts tendinously or muscularly from the III rib, from the sternal end of one or many cartilaginous ribs (up to seven), from the edge of the sternum or xiphoid process or from the sheath of the rectus abdominis muscle. With stronger development, the muscle touches the fascia of the pectoralis major, obliquus externus abdominis muscles, the tendon or the sternocleidomastoid muscle itself. The shape of the muscle is also very diverse: from spindle-shaped to wide triangular or elliptical. The direction can also be different: from longitudinal, cranio-lateral and caudo-lateral. The attachment can be different: tendinously to the sternal membrane, body, angle or manubrium; or, if the muscle continues further cranially into the sternocleidomastoid muscle, the fascia of the pectoralis major muscle with one or several bundles. Antimeres can be symmetrical and asymmetrical, fuse with each other, cross to the opposite side, intersect in the form of the letter X, form a star; the muscle reaches especially great development with underdevelopment of the sternal part of the pectoralis major muscle. With very large development, the muscle is noticeable in the living under the skin. The frequency of the muscle on average in Europeans is 4.4%, in Negroes 5.5%, in Japanese, according to Adashi, 14.3%, according to Koganei 6.7%, in anencephalics 48%. 1) The origin of the muscle can reach on the sternum to the second cartilaginous rib; 2) the attachment of the muscle can be: on the clavicle at the trapezoid part of the coracoclavicular ligament, on the coracoacromial ligament; 3) with bilateral development, tendinous fibers can pass to the opposite side and thus an unpaired muscle is obtained—the anterior digastric interclavicular muscle. 1) The muscle can be on one or both sides; 2) antimeres can connect with each other—this is the interclavicular (superior) muscle (Hyrtl), which lies ventrally from the interclavicular ligament; 3) once (Vestarini-Cresi) this muscle was attached to the medial edge of the cleidomastoid muscle; 4) related to this muscle are: a) sternofascial or sternocervical muscle—from the manubrium of the sternum (dorsally from the sternomastoid muscle) into the fascia of the omohyoid triangle; b) singular supraclavicular muscle—from the manubrium of the sternum and clavicle, its dorsal surface—to the tendon of the deep isolated bundle of the cleidomastoid muscle; c) cleidohyoid muscle—from the cranial surface of the clavicle to the body of the hyoid bone. Sternocleidomastoid artery from the external carotid artery, and also branches from it of the occipital, posterior auricular, superior thyroid arteries and from the subclavian artery—superficial cervical artery and transverse cervical artery. Turns the head to the opposite side and upward, and to its own side downward; with contraction of both antimeres, the head and neck are flexed; if they are extended by the contraction of the back muscles, then the chin is raised upward and the head is thrown back.
With a fixed head, it raises the thoracic cage and the shoulder girdle. 1) Complete separation of both portions is quite frequent (the accessory nerve passes between them); 2) their complete fusion, on the contrary, is quite rare; 3) the absence of the entire muscle is very rare (coincides with the absence of the clavicle); the absence of the sternal head is also rare; 4) occasionally, an increase in the number of portions to 3 or 4 is observed; these are: mm. sterno-occipitalis, sterno-mastoideus, cleido-occipitalis, and cleido-mastoideus; 5) there may be bundles between it and the m. trapezius; 6) sometimes there may be an independent m. cleido-occipitalis from the dorsal surface of the clavicle to the superior nuchal line; 7) the clavicular head may sometimes attach to the transverse process of the epistropheus (axis); 8) tendinous inscriptions are described on the sternal head; 9) an aberrant bundle from the ventral edge of the muscle may go: a) to the angle of the mandible; b) to the stylo-mandibular ligament; c) to the tympanic bone; d) from the dorsal edge into the fascia of the nuchal region; e) to the auricle; f) to the parotid gland (m. mastoido-parotidien Chudzinski); g) to the hyoid bone. No. Name in Latin and Russian. Synonyms. Form and position. Origin and attachment. Innervation and relation to segments. Sterno-humeralis (Huntington) (sterno-humeral muscle). Syn.: sterno-chondro-humeralis. [Variation.] See m. tensor semivaginae articulationis humero-scapularis. Sterno-hyoideus (sterno-hyoid muscle). Syn.: cleido-hyoideus, sterno-cleido-hyoideus, sterno-hyalis, depressor ossis hyoidei. It is a flat muscular ribbon, which is located along the anterior part of the neck, in the space between the sternum and the hyoid bone, covered at its origin by the m. sterno-cleido-mastoideus, and then only by the skin, superficial fascia, and partly by the m. platysma; in turn, it covers the m. sterno-thyreoideus and thyreo-hyoideus and lies with its lateral edge against the m. omo-hyoideus, in its upper part. Origin: sternum—manubrium sterni, its posterior surface, articular capsule of the sternoclavicular joint (clavicle). Attachment: hyoid bone—body of the hyoid bone. Innervation: I-III spinal nerves, their anterior branches via the ansa hypoglossi. Segment: C(i)-C(iv). Sterno-fascialis (Gruber) (sterno-fascial muscle). [Rare muscle.] See m. sterno-clavicularis superior. Sterno-mastoideus (sterno-mastoid muscle). [Variation.] See m. sterno-cleido-mastoideus. Sterno-occipitalis (sterno-occipital muscle). [Variation.] See m. sterno-cleido-mastoideus. Sterno-petroso-pharyngeus (Rennie) (sterno-petro-pharyngeal muscle). [Muscle encountered once.] Origin: sternum—manubrium sterni, its ventral surface. Attachment: by three teeth to the temporal bone—vaginal process of the temporal bone and to the m. cephalo-pharyngeus. Innervation: branches of the glossopharyngeal nerve. Sterno-scapularis (Anderson) (sterno-scapular muscle). [Atypical muscle.] See m. omo-hyoideus. Sterno-thyreoideus (sterno-thyroid muscle). Syn.: sterno-thyreoides, sterno-costo-thyreoideus, sterno-thyricus, bronchius. A thin muscular ribbon on the anterior part of the neck, in the space between the sternum and the first rib on one side and the thyroid cartilage on the other; it lies on the trachea and thyroid gland and is covered by the m. sterno-hyoideus and m. omo-hyoideus, in the upper parts only by the skin, superficial fascia, and m. platysma. Origin: sternum—manubrium sterni, its posterior surface and I, and sometimes II, costal cartilages. Attachment: thyroid cartilage—oblique line of the thyroid cartilage. Innervation: I-III spinal nerves, anterior branches via the ansa hypoglossi. Segment: C(i)-C(iv). Blood supply: superior thyroid artery, hyoid branch of the lingual artery from the external carotid artery. Action: lowers the hyoid bone. Variations: 1) Unilateral and bilateral absence of the muscle has been observed; 2) it may originate: from the middle of the manubrium, or from the medial third of the clavicle, or only from the sternoclavicular joint, or only from the clavicle and the first rib, or only from the middle of the dorsal surface of the clavicle; 3) the muscle may be double when divided into two portions: m. cleido-hyoideus and m. sterno-hyoideus or have two heads; 4) antimers may exchange fibers along the midline or fuse with each other; 5) there may be a bundle extending above the hyoid bone into the m. mylo-hyoideus or into the tendinous loop of the m. digastricus; 6) fusion of the m. sterno-thyreoideus or with the cranial belly of the m. omo-hyoideus or with the m. mylo-hyoideus by means of muscle fibers is possible; 7) besides the typical tendinous intersection, there may be a second one in the region of the oblique line of the thyroid cartilage; 8) a bundle in the cervical fascia—m. costo-fascialis. Blood supply: superior thyroid artery and hyoid branch of the lingual artery from the external carotid artery. Action: lowers the thyroid cartilage. Variations: 1) Its complete absence has been observed occasionally; 2) with pathological enlargement of the thyroid gland, the muscle becomes wider and thinner; 3) splitting into two layers throughout the muscle or partially is possible; 4) there is also division into two or three parallel bundles; 5) fusion with the m. sterno-hyoideus has been observed; 6) the origin may not involve the I rib or may extend to the II, the sternal end of the clavicle; an additional bundle may originate from the middle of the clavicle; 7) fusion of both antimers along the midline is possible; 8) the attachment may be limited to the superior thyroid tubercle, or expand significantly to the caudal edge of the thyroid cartilage, or to the base and superior horn and to the greater horns of the hyoid bone; this bundle may be independent—this is the m. costo-hyoideus; a similar dorsal bundle may be directed to the deep fascia of the neck in adjacent parts: to the horn of the hyoid bone—this is the m. costo-fascialis cervicalis, or to the submandibular fascia, or to the sheath of the cervical bundle, or into the mm. hyo-pharyngeus, or laryngo-pharyngeus, into the thyroid gland; 9) besides the tendinous inscription in the region of the interclavicular ligament, there may be a second intersection above it; 10) fusion of both antimers occurs only below, and along the length there may be bundles crossing from one side to the other; transverse bundles have even been observed—m. transversus colli (Luschka) from the dorsal surface of the first costal cartilage, diverging fan-like into the leaf of the cervical fascia, connected with the endothoracic fascia; sometimes their bundles may pass one into another; perhaps this is a remnant on the neck of the m. transversus thoracis; 11) once the m. thyreo-mediastinalis was observed—from the capsule of the thyroid gland into the anterior mediastinum—up to the anterior sterno-pericardial ligament. No. Name in Latin and Russian. Synonyms. Form and position. Origin and attachment. Innervation and relation to segments. Stylo-auricularis (Hyrtl) (stylo-auricular muscle). Syn.: depressor auriculae. [Rare muscle.] Origin: temporal bone—styloid or vaginal process. Attachment: auricle—agger of the auricle. Stylo-chondro-hyoideus (Douglas) (stylo-chondro-hyoid muscle). [Variation.] See m. stylo-hyoideus. Stylo-glossus (stylo-glossus muscle). A spindle-shaped bundle between the styloid process and the root of the tongue. Origin: temporal bone—styloid process and stylo-hyoid ligament. Attachment: tongue—lateral edges of its root. Innervation: hypoglossal nerve. Stylo-hyoideus (stylo-hyoid muscle). Syn.: stylo-hyalis, stylo-ceratoideus, stylo-hyoideus major, levator ossis hyoidei. A small spindle-shaped muscle bundle on the lateral upper part of the neck, between the styloid process and the hyoid bone, to which it often attaches with two bellies; the tendon of the m. digastricus mandibulae (posterior belly) passes between them. Near the styloid process, the muscle is in contact with the mm. stylo-glossus, stylo-pharyngeus, and hyo-glossus. Origin: temporal bone—styloid process. Attachment: hyoid bone with two bellies: one belly—body of the hyoid bone, and the other—greater horn. Innervation: facial nerve—digastric branch. Stylo-mandibularis (Fusari) (stylo-mandibular muscle). Syn.: stylo-maxillaris. [Variation.] See m. stylo-hyoideus. Stylo-pharyngeus (stylo-pharyngeus muscle). Syn.: stylo-pharyngo-laryngeus, dilatator pharyngis, levator pharyngis externus. A small muscle bundle on the upper part of the lateral surface of the neck in the depth at the level of the lateral wall of the pharynx between it and the styloid process. Origin: temporal bone—styloid process, its medial surface. Attachment: pharynx, its lateral surface, epiglottic and thyroid cartilages. Innervation: vagus nerve—pharyngeal branches. Stylo-tonsillaris (stylo-tonsillar muscle). Muscle bundles of the m. stylo-glossus, which go to the palatine tonsil. Subclavius (subclavius muscle). A small elongated spindle-shaped muscle between the clavicle and the first rib. Origin: I costal cartilage, its anterior surface. Attachment: clavicle—acromial extremity, its inferior surface. Innervation: subclavius nerve. C(v) IV and (V). Subclavius posticus (Rosenmüller) (posterior subclavius muscle). Syn.: subclavius accessorius, scapulo-costalis minor. [Variation (7% according to Macalister).] Origin: I costal cartilage laterally from the costo-clavicular ligament. Attachment: scapula, its cranial edge, between the root of the coracoid process and the coraco-clavicular ligament on one side and the superior angle on the other. Innervation: brachial plexus, subclavius nerve.
Cv i yi Blood supply Action Variations Raises the root of the tongue and retracts the tongue 1) The muscle may be absent; 2) it may double; 3) it may receive reinforcing bundles: a) from the stylo-mandibular ligament; b) from the inner surface of the angle of the mandible; c) from the stylo-hyoid muscle; d) from the stylo-pharyngeus muscle Branches of the occipital, posterior auricular, and hyoid branch of the lingual artery from the external carotid artery Raises the hyoid bone 1) Both or one belly may be absent; 2) both bellies may fuse or, conversely, be completely independent muscles; 3) there may be an additional head: from the mastoid notch, from the origin of the digastric muscle, from the stylo-mandibular ligament, from the angle of the mandible, from the posterior belly of the digastric muscle; a bundle from the angle of the mandible, reaching great independence—the hyo-angular muscle; 4) variations of attachment consist in the separation of a bundle, which may go to the lesser horns of the hyoid bone, into the perimysium of the hyo-glossus muscle, into the suprahyoid fascia, to the angle of the jaw; this bundle, running independently from the styloid process itself—the stylo-maxillary or stylo-mandibular muscle; 5) additional bundles from the styloid process may go: to the lesser horns of the hyoid bone—the new stylo-hyoid muscle (Santorini), or the alter (Douglas), or the parvus (Gavarde), or the profundus (Sappey), or the stylo-chondro-hyoid muscle (Douglas); these bundles may also attach in other places: the end of the greater horns of the hyoid bone, the triticeous cartilage, simultaneously the triticeous cartilage and the greater or lesser horns, the triticeous cartilage and the body of the hyoid bone in cases of division into two bundles; 6) a triple muscle was even observed: besides the normal one (with division) there was also a belly under the hyo-glossus muscle to the lesser horn of the hyoid bone and a third from the styloid process to the greater horn of the hyoid bone; 7) Walsham described small muscles: a) in the mobile bony connection between the base of the skull and the hyoid bone; b) in the vicinity of the cartilaginous auditory canal Ascending pharyngeal artery from the external carotid artery Raises the pharynx 1) There may be an accessory bundle from the mastoid process—this is the pharyngo-mastoideus muscle, if it is sufficiently independent; 2) several times the doubling of the muscle was observed—this is the stylo-pharyngeus alter (Bohmer) Branches of the transverse scapular artery from the subclavian artery and the thoraco-acromial artery from the axillary artery Fixes the clavicle 1) The size of the muscle is subject to great changes; 2) isolated complete absence is extremely rare, more often in the absence of the pectoralis minor muscle and other pectoral muscles; 3) cases of doubling, of accessory ventral and dorsal bundles to the main one were observed; 4) it may attach from the middle of the clavicle to one of the parts of the coraco-clavicular ligament or to the coracoid process of the scapula or to the transverse scapular ligament—the scapulo-costalis muscle 1) The scapulo-costo-clavicular muscle—such a variation of the muscle, when besides the costal origin there is also an origin from the dorso-caudal edge of the clavicle No. Name Latin and Russian. Synonyms. Form and position Origin and attachment Innervation and relation to segments Subcostales (subcostal muscles). Syn.: infra-costales, intracostales, depressores costarum proprii, serrati interni, transversi thoracis posteriores On the inner surface of the chest, starting from the angle of the rib, they pass in the form of teeth from the XII rib and from the body of the XII vertebra and, skipping one or two ribs, attach to the ribs located above; the uppermost ones start from the IV (or III) rib and attach to the II (or I) rib Intercostal nerves Subcutaneus nuchae (subcutaneous muscle of the nape) See rhomboideus muscle Submultifidus (Hyghes): thoracalis, cervicalis, lumbalis and sacralis (submultifidus muscle). Syn.: submultifidus thoracalis=rotatores muscles (BNA); submultifidus cervicalis=interarcual fasciculi (H. Virchow) Small muscle bundles located under the multifidus muscle from the transverse processes of one vertebra to the spinous process of the one lying above, and in the lumbar region between the mammillary process and the accessory process of the one lying above, see rotatores muscles Subscapularis (subscapular muscle). Syn.: infrascapularis, immersus, rotator humeri anticus, subscapulo-humeralis, subglenoidalis, subscapularis major. Represents a muscle mass located along the entire subscapular fossa and consisting of separate coarse bundles; some of them attach to aponeurotic plates extending from the muscular lines of the scapula, others from the surface of the bone itself; they all interweave and end in a tendon Orig.: scapula—costal surface of the scapula, muscular lines—deep fibers of the muscle and subscapular fascia—superficial fibers. Att.: humerus—lesser tubercle and crest of the lesser tubercle, articular capsule Subscapular nerve. Cv, VI (VII) Subscapularis minor (lesser subscapular muscle) See subscapularis muscle Subtarsalis (Moll). Syn.: Riolan's ciliary muscle Fibers of the palpebral part of the orbicularis oculi muscle, which are located under the free edge of the tarsus Subtrapezius (subtrapezius muscle) See trapezius muscle Suctionis See orbicularis oris muscle Supinator (supinator). Syn.: supinatorius, supinator brevis. Represents a rhomboid thin, but rather wide muscle plate, which lies on the proximal end of the forearm on its dorso-lateral side on the bones themselves and the interosseous ligament, covered by muscles starting from the lateral epicondyle of the humerus: brachio-radialis, extensor carpi radialis longus and brevis Orig.: humerus—lateral epicondyle of the humerus, lateral collateral ligament, annular ligament of the radius and ulna—crest of the supinator muscle of the ulna. Att.: radius from the tuberosity of the radius to the attachment of the pronator teres muscle Radial nerve—deep branch. C(v), Vi, vii (Vin) Supinator verus (Frohse and Frankel) (true supinator). [Variation.] See brachio-radialis muscle Supraclavicularis proprius (Gruber) (proper supraclavicular muscle). Syn.: tensor fasciae colli, anomalus claviculae [Rare variation.] Runs in an arc from the sternal to the acromial end of the clavicle C-III and IV via the descending branch of the hypoglossal nerve Supracostales posteriores (Eisler) (posterior supracostal muscles). Frequently encountered bundles of three groups: the first coincides with the direction of the external intercostal muscles, the second—with the serratus posterior superior muscle and the third—with the serratus anterior muscle First group: Orig.: cranial ribs. Att.: after passing two intercostal spaces to the ribs themselves. Branches of the intercostal nerves Blood supply Action Variations 1) Very different degrees of their development are observed from a series of them to thin individual plates; 2) their complete absence is, however, extremely rare; in such cases the internal intercostal muscles extend significantly further back to the spine; 3) sometimes the cranial bundles are extremely strongly developed; they start from the II-IV ribs and attach to the first rib near the scalenus anticus muscle Subscapular arteries from the axillary artery Rotates the arm inward and together with others adducts it, and lowers the raised arm 1) Quite often the division of the muscle into separate bundles; 2) an accessory bundle may depart to the fascia of the arm—the tensor fasciae et cutis foveae axillaris muscle, as a rudiment of the panniculus carnosus; 3) more often a special small bundle departs, attaching separately to the lesser tubercle—the subscapularis minor muscle (subscapulo-capsularis, subscapulo-humeralis, subscapularis secundus, infraspinatus secundus—depending on its attachment), usually found in many animals; 4) a case of attachment of the muscle by three heads was observed: a) to the shoulder capsule; b) to the apex of the coracoid process and c) to its base; 5) portion innervated by the axillary nerve, see deltoid muscle Interosseous recurrent artery and radial recurrent artery Rotates the forearm outward and extends the arm at the elbow joint 1) The muscle may rarely be reduced to the state of an aponeurotic plate with individual muscle fibers; 2) often the muscle consists of two portions: superficial and deep, between which there is a canal for the deep branch of the radial nerve (supinator canal); 3) the superficial portion varies in its dimensions quite significantly; 4) at the beginning of the muscle a sesamoid bone is sometimes observed; 5) sometimes there is a supernumerary head from the medial epicondyle of the humerus; 6) sometimes there is a transverse independent bundle—the dorsal and ventral tensor of the annular ligament of the radius muscle 1) Often the teeth of the first group are located so that the muscle belly is in one intercostal space, and the tendon in another; 2) the second group has more sharply defined bundles; they No. Name Latin and Russian. Synonyms. Form and position Origin and attachment Innervation and relation to segments V o n o n Second group: Orig.: III-VI ribs, their outer surface. Att.: superficial fascia or aponeurosis of the serratus posterior superior muscle. Third group: Orig.: VIII-X ribs, their outer surface. Att.: supracostal connective tissue medially and caudally from the inferior angle of the scapula Supracostalis anterior (Boehndalek) (anterior supracostal muscle). Syn.: rectus thoracis, s. sternalis. [Rare muscle.] Orig.: I rib—its outer edge.
Suprapleuralis (Eisler) (suprapleural muscle). [Rarely observed muscle.] Muscle fibers (10-15 mm wide), which lie starting from the 1st rib, between its neck and the attachment of the m. scalenus medius, above the dome of the pleura. Supraspinatus (supraspinatus muscle). A fairly voluminous prismatic muscle mass, filling the entire supraspinous fossa of the scapula with a short but strong terminal tendon. Origin: scapula-fossa supraspinata-deep fibers and fascia supraspinata-superficial fibers. Insertion: humerus-tuberculum majus, its upper facet. Nerve: n. suprascapularis. Suspensorius duodeni (Heitz). (Muscle supporting the duodenum). Syn.: phreno-peritonaealis (Rouget). See diaphragm. Syndesmo-pharyngeus (Kohlrausch). (Ligament-pharyngeal muscle). Origin of the fibers of the m. constrictor pharyngis medii from the lig. thyreo-hyoideum. Tarsalis: inferior and superior (lower and upper tarsal muscles). Syn.: palpebralis (Muller), m. Riolani (Macalister). Smooth muscle fibers along the edge of the eyelids. The upper bundles start between the bundles of the m. levator palpebrae superioris along its posterior surface and go to the tarsus superior; the lower bundles have the same direction directly under the conjunctiva. Temporalis (temporal muscle). Syn.: temporo-maxillaris, crotaphites. It is a flat, wide plate, which consists of fan-shaped muscle fibers converging toward the coronoid process of the mandible, to which it is attached by a strong tendon. The muscle is located in the upper two-thirds throughout the temporal fossa, as if in an osteo-aponeurotic bed formed on one side by the outer surface of the bones, and on the other (lateral) by the dense temporal fascia; muscle bundles also originate from this fascia; in the lower third, the muscle lies between the m. masseter on the lateral side and the m. pterygoideus externus and buccinator and the accumulation of cheek fat, on the medial side. Origin: temporal, sphenoid, frontal, zygomatic, and parietal bones-planum temporale, starting from the linea temporalis to the crista infratemporalis and fascia temporalis. Insertion: mandible-processus coronoideus mandibulae. Nerve: n. trigeminus-n. mandibularis, nn. temporales profundi. Temporalis minor (Henke) (small temporal muscle). See m. temporalis. Tensor fasciae brachialis (muscle stretching the fascia of the arm). [Variation.] See m. pectoralis major. Blood supply. Action. Variations: they can end differently, for example in the mm. scalenus medius and posticus; 3) the teeth of the third group can send their tendons into the fasciae of the deep back muscles and down to the spine itself or into the lower fascia of the m. serratus posterior superior or m. rhomboideus and to the angulus scapulae. 1) The origin may vary: be located at the m. subclavius, or near the m. scalenus anterior, or in the fascia colli, or shift caudally to the first bundle of the m. serratus anterior, or to the III rib; 2) the insertion may also change: to the III rib, or III and IV, or IV and V, or even to the VI rib; 3) its width and thickness may vary. A. transversa scapulae from the a. subclavia and a. circumflexa scapulae from the a. axillaris. Abducts the arm. 1) A very rare case of variations-additional bundles from the lig. transversum scapulae superius; 2) possible: a) fusion of the tendon with the tendon of the m. infraspinatus; b) with the tendon of the m. pectoralis minor; 3) possible strengthening of the muscle by a bundle: a) from the lig. coraco-acromiale; b) from the m. pectoralis major; 4) division of the muscle body into two bellies; 5) attachment to the tendinous plate located above the m. pectoralis major. A. temporalis media from the a. temporalis superficialis, aa. temporales profundae from the a. maxillaris interna. Raises the mandible and pulls it backward. 1) The size of the muscle varies mainly individually; racial and sexual differences are also expressed in this; 2) the anterior end of the attachment can reach the last molar tooth; 3) the case of doubling apparently refers to the appearance of a deep portion of the m. masseter; 4) a sharper separation of portions is observed-spheno-frontalis and sphenoidalis (deeper); 5) Henke observed the m. temporalis minor-a portion departing from the meniscus articularis and merging with the m. temporalis and m. masseter (possibly a portion of the latter muscle); 6) an strengthening of muscle fibers is observed, which originate from the spina infratemporalis and crista infratemporalis and are directed into the m. temporalis and m. pterygoideus externus.
Tensor fasciae cruralis (muscle stretching the crural fascia). Syn.: tensor fasciae cruris. [Variation.] See mm. semimembranosus, sartorius, gastrocnemius. Tensor fasciae dorsalis pedis (muscle stretching the dorsal fascia of the foot). [Variation.] See m. tibialis anterior. Tensor fasciae et cutis foveae axillaris (muscle stretching the fascia and skin of the axillary fossa). See m. subscapularis. Tensor fasciae latae (muscle stretching the broad fascia of the thigh). Syn.: glutaeus anterior, s. lateralis, aponeuroticus, ilio-aponeuroticus, ilio-tibialis, membranosus, fascialis, tensor vaginae femoris, femoralis. It is a mass of parallel muscle fibers of prismatic shape, located along the anterolateral surface of the pelvis. The muscle is located in an aponeurotic sheath formed by the broad fascia of the thigh. In front, the muscle touches the m. sartorius, lies on the mm. rectus femoris, vastus lateralis, and glutaeus medius and is covered from the outside only by the superficial fascia and skin. Origin: ilium-spina iliaca anterior superior and below it a common aponeurosis with the mm. glutaeus medius and minimus. Insertion: thigh-in front of the trochanter major femoris to the fascia lata, and through the tractus ilio-tibialis (Maissiati) to the tibia-condylus lateralis tibiae. Nerve: n. glutaeus superior, Liv, Lv, Si. Tensor fasciae plantaris (muscle stretching the plantar aponeurosis). [Very rare muscle.] A muscle bundle starting below the origin of the m. soleus and attaching either to the lig. laciniatum, or to the caput plantare, or to the aponeurosis plantaris. Tensor fasciae transversalis (muscle stretching the transverse fascia of the abdomen). [Variation.] See m. transversus abdominis. Tensor laminae posterioris vaginae m. recti abdominis et fasciae transversalis (Gruber) (muscle stretching the posterior lamina of the sheath of the rectus abdominis muscle and the transverse fascia). [Variation.] See m. transversus abdominis. Tensor lig. annularis radii dorsalis et volaris (Rauber-Kopsch) (muscle stretching the annular ligament of the radius, dorsal and palmar). [Variation.] See m. supinator. Tensor membranae atlanto-occipitalis posterioris (Laurent) (muscle stretching the posterior atlanto-occipital ligament). See m. rectus capitis posticus major.
Tensor semivaginae articulationis humero-scapularis (Gruber) (muscle stretching the humeroscapular capsule). [Rare variation.] Origin: I or I and II, or II and III, or III and IV ribs-their cartilages. Insertion: bursa subdeltoidea and lig. coraco-acromiale and to the edge of the tendon of the pars sterno-costalis of the m. pectoralis major. Nerve: nn. thoracales anteriores. Tensor trochleae (muscle stretching the pulley). See m. obliquus superior oculi. Tensor tympani (muscle stretching the eardrum). Syn.: m. Eustachii, mallei, mallei interni. A long but thin cylindrical muscle, which lies in the semicanalis m. tensoris tympani (upper part of the canalis musculo-tubarius); before exiting this canal, the muscle forms a long cylindrical tendon. Origin: auditory tube-its cartilaginous wall, sphenoid bone-spina angularis, temporal bone-pars petrosa, wall of the canalis musculo-tubarii. Insertion: malleus-manubrium mallei. Nerve: n. trigeminus-r. mandibularis, n. tensoris tympani (from the n. pterygoideus internus). HUMAN MUSCLES
Blood supply, Action, Variations: A. glutaea superior from a. hypogastrica and a. circumflexa femoris lateralis from a. femoralis. Tenses the fascia lata of the thigh, flexes the leg at the knee joint, and abducts and flexes both the leg and the trunk at the hip joint. 1) Gruber observed the absence of the M.; 2) cases of division of the M. into two and even three bundles have been noted; 3) the M. is sometimes in closer connection with m. glutaeus medius; 4) the M. may sometimes receive additional bundles: a) from the ligamentum inguinale (Pouparti); b) from the abdominal aponeurosis; c) from the ligamentum ilio-tibiale. 1) Perhaps m. articuli humeri novus (Gantzer) also belongs here, which originated from the II rib, its cartilage, and went tendinously to the capsule of the shoulder joint; 2) m. sterno-humeralis, s. sterno-chondro-humeralis (Huntington) started where m. pectoralis minimus departs, and attached to the fascia of the arm at the site of attachment of m. pectoralis major. Pulls the handle of the malleus, tenses the tympanic membrane. B. M. E. Vol. XIX. No. Name (Latin and Russian). Synonyms. Form and position. Origin and attachment. Innervation and relation to segments. Tensor veli palatini (Muscle tensing the soft palate). Syn.: tensor palati mollis, circumflexus palati, spheno-salpingo-staphylinus, peristaphylinus, dilatator tubae Eustachii, staphylinus. Represents a muscle bundle descending from the base of the skull along the sides of the nasopharynx on the medial surface of m. pterygoideus internus and laterally from m. levator veli palatini; having reached the hamulus pterygoideus, the M. bends over it with its tendon and, assuming a horizontal direction, passes into the aponeurosis palatina and merges with the tendinous fibers of its antimere. Origin: temporal bone-pars petrosa, its facies inferior and the cartilaginous auditory tube. Attachment: soft palate-aponeurosis palatina. N. mandibularis-n. tensoris veli palatini. Teres major (Large round M.). Syn.: rotundus major. A flat (and not cylindrical or round in cross-section!) ribbon of more or less parallel muscle fibers, located on the back between the posterior angle of the scapula and the humerus. In the lower posterior part, the M. is covered by m. latissimus dorsi; in the middle, it lies adjacent to the superficial fascia and skin; in the upper part, it is covered by m. deltoideus and caput longum m. tricipitis; in turn, the M. partially covers mm. infraspinatus and teres minor. Origin: scapula-facies dorsalis, near angulus inferior scapulae and aponeurosis m. infraspinati. Attachment: humerus-crista tuberculi minoris, together with the tendon of m. latissimus dorsi. N. subscapularis. Cv, VI (VII). Teres minimus (Smaller round M.). [Variation.] See m. teres minor. Teres minor (Small round M.). A small, flat, elongated spatula of parallel muscle fibers between the posterior edge of the scapula and the humerus, closely adjacent to m. infraspinatus, from which it is often difficult to separate. The M. is partially covered by m. teres major below and behind and m. deltoideus above; in the remaining part, it lies directly under the skin and superficial fascia. The M. itself partially covers mm. infraspinatus and triceps-caput longum. Origin: scapula-margo axillaris scapulae, between teres major and tuberositas infraglenoidalis. Attachment: humerus-tuberculum majus, its lower facet. N. axillaris. Cv. Thyreo-arytaenoideus (Thyro-arytenoid muscle). Syn.: thyreo-arytaenoideus externus, s. superior. Together with m. vocalis, it represents a wide but thin muscle plate lying along the lateral surface of the larynx medial to the thyroid cartilage in the space between the posterior edge of the arytenoid cartilage posteriorly and the inner surface of the thyroid cartilage along the midline anteriorly. Origin: thyroid cartilage-facies interna. Attachment: arytenoid cartilage-facies lateralis processus muscularis. N. vagus, n. laryngeus inferior-r. anterior. Thyreo-hyoideus (Thyro-hyoid M.). Syn.: hyo-thyreoideus, hyo-thyroideus, thyreo-hyalis. A flat, quadrangular muscle plate along the lateral surface of the larynx between the thyroid cartilage and the hyoid bone; covered by mm. sterno-hyoideus, omo-hyoideus and platysma with superficial fascia. Origin: thyroid cartilage-its linea obliqua. Attachment: hyoid bone-corpus and base of cornu majoris ossis hyoidei. First and second spinal nerves-their rami anteriores. CI and II.
HUMAN MUSCLES
Blood supply, Action, Variations: Tenses the soft palate and dilates the auditory tube. A. subscapularis from a. axillaris. Rotates the arm inward and adducts it. 1) Very rarely absent entirely; 2) very often fuses with the terminal tendon of m. latissimus dorsi; 3) fibers may run from angulus inferior scapulae into m. latissimus dorsi; 4) very rarely there is an additional bundle to the initial tendon of capitis longi m. tricipitis brachii; 5) often an additional bundle runs from margo vertebralis scapulae directly below spina scapulae. A. circumflexa scapulae from a. axillaris. Rotates the arm outward. 1) May rarely be absent; 2) may fuse with m. infraspinatus; 3) the lower bundle separates and attaches to crista tuberculi majoris-m. teres minimus or m. subscapularis minor depending on what it is innervated by: n. axillaris-in the first case and n. subscapularis-in the second. Pulls the processus muscularis of the arytenoid cartilage forward and toward the midline, whereby the vocal processes approach each other and the glottis narrows. 1) According to Soemmering, it may be absent; 2) may consist of two bundles, the smaller of which is m. thyreo-arytaenoideus minor; 3) some bundles may run to the epiglottis. A. thyreoidea superior and r. hyoideus a. lingualis from a. carotis externa. Depresses the hyoid bone. 1) Complete absence has not been observed at all, but partial is possible when the M. attaches not to cartilage thyreoidea, but to m. sterno-thyreoideus; 2) division into m. thyreo-hyoideus medialis and lateralis is observed; 3) the first M. may merge with its antimere and attach: a) to the trachea-this is m. hyo-trachealis; b) to cartilago cricoidea-this is m. crico-hyoideus; 4) superficial bundles of the M. may isolate and enter the capsule of the thyroid gland-these are mm. levatores glandulae thyreoideae laterales, s. hyo-glandulares laterales; 5) m. thyreo-hyoideus superior, s. minor-this is a separated portion of the M. from tuberculum thyreoideum superius and from cornu superius to cornu superius of the hyoid bone; 6) m. kerato-hyoideus, s. thyreo-hyoideus superior lateralis-this is a bundle adjacent to ligamentum thyreo-hyoideum laterale and running from cornu thyreoideum superius to cornu majus of the hyoid bone; 7) m. thyreo-hyoideus superior minor, s. impar (azygos)-this is a bundle along the midline from incisura thyreoidea to the body of the hyoid bone; 8) m. thyreo-syndesmicus-bundles from the M. to ligamentum thyreo-hyoideum laterale; 9) m. thyreo-triticeus-bundles of the M. to cartilago triticea; 10) some bundles of the M. often pass into m. hyo-glossus-this is m. thyreo-glossus lateralis
Related articles
Mentioned in
Cite this page
“Muscles.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/muscles/