Intestine
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Comparative anatomical overview of the intestine in vertebrates from the 1st edition of the Great Medical Encyclopedia (1928-1936), detailing its embryonic development, regional differentiation, and structural adaptations such as the spiral valve, villi, and cecum.
Encyclopedia article (1928–1936)
INTESTINE. Comparative anatomical data. The intestine (enteron) is a more or less long tube beginning with the oral opening at the anterior end of the body (usually on the ventral side) and ending in most animals with a special anal opening at the posterior end. The main part of its internal epithelial lining develops from the embryonic primary gut, i.e., from the entoderm, to which more or less significant ectodermal invaginations later join, forming the initial and terminal sections of the intestinal canal. In vertebrates, only part of the oral cavity on the one hand and part of the cloaca on the other develop from the ectoderm; the entire remaining intestinal canal is lined with entodermal epithelium. As the intestine forms in the embryo, it is enveloped by mesodermal elements, which form a layer of connective tissue with blood vessels (mucous membrane), a muscle layer consisting usually of circular fibers covered by longitudinal ones, and finally, in the body cavity, a serous membrane which is a continuation of the general peritoneal lining. Since the body cavity develops as a paired formation growing around the gut on the right and left, its walls fuse dorsally above the gut to form the dorsal mesentery, and ventrally below the gut to form the ventral mesentery. The latter mostly disappears, persisting partially only in those places where it supports the organs developing within it (especially the liver, partly the pancreas, the urinary bladder). The dorsal mesentery plays not only the mechanical role of an organ suspending the gut, but is also the pathway through which blood and lymph vessels and nerves supplying the gut are brought to it. With the elongation of the gut and the formation of its bends, the ventral margin of the mesentery associated with it also grows, so that the latter forms numerous folds. In all vertebrates, the intestine is differentiated into several sections. In the head region ("head gut"), one distinguishes the oral cavity with a number of auxiliary organs (teeth, tongue, salivary glands) and the pharynx. The latter plays an important role as a respiratory organ in lower vertebrates, since the gill apparatus develops in it (see Gills, Respiratory organs). In higher vertebrates breathing with lungs, this part of the intestine also retains a connection with the respiratory organs. In the trunk region, one distinguishes the foregut, consisting of the esophagus and stomach, the midgut, and the hindgut, ending in the cloaca (see) or directly in the rectum with a special anal opening. The boundaries between the sections of the intestine are not always sharply expressed. Sometimes in lower vertebrates the entire gut is represented by a straight tube of approximately the same diameter (cyclostomes), and even the stomach is not expressed as a special section. The oral cavity, pharynx, and esophagus are lined with stratified epithelium, while the stomach and the intestine proper are lined with single-layered columnar epithelium. However, sometimes certain parts of the stomach in mammals are also covered with stratified epithelium; in this case, the "esophageal region" of the stomach is distinguished. The muscular wall of the gut consists of smooth muscle cells. However, in the initial (oral cavity, pharynx, and part of the esophagus) and terminal parts of the intestine, striated musculature is present. The boundary between the stomach and the midgut is usually clear and marked by the presence of a circular pyloric fold. The foregut is innervated by the vagus nerve and has longitudinal folds of the mucous membrane. In the region of the stomach, it is equipped with special tubular glands (cardiac, fundic, and pyloric). The intestine is innervated by the sympathetic nervous system and initially possesses reticulated folds of the mucous membrane. The excretory ducts of two large glands—the liver and the pancreas—empty into the initial section of the midgut. In addition, the walls of the gut themselves possess their own digestive glands (Crypts of Lieberkühn). The hindgut is also separated by a circular fold. In most vertebrates, it is short and sometimes distinguished by a somewhat wider diameter (amphibians, reptiles). Only in mammals does it acquire the significance of a large and important section of the intestine, the beginning of which is marked by the presence of a more or less significant blind outpocketing ("cecum"). The intestine proper initially forms a straight tube, the absorptive surface

Figure 1. Spiral valve of a skate.
of which in lower vertebrates increases due to the formation of a large fold running in a spiral along a significant part of the intestine, which has been named the spiral valve (Fig. 1). In lower fishes, such a fold cuts deeply into the lumen of the intestine and forms more or less steep turns, resembling a spiral staircase. The turns can partly embrace each other, acquiring
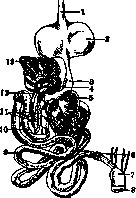
into long villi completely covering the internal
the appearance of cones nested inside each other. With a well-developed spiral valve, the intestine has a short length but a large diameter. Food passes along such an intestine in a spiral path along the valve. In higher fishes and terrestrial vertebrates, instead of this, an elongation of the intestine itself is observed, which forms more or less significant convolutions (Figure 2). The increase in the absorptive surface of the intestine is also achieved by the formation of a system of smaller folds—trabeculae, which have a reticulated arrangement in the midgut. The wall of the intestine then acquires a cellular character. The edges of the trabeculae are often uneven, and irregular rows of numerous papillae develop on them. In birds and mammals, these papillae Fig. 2. Intestine of a pigeon: 1—esophagus; 2—crop; 3 and 5—glandular and muscular stomach; 4—spleen; 6—two ceca; 7—cloaca; 8—anus; 9—large intestine; 10—duodenum; 11—pancreas; 12—liver with ducts; 13—anterior surface of the mucous membrane and giving it a velvety appearance. In mammals, the midgut also contains a rather significant system of larger longitudinal and transverse folds of the mucous membrane. In general, the mammalian intestine reaches a significant length and is clearly differentiated into sections. The initial section of the intestine proper ("duodenum") also contains special Brunner's glands. The long "small" intestine forms numerous convolutions. The hindgut is especially strongly developed in mammals (compared to other vertebrates), divided into the large intestine with a blind outpocketing at its beginning and the rectum. The cecum is absent in many insectivores and in bears. It is also absent in sloths and the hippopotamus, which have a complex stomach. Other herbivores usually have a long cecum, especially in cases where the stomach is simple (horse; Fig. 3). Its surface can be further increased by the formation of numerous outpocketings, as in the large intestine (horse, pig), or by the formation of a spiral fold (rabbit). In many mammals of various systematic groups (some rodents, carnivores, prosimians, and anthropoids), the end of the cecum forms a thin vermiform appendix [appendix (see)]. In many cases, the large intestine forms lateral rows of regularly positioned outpocketings (haustra), separated by longitudinal muscular bands (taenia; Fig. 3). Carnivores and ruminants lack these formations.
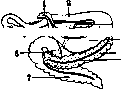
The rectum possesses significant musculature, but is not sharply demarcated from the large intestine. In lower, oviparous mammals, it ends in a cloaca; in viviparous mammals, directly at the anal opening.
I. Schmalhausen. Development of the intestine. In a 3 mm embryo, the intestinal canal is a tube connected in its lower section with the yolk sac by means of the vitelline duct (ductus vitello-intestinalis, s. omphalo-entericus). Its cranial segment (prior to the vitelline duct) gives rise to the pharyngeal gut (see), the stomach, the duodenum, and the anterior section of the small intestine; the caudal segment gives rise to the rest of the small intestine and the large intestine. By the beginning of the 2nd month, the intestinal tube forms a loop with the vitelline duct at its apex, which enters the initial section of the formed umbilical cord (cutaneous umbilicus), forming a physiological umbilical hernia that disappears at the beginning of the 3rd month. This loop includes a section giving rise to the small intestine; the boundary between it and the duodenum is formed by the flexura duodeno-jejunalis (see Duodenum, figure 1, and Peritoneum). In the caudal part of the loop, not far from the apex, the anlage of the cecum appears as a small thickening; the section lying below forms a bend—the flexura coli sinistra; thus, the boundaries of the future sections of the intestine are outlined. Subsequently, the intestine, which previously lay in the sagittal plane, undergoes a rotation to the right, as a result of which the section below the flexura coli sinistra moves to the left, and the section above it moves to the right and upward, and thus the anlage of the large intestine covers the cranial section and the duodenum (Fig. 4). By the middle of the 2nd month, the anlage of the small intestine begins to grow, forming intestinal bends, and coils into a ball lying within the umbilical canal. In the large intestine, the descending and transverse parts are outlined earliest; the ascending part is initially designated by a small bend up to the cecum and develops fully only by the 6th month. The cecum initially represents a single large cavity, the free end of which subsequently lags in growth and forms the vermiform appendix. The rectum develops from the cloaca by the formation of a septum, simultaneously with the urogenital sinus. Initially, the large intestine is comparatively long; by the end of the 3rd month, the small intestine develops intensively; it becomes significantly wider than the large intestine, especially when it fills with meconium in the 4th month. Only in the 7th-8th month does the large intestine begin to grow in thickness. Villi begin to develop in the 4th month in both the small and large intestines; in the latter, they disappear in the 9th month, entering the thickness of the mucous membrane, which causes a large length
Figure 3. Diagram of the large intestine of a horse: 1 - col. transv.; 2 and 4 - col. dors. sin. et dex.; 3 - ileum; 5 - col. ventr. dex.; 6 - taenia coli; 7 - caecum; 8 - opening of the ileum into the caecum; 9 - col. ventr. sin. of Lieberkühn's glands. Lieberkühn's glands appear later than the villi in the form
Figure 4. Semi-schematic depiction of the rotation of the large intestine around the small intestine: 1 - stomach; 2 - duodenum; 3 - large intestine; 4 - small intestine. (After Kölliker.)
of small pouches; circular folds form in the 8th month.
V. Karpov. Anatomical and topographical data. The intestine is divided into two sections: the small and large intestines. The small intestines (intestinum tenue) consist of the duodenum, jejunum, and ileum. The small intestines occupy almost the entire lower section of the abdominal cavity, begin from the flexura duodeno-jejunalis at the level of the body of the 1st lumbar vertebra to the left of the spine, and terminate in the right iliac region, where they pass into the cecum (Fig. 5). The diameter of the small intestines gradually decreases from top to bottom: at the flexura duodeno-jejunalis it is about 2.5-3 cm, at the transition point to the cecum—2.0-2.5 cm. The upper 2/5 of the small intestines are called
Figure 5. Topography of the intestine: 1 - ascending
colon; 2 - ileum; 3 - sigmoid colon; 4 - peritoneum; 5 - jejunum; 6 - transverse colon. the jejunum, the lower 3/5—the ileum. There is no sharp difference between them, and this division is conventional. The walls of the jejunum are thicker than those of the ileum, richer in vessels, and form a large number of folds along their course. In a corpse, the jejunum is usually empty, while the ileum is filled with intestinal
Figure 6.
contents and distended with gases. Still, the jejunum differs very little in appearance from the ileum, and an exact boundary between them cannot be drawn. The jejunum is located in the umbilical region and in the left iliac fossa; the ileum—in the hypogastric region, umbilical region, and pelvic cavity. The length of the small intestines varies with age. According to Treves, in 20-25-year-old individuals it is 6.75 m; but fluctuations ranging from 4.5 to 9.5 m are also possible. Apparently, individual fluctuations in the length of the intestine depend on a number of external factors and primarily on a series of physiological conditions (the nature of the food, the degree of habitual filling of the stomach and intestines, etc.). In the newborn, the length of the intestine exceeds the body length by 7 times, in the adult—by 3-4 times. Along their course, the small intestines form a series of bends and loops, with the loops of the jejunum lying predominantly transversely, and those of the ileum—vertically. Externally, the jejunum and ileum are covered by the peritoneum. Internally, the small intestines are covered by the mucosa. In the upper section, in the jejunum, the mucosa forms folds—plicae, s. valvulae conniventes, circulares Kerkringi. Their number gradually decreases in the direction from the jejunum to the ileum, and in the ileum they are almost absent. Besides the indicated folds, the mucosa also contains fine, thread-like villi—villi intestinales. There are more villi in the jejunum than in the ileum. Their total number reaches 4 million. Each papilla (villus) contains inside the so-called central papillary sinus. The latter represents a club-shaped dilation of the lymphatic vessels of the intestinal mucosa, covered with endothelium. Sometimes there are several such sinuses in a single papilla. Numerous papillary vessels are located between the central sinus and the epithelium. In addition, the mucous membrane of the jejunum contains accumulations of lymphatic tissue called solitary follicles (noduli lymphat. solitarii). They reach the size of a pinhead and in places form accumulations (numbering 20-30 or more). These accumulations of solitary follicles are called Peyer's patches [noduli aggregati (Fig. 6)]. Their shape is oval, and the long diameter is parallel to the axis of the intestines. In individual cases, the patches reach very large sizes (up to 15-20 cm). In the jejunum, solitary follicles are few, and Peyer's patches are almost completely absent. The jejunum and ileum are covered by a smooth serous membrane that passes into the mesentery (see).
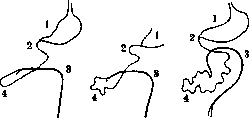
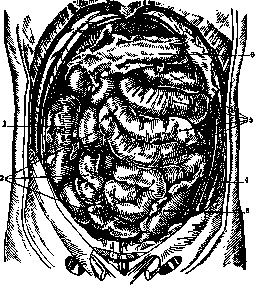

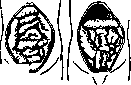
Figure 7. Types of intestinal loops (after Pavlenko). The loops of the small intestine, when filled and distended by gases, can be palpated through the anterior abdominal wall. The relation of the small intestine to neighboring organs is difficult to determine precisely: they lie on the side of least resistance and constantly change their position under the influence of movements and changes in body position, respiratory excursions and contractions of the diaphragm, the degree of filling of adjacent organs, the state of the abdominal press, etc. In the vertical position of the body, the loops of the small intestine descend into the pelvic cavity. In the horizontal position of the body with the pelvis elevated (Trendelenburg position), the intestinal loops shift from the pelvic cavity into the upper regions of the abdominal cavity. Despite such great displaceability of the small intestine, it can nevertheless be said that certain segments of the jejunum and ileum usually lie in the same places in the abdominal cavity. According to the types of mesentery position, two types of position of the small intestine loops are distinguished: in one case—with a narrow lower-thoracic aperture and a comparatively wide pelvis—the loops lie in their main mass vertically, and in the other—with a wide lower-thoracic aperture and a relatively narrow pelvis—the loops lie predominantly horizontally (Figure 7). Above, the small intestine is in contact with the mesentery of the colon and with the transverse colon; in front, with the greater omentum and the anterior abdominal wall, to which they adjoin by the side opposite the attachment of the mesentery. On the sides, the small intestine adjoins the ascending and descending colons; posteriorly, to the kidneys, spine, ureters, inferior vena cava, abdominal aorta; below, they border on the pelvic cavity and its contents (urinary bladder, sigmoid colon). In approximately 2% of cases, a remnant of the omphalomesenteric duct occurs (at a distance of approximately 1 m from the ileocecal valve); at the same time, on the side opposite the attachment of the mesentery, a blind appendix is observed, the lumen of which is approximately equal to the diameter of the small intestine. This blind pouch is called Meckel's diverticulum or ileal diverticulum. Usually, its length is 4-6 cm. Sometimes it is connected by means of a cord to the umbilicus; less commonly, the diverticulum has a communication in the form of a canal with the umbilicus. In these cases, the exit of feces from the fistulous tract is observed. The small intestine is attached to the posterior abdominal wall by means of the mesentery. The root of the mesentery has a length of about 13-15 cm, running obliquely from top to bottom and from left to right. The length of the mesentery is unequal in various sections of the small intestine. It is longer the further the intestinal segment is removed from its beginning [i.e., shortest near the duodenojejunal flexure and longest at the terminal ileum (20-25 cm)]. The position and shape of the mesentery are subject to large individual variations. Two types of position of the root of the mesentery should be distinguished: vertical and horizontal (Pavlenko). The first is characteristic of individuals with a narrow lower-thoracic aperture and a wide pelvis; the second is encountered with a wide lower-thoracic aperture and a narrow pelvis (Fig. 7). The large intestine is divided into the following sections: the cecum with the vermiform appendix, the ascending, transverse, descending colon, and sigmoid colon (Figure 8). In appearance, the large intestine differs sharply from the small one: their diameter is significantly larger (about 5-8 cm); they have bundles of longitudinal musculature known as taeniae (three in number); transversely running cords or folds (semilunar folds), which correspond to depressions (transverse sulci); protrusions of the wall of the large intestine (haustra) in the intervals between the transverse cords, and accumulations of adipose tissue on the surface of the intestine in the subserous layer (epiploic appendages). The length of the large intestine is approximately 1.3 m. The diameter of the upper sections of the large intestine is larger, and of the lower (caudal) ones—smaller. The walls of the large intestine consist of the same layers as the small one. The serous membrane does not cover the colons entirely in all sections: in the region of the ascending and descending colon, it represents an incomplete covering—their posterior wall is not covered by the peritoneum. The muscular tunic consists of two layers: an outer longitudinal and an inner circular. The first layer is distributed unevenly in the walls of the large intestine: it forms three flat, sharply demarcated bundles, about 10 mm wide and 2 to 3 mm thick. The intervals between them are covered only by a very thin layer of longitudinal musculature. The taeniae are located in the walls of the large intestine in three typical places: one (free taenia) lies under the serous membrane (transshining through it) at the free edge of the intestine, and the other two are on the posterior surface of the colon. On the transverse colon, one of the taeniae corresponds to the place of attachment of the mesocolon to the intestine and is called the mesocolic taenia; the other, to the place of attachment of the greater omentum (omental taenia). The circular muscle layer is also distributed unevenly: between the haustra, it is expressed somewhat more strongly. The mucous membrane of the large intestine differs from that of the small one by the absence of villi and circular folds. In places, the mucous membrane forms clearly noticeable folds—semilunar folds of the colon. They consist of mucous, submucous, and muscle tissue (circular fibers) and usually encompass not the entire circumference of the intestinal lumen, but only one third of it. The number of these folds and the nature of their distribution vary very strongly. Semilunar folds and haustra are formed as a result of the uneven contraction of the longitudinal and circular musculature. Epiploic appendages have a flap-like shape and are located at the level of the semilunar folds in two rows: one on the anterior, the other on the medial side of the colon. The transverse colon has only one row of epiploic appendages. In fat subjects, the epiploic appendages reach significant sizes, being located in the form of massive polyps on a thin stalk. The ascending colon begins in the right iliac region and is the direct continuation of the cecum. It goes from bottom to top, bending slightly.
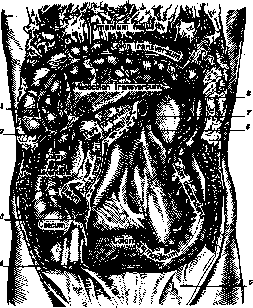
Figure 8. View of the posterior wall of the abdominal cavity: 1—epiploic appendages; 2—right colic flexure; 3— inferior ileocecal recess; 4—deferent duct; 5— epigastric fold; 6— ascending part of duodenum; 7— duodenojejunal flexure; 8— left colic flexure. (From Rauber.)
to the lateral side, and at the lower edge of the liver forms a bend called the hepatic flexure or right colic flexure, after which it passes into the transverse colon (colon transversum). The ascending colon lies below the liver in front of the descending part of the duodenum and the head of the pancreas, and is partially covered in front by loops of the small intestines; in the lateral abdominal region, the ascending colon lies on the fasciae covering the quadratus lumborum muscle, transverse abdominal muscle, and on the iliac fascia, and above it touches the right kidney and the lower surface of the liver (colic impression). Variations observed in this regard are presented in Fig. 9. The ascending colon is projected onto the surface corresponding to the position of the transverse processes of the lumbar vertebrae and the twelfth rib. The transverse colon (colon transversum) lies transversely, running from right to left from the right hypochondriac region through the epigastric region, umbilical region to the left hypochondriac region; near the lower edge of the spleen it forms a bend called the splenic (left) flexure (flexura lienalis, s. sinistra coli). The angles of the transverse colon are attached to the posterior abdominal wall. Usually, the splenic flexure lies somewhat higher than the hepatic flexure and crosses the left kidney either in the upper, middle, or, more rarely, lower third. By means of the phrenicocolic ligament, it is attached to the diaphragm. On the anterior abdominal wall, the transverse colon is projected by means of a line connecting the ends of the cartilages of the tenth ribs. The transverse colon is in contact above with the gallbladder, liver, and spleen, in front with the anterior abdominal wall, behind with the duodenum, pancreas, and below and behind with the small intestines. The transverse colon is slightly protruded forward, while both flexures lie more posteriorly. The descending colon (colon descendens) lies in the left half of the abdominal cavity, runs from top to bottom through the left hypochondriac and lumbar regions to the left iliac region and passes into the sigmoid colon. Above, the border of the descending colon corresponds to the twelfth rib, below to the left iliac bone. In front it is partially covered by loops of the small intestines, above it touches the lower pole of the spleen (colic impression of the spleen), behind with the costal part of the diaphragm, quadratus lumborum muscle, transverse abdominal muscle, and the left kidney. The sigmoid colon (colon sigmoideum), forming a bend, passes at the level of the third sacral vertebra into the rectum. The length, shape, and position of the entire large intestine are subject to great individual variations. The ascending colon is sometimes short (up to 8-10 cm), and the transverse colon in these cases runs in an oblique direction from right to left and from bottom to top, and the hepatic flexure is located low. The transverse colon sometimes lies not horizontally, but forms a bend facing with its convexity downward (U-shape). Comparatively rarely, the sigmoid colon forms a convexity facing upward. Its length ranges from 30 to 80 cm (on average 50 cm). The descending colon is also sometimes very much shortened. The sigmoid colon is the most variable in its position and shape. In some cases it is short, and the bend formed by it is insignificant. In other cases, conversely, it is long, forming one or several loops lying either in the pelvic cavity or high (sometimes even under the liver). According to Sozon-Yaroshevich, the length of the sigmoid colon averages 49.36 cm and increases with age: up to 10 years it is 31.55 cm, from 11 to 20 years 36 cm, from 21 to 30 years 47.75 cm, from 31 to 40 years 51.68 cm, after 40 years 57.27 cm. The relation of the sigmoid colon to neighboring organs [see separate table (vol. IV, art. 147-148), figure 2] is extremely variable and depends chiefly on the state of its filling. In the empty state, it hangs down into the pelvic cavity and is in contact with its bottom, with loops of the small intestines, the anterior surface of the rectum, and the urinary bladder. In the filled state, the sigmoid colon can be displaced high into the abdominal cavity. Special note should be made of those anomalies of the position of the intestines that are explained by their abnormal development. As is known, during embryonic life, torsion of the intestine occurs around the superior mesenteric artery in a counterclockwise direction. Torsion may deviate in the opposite direction or stop at any point between 90 degrees and 180 degrees. In addition, there may be an arrest in the differentiation of the peritoneum at the embryonic stage, premature or delayed formation of adhesions, growth disharmony, and a delay in the movement of the embryonic intestine. In this way, dystopias of the large intestines, sinistro- and dextropositio, etc. can arise (Shevkunenko). The intestine is supplied with blood by means of the superior and inferior mesenteric arteries (figure 10). The superior mesenteric artery supplies the entire small intestine and part of the large intestine up to the middle of the transverse colon.
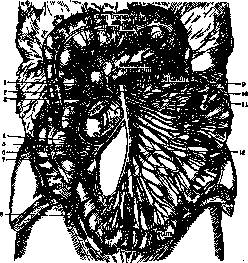
Fig. 10. A. mesent. sup. - 9, 2 - Duodeno-jejun., 2 - A. colica med., 3 - A. colica dex., 4 - A. ileo-colica; 5 - Ram. colicus; 6 - Ram. iliac.; 7 and 8 - A. appendic.; 10 - A. pancreatico-duod. inf.; 11 - Aa. jejun.; 12 - Aa. ileae. (According to Rauber.)
It originates from the abdominal aorta [see separate table (vol. IV, art. 147-148), fig. 3], lies behind the pancreas and descends downward, running in front of the horizontal part of the duodenum in the leaflets of the mesentery of the small intestines. The superior mesenteric artery on its way gives off a large number of branches that anastomose with each other and form a series of arches, arcades, located in several rows and bearing the name of arches of the first, second, third, and so on orders. In its lower section, the artery curves somewhat to the right. To the jejunum and ileum, the superior mesenteric artery gives about 12-16 branches. Just like the artery itself, these branches are embedded in the leaflets of the mesentery of the small intestine. The lowest branch of the superior mesenteric artery is the ileocolic artery. It departs from the right side of the trunk, runs to the right and downward to the ileocecal angle, where it divides into two branches: the iliac branch, running to the left, connecting with the end of the superior mesenteric artery and supplying blood to the terminal ileum, and the colic branch, running upward to connect with the right colic artery and downward to connect with the iliac branch. This branch supplies blood to the terminal
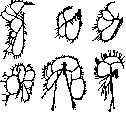
Figure 11. Types of branching of the superior mesenteric artery. (According to Kupriyanov.)
part of the terminal ileum, cecum, vermiform appendix, and ascending colon. From the right side of the superior mesenteric artery, sometimes another right colic artery arises. It runs retroperitoneally from left to right transversely toward the middle sections of the ascending colon, and near the latter divides into ascending and descending branches connecting with neighboring arteries. Very often this artery is merely a branch of the ileocolic artery. From the anterior surface of the superior mesenteric artery arises the middle colic artery, supplying blood to the transverse colon. It runs from bottom to top between the leaves of the mesocolon and, without reaching the transverse colon, connects by means of arches with the right colic artery and left colic artery, which belongs to the system of the inferior mesenteric artery. The arciform connection between the middle colic artery and the left colic artery is called the arcade of Riolan. - The inferior mesenteric artery arises from the anterior surface of the abdominal aorta between the second and third lumbar vertebrae and supplies blood to the left half of the transverse colon, descending colon, sigmoid colon, and part of the rectum. It runs from top to bottom and from right to left, lying within the folds of the peritoneum. The upper branch of the inferior mesenteric artery—the left colic artery—runs retroperitoneally from right to left obliquely upward, lying anterior to the left kidney, toward the descending colon. It divides into ascending and descending branches and anastomoses above with the middle colic artery, and below with the sigmoid artery. The latter is the second branch of the inferior mesenteric artery. It runs in an oblique direction from right to left toward the sigmoid colon and gives off two branches: an ascending branch, anastomosing with the left colic artery, and a descending branch, connecting with the superior hemorrhoidal artery, which is the terminal branch of the inferior mesenteric artery. The superior hemorrhoidal artery runs downward and behind the rectum within the thickness of the mesorectum, divides into two branches spreading along the sides of the rectum. In its lower section, it anastomoses with the inferior hemorrhoidal artery. - In the pattern of branching of the superior and inferior mesenteric arteries, individual variations are observed, which can be reduced to two types: main and ramified. The types of branching of the superior mesenteric artery are presented in Figure 11. The veins of the intestine belong to the portal vein system and represent two large trunks: the superior mesenteric vein and the inferior mesenteric vein (Figure 12). The superior mesenteric vein collects blood from the jejunum, ileum, cecum, appendix, ascending colon, and the right half of the transverse colon, lies within the thickness of the mesentery to the right of the corresponding artery, and is formed from the following branches: 1) jejunal and ileal veins collect blood from the corresponding sections of the small intestines; 2) ileocolic vein collects blood from the terminal ileum, cecum, appendix, and the lower half of the ascending colon; 3) right colic vein collects blood from the upper sections of the ascending colon; 4) middle colic vein services the transverse colon. The drainage area of the inferior mesenteric vein corresponds to the distribution area of the corresponding artery and is composed of the following branches: the left colic vein and the sigmoid vein. The latter anastomoses with the inferior hemorrhoidal vein. The pattern of formation of the veins is subject to individual variations. Between the intestinal veins and the system of the vena cava is a-gal

Figure 12. Superior and inferior mesenteric veins (7 and 8); 1 - pancreatic vein; 2 - right colic veins; 3 - ileum; 4 - inferior mesenteric artery; 5 - intestinal veins; 6 - left colic vein; 9 - superior mesenteric artery. (After Spalteholz.) There exist anastomoses between the inferior mesenteric vein (so-called portacaval anastomoses), through which ascending thrombi after operations on the intestine can spread to the venous system of organs serviced by the tributaries of the inferior vena cava (see Venae cavae, Figures 2, 3, 4, and 7). - The lymphatic vessels of the intestine are arranged in two layers: one lies in the submucosa, the other in the subserous layer. The submucosal lymphatic vessels run around the intestine circularly and are mainly lacteals collecting absorption products from the intestine during digestion. The vessels of the subserous layer run along the intestinal wall and are proper lymphatic vessels. However, between

*" " A A"1* «-»>'» *i«v* Figure 13. these layers there exist anastomoses. Emerging from the intestinal wall, the lymphatic vessels lie perivascularly. They empty into the mesenteric lymph nodes, embedded in the thickness of the mesentery (Figure 13), numbering about 180. The clusters of glands sometimes observed at the root of the mesentery are called the pancreas of Aselli. The lymphatic vessels of the transverse colon (Figures 14 and 15) empty into the mesocolic lymph nodes located at the base and in the thickness of the mesocolon. The efferent vessels of these glands unite into the intestinal trunk. The latter, together with the lumbar trunk, empties into the cisterna chyli. The nerves of the intestine belong mainly to the vagus nerve and sympathetic nerve systems, but contain spinal nerve fibers: intestinal branches, innervating the jejunum,
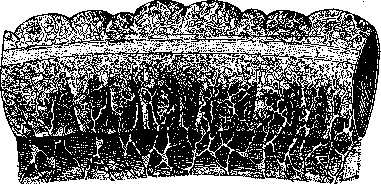
Figure 14.

Figure 15. ileum, and colic branches, running to the cecum, ascending colon, and part of the transverse colon. Reaching the mesenteric border of the intestine, the nerves form a plexus beneath the serous membrane and send numerous branches to the ganglionic plexus embedded between the longitudinal and circular muscle layers of the intestines, bearing the name of the myenteric plexus or Auerbach's plexus. In the submucosal layer there is a second nerve plexus, which is called the submucosal plexus or Meissner's plexus. It connects by numerous branches with the preceding one. Both of these plexuses extend along the entire intestinal tract. The aortic plexus also sends branches to certain sections of the intestine, namely: to the descending colon, sigmoid colon, and superior part of the rectum. The vagus nerve sends its branches to the intestines through the mediation of celiac branches running along the left gastric artery to the celiac plexus, and from there to the intestine. The quantitative ratio of the branches of the vagus, sympathetic, and spinal nerves in the ganglia is different: in some cases the branches of the vagus nerve predominate, in others the sympathetic nerve branches, and in others the spinal nerves. The pattern of origin of the branches from the celiac ganglion is different in various individuals and can be represented in the form of 2 types: in one—the number of branches is small, and they depart in the form of trunks that branch weakly; in the other—there are many branches, and they themselves in turn break down into a whole series of smaller branches (Figures 16 and 17). F. Walker. Histology of the intestine. The wall of the intestine consists of three layers: 1) mucous membrane (tunica mucosa), which is divided by a layer of smooth muscles (muscularis mucosae) into the mucosa proper and the submucosa (tunica submucosa); 2) muscular coat (tunica muscularis), and 3) serous membrane (tunica serosa). In view of the fact that the structure of the mucous and muscular membranes in the small and large intestine exhibits differences, it is more convenient to describe them separately. - Small intestine. The mucous membrane has a thickness of about 0.5 mm; it forms permanent folds running across the intestine for approximately 2/3 of its circumference (circular folds of Kerkring), which include the muscularis mucosae as well. The folds begin in the duodenum at a distance of 2-5 cm from the pylorus in the form of low elevations, reach full development at the duodenal papilla, and continue in this form to the middle of the jejunum, whence they become lower and end in the middle of the ileum. The entire surface of the mucous membrane, including the folds, is covered with villi (intestinal villi), thin outgrowths 0.5-1.0-1.5 mm in length, which impart a velvety appearance to the mucosa (Figure 18). Their number per 1 mm2 in the duodenum and jejunum is 22-40, in the ileum—18-31 (Kölliker). The shape of the villi is somewhat different and can be reduced to two main types: lamellar or leaf-like, and cylindrical or finger-shaped (Sappey); the former predominates in the duodenum, the latter in the remaining part of the intestine. Between the villi are visible the openings of Lieberkühn's glands (from 2 to 7). - The epithelium covering the mucous membrane and villi is single-layered columnar and consists of cells of two kinds: striated and goblet cells (Figure 19). The striated epithelium (cells 22-30 µ in length, 6-9 µ in width) bears on its free surface a shiny cuticular border, which on thin sections reveals transverse striation. Views on its structure have not yet been brought to unity: some authors (Brettauer and Steinach, Prenant) believe that it consists of thin rods, or hairs, having lost the ability to flicker; others (Kölliker, R. Heidenhain, Flemming) see in it a cuticular formation penetrated by pores into which fine protoplasmic outgrowths enter (porous epithelium). By acting with 2% NaCl, it is possible to detach the border and draw out outgrowths from it (R. Heidenhain). In the body of the cell, several zones can be distinguished: beneath the border lies a narrow transparent zone, in which a centrosome is described in the form of two granules; behind it is located a broader—granular one; from here to the nucleus extends a wide zone containing fibers, tonofibrils (M. Heidenhain), which other authors consider to be mitochondria (Champy); housed within it is also the reticular Golgi apparatus, giving off outgrowths on the sides of the nucleus; further located is the oval nucleus,
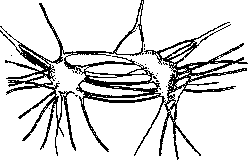
Figure 16. Celiac ganglion. Concentrated type.
and beneath it a basal zone also with mitochondria. The striated epithelium serves for absorption; during digestion, tiny fat droplets appear in it in the second zone; descending downwards, they merge into larger ones. Goblet cells were formerly considered independent elements (Bizzozero); currently, most authors regard them as mucin-transformed striated cells which, after expelling the mucus, acquire a striated border anew (List, Paneth, Möllendorff). The lamina propria of the mucous membrane, separated from the epithelium by a structureless basement membrane, consists of reticular tissue in the meshes of which a large number of leukocytes are lodged, mainly lymphocytes, fewer eosinophils, and plasma cells, which partly undergo degeneration (Schollenleukocyten) and partly emigrate into the lumen of the intestine; a certain number of leukocytes are always found in the epithelium in the form of rounded bodies with nuclei. The villi (Fig. 20) as outgrowths of the mucous membrane are constructed in the same way; their feature lies in the arrangement of blood vessels and the presence of smooth muscles, which
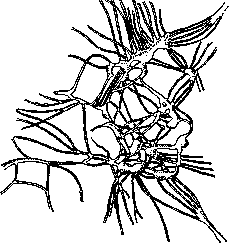
Figure 17. Gangl. coeliacum. Scattered type.
is connected with the function of the villus—absorption. The arterioles, entering the villus, break up into a finely meshed capillary network located beneath the epithelium, which then collects into a single venule. Along the axis of the villus is located a straight and wide lymphatic capillary (rarely 2 or 3) 27-36 μ in length, beginning blindly above and passing into the deeper-lying lymphatic network; the absorbed fat is transported into it (by a poorly clarified pathway). Between the blood and lymphatic vessels in the core are located bundles of smooth muscles rising from the muscularis mucosae to the apex of the villus, where they anastomose. At the moment of absorption, the villi fill with blood, swell, and rise; the contraction of smooth muscles shortens and wrinkles them, which facilitates the outflow of fluids. Lieberkühn's glands (glandulae intestinales; Fig. 21),
otherwise crypts, are simple tubular glands, rarely branched, 0.3-0.4 mm long; in humans they are significantly shorter than in carnivores. The cells lining their lumen are of the same character as those of the mucous membrane and in sections are a direct continuation of the villus epithelium; only they are lower (18 μ), and the striated border in the deeper-lying cells is thinner. Mitoses are frequently encountered in these cells, which is why Bizzozero asserted that the purpose of the crypts is to serve as a site of regeneration for the epithelium of the mucous membrane. However, at the bottom of the glands, Paneth described special cells containing in their upper part
Figure 18. Mucous membrane of the small intestine from the surface under low magnification. Villi and openings of Lieberkühn's glands. (After Kölliker.) clear granularity of a protein character, clearly visible in life and staining with both acidic and basic dyes, which places the glandular character of the crypts beyond doubt. In the mucous membrane of the small intestines there are further lymphatic nodules, the so-called solitary follicles, measuring 0.5-2 mm, in variable quantity; developing, they bulge the mucous membrane, pushing apart the villi and glands; they can also penetrate into the submucosa. Small follicles are of a rounded shape; larger follicles often become pear-shaped with a broad base and a pointed apex. Clusters of follicles (usually 20-30 up to 60 and 100), the so-called Peyer's patches (agmina Peyeri), protrude on the mucous membrane of the lower part of the jejunum and ileum in the form of oval plaques from 2 to 12 cm long (in rare cases more), from 1 to 3 cm wide; their total number is 30-40; they are always located on the side opposite to the attachment of the mesentery. Sections show Figure 19. Striated and goblet epithelium,


Figure 20.
Figure 21. Figure 20. Section of the mucous membrane of the human small intestine. Villi and Lieberkühn's glands. (After Braus.) Figure 21. Section of the bottom of a Lieberkühn's gland under high magnification. At the bottom, Paneth's granular cells are visible. (After Braus.) that the follicles making up the patches lie deep in the submucosa; on their surface, the villi are shortened and smoothed out. The muscularis mucosae represents a thin layer of an inner circular and outer longitudinal layer of smooth muscles. The submucosa located beneath them consists of loose fibrous connective tissue and contains a network of blood and lymphatic vessels and a nerve plexus (plexus entericus, s. Meissneri) (see Autonomic nervous system). The submucosa has its greatest thickness in the duodenum, where Brunner's glands are embedded in it. The muscular coat consists of two layers of smooth muscles: the inner circular and the outer longitudinal, which is more weakly developed; between them lies the nerve plexus (plexus myentericus, s. Auerbachi). The outer coat is serous, or the peritoneum (see). Large intestine. The mucous membrane (Fig. 22) is distinguished by the absence of vil
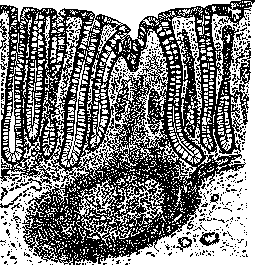
Figure 22. Section of the mucous membrane of the human large intestine: Lieberkühn glands, below them a solitary follicle with a light germinal center. (According to Braus.) sinus; its surface is covered with striated epithelium containing goblet cells. The Lieberkühn glands are considerably longer than in the small intestine, reaching 5-7 mm in the rectum. The number of goblet cells in them is extremely large, especially in the neck and middle of the gland; simple cylindrical cells with a thin cuticular border are located in the base; mitoses are encountered among them, and epithelium regeneration apparently proceeds from there. Paneth cells are absent. The proper tissue of the mucous membrane is infiltrated with leukocytes; solitary follicles of large size (1.5-3 microns) with tubular depressions of the mucous membrane at their apices are scattered in it. Follicles develop especially strongly in the vermiform appendix, sometimes leading to the complete destruction of the Lieberkühn glands, which, after the atrophy of the follicles, can supposedly grow back again (Rudinger). The muscular coat is characterized by the incomplete development of the outer longitudinal layer, forming three bands (taeniae). The serous membrane is absent on the posterior wall of the ascending and descending parts and in the lower section of the rectum. V. Karpov. Anatomical features of the intestine in children. Age-related features of the intestine concern its dimensions (length and width of the lumen), structure, and topography. From the first days of life to adulthood, the dimensions of the intestine continuously increase. But, as established by a number of authors [Beneke, Taronetsky, Debele, Anserov, and others], the growth rate of the intestine at various ages is unequal. Likewise, there is a difference in the growth ratio of the small and large intestines. Finally, the intestine grows differently in length than in width. Even during the first year of life, the intestine grows unevenly. According to Frolovsky, the greatest increase in length falls on the 2nd month. Already at this age, a disproportion in the growth of the small and large intestines becomes noticeable: the latter grow at a more energetic rate than the former. - The relative length of the intestine (compared to the length of the trunk) in newborns is greater than in adults due to the relatively greater length of the small intestines. Up to 3 years it continues to increase, then gradually decreases, and by the time of puberty becomes a constant value (Table 1). Table 1. Age Spine and intestine length ratio Spine and small intestines ratio Spine and large intestines ratio 0-1 yr...... 1-3 yr..... 3-10 yr..... 10-15 yr..... Adults .... 1:15.3 1:17.4 1:14.0 1:13.4 1:13.2 1:13.0 1:14.6 1:11.5 1:10.8 1:10.7 1:2.3 1:2.9 1:2.5 1:2.6 1:2.6 The indicated change in relative length applies equally to both the small and large intestines and is explained by fluctuations in the growth not only of the intestine itself, but also of the spine, the length of which is taken as the unit of measurement. From this it is clear that the relative length does not give a distinct idea of the growth rate of the intestine. The latter proves possible if we take the percentage increase in the length of the intestine at each age compared to the previous one (Table 2). Table 2. Age Length increase (in %) small intestines large intestines 1-3 yr. . . . 3-10 yr. . . . 10-15 yr. . . . Adults . . 23.9 8.2 22.0 18.7 36.8 18.6 34.3 18.8 The data of Table 2 indicate that there are two rises in the growth of the intestine: 1) from 1 to 3 years, when the organism transitions from milk, easily digestible food to mixed food, which requires a larger digestive and absorptive surface, and 2) from 10 to 15 years, during puberty, associated with the enhanced development of all body functions. It is understandable that the intestine must satisfy the increased demands placed upon it; this is expressed in its energetic growth in length. The aforesaid applies equally to the small and large intestines. But the latter grow at a faster rate not only during the first year of life, but also later, up to and including the period of puberty. As a result, the difference in length between the two gradually smooths out (Table 3). It should be added that in newborns the ascending part of the large intestines (caecum - colon transversum) is generally longer than the descending part (Debele, Natiev), and this ratio Table 3. Ratio of the length of the large and small intestines. Age Ratio 0-1 yr. . . . 1:5.6 1-3 yr. . . . 1:5.0 3-10 yr. . . . 1:4.6 10-15 yr. . . . 1:4.1 Adults . . 1:4.2 according to Debele's observations exists up to 4 years. The width of the lumen, in contrast to the length, increases evenly. - The majority of authors acknowledge that the dimensions of the intestine change under the influence of a number of factors. Among the latter, various pathological conditions of a general and local nature occupy a prominent place. Some of them reduce the dimensions of the intestine compared to normal ones of the same age (e.g., general exhaustion in tuberculosis, peritonitis), while others, on the contrary, increase them (e.g., ascites). Features in the structure of the intestinal tube in main outlines come down to the following. The folds of the mucous membrane of the small intestines in early childhood are less developed than in adults; their length and height are smaller. The same must be said regarding the size and number of villi. The muscular layer does not achieve full development. The mucous membrane, yielding only insignificantly to it in thickness, is rich in cellular elements in contrast to the weak development of the connective tissue framework, and has a relatively more developed network of blood vessels and wider lymphatic vessels than in adults (Bagirtsky). The intestinal glands are underdeveloped. This predominantly applies to Brunner's glands; but Lieberkühn's glands also display signs of incomplete development. The lymphoid apparatus does not have any significant differences, except for certain features in the structure of Peyer's patches; with age, the size of individual patches increases. The absolute number of follicles increases with age, but the relative number in early childhood is 3 times greater (per unit area) than in adults (Gundobin). - It is necessary to especially note some features in the structure and topography of the large intestine, especially the colon. The retarded growth of the large intestines in the embryonic period is reflected in young children by the fact that certain parts of this section of the intestine retain the embryonic type of structure. The aforesaid fully applies to the cecum, which usually has the shape of a cone, gradually tapering and passing into the vermiform appendix. This same circumstance explains why positional features are of predominant importance only in relation to the large intestines. These features are mainly caused by the nature of the relationships of the large intestines with the peritoneum, which are substantially different compared to adults. Significant displacement is typical for the cecum, upon which very significant variations in its position depend. The vermiform appendix is located intraperitoneally and as a rule hangs down into the lesser pelvis. The ascending colon very often (according to Natiev - 59.7%) in its initial section lies intraperitoneally, which explains the intestine's ability to shift. The position of the transverse colon depends mainly on the features in the size of the liver and stomach. Due to the incompleteness in the development of the hepatic flexure, the position of its right half is especially variable. Differences in the position of the descending colon are insignificant. The sigmoid colon is characterized by unusual positional variability, explained by the great length of the intestine and its high mesentery. The sigmoid colon is located above the entrance to the lesser pelvis along the midline or extends to the right side. Due to the underdevelopment of the lesser pelvis and the relatively large liver, the sigmoid colon forms a large number of flexures. - These most important anatomical and topographical features of the intestine in children explain its functional features and are a predisposing moment for the development of various pathological deviations. The underdevelopment of the glands, especially Brunner's glands, in connection with the rich network of blood vessels and relatively wide lymphatic vessels, and finally the insufficient development of the musculature - all this leads to the conclusion, which was drawn by Gundobin, that in early childhood the intestine is more adapted to absorption than to food digestion. The high absorptive capacity explains the easy vulnerability of the child's intestine. The weak development of the muscular layer with great mobility of the intestine causes the frequency of constipation in children. The underdevelopment of the sacrum and coccyx, insufficient fixation, and incomplete development of the muscular layer of the rectum must be linked to its frequently encountered prolapse in childhood. N. Anserov. Physiology of the intestine - see Digestion. P. Research methodology. Diagnostic methods for intestinal diseases should include physical research methods (inspection, palpation, and percussion of the abdomen - see Abdomen), examination using duodenal and intestinal probes, fluoroscopy, rectomanoscopy, urine examination; in addition, very important data are obtained by examining the feces (see). Functional diagnostics. A. Schmidt and Strasburger established and refined the methodology for examining intestinal excrements for the functional diagnostics of intestinal diseases. A standard diet was proposed by Schmidt; the nature of the feces under it does not depend on the contingencies of the food composition.
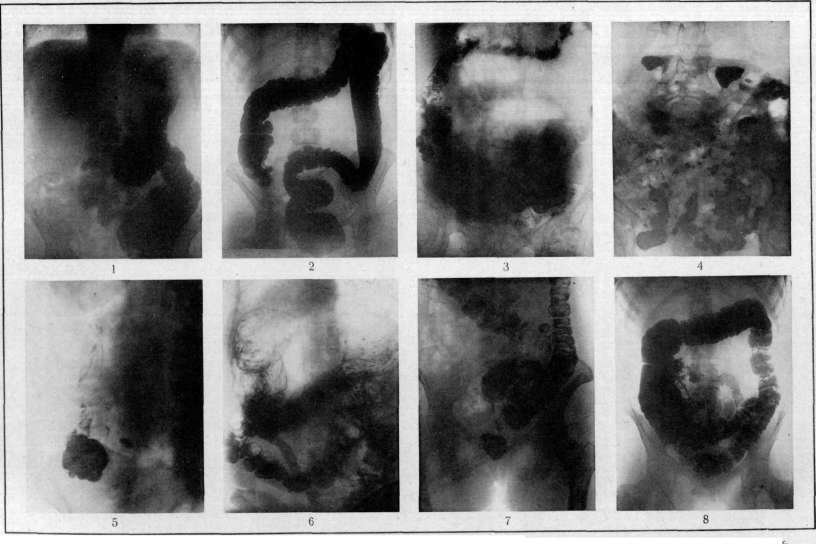
Investigation of intestinal excretions on this diet provides data characterizing the functional capacity of the intestine. This test diet is as follows: 1st breakfast - 0.5 l of milk and 50 g of rusks; 2nd breakfast - 0.5 l of mucous oatmeal soup (40 g of oatmeal, 10 g of butter, 200 g of milk, 300 g of water, 1 egg, and a little salt); lunch - 125 g of minced meat (raw weight), slightly fried with 20 g of butter, and 250 g of mashed potatoes (190 g of potatoes, 100 g of milk, 10 g of butter, and a little salt); at 5 o'clock - the same as the first breakfast; dinner - the same as the second breakfast. The diet is prescribed to the patient for 3 days, and the intestinal excretions obtained during this time are subjected to careful macroscopic, microscopic, bacteriological, and chemical examinations. To demarcate the feces to be examined from the preceding ones, carmine is given. Normally, on such a diet, macroscopically, only an insignificant amount of plant food residues is found in the excretions; upon microscopic examination, besides detritus, one finds isolated muscle fibers, individual crystals of fatty acids, residues of oatmeal soup and bread, isolated residues of potatoes; the reaction to litmus is weakly alkaline or weakly acidic; the fermentation test (see) either fails or proves very weak. At present, Schmidt's test diet is far from being used by everyone, since many believe that it has not justified the hopes placed in it; thus, it is often possible to state an increase in fermentation processes with a negative result of the fermentation test (acetic acid fermentation), without liquid stool and with an alkaline reaction of the feces to litmus. French authors suggest for investigating the function of the intestine to add 75 g of minced meat, raw or slightly fried, and potatoes to the usual food. At the Institute of Balneology in Moscow, the test diet consists of 200 g of minced and slightly fried meat, rice porridge, mashed potatoes, and grated carrots; for a special study of the functional capacity of the pancreas, 100 g of butter is added to this diet. For functional diagnostics, the consistency and shape of the feces, the color of the feces, pathological impurities, the degree of utilization of various food components, the nature of the bacterial flora (see Feces, Constipation, Diarrhea, Intestinal dyspepsia), and the amount of organic acids and ammonia are taken into account. The amount of organic acids and ammonia in the feces is determined by the method of Roux and Goiffon (G. Ch. Roux, Goiffon). In a tared porcelain mortar with a capacity of up to 70 cm3, 5 g of feces, taken from various places of the delivered portion, is weighed and rubbed with a pestle with 50 cm3 of distilled water, adding the latter gradually, in small portions. The obtained homogeneous mass of feces, after adding 2-3 drops of a 1% alcohol solution of phenolphthalein, is treated with a 30% solution of aluminum chloride and caustic potash is added in pinches until a pink coloration appears. After this, the mixture is allowed to stand for 5 minutes and then 25 cm3 of liquid is filtered off. The obtained 25 cm3 of filtrate is brought by the addition of n/10 HCl solution and n/10 soda solution to a weakly pinkish color, 5 cm3 of tropeolin 00 indicator is poured in (0.1 of tropeolin is dissolved in 300 cm3 of 96° alcohol in a 500 cm3 capacity flask and added with water to the mark), and poured into a test tube with a 60 cm3 mark. The solution is titrated with n/10 HCl solution to an orange color; then water is added to the mark and titrated again to the color of the previously prepared standard. The standard is prepared as follows: into a test tube with a 60 cm3 mark (of the same diameter and glass as the first one), 1.2 cm3 of n/10 HCl solution, 5 cm3 of tropeolin, and water to the mark are successively poured. The standard solution keeps for a long time. The calculation is made according to the formula: x = [(y - 1.2) · 100] : 25, where y is the number of cubic centimeters of n/10 HCl. The amount of organic acids in the feces is characterized normally by the figure 14-18. The amount of ammonia is 2-4. An increase in organic acids in the excretions is the result of strong fermentation in the intestine, while their decrease indicates that normal fermentation was delayed either by an intensification of putrefactive processes (a large amount of ammonia in the feces), or by accelerated evacuation, or else part of the organic acids was neutralized by the secretion of the intestine. Cases are often encountered where, along with a high content of organic acids and traces of ammonia, the reaction of the feces to litmus is alkaline, which depends on the influx of alkalis into the intestine from tissues: the acidic reaction of the intestinal contents sharply irritates the intestinal wall, which responds by the release of alkalis - a "protective" reaction of the intestine (Pevzner and Lindenbraten). With an intensification of putrefactive processes, the amount of ammonia in the feces increases with a normal or reduced content of organic acids. Finally, in mixed cases, the amount of both organic acids and ammonia may be elevated. The data of stool examination can, following the example of French authors, be divided into the following 4 groups characterizing the abnormal function of the digestive apparatus in general and the intestine in particular. 1. Insufficient secretion of digestive organs. Insufficient secretion of the stomach is characterized by the presence of connective tissue and undigested muscle fibers in the feces, and often also crystals of calcium oxalate; sometimes there are starch residues or particles of plant food; putrefactive processes prevail with strong irritation of the mucous membrane of the intestines, although in some cases there is also an intensification of fermentation processes. Insufficient function of the pancreas is characterized by: a) a large amount of feces, pasty or liquid, mostly gray in color (due to a large amount of fat), of a sharp odor, alkaline reaction; b) an abundant amount of neutral fat droplets; c) a positive Schmidt nuclear test; d) the presence of a large amount of starch and cellulose residues; e) a positive reaction for hydrobilirubin. Insufficient bile excretion into the intestine yields solid or liquid light gray excreta (absence of hydrobilirubin), of an acidic reaction; all food substances are well digested, except fats, which are excreted in the form of fatty acid crystals; the reaction for hydrobilirubin is negative. Insufficient digestion and absorption of milk sugar in the small intestines is characterized by foamy and acidic excreta. 2. Disturbance of the balance of the intestinal flora. In the intestine, there are two groups of bacteria participating in the processes of food digestion: the anaerobic flora, favoring putrefactive processes, and the aerobic flora, saccharolytic, promoting the development of fermentation processes. Depending on the prevalence of one or the other group, either a fermentative stool or a putrefactive one is obtained (see Dyspepsia). When a large number of Entamoeba coli, Balantidium, and other parasites are encountered in the feces, putrefactive processes may depend on them. In some cases, both the amount of organic acids and the amount of ammonia are increased in the feces; the reaction of the feces to litmus is amphoteric (so-called mixed forms). 3. Disturbance of intestinal evacuation. With accelerated evacuation, the fecal masses are more or less liquid and contain a large amount of poorly digested food residues and iodophilic bacteria. The excreta have an admixture of slightly changed contents of the small intestines, are semi-liquid, golden-yellow in color (due to the bilirubin content), with a very sharp odor; the reaction is alkaline; muscle fibers are poorly digested; there are many fatty acids and neutral fat, much starch and plant fiber; traces of organic acids and ammonia are present. Excreta with an admixture of slightly changed contents of the cecum are of pasty consistency, yellowish in color, with an oily odor; muscle fibers and fats are well digested; there is much plant fiber and starch, as well as iodophilic bacteria; bile pigments are in the form of stercobilin; organic acids are contained in a normal amount, ammonia - in an insignificant amount; the reaction is neutral or weakly acidic. With delayed evacuation (constipation), the fecal masses are dense, dark in color, contain no food residues or iodophilic bacteria; the ammonia content is increased, while organic acids are decreased; the reaction is neutral or alkaline. 4. Enterocolitis, the main characteristic signs of which are an increased water content in the feces, the presence of albumins (from the secretion of the affected intestines), mucus, and an intensification of putrefactive processes. If there are ulcers in the intestine, the feces, besides mucus, usually (not always) contain blood and a large number of leukocytes (pus); in the case of retention of fecal masses above the ulceration point, only pathological products are excreted - pus, mucus, blood, while fecal masses are absent. Symptoms of a disturbance in the proper function of the large intestines can be various in Figure 1. Normal picture of the filling of the stomach and loops of the small intestines 30 minutes after taking a contrast meal according to Rieder. Figure 2. Normal picture of the large intestines after a contrast enema: the mass has filled the ampulla recti, flexura sigmoidea, colon descendens, colon transversum, and colon ascendens. Haustra are well expressed in the upper section of the flexura sigmoidea, colon transversum, and colon ascendens.
Flexura lienalis stands much higher than flexura hepatica. Figure 3. In the region of the small intestines, accumulations of fluid with a horizontal level are visible. Above them, accumulations of gases are visible in the form of a very light shadow (a case of stenosis of the small intestines, confirmed operatively). Figure 4. Multiple diverticula: irregular semicircular accumulations of the contrast mass with gas bubbles beneath them are visible (a case confirmed by surgery). Figure 5. Colica mucosa: in the colon ascendens throughout its extent, there are small punctate accumulations of the contrast mass. Figure 6. Megasigma: the flexura sigmoidea is elongated and dilated. Interposition of the colon: the colon transversum is distended with gases and is located above the dropped liver and beneath the right dome of the diaphragm (a case confirmed by surgery). Figure 7. Carcinoma recti: a filling defect over the course of several centimeters in the region of the ampulla recti (a case confirmed by rectoscopy and microscopic examination). Figure 8. Polyposis recti et flexurae sigmoideae: in the region of the rectum, flexura sigmoidea, and colon descendens, roundish filling defects the size of a small pea are visible (a case confirmed by rectoscopy). (To the illustr. of the article Intestine).
depending on the localization of the inflammatory process: a) in lesions of the cecum and ascending colon, the stool is usually liquid, fermentative, with an admixture of slightly altered contents of the cecum; b) in lesions of the left part of the large intestines (including the colon sigmoideum and rectum), inadequate evacuation is more frequent with the discharge of non-homogeneous feces (see above): quite often so-called false diarrheas are present; for the diagnosis of this affliction, besides fluoroscopy, the following method can serve: the patient is given 0.5 of carmine or charcoal on an empty stomach half an hour before a meal, and then the first appearance of colored stool is noted; in cases of delayed evacuator capacity of the stomach (motor insufficiency), carmine is introduced through a duodenal tube into the duodenum. The appearance of carmine later than 24 hours indicates a retention of fecal masses. This method does not yield precise results.
M. Pevzner and L. Berlin. X-ray diagnostics. Methodology and normal picture. An unprepared intestine does not differ upon fluoroscopy and on the radiograph from the surrounding parts. Only an accumulation of gases in its lumen, the presence of foreign bodies in it, and fecal masses sometimes give clear images. For a systematic study of the intestine, it is necessary to fill it with a contrast agent that strongly absorbs rays. After taking contrast food per os (see Stomach, X-ray examination), partial filling of the loops of the jejunum can be observed already after 15 minutes. Here the food slurry does not linger for long; its distribution in a thin layer over the mucous surface promotes rapid digestion and absorption. Correspondingly, a thin feathery pattern of the jejunal loops is obtained, on which gentle Kerkring folds with a rather variable contouring (see separate table, Fig. 1) are visible under the influence of contractions of the muscularis mucosae (Forssell). Half an hour after ingestion, dense shadows of filled ileal loops are already visible, and in 3-4 hours the jejunum usually no longer contains the contrast agent, which has accumulated entirely in the ileum. The latter has the appearance of irregularly located, densely filled loops in the lower half of the abdomen. 5-7 hours after ingestion, filling of the cecum and ascending colon up to the hepatic flexure is visible. During the same time interval, it is sometimes possible to obtain an image of the vermiform appendix. The latter is facilitated by careful clearing of the intestine from fecal masses before taking the contrast agent and palpation of the ileocecal region during fluoroscopy. Under normal conditions, both the cecum and the vermiform appendix are easily displaced by the palpating hand. A distinctive feature of the X-ray image of the large intestine is the haustra; their outlines change under the influence of so-called minor movements of the colon. In its initial part, fecal masses linger the longest: after 24 hours, filling of the transverse colon is still visible; after a further 5-6 hours, filling of the descending colon, sigmoid flexure, and rectum. After 30-40 hours, the entire colon is empty. Holzknecht observed under normal conditions very rapid movements of large fecal masses towards the anus. In the ascending colon and the initial part of the transverse colon, antiperistaltic movements also occur under normal conditions. The cecum is usually located at the level of the femoral head, the hepatic flexure under the lower edge of the liver, the splenic flexure considerably higher, often under the left dome of the diaphragm. The very mobile transverse colon runs sometimes in an almost straight line, more often it sags downwards; its upper contour usually abuts the greater curvature of the stomach; both in general ptosis and in limited coloptosis, it can descend to the symphysis. The position of this part of the intestine is very inconstant: it changes even in the same person depending on the tone of the abdominal press, the standing of the diaphragm, etc. In general, a more rectilinear course is observed more frequently with a hypersthenic constitution; a garland sagging downwards, with an asthenic one. The descending colon descends in a straight line downwards, the sigmoid flexure represents a series of variants from a slight bend to the formation of a large loop extending to the right and upwards. The lumen of the colon gradually decreases from the cecum to the rectum; the rectal ampulla appears as a clear expansion. The advantage of the described method lies in its proximity to physiological conditions. For studying the anatomy of the large intestine in the living, filling per rectum (see separate table, Fig. 2)—the so-called contrast enema—deserves preference; its approximate composition: a) barium sulfate 150.0, hot water 500.0; b) wheat starch decoction 30.0:1000.0, mix a and b while hot, let cool to 37-40°. The patient is placed on a trochoscope and the gradual filling of the colon and its evacuation are monitored on a luminous screen (Haenisch). It is preliminarily necessary to thoroughly clean the intestine with a laxative and an enema. Fischer recommends inflating the colon after partial removal of the enema with the contrast agent; this gives very clear pictures with an image of the mucosal folds. Knothe first introduces a contrast enema and lets it drain off, so that a small sediment of the contrast agent remains on the wall, by which the mucosa can be studied. With simple inflation of the large intestine, clear images of its outlines are obtained. To study the small intestine, one can also use a thin duodenal tube through which a liquid contrast agent, e.g., potassium iodide solution, is poured. Pathological picture. Small intestine. (X-ray picture in diseases of the duodenum—see Duodenum.) In fermentative dyspepsia (Lampe) and in some cachectic states, the motor function of the jejunum is sharply disturbed; its loops give dense shadows with gas bubbles and horizontal levels after taking the contrast agent. The same gas bubbles and horizontal levels can be caused by atonia and stasis before an organic stenosis (see separate table, Fig. 3). Since they can be detected even without taking a contrast agent, they serve as a good diagnostic sign in acute obstruction. Individual densely filled loops, discovered at a time when the jejunum should already be empty, argue for stenosis and are one of its earliest clinical symptoms. Individual irregularly semicircular constant contrast spots with gas bubbles were noted in diverticula (see separate table, Fig. 4). A limited protrusion near the gastrocolic anastomosis speaks for peptic jejunal ulcer. Prolonged retention in the lower loops of the ileum is often observed in the presence of peritoneal adhesions after past pelvic peritonitis, in organic diseases of the cecum, in insufficiency of the ileocecal valve. For the latter phenomenon, according to some authors, the visible filling of ileal loops when using a contrast enema is decisive. Ascariasis can have the appearance of light stripes in the filled intestinal loop; sometimes an image of the intestine of the parasite containing the contrast agent is also obtained. Large intestine. An increase in colon tone leads to a narrowing of its lumen; the haustra give a bead-like fine pattern; sometimes with pronounced spasm they are not visible at all, and the filled colon appears as a thin strip. Such pictures are also obtained with irritation of the vagus nerves and under the influence of pilocarpine and physostigmine. A wide lumen without pronounced segmentation of the haustra is characteristic of atonia; irritation of the sympathetic nerves, the use of atropine leads to a similar change in motor function. In some cases of constipation, prolonged retention is observed in the ascending colon, in others in the transverse colon or in the sigmoid flexure and rectal ampulla. Often a combination of cecal atonia with spasm in the descending colon is visible. With mucous colic, one can see in the lumen of the intestine light stripes of mucus with clusters of the contrast agent adhering to them and compact lumps of contrast stool (see separate table, Fig. 5). Flatulence gives fairly striking pictures of gas accumulation; the inflated splenic flexure of the colon, propping up the diaphragm, is important for the so-called gastrocardiac symptom complex; an inflated loop of the colon under the right dome of the diaphragm above the liver (interposition of the colon) for the diagnosis of liver displacement (see separate table, Fig. 6). Inflammatory diseases of the colon are characterized by spastic narrowing of the lumen and irregularly mottled contrast shadows in connection with the accumulation of mucus and anatomical lesions of the mucosa. An irregular fine-toothed contouring is typical for tuberculosis. In tuberculosis of the cecum, retention in the ileal loops, the absence of a contrast mixture in the cecum, and distinct filling of the transverse colon (Stierlin's sign) are often noted. In general, in tumors (see below), both inflammatory and new growths, the absence of contrast contents at the site of the lesion with normal filling of neighboring parts is noted. In other cases, irregularly contoured filling defects, images of narrow channels with eroded edges are obtained (see separate table, Fig. 7). These signs belong to the early ones, when there are still no indications of obstruction; but they are decisive only under the condition of great constancy and especially under the condition of preliminary thorough cleansing of the intestine, since the simultaneous presence of contrast and non-contrast stool in the intestine can also give a picture of a defect with irregular edges. Distinct pictures of polyposis are obtained after the removal of the contrast enema, when traces of barium salt have settled between individual polyps and give a characteristic filigree pattern (see separate table, Fig. 8). In acute obstruction, one can see, even without a contrast agent, a strongly inflated section of the colon with a horizontal fluid level and dark bands—haustra. The elongated and gas-inflated sigmoid flexure is depicted particularly clearly during its volvulus, as well as with congenital megasigma without phenomena of obstruction. In cases of invagination, one can use a contrast enema to obtain an image of the section of the intestine invaginating into the lumen of another, in the form of a light strip bordered by dark edges.
For the diagnosis of chronic appendicitis, uneven filling of the vermiform appendix, club-like dilation of its lumen, and prolonged retention of the contrast medium in it, even after emptying of the cecum, are of importance. A sign of adhesions is the impairment of the displaceability of the intestinal section upon palpation and the strict coincidence of the site of greatest tenderness upon palpation with the image of the affected part of the intestine. Abnormal position of the intestine under the influence of abdominal tumors, in eventrations and hernias, and pathological fixation by adhesions are also well determined by X-rays and may be of importance for the diagnosis of the underlying disease. - The X-ray picture in diseases of rectum - see Rectum.
III. Pathological anatomy. Malformations of the intestine may manifest as underdevelopment of the entire intestine as a whole or its individual parts, irregularities of the intestinal lumen, persistence of embryonic structures, or finally, abnormal positioning of the intestine. Malformations of the first type include rare cases of complete absence of the intestine, which is observed only in acardius-type monsters (see), or underdevelopment of a particular section of the intestine, for example, part of the ileum together with part of the large intestine, with the free ends of the developed sections of the intestine terminating blindly. Cases of a too short or too long large intestine may also be observed. In the latter case, we speak of dolichocolia, and there are observations that such dolichocolia may be hereditary, as well as a racial feature, largely determined in turn by dietary conditions; thus, the so-called "long Russian intestine" is attributed to this, developing, according to Hansemann and others, on the basis of a predominant diet of coarse and abundant vegetarian food. The question of dolichocolia has practical significance in terms of predisposition to intestinal volvulus; on the other hand, there are indications that transitions exist between dolichocolia and megacolon (or megasigma) and the so-called Hirschsprung's disease; Uspensky speaks of latent forms of Hirschsprung's disease. Congenital irregularities of the intestinal lumen are most often expressed in local narrowing, stenosis, or complete closure, i.e., atresia (see) of the intestinal lumen. Congenital stenoses and atresias can be observed in various parts of the intestine and are sometimes multiple. They are most commonly found in the duodenum, where stenosis or atresia usually occurs in the region of the ampulla of Vater, further at the site of transition of the ileum into the cecum (atresia ileo-caecalis), in various parts of the large intestine, and finally, most often in the rectum. With the exception of atresias of the rectum, which are the result of maldevelopment of the cloaca, stenoses and atresias of the intestine can be the result of pathological processes that occurred during intrauterine life (peritonitis, enteritis), but more often they represent developmental anomalies of the intestine in the sense of delayed lumen formation after the phase of epithelial closure of the latter (during a certain period of embryonic life, the intestinal lumen is filled with proliferated epithelium). In cases of atresia and severe stenosis, the overlying section of the intestine is dilated to a greater or lesser extent. Independent congenital dilatation of the intestine is observed almost exclusively in the large intestine and belongs to the so-called Hirschsprung's disease (see). Limited congenital dilatations or protrusions of the lumen are designated as congenital diverticula (see) and most commonly belong to false diverticula, representing hernia-like protrusions of the mucosal and submucosal layers through congenital defects in the muscular layer. - Embryonic structures persisting in the intestine include Meckel's diverticulum; related malformations include accessory pancreases in the intestinal wall, as well as congenital tumor-like formations of the myoma and adenoma type (see below - tumors of the intestine). - Congenital positional abnormalities may involve the entire intestine, as occurs in situs viscerum inversus, or only a part of it, which most commonly occurs in relation to the cecum, which may be located too high or, being provided with a mesentery, turns out to be mobile (caecum mobile). Sometimes the entire large intestine has a mesentery common with the mesentery of the small intestine (mesenterium commune) and is mobile. It is rare for the ascending colon to be located on the left side next to the descending colon. Duplication of certain sections of the small or large intestine belongs to very rare malformations. - Congenital hernias, see Hernias. Atrophy of the intestinal wall was previously considered a very frequent change. Nothnagel and others found atrophy of the intestinal wall in 80% of all cadavers. Subsequently, however, this Nothnagelian doctrine of intestinal atrophy was strongly shaken by observations proving that the pictures that were considered a manifestation of atrophy of the intestinal wall are in most cases the result of cadaveric changes. They are based on the distension of the intestine by gases and maceration of the superficial layers of the mucous membrane; even in cases where the autopsy is performed immediately after the death of the subject, the intestinal distension that occurred during the patient's life can already produce such a condition of the intestine that simulates atrophy at autopsy. In connection with the above, when judging atrophic changes in the intestinal wall on a cadaver, one must be very cautious; the presence of atrophy can be established only in cases where there was no intestinal distension and the autopsy is performed shortly after death or after the immediate introduction of 20% formalin into the abdominal cavity after death. Studies performed with the indicated precautions reveal that atrophy of the intestinal wall is rarely observed; it is encountered sometimes either as a partial manifestation of general atrophy, e.g., in starvation, various cachexias, or as a result of prolonged intestinal inflammations, e.g., in children as a result of chronic or frequently recurring catarrhs. In these cases, the entire wall of the intestine appears thinner and paler, and the mucous membrane is smoothed out, in the small intestine lacking its velvety appearance. In the small intestine, spread out in water, a magnifying glass can be used to note a decrease in the number and height of the villi. Under the microscope, the mucous membrane appears lower, the number of Lieberkühn's glands is reduced, they are shortened; the amount of interstitial tissue between the glands is increased; the submucosal layer is usually somewhat thinner and denser. The muscular layer often does not show special changes, sometimes it is also atrophied; sometimes muscle cells contain brown pigment. In individuals suffering from chronic constipation, Rost as a rule found atrophy of the muscular layer in the transverse and descending colons. Sometimes in the descending colon in the region of the haustra, atrophy of the muscular layer is observed in limited areas with the formation of true diverticula (often multiple) filled with feces (fecal diverticula). These true diverticula of the large intestine, in the formation of which all layers of the intestinal wall participate, must be distinguished from the more frequent false diverticula, which are based on the separation of muscle bundles and the protrusion of only the mucous membrane with the submucosal layer (in the small intestine usually at the site of attachment of the mesentery, in the large intestine at the sites of entry of blood vessels). Degenerative changes. Among degenerative changes of the intestine, amyloidosis is of the greatest importance. Amyloidosis of the intestine in the vast majority of cases is a partial expression of general amyloidosis; isolated amyloidosis of the intestine is a great rarity (Askanazy's case). Deposition of amyloid can occur throughout the entire length of the intestine. However, in the ileum, it is most pronounced and begins earlier than in other parts of the intestines. Pathologo-anatomically with the unaided eye, amyloidosis of the intestine can be determined only at a relatively high degree of it; a weak degree is not accompanied by any special changes in the appearance of the intestine. A more significant deposition of amyloid is manifested by pallor of the intestinal wall and a peculiar lardaceous appearance of the surface of the mucous membrane; at a very high degree of amyloidosis, thickening of the wall and its density are noted. As a sign observed in 70% of cases, Lubarsch points to "hemosiderin pigmentation" in the form of gray and grayish-black spots on the mucous membrane. At a significant degree of amyloidosis, a reaction with iodine and sulfuric acid can be obtained on the mucous membrane. Histologically, homogeneous lumpy masses of amyloid are found, mainly in the walls of blood vessels of the submucosal layer and the reticular framework of the mucous membrane; at a significant degree of amyloidosis, deposition is also present in the lamina propria of Lieberkühn's glands, as well as in the form of lumps and strands between the bundles of the muscular layer, which may atrophy in the process. Lymphoid follicles of the intestinal wall as a rule do not participate in amyloidosis; only Hayem in amyloidosis in children observed selective deposition of amyloid in the intestinal follicles. Very much often amyloidosis of the intestine is complicated by ulcerative processes; such "amyloid ulcers" arise apparently as a result of narrowing of the lumens of blood vessels affected by amyloid and anemization of the mucous membrane; a feature of them is a lardaceous base giving a reaction with iodine and sulfuric acid. Of other changes of the degenerative type encountered in the intestine, degenerative fatty degeneration of the elements of the intestinal wall and its pigmentation deserve mention. Judgments about pathological fatty degeneration of the epithelial cells of the intestine must be very cautious, since these cells contain fat physiologically during the process of absorption. However, in the large intestine, in connection with inflammatory changes, the epithelium of the glands may undergo degenerative fatty degeneration.
In consumptive patients, heavy drinkers, depleted old people, as well as in prolonged inflammatory changes in the abdominal cavity, degenerative fatty infiltration of the cells of the muscular layer of the intestine is observed, as well as sometimes of the ganglion cells of the nerve plexuses of the intestinal wall. Among pigmentations in the intestine, the deposition of hemosiderin (see) is frequently encountered; the latter, under the influence of sulfur compounds present in the intestinal contents, appears as an ashen-gray and black color, which disappears upon the addition of an HCl solution, a condition designated as pseudomelanosis. Lubarsch distinguishes three forms of this pseudomelanosis: villous, nodular, and irregularly spotted. The first involves the tips of the villi and is expressed as a continuous fine-dotted stippling of the small intestine; the second pertains to the pigmentation of the lymph follicles (solitary and in Peyer's patches); the third irregularly affects certain regions of the mucosa. Pseudomelanosis is the consequence of past small hemorrhages and diapedesis of erythrocytes; in the villi, it can be the result of the absorption of blood present in the intestinal lumen. True melanosis (melanosis coli), also called ochronosis, is expressed by the appearance in the wall of the large intestine (in the reticular framework of the mucous membrane and in the submucosal layer) of a brownish-black pigment which, in contrast to hemosiderin, contains no iron and is not dissolved by an HCl solution [see separate table (p. 583-584), Fig. 6]. The chemical nature of this pigment has not yet been established; it is suggested (Pick) that it originates from aromatic protein decomposition products (indole, skatole) absorbed by the mucous membrane of the large intestine and converted into pigment within the mucosa itself by means of the enzyme tyrosinase. Besides these pigmentations, the deposition of wear-and-tear pigment, lipofuscin, takes place in the intestine; in a small amount, this is observed in atrophic processes of the intestine, and to an especially marked degree in a disease called hemochromatosis (see); in the latter case, the pigmentation affects the small intestine and to a much lesser degree the large intestine, with lipofuscin being deposited in the cells of the muscular layer, in the ganglion cells of the nerve plexuses, and partly in the cells of connective tissue. The color of the corresponding sections of the intestine takes on a brown hue. Syphilitic changes of the intestine can occur in both congenital and acquired syphilis. In congenital syphilis of newborns, involvement of the intestine is observed in 5–8% of cases, with the ileum being the most frequent site of the lesion. The change consists in the formation of miliary gummas in the intestinal wall, as well as in the development of gummatous infiltrates (see Gumma), sometimes more circumscribed, sometimes more diffuse, frequently encircling the intestinal wall; in cases of the latter type, multiple, usually circular thickenings of the intestinal wall of a gray-pink, lardaceous appearance, raising the mucous membrane, are visible to the naked eye. Sometimes they narrow the intestinal lumen and frequently ulcerate. On the serous covering of the intestine, sometimes corresponding to the affected areas, there is a delicate fibrinous coating containing spirochetes. In acquired syphilis in adults, clinicians sometimes note acute catarrhal enteritis in the papular period of syphilis. However, anatomical-pathological changes in the intestine in acquired syphilis appear at a later period and are generally observed rarely. The localization of these changes is most frequently encountered in the large intestine, most often in the rectum. Involvement of the small intestine by syphilis in adults is a great rarity, and in most of the described cases, it is a matter of changes in the upper section of the small intestine, i.e., the jejunum. The basis of intestinal changes in acquired syphilis is the development in the submucosal layer of gummatous infiltrates accompanied by changes in the blood vessels characteristic of syphilis; these infiltrates raise the mucous membrane in the form of nodules or encircling ridges; their ulceration leads to the formation of ulcers, frequently multiple, usually shallow, with dense, ridge-like edges and a dense, lardaceous base. Sometimes these ulcers are sources of hemorrhage, and rarely they undergo perforation. The scarring of infiltrates or ulcers as a rule leads to strictures of the intestine; such strictures in the small intestine are sometimes multiple and entail phenomena of prolonged, progressive obstruction. Syphilitic involvement of the large intestine is accompanied by a strong development of dense connective tissue in the surrounding parts, which is especially characteristic of syphilitic involvement of the rectum; here, gummatous infiltrates develop not only within the intestinal wall, but also in the surrounding cellular tissue; subsequent ulcerations and scarring produce the characteristic syphilitic ulcerating and stenosing proctitis (see) and periproctitis. Actinomycosis of the intestine—see Actinomycosis. Lymphogranulomatosis of the intestine—see Lymphogranulomatosis. Anthrax of the intestine—see Anthrax. Changes in the intestine in leukemia—see Leukemia. Intestinal calculi, syn. enteroliths (enterolithon), are dense (frequently of stony density) formations encountered in the intestinal lumen. They are observed most often in the large intestine, e.g., in the cecum, in its vermiform appendix, in the haustra of the large intestine; much less frequently they are encountered in the small intestine (e.g., in the presence of a diverticulum in it). By their nature, intestinal calculi are not always identical. Sometimes a calculus is nothing other than a lump of compacted fecal masses; these calculi are light, break apart without difficulty, have a uniformly granular, less often faintly layered appearance on the fracture, and are dark brown in color. These calculi are called fecal calculi, coproliths (koprolithon, scybala). Other calculi are heavy, very dense, and break apart with difficulty; on the fracture, distinct layering is visible in the form of an alternation of brownish-gray and dark-brown layers; in the center, such a calculus reveals a foreign body in the form of hairs, a food residue, a group of epithelial cells, a lump of mucus, a gallstone, etc., and the layers consist of fecal elements with calcium and magnesium salts. Calculi of the above two types are usually sized from a pea to a chicken egg, rarely of larger dimensions, and are of a rounded or oval shape. Finally, small calculi can form in the intestine from a medicinal substance used over a long period, e.g., from salol, from magnesia; in carpenters and polishers, as a result of the chronic introduction of varnish and polish into the digestive tract, peculiar, sometimes very large concretions of shellac can form in the stomach and intestines. In addition, gallstones that have penetrated here through the bile duct or through an established fistula, and urinary calculi upon the adhesion of the intestine to the urinary tract and the formation of a corresponding fistula, can be found in the intestine. Calculi in the intestine can cause inflammatory changes of the mucous membrane or even necrosis and pressure sores in the intestinal wall, resulting in ulceration and sometimes perforation of the wall. Sometimes a calculus or a group of calculi can become incarcerated in the intestine and cause its obstruction; in particular, calculi forming in the lumen of the vermiform appendix, by narrowing the lumen, cause stagnation of contents in it and thereby contribute to the occurrence of appendicitis (see).
A. Abrikosov. IV. Neoplasms of the Intestine. Pathological anatomy. Intestinal tumors are extremely diverse due to the fact that they can originate from a wide variety of tissues making up the intestinal wall. Among benign connective tissue tumors, fibromas and lipomas are found in the intestine. Fibromas are very rare, and some of the described cases are not entirely distinct from inflammatory proliferations of connective tissue (e.g., fibromas of the vermiform appendix, Meckel's diverticulum); there are authors (Gosset) who generally doubt the existence of intestinal fibromas, considering the majority of described cases to pertain to neurofibromas. Lipomas are fairly common intestinal tumors, most frequently observed in the large intestine, where they may either protrude into the lumen of the intestine, lifting the mucous membrane in the form of a nodule or a polyp on a stalk (internal lipomas), or protrude outward either as a round nodule or as a hanging polyp (external lipomas). Lipomas of the latter kind, often originating from appendices epiploicae, can reach enormous sizes (intestinal lipomas weighing over 6,000 g have been described); furthermore, they are frequently multiple. It should be kept in mind that intestinal lipomas, as is generally characteristic of fatty tumors, do not decrease in volume during general emaciation. Tumors from smooth muscle tissue, myomas and myofibromas of the intestine, are not particularly rare; they are usually discovered in the duodenum and small intestine, more often in persons of older age, and may either protrude into the intestinal lumen or bulge outward (internal and external myomas). Most often they do not exceed the size of a hazelnut: myomas weighing over 1,000 g are very great rarities. Sometimes myomas are multiple. Myomas are characterized by softening and necrosis of the tissue followed by petrification; the surface of internal myomas may ulcerate. Internal myomas (which, incidentally, is also observed in relation to other submucosal tumors, e.g., fibromas, neuromas, angiomas) sometimes draw the intestinal wall inward into the lumen, which causes invagination; external myomas can pull the intestinal wall outward and give rise to diverticula. Sometimes a myoma acquires a malignant course (myoma sarcomatodes). Often myomas are difficult to differentiate microscopically from neuromas (see below). It is generally thought that intestinal myomas belong to hamartomas (see). True tumors from blood vessels of the cavernous or capillary angioma type in the intestine are very rare. Limited telangiectasias of the varicose vein type are observed here much more frequently. They are often multiple, spreading throughout the small intestine in the form of dark red nodules of various sizes slightly raising the mucous membrane. Sometimes there are simultaneously the same telangiectasias of the skin and internal organs. The fact that these formations are not tumors, but vascular expansions, was established by Müller (P. Müller) by means of the reconstruction method. Likewise, focal expansions can form from the lacteal vessels of the intestine, protruding on the mucous membrane in the form of whitish fine-villous spots; it is more correct to call them chylangiectasias rather than chylangiomas. True lymphangiomas restricted to the intestinal wall are extremely rare; in most cases, these are lymphangiomas of the mesentery secondarily involving the intestinal tract. Tumors from nerve tissue, as shown by the work of recent years, are not so rare in the intestine; apparently in former times they were incorrectly diagnosed and otherwise designated (e.g., as fibromas, myomas). Of these tumors, neurofibromas are most frequently found in the intestinal wall, having the appearance of small (from the size of a pinhead to a hazelnut) dense nodules; they are most commonly found in the duodenum and small intestine; in rare cases they are multiple (in Gubermann's case, 250 specimens). Sometimes such intestinal neurofibromatosis appears as if part of a generalized neurofibromatosis. Tumors of the neurinoma type and ganglioneuromas containing ganglion cells are less common. A separate category must be made of those neuromas which represent intertwining bundles of nerve fibers and occur with sclerotic changes in the vermiform appendix (similar neuromas are sometimes observed in the sclerotic base of a round ulcer of the stomach, in adhesions after cholecystectomy, etc.); these formations are apparently analogous to amputation neuromas and do not belong to true tumors. The indicated neuromas of the vermiform appendix develop (according to Masson) from the argentaffin cells of Kulchitsky. Malignant tumors from immature connective tissue, sarcomas, are not uncommon in the intestine; intestinal sarcomas account for about 3% of all malignant tumors of the intestines, and in general, intestinal sarcomas account for 1-2% of all sarcomas of the human body. Sarcoma more frequently affects the small intestine. The most frequent histological forms are round-cell sarcoma and lymphosarcoma, and in many cases, when the tumor does not show an obvious relation to the lymphatic apparatus of the intestine, it is not possible to say precisely whether a round-cell sarcoma or a lymphosarcoma is present (Oberndorfer). Rarer forms are spindle-cell, polymorphocellular, alveolar sarcoma, as well as angiosarcoma. By their external appearance, intestinal sarcomas can be divided (Stammbler) into nodular and diffuse; the former are sessile with protrusion inward or outward from the intestine or polypoid, while the latter take the form of a localized thickening of the intestinal wall or diffuse sarcomatosis; in the latter case, the entire intestinal wall over a considerable extent appears thickened due to infiltration by tumor elements, or the tumor forms a series of flat, poorly demarcated nodules slightly raising the mucous membrane. It is precisely to such forms that the intestinal manifestation of the so-called Kundrat's lymphosarcomatosis belongs, when, with a lymphosarcomatous lesion of the lymphatic apparatus of the entire body, there is a lymphosarcomatous proliferation of the follicles and Peyer's patches in the intestine, which turn into large, slightly protruding pale pink succulent plaques. Primary melanoma of the intestine can occur only in the region of the anus; multiple metastases of melanoma, appearing as brownish-black nodules, are very common in the intestine. The most frequent tumors of the intestine are epithelial neoplasms. Benign growths of this kind include polyps and polypoid adenomas of the intestine; although both formations are essentially different (a polyp is based on hypertrophy and sometimes simply a sagging of the mucous membrane, while an adenoma is based on a neoplastic proliferation of the glandular epithelium), practically it is very difficult to distinguish them from each other. Polyps and polypoid adenomas occur at any age, but more often in individuals under 30 years of age. Their main site of development is the large intestine, where they are single or multiple; rarely do they reach a size larger than a hazelnut. In some cases, with the formation of a huge number of polyps, one can speak of polyposis diffusa [see separate plate (pp. 255-256), Fig. 7]. Many polyps of the intestinal mucosa have an undoubted connection with its chronic inflammation, others develop completely independently and sometimes apparently have a congenital origin. True nodular (non-polypoid) adenomas of the intestine are rare: these include the described cases of adenomas of Brunner's glands of the duodenum. Carcinoids (see) belong to the peculiar tumors of the intestine of a benign type. Tumor-like heterotopias (displacements) and other nodular developmental defects of the intestine must be distinguished from true epithelial tumors. Thus, due to the abnormal proliferation of the epithelium of the serous coat of the intestine, nodules with the structure of endometrioids or adenomyosis can form. From the mucous membrane, there are heterotopic proliferations of its epithelium plunging deep into the intestinal wall (so-called enteromas and enterocystomas); close to them are glandular proliferations among abnormally located bundles of smooth muscle fibers, encountered in the form of nodules, often multiple, in the small intestine (so-called adenomyomas or epitheliomyoses of the intestine). Finally, single or multiple accessory pancreatic glands with ducts opening into the intestinal lumen may be found in the wall of the small intestine. Malignant epithelial tumors, carcinomas, are frequently encountered in the intestine. According to old statistics by Nothnagel, intestinal cancers account for 10% of all cancers; according to newer data: Lubarsch—16.4%, Oberndorfer—20%. According to summarized data from Moscow prosectoriums for 1923–1927, out of 2,765 cancers, 147 (5.3%) were intestinal cancers, of which about 16.9% fell on cancer of the small intestines, 51.9% on the large intestines (excluding the rectum), 28.8% on the rectum, and 2.4% on the appendix. In terms of the frequency of cancer involvement in various sections of the intestine, the rectum is by far in first place, followed in descending order by: caecum, colon sigmoideum, duodenum (Vater's papilla), colon transversum with its splenic and hepatic flexures; cancers of the small intestine are the rarest. Cancers of the vermiform appendix are very rare.
According to their external properties, cancers of the intestine are: 1) polypoid and fungous, forming a node projecting into the lumen of the intestine on a stalk or on a wide base, usually with rapid decay and ulceration of its surface; 2) diffuse, manifesting as a thickening of the intestinal wall in a limited space, frequently circularly embracing the bowel; in these cases, the mucous membrane may remain intact and only edematous and raised in the form of a series of flat elevations; subsequently, ulceration occurs along with the formation of a crater-like ulcer with raised massive edges. In consistency, intestinal cancers can be soft (medullary) and dense (scirrhous); mucous and colloid cancers are not uncommon, especially in the large intestine. The most frequent histological forms of intestinal cancer are malignant adenoma and adenocarcinoma, as well as mucous cancer; solid cancer is rarer. Squamous cell carcinoma is sometimes observed in the rectum (from the epithelium of the anus) and very rarely in the cecum (as a heterotopic cancer). Not infrequently, primary multiple cancers are observed in the intestine (from multiple polyps or from scarring tuberculous ulcers). Cancers cause strictures of the lumen of the intestine, and as they grow, they spread to neighboring organs; upon destruction of the intestinal wall, they can cause perforation. Metastasis in intestinal cancers occurs mainly along the serous cover of the abdominal cavity and sometimes (e.g., in colloid cancers) achieves enormous dissemination. Further, metastases form in the retroperitoneal lymph glands and in the liver; sometimes widespread dissemination to various organs can be observed. Metastases of malignant tumors of other organs to the intestine are uncommon. A. Abrikosov. Clinic. Benign tumors. Among the various types of benign tumors of the intestine, adenomas in the form of polyps are of the greatest practical importance. The symptoms of this affliction vary in character and intensity. They are expressed in more or less abundant hemorrhages, discharges of pus, mucus, diarrhea, pain during defecation (especially sharp when strangulated), and tenesmus. The latter occur when polyps are located in the rectum. Frequently, polyps cause a narrowing of the lumen of the bowel and are the cause of intussusception of the intestine. Multiple polyposis clinically proceeds like ulcerative colitis, is accompanied by the discharge of mucus, blood, and pus in the feces, and leads to severe exhaustion and anemia of the patient. Fibromas, lipomas, myomas, and other benign tumors give the same clinical manifestations as adenomatous polyps. For a long time, polyps can be asymptomatic. Palpation of the abdominal cavity yields very little indication for the diagnosis of polyps. At the present time, thanks to radiography and sigmoidoscopy, the recognition of polyps has significantly improved. Polyps located in the rectum can be detected upon digital examination. During sigmoidoscopy, it is very important to establish the character of the tumor by trial excision, since one must always keep in mind the possibility of malignant degeneration of polyps. Some authors (Schmieden and Westhues) believe that the chances of preventing the disease of cancer of the large intestines and especially cancer of the rectum have significantly increased thanks to the possibility of timely removal of polyps. Postoperative recurrences of cancer observed were in essence not recurrences, but genuine cancers formed from unremoved polyps. Great harm to the prophylaxis of cancerous diseases is caused by the underestimation of the danger of polyps, as well as the fact that polyps are diagnosed significantly less often than they actually occur. Frequently, the general practitioner in chronic intestinal hemorrhages stops at a diagnosis of hemorrhoids, without considering the possibility of the presence of polyps, and does not perform the appropriate examination. The most radical treatment for polyposis is the removal of polyps. Schmieden puts forward the proposition that "every polyp must be removed, even if this must be done with the aid of laparotomy and enterotomy." Single and multiple polyps located in the rectum and sigmoid colon can easily be removed by galvanoplasty or cauterization with a Paquelin cautery through a sigmoidosope. A special indication exists for the removal of polyps that are dark-colored or provided with a short and wide stalk, since these polyps have the greatest tendency toward malignant degeneration. With a higher location of polyps and with significant severity of the aforementioned symptoms, Obraztsov already considered cecostomy and appendicostomy indicated with subsequent flushing of the large intestines. Schmieden performs excision of single polyps, in diffuse polyposis—extirpation of the affected part of the large intestine, and if necessary—of the entire large intestine in several stages. He considers this the only rational measure based on taking into account the danger threatening in this disease. In intussusception of the intestines caused by a polyp or myoma, appropriate treatment of the intussusception is necessary. In surgical intervention, unconditional excision of the polyp or myoma is required unless excision of the entire intussusception is necessary. The clinical manifestations of malignant tumors of the intestine differ depending on the localization of the tumor. Cancer of the duodenum—see Duodenum. Cancer of the small intestines is relatively rare, especially cancer of the jejunum. In lesions of the small intestines, signs of intestinal affliction, such as phenomena of narrowing (liquid food passes even if the lumen of the intestine is partially narrowed), diarrhea, discharge of pus and blood, are in the majority of cases not observed. The initial signs of this affliction are inconstant pains in the abdomen radiating to the back, and constipation. Over time, cancer of the small intestines leads to a sudden acute stricture of the bowel. Before the appearance of stricture, in many cases a significantly mobile, dense tumor can be felt. Obraztsov described a case where he found by digital examination of the rectum in the lesser pelvis (in the posterior pouch of Douglas) a tumor of the ileum, which after a few days was determined by him already in the lower part of the abdomen. For an early and accurate diagnosis of this affliction, it is necessary to resort to X-ray examination, which reveals gas bubbles with a lower horizontal, sharply delimited plane formed thanks to partial stenosis. It must be remembered, however, that the same picture—and significantly more often—is present in tuberculous strictures and in chronic peritonitis. Significantly more often than cancer, the small intestines are affected by sarcomas. The latter afflict a younger age group and predominantly males (Pagenstecher). The sarcoma is mobile and its size ranges from an egg to a child's head; it never leads to severe narrowing of the intestinal lumen, but nevertheless the passage of food masses is hindered; above the site of the tumor, hypertrophy of the musculature develops and visible intestinal peristalsis (Darmsteifung) is observed. The small intestines are also affected by lymphosarcomatosis originating from retroperitoneal and mesenteric glands. Sarcoma of the small intestines has a rapid course, causes profuse bloody diarrhea, and leads to rapidly increasing severe emaciation, anemia, and edema. Cancer of the large intestines proceeds for a long time latently, without producing acute phenomena. Complaints of the patient of emaciation, weakness, loss of appetite, pains in the right iliac fossa, in the right or left hypochondrium, and of severe constipation lead one to think of the possibility of cancerous involvement, especially if elderly individuals point to such phenomena. In these cases, X-ray examination is of exceptional importance for diagnosis, as it reveals the beginning narrowing of the large intestines, which is already present at a time when other clinical symptoms are still poorly expressed. The best method is examination with the introduction of a contrast mass by enema. Of great importance is the X-ray study of the "relief" of the intestines according to Berg's method; it frequently makes it possible to make an early diagnosis of tumors of the intestines before such formidable symptoms as partial obstruction and a palpable tumor appear. With the development of a stricture, the advancement of intestinal contents in its region is hindered. When a contrast mass is given per os, expansion of the intestine above the tumor is observed. In far-advanced cases, the tumor is outlined, and the lumen of the intestine at the site of the tumor is filled with a smaller amount of contrast mass. A valuable sign is the finding, after evacuation of the intestine, of remnants of the contrast mass at the affected site (Restschatten). In individual cases, the tumor can be detected without the administration of a contrast mass in the presence of a gas bubble, thanks to which the tumor is clearly outlined. With significant development, the tumor is palpated in the form of a slightly sensitive, dense, mobile formation located as if isolated from the intestine. Gradually, the tumor becomes less mobile and is then fixed due to the shortening of the mesentery, which is also affected by the neoplasm. It is very important to differentiate neoplasms of the large intestine from a number of other diseases of the abdominal cavity having common symptoms. With the aid of X-ray examination, it is possible to distinguish tumors of the large intestine from tumors of the kidneys, liver, and gallbladder, retroperitoneal tumors, tuberculosis of glands located in the mesocecum and mesocolon, and others.
Significant difficulties are presented by the differential diagnosis of cancer and sarcoma of the cecum from its tuberculosis. Tuberculous infiltrate, unlike a neoplasm, decreases gradually toward the ascending colon (Obsttsov). A significant size of the tumor and repeated hemorrhages speak in favor of cancer; diarrhea, elevated temperature, and the presence of tubercle bacilli in the stool speak in favor of tuberculosis. The duration of the course of the process does not categorically speak in favor of tuberculosis. Cancer leads gradually to complete narrowing of the intestinal lumen. The course of large intestine neoplasms is very varied: in some cases, symptoms sharply increase and within a year lead to significant exhaustion; in others, they develop slowly over the course of several years. Unoperated neoplasms lead to death due to sharp exhaustion, septic intoxications, metastases to other vital organs, etc. The main task of the physician consists in establishing its presence and character by all available research methods as early as possible, before the tumor can be well palpated, and giving the patient the appropriate direction. The sole radical treatment for malignant neoplasms is surgical intervention, which yields better results the earlier it is performed. Unfortunately, a significant portion of cancer patients (according to Kuttner's statistics, 40%) are referred for operation when it is no longer possible to perform it. The treatment of intestinal tumors with radium and X-rays is merely in the study stage. Of special note is the significant mortality in the first weeks after intestinal cancer surgery, which in a large number of cases can be explained by patients being delivered late for surgical intervention. L. Buchshtab, D. Marshalkovich. Regarding tumors, the surgeon is interested in the questions: 1) of the tumor's localization, 2) of the tumor's character. Tumors located in the middle part of the abdomen and relatively mobile belong most often to the small intestines. Bloating of the small intestines, peristaltic movements in the middle part of the abdomen, and splashing phenomena point to a tumor of the small intestine, starting from the jejunum and ending with the last loop of the ileum. If the tumor occupies the right iliac region, it belongs most frequently to the cecum; when the tumor is localized in the left iliac fossa, it obviously pertains to the sigmoid colon, etc. However, one must keep in mind that a small intestine tumor can descend into the lower parts of the abdominal cavity by virtue of gravity. To determine the location of the tumor, one also has to take into account other factors, e.g., the direction and location of the expanded afferent segment. In cecal tumors, the expanded afferent segment (ileum) runs from the left and below, from the cavity of the lesser pelvis, into the right iliac fossa. In tumors of the hepatic flexure with a normally functioning ileocecal valve, a pouch is formed in the right half of the abdomen from the cecum and ascending colon. During peristalsis, this pouch has the shape of a flask, the bottom of which is determined in the iliac fossa, and the neck looks under the liver. For a more precise diagnosis of the tumor's location, if such is suspected along the course of the large intestine, one can resort first of all to cautious inflation of the intestine per anum. The character of the tumor is determined by the sum of various signs: sarcomas, for example, grow rapidly and therefore yield comparatively large smooth tumors. Cancers develop more frequently in older people, while tuberculous lesions simulating a tumor develop in younger people. Cancers, tuberculous, and actinomycotic tumor-like foci can be mobile and immobile. All of them are rather dense; cancers are more coarsely nodular. Actinomycosis is distinguished by its woody density. Precisely it has a tendency to spread to the integuments of the abdominal wall, with woody-density infiltrates being determined in the latter. Large intestine cancers are usually accompanied by constipation, which gradually increases and in cancers, especially of the sigmoid colon, leads to absolute intestinal obstruction. Tuberculous foci usually, while producing obstruction phenomena, at the same time cause diarrhea: tuberculous ulcers irritate the intestinal mucosa, cause abundant mucus secretion, which is why the intestinal contents, even of the large intestine, become liquefied. Most frequently, the diagnosis oscillates between cancer or tuberculosis of the large intestine. For differential diagnostic purposes, one can utilize Fedorov's symptom: in cancers, alimentary glucosuria can usually be easily induced, and the type of sugar curve resembles a diabetic one. In tuberculosis, there is hypoglycemia; it is not possible to induce alimentary glucosuria; the blood sugar curve type is low. Nevertheless, the diagnosis of the character of an intestinal tumor is often extremely difficult. Hence it is seen that opening the abdominal cavity provides the opportunity to verify the location of the tumor and establish its character, although precise establishment of the diagnosis may require detailed microscopic studies already after the operation. An intestinal tumor recognized as malignant (cancer, sarcoma) is subject to excision, provided resection is technically feasible. Contraindications to resection are severe exhaustion of the patients, metastases of the neoplasm, and extensive adhesions of it to surrounding tissues. An intestinal tumor recognized as an actinomycotic lesion is unquestionably subject to resection, if only resection is feasible. Unfortunately, in actinomycotic processes in the intestines, patients often come under the observation of surgeons when the process has emerged from the intestine and already passed to the abdominal wall. Even in such cases, it is sometimes possible to resect the diseased intestine together with a section of the abdominal wall, but such a resection is difficult and often unfeasible (presence of fistulas). Indications for resection are not as categorical in tuberculous tumor-like lesions of the intestines. One must remember that intestinal tuberculosis is most often secondary, and that furthermore, tuberculous intestinal ulcers after exclusion of the diseased intestinal segment tend to scar, with scarring being able to lead to complete destruction of the lumen. Results of resections. The remote results of intestinal resections for cancer can be considered encouraging. Among Fedorov's cases (Punin) there are recoveries followed up over the course of 5 years. According to Korte's pooled statistics (Korte, cited by Schaak), out of 266 surviving after intestinal resection for cancer, 102 people lived from 3 to 20 years, i.e., 38.5%. Recoveries followed up over a comparatively long period have also been noted after resections and exclusions of tuberculous tumor-like intestinal lesions (Tsvetkov, Evoyan).
V. Oppel. V. Circulatory disorders. Hemorrhages into the intestine most frequently occur in various inflammatory and ulcerated processes in the intestinal wall in cases where the corresponding process produces a breach in the integrity of a blood vessel; these include hemorrhages in typhoid fever, dysentery, tuberculosis, in non-specific follicular and catarrhal ulcerations, in decubital ulcers from intestinal stones, and in ulcerating tumors. Hemorrhages into the intestine can also be a consequence of ruptures of arteriosclerotically altered arteries, varicose veins of the intestinal wall, damage to the wall by a foreign body, or some other trauma. Bleeding is also caused by certain intestinal parasites (Ankylostoma duodenale, etc.). Furthermore, hemorrhages impregnating the entire intestinal wall to some extent or only its internal layers (mucous membrane and submucous layer) are frequently encountered in the intestine; more or less extensive hemorrhages of this sort are observed in sharp circulatory disorders (embolism of the mesenteric vessels, their thrombosis) and are designated as hemorrhagic infarction of the intestine; minor, sometimes punctate hemorrhages into the mucous membrane occur with strong hyperemia (active and congestive) of the intestinal wall, with minor emboli (e.g., in ulcerative endocarditis), with various hemorrhagic diatheses (scurvy, leukemia, anemia, thrombocytopenia, etc.), with septic diseases, with typhus in the form of the so-called exanthema, and with poisonings (arsenic, phosphorus, etc.). Despite the fact that the aforementioned minor hemorrhages occur via diapedesis, they can sometimes yield significant effusions of blood into the intestinal lumen; in particular, there are cases when hemorrhages of this sort from the intestinal wall (e.g., due to blood stasis in liver cirrhosis) are accompanied by fatal blood loss; at the same time, upon autopsy, the mucous membrane turns out to be undamaged, and the site of hemorrhage is not discovered. Hemorrhage into the intestine observed in newborns is designated as melaena neonatorum (see). Bleeding from hemorroidally dilated veins of the rectum—see Hemorrhoids. Blood poured into the intestinal lumen in the case of rapid passage through the underlying intestinal segment is excreted through the rectum in the form of a bloody-red, foamy, liquid mass; whereas in the case of delayed excretion, the blood in the large intestine thickens, turning into a black, tarry mass (the so-called melaena). One must also bear in mind that blood can be observed in the intestinal lumen that has penetrated here from hemorrhages in the stomach or esophagus, or from the swallowing of blood from the oral cavity, nasopharynx, and respiratory tract.
A. Abrikosov. The symptomatology of intestinal hemorrhages consists of general and local signs. Significant intestinal hemorrhage is usually accompanied by dizziness, tinnitus, and a syncopal state; the skin and mucous membranes turn sharply pale, the pulse drops; in profuse hemorrhages, all these phenomena assume a particularly threatening character, preceding a fatal outcome. If such a clinical picture is not accompanied by bloody stools or bloody vomiting, it should nevertheless make the physician think about internal hemorrhage and direct his attention in this direction. With small, but frequently and long-term recurring hemorrhages, symptoms of anemia develop: weakness, rapid fatigue, dizziness, etc. Among local signs, patients usually note pulsation, a feeling of heat and tension in the abdomen, and sometimes pronounced pain. If the source of hemorrhage is located high up, e.g., in duodenal hemorrhages, bloody vomiting may also frequently appear. The higher the source of hemorrhage, the greater the changes the blood passing through the intestine undergoes. Methemoglobin and hematin formed from hemoglobin impart a black color and a tarry appearance with a brilliant lacquer sheen to the intestinal discharges. The lower the source of hemorrhage, the more the discharges acquire a bloody color, and in hemorrhages from the rectum, bright red unchanged blood appears, mixed with normal-colored feces (see). While hemorrhages from the small intestines or the upper section of the large intestine may not be accompanied by any painful symptoms, rectal hemorrhages are often associated with colicky pains, tenesmus, and mucus discharge. Particularly characteristic of hemorrhages from hemorrhoids, fissures, or polyps are normal-colored feces covered on top with streaks of bright red blood or several drops of fresh blood discharged at the end of defecation, while inside the fecal cylinder the feces retain their normal color. In hemorrhages from more upper parts of the rectum or S-Romanum (e.g., in carcinoma recti, s. sigmoidei), mucosanguineous discharges are admixed with slightly altered feces; if, however, the cancer tumor is heavily ulcerated and is a source of constant irritation of the intestinal wall or narrowing of its lumen, then the external appearance of the feces (bloody-purulent or meat-water-like with an admixture of necrotic tissue fragments) and the character of their discharge (frequent painful urges) may provide grounds to suspect dysentery or ulcerative colitis, but careful examination of the rectum and S-Romanum with a finger and sigmoidoscope immediately clarifies the truth. Hemorrhages from the overlying sections of the intestine, especially from the small intestines, e.g., in typhoid fever, are distinguished by greater profuseness and lesser frequency. In volvulus, intussusceptions, and strangulations, the discharges also have a liquid consistency, but since their source is stagnant veins located below the site of the stenosis, they are distinguished for the most part by a very small admixture or complete absence of fecal masses and consist of serous fluid mixed with dark blood. Thus, by the character of intestinal hemorrhages, one can judge with a high degree of probability about the localization of the source of hemorrhage. To a certain extent, the odor of bloody discharges is also an important diagnostic symptom. Thus, a sharply putrid, cadaveric odor of feces is encountered mainly upon the breakdown of cancer tumors. But tarry ulcerated feces can also undergo putrid changes and become sharply malodorous upon a more prolonged stay in the intestine. In connection with this, it is necessary to point out yet another sign almost constantly accompanying intestinal hemorrhage— indicanuria. Strauss and his school attach great importance to this sign and find a pronounced parallelism between gastrointestinal hemorrhages and the excretion of indican in the urine. Indicanuria in these cases is a consequence of enhanced putrefactive processes in the intestine. In prolonged and severe gastrointestinal hemorrhages, a sharp foetor ex ore is also very frequently encountered, which apparently depends on the absorption of products of intestinal putrefaction and their excretion with exhaled air. On the part of the blood, the picture of secondary anemia is determined. On the part of the heart and blood vessels—the usual signs of anemia: small and frequent pulse, cardiac dilation, heart and venous murmurs, and phenomena of hydremia. When intestinal hemorrhage is suspected, it is necessary to subject the feces to careful examination (see Feces). Special mention must be made of the clinical significance of so-called "occult" hemorrhages, i.e., those minimal hemorrhages that do not cause any visible change in the color of the feces. Diagnostically, the examination of feces for occult hemorrhage plays such a prominent role because it is an almost constant or at least very frequent companion of malignant neoplasms and ulcerative processes of the gastrointestinal tract. When tuberculous ulcers in the intestines are suspected, a positive reaction for occult hemorrhage is also a valuable diagnostic sign. Treatment of intestinal hemorrhages. The main condition for the treatment of severe intestinal hemorrhages is absolute rest, both physical and mental. The patient must lie on his back without any movements, if possible not talking, and use a bedpan and urinal. An ice bag is placed on the abdomen. In phenomena of excitement or insomnia, pantopon or morphine is given subcutaneously. By all these measures, they try to achieve the cessation of hemorrhage and the formation of a thrombus. Blood stagnating in the intestine can at first serve partly as a source of nutrition for the patient, since part of it is digested and absorbed. This compensates to a certain extent for that complete abstinence from food and drink which must be carried out with great persistence for at least the first 2–3 days. In recent years, nutrient enemas have been almost completely abandoned both because their caloric value is extremely small and because such a method of feeding is associated with a violation of the basic principle of absolute rest for the patient, causing undesirable secretory and motor activity on the part of the gastrointestinal apparatus. Very useful are drip enemas of physiological NaCl solution or a 6% grape sugar solution as a means compensating for the need for fluid and supporting heart function. Determining the period of complete rest appears to be very difficult: it is necessary to carefully monitor the continued discharge of blood—manifest and occult; if the hemorrhage is not of gastric or duodenal origin, one can somewhat earlier begin feeding per os, which at first consists of lukewarm milk at 30–50 g per dose, milk or fruit jelly by the dessertspoonful several times a day, whipped egg whites with sugar, and mucilaginous broths. Only a slow and gradual expansion of this diet is strongly recommended (see Stomach ulcer and Duodenal ulcer). Among agents that directly affect the cessation of hemorrhage, intravenous administration of calcium chloride (10–20 g of a 5% solution) and a hypertonic NaCl solution of 1.8–10% is usually recommended; more concentrated NaCl solutions (10–15% in an amount from 20 to 50 cm3) should be introduced with great caution in terms of technique, since upon getting into the surrounding tissue, this solution can cause severe necroses. In addition, one can recommend subcutaneous injection of Merck's gelatin (ampoules of 50 cm3 of a 20% solution), ergotin (Ergotini 2.0, Aq. destillat. et Glycerini aa 5.0—1 cm3), and horse serum 10–20 g. Intravenous administration of a 5–20% grape sugar solution from 50.0 to 200.0 is very useful. Its action is apparently analogous to the action of a hypertonic NaCl solution, but at the same time, it represents a very valuable nutritive agent. In severe cases, one can also resort to temporary ligation of the extremities with a rubber tourniquet. In threatening collapse, expressed by severe anemia and a falling pulse, besides camphor, it is necessary to resort to subcutaneous administration of an isotonic NaCl solution (0.9%) or grape sugar (5.5%) with the addition of 1 cm3 of adrenaline (1:1,000 solution). In hemorrhoidal hemorrhages, microenemas of a 5–10% calcium chloride solution (20.0 each) or suppositories with adrenaline recommended by Boas are very useful. Surgical treatment of acute intestinal hemorrhages, in view of the great danger associated with it and the difficulty of finding the site of hemorrhage, is rejected by the majority of surgeons. In recent years, a certain change in views on the surgical treatment of acute hemorrhages in gastric and duodenal ulcers has been noticed, since a broader possibility of simultaneous blood transfusion significantly reduces the danger of surgery in severe anemia. In severe hemorrhages from the rectum, mainly hemorrhoidal, surgical intervention may prove to be life-saving. Occlusion of mesenteric vessels, although it occurs infrequently, is of considerable practical interest.
Both the trunk of the mesenteric arteries and their branches can be occluded by an embolus brought from the outside or by a thrombus formed locally. Thrombosis of the mesenteric veins is very rare and mostly occurs per continuitatem from a thrombosed portal vein. Arterial occlusion affects almost exclusively the superior mesenteric artery, most often its trunk and less frequently its branches. Despite the fact that anastomoses exist between both mesenteric arteries and their branches, sufficient collateral circulation upon arterial occlusion rarely develops, however; due to the reverse blood flow from the veins, a hemorrhagic infarction develops, and the corresponding section of the intestinal wall undergoes necrosis. When the smallest branches of the artery are occluded, small ulcers form on the intestinal mucosa. The clinical picture of the disease varies depending on whether one is dealing with an aseptic or infected embolus. When the trunk of the superior mesenteric artery is occluded, a huge part of the intestine from the lower section of the duodenum to the descending part of the colon undergoes necrosis. When the inferior mesenteric artery is occluded, the intestine becomes necrotic only in some cases. The formation of collateral circulation is more common here. The sources of arterial occlusion are mostly endocarditis or atherosclerosis of the abdominal aorta. Venous thrombosis occurs as a result of infectious-inflammatory processes in the intestine. The clinical picture of the disease resembles acute intestinal obstruction: sharp acute abdominal pain, pulse drop, vomiting, abdominal distension and tenderness, constipation, and in individual cases even fecal vomiting. In some cases, pronounced diarrhea is observed. In almost half of all cases, blood appears in the stool, which, depending on the localization of the source of bleeding, is either tarry-black or completely fresh-scarlet. With rapidly onset paralysis of the intestine, blood can accumulate inside it and not be excreted outwards. Abundant blood loss, on the one hand, and sharp pain on the other, lead to a state of collapse. Differential diagnosis between internal strangulation, invagination, volvulus, and occlusion of mesenteric vessels sometimes presents insurmountable difficulties. It is necessary, of course, first of all to look for sources of embolism, or—what is no less important—to establish the presence of embolic processes in other areas. The thought of the possibility of embolic or thrombotic processes in the mesenteric vessels should arise in those cases when dealing with elderly patients in whom, with pronounced changes in the vessels, violent phenomena of intestinal obstruction suddenly occur. The prognosis depends, of course, on the extent of the occluded area, but in all cases appears doubtful. In lesions of the inferior mesenteric artery (blood in these cases is mostly excreted fresh), one can sooner hope for a favorable outcome due to the formation of collateral circulation. Treatment for non-extensive infarctions can only be surgical and consists in the excision of the affected section of the intestines. In other cases, one has to be limited only to symptomatic measures. The so-called abdominal angina also belongs to the sphere of intestinal circulation disorders. In addition to the treatment used for angina pectoris, special attention must be paid to diet in abdominal angina, prohibiting hard-to-digest (fatty and coarse) food, heavy meals, alcoholic beverages, and smoking. Local application of heat in the form of heating pads, warm half-baths, etc., has a favorable effect.
I. Bichunsky.
VI. Surgical diseases of the intestine. Congenital anomalies. These include primarily Hirschsprung's disease (see). From time to time, surgeons have to encounter patients with situs viscerum inversus. Such a position in itself, where the cecum lies on the left and the sigmoid colon on the right, does not constitute a disease. But in cases where the patient develops some disease, e.g., appendicitis, situs inversus complicates both diagnosis and treatment. Something similar occurs when all the large intestines, due to an arrest in embryonic development, end up in the left half of the abdominal cavity. This condition is called congenital dystopia of the large intestine. The literature describes only 35 cases of congenital anomalies of the large intestine. Congenital predispositions to diseases are of three kinds: 1) drooping of the intestines, 2) abnormal mobility of the intestines, and 3) intestinal diverticula. The low position of the intestines is called enteroptosis, and the low position of the large intestine is called coloptosis. Both in enteroptosis and coloptosis, the low position of the intestines in itself does not yet constitute a disease. An excessively low position without clinical manifestations is called compensated entero- or coloptosis (Ochldel). Uncompensated coloptosis is most often caused by the fact that the splenic flexure of the large intestine (less often the hepatic flexure) turns out to be relatively strongly kinked, which is why obstacles to the passage of intestinal contents arise in this place. Therefore, chronic constipation in such patients is at times interrupted by copious repeated stools; the expelled masses often contain a lot of mucus and even blood. The situation is complicated by pericolitis: the latter fixes the segments of the intestine to each other, interfering with their peristalsis. Pericolitis, developing around the hepatic and splenic flexures of the intestine, narrows their lumens, which increases the phenomena of obstruction. In the presence of coloptosis, the transverse colon often turns out to have its apex lowered into the lesser pelvis. However, at the same time it is mobile, due to which the curvature of, for example, the splenic flexure can be corrected to a certain extent by the force of peristalsis. When the apex of the transverse colon is fixed by inflammatory adhesions of the greater omentum (colon transv. fixatum), there can be no question of any, even partial, correction of the kinking. For the treatment of coloptosis, the following operations have been proposed: 1) fixation of the transverse colon, 2) lowering of the angle of the splenic (hepatic) flexure, 3) exclusion of flexures, proposed by Payr. Exclusions for kinks of the hepatic and splenic flexures are performed economically. An anastomosis is applied (colo-colostomia): in case of a kink of the hepatic flexure - between the ascending and the right half of the transverse, in case of kinks of the splenic flexure - between the left half of the transverse and the descending. Excessively large mobility of individual sections of the intestines is a congenital predisposition to disease because it contributes to the formation of temporary kinks of the intestinal section, the occurrence of temporary overfilling of these sections with subsequent inflammation of not only the intestine itself, but also its mesentery, with cicatricial degeneration of the mesentery and an outcome into volvulus. Practically, surgeons are mainly interested in two sections of the intestines, which often possess excessive mobility: the cecum (caecum mobile) and the sigmoid colon (S-Romanum mobile). The mobility of the cecum is due to a common mesentery for the cecum and ileum. Regarding the mobile and large sigmoid colon, resection of the intestine must be considered the most radical and reliable method of treatment. The simplest and safest method of resection is Grekov II resection. Pexy of the sigmoid colon does not justify itself. If one does not resort to resection, the Hagen-Thorn operation should be preferred. The third congenital predisposing moment for diseases turns out to be diverticula, because fecal masses and even the smallest foreign bodies (e.g., cereal hairs, pieces of enamelware, etc.) get stuck in them, which injure the mucosa and open the gates of infection. The classical diverticulum is the vermiform appendix, then Meckel's diverticulum, and finally diverticula of the mucosa of the sigmoid colon (Graser). The latter sometimes penetrate through the thickness of the entire wall of the intestine and reach its serous cover. Intestinal injuries are of three kinds: 1) from the inside, i.e., from the side of the mucous membrane, 2) from the outside without violating the integrity of the abdominal wall - the so-called subcutaneous injuries, and 3) from the outside with a violation of the integrity of the abdominal wall - the so-called penetrating wounds. Injuries from the inside are caused by sharp objects getting into the intestine through the mouth and stomach. Interestingly, the entry of even sharp objects into the lumen of the intestines does not necessarily lead to an injury to the intestine; clinical practice and experiments show that even very sharp objects, such as needles, knives, hooks, can safely bypass the intestine and exit per anum. This happens because the sharp object is often enveloped by food masses; in addition, the sharp object causes a reflex spasm of the intestine upon contact with the mucosa: the latter, as it were, slips away from the object. However, sometimes sharp objects get stuck in the intestine, embed themselves in the intestinal wall, and cut through it. The cutting through proceeds relatively slowly, which is why the signs of peritoneal irritation also develop relatively slowly. Along the path of the cutting foreign body, the peritoneum of surrounding organs creates adhesions and bonds. Therefore, even such small sharp objects as needles can cut through the peritoneum and even the abdominal wall without causing noticeable phenomena of peritonitis. Large objects can cut through the intestinal wall into the region of the formed adhesions and may end up lying inside an infiltrate or abscess. In a number of cases, however, the cutting through of the foreign body occurs into the free peritoneal cavity, and either perforating peritonitis ensues or the foreign body (e.g., a needle) becomes encysted by parts of the omentum, while the very place of passage remains even unnoticeable. The diagnosis of foreign bodies of the intestine is based primarily on anamnestic data. Special attention should be paid to hysterics, who sometimes report fabricated data: allegedly they swallow a mass of needles and these needles supposedly emerge from various parts of the organism. The fact that a foreign body has actually passed through the intestines is proven by finding it in the fecal masses; sometimes the body can be found in the rectum. A number of foreign bodies can be ascertained using X-ray examination. The most important moment in diagnosis is determining the onset of the cutting through of a foreign body. The latter can be judged by signs of peritoneal irritation: pains localized in a certain area, local contraction of abdominal muscles, elevated temperature, infiltrate at the site of the presumed cutting through, leukocytosis. Treatment is initially expectant. To help the body exit, under no circumstances should laxatives be given; there is no need to give opium either. It is best to leave the intestine to work physiologically, giving inwardly enveloping food: porridge, potatoes, bread. If the body is delayed and signs of peritoneal irritation appear, laparotomy is necessary. The choice of the incision site depends on the localization of the cutting object. If its localization is not established, the incision along the midline is most advantageous. To extract the foreign body, enterotomy is performed. In a number of cases, the abdominal cavity can be closed tightly after the operation. Sometimes, in the case of an encysted abscess or peritonitis, the wound has to be tamponaded. Sometimes the surgeon, mistakenly taking a foreign body for a tumor, resects the intestine. According to the statistics of Wölfler and Lieblein (Wolfer, Lieblein), one-third of all swallowed foreign bodies exit per vias naturales; perforation is observed in 15%. The latter mostly occurs not in the stomach, but in the intestine (according to Protasyev). Subcutaneous injuries of the intestines. According to the data of the Obukhov Men's Hospital, 60% of abdominal contusions are accompanied by damage to internal organs. According to Staroverova-Rudy (Tomsk), out of 3,053 hospitalized patients, subcutaneous injuries of internal organs were noted 9 times. Among subcutaneous injuries of the organs of the abdominal cavity, intestinal injury is in first place - 34.5% according to Podobedova. Most often the small intestine is damaged: out of 51 subcutaneous intestinal injuries, there are only 3 ruptures of the large intestine (Chistoserdov). The main etiological moment of intestinal injury is a blow to the abdomen with a horse's hoof, followed by a blow to the abdomen with a fist, a blow to the abdomen with a foot, etc. The intestine is damaged in three ways: it is torn off from the mesentery (the rarest case), crushed, or bursts. Surgeons are particularly interested in the mechanism of subcutaneous bursting of the intestine. It is easiest to imagine the bursting of the intestine similar to the bursting of a rubber ball if it is hit, for example, with a hammer. The transformation of an intestinal loop into a ball is facilitated by the accumulation of gas in the intestine and its difficult exit into the efferent and afferent loops of the intestine (Krymov). The most acceptable theory of bursting can be considered Gurevich's theory; in the intestine, gas alternates with semi-liquid contents.
If a blow falls, for example, on a section of the intestine filled with gas, the latter cannot at that moment be expelled in the distal and proximal directions, and therefore bulges and sometimes ruptures the stretched wall of the intestine. - The diagnosis of subcutaneous injuries of the intestine differs little from the diagnosis of open injuries. The only difference is the absence of an external wound. However, instead of a wound, there is a precise designation of the site of the bruise. Penetrating wounds of the abdominal cavity with wounds of internal organs have their own peacetime statistics. However, gunshot wounds of the intestines in wartime acquire special importance. It turns out that in 89% there is a combined wound of the intestine with other organs (Sharetsky). According to Prokin, however, combined wounds were noted in 38%, isolated wounds in 27.7%. - In the interests of diagnosis, the site of application of violence or the location of the entry wound in blind wounds deserves attention; in through-and-through wounds, the location of both the entry and exit openings is important. Gridnev, using material from 170 cases of wounds of the gastrointestinal tract, classifies the frequency of various symptoms in wounds of the small and large intestines as follows: Small intestines Large intestines Symptoms % frequency Symptoms % frequency Tension of the abdomen... Tenderness of the abdomen... Frequent pulse... 6 39 39 39 Meteorism... Vomiting... Tenderness of the abdomen... Disappearance of liver dullness... Slight increase in pulse rate... 20 30 In wounds of the large intestines, the symptom of bloody stool is added, which is absent in wounds of the small intestines. The location of the wound aids diagnosis. Particular attention is drawn to the pulse rate; Pavlov-Silvansky says: "The surest sign of damage to internal organs is the pulse, by the fullness and frequency of which one can decide whether the intestine is damaged or not and whether it is still possible to operate or not." The same is emphasized by Prokin. - In prognosis, one mainly has to be guided by the state of the pulse: the more frequent the pulse (greater than 120), the worse the prognosis; the rarer the pulse (up to 100), the better the prognosis. Gridnev insists that it is necessary to diagnose damage to the gastrointestinal tract before taking up the knife; he refers to a 35% mortality rate in those patients where, upon laparotomy, no wound of the viscera was found. Unfortunately, such diagnostic accuracy, especially in the early stages, is impossible. Statistics show that early laparotomies yield the best results. Therefore, the principle of applying laparotomies as early as possible in subcutaneous and open injuries of the intestines stands firm. The diagnosis of a wound or injury of the intestine is equivalent to an indication for surgery. Suspected wound or injury of the intestine is also equivalent to an indication for laparotomy. The first act of the operation—laparotomy—is the last act of exploration. - The conditions of injury (data regarding the site of application of blunt violence, entry and exit wound openings) may necessitate the use of a particular special incision to open the abdominal cavity. In cases of any doubt, the midline incision is most advantageous. The question of the final act of the operation can be decided differently: with just beginning phenomena of peritonitis—a tight suture; with phenomena of peritonitis, especially purulent diffuse or encysted—tamponade. Intestinal or fecal fistulas are divided into 2 groups: 1) typical fistulas, which empty part of the intestinal contents, 2) anus praeternaturalis, which discharges all intestinal contents outward. By their origin, intestinal fistulas again fall into 2 groups: 1) fistulas for therapeutic purposes—external and internal (jejunostomy, ileostomy, colostomy, enteroanastomosis, etc.), 2) pathological fistulas (external and internal). According to Oppel's classification, pathological fistulas fall into 1) complete fistulas, so-called labial, when the intestinal mucosa directly transitions into the skin, 2) incomplete, canalicular fistulas, when between the fistula opening in the intestine and the fistula opening on the integument there is a fistuary passage, a fistuary canal. Judging by the pathological process underlying the formation of fistulas, the latter can be divided into 1) uncomplicated and 2) complicated. Complications are caused by suppuration processes (acute and chronic) and neoplasms. Fistulas of the small intestine erode the integument surrounding the fistula. For the general condition of the organism, a fistula is the more dangerous the more intestinal contents it secretes and the higher it is located. Therefore, duodenal and jejunal fistulas threaten the patient with exhaustion. Fistulas of the lower part of the ileum and large intestine do not threaten exhaustion, even if they bear the character of anus praeternaturalis. - The origin of fistulas is diverse. They sometimes form as a result of an operation to restore the continuity of the intestinal canal, i.e., as a result of an intestinal suture. Wounds penetrating the abdominal cavity and injuring the intestine can lead to the formation of an intestinal fistula. Thus, intestinal fistulas are the result of, for example, gunshot injuries of the abdomen. Furthermore, intestinal fistulas form as a result of necrosis of the intestine during its strangulation. Therefore, they are observed after far-advanced strangulated hernias. Finally, a whole series of pathological processes destroying the intestinal wall can lead to the formation of intestinal fistulas. These include acute inflammatory processes, abscesses near the appendix, intestinal ulcers, tuberculosis, actinomycosis, cancer. Sometimes fistulas form a long time after intestinal operations. In this regard, cecal fistulas forming a long time after excision of the appendix, gastrocolic fistulas after gastroenterostomy operations, etc., deserve attention. It must be thought that the appendix stump in such cases does not cut through into the interior of the intestine, but opens outward with the formation of an abscess around the cecum, destroying the cecal wall. The question of treating fecal fistulas largely depends on the character of the fistula. As for labial fistulas and the character of anus praeternaturalis, Billroth already recommended treating such fistulas by resection of the intestinal segment with the fistula and obtained good results. This method of treatment can be called ideal. Recently, Rose also speaks out in favor of resection of the intestine with the fistula, however, he uses a different technique in the resection of the small and large intestines with the fistula. "For the former—laparotomy far from the fistula; the resected intestinal segment is everted through the fecal fistula; for the latter, the fistula is located in the center of the operating field and is removed together with a part of the intestine like a tumor" (Chaklin). Thus, Rose, in fistulas of the small intestine, first completely bilaterally excludes the section of the small intestine with the fistula, moreover excluding it economically, and in the same operation excises the intestinal section with the fistula, producing evagination of the intestine. But these two moments can also be performed in two sessions. Rose does not use the treatment of large intestine fistulas by resection in fistulas of either the right or left flexure; for the treatment of fistulas on the latter, "according to anatomical conditions, bilateral exclusion will be safer" (Chaklin). Surgical treatment of fecal fistulas requires first of all the elimination of fecal discharge; this requirement is absolute. The second requirement consists in the elimination of the fistula in general. The latter requirement is relative, since in a number of cases (unoperable cancers, actinomycosis, tuberculosis with fistulas) it is unrealizable. To fulfill the first requirement, it is necessary either to restore the continuity of the intestine at the site of the fistula or to completely isolate the intestine with the fistula from contact with feces. Restoration of the intestinal lumen can be achieved 1) by means of resection of the intestinal segment with the fistula, 2) by means of sewing up the fistula with its plasty, 3) by means of preliminary destruction of the spur in anus praeternaturalis and subsequent suturing of the intestine. - Complicated canalicular fistulas are not subject to such a method of treatment, since it is impossible to suture degenerated intestine. Therefore, for the treatment of complicated fistulas, another method should be used—bilateral complete exclusion of the intestine. Unilateral incomplete exclusion (Fig. 23), which Grekov especially recommended, can sometimes bring a cure in narrow canalicular fistulas; but this operation does not guarantee the fistula against the inflow of feces from both the afferent and efferent segments of the intestine. Wide exclusions also do not help, because feces flow in a reverse current even, for example, from the sigmoid colon into the cecum (Oppel). For fistulas of the lower part of the ileum, complete bilateral exclusion can be replaced by complete unilateral exclusion with transection of only the intestine leading to the fistula (Fig. 24), since the ileocecal valve transforms the lower segment of the ileum after transection of the intestine leading to the fistula into a bilaterally completely excluded one, with the possibility of emptying contents into the cecum. - Bilateral complete exclusion (Figure 25) can be applicable to the treatment of even labial fistulas of the small intestine when they cannot be sutured. This same operation can be applicable in a number of cases for the treatment of labial fistulas of the large intestine.
When dealing with labial fistulas without pathological changes in the intestine itself, after a certain interval following exclusion, either resection of the excluded intestine or its demucosization (see) according to Sapozhkov is joined.-The principles of treatment of internal pathological fecal fistulas are the same as those of external ones. However, the separation of organs and their suturing after the destruction of the fistula often presents great difficulties. Among surgical diseases of the intestines, in addition to those mentioned above, there are a number of other processes. In the first place is protracted ulcerative colitis, which does not yield to therapeutic treatment. At the same time, ulcerative colitis is either of sporadic or epidemic dysenteric origin. The simplest course is to resort to a two-stage appendicostomy (first sewing the appendix into the abdominal wall, and after 2-3 days cutting off the tip of the appendix) and subsequent washing of the large intestine through the appendix. One can resort to colostomy, again in two stages, so as not to infect the operation site. In extreme cases, one can apply an anus to the ileum. The latter operation is, of course, an extreme measure. Appendicostomy sometimes helps to such an extent, relieving patients of suffering, that patients, having already recovered, do not agree to the closure of the fistula (Finkelstein). The ulceraive process in the intestines can end and sometimes does end with perforation of the intestinal wall followed by peritonitis, more often diffuse, sometimes encysted. In the latter case, complex cloacae are sometimes formed in the abdominal cavity, with both small and large intestines flowing into the cloaca. Perforation of ulcers, caused by the development of both a single, simple ulcer and multiple ulcers, indicates urgent intervention. Interestingly, timely intervention sometimes makes it possible to find an ulcer that has not yet perforated, but is ready for perforation, and sew it up (Vasilevsky). In such a case, recovery is quite possible. More often, one has to intervene when perforative peritonitis is present. The results of such intervention are almost always discouraging. Chronic colitis and chronic enteritis cause a number of complications, the latter falling into three groups: 1) acute inflammatory purulent diseases of the intestinal walls, so-called intestinal phlegmons; 2) intestinal polyposis, and finally 3) blockage of both arteries and veins resulting in extensive ulceration and even gangrene of widespread areas of the intestine.-Phlegmons of the gastrointestinal tract are encountered rarely. The duodenum and the upper section of the small intestines are most frequently affected. The causative agent of the phlegmon turns out to be streptococcus, which implants itself onto the mucous membrane thanks to its minor injuries. The symptom complex is very unclear. Diagnosis is made either on the operating table or at the autopsy table. If the diagnosis is made during surgery, the most reliable method of treatment turns out to be resection of the affected segment of the intestine. At the present time, only 13 cases of recovery from phlegmon of the gastrointestinal canal are known. Out of 18 patients subjected to resection, 8 recovered.-Polyposis of the gastrointestinal canal also belongs to rare diseases. It most often affects the rectum, the sigmoid colon, and the large intestine in general, showing a predilection for its bends. The symptom complex is similar to that of chronic ulcerative colitis. Aisman recommends a radical method of treatment—resection of the affected intestine. This proposal deserves attention all the more because in 30%, or even 50%, polyposis turns into cancer. The overall postoperative mortality rate reaches 30% (Aisman).-Vascular occlusion most often concerns arteries and results from arterial embolism of cardiac origin or from thrombosis on the basis of arteriosclerosis. (The symptom complex of ileus haemostaticus—see Ileus.) In second place is thrombosis of large intestinal veins. Since the blockage of arteries and large veins leads to gangrene of the intestine and subsequent peritonitis, the outcome of the disease is fatal. Operative treatment must be as early as possible. In such a case, a cure can be achieved. It is often necessary to resect large segments of the intestines. Yudin resected about 3 m of the small intestine, Nikitin 5.94 m. Both patients successfully underwent the operation. Next, we should dwell on an even rarer disease—air cysts of the intestine (pneumatosis intestinorum). In the Russian literature, according to Alferov, only 9 cases have been described. Usually, the diagnosis is made during surgery. Treatment consists of emptying as many cysts as possible by punctures.-Laye at the beginning of the 20th century moved on to the operative treatment of constipation (intestinal stasis); he either resected the entire large intestine or excluded it, i.e., formed an anastomosis between the ileum and the sigmoid colon with transection of the afferent loop of the ileum. Exclusion of the entire large intestine cannot be recommended. It is better to resort to resection of the entire large intestine or its segments. However, the question of the applicability of large intestine resections for intestinal stasis cannot yet be considered resolved for the reason that changes in bowel activity can be of a purely functional nature. Nevertheless, a number of surgeons resort to resection of the large intestine, with the right half being resected more often. Foreign statistics note only 4% mortality after colectomy. The data of Russian authors are worse: out of 17 operations, 3 deaths (Samarin). V. Oppel. VII. Surgical treatment of diseases of the intestine. Operations performed on the intestines can be classified as follows: 1) operations restoring and strengthening the position of the intestines, favorable for the movement of their contents; 2) operations emptying the intestine; 3) bypass operations, relieving sections of the intestine; 4) operations excising sections of the intestines; 5) operations restoring the intestinal lumen; 6) operations narrowing and widening the intestinal lumen; 7) operations for closing fistulas.-Intestinal surgery could begin to develop only after Lembert (1826) developed the principle of the intestinal suture (see). The first group primarily includes operations for suturing the intestines (enteropexy), fixation, wherein it is a matter either of fixation of the small intestines by means of fixing their mesentery (Pavlov) or fixation of various sections of the large intestines (caecopexy, transversopexy, sigmoidopexy). The reason for fixation is too much mobility of the sections of the intestine. Caecopexy was first performed by Wilms (1908). It is undertaken for a mobile cecum, i.e., such a cecum that possesses a common mesentery with the ileum (mesenterium ileo-caecale commune) or only its own mesentery.-The technique of Wilms's operation is as follows: upon opening the abdominal cavity, upon deflecting the cecum inwards, a semi-lunar incision is made behind and below it through the parietal peritoneum. The latter is detached downwards, as a result of which a peritoneal pocket is formed. The cecum is lowered into the latter. The edge of the peritoneal pocket is sutured to the anterior and outer surfaces of the cecum. A number of modifications of the operation have been proposed. The latest modification was proposed by Ilyin from the clinic of S. P. Fedorov.-The indication for sigmoidopexy is a long sigmoid colon, predisposed to volvulus (see). The operation, according to Pikin, is performed in the following manner: "Upon opening the abdominal cavity—untwisting of the intestine and emptying it by squeezing. Then an incision of the peritoneum is made 25 - 30 cm long along the outer edge of the intestine. Into the retroperitoneal space formed by separating the peritoneum outwards and towards the anterior abdominal wall, the freely placed part of the sigmoid colon is laid, and the separated peritoneum is thrown over it, which in turn is sutured with separate stitches to the medial edge of the laid intestine or to the very edge of the right leaf of the mesentery."—As can be seen, the principle of suturing the cecum and sigmoid colon is the same. The reliability of the method is not very high, the result is often doubtful. The situation is even worse with the fixation of the transverse colon. The indication for this operation is sagging of the intestine, i.e., coloptosis. It is recommended to shorten the gastrocolic ligament, and then along its entire length suture the transverse colon to the anterior abdominal wall. For the radical operation of volvulus of the ileocecal region of the intestines, when for the most part a wide mesentery, pouch-like and easily mobile cecum are observed, Pavlenko in 1922 proposed, after preliminary cecoplication, to suture the mesentery of the ileum starting from the cecum and up to the duodenojejunal fold at a distance of 3-4 cm from the intestinal edge, thus forming a blind tunnel. The method has been applied clinically and, according to the author's observations, has given excellent results. It is currently difficult to express a positive opinion on this method. In principle, Pavlenko's operation converges with the Hagen-Torn operation, undertaken on the mesentery of the sigmoid colon in case of a large size and mobility of the latter. Hagen-Torn strives with his operation to turn the long, curved sigmoid flexure with limbs converging at the base into a shorter and evenly arcuately bent one. He achieves this in such a way that he places a series of stitches on the outer and inner surfaces of the mesentery of the sigmoid colon. Each of the stitches captures the mesentery at the base and not far from the apex of the intestine. Thus, the apex of the intestine approaches the base of the mesentery, the limbs of the intestine at the base diverge and move away from each other.
Hagen-Torn reports very good results from the operation. All the listed operations aim to create favorable conditions for the advancement of contents. To this kind of operations one must add untwisting (detorsio and desinvaginatio; see Volvulus of intestine). In a number of patients, the main cause of impaired content advancement turns out to be adhesions that bend or compress the intestine (for example, pericolitis). Such adhesions are the result of peritonitis; sometimes they produce long fibrous cords. Upon excision of such a cord, the obstacle to the movement of intestinal contents is immediately eliminated. Along the large intestine, there are 2 places where bends are created even under physiological conditions: these are the right and left flexures of the transverse colon (flexurae hepatica et lienalis coli). Bends of the left flexure are especially frequent. To eliminate the bend, the operation of cutting the phrenicocolic ligament can be performed. An evaluation of the latter operation was given in 1925 by Lindenbaum: "The simplest and most normal operation for eliminating the bend of the splenic flexure must be considered mobilisatio flexurae lienalis, which consists either in cutting the adhesions or in cutting the phrenicocolic ligament (Oppel, Raug), or in both manipulations." Emptying operations are used when the intestine cannot empty itself naturally (per vias naturales). Most often they find their application in intestinal obstruction of mechanical and paralytic origin (see Ileus). They are also used to remove foreign bodies stuck in the intestines (small or large) and not causing symptoms of obstruction. This category of operations primarily includes puncture of the intestine. By puncture, strongly dilated small intestines are emptied. To perform a puncture, the loop of the intestine to be punctured is extracted from the abdominal cavity, delimited from the rest of the intestines and the abdominal cavity by towels and napkins. The site of the upcoming puncture is surrounded by a purse-string suture. After this, a trocar is pierced into the intestinal lumen. It is advantageous to use a trocar with a side outlet, since a long rubber tube can be put on the latter in advance, through which the contents will flow into some placed vessel. While the fluid flows out, the abdomen or eventrated intestines are evenly compressed. Upon emptying the intestines, the trocar is removed, the suture is immediately tightened, and the area of the puncture site is thoroughly wiped with a physiological solution or rivanol solution. Over the suture, for strength, several interrupted sero-serous sutures are placed. After this, the intestinal loop is wiped again, and then it can be lowered into the abdominal cavity. The next emptying operation is the opening of the intestinal lumen—enterotomy (enterotomia). The latter ends either with the suturing of the intestine (enterorrhaphia) or with the creation of a fistula on it (enterostomia). Indications for enterotomy are foreign bodies of the intestine, even if they do not cause symptoms of obstruction. These include: Ascaris conglomerates, gallstones, intestinal stones, dentures, pieces of metal and glass objects, etc. If there are several objects in the intestines and they can be moved to one place without danger, then enterotomy is performed in one place. Otherwise, one has to make several enterotomies. During the operation, infection of the surgical field should be avoided in every possible way; therefore, the intestinal loop subject to enterotomy is separated from the peritoneal cavity by towels or napkins, the site of enterotomy is, if possible, separated from the rest of the intestine by applying elastic clamps to both the afferent and efferent ends of the intestine. Usually, a small incision in the intestine is required. Therefore, the lumen of the intestine can be opened with either a transverse or longitudinal incision, but the intestine is necessarily sutured in the transverse direction to avoid possible narrowing of the intestinal lumen. It is better to suture the intestine with a two-layer suture (see Intestinal suture). Enterostomy is used more often to empty the intestine for paralytic obstruction. In peritonitis, in general, it is more profitable to perform enterostomy on the jejunum. Sometimes enterostomy, specifically jejunostomy, is used for feeding the patient as a bypass operation (see below). Emptying enterostomy removes part of the contents from the jejunum; therefore, in such cases, a temporary intestinal fistula is applied. The last operation from the emptying group is also enterostomy, but one that removes all the contents of the intestine. Such an operation is called an artificial anus (see Anus praeternaturalis). The third group of operations on the intestines consists of bypass operations, i.e., unloading the intestine. These primarily include jejunostomy for stomach cancers. The purpose of the operation is to bypass the stomach and make it possible to feed the patient through the jejunum. Technically, the operation differs from an emptying enterostomy inasmuch as with a feeding enterostomy, not a single drop of contents should pour out of the intestine. Therefore, the technique of the operation is somewhat more complicated: the operation is performed according to the type of gastrostomy. Bypass operations also partly include a temporary artificial anus, which precedes resection of the intestines (usually large and rectal). The center of gravity of bypass, unloading operations
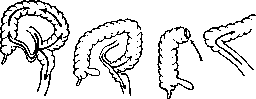
Figure 23.
Figure 24.
Figure 25.
lies in the formation of internal interintestinal fistulas, enteroanastomoses. The idea and first implementation, albeit unsuccessful, belong to the French surgeon Maisonneuve, who in 1854 reported the first enteroanastomosis, which ended in the patient's death. To this day, a simple lateral interintestinal anastomosis bears the name of Maisonneuve's operation. Thus, Maisonneuve's anastomosis began the history of intestinal exclusion. At present, surgery has three types of intestinal exclusion: 1) incomplete unilateral—Maisonneuve's anastomosis, 2) complete unilateral—lateral anastomosis + transection of the intestinal segment branching off from the anastomosis, 3) complete bilateral—lateral anastomosis + transection of both the segment branching off from the anastomosis and the segment leading to the anastomosis. Indications for their use are obstacles to the movement of intestinal contents that for one reason or another are not subject to radical treatment (resection), intestinal fistulas of various origins, non-radically operable intestinal tumors, even when they do not cause symptoms of obstruction. One can distinguish economical and uneconomical types of intestinal exclusion. Economical ones are understood to mean those in which the anastomosis is located close to the excluded place; with uneconomical ones, the anastomosis sometimes lies far from the place subject to exclusion. Generally speaking, it is more profitable
Fig. 26
economic exclusions. Uneconomic exclusions create a large excluded segment of the intestines, which, depending on the nature of the exclusion, either forms something like a ring of continuous intestine (incomplete unilateral exclusion; Fig. 23) or a long blind sac (complete unilateral exclusion; Fig. 24). Economic exclusion does not have the latter drawbacks (Fig. 26). The technique of bypass operations on the intestines is primarily the technique of creating lateral interintestinal anastomoses. It consists of the following: two intestinal loops intended for anastomosis are selected. Each of them is grasped parallel to the axis by curved elastic clamps, thanks to which the segments of the intestines being sutured are isolated from the rest of the intestine. Before applying the clamps, the loops of the intestine can be emptied by expressing the contents between the fingers. When the clamps are applied, the clamped sections of the intestines are placed one next to the other. A gauze tampon is placed between them near the mesentery. The segments being anastomosed are separated from the rest of the peritoneal cavity with napkins. Then the adjacent sections of the intestines are sutured with a continuous sero-serous suture. The length of the suture line is about 3 finger breadths. When the sero-serous suture is applied, longitudinal incisions are made on both intestines, parallel to the suture line and penetrating through the serous and muscular coats. The incision is set off from the first suture line by approximately 0.5 cm. The incision may not quite reach the ends of the suture. Every effort should be made to avoid accidentally opening the mucous membrane. It is better to work at this moment with a sharp knife, but carefully, than with a dull one and with force. Now comes the continuous suture—the second tier, which on each intestine captures the submucosa, the muscular layer, and is brought out next to the incision. When the last stitch is finished, the submucosa of first one and then the other intestine is grasped with two surgical tweezers. Between the tweezers, the lumen of the intestine is opened, and the incision with the knife is expanded to the ends of the deep suture. After processing (see Intestinal suture) of both lumens, the second half of the anastomosis is sutured. Complete unilateral exclusion differs from the previous operation only in that the end of the intestine leading away from the anastomosis is transected. For the latter purpose, the intestine, 5–8 cm away from the anastomosis, is separated from the mesentery for a certain distance. A tampon is passed into the opening in the mesentery; after this, a ligature is tied in two places on the intestine, and the intestine is transected between the ligatures. Each of the stumps is invaginated into the lumen, and a purse-string suture is placed over the invaginate and tied. Over the purse-string suture, a few interrupted sutures or one continuous sero-serous suture can be applied for strength. A rather bulky stump is obtained. To make it thinner, one can proceed in various ways: either make a circular incision on the intestine down to the mucosa, or crush the intestine at the site of ligature placement with an enterotribe, or finally transect the intestine and then close the intestinal lumens with two tiers of continuous suture. Klapp's method—rotation of the intestine around its longitudinal axis—cannot be recommended. Transection of the intestine followed by the closure of its lumens should be considered the most advantageous: this method produces the most delicate stump and makes it possible to create the smallest blind sac. However, this method is more painstaking. Stumps formed by tightening a ligature must cut through into the lumen of the intestine. Before cutting through, the stump finds itself in a certain enclosed space.
Figure 27.
it is necessary to have a section of the intestine into which to invaginate. Therefore, a blind sac is created on the end of the intestine leading away from the anastomosis. In former times, no attention was paid to what length of blind sac was formed at the afferent segment of the intestine (Figure 27 a). The blind sac accidentally turned out to be sometimes large, sometimes small. However, it became clear that blind sacs, especially at the end leading to the anastomosis, have a tendency to fill and stretch. Stretching, they bend the anastomosis itself, making it poorly patent. At the same time, stretching, they become thinner, inflamed, and even perforate. Therefore, a rule was put forward (Oppel) to eliminate blind sacs by suturing them if they are present, and best of all, to create such a stump of the transected intestine that there is no blind sac at all. The best conditions for this are available when the intestine is transected not far from the anastomosis and the lumen of the intestine is sutured with two rows of sutures (Fig. 27 b). The same can be achieved if the afferent end of the transected intestine is implanted into the wall of the intestine with which the anastomosis is made (Fig. 28). Complete bilateral exclusion differs from complete unilateral exclusion only in that in the former, not only the segment of the intestine leading away from the anastomosis is transected, but also the section leading to the anastomosis (Fig. 25). Initially, complete bilateral exclusion was performed in such a way that the excluded segment of the intestine was plunged into the abdominal cavity. Facts have revealed that secretion in the excluded section does not cease. Therefore, at present, it is customary in bilateral complete exclusion to obligatorily provide the excluded section with an evacuating mucous fistula. Operations of excision of an intestinal segment, resection (resectio intestini). The first question that must be raised regarding resections is the question of the permissible dimensions of resections. Laue showed that complete excision of the large intestine (colectomia totalis) is permissible. Somewhat more complex is the question of the permissible dimensions of resections of the small intestine. It was considered permissible to remove one-third, or even one-half of the small intestine. Nikitin, on account of gangrene, removed 594 cm of the mesenteric small intestine, leaving only 50 cm. 3 months after the operation, the patient turned out to be completely healthy and able to work ("at medium-heavy work and in clerical positions"). This case shows that in an extreme situation almost the entire small intestine can be excised, but nevertheless, one should not excise more than half of the small intestine. Indications for intestinal resections are first of all tumors of the intestines of various characters; further—strictures, volvulus, incarcerations, gangrene from arterial embolism or venous thrombosis, stretches,
Figure 28.
fistulas, and atonies. As diverse as the indications are, so diverse is the technique of resections. From the technical side, one has to distinguish between resections without opening the lumen of the intestines (these resections concern sections of the large intestine) and resections with the opening of the lumen of the intestines. The latter fall into one- and two-stage or one- and two-session, single- or double-step procedures. Usually, they are distinguished as one- and two-stage operations. The latter definition is not entirely accurate. Finally, there are three-stage intestinal resections: in the first session, an intestinal evacuating fistula is applied, in the second, the resection of the intestine is performed, in the third session, the fistula or anus is eliminated. Resections not accompanied by the opening of the intestinal lumen include S. P. Fedorov's operation on the transverse colon and Grekov's operation (evaginatio) on the sigmoid colon. Fedorov, while excising cancer of the stomach, separated the transverse colon from the mesentery (1903). Not wishing to complicate the operation, he invaginated the section of the transverse colon separated from the mesentery in the anal direction. The patient recovered. The same was performed by Emelyanov in 1927. Grekov's method, proposed by him in 1911, initially concerned volvulus of the sigmoid colon, but was later expanded. It consists in the fact that the sigmoid colon is separated from the mesentery and brought out per anum. Single-session resection of the intestines with opening of the lumen consists of three moments: 1) separating the intestine from the mesentery, 2) transecting the intestine, and 3) suturing the intestine, i.e., restoring its lumen. During resection of the small intestine, it is customary to separate the mesentery not far from the mesenteric border of the intestine. When resecting the right half of the large intestine, it is advantageous to immediately ligate the trunks of the ileocolic artery and vein, i.e., ligate them at some distance from the intestine. When resecting the sigmoid, one should not go far into the depth of the mesentery; the same applies to the transverse colon. The small intestine is separated from زمین the mesentery for such an extent as is subject to resection according to the state of the disease. The situation is different with the right half of the large intestine. Since the removal of one or two dozen centimeters of the large intestine does not play a role in the economy of the organism, if it is necessary to resect only the cecum, it is advantageous to extend the resection to the ascending colon and the hepatic flexure of the transverse colon, since it is more convenient to apply the suture in this case and there are fewer chances of contamination of the surgical field (there are many microbes in the cecum, the contents are semi-liquid). Moreover, if it is necessary to resect only the hepatic flexure or the right half of the transverse colon, the entire afferent section of the large intestine should be included in the resection for the very same reasons. When the pathological process is localized in the splenic flexure, the resection downwards should be brought to the sigmoid colon, with which it is easier to anastomose the transverse colon. Single-session resection of the intestines has several modifications, and the latter are attributed to the restoration of the intestinal lumen. 1. The lumens of the intestines can be sutured end-to-end.
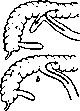

This method is particularly recommended among us by S. P. Fedorov. In this procedure, the two-row Czerny suture is usually employed. The suture presents special difficulties at the mesenteric border of the intestines. It is precisely here that it reveals the greatest dangers of insufficiency. To avoid the latter, some surgeons employ an invagination method: the afferent end of the intestine is invaginated for a certain distance into the efferent end. Closure of the lumina is achieved successfully.
2. The clinic of Spasokukotsky prefers suturing the opening of the afferent intestinal segment to the side of the efferent intestine. In this procedure, the end of the efferent intestine a
is closed tightly. 3. The simplest suture consists in forming a side-to-side anastomosis between the ends of the resected intestine. This suture is the most reliable and can be performed without special technical skill. In this regard, it is fairly immaterial
but whether the connected loops of the intestine are arranged isoperistaltically (Fig. 29, b) or antiperistaltically (Fig. 29, a), since both the first and second arrangements result in isoperistalticity. The disadvantage of this method lies in the fact that, in addition, the ends of the severed intestine must be closed, which creates the danger of forming blind pouches. Blind pouches are eliminated in the exact same way as in exclusions. All the enumerated methods immediately restore the lumen of the intestines. To complete such a resection, it is necessary to eliminate the openings between the mesenteries. Intestinal loops can become incarcerated in them after operations. The openings between the ends and edges of the mesenteries are sutured. When the intestines are sutured end-to-end, difficulties can and do arise, since the afferent segment may turn out to be either narrower or wider than the efferent one. It is more often narrower than the efferent one when a small intestine is sutured to a large one, e.g., the ileum to the transverse colon; the afferent segment may turn out to be wider than the efferent one when the lumen of, e.g., a dilated small intestine is sutured with the lumen of a collapsed small intestine below the site of the obstruction. To equalize the lumens, one has to suture either the efferent or the afferent end, or obliquely cut the afferent and efferent ends. In a word, one has to seek ways to bring the widths of the lumens to the same diameter. Single-stage intestinal resection is a comparatively difficult and dangerous operation. Therefore, Mikulicz long ago proposed a "two-stage," in essence two-session, resection of the large intestines. The latter is applicable predominantly to the large intestines, in extreme cases to the lower part of the small intestines. Mikulicz's method is as follows: "The intestinal loop subject to resection, together with the tumor and other diseased parts (glands), is freed from connections with the mesentery, etc., and placed in front of the abdominal wound; only after the abdominal cavity is completely closed and the skin is sutured up to the brought-out intestine, is the latter cut off. The brought-out intestine can be severed either immediately, as is currently accepted, or 12-24 hours later. The artificial anus thus formed is closed in such a way that first the spur is crushed with an enterotome, then the fistula is closed" (Mikulicz). From what has been said, it is evident that the resection itself has recently been performed by Mikulicz in a single session. Nevertheless, the entire operation turned out to be two-session. The meaning of a two-session operation lies in the desire to prevent peritoneal infection as much as possible. However, an artificial anus can be established only during resection of the large intestine, in extreme cases of the lower loops of the ileum, since with an artificial anus on the jejunum the patient will become exhausted. Recently, Grekov introduced a two-session resection with exclusion into principle. This operation was named "Grekov II". Its technique is as follows: "Median exploratory incision; upon finding the tumor, a wide incision of the posterior parietal peritoneum lateral to the corresponding intestine with transection of the phrenicocolic ligament." Resection of the descending colon according to Grekov is performed in the following way: "The loop along with its nourishing vessels and glands is bluntly detached up to the transverse colon superiorly and to the sigmoid colon inferiorly. An extensive free loop is obtained, which can be easily brought out, especially through a new incision on the left. The entire affected mesentery is usually resected, and the loop is brought out with the calculation that both legs of the loop remaining in connection with the mesentery will end up on the outside, of sufficient length so that after removal of the loop both of its stumps can be invaginated and sutured at a distance of several centimeters from the edges of the side wound. After a trial fit, a wide anastomosis (usually transversosigmoidostomy) is placed between both loops of the loop, remaining entirely or for the most part inside the abdominal cavity. After 2-3-4 days, the second stage is performed—without anesthesia, under morphine and, if necessary, with infiltration of the mesentery with novocaine—i.e., resection of the brought-out loop with a blind 3-layer suture of its stumps. The intestinal stumps are abundantly moistened with sterile liquid petrolatum and covered with a dry dressing" (Grekov). Thus, Mikulicz's resection with respect to intestinal removal is single-session, whereas Grekov's operation is two-session. This is its weak side, since the intestine, separated from the mesentery, must necrose. During Grekov's operation, it is necessary to prevent the escape of contents during the first days, which can infect the wound, and this can be prevented by simply ligating the intestinal stumps protruding from the wound. If Grekov's operation is performed as its author himself proposes, then it is three-session: 1) isolation of the intestine and its exteriorization with unilateral exclusion, 2) cutting off the intestine, 3) closure of the intestinal fistulas. Schloffer's operation also belongs to three-session resections. The latter, however, begins with the establishment of an artificial anus on the afferent segment of the intestine. In the second session, intestinal resection is performed, and in the third, closure of the artificial anus. And this operation under suitable conditions (fairly pronounced obstruction phenomena) is acceptable. Of the indicated methods of intestinal resection, many surgeons prefer single-session resection and obtain satisfactory results. Mikulicz's two-session method of resection requires closure of the artificial anus. The two-session method with the formation of fistulas, the exclusion of intestines with the formation of mucous fistulas often requires the elimination of the latter. A bilaterally excluded intestine can be resected under certain conditions (for example, in intestinal cancer). Long ago, surgeons had a desire to simplify matters by forming artificial constrictions of the intestinal lumen. In 1897, Mosetig-Moorhof began using the formation of intestinal valves: a thick silk ligature is passed around the intestine through the mesentery and tightened. A knotted or continuous Lembert suture is placed over the ligature. The same operation, independently of Mosetig-Moorhof, was performed by Chernyakhovsky. It turned out that the thread tightened on the intestine cuts through and the lumen of the intestine is restored. The most advantageous method of forming a valve, if it is needed for a long time, is Bogolyubov's method, which Razumovsky called biological. The intestine is constricted by a wide strip of aponeurosis. "A wide plate narrows the intestine over a more significant extent and forms a tubular stricture of the intestine with a narrow, long channel, difficult for intestinal contents to pass through" (Bogolyubov). Operations that narrow the intestinal lumen can also include Rozanov's operation—correction of the ileocecal valve. It is done in the following way: upon clarifying the question of valve insufficiency, "the ileocecal fold is dissected, and thereby the angle of entry is corrected; the ileum at the place of its entry into the large intestine, at the top, where the superior ileocecal recess is located, is fixed with one, two, or three catgut stitches to the ascending colon in order to thereby secure the corrected angle of entry. By such a technical device, we lower the upper lip of the valve and, in addition, as it were, create an artificial semilunar fold." Operations that widen the intestinal lumen are rarely used on the intestines. Even if there is a cicatricial stricture in the intestine, the latter is either excised or excluded. Recently, widening operations have found application on the ileocecal valve. Grekov and then Rozanov use it in bauginospasm (see). V. Oppel. VIII. Neuroses of the Intestine. Intestinal neuroses are diseases of the intestine of a purely functional character, having no organic substrate at all in the form of pathological, morphologically determinable changes in it. This definition does not fully correspond to modern concepts of neuroses in general, nor of pathological disorders of intestinal functions, and requires certain limitations. Thus, for example, intestinal dyspersias (see) can produce disorders of a purely functional character for a long time without at the same time being intestinal neuroses; the same applies to functional disorders of an endocrine character. Furthermore, a number of functional diseases of the intestine are known as a result not of its anatomical changes, but of a pathophysiological reaction to irritation of the allergy or anaphylaxis type; these cannot be considered pure intestinal neuroses either. Finally, even functional disorders of nervous origin, e.g., defecation disorders in organic diseases of the spinal cord, must be regarded as nervous diseases of the intestine, but not as its neuroses. On the other hand, sometimes organic processes, e.g., an anatomically barely visible duodenal ulcer, intestinal adhesion, anal fissure, etc., produce a number of functional disorders, layering to a significant degree onto symptoms of organic origin, and the clinical picture acquires the character of a "pure" intestinal neurose. The newest methods of examining the intestine, functional diagnostics of its diseases, rectomanoscopy, and especially X-ray diagnostics (relief method, Berg's method, etc.) often reveal an organic basis for diseases that for a long time were considered pure intestinal neuroses. This is why the doctrine of neuroses, which previously occupied such a large place in intestinal pathology, has narrowed significantly in recent times, and in the newest major manuals (Bergmann and Staehelin, Kraus, and others).
Brugsch) do not find a separate description of intestinal neuroses as a distinct nosological entity. The rich autonomic nervous system of the intestinal wall, its close connection with overlying vegetative centers and nerve trunks, and finally with the central nervous system—both the spinal cord and the brain—explain why, on the one hand, organic and functional diseases of the intestine sharply affect the psychoneurological system of man, and on the other hand, why not only organic but also subtle pathophysiological processes arising in the central nervous system, processes of a purely psychic character, find reflection in disorders of intestinal function. That psychic affects have a great influence on bowel function has been known for a long time, and Trousseau already described clinical observations on diarrheas of emotional origin; later, a whole series of clinicians described a multitude of motor, secretory, and sensory nervous disorders of the intestine that were in causal connection with psychic reactions and were cured psychotherapeutically. The influence of psychic affects on intestinal functions was already established considerably later fluoroscopically (Cannon) and by the method of the celluloid window in the abdominal cavity (Katsch). Having as their basis most frequently disturbances in the dynamics of psychic processes, intestinal neuroses are a manifestation of the pathological psychic reaction of the organism to external irritation. Hence, the closest mutual connection between functional disorders of the central nervous system and intestinal activity is obvious. The reason why the intestine so frequently reflects psychic affects and conflicts is attributed by some authors (v. Bergmann and his school) to the fact that the unconditioned reflex process of defecation is inhibited in civilized man by a mass of conditioned reflexes developed by upbringing and ultimately determining his behavior (see Defecation); the disinhibition of these conditioned reflexes by psychic affects is one of the causes of intestinal neuroses; the emergence of new conditioned reflexes under the influence of deep psychic affects lies at the basis of another series of neuroses. The prerequisite for the occurrence of neuroses is considered to be either constitutional features, defects of the psycho-physical personality (hereditary neuropathy), or restructuring of the personality as a result of the most diverse psychic traumas experienced by the given patient. Aetiologically, the occurrence of these psychic conflicts is often based on fear, for example, of a disease due to a misinterpretation of a somatic symptom (fear of falling ill with duodenal ulcer, cancer of the rectum, etc.); a poorly understood explanation of the disease given by the doctor ("visceroptosis," "catarrh of the intestines," appendicitis, colitis). In these cases, we may be dealing with so-called iatrogenic disease. Often at the root of intestinal neuroses are also conflicts of a sexual character: sexual dissatisfaction of both a physical and especially a psychic character and all kinds of anomalies of sexual life (coitus interruptus, condomatus), fear of venereal disease, pregnancy, physical aversion in married life, shame, etc. Minor organic lesions, e.g., bleeding erosions of the rectum, slight incarceration of hemorrhoids, or functional disorders, e.g., flatulence due to intestinal dyspepsies in neurotically predisposed individuals, are also the cause of severe and persistent forms of intestinal neuroses. Often the cause of intestinal neuroses is living conditions. Thus, defecation disorders may appear as a result of external conditions unfavorable for regular bowel movements (for example, cold, distantly located toilets, the need to observe large queues with an insufficient number of toilets in overcrowded apartments, etc.). In a number of cases, there is the appearance of intestinal neuroses on the basis of an already existing viscero-visceral reflex to the intestine, for example, in diseases of the genital sphere in women, the urogenital apparatus in men (gonorrhea and its complications) or other organs of the abdominal cavity (diseases of the biliary tract), and finally in organic diseases of the nervous system (radiculitis, tabes dorsalis, etc.). At the base of these neuroses lie frequent abnormal sensations, mainly pains in the abdominal cavity, which painfully affect the patient's psyche and lead to a restructuring of his psychic personality, fixing the patient's attention on the physiological processes of digestion. This constitutes what older physicians called hypochondria intestinalis. The aetiology and pathogenesis of intestinal neuroses are very diverse, and while they occur most frequently in constitutionally burdened neurotics, in hysteria, neurasthenia, and asthenics, intestinal neurosis is nevertheless frequently observed also in people who are otherwise balanced, under the influence of psychic trauma or a deep conflict, often unrecognized by the patient himself or long forgotten by him. Also striking is the appearance of intestinal neuroses as a result of sharp changes in external living conditions, for example, among peasants and workers when they abandon their habitual physical labor for intensive mental studies. Correspondingly, to such a complex pathogenesis of intestinal neuroses, their clinical picture is extremely diverse and highly variable. Proceeding from pathophysiological premises, intestinal neuroses are usually divided into motor, sensory, and secretory, guided by the most important functional disorder of the intestine occurring in the given neurosis. Motor neuroses in turn are divided into forms expressed in the weakening of the motor function of the intestine (atonia, intestinal paresis, habitual nervous constipation) and forms appearing as a result of the enhancement of the motor function of the intestines (hypertonia); these include numerous spastic phenomena of the intestine with an increase in its peristalsis, as a result of which there may appear in some cases spastic constipation, in others diarrhea as a result of intestinal hyperperistalsis. So-called peristaltic unrest of the intestine (tormina nervosa intestinorum) is also referred to motor neuroses. The disease is expressed by the patient's unpleasant sensation of intestinal peristalsis, accompanied by loud sound phenomena in the abdominal cavity, rumbling in the intestine. These sound phenomena suddenly appear and just as suddenly disappear, attract the attention of others to the patient, and make his stay in society burdensome. We are dealing with suddenly appearing attacks of spastic contraction of the intestine, which on occasion can be seen if observed during the attack itself in a patient who has flaccid and thin abdominal walls. According to Boas, the picture of the abdomen in such patients resembles a sack filled with potatoes. If the peristaltic unrest of the intestine is not the result of an organic process (e.g., adhesions), the prognosis for this neurosis is entirely favorable. Sensory neuroses include a) hyperesthesia of the intestine, expressed in vague pains, burning sensations, stabbing pains appearing in the abdomen for no apparent reason or under the influence of psychic irritations; b) intestinal enteralgia, expressed in attacks of severe spastic pains occurring periodically without any apparent reason; and c) neuralgia in the region of the anus—attacks of severe pain during defecation and without it for no apparent reason. Secretory neuroses include the discharge into the intestine of significant amounts of liquid, causing violent, completely unmotivated diarrheas that quickly appear and quickly disappear, which, however, upon detailed examination can be linked to psychoneurological trauma; some authors also include here myxoneurosis intestinalis membranacea, seu enteritis membranacea, a disease most commonly known under the name of colitis mucosa. This peculiar disease, which undoubtedly has great practical importance, belongs most likely to vegetative disorders of the intestine; however, it is often confused with an intestinal neurosis based on the restructuring of the entire personality of the patient as a result of severe psychoneurological conflicts. The stated classification has in mind the presence of one dominant symptom of intestinal neurosis. Meanwhile, the monosymptomatology of neuroses of both the stomach and the intestines, if we are dealing with actual psychoneurological diseases of them and not with reflex nervous disorders, is correctly called into question, which is why a strict classification based on the disorder of individual functions of the intestine must be considered artificial, since practically we are dealing with complex clinical pictures with a whole range of functional disorders, simultaneously motor, sensory, and secretory. In a whole series of cases, we are not dealing with any single complaint of the patient, but with a whole tangle of very acute and vague subjective sensations changing in their combination every day and united by a very pessimistic mood of the patient. The patient's attention is entirely occupied with studying the state of his digestion, and completely normal activity of the intestine is the subject of numerous complaints by the patient. These are the patients who carefully and daily monitor their stool, its amount and color, the content of food remnants in it, and they suffer equally from both an increase and a decrease in the number and amount of evacuations and conscientiously keep journals of their observations for years. Here, less than in other cases, can one speak of a monosymptomatic type of intestinal neurosis.
This hypochondria intestinalis of the old authors represents one of the most severe forms of intestinal neuroses, wherein precisely the iatrogenic origin of the patient's complaints and subjective sensations often has its basis in the overly detailed examination of the patient by numerous physicians to whom he constantly applies. Not the last role is played here also by the examination documents (stool analyses, X-ray protocols, and rectoscopic examinations), arbitrarily interpreted by patients unfamiliar with terminology, most often people of intellectual labor, not infrequently standing high in their intellectual development. The recognition of intestinal neurosis represents far from an easy task, even if we are talking about persons with a definitely expressed neuropathic constitution or in the presence in the anamnesis of a definite psychological trauma. It is necessary first of all by the most careful examination of the intestine with the application of methods of functional diagnostics to exclude the presence of organic disease or intestinal dysepsias of alimentary origin. It is necessary to keep in mind diseases of other organs of the abdominal cavity and especially the genital sphere as the most frequent source of viscero-visceral reflex on the intestine, as a result of which intestinal spasms, constipation, diarrhea, and constant pains appear. Finally, it is far from always possible to establish endocrine causes of intestinal disorders (e.g., thyrotoxicoses, hypofunction of the adrenal glands) as a cause of, e.g., diarrhea and (which is taken into account even less) allergic diseases of the intestines, significantly more frequent than is commonly thought, and causing motiveless diarrheas and pains of a "nervous" origin. The differential diagnosis between organic reflex nervous diseases of the intestine and frequent neuroses of it presents in each individual case features not amenable to general accounting. Typical are the lability of the clinical picture, the absence of a connection between the oncoming attacks of the disease and physical exertions or dietary errors and, conversely, the dependence of the attack on the state of the psychoneurological sphere of the patient, the sudden onset and sudden end of the attacks and finally the general psychoneurological physiognomy of the patient, imparting a definite coloring to the entire clinical picture of the disease. A careful study of the anamnesis, the conditions of life and labor of the patient, a detailed acquaintance with the internal life, the experiences of the patient, especially in his sexual sphere, lead to the correct path of the diagnosis of intestinal neurosis and predetermine the therapy. The prophylaxis of intestinal neuroses represents a major and gratifying task of the physician: regulation of labor, especially mental, correct alternation of it with physical culture and sports, the fight against sexual perversions and excesses, the prohibition of excessive smoking, systematic sports, especially during the period of puberty, the organization of reasonable rest, especially collective summer excursions,—such in general words are the foundations of the prophylaxis of these frequent diseases. Daily occupations in physical labor are very useful in persons torn away from habitual physical work and engaged, e.g., in studies or economic and social activity with excessive mental load; on the other hand, attention must be paid to the careless prescription of diet by physicians and to the psychological traumas of persons predisposed to neuroses of the intestines on the part of the medical and nursing personnel (negative psychotherapy). — T r e a t m e n t of intestinal neuroses is in close connection with their pathogenesis in each individual case, as a result of which more than in other diseases of the intestine, a deep individualization of each case and a deep study of the personality of the patient are required here, and less can be expected of success from general prescriptions and appointments. For example: if one patient can be permitted all sorts of food and the "strict" diet categorically rejected, to which the patient himself most often subjected himself, then in another such permission to consume any food will undermine the authority of the physician or lead to the thought of the incurability of the intestinal disease. There are no general rules here and by the very essence cannot be. At the basis of treatment must be laid a broadly understood psychotherapeutic action on the patient with an attempt to study the proximate or remote causes of the psychological conflict causing the neurosis of the intestines. If this succeeds, then not infrequently a multi-year suffering is quickly cured. The methods of psychotherapeutic action on the patient are very diverse, ranging from explanation and direct medical suggestion to psychoanalysis and hypnosis, requiring the intervention of a specialist. — Besides psychotherapeutic treatment and regulation of the patient's lifestyle (especially in the sexual sphere), a certain benefit is brought by a change of surroundings, travel, even short-term ones; significantly less benefit can be expected from treatment at special health resorts, e.g., at the Caucasian Mineral Waters, which are rather contraindicated in these cases; physical methods of therapy, especially warm general procedures (aromatic, carbonic acid baths, sometimes general electrotherapy), can be applied, but local procedures on the abdominal region and in the rectum are rather contraindicated. Of medicinal remedies, one should avoid medicaments used in organic diseases of the digestive tract (hydrochloric acid, pepsin, alkalis, bismuth, salol, etc.), as strengthening in the patient the idea of a disease of the intestine, and it is necessary to try to apply atropine and its derivatives, sometimes cocaine (3 times a day 10 drops of a 3% solution before meals in diarrhea), caffeine in constipation, quinine, strychnine, etc. Sometimes great benefit is brought also by corresponding organotherapeutic preparations (ovariin, spermin, antithyroidin, etc.). R. Luria. IX. Tuberculosis of the intestine. Pathological anatomy. Tuberculosis of the intestine can be observed in the form of a primary tuberculous lesion and in the form of secondary tuberculosis. The primary tuberculous complex, developing at the site of the primary introduction into the organism of the tubercle bacillus, in connection with the fact that the digestive tract comparatively rarely plays the role of a portal of entry for tuberculosis, is observed in the intestine rarely. As it is described by Ghon, Pototschnig, and Siegmund, it, just like the primary tuberculous complex in the lung, represents a combination of a limited tuberculous lesion at the site of introduction of the infection, i.e., in this case in the mucous membrane of the intestine [analogously to Ghon's focus (see) in the lung], tuberculous lymphangitis and a tuberculous lesion of the regional lymph gland (in the mesentery). Most frequently the primary focus is located in the small (ileal) intestine, more rarely in the large. In the mucous membrane, the change can be expressed in the form of a small ulcer, either fresh with a cheesy floor and tubercles at the edges or already cicatrizing; in other cases, the matter is limited to the formation of a cheesy nodule in the submucosal layer, and the mucous membrane remains intact. Tuberculous lymphangitis in the fresh period is detected in the form of a series of tubercles extending from the focus in the mucous membrane to the mesenteric lymph gland; subsequently, only thickening along the course of the indicated lymph vessels may remain. The change of the mesenteric lymph gland usually is very sharply expressed and manifests itself in the form of a continuous cheesy lymphadenitis with the subsequent calcification of the cheesy mass. In view of the fact that the change of the intestinal mucosa can be easily overlooked, e.g., upon the cicatrization of a small tuberculous ulcer or upon the submucosal localization of a small tuberculous nodule, it sometimes seems that there is a lesion of the lymph gland without a lesion in the area of the portal of entry of the infection, i.e., in the intestinal wall. It goes without saying that frequently in connection with the spread of the process, a lesion is observed not of one, but of several mesenteric lymph glands. Secondary tuberculosis of the intestine, i.e., the lesion of the intestine by the tuberculous process from a tuberculous focus existing in another organ, is observed very frequently; wherein most often such secondary tuberculosis of the intestine takes place in patients with pulmonary tuberculosis (about 85% of all deceased from pulmonary tuberculosis patients have tuberculous changes in the intestine) thanks to the introduction from the lumen of the intestine into the mucous membrane of tubercle bacilli getting into the intestine with swallowed sputum. Much lesser significance for the origin of secondary tuberculosis of the intestine has the hematogenous transfer of tubercle bacilli, thanks to which, e.g., in chronic hematogenous dissemination, tubercles can arise in the submucosal layer, subsequently ulcerating. The lymphatic pathway of infection of the intestine, presupposing retrograde transport of tubercle bacilli from the affected lymph glands of the mesentery into the intestinal wall, cannot be considered proven. Pathologo-anatomically, secondary tuberculosis of the intestine, complicating pulmonary tuberculosis, most frequently affects the ileum; however, it must be noted that any department of both the small and large intestines can be the site of development of the tuberculous process. Initially, the appearance of tubercles is usually noticed in the region of solitary follicles or, more frequently, follicles entering into the composition of Peyer's patches; to the naked eye this is noticeable in the form of the appearance in individual of the indicated follicles of yellowish-gray specks. Tubercles can arise also outside the lymphatic apparatus and in such a case appear under the mucous membrane. Subsequently, ulceration of the tubercles occurs and the appearance of small lenticular ulcers; in Peyer's patches, several such ulcers are usually noticeable; later they merge, thanks to which larger ulcers with uneven, as if gnawed and undermined edges are formed. The floor of the ulcers is greasy, caseous; tubercles can be noticeable in it, just as in the edges of the ulcers [see separate table.
(see p. 583-584), Fig. 7]. The outline of the ulcers is extremely irregular; however, ulcers originating in Peyer's patches may subsequently occupy the entire patch and repeat its shape. Usually, very soon the tubercular process from the site of the initial lesion of the intestinal wall begins to spread along the lymphatic vessels that annularly embrace the intestinal tube; this results in the spread of the tubercular ulcerative process in a direction transverse to the longitudinal axis of the intestine and the formation of girdling, circular ulcers very characteristic of tuberculosis. The involvement of the lymphatic vessels is manifested, furthermore, by the appearance of tubercles on the serous membrane of the intestine and the nearest parts of the mesentery, and these tubercles are arranged in characteristic rows resembling beads or strings of pearls. In the large intestines, tubercular ulcers can have an extremely irregular shape, but also often show a tendency to girdling spread. In some cases of very long existence of tubercular ulcers in the large intestine, hypertrophic thickening of the mucosa at the edges of the ulcers and in the intervals between them is observed, sometimes the formation of multiple polyps (hypertrophic form of tubercular ulcers). In the lower section of the large intestine, the tubercular process can produce almost continuous ulceration with the preservation of only small islands of the mucous membrane; such forms, giving a patho-anatomical picture very similar to the picture of chronic ulcerative dysentery, Aschoff calls "tuberculous dysentery." The course of the tubercular process in the intestine can be different and in the majority of cases coincides with the course of the process observed in the same subject in the lungs. Predominantly exudative forms of pulmonary tuberculosis are usually accompanied by the formation in the intestine of tubercular ulcers that spread rapidly, often resulting in hemorrhages due to the destruction of blood vessels, and sometimes leading to perforation of the intestinal wall. Conversely, in productive and cirrhotic forms of the pulmonary process, intestinal tuberculosis exhibits an extremely very slow course, with the alternation of the formation of new tubercles and scarring noticeable in the ulcers. Sometimes tubercular ulcers of the intestine exhibit a very significant tendency to scarring, with tissue-contracting scars being formed that cause narrowing of the intestinal lumen with all its consequences. The scarring of ulcers is frequently accompanied by atypical proliferation of the epithelium of the regenerating mucous membrane, and sometimes cancers arise in chronic scarring tubercular ulcers (cases of cancer arising simultaneously in several tubercular ulcers have been described). Tuberculosis of the rectum — see Rectum.
A. Abrikosov. Clinic. During life, the recognition of intestinal tuberculosis is very difficult, and the frequency of clinical diagnosis varies sharply depending on the thoroughness of clinical observation and research methodology. Isolated tumor-like foci, ileocecal infiltrative processes accessible to methodical palpation according to Hausmann or Obraztsov can be recognized even by physical examination taking into account the entire symptom complex. To a certain extent, strictures of the small intestines on the basis of scarring of circular ulcers are also amenable to recognition. Of course, in cases where phenomena of obstruction are present, diagnostics is already rather late. Dispersed ulcers of the intestines may not cause any symptoms until death. Therefore, it is especially important to carefully monitor all moments of disruption of the correct function of the intestine and general changes in the condition of the patient, which may lead to a suspicion of intestinal tuberculosis. To this group of diagnostic signs should be referred: 1) pains (upon transition of the process to the peritoneum and involvement of the terminal branches of the intestinal nerves, with strictures and adhesions). Pains are either diffuse or localized in the ileocecal region. Pain points have been described along the edge of the rectus muscles at the level of the second lumbar vertebra and medial to McBurney's point, which authors explain by involvement of the regional mesenteric glands (periadenitis) — an inconstant sign. 2) Diarrhea alternating with constipation; profuse diarrhea of consumptives with smelly excrement and meteorism very frequently accompanies intestinal tuberculosis. On the other hand, they are not pathognomonic for tubercular lesions of the intestine, because they are frequently caused by an incorrect dietary regimen (overfeeding, excess fats), poor condition of the teeth, general intoxication. Therefore, in the presence of these disorders, it is necessary first of all to regulate the dietary regimen of the patient. Persistent complaints of such diarrhea in the anamnesis must be taken into account very attentively. 3) Laboratory data: a) tubercular bacilli in the excrement — indicative only are facts of repeated discovery of large quantities of tubercular bacilli, especially on the surface of fecal masses and with strict discipline of patients guaranteeing against swallowing sputum; b) presence of occult blood in the excrement, indicating capillary bleeding from ulcers (Weber's test or the more sensitive Gregersen test, see). 4) Roentgenological examination (with a special diaphragm of the Bucky system; images only on films, powerful apparatus) 6, 7, 8, 9, 24 hours after taking the contrast mass. Characteristic are: increased peristalsis of the entire intestine or its individual sections, filling defects (ulcers!), segmentation or expansions of individual segments. The symptom indicated by Stierlin of non-filling of the ascending part of the cecum is rejected by a number of authors. 5) Symptoms of general intoxication — paleness with a subicteric tint, anemia, weakness, poor well-being, poor appetite, tachycardia — must be taken into account as an indication of intestinal tuberculosis in the absence of other localizations that could explain the symptom complex. 6) Of diagnostic significance are partly a negative tuberculin reaction, high erythrocyte sedimentation rates, hemogram. Prevention of tubercular lesions of the intestine of enterogenous origin in consumptives is largely possible and consists first of all in teaching patients to spit out sputum without swallowing it; rational organization of the nutrition of patients with the exclusion of any excesses and strict monitoring of the regularity of the stool is of very serious significance. — Therapy. In the first place is the general hygienic-dietetic regimen (spare diet); great success is noted from ultraviolet rays; roentgenotherapy, according to many observations, does not give a satisfactory effect. Tuberculin therapy is contraindicated in the majority of cases in view of negative anergy. With isolated tumor-like lesions, ileocecal infiltrates, strictures — surgical intervention. Postoperative mortality is very significant (20–25%), in a number of cases — generalization of tuberculosis. — Prognosis is generally very poor, because the lesion of the intestine in the majority of cases is accompanied by widespread amyloidosis of the organs. If it is possible to localize and arrest the pulmonary process, with prolonged systematic treatment, significant and persistent improvement and even cure of tubercular ulcers is possible.
B. Holzmann. X. Intestinal flora. The intestinal flora of a healthy person consists of a relatively small number of species of bacteria possessing the ability to split carbohydrates with the formation of acids. The intestinal tract of an infant begins to be colonized by bacteria already in the first hours of life. According to Tissier's research, during the first three days of the child's life, a gradual colonization of the intestinal tract takes place, initially by various bacteria of a largely accidental character. By the end of the 3rd day, in the event that the child is nursed by the mother's breast, a permanent microflora is established in which Bacillus bifidus Tissier predominates (Fig. 30). In smears from the child's stool, almost exclusively this microorganism is visible, but in cultures, enterococcus (Enterococcus), Bact. coli com., and Bacillus lactis aerogenes can always be found. All these microorganisms should be referred to the normal or main microflora of the child's intestinal tract. With artificial feeding of the child, the same bacteria are found in his intestine, but the predominance of Bacillus bifidus is usually absent. Quite often Bacillus acidophilus, Bacillus exilis, Staphylococcus albus, and others join the main microflora. — In the intestine of an adult human, according to Vasina's research (1929), enterococcus belongs to the main microflora. It is present in all healthy people without exception, and is distributed rather evenly along the entire intestinal tract, starting from the duodenum and ending with the rectum. Also almost constantly in the intestinal contents is Bact. coli com. Considerably less frequently in a healthy person can one find Bacillus lactis aerogenes and Bacillus acidophilus. Characteristics of microbes of the main microflora of the intestines. 1. Bacillus bifidus Tissier (1905) in smears prepared from faeces of a child has the appearance of a straight rod, 3–4 µm long, 0.5–0.6 µm thick. In cultures on solid nutrient media, the form of this bacterium is more diverse: it varies not only in length, but bacteria with thickened, bifurcated ends or branching ones are encountered. Bacillus bifidus stains positively by Gram, is immobile, does not form spores, and does not have a capsule. It

Figure 30.
belongs to anaerobic bacteria. When cultured on agar containing glucose or some other sugar, Bacillus bifidus grows in its thickness in the form of colonies of two types: fairly large lenticular and small oval ones. It clouds glucose broth while simultaneously settling to the bottom in the form of a voluminous sediment. It does not curdle milk. It ferments grape sugar and lactose with the formation predominantly of lactic acid. It does not release gas during fermentation. It does not form indole. — 2. Bacillus acidophilus Moro (Fig. 31) (1900) is very close to the previous species of lactic acid bacteria, but can be unmistakably differentiated from them


Figure 31. Figure 32. by its ability to grow with access to air. Bacillus acidophilus is known in two variants: the first of them forms delicate small discs with a smooth surface and an even edge (Merezhkovsky type). These smooth colonies, according to English terminology, should be classified as type S (smooth). The second type, described by Moro, grows on the surface of glucose agar in the form of small colonies having a rough surface and edges scattered in strands. According to the doctrine of microbial dissociation (see), Bacillus acidophilus Moro should be considered a rough variant, that is, type R (rough) of the same species as the S variant described by Merezhkovsky. In colonies of the smooth type, the bacteria have the shape of straight rods, 2–3 µm in length with a thickness of 0.5–0.6 µm. Type R consists of straight, slightly curved, or wavy rods varying in length from 2 to 10 µm or more, with a thickness of 0.5–0.8 µm. Bacillus acidophilus stains Gram-positive, is non-motile, and does not form spores or capsules. It splits glucose and lactose with the formation of lactic acid. It does not form gas. It curdles milk slowly. — 3. Enterococcus (Fig. 32) (Streptococcus faecalis


Figure 33.
Figure 34. (English authors) has the shape of elongated oval or lanceolate, and sometimes round cocci, arranged in pairs or chains. When growing in broth with glucose, the chains can reach a fairly large length, characterized by an uneven size of cocci and variability in their shape from a coccus to a short rod. On agar with carbohydrates, enterococcus grows in the form of small colonies, transparent (S), cloudy (O), or slightly rough (R). It decomposes glucose and lactose with the formation of lactic acid. Fermentation occurs without gas evolution. Mannitol as a rule is not split. It coagulates milk without whey separation. These 3 species of Gram-staining bacteria belong to the genus of lactic acid bacteria (Genus Lactobacillus). - 4. Bact. coli commune (see) (Fig. 33 and vol. II, p. 720). - 5. Bac. lactis aerogenes has the shape of a coccobacillus, non-Gram-staining, non-motile, non-spore-forming. On the surface of solid nutrient media, Bac. lact. aerog. grows in the form of large mucous, juicy, milky-turbid, hemispherical colonies (Fig. 34). The rough type of colonies of this rod does not form mucus; it ferments glucose, lactose, and mannitol with the formation of acids and gas. It coagulates milk. It does not form indole. Apparently, this microorganism is identical to Bact. acidi lactici (Huppe), often found in sour milk. - Bac. lactis aerog. is not constantly present in the intestine of a healthy person. Bact. coli and Bac. lactis aerog. belong to the group of bacteria that, upon carbohydrate splitting, form, besides lactic acid, acetic, formic, propionic acids, as well as alcohol, hydrogen, and carbon dioxide. All the microorganisms of the main intestinal flora described above possess one common property: the ability to ferment carbohydrates with the formation of lactic and some other acids. It is precisely this function of theirs, according to Mechnikov, that determines their beneficial action for humans. They sour the food gruel in the intestine in the same way as it is done in households and food technology when preserving such food products as sour milk, kefir, kumys, sauerkraut, etc. The acidic reaction of the food gruel prevents the development of putrefactive processes in it, which are harmful and sometimes dangerous to human health. The most beneficial microorganisms for an infant should be considered Bac. bifidus and enterococcus. It is they that are found with absolute constancy in the intestine of a healthy child. In an adult, enterococcus comes to the first place, performing the main work of souring the food gruel. There is hardly any doubt that enterococcus is identical with the salivary streptococcus (Streptococcus salivarius). Consequently, the process of infection of the food mass with lactic acid bacteria begins already in the oral cavity, but it systematically occurs in the duodenum and small intestine. - Of all five main species of bacteria of the normal intestinal microflora, only Bact. coli is able to form indole and phenol during the breakdown of protein digestion products. On this basis, Mechnikov classifies Bact. coli among microbes harmful to humans, contributing to chronic poisoning of intestinal origin. But such an assertion cannot be taken as strictly proven, since the intestine of completely healthy and long-lived people also contains Bact. coli. Mechnikov put forward a hypothesis about the connection between longevity, the structure of the digestive organs, and the intestinal microflora. According to his assumption, those animals that have a relatively short intestine and often empty it, e.g., birds or reptiles, possess the greatest longevity. The large intestine is necessary for mammals as a reservoir for food, freeing them from the necessity of frequently emptying the intestine. In the large intestines, the remains of digested food stagnate, and conditions are created that favor the reproduction of putrefactive bacteria. The decomposition products of proteins formed during putrefaction, as well as the toxic substances of the bacteria themselves, chronically poison the organism of animals having developed large intestines. Intestinal intoxication increases during constipation. As a result of intestinal self-poisoning, premature old age sets in. Mechnikov proposed to introduce lactic acid bacteria with food to eliminate putrefactive processes in the intestines. He especially recommended dairy products containing the Bulgarian or Caucasian bacillus, close to Bac. acidophilus. It should be emphasized that putrefactive processes in the intestines occur in intestinal infections, improper nutrition, and reduced internal and outside secretion. Poorly digested food gruel represents a mass easily subject to putrefaction. - The question of whether the life of animals without intestinal microbes is possible was studied by a number of authors. They set up experiments of raising guinea pigs, chicks, and tadpoles in sterile conditions. These experiments proved that life without bacteria is possible, that animals with a sterile intestine do not perish even under unfavorable living conditions; but they nevertheless develop significantly worse than control ones. According to the experiments of Cohendy, infection of food with enterococcus is sufficient for the development of the chick to proceed normally. Consequently, the experiment also provided material for proving the usefulness of intestinal lactic acid bacteria. In the human intestine, butyric acid or putrefactive bacteria are also found. In a healthy person, there are few of them. During digestive disorders, they can multiply and become the predominant bacteria. One can always detect: 1. Bac. perfringens Veillon and Zuber. This microbe is named perfringens because, during hernia strangulations, it first perforates the intestinal wall and appears in the abdominal cavity exudate (perfringo - to perforate). 2. Bac. sporogenes of Mechnikov is identical to Bac. putrificus in biochemical and cultural properties, but is coarser in morphological characteristics and grows on agar with rough colonies. It is possible that it is a rough (R) variant of Bac. putrificus (see vol. VII, p. 448, fig. 1-4) (see Putrefaction). - In pathological processes accompanied by a violation of the integrity of the intestinal mucosa, putrefactive bacteria appear in the feces, possessing the ability to destroy proteins or peptone. Indicator aerobic proteolytic bacteria include: 1. Proteus vulgaris Hauser, having the shape of a small, motile, non-Gram-staining rod. Its smooth variety (S) grows on the agar surface with a thin, slightly turbid coating, makes the broth turbid, and rapidly liquefies gelatin. To the genus Proteus belongs the second species - Bact. dahlem Gildemeister and Baerthlein (1911), differing from Proteus vulg. by the absence of the ability to destroy proteins, weak motility, and growth on agar in the form of round transparent colonies. The biochemical properties of both bacteria are identical. In English literature, Bact. dahlem is described as a species of paratyphoid bacteria (Bact. paratyphi Morgan), which is hardly true. 2. Flavobacterium aromaticum Stutzer (see Putrefaction). It vigorously destroys proteins. On agar, it grows in the form of round, juicy, yellow-colored colonies smelling aromatically. Very often, during ulcerous processes, staphylococci appear in the intestinal contents, more often golden and less often white. During putrefactive processes arising from constipation, overfeeding, or irrational nutrition, bacteria of the polysaprobic type multiply in the intestinal contents. Of these, the most characteristic can be considered Bac. alcaligenes, Sarcina flava, Bac. pseudodiphtheriae, Micrococcus candidus. - According to Finkelstein (1907), infant diarrhea arises during improper feeding as a result of poisoning by products of insufficiently digested food. Bacterial processes in this case, in his opinion, play a secondary role. Another point of view was expressed by Mechnikov (1908), who considers it proven that Proteus vulgaris causes the disease of infantile cholera. According to Tissier, during pathological processes in the intestine of children, Bac. perfringens, Bac. proteus, and others multiply. Nicolle (M. Nicolle) suggests that non-pathogenic intestinal bacteria under conditions weakening the body's resistance (overheating, improper nutrition, etc.) can become pathogenic (microbes de sortie). Such bacteria include Bact. coli, enterococcus, Bac. alcaligenes, and others. The role of overheating in the origin of diarrhea has been proven experimentally by Zdrodovsky (1928). - In intestinal diseases of various characters, numerous varieties of Bact. paracoli (see Bact. coli commune), which are not present in the normal intestine, appear in the intestinal contents. This microbe can be classified among the indicators of the presence of pathological processes in the intestine. Sometimes Bact. paracoli turns out to be the predominant microbe. Its appearance in the intestinal contents is apparently connected with the presence of bacteriophage. With the help of bacteriophage, Breinl and Hoder under experimental conditions obtained various variants of Bact. coli from Bact. paracoli. Just like Bact. coli, paraintestinal bacteria can participate in pathological processes of the intestinal mucosa as microbes de sortie. - The distribution of microflora along the intestinal tract is rather uneven. In the duodenum and jejunum, there are few of them: enterococcus is always present here and often Bact. coli. In the ileum, the number of the same bacteria becomes greater.
Sometimes Bacillus acidophilus and Bacillus lactis aerogenes are associated. In the large intestine, the anaerobic Bacillus perfringens, Bacillus putrificus, and Bacillus sporogenes are found in greater numbers than in the small intestine. In the rectum, bacteria are present in the greatest numbers. None of them predominates (Tissier). In the breast-fed infant, Bacillus bifidus and the enterococcus are distributed fairly evenly along the entire intestinal tract.
M. Shtutzer. XI. Intestinal parasites. Intestinal parasites belong to protozoa and worms; various arthropods (mites and insect larvae) may live in the intestine as pseudoparasites. The intestine is either the definitive habitat of the parasites or serves only as a stage in their biological cycle. In the second case, the parasites are not revealed during diagnostic examination. The parasites that inhabit the intestine itself and reach maturity in it are as follows. Among protozoa, the parasites are amebas (see)—the dysenteric ameba (Endamoeba histolytica), the intestinal ameba (Endamoeba coli), and others. Non-pathogenic amebas reside in the lumen of the intestine, whereas the dysenteric ameba ulcerates the intestinal wall and localizes in the submucosal tissue. The parasites of the intestine also include various flagellates (see)—Giardia intestinalis (see), Trichomonas (syn. Cercomonas) intestinalis, Chilomonas mesnili, and the ciliate Balantidium coli (see), which also penetrates into the thickness of the intestinal wall. Coccidia (see) described as human parasites—Eimeria oxyspora, Eimeria wenyoni, Eimeria snijdersi—are actually parasites of fish and enter the human intestine with food. Blastocystis hominis, classified among flagellates, is apparently a saprophytic fungus. Of the parasitic worms, the majority inhabit the intestine (see Human helminthiases, as well as individual helminthic diseases). In addition, various strongyloids, Rhabditides, the parasitic role of which is unclear, are found in the intestine. Larvae of Porocephalus armillatus (see Linguatulidae) occur beneath the peritoneal covering of the intestine. Larvae of various flies (see Myiasis), certain beetles (see), such as the larvae of various coleopteran species, and some centipedes, such as Geophilus (see), Henia (formerly Chaetechelyne), Stigmatogaster, Himantarium, Scutigera, Julus (all pseudoparasites), can live in the intestine itself. The frequent presence in the feces of mites of the family Tyroglyphidae, which are swallowed by humans with food, has been noted. In addition, the intestine serves as the starting point from where a parasite begins its life cycle. The reproduction of trichinae takes place in the intestine, and their larvae pass further into the bloodstream. The hatching of ascarid eggs and their burrowing into the intestinal wall for subsequent migration also take place here. The fact that an organism is found in the feces does not yet prove that it actually lived in the intestine. There is a fairly significant number of coprophoic protozoa whose cysts pass unchanged through the digestive tract; they hatch in already voided feces. In addition, various worms may be swallowed with food (e.g., flukes parasitizing the liver of cows, sheep, and goats; free-living nematodes or nematodes inhabiting plant objects with vegetables), and their eggs may be detected in the feces and lead to a false conclusion about the presence of imaginary parasites in the intestine (imaginary alimentary trematodiases, Heterodera radicicola of vegetables, the eggs of which were described under the name Oxyuris incognita, etc.). Finally, animal organisms can get into the feces from the outside and also mislead the physician (various protozoa, strongyloids, mites, etc.). E. Pavlovsky.
Related articles
Cite this page
“Intestine.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/intestine/