Hemochromatosis
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
A 1930s medical overview of hemochromatosis, describing it as a disorder of iron metabolism characterized by skin pigmentation, liver cirrhosis, and diabetes. The article details the etiology, pathological anatomy, and symptoms, noting the historical confusion with "bronze diabetes."
Encyclopedia article (1928–1936)
HEMOCHROMATOSIS (from Greek haima—blood and chroma—color), a disease, the essence of which is a disturbance in the body's iron metabolism. This term was introduced by Recklinghausen and points to the abnormal (brown) coloration of the skin and organs, which is essentially of hematogenous nature. Hemochromatosis is often combined with hypertrophic cirrhosis of the liver and glycosuria. Hence its former designations: "cirrhose hypertrophique pigmentaire dans le diabete sucre" (Hanot, Chauffard) or "diabete bronze" (Marie). Previously, bronze diabetes was distinguished by some authors as an independent nosological unit. This finds its justification in the fact that the phenomena of diabetes—polydipsia, polyphagia, glycosuria, and emaciation—sometimes play a dominant role in the picture of hemochromatosis. The accompanying melanoderma completed the picture. At the present time, it is well known that "bronze diabetes" is only one of the symptoms of hemochromatosis. Etiology. Despite the clear independence of hemochromatosis from disturbances in hemoglobin metabolism, until recently its cause was considered to be the slow intravascular breakdown of blood, conditioned by one or another accompanying chronic disease (tuberculosis, cancer, etc.) or the absorption of harmful substances from the intestine. There is a particular opinion that hemochromatosis is caused by erythrophagia by liver cells. At the present time, the view is increasingly strengthening that pathological breakdown of blood plays no role in the pathogenesis of hemochromatosis. In other words, it is now considered that hemochromatosis is not "maximal hemosiderosis," but a disturbance of general or local iron metabolism, in which the iron molecule, brought into the cell in the usual quantity, is not assimilated by it, but is deposited and accumulated. Whether this happens because the cells are incapable of assimilating Fe due to their toxic damage, or because the iron is offered to them in an unassimilable form, is an open question. Alcoholism is pointed out as an important etiological factor.
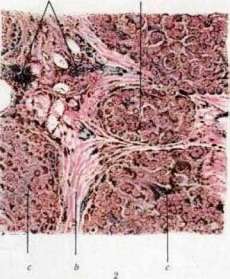

Fig. 1. Liver in hemochromatosis (from a preparation). Fig. 2. Liver in hemochromatosis: a—portal vein. b—bile duct. Pronounced cirrhosis of the liver; iron-containing pigment (tr) fills the parenchyma, leaving separate areas free. Stained with Berlin blue. Fig. 3. Hemochromatosis of the pancreas; iron-containing pigment in the glandular cells, in places accumulating in the stroma (st); pigment in the vessel walls and inter-fibrillar spaces (rj). Stained with Berlin blue.
Pathological anatomy. Upon autopsy, it is discovered that all internal organs are colored a rusty-brown or chocolate color, while large hemorrhages, which could cause such extensive "pigment metastasis," are described only as an exception. The liver, pancreas, and intra-abdominal lymph nodes are particularly heavily pigmented. The weight of the liver reaches 2,500–3,000 g; its appearance corresponds to the picture of hypertrophic cirrhosis (see separate table, Fig. 1 and 2). The pancreas is dense and cuts with difficulty. In the stem part of the brain, small hemorrhages may be found, and in the putamen—foci of yellow softening. In cases of the initial stage of hemochromatosis, in those who died from intercurrent diseases, only the 1st symptom of the disease is clearly expressed—pigmentation; cirrhotic processes at this time may be completely absent or weakly expressed. Microscopic examination reveals that the rusty coloration of the internal organs depends on the extensive deposition of a golden-brown pigment in them, and the latter is always of two kinds. One pigment, which does not give a reaction for iron, is located in the skin and in the smooth musculature of the digestive tract and vessels. It is interpreted as hemofuscin or, according to newer views, as lipofuscin, and in the skin—as melanin. The other, iron-containing pigment—hemosiderin—is deposited, mainly, in all secreting organs (liver, pancreas, salivary glands, thyroid, pituitary, vascular plexus of the brain, and many others), in the heart, and in lymph nodes. To a lesser extent—in the spleen, bone marrow, and kidneys. In the latter, it may even be completely absent. Particularly abundant deposition of pigment is noted in the parenchyma and the proliferated stroma of the liver and pancreas, then—in the periportal and retroperitoneal glands. In the latter, the deposition of iron can be so great that it leads to the disappearance of lymphoid tissue; iron-hardening of the reticular stroma is also observed. The further from the main focus of the lesion, the poorer in pigment the lymph nodes become. The amount of iron deposited in this way in the organs can exceed the norm by 100 times; for example, in the dry residue of the liver, with a norm of 0.08% iron, there can be 7.62%, in the pancreas—5%, and in the lymph nodes—14.69%. The iron found in the brain can in no way be considered physiological, as its location (perivascular and in the walls of capillaries) does not correspond to the centers where, according to Spatz, physiological iron is normally found.
Symptomatology. The most striking symptom is the bronze (or smoky) coloration of the skin, most sharply expressed in exposed places—face, neck, hands (with the exception of the palms), in places normally more pigmented (genitalia, nipples), and, finally, in areas subject to pressure or irritation (armpits, inner surface of the thighs). Similar to Addison's disease, smoky-brown spots are sometimes observed on the mucous membranes (on the gums, on the inner side of the cheeks, on the tongue). The coloration of the skin begins gradually and sometimes reaches strong degrees. Sometimes it may be absent altogether. It is often accompanied by early hair loss. Pigmentary cirrhosis is expressed by the symptoms of ordinary cirrhosis of the liver: digestive disorders, pressure in the right hypochondrium, later—signs of portal hyperemia (hemorrhoids, nosebleeds). Jaundice is rare; ascites is observed in the later stages and is usually small. The liver is always enlarged, its edge is sharp, the surface is smooth. The spleen is almost always enlarged. Diabetes is accompanied by the usual symptoms: polydipsia, polyphagia, fatigue, polyuria, and more or less expressed glycosuria; acetonemia is a rare phenomenon. The blood picture and in particular the amount of hemoglobin are within normal limits. Occasionally, slight anemia is described. The osmotic resistance of erythrocytes is normal. Urobilin is absent in the urine; hemoglobinuria is observed only in isolated, far-advanced cases. At the present time, it has been established that pigmentation is the very first symptom. It is followed by cirrhosis of the liver and other organs. Diabetes is caused by damage to the pancreas and is an inconstant and terminal complication. Hemochromatosis is an extremely rare disease. Only about 60 cases have been described. It occurs in adults, predominantly in men; in women, only 6 cases have been observed. Diagnosis presents no difficulties if the typical symptom complex is expressed: skin pigmentation, cirrhosis of the liver, and glycosuria. If the former is absent, which is not at all rare, then one has to be guided by the combination of hypertrophic cirrhosis with glycosuria in the absence of jaundice. The prognosis of hemochromatosis is unfavorable, especially in the presence of diabetes. Death may be preceded by prolonged coma. Treatment of hemochromatosis is purely symptomatic. Cholesterol was proposed internally up to 1.0 per day (with the goal of increasing the resistance of erythrocytes) and extirpation of the spleen. E. Herzenberg.
Related articles
Mentioned in
Cite this page
“Hemochromatosis.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/hemochromatosis/