Uterine Rings
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This 1930s encyclopedia article discusses the types, indications, application methods, and potential complications of uterine rings (pessaries) used in gynecology for treating uterine displacements and prolapse.
Encyclopedia article (1928–1936)
UTERINE RINGS (pessaries), devices placed in the vagina to maintain the uterus in a normal position; they are so called because their original form had the appearance of a ring. Uterine rings were used even in antiquity; accordingly, they are also found in folk medicine. In modern gynecology, their practical application began with Hodge (America, 1860), after which numerous inventions appeared (mainly by American and German authors), extremely diverse in appearance and method of application. At the present time, only a few forms are used; uterine rings are used, firstly, for the treatment of abnormal positions of the uterus and, secondly, for its prolapse. 1. For the first purpose, Hodge's pessary is most widely used in the USSR, followed by those of Thomas and Schultze.
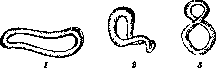
Figure 1. Uterine rings; 1—Hodge's; 2—Thomas's; 3—Schultze's. (Thomas, Schultze) (Fig. 1). All of them have been manufactured, since Prochownik's suggestion, from hard rubber; rings made of celluloid or metal (aluminum) are less expedient; however, rings with a bendable metal frame (copper wire) covered with soft rubber are also convenient, since they can easily be given any shape convenient for the given case. Rings made of dense rubber and celluloid also lend themselves to shape modification if they are thoroughly heated in hot water beforehand. Hodge's pessary in its modern form is a ring of uniform thickness of 0.8-0.9 cm; its oval lumen is wider on one side and narrower on the other; since the ring is S-shaped along its length, the edge of the wide part of the ring, if the ring is laid on a table, will rise upward; it is called the back of the ring. Thomas's ring generally retains the same shape, but has a thickened back. Schultze's S-shaped pessary, as its name implies, is twisted so that it forms two lumens: a smaller one on the side of the back and a larger one on the opposite side; along its length it is slightly arched, with the concavity facing forward. Rings differ in size, by numbers; for Hodge's rings, the number corresponds to the magnitude of the ring diameter in centimeters if the ring is given a regular round shape. Rings are used where the uterus, standing incorrectly due to relaxation of the ligamentous apparatus (retroflexion, retroversion, lateroflexion), is mobile and not bound by adhesions. Previously, it must be brought into a normal position. If it is not straightened, the ring is useless; if there are adhesions, it can cause pain. Corresponding to the width and length of the vagina, the size of the ring (its number) is chosen: in nulliparous women, most often numbers 6 and 7; in parous women, numbers 8, 9 and larger. According to the state of the ligaments and the flaccidity of the uterus, it is given the most expedient shape: the lumen is widened or compressed, the S-shaped curvature is increased, and the back is raised. The washed ring, lubricated with soap or petroleum jelly, is inserted in the oblique size of the entrance with the back forward and is positioned in the vagina so that the back is placed in the posterior fornix, with the apex forward; the cervix looks into the lumen of the ring, and the lower edge of the latter falls almost immediately behind the entrance and can sometimes even be seen during straining, especially with an insufficient pelvic floor. The S-shaped pessary is inserted in the same way, wherein the cervix is inserted into the upper smaller lumen of the ring (Figs. 2 and 3); therefore, the latter must be formed corresponding to the cervix and applied to it; the lower half of the figure eight is placed in the lower section of the vagina and with its anterior (lower) end rests against the anterior vaginal wall, pushing the cervix backward. Thus, it promotes the correct position (anteversion-flexion) of the uterus, fixing its cervix; it does not stretch the posterior fornix, which is an advantage, but can cause unpleasant pressure on the urethra and bladder with its anterior part (arch); therefore, one has to sometimes bend this part downwards (posteriorly), giving the pessary the S-shaped curvature common to other rings. Hodge's ring acts by stretching the fornices and increasing the tension of the uterosacral ligaments; its back, filling the posterior fornix, prevents the retrocession of the uterine body into the pouch of Douglas; the entire ring, lying in the vagina, receives support in the muscular pelvic floor. A correctly lying ring does not cause any sensations and does not interfere with urination, defecation, or coitus. Maintaining the uterus in its normal position, rings allow the relaxed ligamentous apparatus to regain its tone, which can be
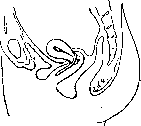
Figure 2. Hodge's uterine ring in the vagina holds the uterus in its normal position.

facilitated by appropriate measures (gymnastics, massage). After 2-3 months, you can try to remove the ring, and if the uterus retains its correct position, the goal is achieved; but quite often to cure the condition, the ring has to be worn for a long time (up to a year or more) and then it becomes necessary to periodically (every 1-2 months) check its position, remove it and clean it; otherwise, calculi may grow on the ring, and bedsores and inflammation may form in the vagina. It is clear
Figure 3. Thomas's uterine ring in the vagina holds the uterus in its normal position.
that while the ring is worn, vaginal douches with warm water, pure or with the addition, depending on necessity, of disinfecting and astringent agents, are necessary. 2. In cases of prolapse and descensus of the uterus, if for some reason surgical treatment is impossible, rings are also used. In mild cases, one can be content with Hodge's and even Schultze's rings, which, holding the uterus in anteflexion, thereby prevent its prolapse. For older and significant prolapses, rings having a round shape and acting on a somewhat different principle are used. Such are Meyer's rings with a thick hollow rim (2-2.5 cm thick) and a relatively small lumen. They are made either elastic (so that they can be more easily inserted into the vagina in a compressed state) or dense, made of hard rubber or celluloid. In folk medicine, one has to encounter rings made of twigs filled with wax. The size of the ring is determined by the degree of stretching of the vaginal walls, which must be maintained in a state of a certain tension; on the other hand, an excessively large ring can quickly cause trauma to the vagina. A hard ring is chosen of such a size (diameter) that it passes with a certain difficulty through the dilated entrance to the vagina. There it is placed in the same way as Schultze's ring, i.e., resting its rear edge against the posterior fornix and fixing the uterine cervix in its lumen. It stretches the vagina and fornices, rests on the remains of the muscular pelvic floor and together with the uterus forms a mass (pessary) which, being fixed by the tension of the tissues, cannot pass through the genital hiatus and, remaining in place, helps to keep the overlying organs of the pelvis and abdominal cavity in equilibrium. Special care must be taken with these rings, because they remain in the vagina for years, and sometimes for life, where, if they are not periodically removed, they become overgrown with calculi, eat into the tissues, producing ulcers with purulent discharges and the formation of synechiae and sometimes even with perforations into the bladder and rectum. If complications have already occurred, the ring must be removed altogether, which presents difficulties in case of adhesions. Then the ring is sawed (with a Gigli saw) in the most accessible place (at the entrance), rotated in its plane by 120-180°, so that the sawed place goes to the posterior fornix, sawed again at the entrance and, thus dividing the ring into 2-3 parts, each segment is released separately. Rings are sometimes also called devices placed in the vagina to prevent the penetration of semen into the uterus ("locking pessaries") and thus protect against pregnancy (see Contraceptives).
V. Preobrazhensky
Related articles
Mentioned in
Cite this page
“Uterine Rings.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/uterine-rings/