Tuberculosis
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia provides a comprehensive historical overview of tuberculosis, tracing its recognition from ancient civilizations to the 18th century. It details early medical observations, the evolution of diagnostic understanding, and the development of pathological theories, including the transition from the 'lymph node' theory to the recognition of the disease's unity.
Encyclopedia article (1928–1936)
74 VII. Immunoprophylaxis and immunotherapy . .
Tuberculosis (from the Latin tuberculum - tubercle), an infectious disease caused in humans, animals, and birds by a specific microorganism discovered by R. Koch (see below), is currently widespread, apparently everywhere, with a diverse and prolonged course, affecting a number of organs, but most often the lungs, intestines, bones, and joints. The manifestation and severity of the disease, in addition to the peculiarities of localization, the massiveness of the infection, and the nature of the biological reaction of the organism, are decisively influenced by the working and living conditions in which the patient is located. This closest connection of tuberculosis with social conditions gave rise to calling tuberculosis a social disease, a proletarian disease. K. Marx in "Capital" characterizes tuberculosis as an inevitable consequence of the capitalist economic system. I. Historical sketch. Tuberculosis has been known since ancient times, but until the 19th century, when this name was proposed by Laennec, it went under other names: phthisis, phthoe, consumptio (combustion), tabes, Schwindsucht, Auszehrung, consumption; its individual local manifestations also went for a long time under various names: scrofula, lupus, tabes mesaraica, etc. Although before the discovery of the causative agent of the disease, tuberculosis was confused with various diseases similar in symptom complex, nevertheless, even in the most ancient medical works that have reached us, the signs characteristic specifically of tuberculosis stand out quite clearly, and we have the opportunity to form a fairly clear idea of the views of doctors of past eras on tuberculosis, its pathogenesis, clinical picture, and treatment. The earliest indications of tuberculosis are found in the Code of Hammurabi (2250 years before the modern era), where in §§ 148 and 149 a very vivid description of the pulmonary form is given and the right to divorce a woman who has fallen ill with consumption is regulated. In the Laws of Manu (1400 years before the modern era), pulmonary consumption and the affection of the lymph glands by tuberculosis are recognized as an "unclean, incurable" disease, and, judging by the prohibition to marry women from families where such diseases occur, the observations of that time had already noted the facts of the transmission of the disease from one family member to another. Data from Egyptology allow us to consider tuberculosis in Egypt as little widespread among the ruling nation (landowners and slave owners) and more widespread among the oppressed nations ("Semitic disease"). It is absolutely certain that pulmonary tuberculosis was known in China: the treatise on medicine by Wang Shu-he (6 centuries before our era) even gives prognostic indications (slow, soft pulse—a favorable sign; tense, rapid—a bad prognosis). The advice to treat scrofula and tuberculosis of the lymph glands with alkaline waters and seaweed (iodine) deserves attention. Ancient Greek medicine, which was at the beginning of its development under the influence of Egyptian medicine, gives us many valuable indications, allowing us to assert that even at that time doctors had noted the connection of tuberculosis with constitution, the influence of family predisposition, and even its contagiousness. Fragments of the treatise of the Cnidian school allow us to establish that the Greek doctors of that era knew how to recognize outbreaks of the process accompanying the softening of foci, the cirrhotic nature of the process, rapid confluent and miliary forms, and a number of complications accompanying pulmonary tuberculosis (spontaneous pneumothorax, hydropneumothorax, Hippocratic succussion, empyema, amyloid, etc.). The semiotics of these complications are set forth very vividly and accurately. Therapeutic measures (removal of pus by opening the chest cavity with subsequent drainage and filling with an alcohol-oil emulsion), as well as the prognostic assessment of cold (tuberculous) and hot (septic) pus, leave no doubt that the doctors of that era understood the clinical picture quite clearly. A number of indications of symptoms characteristic of tuberculosis patients—sweats, constantly cold feet and hands, diarrhea, lack of appetite, affection of the larynx, pleura, nummular sputum—very vividly illustrate the great experience of Greek doctors in recognizing the manifestations of tuberculosis. With a pessimistic view of the curability of tuberculosis, given that according to the state of diagnostics, doctors knew only severe forms of tuberculosis, therapeutic measures were reduced to a hygienic-dietary regimen [rest, warm baths, intestinal hygiene, expectorants; upon improvement or transition to a chronic course—moderate physical exercise, abundant but non-irritating food, milk (preferably human, donkey, or goat)]. Among the Romans, who used mainly Greek doctors or slaves trained in Greek schools, we do not find anything essentially new. The most original are the works of Aulus Cornelius Celsus, who emphasizes the connection between tuberculosis and meteorological conditions, the significance of age (consumption of the transitional period), and includes long sea voyages in the arsenal of therapeutic measures. In the works of Galen, the tenets of the Greek school find a brilliant interpretation. In the following eras until the end of the 16th century, we note the transmission of the stated tenets of the Greek schools both in Arabic medicine (Rhazes—10th century, Maimonides—12th century) and in medieval Christian medical schools. Pathological-anatomical study of tuberculosis dates back only to the middle of the 17th century, precisely from the time when scientists began to perform autopsies of deceased patients more or less systematically. Researchers of that time describe nodules sometimes encountered in the lungs of corpses, which they designate as tubercula or as scirrhus. However, the connection of these nodules with the clinical picture of "pulmonary consumption" was first established by Sylvius de le Boe (1614–72), who claimed that consumption begins with the appearance of these nodules, which subsequently enlarge, disintegrate, and ulcerate. Sylvius de le Boe, as well as a number of subsequent scientists (Morton, Cullen, Portal, Kortum, Hufeland), believed that tubercles represent enlarging lymph nodules of lung tissue, invisible in the normal state. Their enlargement occurs due to lymph stasis or, according to Portal, due to the deposition in them of a special product in the form of tuberculous or scrofulous matter (obstruction theory of the origin of consumption). By the way, authors of that time found much in common between the nodules that occurred in the lungs during consumption and the change in lymph glands related to the so-called scrofulosis, which is why the designation of tubercles as scrofula (German: Skropheln) and the attribution of lung changes during consumption to scrofulosis is encountered very often in the writings of scientists of the 17th and 18th centuries. The view of tubercles as enlarged lymph nodules persisted for quite a long time despite the doubts expressed about this in 1766 by Morgagni and in 1785 by Reid; the latter author claimed that tubercles, or "granulations," represent not lymph glands, but a product of exudation. Reid, moreover, objected to combining tubercles with the concept of scrofulosis; in his opinion, tubercles and the manifestations of scrofulosis are completely different diseases. In this respect, Reid can be considered the founder of the so-called dualism in the assessment of tuberculous changes (see below). Morton's Phthisiology (end of the 17th century) is the first monographic work that summarized the experience and knowledge about tuberculosis accumulated over previous centuries. Morton attempts to establish the etiology of tuberculosis and quite correctly notes the provoking influence of a number of diseases (typhus, scurvy, scarlet fever, measles, smallpox, etc.), depressive mental states, overwork, and a damp, foggy climate. In the development of the process, he notes on the basis of autopsies the phases: serous infiltrate, reaction of lymph nodes, pneumonia, and cavitation. The description of symptoms, in particular the characterization of the instability of the psychic reactions of tuberculosis patients, is very vivid and accurate. The therapeutic-prophylactic measures recommended by Morton fully coincide with the indications of the Greek schools. The idea of the infectiousness of tuberculosis in the 18th century is documented by a law of 1751 issued in Spain, and later similar decrees in Naples (1782) and other Italian states. These laws prescribed a number of measures for the disinfection of dwellings and household items of consumptives. The treatise on percussion (see) published in 1761 by Auenbrugger gave a great impetus to the development of accurate diagnostics of pulmonary diseases and, in particular, consumption. A big step forward in the development of the pathological anatomy of tuberculosis was made by the Englishman Baillie (1793); he gave a good description of the tubercle and other changes in pulmonary consumption and established that "tubercles," "scrofula," nodular changes, and diffuse caseous infiltration represent different morphological expressions of one and the same disease process. An important merit of Baillie is that he discovered the formation of tubercles in other organs besides the lungs, which could merge into large caseous nodes. In addition, he categorically rejected the interpretation of tubercles as enlarged lymph nodules. The recognition by Baillie of the pathogenetic unity of tubercles and caseous, "scrofulous" infiltration forces us to recognize him as one of the founders of unitarism in the assessment of tuberculous changes. The dissertation by Hufeland, published in 1797 and having gone through a number of editions and translations into French and English, gave a brilliant analysis of the semiotics and clinical picture of tuberculosis of the lymph glands and chronic tuberculous intoxication (scrofulous diathesis) and the connection of these phases of the tuberculous process with bone tuberculosis, tuberculosis of the mesenteric glands, etc.
An attempt to bring further clarity to the nature of the changes in tuberculosis was made by the research of the French scientist Bayle (1774–1816). He was the first (1810) to introduce the term "miliary gray tubercle" or "miliary granulations"; Bayle traced the evolution of miliary tubercles from initial dense formations to their caseation and softening, and argued that they are the basis of all tuberculous changes. Tuberculosis, according to Bayle, is not a disease of the lungs alone; it is a general disease based on a specific diathesis; tubercles appear now in one organ, now in another, as manifestations of this diathesis. Bayle provided a differential diagnostic characterization of non-tuberculous lung lesions and pulmonary tuberculosis that has retained its significance to this day. However, Bayle greatly complicated the concept of "consumption" by recognizing six forms of it: 1) phtisie tuberculeuse; 2) phtisie granuleuse; 3) phtisie avec melanose; 4) phtisie ulcereuse; 5) phtisie calculeuse; 6) phtisie cancereuse. All these obscurities were eliminated by the monumental works on the pathological anatomy of tuberculosis by one of the greatest French scientists, Laennec (1781–1826). He united under the concept of "tuberculosis" various changes that some had excluded from the categories of tuberculous changes; in particular, he clarified the nature of scrofulosis as tuberculosis of the lymph glands. On the other hand, he cleansed the concepts of "tuberculosis" and "consumption" of the excessive forms that complicated them. Laennec considered Bayle's classification incorrect; in particular, in his opinion, the division of consumption into tuberculous, granulous, melanotic, and calculous forms was illogical; the ulcerative form should be excluded as belonging to gangrene of the lung, and the cancerous form as belonging to another disease—cancer. Being thus a representative of unitarianism in relation to tuberculous changes, Laennec recognized only two types of initial tuberculous changes: 1) isolated "yellow" tubercles and 2) tuberculous infiltration; these formations have an initially yellow, translucent appearance, then become dry and opaque; then follows their softening, suppuration, and, in the case of the rejection of purulent masses, the formation of ulcers and cavities. Thus, for the first time, the dynamics of tuberculous changes were precisely outlined. As for the nature of tuberculous changes, Laennec, just like Bayle, spoke out against their inflammatory origin and assumed their proximity to the process of tumor formation. Laennec's research had a tremendous influence in the first half of the 19th century on the understanding of pathological-anatomical changes in tuberculosis. Laennec verified and critically evaluated all the methods of physical diagnosis used before him and, by introducing auscultation with the help of a stethoscope, gave these methods the necessary completion. Studying at autopsies the patients whom he had observed in the clinic, Laennec had the opportunity to compare clinical data with the changes revealed at autopsy, and this ensured his descriptions an exceptional accuracy and vitality, which has preserved the significance of his research to the present day. Like Bayle, Laennec dealt mainly with severe hospital material, and this explains their pronounced therapeutic pessimism and the absence of any significant new therapeutic instructions. In subsequent years, right up to the beginning of the development of the histology of tuberculous changes, almost no additions to Laennec's doctrine were made. One can only point to the discussion about the nature of tuberculous changes: while Louis defended Laennec's point of view on the tumorous origin of the tubercle, Andral argued that the tubercle is a product of a peculiar secretion of tissue, and Broussais, Rokitansky, and others insisted on the inflammatory nature of tubercles and tuberculous infiltration, and that they represent a product of inflammatory exudation. To the same period belongs the discovery in the lungs of cows of changes analogous to those encountered in human consumption. The development of physical diagnosis continued after the powerful impetus given by Laennec. Piorry introduced the pleximeter into use, and Wunderlich the percussion hammer. A stethoscope was proposed for simultaneous listening with both ears; finally, in 1839, Skoda (Vienna) provided for the first time an accurate acoustic analysis of percussion and auscultation data, which has retained almost its full significance to the present day. With the development of biochemistry, attempts began to appear to study the structure of tuberculous foci by chemical means. The first detailed histological studies of tubercles belong to Lebert (1849), who established that tubercles consist of special rounded bodies (corpuscule, globule tuberculeux) emerging from the blastema; however, simultaneous studies by Henle and Reinhardt, who discovered these same bodies in pus, did not confirm the specificity for tuberculosis put forward by Lebert. Incidentally, Reinhardt, on the basis of his microscopic investigations, subjected to discussion the question that interested researchers of that time regarding the difference between gray and yellow tubercles. In contrast to Laennec, who advanced the idea that gray and yellow tubercles belong to different stages of one and the same process, Reinhardt began to assert that these are two completely different formations: the gray tubercle is a focus of exudation with organization of the exudate, whereas the yellow tubercle is simply thickened pus. With this, Reinhardt again resurrected the dualistic point of view on the nature of tuberculous changes. The studies of Rokitansky (1855) on the histology of the tubercle, dating to the same time, are interesting in that he was the first to see that large multinucleated elements are often encountered in the tubercle among mononuclear cells. The most significant importance in the middle of the 19th century was held by Virchow's research on tuberculosis. At first (1847), Virchow followed the path outlined by Laennec, but later (1856) he took a categorical stand on the dualistic point of view. He singled out the tubercle as a neoplasm originating from connective tissue, close in nature to lymphosarcoma; he well described its cellular structure, the absence of vessels in it, and its outcome in scarring or caseation, softening, and ulceration. In contrast to the tubercle, scrofulosis and diffuse caseous infiltrates, according to Virchow, have an exudative origin, belong to the outcomes of non-specific inflammation, and represent a manifestation of a special pathological constitution, a special vulnerability of tissues. Virchow's authority was the basis for the fact that his dualistic view of the changes found in consumptives gained wide distribution among both pathologists and clinicians (Niemeyer and others). The expression became current: "The greatest danger for a consumptive is to contract tuberculosis." The establishment of dualism in the doctrine of tuberculosis was facilitated by the histological studies of a number of French researchers; thus, Jaccoud came to the necessity of distinguishing between tuberculous and caseous (pneumonic) consumption, Robin began to draw a sharp line between gray granulations, which never undergo caseation, i.e., "tuberculization," and yellow tubercles with their outcome in softening, and Empis emphasized this even more sharply, separating small gray tubercles with the special name "granulie" and calling the disease with an eruption of a mass of gray nodules "maladie granuleuse." It was pointed out that Bayle and Laennec, not having the method of microscopic examination at their disposal, apparently knew little about true miliary tubercles, i.e., Empis's granulie, and described mainly large (in the lungs—pneumonic) nodules and therefore inclined toward unitarianism. Further development of the pathological anatomy of tuberculosis proceeded along two paths. On the one hand, there was a further deepening of anatomical and especially histological knowledge about tuberculous changes, and on the other, the clarification of the nature of changes in experimental tuberculosis. From the pathological-anatomical investigations, the studies of Buhl (1857 and 1873) deserve mention, who in the first work established that an eruption of miliary tubercles is observed only in the presence of a caseous focus, from which, via the blood, there occurs the spread of a special decay product appearing in such a non-specific focus; in the second work, Buhl worked out in detail the histology of caseous pneumonia, noting the prominent participation of alveolar epithelium in the exudate, which distinguishes this pneumonia from banal inflammations. Extremely great importance was held by the studies on the histology of tuberculosis by Langhans (1868), who was the first to describe in detail giant cells in tubercles and assessed them as something very characteristic of tuberculosis (hence the name of these cells, "Langhans giant cells"). He also outlined two possibilities for the formation of these cells (the growth of one cell during the division of its nuclei and the fusion of several cells). Through the studies of Koster, Bazin, Klebs, Wagner, and Schüppel, the histology of tubercles was developed to a significant degree; in particular, Schüppel (1871) very accurately describes three types of cells that make up the tubercle: 1) giant cells with numerous nuclei, 2) large lamellar cells resembling epithelium and which can be called "epithelioid" cells, 3) small cells of the lymphatic type—and also quite correctly points out the topographical relationship of these cells in the tubercle. Schüppel, moreover, became convinced that from tubercles in the lymph glands, a solid caseous (scrofulous) mass can subsequently form.
However, despite the precision of information regarding the structure of the tubercle, the question of the origin of the cells comprising it and the question of the essence of the tubercle were resolved in contradictory ways. Wagner classified the tubercle as a lymphoid neoplasm (lymphadenome tuberculeux); Klebs derived the cells of the tubercle from the endothelium of lymphatic vessels; Schüppel initially thought the elements of the tubercle originated from blood leukocytes, but later leaned toward the endothelium and even suggested that the development of the tubercle begins inside a blood vessel, etc. It can also be noted that a number of researchers developed the pathological anatomy of pulmonary Tuberculosis quite thoroughly. Experimental work on Tuberculosis dates back to the well-known studies of Villemin ["The Tubercle from the Point of View of Its Localization, Development, and Nature" (1862), a report to the Medical Academy (5/XII 1865), and the monograph "Studies on Tuberculosis"]. The formation of Villemin's views was decisively influenced by Virchow's work on the cell as the morphological expression of life and by Pasteur's work, which debunked the idea of the spontaneous generation of microbes and created the foundation for the study of the etiology of infectious diseases. Villemin, being a talented and inquisitive researcher, was able to provide brilliant argumentation in favor of the infectious origin of Tuberculosis and to confirm his considerations with convincing experiments. Rejecting the influence of diathesis, constitution, and heredity (e.g., mass outbreaks of Tuberculosis in the French army among soldiers selected from the most physically fit and healthy people), Villemin points to a number of circumstances that compel one to accept an infectious etiology for Tuberculosis: a) Tuberculosis is observed in all climatic conditions; b) Tuberculosis is not widespread where population density is low (highlanders, nomads), and, conversely, is observed most frequently where people live especially closely together (large cities, barracks, prisons, etc.); c) Tuberculosis is rare among livestock living on pastures and is observed during stall-feeding; it is unknown among wild animals and affects domesticated ones living among humans in zoos. All these points compel Villemin to draw a complete analogy between Tuberculosis and glanders or typhus, the infectious nature of which was already obvious. In order to confirm these considerations, Villemin performed 17 series of experiments inoculating tubercular tissue, blood, and sputum from humans and animals into animals. Thus, he performed inoculations of human tubercular material into rabbits, guinea pigs, dogs, cats, sheep, and birds. He also inoculated rabbits with tubercular material taken from a cow and from a rabbit; in addition to pronounced tubercular tissue, he performed inoculations of material from "scrofulous" foci. The success of his experiments was facilitated by an original method of introducing the test material into the trachea. Thanks to this, all his experiments yielded a positive result. Based on his experiments, Villemin arrives at the inevitable conclusion regarding the parasitic etiology of Tuberculosis. Villemin's works provoked a number of objections from his contemporaries. He was reproached for using animals in his experiments that were supposedly capable of "spontaneously" contracting Tuberculosis; the success of his experiments was contrasted with the lack of results in a number of experiments preceding Villemin's work (Kortum, Lepelletier, and others) and with the experiments of Cruveilhier, who obtained changes in organs similar to tubercular tubercles upon the injection of mercury; these comparisons were cited as objections against Villemin's arguments. Even Virchow's considerations regarding the possibility of changes analogous to tubercular foci with a non-tubercular etiology were used against Villemin.
Koch's discovery of the causative agent of tuberculosis—the tuberculosis bacillus—settled the question of the unified etiology of the manifestations of tuberculosis. It would seem that the above-mentioned experiments should have completely abolished the dualistic point of view in the sense of recognizing an etiological difference between tubercles and diffuse caseous infiltrates and returned researchers to the unitarism of Laennec. However, in reality, the authority of Virchow and the major pathologists and clinicians who adhered to his views (Aufrecht, Wildenburg, and others) caused their dualism to persist in Germany for a very long time, despite very weighty objections from such major pathologists as Baumgarten and Cohnheim, who adhered to the unitary point of view. In France, the dualistic point of view ceased to exist much sooner thanks to the recognition of unitarism in tuberculosis by such major scientists as Grancher, Lépine, Charcot, and others, although a certain hint of dualism among the French manifests itself even at the present time in the tendency to separate Laennec's yellow tubercle and Bayle's gray tubercle from one another. In England, the unitary point of view spread thanks to the works of Wilson and Fox, and in Italy, thanks to Sangalli. After Koch's discovery, the etiological dualism of Virchow-Buhl finally collapsed. Through the brilliant works of Koch, Baumgarten, and Cohnheim, which represented a synthesis of bacteriological and pathological-anatomical research, the etiologically identical origin of both tubercles and all kinds of diffuse caseous infiltrates was established. Despite the fact that etiological dualism ceased to exist, some researchers began to preach dualism in a somewhat different form, specifically in the sense of two variants of the morphological expression of the tuberculous process. Orth must be considered the founder of this new dualism. The latter insisted that in tuberculosis, changes of two types take place: 1) a productive process in the form of the formation of tubercles, and 2) an exudative process in the form of the secretion of exudate. The main difference between these two processes lies in the fact that in a tubercle there are no clear manifestations of exudation, whereas in exudative changes, in exudate that is always rich in fibrin, there are no phenomena of proliferation. Baumgarten, Fraenkel, and others objected to this point of view, pointing out that in tuberculosis, productive and exudative changes are always combined with one another; in particular, in a tubercle, one can discover fibrin between the cells, and in exudative processes, there is always proliferation, for example, in the lungs in the form of the multiplication of alveolar epithelium. In 1901–1902, a lively discussion on the above-mentioned topic took place between Orth and Baumgarten, partly at a meeting of the German Pathological Society and partly in print. Subsequently, Kaufmann, Tendeloo, Marchand, and others put forward the proposition that tuberculosis in all its expressions is an inflammatory reaction and, as such, always represents a combination of alterative, exudative, and productive changes. Therefore, in tuberculosis, there cannot be purely exudative and purely productive changes. Despite this, Orth's views on the fundamental difference between exudative and productive forms of tuberculosis gained significant currency, in particular in the teachings of Aschoff and in the classifications of Beitzke, Nicolas, and others. The discovery of the causative agent and further work by Koch on the bacteriology and epidemiology of tuberculosis, the development of the doctrine of immunity, the successes of pathological histology, pathophysiology, and biochemistry, and in recent decades, of radiology and pulmonary surgery (artificial pneumothorax and other surgical interventions), along with the emergence of an entire system of preventive and therapeutic tuberculosis institutions, sharply accelerated and deepened the development of theoretical and practical knowledge about tuberculosis. The literature on tuberculosis has grown to enormous proportions, and the number of scientific studies continues to grow. Among the most significant stages in the development of knowledge about tuberculosis over the last 50 years, it is necessary to note the works of Behring (1903–1904) and Römer on the immunization of animals and humans against tuberculosis, which formed the basis for all subsequent attempts that led to the widespread use of the Calmette-Guérin vaccine (see below—Causative agent of tuberculosis); the works of Pirquet (1902, 1907) on allergy and the significance of allergic reactions in the clinical practice of tuberculosis, which served as a starting point for numerous studies that continue to this day; studies on the routes of entry of tuberculosis bacilli into the organism (the doctrine of dust and droplet infection, developed by Flügge, Hüppe, and Lange). The works of Cornet (1888) and Ghon (1912) on the regularities observed during the primary localization of the tuberculosis virus in the organism (primary affect, reaction of regional glands), which entailed a series of studies, culminated in the talented research and generalizations of K. E. Ranke (1916–1922), who outlined the connection between the primary phase of the development of the tuberculous process (primary complex) and subsequent phases of generalization and organ lesions (isolierte Phthise) and outlined the regular interrelationships between morphological changes and allergic reactions of the organism. Modern works by Assmann, Redeker, and many others on the manifestations of the tuberculous process that directly transition into pulmonary consumption (the doctrine of the infiltrate; see below—Clinical practice), and the works of Grau (1916–1919) on chronic hematogenous forms of tuberculosis, along with numerous pathological-anatomical and radiological studies of various forms of tuberculosis, served as a powerful impetus for the revision of clinical methods for diagnosing pulmonary tuberculosis in that period when timely adopted treatment methods can provide a rapid and lasting effect. Finally, the method of treating pulmonary consumption with artificial pneumothorax, proposed in 1882 by Murphy and Forlanini, and the methods of surgical treatment of tuberculosis (thoracoplasty, etc.) subsequently introduced into clinical practice, as well as physical methods of treating other manifestations of tuberculosis, the modern development of which in sanatorium-climatic conditions dates back to the works of Brehmer and his closest students and associates, have sharply increased the effectiveness of our therapeutic measures for tuberculosis.
A. Abrikosov, V. Kholsman. P. Causative agent of tuberculosis. The tubercle bacillus (TB), discovered by R. Koch in 1882, belongs to the group of acid-fast (resp. acid-resistant) microbes [see separate table (cols. 19-20), figs. 1 and 2], which, besides the TB, includes the leprosy bacillus, as well as a whole series of acid-fast saprophytes widely distributed in nature. Acid-fastness consists of two properties: difficulty in staining and non-decolorizability under the action of acids, alkalis, and alcohol. TB, like other acid-fast microbes, are stained only upon prolonged action of the dye in the cold, or upon staining with heating, or finally upon strengthening the staining effect by adding a mordant to the dye (carbolic acid, etc.). However, once stained, acid-fast microbes are not decolorized (or are decolorized with difficulty) when treated with diluted acids, alkalis, or alcohol. In the group of acid-fast microbes, TB possess acid-fastness to the greatest degree; typical TB are not decolorized, no matter how long acids or alkalis act upon them. The question of the cause of acid-fastness cannot be considered solved; the opinion that such a cause is the presence in the bacillus of certain substances (fatty or wax-like according to Much, Goris, and others, chitin-like according to Ruppel) is opposed by the point of view of researchers who see the cause of acid-fastness in physical-chemical factors (Auclair, Paris). TB, like other acid-fast microbes, are not decolorized when stained by Gram's method; this property (iodophilia) is very sharply expressed, and even prolonged stay in a mixture of acetone and alcohol does not decolorize Gram-stained TB. Tubercle bacilli are immobile; in accordance with this, they are devoid of flagella. Morphologically, TB are rods 1.5-3.5 microns in length; longer bacilli of 5-8 microns are also encountered, as well as (rarely) filamentous forms. The rods are solid or granular; in the latter case, one, two, or more coccoid formations (granules) are embedded in the rod along its length, or the rod represents a chain of such granules, resembling a streptococcus. The granules (see separate table, figs. 4, 5, and 8) are round or (rarely) oval formations; their size is not uniform; along with large ones with a diameter exceeding the cross-section of the rod, very small granules are encountered; the number of granules varies; often there are 1 or 2, and in such a case they are often located at the poles; rods with 3-4 or more granules are also encountered; rarely are there more than 6-7. Apparently, the granules are a constant constituent part of TB, since rods that are solid when stained by the Ziehl-Neelsen method turn out to be granular when stained by Gram's method (see separate table, fig. 11). The causative agent of T. is distinguished by sharply expressed polymorphism (pleomorphism), and along with typical forms, atypical forms are encountered. This atypicality proceeds in various directions. First of all, the granules that are part of the TB can also lead an independent existence, and thus, along with acid-fast rods, one must accept the existence of acid-fast granules. But the atypicality of TB also proceeds in the direction of their loss of acid-fastness. Along with acid-fast forms, there exist non-acid-fast forms, and some of them, not being acid-fast, retain the ability not to be decolorized by Gram's method (Much's forms - see separate table, figs. 3 and 12), while others are devoid of both acid-fastness and the ability to be stained by Gram's method. The variety is further increased by the fact that the granules can also be non-acid-fast; theoretically, therefore, the existence of six forms of the T. virus is conceivable: acid-fast rods and acid-fast granules, non-acid-fast Gram-positive rods and the same granules, non-acid-fast Gram-negative rods and the same granules; practically, non-acid-fast rods and granules are usually Gram-positive (Karwacki). The transformation of typical acid-fast forms into non-acid-fast ones was most often observed in cultures of TB and in experiments on animals; in cultures, such transformation occurs under the influence of the most varied conditions (aging, frequent subculturing, cultivation on nutrient-poor media, on media with the addition of harmful substances, organ extracts, other microbes, etc.). In pathological products and organs, non-acid-fast forms were not found often, which to a significant degree depends on the difficulty of their differentiation. Non-acid-fast T. forms are described by various authors differently; most often, diphtheroid rods (see separate table, figs. 6, 7, and 10) (Sweany, Duffy, Karwacki, and others), streptobacilli, but also yeast-like microbes (Reenstierna, Vaudremer, Maher), sarcina-like forms (Kirchner), and others (see separate table, figs. 5 and 9) were observed as such forms. A special form of the T. virus constitutes the filterable virus or T. ultravirus (Calmette). By this name, one understands the forms of the T. virus discovered by Fontes that are capable of passing through a porcelain filter. These forms are invisible under a microscope at ordinary magnifications and do not grow on media used for cultivating typical TB. The only method for recognizing the presence of the ultravirus is an experiment on a guinea pig, which consists in injecting under the skin of this animal a filtrate of a TB culture, secretions, or organs containing TB; in the presence of the ultravirus in the filtrate, the guinea pig reacts with a peculiar disease: it becomes cachectic, it develops an enlargement of the lymph nodes (mainly tracheobronchial) and an enlargement of the spleen; histologically, atypical T. changes in the form of hyperplasia of the reticulo-endothelium and scattered epithelioid cells are found in these organs. Joining together, the latter can form limited epithelioid tubercles. The disease caused by the ultravirus is usually not accompanied by the death of the animals: after 1-1.5 months, all phenomena disappear. In the enlarged lymph nodes, upon careful examination of smears, one can sometimes detect acid-fast rods that do not cause typical T. in the guinea pig in the first passage. Investigations of the French school have shown that by injecting a guinea pig infected with the ultravirus with an acetone extract of tubercle bacilli (2 times a week, 1 cm³ each) for 6-7 weeks, one can obtain a significant multiplication of acid-fast bacilli and an increase in their virulence up to the ability to cause generalized T. A rapid emergence of acid-fast bacilli from the ultravirus is obtained as a result of introducing the filtrate into the peritoneal cavity of a guinea pig, which 1-2 days prior to this had been injected into the same cavity with 2.5 cm³ of a suspension of precipitated calcium phosphate salt (0.5 cm³ of 5% calcium chloride + 2 cm³ of 5% dibasic sodium phosphate salt). Already 1-2 days after the introduction of the filtrate into the peritoneal cavity, numerous acid-fast bacilli are confirmed. For the French school headed by Calmette, the ultravirus is a peculiar form of the T. virus, sharply opposed to classical TB and capable of causing an atypical T. process. For the majority of researchers, the T. ultravirus is one of the forms of existence of the T. virus, capable of passing through a porcelain filter; in all probability, this involves the smallest T. granules. According to Plotz, Jousset, and others, individual low-virulence TB pass through the filter, giving a picture of benign atypical tuberculosis in the guinea pig. The polymorphism of the causative agent of T. is not exhausted by the fact of the existence of its non-acid-fast varieties. There are numerous data speaking of the possibility of the transition of TB into actinomycetes (resp. streptothrices). Besides old data, rich material on this question has been collected recently by Karwacki, who managed to convert into Streptothrix all the strains of tubercle bacilli at his disposal (a total of 80 strains of streptothrix). Similar observations on the kinship of TB and actinomycetes belong to V. I. Kedrovsky, M. V. Trius, and E. I. Politova. All these facts prove with complete certainty the kinship between TB and actinomycetes (resp. streptothrices) and explain the term Mycobacterium tuberculosis, long ago given to tubercle bacilli by Lehmann and Neumann. Types of TB. There exist three types of true TB: the bacillus of human T. (typus humanus), the bacillus of T. of cattle (typus bovinus), and the bacillus of T. of birds (typus gallinaceus, s. tuberculosis avium). Morphological differences between these...

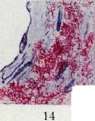
Fig. 1. Typical acid-fast tubercle bacilli. Fig. 2. Predominantly granular forms. Fig. 3. Culture of tubercle bacilli (stained according to Ziehl-Neelsen). Fig. 4. Tubercle bacilli in sputum (stained according to Ziehl-Neelsen). Fig. 5. Acid-fast and diphtheroid rods. Fig. 6. Many diphtheroid rods. Fig. 7. Granular; actinomycetous forms. Fig. 8. Branching forms of tubercle bacilli (with club-shaped ends, etc.). Fig. 9. Isolated acid-fast granules and diphtheroid rods. Fig. 10. Tubercle bacilli in sputum. (Figures 2-10 - cultures of tubercle bacilli on glycerin medium; figures 1, 2, 4-11 - stained according to Ziehl-Neelsen). Fig. 12. Tubercle bacilli in sputum (stained according to Ziehl-Neelsen). Fig. 13. Tubercle bacilli in urine: phagocytosis. Fig. 14. Tubercle bacilli in tissue. To the article Tuberculosis.
Tuberculosis
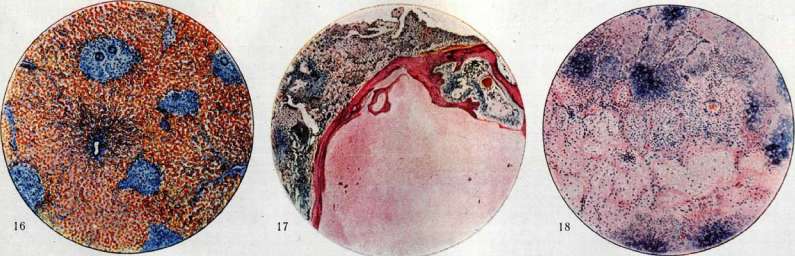
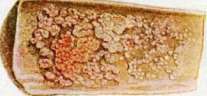
Fig. 15. Types of tubercle bacilli colonies on glycerin medium, with growth in the form of: a - dry wrinkled film on the surface; b - smooth colonies; c - growth in the form of a wrinkled film with pigmented outgrowths.
in the center: R- dry rough colonies. Figure 16. Tubercular tubercles in a fatty liver ('goose liver' in tuberculosis). Figure 17. Exudative primary affect of the lung; amorphous caseous mass of the affect surrounded by a bony capsule. Figure 18. Exudative tuberculosis of the lung: caseous necrosis of the exudate and lung parenchyma. - To the article Tuberculosis.
types are small and have relative significance. Typus humanus is longer than typus bovinus; the length of the bovine tuberculosis bacilli is on average 1-2 μ, these bacilli are thick, slightly granular.
Bacilli of avian tuberculosis are relatively long, thin, often (in cultures) form swellings and sometimes take on the character of filaments. The temperature optimum for these bacilli is 40-43°, whereas bacilli of typ. humanus and typ. bovinus grow best at a temperature of 38°.
Regarding growth on artificial nutrient media, there are the following differences. Typ. humanus grows faster than typ. bovinus and produces more luxuriant growth (eugonic growth of English authors).
When inoculated into a flask with glycerin broth, after 5-6 weeks typ. humanus forms a thick wrinkled film on the surface of the medium, rising upward along the walls of the flask.
Typ. bovinus grows more slowly than typ. humanus and produces scanty growth (dysgonic growth). Its colonies are smaller than the colonies of typ. humanus, and on glycerin broth after 5-6 weeks of growth, a thin, intermittent film is obtained, presenting warty thickenings in places.
Typ. gallinaceus grows significantly faster than typ. humanus. On glycerin agar, growth in the form of a colorless moist coating is obtained after only 4 days, whereas typ. humanus and typ. bovinus grow in the form of dry colonies, appearing 10-14 days after inoculation (typ. bovinus even later).
All the cited signs have relative significance and cannot serve for the purposes of differentiation. The unequal attitude toward glycerin also has relative significance; the addition of glycerin to the medium favors the growth of typ. humanus and sometimes exerts an inhibitory effect on the growth of typ. bovinus.
The only criterion allowing one to determine the affiliation of the tubercle bacillus to one type or another is their unequal pathogenicity for different species of animals. Typ. gallinaceus is highly pathogenic for birds and causes generalized tuberculosis in them with the formation of tubercles; in the rabbit, rat, and mouse, this type causes tubercular bacteremia without the formation of tubercles or with the formation of microscopic tubercles.
The guinea pig and man are practically insusceptible to infection by the tubercle bacillus typ. gallinaceus. Typ. humanus is pathogenic for man and the guinea pig and is slightly pathogenic for the rabbit. Typ. bovinus is pathogenic for cattle, man, the guinea pig, and the rabbit.
The different pathogenicity of typ. humanus and typ. bovinus for the rabbit serves as the method most often used for the differentiation of these two types. Good results are given by the method of Park and Krumwiede, which consists of injecting an emulsion of tubercle bacilli into the ear vein of rabbits weighing 1,500-2,000 g—two with 1 mg and two with 0.01 mg.
If the bacilli belong to typ. bovinus, the rabbits, even those that received 0.01 mg, die within 2-3 months with symptoms of generalized tuberculosis. A rabbit infected with typ. humanus does not die within this period; when killed, it shows no changes or limited changes upon autopsy, mainly in the lungs.
The question of the interrelationships of the types of tubercle bacilli cannot be considered resolved. At one time there were reports about the existence of strains transitional between typ. humanus and typ. bovinus; upon further study, they turned out to be mixed. Recently, facts have appeared that bring the bacilli of the three types closer together.
From a filtrate containing the tubercular ultravirus, one can, using the acetone method, obtain cultures of acid-fast bacilli (by inoculating organs). The strains obtained in this way are not homogeneous (Valtis and van Deinse), but represent a mixture of dissociants—moist S-forms and rough R-forms with a predominance of the former. Such a strain has properties that bring it closer to typ. gallinaceus.
During successive passages through the organism of guinea pigs, R-forms come to the fore, and the strain approaches the original typ. bovinus from which the ultravirus was obtained. From these and similar observations, the Calmette school concludes that the tubercular ultravirus represents the true tubercular virus, single and identical for all species of animals, and the type arises only during the further passage of the virus through the organism of one animal or another. Recently, Valtis and others have described strains transitional between typ. bovinus and typ. humanus.
Acid-fast saprophytes. The so-called tubercle bacilli of cold-blooded animals, which are classified by some researchers as true tubercle bacilli, apparently belong to acid-fast saprophytes, which are widely distributed in nature and enter the organism of fish, frogs, snakes, etc., from there (from water, from soil). Penetrating the animal organism in large quantities, these bacilli can cause changes simulating tubercular ones. Since the discovery of the tubercle bacillus, a large number of acid-fast saprophytes have been described by various researchers. Such are the smegma bacilli, bacilli found by L. Rabinowitsch in sputum in gangrene of the lungs, bacilli of nasal mucus (Laabs, Karlinski), earwax (Bienstock, Gottstein), Timothy grass bacilli (Moeller), manure bacillus (Moeller), milk bacilli (Petri, Rabinowitsch, Korn, Tobler, etc.) and oil, bacilli of distilled water, mucus of wind instruments, water taps, etc. Acid-fast saprophytes are grown without difficulty on ordinary nutrient media at a temperature from 15° to 38°. On liquid media, a film is formed; on solid media, a dry or moist coating, often pigment arises (red, yellow). The bacilli are acid-fast, but this property is less sharply expressed than in true tubercle bacilli. The question of the interrelationships of acid-fast saprophytes can now be considered resolved. Recent studies have established (Frey, Hagan) that these microbes are found everywhere in soil and water (Eichbaum). One can therefore think that there exists only one species of acid-fast saprophytes, but, by settling in various objects, these microbes acquire properties that slightly distinguish them from each other. Chemistry of the tubercle bacillus. Chemically, the tubercle bacillus is characterized by a high content of fatty and fat-like substances (Hammerschlag-26.2-28.2%, Schweinitz, Dorset-39.29-40.8%, Kressling-39.69%, Baudran-36.0-44.0%, Goris-38%, Johnson, Brown-43.5%, Model-18.8%). Qualitatively, these substances include neutral fats (esters of glycerin and fatty acids), waxes, sterins, phosphatides (esters of fatty acids and glycerin + phosphoric acid and a nitrogenous base), sulfatides. According to Much, the composition of the tubercle bacillus includes neutral fats, free fatty acids, lipoids, and wax-like substances (in small quantities). According to the data of American researchers (Sabin, Doan, Forkner), the lipids of the tubercle bacillus consist of substances insoluble in acetone and soluble in it. The first group includes phosphatide A-3, soluble in alcohol and ether, and waxes (purified and soft), extracted with chloroform. Substances soluble in acetone include glycerides. American researchers established the fact (pointed out, however, already by Much) of the different physiological action on the animal organism of various fatty fractions of the tubercle bacillus. Of greatest importance in this regard is phosphatide A-3, which itself exhibits the action characteristic of the tubercle bacillus as a whole (the ability to cause the formation of tubercles). The amount of carbohydrates in the tubercle bacillus, as well as lipids, varies depending on the composition of the nutrient medium and the type of bacilli. There are most carbohydrates in typ. humanus. The shell of the bacilli consists of cellulose (Hammerschlag), hemicellulose (Drieger, Marpmann), hydrocellulose (Auclair, Paris). Laidlaw and Dudley isolated from the tubercle bacillus a polysaccharide that precipitates the serum of immune animals in dilutions up to 1:6,000,000. According to Matius, the composition of the complex carbohydrate (polysaccharide) of the tubercle bacillus includes mannose and arabinose, as well as glucose, inositol, and galactose (Chargaff, Anderson). The protein fraction of the tubercle bacillus, according to Tamura, constitutes 57% of the weight of defatted bacilli; according to Johnson-84%. Most characteristic is the nucleoprotein included in the composition of the tubercle bacillus; the nucleic acid of tubercle bacilli was obtained for the first time by Ruppel and named by him tuberculinic acid; Johnson and Brown obtained 7.7 g of tuberculinic acid from 436 g of defatted dry bacilli. Johnson classifies the tuberculinic acid of the tubercle bacillus as the animal type of nucleic acids. Qualitatively, besides tuberculinic acid, globulins are characteristic for the tubercle bacillus; albumins are not very typical. Biologically, proteins cause a neutrophilic leukocytic reaction, as well as the accumulation of histiocytes phagocytizing neutrophils. Water in the tubercle bacillus (Hammerschlag) is on average 85.9%; inorganic substances-6.75-6% of the dry residue (Hammerschlag), 2.55% (Kressling), 1.92% (Dorset), 2.5% (Goris and Liot). Qualitative analysis gives the following: Schweinitz, Krauss and Dorset, Goris and Liot, Phosphoric acid, 55.23, 51.25, 0.84, 0.60, 10.10, 9.18, 5.27, 26.55, 6.92, 3.22, 9.03, 2.17.
Biology of the Tubercle Bacillus. Nutrition. The best source of carbon for the Tubercle Bacillus is glycerin. Glucose is an inferior substitute for it: growth on glucose media occurs less intensively. Levulose, lactose, and maltose yield even worse results. According to Long and Finner, there is a connection between the glycerin content in the medium and the amount of fatty substances in the Tubercle Bacillus. The source of nitrogen for the Tubercle Bacillus is protein decomposition products, with simple amino acids being of the greatest importance, from which the Tubercle Bacillus draws the amino group. Instead of amino acids, ammonium salts of inorganic and organic acids serve the same purpose (L. M. Model). Of the amino acids, asparagine gives the best results, as well as alanine and leucine. Needing glycerin and amino acids (or ammonium salts), the Tubercle Bacillus is otherwise not very fastidious regarding the choice of nutrient substrate. On synthetic nutrient media, they provide very good growth. Among such media, one can note the medium of Lowenstein and Pick: Asparagine 6.0, Amon. lact. 6.0, Natr. phosph. (neutr.) 3.0, NaCl 6.0, Glycerin 40.0, Aq. dest. 1,000 cm³. For the composition of the Sauton medium, see Bacteria, Calmette-Guérin bacillus. As for mineral nutrition, potassium, magnesium, sulfur, and phosphorus are necessary for the Tubercle Bacillus. Tubercle bacilli are aerobes and are characterized by a greedy affinity for oxygen. Growth in relatively anaerobic conditions is possible but extremely meager (Calmette, Vaudremer); in such conditions, atypical forms appear. Reproduction of the Tubercle Bacillus occurs by transverse division. Along with this, under certain conditions, the Tubercle Bacillus can arise from granules, both acid-fast and non-acid-fast (Morton, Kahn). Some researchers also point to the possibility of the reproduction of the Tubercle Bacillus by the budding of bacilli from granules that are part of the composition of tubercle bacilli. The Tubercle Bacillus is characterized by significant endurance in relation to various physical and chemical influences. Boiling kills them in 2 minutes; heating to 60°—in 1/2 hour. In a dried state, the Tubercle Bacillus tolerates 100° for 1/2 hour. Sunlight kills the Tubercle Bacillus in an emulsion in 10 minutes; ultraviolet rays under suitable exposure conditions—in 2 minutes. In sputum, under the influence of direct sunlight, the Tubercle Bacillus remains alive for 6-8 hours; in diffused sunlight—1-6 days. In a dark room, the Tubercle Bacillus can remain alive in sputum for 2-3 months and longer. 1.5% phenol kills the Tubercle Bacillus in 30 minutes, 0.5% cresol—in 60 minutes, 1%—in 50 minutes. In putrefying substrates, the Tubercle Bacillus remains alive for a long time. Methods of staining and cultivating the Tubercle Bacillus. For staining, methods based on acid-fastness, alkali-fastness, and iodophilia are used; methods of double staining are also resorted to. Of the methods based on acid-fastness, the Ziehl-Neelsen methods (see Ziehl-Neelsen method) and Spengler (C. Spengler) (see Sputum) have the greatest application. The Hermann method is also good (staining until vapors form in a mixture of three parts of a 1% solution of ammonium carbonate in distilled water and one part of a 3% solution of crystal violet in 95% methyl alcohol, decolorization for several seconds in 10% nitric acid, treatment with 95% alcohol until the preparation is pale blue, additional staining in a 1% solution of eosin or safranin). In the Cepede method, the preparation is stained with carbol-fuchsin, as in the Ziehl-Neelsen method; then follows simultaneous decolorization and additional staining with methylene blue in a solution of lactic acid (methylene blue in excess, pure lactic acid 20 cm³, Aq. dest. 80 cm³). The Gasis method is based on alkali-fastness. The preparation is treated with a mordant for 1-2 minutes while heating; the mordant is prepared as follows: a piece of corrosive sublimate the size of a lentil is dissolved while heating to a boil in a liquid of the following composition: crystalline eosin—1 g, absolute alcohol—5 cm³, distilled water—95 cm³; the liquid is decanted. Decolorization follows in the following solution: caustic soda—0.5, KI—1 g, 50% alcohol—100 cm³. The final step is staining for 2-3 seconds with the following solution: crystalline methylene blue—1 g, absolute alcohol—10 cm³, hydrochloric acid—0.5 cm³, distilled water—90 cm³. Of the methods based on iodophilia, the modified Much method of Gram (Gram-Much II) is most often used: 10 cm³ of a saturated alcoholic solution of methyl violet (B. N.) is mixed with 90 cm³ of a 2% solution of carbolic acid. Staining for 24-48 hours in the cold or while heating to a boil. Treatment with iodine (1 g of iodine, 3 g of KI, and 300 cm³ of Aq. dest.) for 5-10 minutes, washing with water, 5% nitric acid—1 minute, 3% hydrochloric acid—10 seconds, acetone-alcohol aa until complete decolorization, additional staining with an aqueous solution of safranin. Of the double staining methods, the Much-Weiss method should be noted: staining with a mixture of 3 parts carbol-fuchsin and 1 part methyl violet, used in the Much method, otherwise as in the Gram-Much II method, excluding additional staining. To obtain a pure culture of the Tubercle Bacillus, various methods are used: 1) infect a guinea pig with the material, kill it in the 3rd-4th week; extract the spleen, crush parts of it containing tubercles, and rub the resulting mass onto the surface of an egg medium; one can also pre-treat the spleen according to Gohn (see Sputum); 2) mix the material with 15-20% antiformin aa; the mixture is shaken, homogenized in an incubator, centrifuged, the sediment is washed 3-4 times with sterile water, repeating the centrifugation, the washed sediment is rubbed onto the surface of a solid medium (best of all, egg); 3) according to Petroff, the material (sputum) is mixed with a 4% solution of caustic soda aa, shaken, homogenized for 15-30 minutes in an incubator, centrifugation is performed for 10 minutes, 1-2 drops of normal HCl are added to the sediment, the sediment is inoculated onto Petroff's medium with gentian violet; 4) the Kitasato method is of historical interest, consisting of washing a lump of sputum sequentially in 7-10 Petri dishes with sterile physiological saline; 5) the Lowenstein-Sumiyoshi method gives the best results, especially in the Gohn modification (see Sputum). Regarding the media used for cultivating the Tubercle Bacillus, see Nutrient media, special nutrient media. To obtain pure cultures, egg media are of the greatest importance [see separate table (art. 19-20), fig. 15] (Lubenau, Petroff, Gohn, Petragnani, etc.); for maintaining cultures, glycerin potato, agar, broth, etc., are widely used. The Cumbari medium, used for obtaining non-acid-fast Tubercle bacilli, is prepared as follows. A. Potato is left for 24 hours in a liquid consisting of Aq. dest., 6% glycerin, 3% ethyl alcohol, and ammonia until a strongly alkaline reaction is achieved. The medium is prepared in the usual way. B. 400 g of potato mash are boiled with 500 cm³ of Aq. dest.; the mixture is filtered, strongly alkalized with ammonia, and boiled on a water bath until the ammonia is completely removed (neutral reaction). For cultivation, medium A is used first, and then the bacilli are subcultured onto medium B. For cultivating the Tubercle Bacillus from blood, Lowenstein proposed a medium of the following composition. To 150 cm³ of synthetic medium (monobasic potassium phosphate—1 g, sodium citrate—1 g, magnesium sulfate—1 g, asparagine—3 g, glycerin—60 cm³, distilled water—1000 cm³) add 6 g of potato flour and 12 cm³ of glycerin; the mixture is boiled for 1/4 hour, left to stand for 1 hour at 56° until dextrin is formed, 4 eggs are added and then one more, shaken, 5 cm³ of a sterile 2% solution of Congo red or malachite green is added, filtered, and poured into test tubes. Sweany and Evanoff recommend an egg medium prepared with veal; the veal is infused not with water, but with milk. Particularly good results are obtained if, instead of glycerin, 10% sterile cream is added to the medium. Experiments on animals (see Sputum). An animal exceptionally suitable for the recognition of Tuberculosis by experiment is the guinea pig. Upon infection with the Tubercle Bacillus, it develops a progressive loss of weight; after 6 weeks—3-4 months or more, the animal dies with symptoms of generalized Tuberculosis. Upon subcutaneous infection (the usual method of introducing the virus), the clinical picture of the disease consists of an infiltrate and ulcer at the site of injection, enlargement and cheesy degeneration of the regional glands, the same lesion of other lymph glands, especially the nearest ones, lesion of the spleen (enlargement and tubercles), liver (the same), and lungs. With other methods of infection, the picture changes depending on the method of introducing the virus. Smears of the affected organs reveal the presence of the Tubercle Bacillus [see separate table (art. 19-20), fig. 14]; with a long-standing process, the bacilli may be few or absent altogether. Sources of Tuberculosis infection.
The main source of infection for tuberculosis is a person sick with tuberculosis; taking into account that 9/12 of all cases of human tuberculosis are pulmonary tuberculosis, it is necessary to recognize that tuberculous sputum is of the greatest importance as a source of infection. The question of how tubercle bacilli from sputum enter the body of a healthy person has been resolved differently over the last 50 years. Koch, proceeding from his idea (as is known, erroneous) about the existence of spores in the tubercle bacillus, came to the conviction that the main importance in the spread of tuberculosis belongs to dust infection. This idea was developed by Koch's student Cornet into a coherent theory (the Koch-Cornet doctrine). According to this doctrine, sputum, drying out and turning into dust, disperses tuberculosis; the tubercle bacilli found in the dust retain their viability and, rising from the floor into the air (due to walking, drafts, etc.), become a source of infection. The danger of dust infection exists only in closed rooms; in the open air, the bacilli perish (putrefaction, the influence of light, etc.). In confirmation of the theory of dust infection, Cornet examined 147 samples of dust from rooms where tuberculous patients were located, and in 46 cases he discovered tubercle bacilli. Cornet's data were confirmed by other researchers, and in places of public use, tubercle bacilli were found only in railway carriages. Cornet found another confirmation of his theory in an experiment with a "carpet." The carpet was abundantly smeared with tuberculous sputum; the layer was dried and then the carpet was subjected to vigorous beating with brooms; guinea pigs placed in the resulting cloud of dust contracted tuberculosis. Flügge came out with sharp criticism against the Koch-Cornet doctrine. Relying on the work of his students, he showed that the conditions required by the Koch-Cornet theory for the realization of dust infection do not exist in everyday life. For tubercle bacilli from sputum to get into the air, the sputum must turn into the finest dust. This does not happen in practical life, because such a transformation requires several days, and during this time, even in the most uncultured environment, the sputum is removed from the floor in one way or another. As for the experiment with the "carpet," its conditions are such that they cannot be encountered in everyday life. According to Flügge, the main method of infection is not dust, but droplet infection. Its essence boils down to the fact that when coughing, talking, laughing, or sneezing, a person scatters around themselves the smallest droplets of mucus containing tubercle bacilli in tuberculous patients. By placing glass slides at a certain distance from the mouth of a coughing tuberculous patient, it is easy to verify (staining, experiment on an animal) that in 80% of cases there are tubercle bacilli in the droplets, sometimes in very large quantities (within 1/2 hour at a distance of 40-80 cm, over 400). That droplets can cause tuberculosis is proven by direct experiments by Heymann, who placed guinea pigs in cages in the immediate vicinity of the mouth of a coughing patient, and some of them (admittedly, a small number) contracted tuberculosis. Droplet infection occurs only if the distance between the coughing tuberculous patient and the healthy person is no more than one meter. The theory of droplet infection quickly supplanted the Koch-Cornet doctrine. However, this theory could not withstand the facts either, and at the present time, the theory of Koch-Cornet and Flügge has been replaced by a new theory, synthesizing the first two; this new theory can be called the Chausse-Lange theory. The pioneer was Chausse, followed by Lange. The main objection raised by these researchers against Flügge's doctrine is that the droplets usually have significant dimensions; in any case, they are much larger than 20 microns; meanwhile, only small droplets, less than 20 microns in size, can penetrate into the lungs, as the studies of Chausse and Lange show; thus, only in rare cases can droplets be the cause of pulmonary tuberculosis. In contrast, dust particles have a very small size and are usually smaller than 20 microns. It is therefore incomparably easier to become infected with dust than with droplets; however, the dust of Chausse-Lange is not the dust of Koch-Cornet. According to Chausse and Lange, the main source of dust is the droplets scattered by the tuberculous patient. Separating from the patient, they settle on surrounding objects and, due to their size, quickly dry out, turning into dust. Thus, the greatest danger is posed by the patient's linen, his bedding, etc. Chausse and Lange prove their doctrine with a whole series of very convincing experiments. Of these, only one can be cited: guinea pigs were placed in a patient's ward by his bed, but in his absence, at the time when cleaning and shaking of bedding was being carried out; some of the guinea pigs contracted tuberculosis. Thus, the main importance in the spread of tuberculosis belongs to dust infection, with droplets being the source of the dust. Moist droplets play a secondary role in the spread of tuberculosis. Compared with sputum, other secretions of a tuberculous patient have limited importance as sources of infection. Tubercle bacilli can be found in breast milk; according to the studies of Calmette and others, they are very often present in feces in the absence of intestinal tuberculosis, since bile and feces are normal secretions, by using which the body rids itself of tubercle bacilli; urine also in certain cases (not often) can contain tubercle bacilli in the absence of kidney lesions; finally, according to Piery, tubercle bacilli can also be found in the sweat of patients (in 30.76%, according to this author). It goes without saying that with lesions of the corresponding organs, urine, feces, milk, pus, etc., can contain very large quantities of tubercle bacilli. Thus, all secretions of a tuberculous patient can serve as a cause for tuberculosis infection, but compared with sputum, all these sources have a very secondary importance. Besides humans, a source of tuberculosis infection is cattle, since the milk of tuberculous cows very often contains tubercle bacilli. The question of what role cattle play in the epidemiology of human tuberculosis is decided on the basis of how often the bovine type is the cause of tuberculosis in humans. According to extensive research conducted in this direction in England and America (Griffith, Park, and others), approximately one-fourth of cases of tuberculosis in children aged 0 to 15-16 years are caused by bovine type bacilli. According to Park, out of 1,038 cases, the bovine type was detected in the age from 0 to 5 years in 26.5%, from 6 to 16 in 25%, and older in 1.31%. The forms caused by bovine type bacilli are predominantly tuberculosis of the abdominal organs, lymph nodes, and others. The number of cases of pulmonary tuberculosis in adults caused by bovine type bacilli is calculated in a few units. Thus, for children, there is a real danger of contracting tuberculosis through infection with bovine type bacilli. This danger in some countries (due to obvious living conditions) is especially acute. Thus, in Scotland, according to Fraser, the percentage of children infected with the bovine type reaches 70 and higher. Bovine type bacilli enter the child's body mainly from milk; along with it, the role of other dairy products should not be underestimated; thus, according to Eber, in milk in a large city, tubercle bacilli were detected in 10.5%, in butter in 12%, and in cream in 6%. Compared with cattle, other animals occupy a very small place in the epidemiology of human tuberculosis. Pigs suffer from tuberculosis (bovine type), but their danger to humans is very small, since tuberculosis in pigs is closed and benign. In goats, tuberculosis is rare. Parrots suffer from tuberculosis (human type). Furthermore, cases of tuberculosis in cats are known. A frequent disease is tuberculosis in chickens. For humans, this disease does not present a great danger, since it is caused by avian type bacilli, to which humans are little susceptible. In several (over 10) cases, this microbe was the cause of tuberculosis in humans, and apparently, the source of infection was chicken eggs. Portals of entry of infection in humans with tuberculosis. By the law of localization, one understands the regularity by which tubercle bacilli, penetrating into an animal organism, cause specific changes at the site of entry. In such a form, this law does not correspond to reality. At the present time, it is well known that tubercle bacilli can penetrate into the body without causing any changes either on the skin or on the mucous membranes; such penetration of tubercle bacilli into the body is more the rule than the exception. In view of this, the law of localization should be understood in the sense that tubercle bacilli, penetrating into the body, cause specific changes in the regional lymph nodes closest to the site of entry. In this modified form, the law is valid in essence for guinea pigs, but even in these animals, the introduction of tubercle bacilli is not always (Oerskow) accompanied by a lesion of the regional nodes. The virulence of the tubercle bacilli plays a large role in this regard. In relation to humans, the localization law has a conditional, limited significance. In view of this, from the fact of a lesion of one or another group of lymph nodes, in most cases, one cannot draw a conclusion regarding the entry of bacilli specifically at that given place. A person's illness with tuberculosis can be the result of intrauterine or extrauterine infection. The existence of hereditary tuberculosis in the proper sense of the word cannot be considered proven.
There are, in essence, no data that would speak to the possibility of infection of the ovum or spermatozoon by tubercle bacilli. But even if one assumes the possibility of infection of a spermatozoon by the tubercle bacillus, there is every reason to think (Gartner) that a fetus resulting from fertilization by such a spermatozoon would prove nonviable. Thus, when speaking of the hereditary transmission of tuberculosis, one has in mind intrauterine infection by tubercle bacilli passing from the maternal organism into the organism of the fetus through the placenta. It is impossible to deny the possibility of the occurrence of tuberculosis in this way. One can, however, assert that intrauterine infection with tuberculosis represents a very rare phenomenon. If tuberculosis frequently arose by way of intrauterine infection, then congenital tuberculosis—the birth of a child with undoubted clinical signs of tuberculosis—would represent a very common phenomenon. Meanwhile, to this day, there are only a few dozen cases of such congenital tuberculosis in the literature, and not all of these cases are reliable. The results of separating children from their tubercular mothers immediately after birth (Grancher system), as well as similar results from separating newborn calves (Bang), speak against the frequency of intrauterine transmission of tuberculosis. In both cases, the newborns turn out to be spared from tuberculosis. The discovery of the tubercular ultravirus strengthened the position of proponents of placental transmission of tuberculosis. If the ultravirus passes through a porcelain filter, then there is reason to think that the placenta cannot be a barrier to the tubercular ultravirus. And indeed, soon after the appearance of works on the ultravirus, reports appear stating that both experiment and observations on humans allow one to think about the frequency of fetal infection by the tubercular ultravirus (Calmette, Couvelaire, et al.). A doctrine is being created that congenital cachexia, sometimes observed in newborn children, represents a disease analogous to the disease developing in guinea pigs after their infection with the ultravirus. Under the influence of the doctrine of the ultravirus, some proponents of intrauterine infection (Lumiere) went so far as to deny the extrauterine origin of tuberculosis. Despite this, there are no grounds to assert that the existence of the tubercular ultravirus changes in any way our understanding of the rarity of intrauterine infection. As indicated above, the tubercular ultravirus causes a disease in guinea pigs that ends in complete recovery after 1–1.5 months; thus, even if the ultravirus frequently passed from the maternal organism into the organism of the fetus, a rapidly passing mild disease with an outcome of complete recovery would develop in the child. On the other hand, the placenta is by no means a filter that lets everything pass through it. According to physiological data, colloidal substances related to the proteins of the fetus pass easily through the placenta, while substances foreign to the organism of the fetus are retained. Antitoxin passes (Ramon, Grasset), while toxin does not pass (or passes in an insignificant quantity). Based on this, one can expect the passage of the tubercular ultravirus into the organism of the fetus only in the case where there is a lot of it in the mother's organism. Such cases are not frequent, since a large quantity of the ultravirus is present only in the case of an active, progressing process. Thus—just as before the discovery of the ultravirus—it is necessary to maintain the point of view that tuberculosis represents a contagious disease arising by means of extrauterine infection. Intrauterine infection can take place, but its practical significance is very small. The portals of entry for tubercular infection can be the skin, mucous membranes, and alveolar pulmonary epithelium. Practically, the question of how pulmonary tuberculosis arises is of the greatest importance. The majority of researchers hold the point of view that tuberculosis of the lungs arises as a result of the penetration of tubercle bacilli with inhaled air into the pulmonary alveoli. Proof of this is the fact that the primary affect usually consists of a focus in the lungs and in the corresponding bronchial glands. According to Ghon, the pulmonary focus is always older than the focus in the gland. In experimentation, the task of obtaining pulmonary tuberculosis by way of inhaling tubercle bacilli appears easily solvable. In contrast to this point of view, Calmette believes that pulmonary tuberculosis arises as a result of alimentary infection. Calmette depicts this process in the following way. Having penetrated into the digestive tract, the tubercle bacilli pass through the mucous membrane without causing any changes at the site of entry. The bacillus, phagocytized by a neutrophilic leukocyte, enters a lymphatic vessel, then into a mesenteric gland, the ductus thoracicus, and finally into the lungs. Here it gets stuck in a pulmonary capillary, the lumen of which is smaller than the diameter of the leukocyte, and gives rise to a tubercular focus. In confirmation of the alimentary origin of pulmonary tuberculosis, the fact is usually cited that in experimentation it is possible to cause lung damage in an animal by feeding it tubercle bacilli. While not denying this fact, established by the experiments of Calmette, Orth, L. Rabinowitsch, and others, it is necessary, however, to point out that for the success of such an infection, very large quantities of bacilli are required (Findel, Reichenbach, and Alexander), whereas the inhalation of very small quantities of them (Chaussé, Lange) is sufficient to cause lung damage. This fact is of great importance for resolving the question, since (Lange) humans are usually infected by small quantities of bacilli. The cruel Lübeck experiment also serves as proof that upon infection per os, tuberculosis of the abdominal organs usually develops, and not of the lungs. (In Lübeck in 1930, 252 children, instead of the BCG vaccine, received due to an error per os in three doses virulent tubercle bacilli in a total amount equal to 1–1 1/8 billion live bacilli. 199 children fell ill, and in all of them, excluding one, only tuberculosis of the abdominal organs developed; in one child, along with tuberculosis of the abdominal organs, there was also tuberculosis of the lungs.) Other mucous membranes (conjunctiva of the eyes, mucosa of the genital organs, pharyngeal tonsils) can in certain cases be the site of entry for tubercular bacilli. Libin established the possibility of the introduction of tubercle bacilli through the pulp and canal of carious and gangrenous teeth. The significance of this route in the epidemiology of human tuberculosis, however, is not great. Immunity to tuberculosis. Natural congenital immunity (resistance) to tuberculosis is widely distributed among animals; there are species (horse, dog, rat, white mouse) possessing high, although not absolute, resistance to tuberculosis. Congenital resistance is also inherent in humans (Lange, V. Lyubarsky). The following facts speak to this: 1) the relatively low incidence of tuberculosis in children despite the ubiquitous distribution of tubercle bacilli in conditions of urban life; 2) the experiments of Selter, who vaccinated children with virulent tubercle bacilli in doses from 12 to 10,000 bacilli and never once obtained the disease in them, etc. The degree of congenital resistance is not uniform. Acquired immunity to tuberculosis has the character of infectious immunity; it arises as a result of infection with tuberculosis and exists as long as this infection is present, i.e., as long as there are tubercular changes and tubercular bacilli in the organism. According to Lange, immunity is the more valid and pronounced, the more active the tubercular process and the more virulent the tubercle bacilli present in the organism. According to Selter, immunity is most pronounced in the presence in the organism of a latent, slightly active focus or a focus in the stage of healing. Finally, according to Calmette, for the existence of immunity, the presence of tubercle bacilli in the organism is sufficient, even if they have not caused specific changes (latent microbism). Experiments speak in favor of Lange's point of view. With the existence in the organism of a slightly active focus or only bacilli, immunity is present, but its degree is not great. Being connected with the presence of tubercular tissue in the organism, immunity is at the same time connected with allergy, i.e., with increased sensitivity to tuberculin. An organism immune to tuberculosis usually reacts to tuberculin, and in any case, every organism that reacts to tuberculin possesses at the same time a certain degree of immunity to tuberculosis. It is impossible, however, to deny the possibility of the existence of immunity even in the absence of sensitivity to tuberculin (Calmette); such cases are not frequent. An organism immune to tuberculosis is insusceptible to superinfection; thus possessing immunity to foreign bacilli, the organism remains susceptible to its own bacilli that penetrated into it during infection. The highest degree of immunity exists in the case where the bacilli of superinfection are destroyed in the organism without causing any changes. If immunity is not sharply pronounced, the bacilli of superinfection cause specific changes; they differ, however, qualitatively and quantitatively from the changes formed during primary infection. The existence of acquired immunity to tuberculosis is proven by experiment, which shows that the infection of an animal (cattle, laboratory animals) with tubercle bacilli makes it insusceptible to subsequent infection—on the condition, of course, of correct dosage, etc. The doctrine of acquired immunity, developed by Behring and Römer and bearing their name, retains its validity also in relation to humans.
Proof of its existence in humans is provided by pathological-anatomical data (the existence of tuberculous foci in almost all adult city dwellers), the results of determining tuberculin sensitivity (almost the entire adult population reacts to tuberculin), and others. Many are inclined to explain the different course of Tuberculosis in peoples coming into contact with tubercle bacilli for the first time, and in peoples among whom Tuberculosis has existed for a long time, by acquired immunity. In the former, acute forms predominate with frequent outcomes in acute miliary Tuberculosis and death ("normal" Tuberculosis), while for the latter, isolated lung lesions in the form of chronic pulmonary consumption without the involvement of lymphatic glands, which is mandatory for normal Tuberculosis, are characteristic ("modified" Tuberculosis). Acquired immunity has a certain influence on the clinical picture of Tuberculosis, but congenital resistance and, in particular, social factors have an even greater influence on it. In particular, pulmonary consumption can develop not only in an organism possessing acquired immunity to Tuberculosis, but also in an organism that does not possess such immunity. The significance of social factors is revealed by the fact that acute forms of Tuberculosis can arise in those immune to Tuberculosis in the presence of unfavorable social conditions (V. Lyubarsky and others), and on the other hand, chronic pulmonary consumption can develop in the presence of good social conditions in individuals who do not possess acquired immunity to Tuberculosis (Kleine). As the infection rate of the population with Tuberculosis increases, the number of those immune to Tuberculosis also grows ("natural immunization"). The tendency of some researchers (Sanarelli) to explain the decline in mortality from Tuberculosis by this does not find full justification in the facts; however, it is undoubtedly the case that natural immunization of the population is one of the factors lowering mortality from tuberculosis. Mechanism of immunity to Tuberculosis. The basis of congenital resistance to Tuberculosis lies in the increased ability of the organism to destroy tubercle bacilli invading it. As studies by Corper, M. Lurie, and others have shown, the animal organism possesses the ability to destroy tubercle bacilli, although it takes several months for a non-immune organism to do this, and not all bacilli are destroyed. In different organs, the process of destruction of bacilli occurs with varying degrees of intensity and speed. In the liver and spleen, bacilli perish faster than in the lungs. In an organism resistant to Tuberculosis, the death of bacilli occurs faster than in a non-immune one; furthermore, all bacilli, or in any case the majority, perish. The destruction of bacilli is apparently connected with the presence (or appearance) in the organs of substances (Lyubarsky, Model) that inhibit the growth of tubercle bacilli. Along with the destruction of tubercle bacilli, the organism rids itself of them by excreting them with bile and with faeces. In a resistant organism, this process occurs with greater intensity than in a non-immune one. In an organism possessing acquired immunity to Tuberculosis, antibodies (agglutinins, precipitins, etc.) appear (or may appear). Such an organism furthermore becomes allergic. As for antibodies, they are not a factor of immunity. There is no parallelism between the content of antibodies and immunity; they may be absent when immunity is present and be in excess when it is absent. The question of the relationship between allergy and immunity cannot be considered resolved. According to Krause (A. K. Krause), "immunity is a function of allergy." According to Calmette, allergy and immunity represent states that are different and independent of each other. According to Maragliano, "allergy is most closely connected with the evolution of the process of immunity." According to Rich, a sharply expressed immunity corresponds to a weakly developed allergy and vice versa. Thus, at the present time, when neither the essence of immunity nor the nature of allergy is yet known, one can speak only of a connection between these states, without resolving the question of their actual relationships. Immunity reactions. Agglutination has no practical significance in the diagnosis of Tuberculosis, because it lacks strict specificity (it has been observed in pneumonia, typhoid fever, etc.) and, furthermore, it is obtained both in active forms of Tuberculosis and in inactive ones, sometimes proving negative in cases of active Tuberculosis. The methodology was developed by Arloing and Courmont, who proposed for its performance a so-called homogeneous culture (tubercle bacilli causing uniform turbidity of the broth). Precipitation has also not gained practical significance. The existence of bacteriolysins is controversial; the serum is in any case devoid of lytic action. The complement fixation reaction has a certain practical significance. Its success depends to a significant degree on the antigen. The Besredka antigen consists of a 4-day culture of tubercle bacilli on his egg medium (see Culture media), killed at 115° and centrifuged. An emulsion of bacilli in a specific amount of physiological saline is the antigen. The Boquet-Negre antigen is prepared in the following way. A six-week culture of tubercle bacilli on glycerin broth is sterilized for 30 minutes at 120° and filtered through paper; the bacterial bodies are washed on the filter with distilled water and dried. Extraction with acetone (1 cm3 per 0.01 of bacilli) follows for 24 hours, then re-drying and extraction with 99° methyl alcohol (1 cm3 per 0.01 of bacilli) for 12 days at 37°. Shake. Filter. The liquid constitutes the antigen. Petrov uses a glycerin extract of dried and powdered tubercle bacilli (a 21/2% dilution in physiological saline). Wassermann treated the bacilli with tetralin, washed them repeatedly with ether, and dried them. Lecithin in the amount of 0.2% was added to the resulting yellow-white powder. The powder remains with the lecithin for 1 hour. Centrifugation follows; the sediment constitutes the antigen. The Witebsky, Klingenstein, and Kuhn antigen is obtained by treating dried tubercle bacilli with hot alcohol, extracting the sediment with hot pyridine, and purifying with acetone; the sediment is suspended in a 10% solution of benzene; lecithin is added to the suspension. The diagnostic value of the complement fixation reaction is as yet small.
V. Lyubarsky. III. Pathological anatomy. The pathological anatomy of tuberculosis at the present time, in the sense of an etiological understanding of the fundamental changes in tuberculosis, is strictly unitary. It is clear to us that the fundamental changes, whatever morphological expression they may have, are connected with the introduction of the tubercle bacillus into the tissue. It is no less clear that the changes arising upon the introduction of the tubercle bacillus into the tissue represent an inflammatory reaction of the tissue. This reaction, like any inflammatory reaction, represents a combination of alterative, exudative, and proliferative (productive) changes in the tissue. However, the combination of alteration, exudation, and proliferation in this case is very different, which gives extreme diversity in the morphological and dynamic expression of the tuberculous process. This diversity essentially has at its base, mainly, the predominance in individual cases of either the alterative, the exudative, or the productive moment; the reasons for this predominance of one factor or another in the inflammatory tuberculous reaction are very complex, as they concern not only the peculiarities of the pathogen but also the diverse properties of the affected organism (see below). It goes without saying that such an assessment of the morphological expressions of tuberculous changes is far from both the dualism and the primitive unitarism of earlier authors. If, in the etiological assessment of tuberculous changes, we hold to a unitary point of view, then in assessing all the pathogenetic conditions for the emergence of one or another morphological expression of the tuberculous process, the modern point of view, in the just expression of Pagel, is synthetic. Pathological changes in tissue occurring upon the introduction of the tubercle bacillus into it can, first of all, present some differences depending on the character of the tissue. The structure of the organ and even which of its tissues has come into contact with the tubercle bacillus leaves its imprint on the type of reaction, i.e., on the morphology of the tuberculous process and on its course. However, wherever tuberculous changes arise, they always initially show a tendency to express themselves in a limited nodular change, which has received the name of tubercle, nodule [see separate table (col. 19-20), fig. 16; separate table (col. 35-36), fig. 1, 2 and 5; separate table (col. 111-112), fig. 4] (tuberculum, French follicule tuberculeux). To the naked eye, a fresh nodule appears as a gray, translucent, round nodule, usually slightly bulging on the surface of the organ and on the plane of its cross-section. The size of the nodule can be different; the usual millet-seed-like, miliary tubercle (tuberculum miliare, French granulation miliaire) corresponds to the size of a millet seed (milium—millet seed), but nodules can also be of smaller sizes, down to microscopic dimensions inaccessible to the naked eye. A gray translucent nodule larger than a millet seed is very rare; larger nodules are distinguished by the fact that their central part has a yellow tint and is opaque; in this case, often, for example in the lungs, such larger nodules are not round but angular. In the kidneys, tubercles are generally very indistinctly contoured and appear as pale spots. The development, or histogenesis, of the nodule has been studied both experimentally and on human material by a very large number of researchers and can be presented in the following form. Tubercle bacilli, having entered the tissue and multiplying in it, cause damage to tissue elements (the alterative phase of nodule formation), which can have different degrees and extent; sometimes it is so insignificant that it is elusive under the microscope, sometimes focal necrosis of the organ tissue is visible with the disintegration of cells and intercellular substance, with karyorrhexis of nuclei. Very soon, hyperemia of small vessels, the release of exudate, and the emigration of leukocytes and lymphocytes (exudative phase) are discovered at the site of damage and next to it, which in most cases is short-lived and weakly expressed. Immediately, the multiplication of local cells begins (productive phase), from which large, plate-like cells with homogeneous, light protoplasm and a vesicular nucleus are formed; these cells, due to their similarity to flat epithelium, have received the name 'epithelioid' cells. In most cases, the entire gray nodule is formed from these epithelioid (or, according to Hubschmann, 'tuberculous') cells; only at its periphery is there some quantity of small round cells of the lymphocyte, polyblast, rare plasma cell, and polymorphonuclear leukocyte type. Extremely characteristic for the tubercle is the presence in its central part, among the epithelioid cells, of one or two multinucleated giant cells with the arrangement of numerous nuclei toward the periphery of the cell body. Due to the fact that these giant cells with their peculiarities were first described in detail by Langhans, they are often called Langhans giant cells. Between the elements of the nodule, one can discover the finest fibrils ('reticulum' of the nodule), which were previously attributed by some to fibrin released between cells, and by others to connective tissue. However, at the present time, on the basis of good impregnation of these fibers with silver, it has been finally established that they belong to argyrophilic connective tissue fibrils. The question of the origin of the elements of the nodule cannot be considered fully clarified. There is no doubt that in lymph nodes, epithelioid cells are formed from cells of the reticular tissue, in the liver (inside its lobules)—from the endothelium and Kupffer cells of the capillaries; there is quite convincing data that the endothelium of small blood and lymph vessels takes an active part in the formation of the elements of the nodule; the same must be said about the fibroblasts of the connective tissue. During the formation of a tubercle among epithelial complexes, for example, inside pulmonary alveoli, inside the seminiferous tubules of the testicle, apparently, the epithelium can also give rise to the formation of epithelioid cells. Finally, in recent times, the old view of Metchnikoff regarding the formation of all elements of the nodule from wandering cells, macrophages, is being put forward again; such an idea is expressed, among others, by Maximow, Timofeevsky, and Benevolenskaya on the basis of experiments with obtaining nodules in tissue cultures; in addition, American authors (Sabin et al.) have recently become convinced of the formation of nodules from monocytes emigrating from vessels. All this, taken together, forces one to come to the conclusion that the epithelioid cells of the nodule can be formed not from one particular type of cell, but from diverse cellular elements (reticular cells, endothelium, fibroblasts, macrophages, monocytes, epithelium); in other words, the formation of epithelioid cells is a definite form of reaction to the tubercle bacillus, characteristic of various cellular elements. Giant cells are formed from epithelioid cells under the condition of amitotic division of the cell nuclei without division of its growing body. This process, carefully traced by Herxheimer and Roth, is connected with peculiar necrobiotic changes in the protoplasm of these cells, sometimes noticeable in the central part of the cell in the form of a different degree of its staining, liquefaction, or adsorption of small lime granules. Giant cells can also be formed directly from the endothelium of capillaries (during their abortive budding). The small round cells of the periphery of the nodule relate to manifestations of a banal inflammatory reaction. At the beginning of the development of the nodule, there are hyperemic vessels in this marginal zone of it and often phenomena of inflammatory exudation. Apparently, this peripheral zone of the nodule, which can be expressed to one degree or another, must be attributed to the manifestations of so-called perifocal, collateral inflammation (see below). The reticulum of the nodule represents partly preserved fibrils of the pre-existing tissue; however, a significant part of the argyrophilic fibrils is newly formed among the epithelioid cells. In general, the cellular elements of the nodule and the reticulum represent an organized tissue corresponding to granulation tissue; consequently, the nodule, the tubercle, represents a tuberculous granuloma (see separate table, fig. 4), which belongs to infectious granulomas. Usually, the nodule is characterized as an avascular granuloma; however, the avascularity of the nodule is something relative. Indeed, in the part of the nodule consisting entirely of epithelioid cells, vessels are as a rule absent; this is explained by the fact that the elements of the walls of the capillaries that were present here earlier (possibly also newly formed ones) participate in the formation of epithelioid and giant cells, and thus the vessels are, as it were, consumed, expended on the formation of the nodule. In those parts of the periphery of the nodule where there are few or no epithelioid cells, one usually observes...
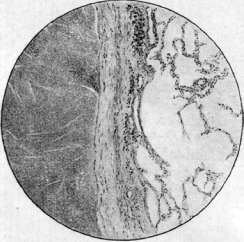
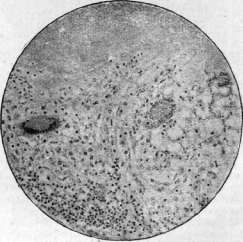
Figure 1. General view of tuberculous granulations; between the tubercles are layers of fibro-scar tissue. Figure 2. Tubercle; in the center is a giant cell; around it are epithelioid cells; on the periphery are lymphoid cells. Figure 3. Fibro-scar capsule, delimiting a caseous focus of the lung. Figure 4. Productive tuberculosis; coalescing granulomas of epithelioid, lymphoid, and giant cells; above is caseous necrosis.
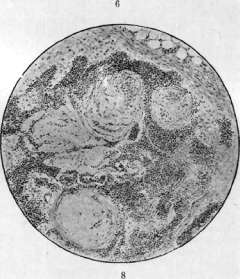
Figure 5. Tubercular meningitis; tubercles and diffuse infiltrates in the pia mater; lymphoid infiltrates along the vessels. Figure 6. Chronic pulmonary tuberculosis with exacerbation; sclerosis of the lung tissue in the upper half of the specimen; exudative phenomena below. Figure 7. Tubercular focus in the adrenal gland. Figure 8. Healed hyalinized tubercles in a lymph node. Figure 9. Healed primary pulmonary affect: a—fibrous capsule around the affect (with coal deposits); b—trabeculae of bone tissue with bone marrow (c); d—caseous center of the affect. Vessels; this is easy to verify in cases where there is a group of closely situated but not fused tubercles; in their fusing peripheral zones, there are always vessels, often highly engorged with blood; experiments with injection of vessels show the same thing. Everything stated above about the structure and development of tubercles refers to the most frequent and, one might say, typical type of tubercle, called the epithelioid tubercle; it is characterized by the short duration and weak expression of the alterative and exudative phases, and the rapid onset and predominance of the productive phase in the form of an epithelioid cell granuloma. However, the course of tubercle development does not always follow this path. In some cases, the first, alterative phase is extremely sharply expressed and prolonged, remaining for some time in its initial state without the addition of subsequent phases, in particular without any hint of productive changes. Such tubercles are distinguished by the fact that they do not bulge in the form of grains, but appear as miliary yellowish-gray spots. Under a microscope, they turn out to be small foci of tissue necrosis with karyorrhexis of the nuclei, interspersed among normal tissue; the fact that this is a case of primary tissue necrosis, and not secondary caseous necrosis of an already formed tubercle, is proven by the fact that the necrosis always uniformly captures the entire area of the tubercle without any hint of proliferation at its periphery, and especially by the fact that in the necrotic mass, particularly when the specimen is impregnated with silver, the outlines of the tissue of the given organ are clearly visible. Such necrotic, or toxic, tubercles can be scattered in large numbers throughout all organs, which is characteristic of that form of generalized miliary tuberculosis that is distinguished under the name of tubercular sepsis (see below). In other cases, after the alterative phase, which may be clear or barely noticeable, there is observed an exudation of serous or, more often, serofibrinous exudate with an accumulation of lymphoid cells and, less frequently, leukocytes. In such exudative tubercles [see separate table (col. 35-36), fig. 6 and separate table (col. 19-20), fig. 18], to which belong those tubercles that were previously called small-cell or lymphoid tubercles, a productive phase is subsequently revealed (see separate table, fig. 4); however, here it is expressed in the formation of a granulation wall of characteristic structure (epithelioid cells, Langhans giant cells, etc.), surrounding the area of exudation, which in this process transitions into caseous necrosis. Along with these three types of tubercles, intermediate transitional types can also be observed. When staining sections for tubercle bacilli, the latter are found in particularly large numbers in necrotic tubercles, and somewhat fewer in exudative tubercles. In epithelioid tubercles, bacilli are usually few. The bacilli lie both inside cells and outside them; their preferential localization in giant cells, as was usually mentioned earlier, is not noted. From the above, it is clear that a tubercle, which represents the initial change at the site of the introduction of the tubercle bacillus into the tissue, can have different structures and courses. In some cases, the productive phase predominates in it, in others, the process seems to freeze at the alterative phase (tissue necrosis), and in others, exudation dominates the process. The pathogenetic basis for such a diversity of structure and course of tubercles is not exhausted by any single cause. First of all, the assumption that might arise regarding the significance of the time of development of the tubercle, i.e., that phenomena of alteration and exudation predominate in a fresh tubercle, and productive changes in an older one, must be rejected. Based on the description of the development of tubercles given above, it is clear that this is not so. Furthermore, for example, in cases of generalized miliary tuberculosis, it is easy to see that one type of tubercle or another is not related to the duration of the disease. In particular, Korteweg became convinced that with exactly the same time separating the moment of death from the outbreak of generalized miliary tuberculosis, the tubercles in some cases bear a clear predominance of exudative manifestations, while in others they turn out to be entirely productive and epithelioid throughout. The character of the site, the soil of its development, i.e., the structure of the organ and tissue in which the tubercles develop, has much greater significance than the age of the tubercle. For example, it can be noted that sometimes, with the simultaneous presence of many tubercles in the liver, those that form in the interstitial connective tissue bear all the signs of productive, epithelioid tubercles, whereas in those located inside the lobules, among the parenchyma, alteration in the form of necrosis of the parenchymal elements predominates. In the lungs, due to the peculiarity of their structure (porosity, thinness of the alveolar septa, thin-walled capillaries), exudation occurs very easily. Thanks to this, purely productive epithelioid tubercles are encountered relatively infrequently in the lungs; usually, exudation into the alveoli begins very early, and often the tubercle turns out to be nothing more than a group of alveoli filled with serous-fibrinous exudate (miliary tubercular pneumonia); productive changes may subsequently develop at the periphery of such a focus. However, the character of the structure of the soil gives only a certain shade to the structure and course of the tubercle and is not decisive in this sense. Again, in cases of general dissemination in generalized miliary tuberculosis, it is easy to see that along with some difference in the type of tubercle depending on the organ, one or another variant of structure characteristic of all tubercles of the given case can still be observed. In particular, in the lungs as well, either productive tubercles or exudative ones in the form of foci of miliary pneumonia can be observed in different cases. Knowing that a tubercle represents an expression of an inflammatory reaction, the picture of which always depends on the properties of the pathogen and the properties of the macroorganism reacting to the pathogen (see Inflammation), it is easy to understand that this is also applicable to the tubercle. The idea that the main reason for the predominance of either productive or exudative changes in a tubercle lies in the properties of the pathogen has its source in the experimental studies of Baumgarten, Cohnheim, and others at the end of the 19th and beginning of the 20th centuries; it was established that the tubercle bacillus itself causes only a productive reaction, while its toxins cause alteration and exudation. Therefore, it was assumed that a massive infection with virulent (toxic) bacilli produces a predominantly alterative or exudative process, whereas an infection with a small number of bacilli, which secrete few toxic products, results in a predominantly productive process. This view was further supported by the fact that when staining sections for tubercle bacilli, the latter are found in the greatest numbers in necrotic and (usually somewhat fewer) predominantly in exudative tubercles; in productive epithelioid tubercles, they are usually found in very small numbers. The indicated point of view regarding the exclusive significance of the character of the infection for the development of a certain type of tubercle is maintained by some to this day (Kaufmann, 1931); in particular, data have recently been put forward (Winn et al.) that necrotic or toxic tubercles are caused by the introduction of avian tuberculosis bacilli into the human body. Based on all the data of modern teaching on inflammation, one cannot fully agree with the above point of view; if the character of the infection has an undoubted significance for the character of the inflammatory process, then the reactive capabilities of the organism have no less significance. To one and the same cause in a quantitative and qualitative sense, i.e., the pathogen, two different organisms, and even one and the same organism, but in different periods of its life, can react differently. All this is fully applicable to tuberculosis and to the different types of tubercles. As early as 1904, Abrikosov pointed out that in generalized miliary tuberculosis in weakened and cachectic individuals (with severe anemias, cancerous cachexia, etc.), the tubercles very often have a necrotic type. Saltykov notes that in individuals with a so-called fibrous constitution, tuberculosis as a rule has a sharply productive character and the tubercles are always epithelioid, with a tendency toward rapid fibrosis. On the basis of all this, one can think that the alterative (necrotic) type of tubercle, its predominantly exudative and predominantly productive types, to a significant extent represent reflections of different settings in the reactive manifestations of different organisms (for more details on this, see below).
The ratio of the number of tuberculous bacilli to the nature of the process in a tubercle may be a phenomenon of a sequential order; it is clear that in the necrotic mass, in the exudate, tuberculous bacilli multiply significantly faster than among the cells of an epithelioid tubercle. Bacilli of avian tuberculosis have pathogenic significance for humans probably in exceptional cases, and to explain all cases with necrotic tubercles by avian tuberculosis infection would be a great stretch. The outcome of tubercles is to a significant degree connected with the type of their structure and development. Extremely characteristic for both tubercles and larger tuberculous foci is the outcome in cheesy, caseous degeneration (degeneratio caseosa), called for short caseosis, caseification. This is a peculiar necrobiotic process, expressed by the fact that the center of a gray tubercle becomes yellow, opaque, and dry. When larger tuberculous foci are affected by caseosis, a homogeneous yellowish-gray, dryish mass appears, sometimes granular, resembling cottage cheese, sometimes more homogeneous, elastic or smeary, close to certain varieties of cheese; hence the names cheesy mass, cheese-like mass, cheesy degeneration, caseosis, etc. Upon microscopic examination, the cheesy mass appears as an amorphous, fine-grained protein substance with an admixture of small droplets of fat; in a fresh caseous mass, grains of chromatin (karyorrhexis of the nuclei of the cells that were there) can be seen, whereas in an old one, there are no signs of chromatin left. When staining a specimen for elastic fibers, the skeleton of tissue made of elastic fibers preserved within it can be revealed in the amorphous cheesy mass, and upon silver impregnation of the specimen, thanks to the preservation of argentophilic fibrils in the caseosis, the outline of the pre-existing tissue or the reticulum network of the tubercle appears. However, with the prolonged existence of the caseous mass, these long-persisting tissue formations nevertheless degenerate and disintegrate. The region of caseosis is surrounded by the persisting epithelioid tissue of the periphery of the tubercle, and the cells of this tissue, directly adjacent to the caseous mass, are sometimes arranged radially, like a palisade [see separate table (col. 35-36), fig. 3]. The course of development of caseosis in a tuberculous focus and the essence of cheesy degeneration have still not been fully clarified to this day. Virchow believed that the main essence of the process consists in the gradually increasing fatty degeneration of the cells of the tubercle and exudate, ending in disintegration. This necrobiotic process, according to Virchow, is a consequence of a disturbance in nutrition resulting from the absence of vessels in the tubercle. Weigert and others classified the caseosis of a tubercle as a manifestation of coagulation necrosis. Subsequently, it was clarified that fatty degeneration of cells is not mandatory for caseosis, that in general the process of caseification cannot be interpreted simply as a process of necrosis or necrobiosis, and that with it, very important changes take place not in the cells, but between the cells. Pagel, Schleussing, and others believe that during caseification, a peculiar transudate is released, which, upon exposure to cellular disintegration, especially chromatin, produces coagulation of the precipitation type (antigen-antibody reaction); a certain analogy is seen between the process of caseosis and the deposition of hyaline and amyloid. Hübschmann links caseosis entirely with exudation and believes that at the basis of caseification lies a peculiar change (swelling) of fibrin and that the degeneration and disintegration of cells is a secondary process. Hübschmann generally believes that caseosis joins the exudative phase of the tubercle even before productive phenomena; the latter, as a rule, follow caseosis and represent, as it were, a reaction to caseosis. Caseification of productive tuberculous tissue, e.g., an epithelioid tubercle, according to Hübschmann, is encountered rarely and, if observed, is always connected with an outbreak of exudation in the tubercle; the latter, e.g., is expressed in the appearance of leukocytes among the epithelioid cells of the center of the tubercle. Hübschmann's point of view that the tuberculous process always has a course of development in the direction of exudation-caseosis-productive reaction did not meet with general sympathy; such a course of development, as can be seen from the above, is characteristic of only one type of tubercle (see above, exudative tubercle). It can be emphasized that in the region of a tuberculous focus, not only the exudate is subjected to caseosis, but also all kinds of cells and the interstitial tissue of the stroma (e.g., alveolar septa of the lungs); from this it follows that the matter is not in exudation, but in a change in the relationship between the tissue and the tuberculous virus spreading to all elements of the tuberculous focus; the circumstance that caseification, spread over the entire tuberculous focus and even often simultaneously over several foci, sometimes occurs immediately, as if suddenly, speaks for the fact that a disturbance in the reactive state of the organism plays far from the last role in the origin of the process of cheesy degeneration. The moment of exudation undoubtedly greatly contributes to the onset of caseosis, and it can be said that all predominantly exudative expressions of the tuberculous process have caseification as their constant outcome. It was already indicated above that necrotic and exudative tubercles as a rule undergo caseosis even before the onset of the productive phase (primary caseification according to Ranke); in this process, the cells of the exudate disintegrate, fibrin turns into a fine-grained mass, elements of the interstitial tissue, e.g., alveolar septa of the lungs, die and disintegrate, merging with the general cheesy mass. The productive phase in this case is manifested in the formation of only a granulation wall around the cheesy focus. In a productive, epithelioid tubercle, the process of caseosis takes place in the cellular mass of the granuloma itself, i.e., it complicates the productive phase (secondary caseification according to Ranke); under the microscope, it is expressed by the fact that the cells of the central part of the tubercle undergo disintegration, the reticulum undergoes fibrinoid transformation and disintegrates, as a result of which the center of the tubercle turns into a granular amorphous mass. The cheesy mass can subsequently undergo softening or, conversely, it thickens and becomes encapsulated. Softening sometimes proceeds with the participation of leukocytes and macrophages, which appear among the cheesy mass; in other cases, it occurs without the participation of cells by way of a peculiar swelling and liquefaction of the cheesy mass. Most often, the process of softening first captures the peripheral zone of the cheesy focus, thanks to which the central, not yet softened parts are separated, sequestered; subsequently, they too can undergo softening. Thanks to softening, the cheesy mass undergoes transformation into a semi-liquid, pus-like ("pyoid") mass or into a turbid liquid with a crumbly admixture. Caseous masses of exudative origin with weak development of the productive zone are most susceptible to the process of softening. The process of softening itself, sometimes manifesting extremely rapidly, is apparently connected with a peculiar disturbance in the organism's reaction to the tuberculous virus. Softening is the main basis for tissue destruction; after softening, the separation of softened sequestered masses and the formation of cavities-caverns inside organs can occur, and in the case of affection of one surface or another (skin, mucous membrane)-tuberculous ulcers. The outcome of caseosis into encapsulation is connected with the fact that the cheesy mass thickens, and a connective tissue capsule develops around it. This connective tissue capsule can have a twofold origin (Aschoff, Puhl, Pagel, and others); it either develops at the expense of fibrous transformation of the specific tuberculous granulation zone existing around the caseous focus ("specific encapsulation"), or it represents an overgrowth of ordinary connective tissue of neighboring parts ("nonspecific encapsulation"). Besides this, sometimes a sort of connective tissue, collagenous transformation of the cheesy mass itself is noticed; this is possible either in the sense of organization of the dead cheesy substrate or in the sense that the fibrillar substance always preserved among the caseous mass undergoes collagenization and compaction; there is also data that fibrin fibers can, through collagenization, directly turn into connective tissue fibers (Nageotte, Doljansky u. Roulet). Lime salts usually easily deposit into an encapsulated, dry cheesy mass [see separate table (col. 19-20), fig. 17 and separate table (col. 111-112), fig. 2, 3 and 7]. This petrification has at its basis the adsorption by the dead cheesy mass of lime salts dissolved in tissue fluids. Lime can be deposited in the form of a fine-grained substance diffusely throughout the entire caseous mass, which in this process turns into a white mass that is easily crushed between the fingers (so-called calcification); in other cases, lime is deposited in dense concentric layers around one place (nucleus) in the cheesy mass, gradually capturing it all; in this process, a real calcareous stone is formed in a fibrous capsule. Petrification is often followed by the formation of bone [see separate table (col. 35-36), fig. 8 and 9]; usually, it is preceded by the ingrowth into the calcareous masses of young connective tissue rich in vessels and the resorption of lime salts.
Along with this resorption, trabeculae of true bone tissue with bone marrow between them appear on the inner surface of the focus capsule. Bacteriological and experimental study of petrified and encapsulated tuberculous foci shows that virulent tuberculous bacilli can persist in them for a very long time. The different direction in the outcome of caseous foci (softening or encapsulation with petrification) is connected mainly with the different setting of the reactive manifestations of the organism. Productive epithelioid tubercles are also characterized by an outcome in direct fibrous transformation, fibrosis of the entire tubercle as a whole. It is a matter of the granulation tissue of the tubercle undergoing maturation up to mature fibrous and further to cicatricial connective tissue; epithelioid cells take on a spindle shape, fold into bundles, argyrophilic fibers between them increase in number, collagen fibers appear (so-called fibrous tubercle), and with the growth of the latter and the decrease in the number of cells, the entire mass of the tubercle turns into a small rounded scar, which subsequently usually undergoes hyalinization. Large fibrous hyaline nodes, resembling pearls, are formed in that form of Tuberculosis of serous cavities which is designated as pearl disease (see Pearl disease, Tuberculosis in animals); in humans, this form is rare. In relation to predominantly exudative tubercles and tuberculous foci in general, two more possible outcomes must be indicated that can take place before the onset of caseous degeneration. In some cases, an exudative focus, for example in the lung, can stop in its development, with the exudate undergoing resorption, just as in banal pneumonia; in these cases, no traces remain of the tuberculous focus or only a slight thickening of the tissue. In other cases, the exudate is not resorbed but undergoes organization, which in the lungs gives a picture of carnification (see); this carnification can be nonspecific (exudate is replaced by banal connective tissue) or specific (exudate is replaced by tuberculous granulation tissue); in the latter case, strictly speaking, it is not an outcome of the process, but a change in its character: from exudative it turns into productive. Everything said above regarding tubercles as initial changes upon the introduction of tuberculous bacilli into tissue can be transferred to the pathological anatomy of the tuberculous process as a whole. All those variants of structure, course, and outcome that relate to tubercles also take place in large tuberculous foci and in the tuberculous process as a whole. The difference between a tubercle and a developed tuberculous process is to a large extent volumetric, and in order to imagine the dynamics of the entire tuberculous process, one must first of all recall the paths of its spread in the organism. This spread can proceed by contact, when the process captures the immediately adjacent tissue. Such a type of increase in a tuberculous focus can be realized in different ways. Sometimes changes, having started in some place, very quickly capture adjacent parts, which can simulate the occurrence of a lesion of tissue that is, as it were, immediately significant in volume. This happens, for example, during the occurrence of some tuberculous pneumonic processes in the lungs (so-called early infiltrate, lobar pneumonias). In other cases, there occurs a proliferation of the tuberculous granuloma and its encroachment onto adjacent tissue, and in parallel with this, the region of caseosis expands in the center of the focus; a large focus of rounded shape arises, caseous in the center and with a granulation zone at the periphery; such a tuberculous focus is called a solitary tubercle [see separate table (art. 111-112), fig. 6 and separate table (art. 119-120), fig. 6]. Similar foci can form in those cases where a focus of an exudative process, for example in the lung, is successively surrounded by epithelioid granulation tissue; the latter subsequently undergoes proliferation in the outer layers, and in the parts adjacent to the caseous center, it itself becomes involved in caseification. In rarer cases, Tuberculosis granulation tissue sometimes grows to a significant volume, not showing a tendency to caseosis or with caseosis, but without softening of the caseous masses; this gives a tumor-like Tuberculosis. Large, isolated tuberculous growths are sometimes also designated as tuberculoma. Diffuse proliferation of the granuloma from epithelioid cells without a tendency to caseosis lies at the basis of that form of Tuberculosis of lymph glands which bears the name of large-cell hyperplasia. Diffuse proliferation of tuberculous granulation tissue is characteristic of tuberculous lesions of bone tissue. Finally, it happens that next to the initial tubercle of one type or another, new tubercles arise, merging with the first; such tuberculous foci, designated as conglomerate tubercles, usually have a scalloped edge, which causes the similarity of the focus to a clover leaf. With all these variants of the spread of the process by contact, there occurs the growth of the initial small focus, the tubercle, and its transformation into a larger tuberculous focus, which continues to increase. Such a tuberculous focus can present the same variants of structure and course that were cited above in relation to the tubercle; it can be predominantly productive or predominantly exudative; undergoing caseosis, it can become encapsulated, petrified, or undergo softening; upon the rejection of softened caseous masses, a cavity or ulcer is formed from it. In turn, from the cavity or ulcer, the process can continue to spread to adjacent tissues. Spread by contact is also observed in the form of the transition of the tuberculous process from bone to joint, from the spine or from a rib to the pleura, to the mediastinum, etc. By contact, there also arises that change accompanying the tuberculous process which is called perifocal or collateral inflammation. This is a zone of exudative inflammation, often of a nonspecific banal type, which sometimes surrounds the tuberculous focus itself, be it a tubercle or a larger tuberculous focus. Perifocal inflammation is explained by the diffusion from the tuberculous focus of toxic products both related to the vital activity of tuberculous bacilli (tuberculin) and those associated with decay processes in the tuberculous focus. Perifocal inflammation in Tuberculosis can flare up and subside episodically, being a sign of increased tissue sensitivity; it is observed far from every tuberculous focus. Clinicians classify perifocal inflammation in the lungs in the category of "infiltrates." Exudative inflammations of serous cavities of tuberculous origin have much in common with perifocal inflammation; here, in the presence of a tuberculous focus or tubercles, often productive, in the tissue of the serous membrane (pleura, peritoneum, pericardium), an exudative inflammation flares up, essentially nonspecific, banal, with the release of serous, fibrinous, less often purulent exudate into the serous cavity. The second path of spread is along the systems of channels and tubes of the organism, the so-called intracanalicular path. This includes the spread of the tuberculous process in the lungs along the bronchi, which is the usual basis for the lesion in pulmonary Tuberculosis of ever new sections of the lung (bronchogenic dissemination of the tuberculous process in the lungs). This same path is realized during the spread of the tuberculous process from the kidneys to the ureters and bladder, from the epididymis to the vas deferens, seminal vesicles, and prostate. If in these cases it is a matter of secretory channels, then usually the infection spreads in the direction of the flow of the secretion. In some tubular systems, the so-called autoinoculation is sometimes observed, the inoculation of infectious material coming into contact with one surface or another. Thus, sputum released from the respiratory tract in pulmonary tuberculosis often infects the mucous membrane of the larynx, pharynx, tongue, and intestine, where the tuberculous process then arises. Of extremely great importance is the lymphogenous spread of the tuberculous process, i.e., along the lymphatic pathways; at the same time, there is sometimes a lesion of the lymphatic vessels in the form of the appearance of tubercles in their walls, which gives a picture resembling a string of beads (tuberculous lymphangitis); in the majority of cases, however, tuberculous bacilli move with the flow of lymph to the nearest regional lymph gland, where the tuberculous process then arises. As a rule, lymphogenous spread goes with the flow of lymph; however, with lymph stasis (lymphostasis) due to a lesion of the lymph gland, the spread of infection can also proceed in a direction opposite to the physiological flow of lymph (retrograde lymphogenous spread). From one gland, the process can pass along the lymphatic pathways to other glands and finally reach the thoracic lymphatic duct, through which tuberculous bacilli directly penetrate into the blood (see below). Lymphogenous spread of the tuberculous process takes place mainly in primary Tuberculosis in children (see below), and as a rule, changes first arise at the site of the introduction of tuberculous bacilli (primary affect in the lung, in the intestine), and only after this does a lymphogenous lesion of the regional lymph glands arise. Only in rare cases does the tuberculous infection bypass the portal of entry without causing changes in them and giving the first changes only in the lymph gland.
Sometimes the process shows a tendency to spread to many lymphatic glands, involving, for example, the glands of the mediastinum, neck, retroperitoneal, even inguinal and axillary, which is generally attributed to the lymphogenous generalization of the process. Such generalization most often relates to the period of primary tuberculosis of childhood, but can be a manifestation of so-called senile tuberculosis (see below). No less important is the hematogenous spread of the tubercular process, which is a consequence of the presence of tubercular bacilli in the blood. As has been clarified in recent years, in the presence of a tubercular focus in the body, some quantity of tubercular bacilli is almost constantly found in the blood; such tubercular bacteremia, in most cases being a consequence of the penetration of individual tubercular bacilli into the lymphatic pathways and further through the thoracic duct into the blood, may not be accompanied by the appearance of metastatic hematogenous foci of tuberculosis. Only with a corresponding change in the reactivity of the organism does the formation of hematogenous metastases in the form of tubercles of one type or another occur here and there (e.g., in the spleen, in the liver). In this regard, it often happens that the initial focus of tuberculosis is very small, has a hidden, 'latent' character, whereas the aforementioned metastatic focus undergoes proliferation and is clinically and anatomically revealed as a tubercular lesion of one organ or another. Previously, such cases were incorrectly attributed to a primary, independent lesion of the organ. Precisely cases of isolated bone and joint tuberculosis, tuberculosis of the kidneys, genital organs, adrenal glands, serous cavities, and solitary tubercles of the brain have such an origin. The aforementioned hematogenous tubercular lesion of organs and systems (so-called organ tuberculosis, German Organphthise) usually takes place in the period of primary tuberculosis (see below), and a selective lesion of certain systems is noted, often in accordance with certain physiological stages of the development of these systems (lesion of bones during the growth period, of genital organs during puberty, etc.). Hematogenous tubercular lesion of some glandular excretory organs (kidneys, liver) is also qualified as 'excretory tuberculosis' (German Ausscheidungstuberkulose) [see separate table (col. 19-20), fig. 16]. If tubercular bacilli are found in the blood in a significant quantity, then many miliary tubercles appear in the organs, which is called miliary tuberculosis or miliarization of tuberculosis [see separate table (col. 111-112), fig. 1]. Such miliarization can be local, when, for example, tubercular bacilli penetrate into a branch of the pulmonary artery and spread only in the area of its branching, and general, provided that the bacilli circulate in the systemic circulation; in these cases, when a mass of miliary tubercles of one type or another appears in the most diverse organs (lungs, liver, kidneys, spleen, meninges, etc.), they speak of general miliary tuberculosis, of general millet-like tuberculosis. In this case, if the eruption of tubercles is not particularly large and they have a different size due to the unequal age of origin, then this is characterized as chronic miliary tuberculosis; if there is a widespread eruption of an abundant quantity of small tubercles of the same age, then this relates to acute miliary tuberculosis. As already indicated, the finding of a small quantity of bacilli in the blood can be a consequence of their penetration from a tubercular focus into the lymphatic pathways and further through the thoracic duct into the blood. As for the appearance of a large quantity of bacilli in the blood at once, which is a necessary prerequisite for the development of acute miliary tuberculosis, this can occur either with caseous tuberculosis of the thoracic duct itself, when the caseous mass with abundant tubercular bacilli penetrates into the venous blood, or (which happens more often) a tubercular lesion of the blood vessel wall occurs and a breakthrough of the tubercular focus directly into the blood. The significance for the development of miliary tuberculosis of such a 'vascular focus' was first noted by Weigert (1882) and subsequently confirmed by the majority of researchers, who, during careful autopsies of cases of acute miliary tuberculosis, found such an initial vascular focus in 90-95% of them (Schmorl, Hartwich, and others). On the basis of this, the doubt expressed recently by Hübschmann regarding the correctness of Weigert's theory and the opposition to it of a very complex assumption about the latent saprophytic stay of tubercular bacilli in the blood and in the cells of the reticulo-endothelium until a corresponding change in the reactive capabilities of the organism, as if reviving these bacilli, has not been successful. At the same time, it is clear that for the development of miliary tuberculosis, besides the mechanical moment in the form of a breakthrough of a tubercular focus into the bloodstream, a special state of reactive capabilities is necessary. This is proven by the fact that acute miliary tuberculosis in most cases occurs in subjects with weak development of the primary tubercular focus, whereas with a widespread tubercular focus it is encountered rarely, despite the vascular lesions present in such cases; this forces one to think that the weak development of the primary focus provides the corresponding immunobiological prerequisites for the possibility of the development of miliary tuberculosis. Furthermore, it has been noted that an outbreak of miliary tuberculosis often coincides with one episode or another that could result in an increase in the sensitivity of the organism to the tubercular virus. Most often, the tubercular lesion of a vessel, which becomes the source of miliary tuberculosis, takes place in the area of a tubercular lesion in the lung, and most often concerns a branch of the pulmonary vein; either the transition of the tubercular process to the wall of the vein from the outside or the emergence of the tubercular process on the inner lining of the vessel (endangiitis tuberculosa) is observed. The type of tubercles in acute miliary tuberculosis varies. Sometimes the tubercles everywhere have a necrotic type; in these cases, the disease proceeds very severely, which serves as the basis for designating it as severe, or malignant, tubercular sepsis. In other cases, predominantly productive or exudative tubercles erupt everywhere with shades related to the peculiarities of the structure of the organs. Macroscopically, in miliary tuberculosis, we see the lungs as hyperemic and stuffed with a mass of tubercles, which, when stroked with a finger, give the sensation of sand; in the spleen, they appear as small grains against the background of hyperemic pulp; in the liver, they are usually poorly visible and are often detected only under a microscope; in the kidneys, they have the appearance of pale, resolving spots; in the brain, in miliary tuberculosis, tubercular basilar meningitis usually arises. Hematogenous dissemination of tubercular bacilli from the primary focus to various organs lies at the basis of the hematogenous generalization of the tubercular process, which, just like lymphogenous generalization, is most often observed in the period of primary tuberculosis and in senile tuberculosis. Concluding the description of the pathological-anatomical substrate of tuberculosis, it must be noted that all the described tissue changes are extremely characteristic of tuberculosis, but not strictly specific to it. Both the formation of tubercles with epithelioid and giant (Langhans) cells and the outcome in caseous degeneration and scarring are encountered in other infectious granulomas (syphilis, leprosy, etc.) as well. The need for histological differential diagnosis between tuberculosis and syphilis arises especially often, in view of the fact that in the latter, the picture of changes in gummata can present much similarity to the changes in tuberculosis. It is usually pointed out that in syphilitic gummata, lymphoid and plasma cells predominate, while in tuberculosis, epithelioid cells do; in gummata, scarring appears very soon, in tubercles - later; in gummata, it is easy to discover vessels, in tuberculosis - they are rare; caseosis in gummata occurs only in the period of scarring, in tuberculosis - before scarring; in the caseous mass of gummata, the outlines of the former tissue are visible, in tuberculosis - this is not the case. However, these distinguishing features are quite relative, and in some cases, the question cannot be resolved without a number of additional pieces of information (data from bacteriological and serological examination, clinical picture, etc.). The pathological-anatomical picture of tuberculosis can be strongly disturbed by the addition of a secondary infection by extraneous microorganisms, which can happen especially easily in 'open' tuberculosis, namely, when there are ulcers, cavities accessible to the influence of the external environment. In these cases, the introduction of catarrhal micrococci, pneumococci, staphylococci, streptococci, etc., leads to the addition of phenomena of banal inflammation and suppuration to the tubercular processes; the addition of fuso-spirochetal infection causes gangrenous processes. The dynamics of the tubercular process and the variants of its course in connection with the reactive state of the organism represent a problem which, over the last 20-25 years, has undergone thorough development. This was significantly facilitated by the development of the doctrine of allergy, i.e., of that change in reactive manifestations on the part of the organism that occurs after contact of a given virus with the organism; such a first contact of the virus with the organism sensitizes the latter, thanks to which, upon the second contact with the same virus, a different 'allergic' reaction is already revealed, either in the sense of the manifestation of increased sensitivity (hyperergic reaction) or decreased sensitivity (anergic reaction).
In tuberculosis, just as in any inflammatory process, hyperergic and anergic reactions are expressed in different pathological-anatomical pictures. The first to draw attention to this was R. Koch, who, while experimenting with the tuberculosis pathogen he discovered, became convinced that a second introduction of the tuberculosis bacillus into an animal produces a different picture of the process than the first infection (the so-called Koch's phenomenon). Subsequently, these experimental data were confirmed by a significant number of researchers. With regard to human tuberculosis, the dependence of the dynamics of the development of the tubercular process and the variants of its change on reactive capabilities, i.e., on the shift in the allergic state, was revealed particularly clearly by the works of Ranke, who was the first to provide a corresponding 'typical scheme' of the development of the tubercular process (see below). The entire course of infection with the tuberculosis bacillus and the development of the tubercular process can be imagined as follows. The introduction of the tuberculosis bacillus into the human body in the vast majority of cases (90-95%) occurs through the respiratory tract; in 2-10% infection occurs through the digestive tract; other portals of entry (skin, genital organs, tonsils, middle ear, congenital transmission through the placenta) are significant only in isolated cases. In European countries and in the USA, the first infection with tuberculosis occurs in childhood; its frequency increases from early childhood to adolescence. The introduction of the tuberculosis bacillus into tissue does not yet lead to the development of a reaction in the form of a pathological tubercular process. Tubercular bacilli can remain in a latent state for a long time. According to a number of authors, the tubercular reaction begins to develop only after the bacilli undergo dissolution, bacteriolysis, which is carried out with the help of bacteriolysins produced in the body; since a certain change in the reactivity of the body, i.e., allergy, is already manifested in this production of antibodies, then, as for example Lewandowsky and others assert, tubercular changes are allergic from the very beginning of their emergence. If the tubercular bacilli, due to any reasons, do not undergo bacteriolysis, they remain existing in the tissues as saprophytes. This point of view, however, still needs verification. In any case, tubercular bacilli can sometimes, at the site of their initial introduction into tissue (e.g., in the lung, in the wall of the intestine), not cause any changes and pass along the lymphatic pathways to the regional lymph node without causing any reaction; only in this lymph node does the tubercular process begin. However, such a beginning of tuberculosis is an exception; in the majority of cases, the first changes begin at the site of the first contact of the tuberculosis bacillus with the tissues of the body. Both the very fact of the emergence of the tubercular process and its development are dependent on a whole range of conditions. Among them, one must note hereditary and constitutional factors, giving a so-called predisposition to tuberculosis; professional and domestic factors, which change the reactive state of the body, play a huge role; finally, the character of the infection, its massiveness, and repetition are also of significance. The first change that develops in the body coming into contact with the tuberculosis bacillus for the first time is observed as a rule in childhood. This so-called primary affect has the appearance of a small focus of the tubercular process, predominantly of an exudative type with rapid caseation of it; around the caseous center, a zone of a productive process develops. Very soon, a tubercular lesion of the regional lymph node is added to this, just as quickly passing into caseation. According to Ranke's doctrine, this initial tubercular change in the form of a focus at the site of infection introduction and a lesion of the regional lymph node, developing in childhood, is designated as the primary tubercular complex and belongs to the first stage of the tubercular process; Ranke characterized this stage as an expression of allergy I. At the present time, it is considered more correct to attribute the entire primary complex to a normergic reaction, since here we are dealing with the results of the first contact of the tuberculosis virus with the body. The primary complex is observed in the vast majority of cases in the lung, much more rarely in the intestine (see above). Most often, the primary complex does not progress and undergoes healing; around the caseous focus of the primary affect (also called Ghon focus, see) and in the caseous lymph node, specific and nonspecific encapsulation develops, giving rise to the formation of a connective tissue capsule, lime is deposited into the cheesy mass, and bone tissue often forms from the inner surface of the capsule. Such healed foci of primary tubercular affects in the lungs are discovered on almost all corpses of adults (see below - pathological anatomical statistics). In a number of cases, however, the primary complex shows a tendency toward spread, generalization; the latter can occur immediately following the development of the primary complex (early generalization) or occurs later when the primary complex has already begun to encapsulate (late generalization). Ranke attributed generalization to the second stage of the tubercular process, which is an expression of allergy II. From a modern point of view, this generalization in an immunobiological respect coincides with the negative, anaphylactic phase of immunity and is characterized by an increased sensitivity of the body to the antigen, in this case to the tuberculosis bacillus; therefore, we now classify generalization as manifestations of allergy of the hyperergic type. Generalization manifests itself differently and in particular as both a local spread of the process and a general dissemination. Locally, around the focus of the primary affect, perifocal inflammation of an exudative type develops, the focus increases by contact; in connection with exudation, the cheesy masses also soften into the caseous focus, which gives rise to decay, ulceration, and the formation of cavities. Spread also occurs intracanalicularly, e.g., in the lungs along the bronchi; finally, the development of lymphogenous and hematogenous metastases occurs (see above). The outcome of the period of generalization can be different. Significant local spread of the tubercular process, e.g., in the lungs, or acute general generalization in the form of general miliary tuberculosis leads to death; on the other hand, not particularly widespread metastasis or the formation of isolated metastases in one organ or another gives rise to separate foci of the tubercular process, which either develop into a chronically proceeding tubercular lesion of the organ (spine, kidney, epididymis, etc.) or undergo encapsulation and petrification at the beginning of their formation. In this period, when the tubercular process is as if limited to the boundaries of the organ (organ, isolated tuberculosis), metastasis is usually no longer observed either along the lymphatic or blood pathways; if such an isolated process does spread, it is exclusively by contact and along the channels of the organ; usually, there are also no perifocal inflammations. Such isolated tuberculosis of an organ Ranke attributed to the third stage of the tubercular process, which is a manifestation of allergy III; to this stage, according to Ranke, belongs pulmonary consumption of adults. At the present time, we know that the indicated isolated tuberculosis of organs and in particular pulmonary consumption of adults have at their basis a relative immunity of the body to the tuberculosis bacillus, which is expressed in a reduced sensitivity of the body to the antigen, in an anergic reaction of tissues to the tuberculosis virus. Thus, according to Ranke's doctrine, tuberculosis from childhood to old age is one and the same process, connected with the initial infection that took place in childhood; different expressions of the process in different periods of life represent different stages of it, connected with a regular shift of the phases of immunity. This doctrine of Ranke had great significance, as it for the first time clearly established the dependence of the clinical-anatomical expression of the tubercular process on the immunobiological state of the body; in particular, it well explained the essence of the difference between tuberculosis in childhood and in adults. However, subsequently, some additions were made to this doctrine. Firstly, the indefinite designations—allergy I, II, III—it turned out to be possible to replace with more concrete terms: normergy, hyperergy, anergy. Further, it was possible to establish that the passage of the tubercular process through all three stages is far from frequent. The most common is the limitation of the process to the first stage (primary complex with subsequent healing); in second place is the transition of the first stage directly into the third and the skipping of signs of generalization, i.e., the second stage. Finally, many disagreements were caused by the question of the origin of the third stage in the form of pulmonary consumption of adults. With the unanimous opinion that pulmonary tuberculosis of adults is the development of the tubercular process in an organism relatively immune to tuberculosis, it was not entirely clear whether tuberculosis of the lungs develops as a result of an exacerbation of the process in one of the foci belonging to the primary complex or to the period of generalization (endogenous reinfection), or whether pulmonary consumption is the result of a new infection from the outside world of an organism already having a primary tubercular focus and consequently relatively immune to tuberculosis (exogenous reinfection, superinfection).
About 10 years ago, researchers quite unanimously leaned toward the idea of the primary significance of exogenous reinfection for the origin of pulmonary consumption in adults, presenting a number of documentary data in favor of this view, in particular the frequent difference in the type of pathogen in the primary focus and the reinfection focus.
However, in recent years, the doctrine has become very widespread that a reinfection in the lung of adults has, in the vast majority of cases, an endogenous origin, being a hematogenous metastasis from an old focus in the lung, in a lymph node, or in another organ.
Very recently, the frequency of exogenous reinfection is being put forward again, and it is being placed alongside endogenous reinfection.
It is self-evident that when classifying pulmonary consumption in adults as a consequence of exogenous reinfection, it cannot be considered, according to Ranke, without reservations as the third stage of one and the same infection.
As a result of all this, at the present time, the division of tuberculosis into three stages according to Ranke is not applied; they speak of primary tuberculosis (primary complex and generalization) and of secondary tuberculosis, or reinfection.
The Ranke scheme does not include another period of the tuberculous process, namely senile tuberculosis. The problem of senile tuberculosis was put forward in 1928 by Anders; at the present time, the majority of researchers acknowledge that in old age (after 55-60 years), tuberculosis often takes on a character similar to primary tuberculosis: exudation, caseation, softening, and necrosis predominate in the process, generalization occurs via the lymphatic system, and general miliary tuberculosis often flares up.
At the basis of this feature of senile tuberculosis lies, it seems, a decline or complete disappearance in old age of the relative immunity to tuberculosis developed since childhood.
Some researchers (Ranke, Aschoff, Hollo, Shtefko, and others) also distinguish juvenile, pubertal tuberculosis (German: Pubertätsphthise), i.e., a special manifestation of the tuberculous process characteristic of the period of sexual maturity.
The peculiarity of the manifestation of tuberculosis at this age consists in the fact that there are changes that are, as it were, close to primary tuberculosis with generalization (exudativity of the process, lymphogenous generalization, hematogenous metastases), and on the other hand, much that relates to secondary tuberculosis (topography of the onset of the pulmonary process, absence of lymphogenous generalization).
Apparently, pubertal tuberculosis does not always represent one and the same thing; in some cases, this is a manifestation of late generalization, in other cases, it is a reinfection in an organism not yet sufficiently immune, accompanied by one degree or another of lymphogenous and hematogenous generalization.
Besides the significance for the character and course of the tuberculous process of one or another phase of specific immunity, various non-specific factors that change the reactive state of the organism play a huge role, as a result of which the anatomical type and course of the tuberculous process change.
Such non-specific factors include: climate, living, working, and nutritional conditions, and past diseases (for example, in children—measles).
There is no doubt that these factors can influence the reactive state of the organism; in relation to tuberculosis, severe climatic conditions, poor living, working, and nutritional conditions, past disease, etc., change reactivity in the sense of the predominance in the process of exudative manifestations, perifocal inflammations, and a tendency toward caseation, softening, and the spread of the process.
Under opposite conditions, the process can easily take on a productive shade, show a tendency toward fibrosis, and end in encapsulation.
One must not, however, forget that besides specific immunobiological factors and the aforementioned non-specific conditions, hereditary-constitutional factors play a not unimportant role, sometimes having a dominant significance in the type and direction of the tuberculous process, and furthermore, the character and massiveness of the infection; in a relatively immune organism, located in the most favorable conditions, a massive infection can produce a very severe, predominantly exudative process with caseation, softening, etc.
What has just been said provides an answer to the question often put forward in recent times: can the anatomical type of the tuberculous process give an indication of the state of the reactive capabilities of the organism and the character of the allergy, or, in other words, does a certain morphological picture of the tuberculous process correspond to a certain type of allergy (hyperergy and anergy)?
The answer to this question can be different depending on whether we take an individual picture of the tuberculous process or analyze the entire process as a whole in its dynamic development.
In the first case, we naturally give a negative answer to the posed question: in the period of hyperergy, the individual phases of the tuberculous process are the same as in anergy; there are no specific pictures for hyperergy and for anergy.
However, if one takes the entire tuberculous process of an individual case as a whole, when one can think about a more or less definite relationship having been created between the tuberculous virus and the organism, any change in the type of the tuberculous process already speaks of a disturbance of this relationship in the sense of a change in the reactivity of the organism, in the sense of specific or non-specific allergy.
Under these conditions, a change in the process in the sense of an intensification of the exudative factor in it speaks for an increase in sensitivity to the virus and can be considered as a manifestation of hyperergy; conversely, the appearance in the tuberculous process of a predominance of the productive moment is a sign of a decrease in sensitivity to the virus, a manifestation of anergy.
Everything said above in the sense of the dynamics of the tuberculous process refers to the population of European countries and the USA, which has long been in contact with the tuberculous virus.
The inhabitants of these countries become infected with tuberculosis in childhood, undergo the primary complex in childhood, and receive relative immunity to tuberculosis, which in adults causes a sluggish, local course of the tuberculous process.
A different picture occurs among peoples who, in their natural conditions, never come into contact with tuberculous infection (colored tribes of Africa, some peoples of South America, our Kalmyks).
If representatives of these peoples fall ill with tuberculosis in adulthood (for example, having found themselves on the European continent), then the disease proceeds in them as is characteristic of childhood tuberculosis (primary complex with generalization); this is explained by the fact that in this case, there is the first contact with the tubercle bacillus of an organism not immunized to it, which in the conditions of the European continent and in the USA takes place in childhood.
The disease of tuberculosis, besides characteristic changes at the sites of the tubercle bacillus's introduction into the tissue, is also accompanied by a whole series of general changes in the organism.
These changes, for the most part, represent a consequence of the intoxication of the organism by both the toxins of the tubercle bacillus and the products of caseous decay, purulent melting, etc.; the disturbance of metabolism, associated with the disturbance of the function of the affected tuberculous organ, is of no small importance.
To the indicated changes, which are, as it were, a manifestation of the distant action of the infection, belong atrophic processes, manifesting in increasing general exhaustion, weight loss, and atrophy of organs (heart, mucous membrane of the gastrointestinal tract, etc.); simultaneous sclerotic changes (of vessels, liver) are not rare; many forms of tuberculosis are accompanied by anemia with myeloid hyperplasia of the bone marrow.
In the period of a far-advanced process, as a rule, one can see degenerative changes of parenchymal organs and interstitial infiltrates resembling septic manifestations.
Tuberculosis with significant decay is accompanied by hypoplasia of the spleen.
Finally, in long-lasting forms of tuberculosis, especially in bone tuberculosis, the development of general amyloidosis with all its consequences is often observed.
All these changes do not represent anything specific to tuberculosis; therefore, calling them paratuberculous changes, as is sometimes practiced, is hardly correct.
Pathological-anatomical statistics of tuberculosis are of great importance, because besides cases of overt tuberculosis disease determined during life and death from tuberculosis, it registers those small tuberculous changes which not only do not lead to death but do not manifest themselves in any way during life (latent tuberculosis), and therefore do not enter into ordinary statistics registering morbidity and mortality.
But even if one takes only mortality from tuberculosis, even here pathological-anatomical data present somewhat different figures than ordinary statistics.
Thus, for 5 years (1923-27), according to data from the statistical department of the Moscow Soviet, 10-11% of all those who died in Moscow died from tuberculosis, and according to data from Moscow prosectoriums—14.7% (Davydovsky).
As for the general frequency of tuberculous changes detected during autopsies of corpses, the figures relating to this vary significantly among different authors, apparently in connection with different circumstances.
The geographical territory to which the sectional material relates is of very essential significance, because in different countries and even different parts of them, the susceptibility of the population to tuberculosis is very different.
The method of investigation also plays a not unimportant role; if one registers tuberculous changes in passing during a routine autopsy, then the figures obtained are much smaller than if one specifically searches for tuberculous foci (e.g., in the lungs on serial planar sections after preliminary fixation of the entire lung in formalin).
Also of significance is the researcher's attitude toward their findings in terms of interpreting them as a consequence of tuberculosis or denying their tuberculous nature; this concerns, in the main, pleural scars of the lung apices and anthracotic nodules of the pleura. The lowest figures for the finding of latent tuberculous foci, relating to the primary affect in the lungs, are provided by autopsy material in a number of tropical countries (Nauck), especially those that have only recently come into contact with the "civilizing" influences of Europeans (5-6% of all adult corpses); higher figures, and moreover ones progressing by year (20-50%), are discovered in those tropical colonies that have long been under the "patronage" of imperialist states. Much higher figures relate to findings of primary tuberculous affect foci (mainly healed) in the corpses of the adult population of European countries, although even here there is a difference in the figures among different authors. Thus, Harbitz (Norway) indicates 69.2% of all corpses, Necker (Vienna) - 70.2%, Orth (Berlin) - 68%, Lubarsch (Posen) - 69.1%, Naegeli (Zurich) - 93%, Burkhardt (Dresden) - 91%, Schirp (Freiburg) - 92.6%. The impression is obtained that in the Scandinavian countries and in northern Germany, the finding of foci of healed tuberculous affects is encountered less frequently than in southern Germany and in Switzerland. Interesting are the very latest data by Winkler (1933); with very thorough examinations of corpses, he found certain tuberculous foci in 85% of all corpses, and doubtful ones (foci of slate induration in the lungs) in 13%; a total of 98%. Corresponding data for the USSR are almost absent; in 1904, Abrikosov (Moscow) noted the finding of tuberculous foci in 78% of all adult corpses; Stefko and others indicate somewhat higher figures. Unfortunately, there are no comparative data on the frequency of findings of tuberculous foci in corpses in different parts of the USSR. In child corpses, the finding of tuberculous foci is encountered less frequently the younger the age. The character of the foci changes sharply with age. In childhood, these are for the most part fresh foci, active or only with the beginning of encapsulation; by age 15, the number of encapsulated foci begins to increase; after 15-16 years, encapsulated foci begin to predominate. In adults, the above-cited figures in the majority relate to already healed foci (according to Reinhardt, of 96.4% of tuberculous findings in adults, 64% relate to fully scarred foci; according to Schirp, of 92.6%, 63% relate to fully scarred foci). All the above-mentioned data relate to foci of the primary tuberculous affect discovered in the lungs; findings of primary affects in the intestine are rare (2-5%, and according to data from Leningrad prosectoriums, 0.6% of all tuberculous cases). During the examination of adult corpses, besides the almost constant finding of a focus of a healed primary affect (Ghon focus) in the lungs, one often also finds a focus or foci of reinfection (of the Puhl focus type or another kind—see Tuberculosis of the lungs); they are found, according to Strukov (1933), in 46% of all tuberculous corpses. Tuberculous lesions of other organs in comparison with the lungs are encountered much less frequently. According to data from Moscow prosectoriums over 5 years (Davydovsky), isolated organ tuberculosis accounts for 7.4% of all cases of tuberculosis, and of this 7.4%, more than half (57%) falls to tuberculosis of the osteoarticular system, 13% to the genital organs, and 9% to the kidneys. According to data from Leningrad prosectoriums for 1932 and 1933, organ tuberculosis was observed in 7.5% of all cases of tuberculosis, with 37% falling to osteoarticular tuberculosis, and 11% to tuberculosis of the genital organs and kidneys. If one dwells on tuberculous lesion of organs as a complication of pulmonary tuberculosis in adults, then in first place (60-70%) is tuberculous lesion of the intestines, in second place (30-35%) is lesion of the larynx, in 20% are found metastases in the spleen, in the liver, in the kidneys, in various lymph glands, in 10-12% is lesion of the peritoneum, in 5-6% of the adrenal glands, and in 6-7% of the brain and its membranes.
A. Abrikosov.
IV. Statistics. I. General methodological remarks. Statistics of tuberculosis are built on observations of tubercular infection, incidence of tuberculosis (without loss or with loss—temporary or permanent—of working capacity), prevalence (morbidity) of tuberculosis, and mortality from it. By tubercular infection is understood the relative frequency of positive tuberculin reactions discovered during mass screenings for tuberculosis or upon visits to tuberculosis dispensaries; by incidence—the relative frequency of newly discovered cases of tuberculosis upon seeking medical help; by prevalence—the relative number of tuberculosis patients under active supervision of anti-tuberculosis institutions; by affectedness—the relative frequency of the discovery of tuberculosis patients during mass screenings; and by mortality—the relative frequency of death from tuberculosis among all residents of the studied collective (in contrast to the relative frequency of death among tuberculosis patients, termed lethality, or case-fatality rate from tuberculosis). From a cognitive point of view, the listed criteria possess elements of similarity and difference, stemming from the essence of the phenomena on which they are based. Thus, for example, from the point of view of understanding the degree of the spread of tuberculosis, the prevalence of tuberculosis and mortality from it contain much in common, if one considers that every case of death from one cause or another, and in particular from tuberculosis, represents at the same time, in its essence, the last illness in a person's life. Along with this, there is a significant cognitive difference between both indicated phenomena. The study of mortality allows one to judge only those cases of tuberculosis that have reached a terminal state, while the study of prevalence can obviously give an idea of tuberculosis in various phases of its development, and not only in statics (for each given collective), but also in its dynamics. Similar features of similarity and difference exist between the remaining criteria. Therefore, a full-fledged statistical study of tuberculosis must be built, if possible, taking into account all its possible manifestations. The cognitive value of the above-named criteria in each individual study depends on a whole series of organizational-methodological premises upon which the corresponding study is built. Among the main premises influencing them, the following should be noted. A. Organization of diagnostic work and, in particular, the degree of clinical-diagnostic equipment. The most obvious moments that make up the influence of this premise are: the presence or absence of X-ray and laboratory equipment, the nature of the implementation of both diagnostic methods, the degree of mastery of them, the intra-dispensary organization of patient service (conveyor, etc.), etc. For a partial illustration of what has been said, one can refer to the data of W. Rink. Out of 4,677 tuberculosis patients recognized by German insurance doctors as patients with open tuberculosis, upon examination at a tuberculosis dispensary, it turned out that 10.7% had no pulmonary changes, 30.0% suffered from closed forms of tuberculosis, 1.3% suffered from tuberculosis of other organs, and 58.0% were patients with truly open tuberculosis. Out of 2,448 patients diagnosed by the same insurance doctors as patients suffering from pulmonary diseases of a non-tuberculous nature, 43.6% were found in tuberculosis dispensaries to have open pulmonary tuberculosis, 41.1% had closed forms of pulmonary tuberculosis, 0.6% had tuberculosis of other organs, and only 14.7% of the initial diagnosis turned out to be correct. B. The nature of the understanding of the pathogenesis of tuberculosis. For illustration, we will refer to the following data on the composition of tuberculosis patients, published in recent times by the Ukrainian and Leningrad Tuberculosis Institutes, as well as accumulated by the Moscow Regional Tuberculosis Institute (Table 1). Table 1. Composition of patients (15 years and older) registered at tuberculosis institutions (per 100 patients). Diseases: Leningrad (1931), Moscow (1938), Kharkov (1928). Pulmonary tuberculosis: Peribronchitis... Bronchoadenitis... Tuberculosis of others: 59.0, 22.3, 7.0, 5-39.5, 10.2, 1.5, 81.2, 15.1, 3.7, 91.8, 8.2. In the absence of patients with glandular-pleural tuberculosis in the composition of Kharkov tuberculosis institutions, the relative number of patients with [B] in the composition of all patients with subcompensated tuberculosis was equal to 07.3%, and with the presence of 39.5% of patients with glandular-pleural tuberculosis in Leningrad tuberculosis institutions, the percentage of patients with [B] in the composition of the same subcompensated patients was equal to 33.7%. For the city of Moscow, this same ratio was equal to 51.9%. C. The degree of proximity of medical aid to the population, especially the degree of proximity and development of specialized anti-tuberculosis aid. The influence of the degree of proximity of medical aid is most strongly reflected in the value of the indicator of mortality from tuberculosis, since the scientific-practical significance of records of death from tuberculosis is largely determined by the degree of physician participation in this registration. It is obvious that the value of notes on death from tuberculosis is higher the more the deceased used medical aid before death, and even more so where patients used specialized medical aid under conditions of its full accessibility and where the treated patients were hospitalized in a timely manner, and after death were subjected to pathological-anatomical autopsy. For a brief illustration, it can be pointed out that over a number of past years, the number of non-medical notes on causes of death (according to data from Siegfried Rosenfeld) fluctuated in some Western European states in the following amounts: in Bavaria: 1876–1880—47.8, 1881–1890—40.5, 1891–1900—38.6, 1912—29.0; in Switzerland: 1881–1890—10.4, 1891–1900—6.2, 1911–1920—2.4; in Austria: 1895—33.6, 1900—31.8, 1910—31.3; in Holland: 1905—6.8, 1910–1914—6.3, 1915–1919—3.9, 1922—3.4. Besides the listed main premises, there exists a series of secondary organizational-methodological premises that lower or raise the cognitive value of the criteria indicated above, and also often hinder the comparative juxtaposition of statistical data on tuberculosis obtained as a result of various studies. Among them should be named: the technique of performing the tuberculin reaction, the nature of legislative provisions determining the mandatory reporting of the deceased, legislative provisions regulating the organization of expertise on temporary and permanent disability and the payment of benefits, the static nature of the majority of mass screenings, conventions allowed during the processing of mass observations (such as, for example, the first or last diagnosis of tuberculosis in time within a given annual segment of time, or the 'most severe' diagnosis), etc. All these and similar organizational-methodological features must be taken into account every time when using statistical data on tuberculosis by one author or another. II. Spread and dynamics of tuberculosis. On the question of the degree of the spread of tuberculosis among the population of Western Europe, the only data that are to a greater or lesser extent comparable with each other are data on mortality from it. There are no other generalized data, such as data on the incidence of tuberculosis, its prevalence, etc. The structure of medical aid mainly on the principles of private practice, the predominantly sanitary-technical direction in the construction of state preventive measures, and the philanthropic character of public preventive measures in capitalist countries excluded the possibility of accumulating other data on tuberculosis from them. As for the statistics of mortality from tuberculosis, for the reasons indicated above, this statistic possesses the greatest accuracy in cities, especially large ones, to which we will limit ourselves in the future, although for the majority of European states there is also statistics of mortality from tuberculosis of the entire population over a long period of time.
In the large urban centers of Western European states, mainly in capital cities, the spread of tuberculosis and its dynamics are presented in the following table:
[They] presented a rather motley picture (Table 2). The dynamics of mortality from tuberculosis in the cities under consideration are notable in that during the war years, especially in its final years—1917 and 1918 and partly in 1919—mortality in a significant portion of the cities rose to an unprecedented level. This rise in mortality testifies to nothing other than the mass extinction of tuberculosis patients during the war years. In these rises, one should undoubtedly discern one of the essential causes of the subsequent decrease in mortality from tuberculosis in Western European cities and states. Regarding the question of the spread of tuberculosis and its dynamics in the USSR, there is currently limited data. For the pre-revolutionary period, there is satisfactory data only on mortality from tuberculosis, and even then, only for a few large cities. For the post-revolutionary period, work is underway to collect data on mortality from tuberculosis across a significant range of cities and urban settlements of the USSR, on the morbidity and prevalence of tuberculosis among the urban and rural population, on the incidence of tuberculosis with temporary and permanent loss of working capacity, and on tuberculosis infection. The absence of data on tuberculosis in the former Tsarist Russia is one of the numerous expressions of its cultural backwardness and the absence of a properly organized fight against tuberculosis at that time. Attempts by individual advanced municipal governments of that time to establish statistics on causes of death in cities did not lead to the desired results. Only now is it possible to restore and systematize some of the materials relating to the past regarding tuberculosis. Observations organized in recent years on the dynamics of mortality from tuberculosis through the general statistical bodies of the USSR and on the dynamics of tuberculosis infection, morbidity, and prevalence through tuberculosis dispensaries could not, of course, in such a short period, serve as a basis for obtaining developed data on all the listed phenomena. The period of establishing mortality statistics in the past in capitalist countries, as is known, spanned decades. With us, it spans only a few years. And nevertheless, despite the stated difficulties, it is possible to cite a number of data on the state and dynamics of tuberculosis. For example, if one leaves aside the war years (mainly the years of the imperialist war), one can draw the following conclusion about the dynamics of mortality from all forms of tuberculosis in Moscow: over the thirty-six years before the October Revolution, mortality from tuberculosis decreased by 43.0%, and during the ten years under Soviet power (from 1922 to 1931), it decreased by 44.7% (from 26.6‰ to 14.7‰). Similarly, in the former St. Petersburg, during the thirty-three pre-war years, mortality from tuberculosis decreased by 44.6%, while over the last ten years, it decreased in Leningrad by 54.9%. The noted fact acquires even greater significance if one considers that the decrease in mortality from tuberculosis, for example in Moscow, was accompanied by its decrease among the population of almost all ages (except for the male population aged 50 years and older) and in all its urban districts (Table 3). At the same time, it should be borne in mind that this decrease in mortality among men aged 15-19, 20-29, 30-39, and 40-49 years concerned, in essence, the working population. Thus, Table 3. Died in Moscow per 10,000 inhabitants of a given age and sex from all forms of tuberculosis. Age: Men 1923, 1931; Women 1923, 1931. 15-19 years: 34.5, 12.5, 4.9, 8.7. 20-29 years: 17.0, 23.3, 38.1, 36.9. 30-39 years: 24.4, 7.1, 4.3, 6.8. 40-49 years: 12.9, 23.0, 32.7, 42.5. 50 years and older: 28.3, 12.3, 6.0, 8.9. 13.7, 15.2, 12.9, 15.1. 20.3, 6.6, 3.9, 6.0. 10.1, 10.1, 10.1, 12.9. According to data as of April 1, 1931, per 100 men of each given age in Moscow, the number of self-supporting individuals was: 15-19 years—80.0, 20-24 years—97.8, 25-29 years—99.0, 30-34 years, 35-39 years, and 40-44 years—99.2, and 45-49 years—99.1. Regarding the state of tuberculosis morbidity, there is a number of observations collected by special anti-tuberculosis institutions. Based on these observations, it is revealed that the relative number of detected tuberculosis patients among the urban population, and specifically patients in need of monitoring of their health status, fluctuated from 3% to 4%. The fluctuations were caused mainly by the different content in the composition of the patients under consideration of certain groups of patients with compensated tuberculosis and with glandular-pulmonary tuberculosis due to a different approach to understanding the pathogenesis of tuberculosis. As for the incidence of tuberculosis among the rural population, according to data on visits to medical stations in the former Moscow Governorate in 1924, it was equal to 11.9 per thousand of the population for all forms of tuberculosis. In similar observations in the Tatar ASSR over 5 years (1924-1929), an average of 15.8 tuberculosis patients per 1,000 of the population was detected. By individual cantons, this indicator varied from 11.5‰ to 22.5‰. A special sanitary-demographic survey of 2% of the population, conducted in 1923 among residents of the Ukrainian countryside, established the following levels of tuberculosis prevalence: per 1,000 examined residents, there were patients with all forms of tuberculosis: in Volyn Governorate—12.4, in Donetsk—6.2, in Yekaterinoslav—8.0, in Kiev—10.9, in Odessa—9.1, in Podolia—12.5. Observations on the incidence of tuberculosis with temporary loss of working capacity are available for the later period. There is no significant similar data for the pre-revolutionary period. The few fragmentary data preserved from that period are incomparable with the data accumulated during the Soviet period of social insurance, in view of the major restrictions that existed earlier in the organization of social insurance for cases of illness compared to its broad organization with us now. The longest observations on the type of morbidity under consideration have been accumulated in relation to 40.2% of workers in nine branches of factory-plant industry in Moscow, numbering about 208.7 thousand people. According to these observations, the dynamics of morbidity were expressed in the results indicated in Tables 4 and 5. The presented data reveal that the incidence of tuberculosis with temporary loss of working capacity decreased over the seven observed years across all nine branches by 3.8 times in cases of disability and...
Average by industry... 231.6 175.0 285.1 195.6 219.3 176.6 197.6 148.6 262.8 193.9 233.9 199.4 196.6 169.6 248.2 236.0 173.8 138.2 411.3 279.8 360.8 288.1 367.1 325.7 330.4 297.4 261.6 257.1 410.8 290.0 372.0 297.3 361.3 220.9 339.2 356.2 248.4 249.3 224.6 194.1 289.5 227.8 130.1 120.0 140.4 105.0 163.3 160.5 144.7 171.4 141.3 223.6 159.9 171.6 169.3 151.1 182.4 274.4 169.4 265.3 161.3 130.3 163.5 113.0 112.9 120.8 99.2 116.3 133.4 117.4 147.1 144.1 167.8 131.7 104.4 167.1 142.0 172.0 161.2 191.4 164.2 153.1 128.9 135.8 83.3 87.2 68.7 103.4 124.1 123.2 109.5 96.0 162.6 137.7 123.2 169.6 159.3 176.8 147.3 155.1 108.8 128.0 100.7 120.0 59.7 64.7 65.7 35.9 60.6 72.3 67.7 71.9 88.1 79.8 85.1 71.7 102.3 83.6 108.0 90.8 57.3 57.0 74.9 69.8 71.6 60.4 71.2 66.4 35.7 67.9 56.6 67.8 43.0 62.6 74.9 77.6 82.4 72.3 74.2 71.9 80.4 52.2 56.1 76.2 64.1 63.1 73.0 75.0 74.3 91.9 74.2 75.8 65.6 82.7 64.0 81.8 78.5 77.6 78.1 71.6 82.5 78.4 71, 76, 4.2 times in terms of days of disability. In individual industries, this reduction reached even greater proportions. The same was observed in the dynamics of tuberculosis morbidity among workers in the factory-plant industry of Leningrad (Table 6). The last column in the provided tables clearly reveals the picture of the decline in morbidity. The reasons for such a decline lay in the significant improvement of the production environment as a result of the reconstruction of enterprises and the construction of new industrial giants that were perfect in technical and sanitary terms, as well as in the rise of the material situation and culture of the working people. The most significant observations on temporary and permanent disability from tuberculosis are available for 1925. According to the data of the territorial social insurance funds of the USSR, disabled persons due to tuberculosis who passed through the Bureau of Medical Expertise constituted the following percentage of the total number of disabled persons (Table 7). In particular, for individual groups of disability from tuberculosis of the respiratory organs, this percentage was equal to: Group I men - 17.2, women - 17.6; Group II men - 15.4, women - 16.4; Group III men - 8.8, women - 11.2. The degree of invalidization (or retirement on a disability pension) due to tuberculosis of the respiratory organs (according to observations in 1925) is shown in Table 8. P. Kuvshinnikov. V. Social significance of tuberculosis. The social significance of tuberculosis should be considered from two points of view. Firstly, it is necessary to establish the socio-pathological influence of tuberculosis, which is determined by its prevalence, forms of the disease, and its influence on the movement of the population and the productive forces of society. Secondly, it is important to study the social conditioning of tuberculosis, i.e., the connection of the disease, its prevalence, and course with various factors of the social environment. In view of the fact that tuberculosis as a social disease is most closely connected with the foundations of the capitalist system, the question of the social significance of tuberculosis must be considered separately in relation to capitalist countries and the USSR. Tuberculosis in capitalist countries. Tuberculosis is one of the most common diseases on the globe. Thus, according to the report of the Hygiene Section of the League of Nations for 1931, about 1 million people died from tuberculosis annually in Europe in the last pre-war years. In advanced capitalist countries (England, USA, Germany), the number of deaths from tuberculosis significantly exceeds that from all acute infections combined. In 1927-28, out of 100 deaths from all causes, tuberculosis accounted for: in England - 7.9; Holland - 9.2; France - 10.5; Sweden - 10.5; Austria - 11.1; Czechoslovakia - 12.0; Hungary - 13.1; Norway - 15.2; large cities of Poland - 16.6. Thus, from 1/6 to 1/5 of all deaths in a number of European countries fall to the share of tuberculosis. But in the most able-bodied age period (15-40 years), the specific weight of tuberculosis in total mortality is significantly higher and reaches 30-40%. From Western European statistics on tuberculosis morbidity, the statistics of bacillary pulmonary tuberculosis are of the greatest value, since the presence of Koch's bacilli in sputum is a reliable diagnostic sign of tuberculosis. In most German cities, the rate of bacillary tuberculosis is approx. 30-40 per 10,000 population, and the total number of bacillary cases in Germany is estimated at approximately 200-250 thousand. Of particular interest are data on tuberculosis diseases accompanied by temporary or permanent loss of ability to work; these calculations are possible only in countries that have social insurance. Thus, according to pre-war data from German insurance agencies, pulmonary tuberculosis accounts for 1/6 to 1/4 of all paid days of illness. In Berlin in 1910 and 1922, tuberculosis occupied the first place among all causes of disability, accounting for 16% of all disability among men and 13% among women. Thus, tuberculosis occupies a prominent place among diseases that reduce the labor productivity of the population. Western European social hygienists called tuberculosis a proletarian disease. This name is quite fair in relation to bourgeois society. Numerous statistical data collected by authors from various countries prove with impeccable conviction the socio-class essence of tuberculosis as a mass disease of the working people in capitalist society. The most favorable soil for the spread of tuberculous infection and the development of tuberculous diseases is represented by those strata of the population that suffer from economic insecurity, difficult working conditions, malnutrition, unhealthy housing, a low level of hygienic culture, and other inevitable consequences of capitalist exploitation. The listed unfavorable factors of the social environment lead both to a greater frequency of massive tuberculosis infection and to a weakening of the resistance of the population's organism to this infection. Thus, in the city of Charlottenburg (Germany) in 1908-12, the number of deaths from tuberculosis per 10,000 population was: in families with an annual income of up to 900 marks - 16.3, from 900 to 3,000 marks - 9.2, from 3,000 to 6,500 marks - 4.5, over 6,500 - 3.3. Thus, the tuberculosis mortality rate of the population group of Charlottenburg with the lowest income exceeded that in the group with the highest income by 5 times. In Hamburg in 1905-10, 90.5 per 10,000 population died from tuberculosis among the poorest group (income 900-1,200 marks), and 5.5 among the wealthiest (20-25 thousand income), i.e., 18 times less. The question of the connection between tuberculosis and prosperity was studied with great care by the statistician Hersch using materials from 1911-13. Hersch considered the percentage of the population paying real estate tax as a measure of the wealth of various districts of the city. At one pole was the richest district of Paris with an average figure of 421 francs of tax per household; in this district, mortality from tuberculosis for the above-mentioned years was 10.8 per 10,000 population. The district located at the opposite social pole paid 28 francs of tax per household and yielded 63.6 deaths from tuberculosis per 10,000. In other words, the poorest district of the French capital had a six times higher mortality rate from tuberculosis than the most affluent one. Among the latest data, the figures for 1930 for New York are interesting, in which tuberculosis mortality rates ranged from 3.4-4.6 (per 10,000 population) in wealthy neighborhoods to 12.6-23.7 in proletarian ones. The past imperialist war (1914-1919) demonstrated with the precision of an experiment the influence of the deterioration of living conditions of its working people on the growth of tuberculosis. The greatest number of deprivations in these years fell to the lot of the countries of Central Europe (Germany, Poland, Austria): in these countries, the working masses suffered not only from all the usual military hardships (deterioration of housing conditions due to the cessation of civil construction, lack of shoes, soap, and other items of hygienic use, increased labor burden on women, adolescents, weak and elderly men in connection with the mobilization of the strongest male population to the front and the intensified work of the entire industry for defense), but also from the terrifying hunger blockade. In this connection, the movement of tuberculosis mortality rates in German cities with a population of over 15,000 (per 10,000 population) is interesting: in 1913 - 15.7, in 1914 - 16.1, in 1915 - 17.2, in 1916 - 18.8, in 1917 - 26.4, in 1918 - 30.0, in 1919 - 26.4.
Thus, mortality from Tuberculosis in German cities began to rise from the first year of the war and grew continuously, reaching its highest point in 1918, and this year of greatest need for the German people corresponds to an increase in deaths from Tuberculosis of more than 90%. In some large cities of Europe, the wartime jump in mortality from Tuberculosis was even sharper: for example, Warsaw (Poland) had a Tuberculosis mortality rate of 30.6 in 1913, and 84.0 in 1917; Cologne (Germany) - 12.8 in 1913 and 36.5 in 1918 (an increase of almost 3 times). Over 5 years (1915-19), Germany lost 134,000 more people to Tuberculosis than could have been expected based on pre-war Tuberculosis mortality rates. The poverty of the exploited masses of the working population in capitalist countries or a military catastrophe represent, from a socio-pathological point of view, complex phenomena, because they exert an influence on the health of the population through many intermediate social factors (housing, nutrition, labor, etc.). In the interests of scientifically substantiating the most correct paths for the prevention of Tuberculosis, it would be extremely interesting to decompose such a social complex into individual components (poor housing, unbearable labor, unhygienic lifestyle, etc.) and determine the specific weight of each individual factor in the total sum of the social pathology of Tuberculosis. Some Western European hygienists made corresponding attempts, but in doing so, they followed an incorrect methodological path: they compared mortality from Tuberculosis among certain population groups with the light coefficient of housing, literacy, etc., and thereby established certain constant regularities: the fewer windows in apartments, the lower the percentage of literacy, the higher the mortality from Tuberculosis. Such calculations, however, do not give the right to place responsibility for high mortality from Tuberculosis in the studied population groups on any one sanitary factor or social factor, taken in isolation from all other conditions of the social environment, because, for example, in poorly lit apartments lives a population that is under the yoke of pauperism and all its derivatives (malnutrition, harmful labor, unsanitary conditions, etc.). If, nevertheless, bourgeois social hygienists so willingly characterize Tuberculosis as a "housing disease," "disease of ignorance," or "occupational disease," then a deeper socio-psychological meaning lies in this methodological error: it reveals that fundamental difference in the understanding of the social essence of Tuberculosis that exists between the concept of bourgeois social hygiene and the Marxist point of view on this question. Marx and Engels considered Tuberculosis an inevitable consequence of the capitalist mode of production. The striving for the extraction of super-profits through the exploitation of workers leads to the fact that capitalists predatorily use the health of the worker. They economize in every way on labor protection measures, do not introduce necessary sanitary improvements in production, and keep wages at a low level. Therefore, tuberculosis and other pulmonary diseases are conditioned by the very existence of capitalism. Bourgeois scientists, by linking Tuberculosis with the influence of only one factor, for example, housing or occupational hazards, thereby erase the socio-class essence of Tuberculosis, since they substitute one of the fundamental contradictions of capitalism (the exploitation of the working class and the class distribution of material goods) with individual, although very significant, derivatives of the capitalist system. This pursues a definite political goal—to sow in the masses the illusion that a successful struggle against Tuberculosis is possible even under the conditions of capitalism by carrying out certain reforms and individual hygienic measures (sanitary education, improvement of housing, etc.). From this point of view, the narrowly epidemiological view of the Tuberculosis problem, which is very widespread in the West, is of great interest. One of the most prominent proponents of this view was Robert Koch, who considers the entire problem of Tuberculosis exclusively in the context of sanitary-epidemiological factors. He evaluates the role of everyday and social factors only from the angle of the extent to which they contribute to or hinder the spread of tuberculous infection. In his famous report to the Berlin Physiological Society on his discovery of the tubercle bacillus, Koch says: "Until now, Tuberculosis has been considered an expression of social need, and a decrease in morbidity was expected from the improvement of these conditions. Public health has not yet known special measures directed directly against Tuberculosis." To such special measures, Koch counts only those that lead to the limitation of the spread of tuberculous infection. Koch explains the decrease in tuberculous mortality in some countries (Norway, England) by the widely implemented hospitalization of severe and infectious tuberculosis patients in them. Koch considers the mandatory reporting of patients, hospitalization, sanitary education, etc., to be the main measures for combating Tuberculosis. A brilliant scientist, Koch was at the same time a loyal son of his class: he completely ignored the social nature of Tuberculosis, did not want to see that severe social conditions create the basic prerequisites for the massive spread of tuberculous infection and weaken the organism's immunity in the fight against this infection. All of the above does not deprive us of the right to analyze the influence of one or another social factor on Tuberculosis, but in doing so, we must take into account the connection of an individual factor with the social environment as a whole and observe great caution in the methodology of evaluating the role of each component. A number of statistical studies have proven that in cramped, poorly lit, and dirtily maintained dwellings, mortality from Tuberculosis is 3-4 times higher than that in spacious, bright, and clean dwellings. How great the housing need is among the poor in bourgeois states (Great Medical Encyclopedia, vol. XXXIII) can be seen from the data of a survey by German health insurance funds regarding the housing situation of 14,000 sick employees. 800 patients lived in "holes" with 10 m2 of area, of which 38 did not even have windows; over 1,200 patients with a family size of 4 to 7 lived in one room; some patients did not have 5 m3 of air and 5 m2 of area per person—hundreds of Tuberculosis patients lived in the same conditions. Among housing hazards, from the point of view of creating a predisposition of the organism to Tuberculosis, the most practical significance have: 1) dampness, which favors colds, 2) lack of light, which disrupts hematopoiesis, 3) the content and nature of dust, 4) spoiled air, which worsens appetite and sleep, 5) psychic factors, i.e., chronic bad mood caused by poor housing conditions. On the other hand, the role of cramped and unhygienic housing in the spread of massive tuberculous infection is not subject to doubt. In the literature, there are descriptions of individual epidemic outbreaks of Tuberculosis in houses where many patients with open forms lived. From the point of view of the epidemiology of Tuberculosis, the most significant importance have the overcrowding of apartments and poor maintenance of them; in dark, dirty apartments, tubercle bacilli retain their viability longer, and cramped conditions and lack of hygiene in the dwelling create prerequisites for massive tuberculous infection in all its forms—dust, droplet, and contact. The influence of nutrition on the course of Tuberculosis has been confirmed by numerous observations and is not subject to any doubt. In this regard, there is an interesting experimental parallel. In the most well-fed type of domestic animal—the pig—Tuberculosis is encountered extremely rarely and proceeds quite benignly. However, in conditions of poor nutrition, especially with a sharp deficiency in feed of those components from which fat is formed in the organism, a Tuberculosis-infected pig loses its immunity and becomes almost as sensitive to tuberculous infection as a guinea pig. It is known that hunger weakens the organism's resistance to many infections; the World War (1914-18) provided convincing facts. Although the sharp increase in mortality from Tuberculosis during the war is explained by many factors, nevertheless, the quantitative and qualitative deficiency of nutrition played a huge role in this. Thus, mortality from Tuberculosis in German cities (see above) grew slowly in the first years of the war and jumped sharply in 1917, i.e., exactly when the food difficulties of this country reached their highest point: the total number of calories in the daily civilian ration was about 2,000 in 1916, and in 1917 it decreased to 1,100. Agricultural regions of Germany, better provided with nutrition (Bavaria), showed a smaller increase in mortality from Tuberculosis than purely industrial regions (Saxony). In cities, the growth of Tuberculosis indicators was sharper than in the countryside; starting from 1917, the wartime growth of tuberculous mortality in the city was twice as high as that in the countryside, but those rural districts that were in the immediate vicinity of large cities and, like them, suffered from severe malnutrition, showed the same growth in tuberculous mortality as the cities. A terrifying mortality from Tuberculosis was noted in these years in German prisons, almshouses, camps for prisoners and refugees, and psychiatric hospitals.
In some almshouses, mortality from tuberculosis increased in parallel with the deterioration of nutrition and the loss of weight of their inhabitants; this is of particular interest because the dependents of charitable institutions and the mentally ill suffered more than other elements of the population from malnutrition during these years, but were least affected by other wartime calamities. An important role in this was played not only by the quantitative insufficiency of the total caloric content in the daily ration, but also by the qualitative aspect of nutrition: the reduction of proteins, fats, and fresh vegetables had a fatal influence. The deterioration of the course of tuberculosis under the influence of 'avitaminous' nutrition has been experimentally proven in animals. The observations of the Norwegian physician Overland are very interesting in this regard. In many military and nursing schools in Norway, rapid outbreaks of tuberculosis were noted among students. Thus, in one non-commissioned officer school, out of 40 students, 13 fell ill with tuberculosis within four years; in this same school, avitaminoses (night blindness) were frequently encountered. With the regulation of nutrition, especially with the addition of products containing vitamin A, the appearance of new massive cases of tuberculosis ceased in these schools. The question of the biological influence of alcohol on the course of tuberculosis is insufficiently studied. Experimental data (Koch, Roux, Nocard) indicate that alcoholized guinea pigs become more sensitive to acute infections; when infected with tuberculosis, alcoholized animals live less than the control group, but the results of such an experiment cannot be unconditionally transferred to humans; for a guinea pig, only a short-term experiment is possible, guinea pigs feel an aversion to alcohol and it must be administered by a probe, guinea pigs are sensitive to alcohol as a poison; human alcoholism is chronic, lasts for years and decades, and the intake of alcohol is accompanied by a feeling of pleasure. The data of clinicians and pathologists on this issue are contradictory: some believe that lung tissue pathologically altered under the influence of chronic alcohol poisoning is less resistant to all kinds of infections (an example is the frequency of pneumonia in alcoholics), including tuberculosis. Others point out that under the influence of alcohol excreted through the lungs, a process of increased proliferation of connective tissue and sclerosis occurs in this organ, which is a favorable factor from the point of view of curing tuberculosis. On the other hand, statistical data indicate a high mortality rate from tuberculosis among 'alcoholic professions,' i.e., workers in distilleries and drinking establishments (brewers, waiters, etc.). But, if the question of the direct (biological) influence of alcoholism on the course of tuberculosis is not entirely clear, there is no doubt about the other side of the issue—the negative influence of alcoholism on the social position of the alcoholic, i.e., the deterioration of his financial situation (and consequently housing, nutrition, etc.). These adverse consequences of alcoholism cannot remain without a detrimental influence on the course of tuberculosis. Nevertheless, in many German and Swiss sanatoriums, the consumption of beer and wine by tuberculosis patients is not only not limited but even encouraged. This is explained by the entrepreneurial nature of private sanatoriums in bourgeois countries, where the drinking of patients is one of the sources of income for the sanatorium, as well as by the obsequiousness of the administration of these sanatoriums toward wealthy patients and the unwillingness to scare them away with the necessity of giving up favorite habits. Numerous statistical data, mainly Western European, speak of large differences in the mortality rate from tuberculosis among various professions. Thus, in England, particularly low mortality from tuberculosis is found among the clergy, farmers, doctors, miners, millers, and bakers; above the average level in terms of tuberculosis mortality indicators are masons, carpenters, tailors, printers, bookbinders, and shoemakers; the highest mortality from tuberculosis (2-3 times higher than the average) is among grinders, file cutters, waiters, and street vendors. These sharp fluctuations in occupational tuberculosis mortality are explained by many factors. Firstly, one's occupation has a great influence on social position and earnings; these factors determine the nature of nutrition, housing, and other elements of daily life, which in turn influence the pathology of a given occupational group and its tuberculosis mortality in particular. The main role in this can be played by general social factors, and not by specific occupational hazards. This is evident when comparing English data on mortality among various social groups: thus, mortality from tuberculosis among skilled workers exceeds that among the bourgeoisie by only 25%, while the tuberculosis mortality of unskilled workers is 40% higher than that among skilled ones. In other words, the English labor aristocracy stands closer to the bourgeoisie in terms of tuberculosis mortality levels than to the lower strata of the proletariat. Selection has a great influence on the level of occupational mortality in bourgeois countries. Before being hired for certain jobs, for example, in mines (England), in the police, or in transport, a medical examination takes place, as a result of which the weak element is weeded out, in particular those sick with clinically expressed forms of tuberculosis. People with poor health often choose a profession themselves that does not require a great expenditure of physical strength. In this case, a tuberculosis patient is much more likely to end up in a sewing workshop or a barbershop than in a mine or a smithy. On the other hand, there is also a consistent weeding out of tuberculosis patients from hot shops, mines, and other industries that are too strenuous for weakened people. From this point of view, many seemingly paradoxical facts from the field of occupational pathology of tuberculosis become clear. For example, English coal miners, working in difficult sanitary-hygienic conditions, show very low mortality rates from tuberculosis, which gave rise to the hypothesis about the protective effect of coal dust against tuberculosis. This hypothesis is incorrect, which is evident from a comparison of the mortality of miners with the mortality of workers unloading coal in docks—both groups inhale coal dust in large quantities. Although coal unloaders, working in the open air, are in much better sanitary conditions than underground workers, they nevertheless have almost triple the mortality from tuberculosis compared to the mortality of miners. It is perfectly clear that the low mortality of miners from tuberculosis is explained not by the protective effect of dust, but by selection. During the World War, the mortality of miners in the Ruhr region (Germany) from tuberculosis grew threefold, while the tuberculosis mortality of the entire population increased by only 60%. This is explained by the fact that career miners were mobilized to the front, and their place was taken by weaker 'rear-echelon' human material. The selection factor ceased its operation, and the 'protective effect' of coal dust evaporated. Almost the highest mortality from tuberculosis in English cities is found among street vendors, although they work in the open air and do not have hazards predisposing to tuberculosis, but English street vendors (of fish, fruit, toys) are the social dregs, to which representatives of well-paid professions descend in those cases when they find themselves broken in the struggle for existence. If a miner or a metalworker from a hot shop falls ill with a severe form of tuberculosis, he is no longer able to work at the coal face or at the furnace. He seeks other earnings that do not require robust health and special qualifications, and his lot often becomes the street stall. And if he soon dies from tuberculosis, this death is registered under his last profession, although the tuberculosis disease was acquired earlier at the factory or in the mine. From the point of view of tuberculosis disease, the question of the sanitary conditions of labor (lighting, ventilation) and the length of the working day is especially important—experiment and clinical observations have shown that overwork reflects extremely unfavorably on the course of tuberculosis. Among individual factors, the inhalation of certain types of dust (metallic, silicate) is of serious importance. The modern level of technology allows for the introduction of sanitary-technical improvements that eliminate harmful factors in production, including the dustiness of the air. But the unbridled striving for the extraction of maximum profit prevents the capitalist-entrepreneur from carrying out hygienic improvements, since the latter are often connected with the re-equipping of the enterprise. A striking example is the extreme technical and sanitary backwardness of the majority of coal mines even in such an advanced capitalist country as England. At one time, tuberculosis was considered an 'urban' disease, but modern statistics indicate a wide spread of tuberculosis in the countryside as well. If the indicators of morbidity and mortality from tuberculosis in the countryside are usually lower than those in the city, this is in most cases explained by the worse registration of tuberculosis diseases and causes of death in the countryside. True, agricultural labor takes place mostly in the open air and is not associated with the inhalation of inorganic dust, but these favorable factors are countered by such significant factors as the arduousness of certain types of labor in individual peasant farming, the harvest season with its sometimes unlimited working day, and the unhygienic living conditions of the peasant poor and farm laborers in bourgeois countries.
When comparing statistical data for cities and villages in bourgeois countries, one should compare not the city and the village as a whole, but individual classes of the urban and rural population. The fact that English "farmers," i.e., landowners, show low mortality rates from tuberculosis is explained not by the benefits of the rural climate, but by their advantageous social position, since the tuberculosis mortality of the urban bourgeoisie is also low. Agricultural workers in England have a tuberculosis mortality rate higher than that of their employers, but lower compared to the rates of the urban proletariat. The main reason for this difference is selection—agricultural labor is hard and requires strong, hardy people, and an English landlord or kulak will not keep a weak, let alone consumptive, farmhand. Statistical data on mortality from tuberculosis show that the latter has declined in some bourgeois countries over the last decades (see above—statistics). These facts gave social hygienists of the bourgeois and social-fascist stripe, before the last crisis of capitalism, a pretext to construct a theory about the gradual liquidation of tuberculosis under capitalism, due to the fact that industrialization leads to an increase in wages, a cultural rise of the working masses, and sanitary-hygienic progress. As proof of this, the fact is cited that the lowest mortality from tuberculosis is noted in advanced industrial countries (England, Germany, USA), and the highest in agrarian ones (Hungary, Spain, Bulgaria). This theory is incorrect and tendentious. One can, for example, cite the example of Japan, which not long ago underwent a rapid process of urbanization and industrialization, in which, nevertheless, tuberculosis mortality was 15.7 per 10,000 in 1896 and 19.6 in 1929, which means an increase of 25% over 35 years. Many large industrial centers of Europe still show high mortality rates from tuberculosis today. The aforementioned decline in mortality from tuberculosis in capitalist countries refers to average mortality rates calculated for the entire mass of the population, but not for individual social-class groups. In New York, the average tuberculosis mortality rate in 1930 (7.2 per 10,000) was low, but in the poor quarters of the same city, the rate reached 23.7. This means that in the height of its tuberculosis mortality, the working population of advanced industrial New York approaches that of the cities of poor, backward countries. The same applies to England. English statistics, when studying mortality by the social status of the deceased, establish the following five groups (classes): upper class (I), middle class (II), skilled workers (III), intermediate class of workers (IV), and unskilled workers (V). When calculating mortality per 100,000 people of the corresponding group for tuberculosis for 1921-23, the following standardized rates were obtained (Table 9; for men over the age of 20). Table 9. Class I....... 90.1 Class IV........ 177.7 Class II....... 151.8 Class V........ 243.8 Class III....... 173.1 All professions..... 177.3. Mortality from tuberculosis among individual classes differs sharply from the average. The development of capitalism in its imperialist phase is connected with the oppression and monstrous exploitation of the population of colonial and semi-colonial countries, as well as national minorities in the metropolises. For example, in 1927, mortality from tuberculosis (per 10,000) was 8.4 in New York, 9.0 in Amsterdam, 10.5 in London, 51.9 in Manila, 53.9 in Callao, and 54.9 in Lima. Thus, the rate for New York—the largest center of the USA—is more than six times lower than the rate for Manila—the main city of the American colony of the Philippines. In New York in 1930, mortality from tuberculosis was 6.2% among whites, 29.2% among Negroes, and 34.1% among other "colored" people (Indians, Chinese, etc.). A higher mortality rate from tuberculosis among the colored population in the USA is noted in all age groups. In 1930, per 100,000 of the population of the corresponding age, the number of deaths from tuberculosis was (Table 10): Table 10. Age White population Colored population 1-4 years.......... 21.7 80.2 5-9 years........ 8.6 100.6 10-14 years........ 7.9 97.2 15-19 years......... 34.3 51.1 20-24 years......... 73.3 245.4 25-34 years......... 141.0 351.5 35-44 years......... 177.2 295.1 45-54 years......... 172.2 258.7 55-64 years......... 151.2 275.8 65+ years......... 204.4 229.8. Representatives of bourgeois science have tried to prove that the increased tuberculosis mortality of Negroes, Indians, etc., is explained by purely biological factors: 1) peculiarities of their racial constitution, 2) a lack of acquired immunity in connection with the low infection rate of some tribes living far from cultural centers. There is no doubt, however, that the main cause of the high mortality of colonial peoples is their difficult social position (slavery, forced labor, and other undisguised forms of the most monstrous exploitation). It is known, for example, that Negro workers in the USA are not admitted to well-paid professions and, as a result, are pushed into more harmful, low-skilled, and poorly paid types of labor. In the American army, where Negro soldiers are in satisfactory sanitary-hygienic conditions, they show a mortality rate equal to that among white soldiers. Capitalism inevitably leads to periodically arising wars and industrial crises with unemployment. The influence of war on tuberculosis has already been mentioned above. The economic crisis has led to a sharp deterioration in the standard of living of the working masses, a massive cutting of social insurance, and a curtailment of the work of healthcare in general and tuberculosis institutions in particular (corresponding data are already available for Germany, the USA, and England). In its most complete form, this process of degradation of the anti-tuberculosis struggle is playing out in countries with a fascist regime (Germany). Tuberculosis in the USSR. Our country inherited from the tsarist period of its history a heavy legacy of high prevalence of social diseases, including a very high mortality and morbidity from tuberculosis. A wide spread of tuberculosis was noted both in large industrial cities (Petersburg) and in the countryside, and especially in the oppressed national borderlands (Buryats, Yakuts, Kalmyks, etc.). For example, in 1913, deaths from pulmonary tuberculosis per 10,000 population were 28.6 in Petersburg, 22.6 in Moscow, 29.9 in Saratov, and 30.9 in Yaroslavl. In the 90s of the last century, a number of mass surveys of the peasant population for tuberculosis were conducted in various provinces of Russia, predominantly by zemstvo doctors. These surveys revealed an extremely high prevalence of tuberculosis among peasants. Thus, Pirsky, having examined 5,300 peasants of Kobelyaky Uyezd (Ukraine), discovered among them 1.45% of patients with bacillary tuberculosis; Yakub, among 3,155 peasants of Dmitrov Uyezd, Moscow Province—0.82%; Savelyev, among 11,000 peasants of Voronezh Province—0.7%. These indicators exceed our average urban figures by 2-3 times. During the imperialist and civil wars, mortality from tuberculosis showed further growth. After the end of the civil war, when the prerequisites for socialist construction were created in the USSR, the development of which proceeded at an ever-increasing pace, tuberculosis mortality rates began to decline rapidly. Thus, the mortality rate from pulmonary tuberculosis in Moscow, which was 22.6 in 1913, declined to 11.6 in 1931, i.e., by approximately 2 times. When assessing the significance and character of the decline in mortality from tuberculosis in the USSR that took place after the October Revolution, it should be taken into account that our mortality statistics, like the Western European ones, operate mainly with average indicators without a breakdown by social groups; these data, due to the mentioned factor, do not reflect the improvement in the health status of individual social-class groups of the population. Average indicators thus obscure the most essential side of the question, i.e., those qualitative changes that distinguish the problem of tuberculosis in the USSR from this problem in capitalist countries. The October Revolution destroyed the exploitation of man by man, which is the main prerequisite for the inevitability of the existence of tuberculosis. If in capitalist society tuberculosis is an obligatory phenomenon growing out of the class structure of this society, oppression, and exploitation, then in the USSR tuberculosis is only a legacy of the past system, which decreases as our material and cultural power grows. In the USSR, there are already data that indicate that the policy of the Soviet government leads to the improvement of the health of the working people, primarily the proletarian masses. Thus, in Leningrad in 1895-1904, mortality from tuberculosis per 10,000 population in the age group 20-59 years was 59.8 among men and 29.7 among women for the entire population; among workers—71.3 among men and 47.9 among women. In 1926, the picture changes: in the same age group, 28 men and 15 women died out of the entire population; among workers—21 men and 8 women. Before the revolution, mortality from tuberculosis among workers exceeded that among the entire population; in 1926, on the contrary, tuberculosis mortality among workers was lower than that in the population as a whole. While the average tuberculosis mortality rate decreased by 2 times, the same rate among workers decreased by 3 times.
In Odessa, a noticeable decrease in the proportion of bacillary tuberculosis falling to the share of the working population has been noted, despite the growth in the relative number of workers in the city's population: in 1925, among newly discovered bacillus carriers, workers accounted for 53.3%, and in 1930, 38%. Of great interest is the decrease in the figures for tuberculosis morbidity with temporary disability (see above). The October Revolution created the prerequisites for the liquidation of tuberculosis; the tremendous rise in the material and cultural level of the working people of the USSR led to a sharp decrease in tuberculosis mortality and morbidity. But despite the successes achieved, one should not think that the problem of tuberculosis has already been completely solved by us. The legacy received from capitalism has not yet been completely liquidated. The fight against tuberculosis in the USSR is still a very essential section of socialist healthcare.
Public struggle against tuberculosis in the West began at the end of the 19th and the beginning of the 20th century. In accordance with the general character of the bourgeois system, it was initially left almost exclusively to private charity: societies for the struggle against tuberculosis, which merged into national associations or arose as such from the start. These organizations deployed a significant network of tuberculosis institutions using private charity funds, and sometimes with the help of insurance funds or state subsidies. The struggle against tuberculosis was developed much more weakly along sanitary-preventive lines and was not developed at all along social-preventive lines. After the World War, ministries of health, where they were created, included the struggle against tuberculosis in their work programs, which brought to life a number of various anti-tuberculosis laws and contributed to the further expansion and unification of the network of tuberculosis institutions. (For details on the struggle against tuberculosis in the West, see individual countries). In Tsarist Russia before the war, an attempt at a public struggle against tuberculosis along Western lines was made by doctors and a few liberal public figures. A League for the Struggle against Tuberculosis was formed. But the bureaucratic-police system and the lack of public forces, as in all such cases, left a stamp of innate weakness on this initiative. In 1912, the anti-tuberculosis organization in Tsarist Russia numbered 43 outpatient-trusteeships, very modest in their equipment and staff, and 18 sanatorium-type institutions with 307 beds. During the imperialist war, even this weak organization underwent reduction, and by 1917, due to a lack of funds, only a few outpatient-trusteeships and up to 200 beds in inpatient facilities remained. Even Moscow, during the existence of the section for the struggle against tuberculosis (9 years), was unable to develop a network of more than 4 outpatient-trusteeships and 75 beds for tuberculosis patients. Consequently, it can be asserted with full justification that the struggle against tuberculosis on the territory of the former Russia began from the moment of the establishment of Soviet power, and only from this time can one speak of deepened, systematic, and organizationally formalized anti-tuberculosis measures. In the USSR, from the very beginning, the struggle against tuberculosis began to be carried out by a specially organized network of tuberculosis institutions, through broad sanitary and social-preventive measures under the leadership of health authorities and with the direct participation of the working public. The All-Union Communist Party, in its program for the protection of public health, singled out the struggle against tuberculosis as one of the main tasks, clearly defining the category of tuberculosis as a social disease, and thereby indicated the ways to resolve this problem. The organization of the struggle against tuberculosis after the October Revolution is built in the direction of eliminating the root causes of tuberculosis morbidity. This became possible thanks to grandiose socialist construction, the improvement of the material and living conditions of the working people, the improvement of labor and living conditions, and the protection of children's health. The decrees of the Central Committee of the All-Union Communist Party (Bolsheviks) on medical service for workers and peasants (1929), on municipal economy (1931), and on public catering (1932) served as a detailed social-hygienic program for resolving the main tasks of improving the health of collectives, reconstructing daily life, and cultural-living services. In the USSR, the organization of the struggle against tuberculosis develops according to a plan, according to unified principles, methodology, and instructions developed by health authorities, and is provided with corresponding appropriations from state and local budgets. The working public takes part in the struggle against tuberculosis, starting from the creation of an individual institution to all-union congresses on tuberculosis. Trade union organizations, represented by their bureaus of health and social insurance, actively participate in all the work. The role of the state in the struggle against tuberculosis, the nature of public participation, and its class essence leave a mark on the principle of structuring the organization of the struggle against tuberculosis. Leadership of the organization for the struggle against tuberculosis in the USSR is concentrated in state health authorities: in each republic—in the People's Commissariat of Health, and in regions, territories, and districts—in the corresponding health departments of the executive committees. In the indicated apparatuses, except for the districts, in the first period of the organization of the struggle against tuberculosis, there existed tuberculosis sections under sanitary-epidemiological or medical sub-departments. As regional, territorial, and republican tuberculosis institutes were created, the methodological and scientific-practical leadership of the struggle against tuberculosis was transferred to them; only medical specialists (inspectors) for tuberculosis were left in the administrative apparatus of the People's Commissariat of Health for organizational-administrative work and the preparation of government orders in this area. According to regulations, tuberculosis institutes are organized in every territorial or regional center and serve as a methodological and scientific-practical base for health authorities in the struggle against tuberculosis. As of January 1, 1934, there are 12 tuberculosis institutes in the RSFSR, 3 in the Ukrainian SSR, 1 in the Byelorussian SSR, and 1 in the Transcaucasian SFSR. In addition to this, for the resolution of fundamental questions on the organization of the struggle against tuberculosis, the exchange of experience, the resolution of scientific problems, and the establishment of clinical-diagnostic work, all-union, republican, and regional congresses are convened by health authorities, the decisions of which, upon approval by health authorities, have mandatory force and are subject to execution. After the October Revolution, 4 all-union congresses and 1 all-Ukrainian congress were convened. Thanks to the unity of leadership, the organization of the struggle against tuberculosis is built according to a pre-developed plan, covering the entire chain of anti-tuberculosis institutions, in which each link has its own place, its own sphere of activity, its own contingent of patients, and is in the closest direct connection with the central leading link—the dispensary. This ensures a unified guiding line from the People's Commissariat of Health to the grassroots level, creates conditions for the concentration of all forms and ages in a single organization of the struggle against tuberculosis, and ensures unity of observation. In the USSR, the organization of the struggle against tuberculosis, being internally integral and unified, works as part of the entire health organization in the closest connection with the general medical-preventive network. The development of the organization of the struggle against tuberculosis in the USSR can conditionally be divided into four periods. The first period, from 1918 to 1924, is the period of construction, organization, and deployment of anti-tuberculosis institutions, broad propaganda of the struggle against tuberculosis, attracting the attention of Soviet and trade union organizations, the development of methodology, and the creation of a working activist base. The second period, from 1924 to 1929, is the period of growth of anti-tuberculosis institutions, the deepening of work, the creation of a coherent system of anti-tuberculosis measures in cities and industrial centers, the beginning of the deployment of the organization of the struggle against tuberculosis in rural areas, the development of broad sanitary-preventive measures, and the greatest participation of the working public in the struggle against tuberculosis. The second period is also characterized by the desire to establish the closest connection with the primary sources of patient referral—outpatient clinics and polyclinics, which are beginning to switch to the dispensary method of service. The third period, from 1930 to 1934, is a turn toward production, the deployment of work in the leading sectors of national economic life (new construction projects, coal, metallurgical industry, machine building), and priority service for leading groups of shock workers. The fourth period, which began in 1934, has as its starting point the decree of the Council of People's Commissars of the RSFSR of December 10, 1934, No. 1176 "On measures for the struggle against tuberculosis." In this period, all work is built on the basis of a synthesis of production-based and family-territorial service for patients, collective and individual prevention, and sanitary-preventive and medical work. From this point of view, the main lines of work for the struggle against tuberculosis become the implementation of sanitary-preventive measures and the high quality of clinical-diagnostic and medical work based on the application of modern medical technology. The struggle for early detection and timely active therapeutic intervention is placed at the forefront. From the very beginning of its construction, the organization of the struggle against tuberculosis in the USSR was built comprehensively, covering all forms of tuberculosis. Working according to a unified plan, principles, and methodology, the organization of the struggle against childhood tuberculosis, bone tuberculosis, and tuberculosis of the upper respiratory tract is built taking into account the peculiarities arising from age, genesis, course, and the influence of the environment on them. Types of anti-tuberculosis institutions. 1. The main, leading link in the chain of anti-tuberculosis institutions is the dispensary type of institution, working as an independent tuberculosis dispensary or as a special tuberculosis department within a unified dispensary. The Soviet dispensary resolves diagnostic questions, observes the course of the tuberculosis process, draws up a treatment plan, and conducts treatment. At the same time, the dispensary is obliged to process the patient not only clinically but also to make a social diagnosis and develop social therapy. In this direction, the dispensary conducts significant work on the improvement of labor and living conditions, not limiting itself only to the individual patient, but also among entire collectives of both adults and children (enterprises, schools, kindergartens, nurseries, etc.). The dispensary conducts work on the prevention of the spread of tuberculosis. A large section of the dispensary's work is accounting and statistical work.
Finally, the dispensary conducts selection for all anti-tuberculosis medical-preventive institutions. The structure of the Soviet dispensary is also determined by these tasks. It conducts examinations for all forms of tuberculosis lesions for all ages by the appropriate specialists; it has an X-ray room, a laboratory, a pneumothorax room, conducts tuberculin therapy, physiotherapy (quartz), has a staff of social assistance nurses, an accounting-statistical bureau, and auxiliary preventive institutions. In cases where examinations for young children (up to 3 years old) cannot be organized at the dispensary due to its accommodation conditions, a micropediatrician-phthisiatrician conducts them at a children's consultation center. Such a structure has been implemented in large cities, industrial centers, and new construction sites. The least branched are rural points, where there is one doctor and a nurse, but where all available specialists in the relevant field (surgeon, pediatrician) are utilized. Every dispensary institution conducts not only diagnostic, but also therapeutic and preventive work. In accordance with the indicated structure, each dispensary has a special facility, divided for the reception of children and adults and equipped accordingly. Each dispensary serves a strictly limited district, divided into sectors. Each sector and the enterprises located within it are served by a therapist-phthisiatrician attached to it. Pediatricians have the same attachment to the sectors. The indicated type of institution, its organization, and structure relate mainly to industrial centers, large district centers, machine-tractor stations (MTS), and cities. All work of the dispensary consists of work outside and inside the dispensary. Work outside the dispensary is in turn divided into three main sections: work at the place of production, in the sector, and connection with the general medical-preventive network. The first two sections are essentially two sides, complementing and mutually intersecting each other, of one task—improving the environment, preserving and restoring the ability to work through social-preventive measures and the provision of medical-preventive aid. Dispensary doctors conduct the improvement of the production and living environment and the collectives of enterprises, identify tuberculosis patients, detect early forms, implement measures for the organization of labor, and through the dispensary provide the necessary medical-preventive aid. Work in the sector has the same tasks as in production, but special attention is paid to issues of the spread of tuberculosis from family foci. Treatment of the focus and, first and foremost, sanitary-cultural education, control over the observance of the established regimen by the patient and those around him in the family and apartment, conducting current disinfection at the patient's home, verification after the cessation of bacillus excretion, and finally, isolation of the bacillary patient—this is the sum of the work in the focus. In work in the focus, the participation of a doctor is mandatory through systematic, planned visits to the bacillary patients observed by him. One of the types of work in the sector is home aid to tuberculosis patients. If at the beginning of the organization of the fight against tuberculosis, this type of aid was provided by doctors only upon the patient's call in urgent cases or cases not allowing the patient the possibility to go to the dispensary, then recently, doctor's home visits are conducted on the initiative of the doctor and are included in the plan of his work in the sector, regardless of a call from the patient. A special type of home aid, the so-called patronage, is conducted in relation to bone tuberculosis patients. A doctor and a specially trained nurse systematically visit patients at home and conduct the treatment of patients at home or refer them to an inpatient facility. The third section of extra-dispensary work—connection with the general medical-preventive network—is carried out by receiving patients only upon referral from outpatient clinics, polyclinics, and health posts, and by establishing consultations of dispensary doctors in them to develop a unified approach to the understanding of various symptom complexes. This connection is most simply realized in unified dispensaries. The children's department of the dispensary establishes a connection with institutions for the protection of motherhood and infancy and the protection of the health of children and adolescents. With the former, this connection is carried out in the direction of identifying tuberculosis-infected children, primarily from foci, registering them, and joint observation; secondly, along the line of conducting Calmette vaccinations and subsequent observation of the vaccinated, and participation in general health-improving work in nurseries. Connection with the protection of the health of children and adolescents is expressed in the participation of dispensary pediatricians in work in schools and factory apprenticeship schools (FZU), in referring patients to an inpatient facility, analogous to the work of a therapist in production, taking into account the specific aspects of these institutions, and in establishing consultations in children's outpatient clinics, polyclinics, and children's departments of unified dispensaries. The task of the clinical work of the dispensary includes, first and foremost, early diagnosis of tuberculosis. For the detection of early forms, the following groups are referred to the dispensary and are actively attracted by it: 1) those repeatedly ill with influenza, bronchitis, 2) "subfebrile cases," 3) those masking tuberculosis—prolonged increase in t°, hemoptysis, weight loss, and persistent cough, 4) sluggishly progressing pulmonary diseases, 5) individuals with a prolonged period of recovery after an infection, 6) workers from production who are ill for a long time and frequently, 7) individuals having contact with a bacillus excretor at work or at home, 8) individuals of draft age, 9) workers and students living in dormitories, organized adolescents (FZU, FZS), 10) food industry workers, 11) teachers, 12) employees of children's institutions, 13) organized groups of children. Each dispensary, to one degree or another, conducts work on the registration of morbidity, mortality, bacillarity, and loss of ability to work. Each dispensary, to one degree or another, analyzes morbidity, bacillarity, and mortality, and sets for itself questions of coverage and awareness, not only from a quantitative point of view, but also from a qualitative one. Such are the basic outlines of the methodology and organization of the work of dispensary institutions. It applies equally to independent tuberculosis dispensaries and to tuberculosis departments of unified dispensaries. The difference between them is quantitative, but not fundamental. The network in rural areas at the present stage is built less differentially, while maintaining the basic fundamental principles. A beginning has been made in the development of collective farm sanatoriums (Voronezh, Moscow regions), maintained at the expense of collective farm funds and budget funds. The main tasks in the fight against tuberculosis in rural areas are the identification and coverage of tuberculosis patients, and primarily bacillary ones, improvement of living conditions, participation in the improvement of the village, sanitary-educational propaganda, work in school, and hospitalization. In rural areas, the most common dispensary type of institution is the tuberculosis point, consisting of a phthisiatrician and a social assistance nurse. The tuberculosis point is closely connected with the district dispensary and utilizes its consultation for all sections of work. Recently, a new form of organizing the fight against tuberculosis in villages has begun to be implemented—the so-called tuberculosis post (Moscow region). The tuberculosis post is based at a local district outpatient clinic or hospital by utilizing the therapist of these institutions for tuberculosis examinations, registration of tuberculosis patients, and conducting measures for the isolation of bacillary patients. The tuberculosis post works under the guidance of the nearest tuberculosis institution, the doctor of which travels at certain intervals to the tuberculosis post for consultation and instruction. The tuberculosis post is the beginning for the subsequent deployment of a more full-fledged tuberculosis institution. However, it is, of course, possible to cover all tuberculosis morbidity in the village only through the general network of medical sectors, and the opening of special tuberculosis institutions in the village is possible only where there is already a general medical institution. Therefore, a broad anti-tuberculosis organization in the village requires, first and foremost, the development of general medical institutions there. 2. Institutions of a semi-inpatient type: a) night sanatorium, b) day sanatorium, c) open-air site, permanent and seasonal. Besides these semi-inpatient institutions, some dispensaries have a diagnostic department. The diagnostic department of a dispensary is an inpatient-type institution with a small number of beds, intended for the short-term placement of patients in cases where the establishment of a diagnosis requires clinical observation. Semi-inpatient institutions (day, night sanatoriums, sites) are intended for the treatment of patients without separation from production. 3. Inpatient institutions: a) sanatoriums, b) tuberculosis hospital. Tuberculosis sanatoriums are under the administration partly of local health authorities, partly of the All-Union Central Council of Trade Unions (VTsSPS), and in addition, a significant sanatorium network exists at resorts. But under whose administration the sanatoriums may be, the selection of patients for them occurs through tuberculosis dispensaries (in localities where such exist, and in other places through general sanatorium-resort selection commissions). The main method of sanatorium treatment is the hygienic-dietary regimen, as well as physiotherapy, collapse therapy, etc.; at resorts, in addition, the use of resort therapeutic factors (climate, kumis, etc.).
The hospital-infirmary builds its work in the direction of fulfilling the main task—restoring working capacity and proper vocational orientation, not limiting itself only to a purely clinical modification of the process. According to the decree of the Council of People's Commissars in the RSFSR, severe bacillary patients from student and workers' dormitories, patients in need of surgical intervention (thoracoplasty, phrenicoexeresis, etc.), patients with severe pulmonary hemorrhage, patients with tuberculous meningitis, and bone tuberculosis patients in need of surgery must be hospitalized. All institutions are inseparably linked with each other and complement one another, which facilitates maneuvering. 4. For children affected by local forms of tuberculosis and severe tuberculous intoxication, as well as those suffering from mild chronic tuberculous intoxication, there are specific types of anti-tuberculosis institutions. A. For early age (up to 3 years): a) sanatorium groups in normal nurseries, i.e., the separation of weakened children into a special group with a special regimen with a sanatorium orientation; b) daily sanatorium nurseries; c) suburban sanatoriums; d) for severe and acute forms of tuberculosis, special tuberculosis wards at hospitals for children of early age or wards for infants and children of early age at a special tuberculosis hospital. B. For children aged 4 to 14: a) sanatorium kindergartens or sanatorium groups in kindergartens (similar to sanatorium groups in nurseries); for school age, the role of such institutions is performed by open-air classes (Kaluga); b) until the moment of widespread development of health-improvement schools, auxiliary institutions at dispensaries of the day and night sanatorium type are preserved; c) health center; the main task of the health center is to provide rest to an overfatigued schoolchild in a healthy environment with rational application of all health-improving factors to them,
physical culture, proper regimen, appropriate nutrition, etc.; pedagogical and labor workload in health centers is maintained; g) patients with local chronic forms of tuberculosis in a subcompensated stage or with a subacute course, who need individual observation and regimen, constitute the contingent for sanatoriums; d) for the proper use of the sanatorium network, it is necessary to have sufficiently developed hospital care; e) finally, the peculiarities of the course of the tuberculous process in older children urgently require the creation of another type of sanatorium institution intended for chronic bacillus-excretors—a labor sanatorium commune. Of the listed types of children's (4-14 years) institutions, only sanatoriums (pulmonary and bone) and day sanatoriums and playgrounds at dispensaries have received wide development so far. C. For adolescents, the same types of institutions are needed as for older children, but in their organization, all the peculiarities and needs of this age must be taken into account. In the process of the development of tuberculosis at its various stages, treatment in various types of institutions is indicated. In the process of observation, the dispensary, in accordance with established indications, directs patients to one institution or another. Upon completion of the stay in one institution or another, the patient returns to the observation of the dispensary. Network of tuberculosis institutions. After the October Revolution, the network of anti-tuberculosis institutions in the RSFSR began to develop rapidly, and there is growth in all types of institutions. In the Ukrainian SSR, Byelorussian SSR, and other republics, we also have steady growth. Thus, in the Ukrainian SSR from 1923 to 1935, the number of dispensaries grew from 30 to 201, sanatorium beds from 1,550 to 5,977, hospital beds from 500 to 1,819. In the first years of organizing the fight against tuberculosis, dispensaries covered large, predominantly industrial centers; then the dispensary network appeared in medium-sized cities and large workers' settlements. From 1929-30, tuberculosis wards of unified dispensaries began to be deployed, the number of which increased sharply, reaching 98 in 1934. The dispensary network received the greatest development in 1932 and 1933 in new industrial centers, new construction projects (Magnitogorsk, Gorky Automobile Plant, Dzerzhinsk, Urals). In 1933, in the RSFSR, the network was distributed as follows: 40% of dispensary institutions are located in industrial cities, 9.3% in workers' settlements, 39% in non-industrial cities, and 11.7% in rural areas. To characterize the network, it should be noted that out of 335 dispensary institutions, 181 receive patients for childhood tuberculosis and 115 for bone tuberculosis. Out of 421 dispensary institutions (with tuberculosis points in rural areas), the majority have an X-ray unit and a laboratory; the rest use the X-rays and laboratories of other medical institutions. Of the bed capacity of auxiliary institutions in 1934, 62.1% were deployed in industrial cities, 6.2% in workers' settlements, 29.8% in non-industrial cities, and 1.9% in rural areas. The network of inpatient institutions is undergoing significant changes towards an increase in the number of beds in them. From 1928 to 1934, the number of sanatorium beds for adults grew from 15,578 to 22,169, and for children from 2,170 to 6,726. Hospital beds from 1,055 in 1923 to 5,359 beds in 1934. The fight against tuberculosis is not exhausted by the development of the network of medical-preventive tuberculosis institutions; along with this, a whole system of general sanitary-preventive measures is needed, usually combined under the name of anti-tuberculosis legislation. This includes the following laws and mandatory regulations. Mandatory notification of all cases of open tuberculosis and cases of death from tuberculosis (circular of the People's Commissariat of Health of the RSFSR No. 200/35 dated August 11, 1927). Mandatory notification does not extend to the entire territory, but only to those settlements where there are tuberculosis dispensaries (tuberculosis wards of unified dispensaries or tuberculosis points). After the death of a tuberculosis patient or after their move to another apartment, mandatory terminal disinfection is carried out in their dwelling (Instruction of the People's Commissariat of Health dated October 17, 1929); current disinfection in the dwellings of tuberculosis patients is carried out by tuberculosis dispensaries on the basis of the same circular. Regarding housing benefits for tuberculosis patients, see below—individual prophylaxis. The decree of the Council of People's Commissars of the RSFSR of December 10, 1934, No. 1176, prescribes that in all workers' and student dormitories, tuberculosis bacillus-excretors must be separated into separate rooms. The same decree prescribes, for the purpose of timely diagnosis of pulmonary tuberculosis, to conduct systematic examinations of pre-conscripts, students, workers of large enterprises, teaching staff, and food industry workers, etc. Patients with open tuberculosis are not allowed to hold positions related to serving children in all children's institutions (with the exception of medical institutions intended for the treatment of children suffering from pronounced forms of tuberculosis) (decree of the Council of People's Commissars of the RSFSR of December 10, 1934, No. 1176); the same restriction exists for workers and employees in food industry enterprises, trade, and public catering enterprises (decree of the People's Commissariat of Health, People's Commissariat of Labor, and All-Union Central Council of Trade Unions of July 23, 1925). In 1935, the "Instruction on the improvement of labor and employment of tuberculosis-infected workers in production" was issued (All-Union Central Council of Trade Unions, No. 04-409 dated April 27, 1935; People's Commissariat of Health of the RSFSR, No. 117/mv dated July 2, 1935). In homes for the disabled under the jurisdiction of the All-Union Central Council of Trade Unions and the People's Commissariat of Social Security, patients with open tuberculosis are separated into separate homes (decree of the Council of People's Commissars of the RSFSR of December 10, 1934, No. 1176). Article 132 of the Civil Code obliges those entering into marriage to inform each other about having tuberculosis. In order to prevent infection through meat and milk, it is forbidden to sell meat from tuberculous animals (circular of the People's Commissariat of Health No. 34 dated February 5, 1925) and milk from sick animals and healthy ones kept in the same room with them, as well as those animals cared for by people sick with infectious diseases (circular of the People's Commissariat of Health and the People's Commissariat of Trade No. 50/mv dated December 11, 1928). Regarding vaccination according to Calmette, see below. There are also special measures to combat tuberculosis in places of detention.
N. Avgushevich. VII. Immunoprophylaxis and immunotherapy. Vaccination against tuberculosis. Vaccination with killed bacilli confers immunity to the organism, but its strength and duration are not great; in view of this, vaccination with killed bacilli has no widespread use. 1) Langer's vaccine is a culture of young tubercle bacilli grown on 2% glycerin broth with the addition of methylene blue in a concentration of 1:200,000. The bacilli are killed by heating at 70° for 1/2 hour and 1/2 hour at 100°. The vaccine confers increased sensitivity to tuberculin in both guinea pigs and children. The vaccine is administered intradermally. 2) Dreyer's vaccine (Dreyer; Diaplyte-vaccin). Tubercle bacilli are treated with formalin at an elevated temperature and then extracted with acetone. The number of vaccines made from live bacilli is relatively large. The most important of them are the following: 1) Behring's bovovaccine, prepared from a strain of tubercle bacilli typ. humanus, which had been grown for 6 1/2 years in the laboratory. It is used in the form of an emulsion of dried bacilli. It is administered to calves at the age of 6 months twice at 3-month intervals intravenously; doses of 4 and 20 mg. It undoubtedly confers immunity, but its strength and duration are not great. The bacilli introduced during vaccination are excreted in feces and milk, due to which there is a danger of spreading the infectious agent. 2) Koch's Tauruman (Koch and Schütz, Neufeld and Miessner) is a vaccine of the bovovaccine type, consisting of bacilli typ. humanus and typ. bovinus, attenuated by prolonged subculturing on glycerin broth. 3) Klimmer's vaccine (Klimmer) consists of bacilli typ. humanus or typ. bovinus, attenuated by passages through the organism of cold-blooded animals. 4) Arloing's vaccine consists of bacilli typ. humanus, obtained in the form of a homogeneous culture (cultivation with frequently repeated shaking) and attenuated in their virulence. 5) Vaccine from bacilli typ. gallin. (MacFadyean, Sheather, Edwards, and Minett) was used intravenously twice with an interval of 45 days in doses of 10-50 mg. All these vaccines were tested on cattle. 6) Friedmann's vaccine (Friedmann) consists of bacilli isolated from the organism of a turtle that presented a picture of tuberculosis. It is used both in cattle and in humans—in the latter for both prophylactic and therapeutic purposes. It consists of so-called cold-blooded bacilli, i.e., acid-fast saprophytes, to which, perhaps, a certain amount of low-virulence tubercle bacilli typ. humanus may be admixed (the turtle lived in a reservoir where a watchman, sick with tuberculosis, expectorated his sputum). Friedmann's vaccine is harmless; its effectiveness is very low. 7) Ferran's alpha-vaccine (Ferran). Ferran holds the point of view that the acid-fast tubercle bacillus (gamma-bacillus, according to Ferran) represents only a certain stage of development of the tuberculosis virus. Alpha-bacilli, non-acid-fast bacilli, are widespread in nature, from which, in the animal organism, directly or through an intermediate beta-form, typical acid-fast tubercle bacilli arise by mutation. Ferran's vaccine is an emulsion of alpha-bacilli (anti-alpha-vaccine). The vaccine is widely used in Spain, Portugal, and Latin American countries with allegedly good results. It does not deserve use, since Ferran's teaching itself is not substantiated. 8) Shiga's vaccine (Shiga) consists of bacilli grown on glycerin broth with increasing amounts of trypaflavine or neutral red. Another strain of tubercle bacilli was grown with erythrosin. With the help of these strains, a sensitizing serum was obtained, used for the preparation of a serovaccine. It has not received practical application. 9) AO vaccine (Arima, Aoyama, and Ohnawa). Bacilli are grown on a medium containing saponin and a special type of lipase. Under such conditions, some strains lose acid-fastness and become low-virulence. AO has been very well studied in experiments. It is used mainly for therapeutic purposes in the initial stages of tuberculosis. 10) BCG vaccine—from Calmette-Guérin bacilli (see Bacteria, Calmette-Guérin bacillus). As of January 1, 1934, the total number of vaccinated people in France exceeded 1,400,000. The vaccine is harmless. Its effectiveness is undoubted, although the immunity it confers is less than that obtained as a result of natural infection. Of all those listed, only the BCG vaccine has practical significance at the present time. When evaluating the effectiveness of vaccines, it must be kept in mind that only vaccines consisting of virulent bacilli confer a more or less sufficient immunity. Vaccines from attenuated tubercle bacilli—and only such vaccines can be used—confer immunity to the organism that is not sharply pronounced and is short-lived. In view of this, revaccinations are necessary. The nature of the immunity that develops as a result of vaccination narrows the contingent of those to be vaccinated; at the same time, due to the peculiarities of anti-tuberculosis immunity, vaccination cannot replace social prophylaxis of tuberculosis; the vaccinated person must be the same object of this prophylaxis as the unvaccinated one. Serotherapy of tuberculosis. 1) Maragliano's serum is obtained by immunizing horses with a mixture of 1 part of tuberculous toxalbumin and 3 parts of tuberculous protein. Toxalbumin is the toxin of tubercle bacilli, separated by them during growth in broth and obtained by repeated filtration. Protein is the endotoxin of tubercle bacilli, obtained by extracting dried bacilli with water in a water bath at 90°; Maragliano combines serum treatment with vaccine therapy, applying first only serum, then serum + bacillary extract, and finally only the extract. In Italy, Maragliano's serum is still used at the present time. 2) Marmorek's serum (Marmorek) is obtained by immunizing horses with filtrates of young, non-acid-fast "primitive" bacilli. To grow such bacilli, a medium is used that is a mixture of "leukotoxic" calf serum and glycerin broth. To obtain leukotoxic serum, a guinea pig's peritoneal exudate, rich in monocytes, and an extract of its liver are injected into a calf. On Marmorek's medium, the bacilli secrete a weak toxin; he considers his serum to neutralize the true toxin of tubercle bacilli formed in the organism. The serum is administered subcutaneously daily (2-10 cm3) or per rectum (5-10 cm3) 2-3 times a week. The results are contradictory. 3) Vallée's serum (Vallée) is obtained by immunizing horses with intravenous injection of first low-virulence tubercle bacilli isolated from a horse, and then tubercle bacilli typ. humanus in increasing doses up to 250 mg; this is followed by the introduction into the veins of decanted cultures of typ. humanus and bacillary endotoxin obtained by prolonged grinding of the bacilli. Here, too, the results are contradictory. 4) Neporozhny's serum was obtained by immunizing dogs first with sensitized (according to Besredka) tubercle bacilli, then defatted, killed, and finally live tubercle bacilli. In experiments on guinea pigs, the serum proved to be very effective. 5) Ruppel and Rickmann's serum (Ruppel, Rickmann) is obtained in cattle and mules by immunizing them with live, virulent tubercle bacilli typ. humanus (intravenously). When tuberculous changes form, the animals receive increasing amounts of tuberculin, bacillary extracts, and live tubercle bacilli until insensitivity to tuberculin occurs. The serum is very rich in agglutinins and true antibodies. 6) Bruschettini's serum (serum-vaccine) is obtained by immunization with increasing doses of endotoxin and then tubercle bacilli heated for 2 hours to 60°. Endotoxin is manufactured by injecting rabbits with aleuronat and tubercle bacilli and obtaining pleural exudate from them. To evaluate the effectiveness of serum treatment, it must be kept in mind that only some sera (Ruppel-Rickmann, Vallée) contain a significant amount of tuberculous antibodies; at the same time, no serum has an antitoxic character. Thus, the only judge in the field of tuberculosis serotherapy can be the clinic. Its judgments are contradictory in nature, and therefore only in some cases and in some countries do sera find a certain application. Vaccine therapy of tuberculosis. There are only isolated attempts to use vaccines for the treatment of tuberculosis. Möller used virulent tubercle bacilli for this purpose. Sorgo used BCG, injecting intradermally 0.1-0.2 cm3 of suspension (600,000-2,400,000 bodies) and repeating injections after 2-4 weeks and longer. The number of injections is 1-6. The results are generally favorable.
V. Lyubarokii. VIII. Individual prophylaxis. Observations from tuberculosis dispensaries all over the world note a sharply increased (according to Moscow data of recent years, 6-8 times higher than among the general population) prevalence and incidence of tuberculosis among persons in direct contact with bacillus carriers (household, family contacts); an increased incidence is also noted among the medical personnel of tuberculosis hospitals caring for the most severe patients; early childhood is especially susceptible to infection. These facts highlight the necessity of a system of measures that reduce or entirely eliminate the danger of transmitting the infection from a bacillus carrier to a healthy person. In the course of many years of practice in tuberculosis institutions, a number of preventive measures have been tested and have shown their complete expediency. Breuning's studies showed that the greatest danger of droplet infection is created in the zone surrounding the patient with a radius of about 1 m. From this follows the necessity to provide the patient with a separate bed and, at the first opportunity, a separate room. Soviet legislation (a decree of the All-Russian Central Executive Committee and the Council of People's Commissars of the RSFSR) established the right of a bacillus carrier to additional space and a separate room, and for an active tuberculosis patient—to additional space of 10 m2. A circular of the People's Commissariat of Health of the RSFSR and the People's Commissariat for Internal Affairs dated January 13/19, 1928, gave specific instructions to local organs of Soviet power regarding the procedure for providing separate rooms and additional space to tuberculosis patients. In the first instance, this law applies to severe chronic cases in need of prolonged bed rest, then to patients with sharply pronounced catarrhal symptoms (danger of droplet infection). The possibility of allocating separate houses and apartments during new construction is provided for, and in factory and student dormitories—separate barracks and sections. However, in practice, this decree was not implemented everywhere and was insufficient. Therefore, the decree of the Council of People's Commissars of the RSFSR on the fight against tuberculosis (dated December 10, 1934, No. 1176), confirming the previous decree, mandates that the necessity of providing tuberculosis patients with separate rooms be taken into account during new construction. When isolating a bacillus carrier in a separate room or in a separate bed, one must especially watch for the prevention of close and prolonged contact with children under 5 years of age (sending children to nurseries and kindergartens, the French experience of long-term isolation of children in healthy families), as well as for educating the patient in correct habits regarding the handling of sputum, dishes, and personal items; such habits can make him almost completely safe for those around him. A bacillus carrier must have a spittoon (see) for collecting sputum, both a tabletop and a pocket one. Unfortunately, the use of the latter outside the home still encounters an unfriendly and squeamish attitude from those around, who avoid the patient. This circumstance must be taken into account and appropriate mass sanitary-educational measures must be carried out. It is necessary to pour a disinfectant and fly-repelling solution into the spittoon (see below). Sputum must be destroyed every day either by boiling (15 min.) or, if boiling is impossible, by flushing it into the sewage system. It is best if this operation is performed by the patient himself; in any case, children and adolescents must not be entrusted with cleaning up sputum. The patient's linen, especially handkerchiefs and towels (separately from others), must be collected in a separate pouch-bag hanging in his room, and before washing, soaked overnight in soap lye and boiled in a cauldron. Dishes, especially knives, forks, and spoons, must be distinguished from the rest, washed in a separate basin, and dried with a separate towel; the patient's clothing should be aired in the sun or disinfected as often as possible. Its cleaning must take place outside the living quarters (on a balcony, in the yard). It is best to have clothing made of washable material. Floor cleaning must be done by the wet method; every 10-15 days, the floor must be wiped with a disinfectant solution (see below). If the wall paint allows, they should be wiped up to the height of the wainscoting. Furniture, beds, windows, and doors must be wiped down in the same way. Whitewashing of walls and ceilings is recommended annually. One should remove upholstered furniture, carpets on walls and floors, and non-washable curtains and drapes. The most rational way to remove dust from walls, floors, etc., is with a vacuum cleaner. After the death of a patient or upon departure from an apartment, terminal disinfection must be performed (based on the instruction of November 17, 1929). Gas disinfection does not achieve the goal due to its superficial action. Books and other items that cannot be subjected to either dry or wet disinfection must be burned. In tuberculosis institutions where a large number of bacillus carriers accumulate, many of whom are in a period of exacerbation of the process, even stricter adherence to disinfection rules is absolutely necessary. The People's Commissariat of Health of the RSFSR twice issued a detailed 'Instruction on the performance of disinfection in institutions for the fight against tuberculosis and in the homes of tuberculosis patients'. The first instruction was sent to the localities in 1925; the second, more accurately edited but basically confirming the first, was published and sent to the localities on October 17, 1929. In a special circular in 1926, the People's Commissariat of Health drew the attention of tuberculosis institutions to the absolute necessity of disinfecting sputum, spittoons, and dishes, and supplying patients with pocket spittoons. The instruction places the duty of performing constant disinfection in tuberculosis institutions and at home on all tuberculosis institutions under the control of sanitary inspection. Junior and middle-level personnel of tuberculosis institutions, who are entrusted with carrying out disinfection, must be guided by a specially designated physician, receive proper written or printed instructions, and have the necessary solutions and equipment at their disposal. Tuberculosis institutions must have their own disinfection chambers or use district disinfection facilities. Details of the practical implementation of the instruction in accordance with local conditions must be worked out by the sanitary inspection, which is entrusted with the control of execution. In medical institutions, every patient must have a tabletop and a pocket spittoon that can withstand physical and chemical disinfection and allow for convenient cleaning. Pocket spittoons must be portable and airtight. Weak patients must have gauze or rag napkins for spitting out sputum, which must be burned. A solution of phenol or cresol, which repels flies, must be poured into the spittoons daily. Sputum must be destroyed daily after disinfection with steam or boiling in a 2-5% soda solution (30-45 minutes) or burned with peat powder. After washing, spittoons must be boiled in sterilizers. A number of special devices have been designed that simultaneously wash and steam-sterilize spittoons and disinfect sputum. In practice, one can use an autoclave, a large sterilizer, or a hermetically sealing boiler. It is very expedient to have a direct drain for disinfected sputum into the sewage system. If it is impossible to disinfect sputum by boiling, chemical disinfection is permitted (Alcadizol—a 5% solution in hot water of a mixture of 16% NaOH and black carbolic acid—4 hours; a mixture of 5% carbolic acid with equal parts of 1% HCl and 2% tartaric acid—12 hours; an aqueous 4% formalin solution—12 hours). Wet cleaning of wards and their general cleaning using the indicated disinfectant solutions—2 times a month; wetting of sputum stains on the floor for 6 hours with a disinfectant solution. Dishes must be boiled (after mechanical cleaning) for 15 minutes. Linen must be collected in bags or special canisters and counted after 6 hours of soaking in lye and 1/2 hour of boiling before washing. Handkerchiefs, napkins, and pouches for pocket spittoons must be chemically disinfected before washing, just like sputum. Clothing, robes, blankets, and outerwear must be subjected to steam disinfection or airing in the sun. Food scraps must be boiled and cooked for 15 minutes before being handed over for animal feed. During terminal disinfection in medical institutions that do not usually accept tuberculosis patients, after the discharge of a tuberculosis patient, one should proceed as in the general cleaning of a tuberculosis ward and air the ward for several days. The organization of disinfection at home (instruction, verification, etc.) is entrusted to district social assistance nurses. Personnel conducting sputum disinfection must work in rubber gloves, rubber or oilcloth aprons, and galoshes. When cleaning and brushing clothing, robes, and blankets, use headscarves and gauze respirators. After general cleaning of wards, it is mandatory to take a shower or bath. It is impermissible to take robes home or to put outerwear on over them. In order to prevent reinfection, the personnel of a tuberculosis institution must undergo a clinical examination at least twice a year (X-ray, sputum analysis, and ESR are mandatory at the slightest suspicion). All employees of tuberculosis institutions who are losing weight or frequently ill (flu, colds) must be under special observation. Newly hired medical workers who have not yet worked in tuberculosis institutions must also be under special observation for at least the first year of work.
When hiring for tuberculosis institutions, it is necessary to perform tuberculin reactions, and those who do not show tuberculin reactions (not immune to tuberculosis) should preferably not be allowed to work in tuberculosis institutions. An increase in allergic reactions, noted in medical workers while working in tuberculosis institutions, should also serve as an indication of the need for vigilant monitoring of their health. It is necessary to monitor with particular care the health of personnel working in the prosectoriums of tuberculosis institutions, laryngological departments and offices (respirators, protective shields made of celluloid or glass during laryngoscopy), X-ray rooms (protective shields for the fluoroscopy screen, daily thorough cleaning with disinfectant solutions and ventilation of premises), laboratories (gloves when working with sputum), and the registry of tuberculosis dispensaries (glass screens at the tables and windows of registrars). All these groups of medical workers must be carefully monitored (X-ray) no less than once every 3-4 months and after any illness; they must receive vacations during the best time of the year, etc. The proper organization of nutrition for personnel in tuberculosis institutions is extremely important. In 1929, the Scientific-Consultative Bureau of the Central Committee of the Medical and Sanitary Workers' Union issued an appeal-instruction to the personnel of tuberculosis institutions, concisely outlining the basic measures of personal prophylaxis. Prophylaxis of infection during contact with bacillus-excretors in production has not yet been developed, and the significance of occupational contacts for the spread of infection has also not been clarified. In any case, a significant role here is played by the level of sanitary culture of the patient and his discipline when coughing and expectorating sputum (turning the head away from the interlocutor, covering the mouth with the back of the left hand, spitting sputum into a spittoon), as well as the sanitary conditions of the workshop at the workplace (wet cleaning, spittoons, drinking fountains, in the USA, automatic machines with paper cups for water at the taps). Setting aside diet corners in canteens at factories and plants for tuberculosis workers is doubly expedient: a) the danger of infection through dishes is eliminated, b) rational therapeutic nutrition increases the resistance of tuberculosis-stricken workers. Mass measures for the prevention of the spread of infection by sick workers and employees of food enterprises, children's institutions, etc., see above (Organization of the fight against tuberculosis).
V. Khopydaan. IX. Tuberculosis and the nervous system. The pathology of the nervous system in tuberculosis is characterized by the same features that are encountered in other toxemias. If under normal conditions the nervous system is the controlling and coordinating center in relation to the functions of various organs, then in an infectious process it also participates in the formation of the body's defensive reactions. Among the afflictions of the nervous system as an organ, one can note tuberculosis of the brain, tuberculous meningitis (see Meningitis), and tuberculous neuritis. Most pronounced in tuberculosis are changes on the part of the autonomic nervous system. The autonomic complex in tuberculosis is characterized by vasomotor disorders (flushing), sweating, weak expression of skin-dermographic reflexes, dilation of the pupils and their sluggish reaction, inequality of the pupils, tachycardia, hypotension, etc. The change in the trophic action on the part of the nervous system must be considered not only as a result of a local reaction to the process, but also as a reaction of the entire organism. According to Speransky, a tuberculous focus poisons nerve cells with its toxic products, and these latter manifest their dysfunction at the periphery by a disturbance of tissue trophics and a weakening of its defensive means; thus, along the nerve "two different mutually worsening processes flow in both directions: the nerve segment is continuously poisoned by the products of the local focus, and this, in turn, is deprived of the proper degree of protection and care on the part of the former." The influence of the nervous system on the tuberculous process is confirmed by the method of neurotomy (Molotkov) used with success for tuberculous ulcers of the tongue and tuberculosis of the ankle joint. The psychic complex of tuberculous patients is characterized by irritability, frequent mood swings (depression-euphoria), easy suggestibility, fatigue, lethargy, exhaustion, egocentrism, suspiciousness, etc. A whole series of authors attempts to classify the psychic types of tuberculous patients, pointing to a certain affinity of tuberculosis with a number of psychic diseases. Some even strive to establish a specific type of psychic reactions, giving them the nomenclature of "tuberculous character." The opinions of these authors can hardly be considered at all tenable if one takes into account that tuberculosis, as a sufficiently widespread social disease, affects a huge number of people with various constitutional and characterological features. Therefore, it would be more correct, if necessary, to speak about the influence of the tuberculous process on the corresponding constitution or character, rather than to classify a specific tuberculous type of psychic reactions as a "tuberculous character." One could just as well speak of "cancerous," "ulcerous," and other "characters" corresponding to one or another disease process. In a whole series of cases, it is difficult to determine whether the tuberculous process caused the mental illness, or, conversely, whether, thanks to a painful psychic state accompanied by negative reactions (prolonged unwillingness to eat, etc.), a latent tuberculous process flared up on the basis of a weakened state of the organism. A big mistake of some authors in this area is the study of the psyche of tuberculous patients in special hospitals and sanatoriums, where the influence of the environment itself and the psychic induction of a collective of sick people is manifested. Ordinary living conditions, where we meet tuberculous patients at work and in everyday life, scattered among the general mass, do not leave an impression of psychic pathology of these patients. It should be noted the exceptional temperature endurance of tuberculous patients, who can, at a temperature sometimes reaching 39-40°, continue their normal work without experiencing unpleasant sensations. Temperature euphoria even sometimes gave the opportunity to many writers, thinkers, poets, and musicians to manifest their creativity especially talentedly during subcompensated tuberculosis (Chekhov, Belinsky, Chateaubriand, George Sand, Kant, Spinoza, Nadson, Chopin, Schubert, Mozart), when the brightness of images, clarity of thought, and depth of feelings were especially sharpened in this stage of the disease process. The increase in libido sexualis noted by some in tuberculous patients should be attributed to both the febrile (temperature) state and the prescribed excessive nutrition, general increased excitability, as well as in many cases inactivity (in sanatoriums). L. Bruoshgovsky. X. Osteoarticular tuberculosis. Tuberculosis of bones and joints belongs to the number of the most severe afflictions, entailing mass maiming, predominantly of the growing generation. In relation to the total number of tuberculous diseases, osteoarticular lesions constitute 5-10%. The greatest number of diseases falls on the first five years of life. The most frequent and earliest in the onset of the disease is the lesion of the spine, constituting 40% of the total number, then the hip and knee joints (together also constituting 40%); all other lesions account for only 20%. Thus, 4/5 of all lesions fall on these three forms, which constitute the main mass of osteoarticular lesions, and half of these patients fall ill in the first five years of their life, 2/3 in the first decade, and 3/4 in the first two decades. Such a regular connection between localization and age depends, on the one hand, on the anatomical-physiological features of growing bones—the formation of bone nuclei and their blood supply (Lexer), and on the other—on the order of inclusion of the functional load of various parts of the skeleton during the development of the child (Menard). Trauma as a producing cause plays an insignificant role, but it acquires special significance for revealing a hidden ongoing process and the exacerbation of benignly proceeding forms. Acute infectious diseases, which lower the body's resistance to the developing tuberculous process, have the same significance. Tuberculous heredity has significance only as a factor in the transmission of a known inherited weakness of the organism. Anomalies of constitution, especially asthenia, exudative lymphatic diathesis, and endocrine disorders, also influence the emergence and development of the tuberculous process in the same way. Pathogenesis. Osteoarticular lesions by their origin are secondary metastatic foci, owing their emergence to the introduction of the infectious agent from a primary focus (usually from bronchial glands) via blood vessels, mainly into the vascular-rich bone marrow of the spongy substance of growing bones. Here, conditions are created for the development of a tuberculous granuloma, which, with slow development, causes gradual resorption of bone tissue, forming small cavities or narrow tortuous passages in the bones, whereas with faster and more significant growth, the granuloma early undergoes caseous degeneration, which causes necrosis of the bone beams enveloped by it. Such "white" necrosis is gradually delimited in the form of a spongy sequestrum and subsequently can undergo partial resorption, leaving behind a real bone cavity with caseous decay, remnants of the sequestrum, and a granulation wall at the periphery. Consequently, at the basis of the development of bone foci, called by Kornev primary osteitis, lies one and the same process of primary growth of the granuloma with different rates of its subsequent development and necrosis. Studies by the Leningrad Institute of Surgical Tuberculosis (Kornev, Chistovich) did not confirm the previously expressed assumptions about special embolic infarctions (Konig, Lexer), a special caseous form, fundamentally different from the granulation one (Kremer and Wiese) (see Spondylitis). With a central position of the focus in the bone, perifocal reactive phenomena are almost absent, while with a peripheral location or growth of the granuloma through the cortical layer, sharp reactive phenomena occur, determining the clinical severity of the process. The granuloma, growing into soft tissues, receives especially favorable conditions for its growth. If this growth occurs outside the joint, then the growing granuloma, rapidly spreading along intermuscular spaces and decaying in the center, causes reactive changes around itself, ending in the development of a connective tissue capsule. As a result, so-called cold abscesses begin to form, representing peculiar lesions of soft tissues, which would be more correct to call "saccular granulomas" (Kornev), with liquid decay in the center, a zone of granulations at the periphery (membrana pyogenica of previous authors), and a connective tissue shell-sac. If this growth occurs inside the joint, then the granuloma spreads along the synovial membrane, causing its gradual degeneration with subsequent replacement by scar tissue. Approaching the cartilages, the granuloma either detaches them, spreading along the subchondral surface of the bone, or, like a snail, advances onto the cartilage, causing the destruction of the latter. Subsequently, secondary destruction of the bone surface begins, which leads to greater or lesser deformations of the joints. The cycle of development of the process ends, on the one hand, with the indicated degeneration of the entire synovial membrane and the adjacent cartilaginous surfaces, and on the other, with the delimitation in the interarticular spaces of necrotic remnants, caseous masses, and pus.
Such delimitation leads to a quieting of the process, but at the same time determines the "imperfection" of the healing processes. "Tuberculosis does not die, but only falls asleep," in the expression of Menard, which explains the frequency of subsequent exacerbations and relapses. Thus, latently progressing, conditionally benign periarticular primary osteitis (see separate table, fig. 5) is usually a source for the emergence of secondary arthritis, possessing an obvious, seemingly malignant course, but with a tendency toward a certain cyclicity, leading to a gradual quieting of the process, its transition again into a latent state, but already with a destroyed joint (Kornev) (see separate table, figs. 1-4). Primary lesions of the synovial membrane are encountered less frequently and proceed roughly according to the same type as secondary ones, usually with a slower transition to the bone. Clinical course. The same process of an initially latent course of central osteitis is observed in all bones, with subsequent changes depending on the anatomical and functional features of these bones and the tissues surrounding them. Thus, on the shafts of tubular bones around the forming central focus, a productive reaction of the periosteum develops, leading to a club-shaped thickening of the bone, the so-called spina ventosa (see separate table, figs. 6 and 8), usually with multiple lesions of the phalanges, tarsal, and metacarpal bones. In rare cases, the same changes are observed on the diaphyses of long tubular bones (spina ventosa diaphysaria—see separate table, fig. 7). The transition of the process to soft tissues is manifested by significant thickening of the latter, the formation of cold abscesses and fistulas, through which sequestered sections of bone usually exit, which often leads to a pathological fracture, displacement, and shortening of the bone. Lesions of the metatarsal bones and the wrist very quickly lead to the transition of the process to small joints and neighboring bones, giving a picture of panarthritis with multiple fistulas. Nest-like lesions of the calcaneus remain isolated the longest, giving rise to the formation of extensive central sequestra with subsequent fistulas in the soft tissues (regarding changes in lesions of the spine, see Spondylitis). Depending on the evolution of the pathological-anatomical changes, bone and joint tuberculosis has a certain sequential succession of clinical phenomena—stages—of the disease: onset, height, and subsidence. Primary periarticular osteitis gives very insignificant and indefinite, usually quickly passing pains and lameness (reactive phenomena), and only with the transition to the synovial membrane do clinical phenomena gradually develop—initially radiating pains, limitation of mobility, and muscle atrophy, and then at the height of the disease, inflammatory phenomena increase—local pain, local heat, swelling of the joint (mainly due to proliferation), contracture of the limb, displacement of the articular ends, and shortening with significant destruction of the bone. Radiologically, at the height of the disease, bone porosity and indistinctness of the joint contours increase with gradual destruction; upon subsidence, the structure reappears, density increases, and the contours become clear (phenomena of repair). Treatment. Kornev bases the rational treatment of bone and joint tuberculosis on the following principles: a harmonic combination of general and local measures, the inclusion of surgical interventions in the general system of conservative treatment, individualization in the indications and technique of individual methods, and an organic connection of individual treatment with the entire system of planned combat against surgical tuberculosis. General treatment has the goal of increasing the body's resistance to tuberculous infection, which is achieved by creating conditions of maximum physiological rest for the patient in a so-called sanatorium environment. The latter combines three main elements: regimen, nutrition, and the use of natural physical factors—light, air, temperature. The regimen serves as the basic background for this system, on which all its links are distributed in a certain expedient order. Nutrition is the basis for raising the general condition of the weakened organism; it must be sufficient, but not excessive, varied, of a mixed type, with a certain predominance of complete fats and vitamins; special diets are of no particular importance. "Sun and air," in the expression of Oehlecker, "must wash the entire shell so that the core becomes healthy." If a maximum stay in fresh air contributes only to strengthening and hardening the body, then immoderate use of the sun can cause harm. Heliotherapy is a strongly acting agent and must be strictly dosed, mainly by the amount of heat, by calories. The best combination of favorable conditions is found in climatic stations—high-mountain and seaside—but patients should be sent there only according to special indications; the main mass of patients can and should be treated at their places of residence, where appropriate conditions—sanatorium-type institutions—should be created for them. Physiotherapy is a good supplement to general treatment. In particular, in treatment with artificial light sources, the mercury-quartz lamp and the Sollux lamp enjoy special fame, being able to a certain extent to replace the sun in winter time. Drug therapy (calcium, iodine-iodoform, gold preparations, etc.) and tuberculin treatment can be considered as a supplement to the main sanatorium treatment and have no independent significance. Local conservative treatment has the goal first of all to create maximum rest for the easily vulnerable, unstable tuberculous tissues. For the majority of patients, elementary rest is achieved by a lying position on a non-sagging, flat bed. The problem of rest is solved more perfectly by orthopedic measures—immobilization and unloading. Immobilization (see) is best achieved by plaster casts—circular (figure 1), grasping two adjacent joints (in the case of spondylitis—large corsets with collars for upper thoracic lesions), or splint casts, which also include plaster beds applied in cases of spondylitis and coxitis. Unloading is achieved by a horizontal (lying) position of the patient, the application of constant traction, which relaxes his muscle contracture. During the entire active period of the disease, patients must lie down (on average 2-3 years), and then, upon the subsidence of the process, determined clinically, radiologically, and by laboratory means, they can very gradually be taught to stand and sit, but necessarily in orthopedic apparatuses, initially plaster, then removable, gelatin-formalin or celluloid, and on crutches, without stepping on the diseased limb. Muscle contractures, so frequent in tuberculosis of the joints, are initially successfully corrected by gradual traction with relatively small weights; in the future, however, they easily pass into persistent vicious positions, already connected with changes in the joints themselves (arthrogenic contractures), which it is not always possible to correct without forcible straightening, and the latter is dangerous in tuberculosis. Therefore, it is easier to prevent contractures than to treat them by conservative means. It is even more difficult to correct the so-called frequent displacement of articular ends—subluxations and dislocations, which often require surgical interventions. Cold abscesses, threatening rupture, require, on the one hand, particularly careful treatment of the underlying process by immobilization, and on the other—timely evacuation of the liquid contents with the help of punctures (see also Spondylitis). The latter are indicated mainly for progressive and large cold abscesses with tense walls and must be performed with thick, long needles aseptically from the overlying healthy tissues with oblique punctures with a shift of the skin (fig. 2). To liquefy thick and crumbly contents, one can inject a 10% glycerin emulsion of iodoform (see). The frequency of punctures is determined by the filling of the abscess and the tension of its walls. Opening closed cold abscesses and their open management is inadmissible. In particularly stubborn cases, one can attempt to enucleate the entire abscess together with the capsule. The resulting fistulas must be protected from secondary infection by carefully performed aseptic dressings without any injections. In case of infection of the fistula and the formation of purulent tracks, wide incisions are indicated. In protracted cases with scant contents, sometimes...
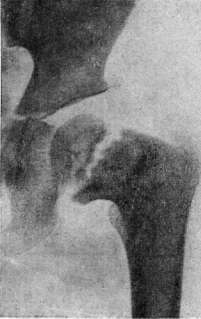
Figure 1. Central neck focus; the joint is not yet affected. Figure 2. Evolution of tuberculous coxitis—I stage; parietal neck focus with sequestrum; the joint is not involved. Figure 3. Evolution of tuberculous coxitis (the same case)—II stage; the joint is involved; destruction and rarefaction of the head; expanded acetabulum; height of the disease. Figure 4. Evolution of tuberculous coxitis (the same case)—III stage; subsidence of the process, reparative phenomena.
Figure 5. Epi-metaphyseal tuberculous osteitis of the lower end of the femur; latent course. Fig. 6. Spina ventosa; ossifying periostitis of the V metacarpal bone. Fig. 7. Spina ventosa diaphysaria. Fig. 8. Spina ventosa with fistulas.
Figure 1. Circular plaster cast: a, b—incorrectly applied; c—correctly applied.
treatment and have no independent significance. Local conservative treatment has the goal first of all to create maximum rest for the easily vulnerable, unstable tuberculous tissues. For the majority of patients, elementary rest is achieved by a lying position on a non-sagging, flat bed. The problem of rest is solved more perfectly by orthopedic measures—immobilization and unloading. Immobilization (see) is best achieved by plaster casts—circular (figure 1), grasping two adjacent joints (in the case of spondylitis—large corsets with collars for upper thoracic lesions), or splint casts, which also include plaster beds applied in cases of spondylitis and coxitis. Unloading is achieved by a horizontal (lying) position of the patient, the application of constant traction, which relaxes his muscle contracture. During the entire active period of the disease, patients must lie down (on average 2-3 years), and then, upon the subsidence of the process, determined clinically, radiologically, and by laboratory means, they can very gradually be taught to stand and sit, but necessarily in orthopedic apparatuses, initially plaster, then removable, gelatin-formalin or celluloid, and on crutches, without stepping on the diseased limb. Muscle contractures, so frequent in tuberculosis of the joints, are initially successfully corrected by gradual traction with relatively small weights; in the future, however, they easily pass into persistent vicious positions, already connected with changes in the joints themselves (arthrogenic contractures), which it is not always possible to correct without forcible straightening, and the latter is dangerous in tuberculosis. Therefore, it is easier to prevent contractures than to treat them by conservative means. It is even more difficult to correct the so-called frequent displacement of articular ends—subluxations and dislocations, which often require surgical interventions. Cold abscesses, threatening rupture, require, on the one hand, particularly careful treatment of the underlying process by immobilization, and on the other—timely evacuation of the liquid contents with the help of punctures (see also Spondylitis). The latter are indicated mainly for progressive and large cold abscesses with tense walls and must be performed with thick, long needles aseptically from the overlying healthy tissues with oblique punctures with a shift of the skin (fig. 2). To liquefy thick and crumbly contents, one can inject a 10% glycerin emulsion of iodoform (see). The frequency of punctures is determined by the filling of the abscess and the tension of its walls. Opening closed cold abscesses and their open management is inadmissible. In particularly stubborn cases, one can attempt to enucleate the entire abscess together with the capsule. The resulting fistulas must be protected from secondary infection by carefully performed aseptic dressings without any injections. In case of infection of the fistula and the formation of purulent tracks, wide incisions are indicated. In protracted cases with scant contents, sometimes...
Figure 2. Rules for puncturing a cold abscess: A and B—incorrect technique of direct puncture—straight channel; C and D—correct technique; puncture from the side—zigzag channel; E and F—incorrect technique; G—correct technique.
For fistulas, forced treatment by injecting 1-3 cm3 of a 10% solution of CuSO4+ZnSO4 (Franke) is sometimes used. In general, however, it is easier to prevent fistulas than to treat them.
Surgical interventions, belonging to the category of local measures, should only supplement the primary sanatorium-orthopedic conservative treatment and be combined with the latter into one general system. A portion of surgeons (the Leningrad school) has recently begun to resort to the operative removal of these delimited foci for the final liquidation of the process: in bones—by means of necrotomy and curettage with subsequent iodoform-vaseline filling; in joints—by means of so-called economical resections. Timely removal of periarticular focal lesions prevents the development of secondary arthritis (radical-prophylactic operation), and timely amputation in progressive purulent joint lesions prevents the development of amyloidosis and saves from death. A significant portion of surgeons (Krasnobaev, et al.) considers this radicalism unjustified. Among the therapeutic-auxiliary interventions that improve the result of conservative treatment, osteoplastic fixation of the spine (see Spondylitis) and extra-articular arthrodesis for coxitis are particularly well-known. Various interventions proposed for the purpose of changing the nature of the course of the process itself—pegs (R. Lavall, Vreden), osteotomies (Kozlovsky), sympathectomies (Leriche), neurotomies (Molotkov), etc.—have not yet emerged from the development stage and therefore cannot be recommended for mass application. Finally, for the correction of persistent malpositions, so-called corrective operations are used, primarily osteotomies, which are indicated mainly in cases of complete bony ankylosis. Indications for the listed interventions are determined by age, localization, stage, and complications. The old formula of Sorrel, that conservative treatment is indicated for children, resections for adults, and amputations for the elderly, while generally retaining its significance, is being revised at the present time, since according to clinical observations by Kornev and others, in children, especially of an older age, resections can be successfully applied, provided that one operates in the stage of subsidence. Such interventions are indicated mainly for the knee joint, where the operation used as the concluding act of treatment for the removal of a delimited focus during the subsidence of the process, the so-called extra-articular economical resection according to Kornev (Figure 3), provides a cure for the process with ankylosis
Figure 3. Extra-articular economical resection of the knee joint. (According to Kornev.)
in the correct position, without disturbing bone growth (Gelikova). This experience should be applied with great caution to the hip joint, where intrafocal interventions are best combined with additional extra-articular arthrodesis to obtain firm ankylosis. The shoulder joint requires surgical intervention more often than the elbow and ankle joints. For the latter, it is recommended to remove the frequently affected talus—to perform a so-called astragalectomy (de la Haye, Sorrel). Finally, one must mention operations for fistulous Tuberculosis, if the source of the latter is an infected bone cavity, usually with a sequestrum. If there is an isolated lesion in the bone, then curettage of the cavity with subsequent iodoform-vaseline tamponade according to Kornev (filling with a paste of 30:100 composition) is indicated. This method has proven itself especially well for Tuberculosis of the calcaneus and for spina ventosa. The fight against bone-joint Tuberculosis. The organization of the fight against bone-joint Tuberculosis must be built on an assessment of the social significance of these diseases as a factor of mass crippling of the rising generation. Preventive measures require, first of all, the timeliness of providing medical assistance, for which it is necessary to have a specific network of specialized institutions and the implementation of a specific plan. The basis of such a plan must be: 1) broad coverage of the entire population with qualified assistance; 2) detection of all patients in a given district and, in particular, detection of early forms; 3) implementation of dispensary registration for these patients and provision of all types of assistance to them—medical and social; 4) timely treatment of fresh, non-neglected cases in order to prevent complications; 5) differentiation of the tasks of treatment from the tasks of caring for cripples and chronic fistula patients; 6) unification of inpatient, outpatient, and home (patronage) care into one general system having a "staged" character. In addition, in each region, its own support point must be created—a clinical institution that should become a scientific-methodological center for the entire periphery.
p- Korne". XI. Tuberculosis in children. Statistical data. The relationship between infection rate, morbidity, lethality, and mortality from tuberculosis in different periods of childhood reflects the significance and influence of the age factor on its course. Data accumulated in large quantities on the state of tuberculin reactions in children of different age groups testify to a regular increase with age in the number of children infected with tuberculosis. The significant fluctuation in the percentage of positive tuberculin reactions in children of the same age according to the data of different authors is caused mainly by the different nature of the examined material. Numerical data from predominantly older authors, based on examinations of selected material, children in hospitals, dispensaries, and clinics, naturally exceed the data on the number of positive tuberculin reactions in children's collectives, in children in nurseries, kindergartens, and schools. For example, when examining 5,000 nursery children in Moscow, a positive Pirquet reaction was noted at the age of 0-1 year - 5%, 1-2 years - 13%, 2-3 years - 24% (Vasich, 1925-26) - a significantly lower percentage than various authors usually indicate for children of this age; when examining children in nurseries of the Zamoskvoretsky district of Moscow and children in nurseries of the city of Orekhovo-Zuyevo in 1932, this percentage turned out to be even lower. In full accordance with the data on tuberculin reactions are the data from autopsy material, confirming the increase in the infectivity of children with their age. Old data from classical authors and more recent data note an increase with age in the number of tuberculous findings at autopsy, reaching, according to Naegeli, 96% at the age of 18. This increase is due to the finding of limited tuberculous lesions, often a latent focus in children who died not from tuberculosis, but from an accidental disease. Thus, in this autopsy material, the quantitative ratio between cases with severe tuberculous lesions and accidental findings of small tuberculous changes in children who died from other diseases changes with age. In the first year of life, the percentage of cases with severe tuberculous changes in relation to all cases with findings of tuberculous changes at autopsy approaches 100, but with age it decreases, reaching, according to Naegeli, 29% at the age of 18. This regular increase with the age of children in the number of tuberculous lesions discovered accidentally at autopsy is noted by all statistical data. In children of the first years of life, a latent primary focus or limited lesion of the bronchial glands is significantly less often noted as an accidental finding at autopsy. Infection at this age leads to a pronounced disease, and the more pronounced, the younger the child. To the same extent as the fact of the increase in tuberculosis infection with age, the decrease in lethality among infected children with age is considered established. The highest lethality is noted among children of the first years of life, especially the first year. In the "pre-tuberculin period", when the entire circle of children infected with tuberculosis was not taken into account and only severe cases of the disease were recognized, the lethality of children in the first year of life infected with tuberculosis was expressed as 100% according to these old data. With the introduction of tuberculin tests into practice and the improvement in the recognition of tuberculosis in children, the circle of accounted for infected and tuberculosis-sick children expanded significantly, and thereby the indicated lethality figures also changed. Thanks to good accounting and careful observations of infected children, especially from bacillary foci, it turned out that even among children infected in the first months of life, there is a significant percentage of survival. The "average lethality figure" for children infected in the first year of life, according to the summarized material of various authors, approaches 60%. This "average figure" of lethality has a very relative significance, since it was derived from the most diverse material, with lethality fluctuating from 20% and lower among a wider circle of infected children in dispensary material, and 80-100% lethality in hospital and clinic material, i.e., selected severe material covering only a part of children infected with tuberculosis. Despite the more favorable assessment of the prognosis of tuberculosis in a child infected even in the first year of life, which has changed in recent years, the position remains completely unshakable that lethality in the first months and years of life significantly exceeds lethality in subsequent periods of childhood. This greater lethality in early childhood, especially in the first year of life, causes high mortality from tuberculosis, which in this period significantly exceeds mortality from tuberculosis in older children. Mortality from tuberculosis in infancy and early childhood is the most significant, many times exceeding mortality in other age groups of childhood; decreasing in subsequent years, it drops sharply after the age of 4, giving another significant rise in the period of puberty (see Tuberculosis Statistics, table 3 - mortality in Moscow). With this high mortality from tuberculosis in children of the first year of life, it is relatively small in comparison with the high general mortality from other diseases in this period of life. Tuberculosis as a cause of death in children of this age occupies one of the last places, standing far behind mortality from "congenital weakness", digestive and nutritional disorders, pneumonia, and acute infectious diseases. Thus, the relationship between infection rate, morbidity, lethality, and mortality in different periods of childhood is such that in infancy and early childhood, with a relatively small number of children infected with tuberculosis, we have a large number of sick children, moreover with severe forms of the disease, which give high lethality and mortality. With age, tuberculosis infection increases, but the percentage of severely ill patients decreases, the tendency toward generalization of the process becomes less pronounced, and thus lethality and mortality decrease. The ratio between the number of infected and tuberculosis-sick children in early age differs sharply from this ratio in subsequent periods of childhood. Among nursery-age children infected with tuberculosis, the percentage of patients with pronounced signs of the disease and clinical identification of the localization of the lesion is significantly higher than among preschoolers and schoolchildren. All this gives particularly great social significance to tuberculosis in infancy and early childhood. The severe course and high mortality from tuberculosis in the pubertal period also force us to pay special attention to the fight against tuberculosis in adolescence. Methods of infection and pathways of penetration of the tubercle bacillus into the child's body - see above, Tuberculosis pathogen. Fundamentals of pathogenesis. The pathogenetic understanding of tuberculosis in children in recent years has been under the significant influence of Ranke's doctrine on the cyclic course of tuberculous disease in humans (see above - pathological anatomy and pathogenesis). From this very point of view, it is very important to note that the pathomorphological characteristic of his secondary stage given by Ranke is essentially a characteristic of childhood tuberculosis. The tendency toward generalization of the process, toward its spread by all pathways - per continuitatem, lymphogenously, hematogenously, and intracanalicularly (bronchogenously), the pronounced localization in lymph nodes, primarily intrathoracic, the tendency toward perifocal inflammation around foci, which characterize Ranke's second stage, find their expression in the picture of tuberculosis in children, and the more sharply, the younger the child. The regular decrease with the age of children in the number of severe forms of tuberculosis and the decrease in mortality clearly testify to the great significance of the age factor and reflect the peculiarities of the age-related reaction of the organism to tuberculous infection. Age, however, is not the only factor determining the reactivity of the organism and the form of tuberculous disease. We also encounter in adults with late infection the picture and forms of childhood tuberculosis (see Pulmonary tuberculosis, clinical forms of pulmonary tuberculosis). In infancy and early childhood, we encounter, along with severe forms of the disease with all the pronounced characteristic features of the "Ranke secondary stage", also mild forms of the disease without significant anatomical spread of the lesion. Within the framework of the peculiarity of the age-related reaction characteristic of a child, we have a very polymorphic course of tuberculosis in him, conditioned by a whole complex of constitutional and conditional factors, geno- and paratypic influences. A whole series of exogenous factors - the method and nature of infection, the massiveness of the infection, the virulence of the pathogen, superinfection - are given great importance regarding their influence on the course and outcome of tuberculous disease in a child. The significance and influence of the entire social environment in which the child resides, in particular the state of care and feeding, as well as the influence of intercurrent diseases suffered, on the form and course of tuberculosis in a child are very evident. Acute infectious diseases (measles, influenza, etc.) are particularly important activators of tuberculosis in a child, often contributing to the emergence of miliary tuberculosis and meningitis. It is not always easy to account for the exo- and endogenous causes leading to an exacerbation of the process in a child and causing the undulating course of tuberculous disease characteristic of it.
Periods of exacerbation, expressed pathomorphologically in the emergence of perifocal infiltrations around old foci, in the appearance of new foci, metastases, or the eruption of tubercles in various organs, are replaced by a period of quiescence. Along with taking into account the individual influences of the complex paratypic complex, one must also strive to consider genotypic influences, individual resistance or lability to tuberculous infection. This influence of genotypic factors on the course of the tuberculous process is still a poorly developed problem. In the picture and course of a tuberculous disease in a child, which is conditioned by numerous factors and represents an equation with many unknowns, the influence of elements of the social environment is quite indicative and clear. Clinical forms and course of tuberculosis in children. The main features characteristic of childhood tuberculosis find their most vivid expression in infants and young children. It is precisely at this age that significant development of tuberculous lymphoma in the bronchial and mesenteric glands is noted in tuberculous children, as well as pronounced perifocal inflammatory lesions around foci, and above all, the primary focus in the lung, and a tendency for the process to spread to various organs and to generalize. But despite this pronounced tendency of the process at this age toward a more severe course, even in the first months of life, localized forms with insignificant spread of the disease are encountered, which proceed relatively favorably. With the child's age, the percentage of children infected with tuberculosis without any signs or with unexpressed signs of the disease grows, the number of children with limited and insignificant lesions of the bronchial glands, not extending beyond the formation of the primary complex, increases, the tendency toward multiple spread of the process in various organs decreases, and the percentage of miliary tuberculosis and tuberculous meningitis decreases. The onset of tuberculous disease, even in children in the first years of life, does not always manifest noticeably. The described symptoms—dyspeptic phenomena, weight stagnation, poor appetite and mood, etc.—cannot, of course, be considered pathognomonic for tuberculosis and rarely fix attention toward tuberculosis. Initial fever, noted by some at the time of the appearance of the tuberculin reaction as a sign of beginning tuberculous disease, is rarely observed. Tuberculous invasion and the pre-allergic period in the vast majority of cases proceed latently. The pre-allergic period, i.e., the period from infection to the appearance of the first tuberculin reaction, lasts on average from 6 to 8 weeks. By the time the tuberculin reaction appears, in some cases, intrathoracic changes are also noted in the form of a lesion in the lung associated with the primary focus. In a significant percentage of cases, and the greater the older the child is, tuberculous invasion throughout the entire subsequent observation manifests only by the presence of a positive tuberculin reaction. These tuberculosis-infected children, who give a positive tuberculin reaction upon examination but do not show either clinical signs of disease and general disorders, or local changes in the form of a definite localization, according to the classification adopted at the IV Congress, are referred to the 'status allergicus' group. Tuberculosis-infected children who do not show pronounced and clear clinical signs of intrathoracic localization, but who show signs of general disorder, such as: undernourishment, anemia, subfebrile temperature in the presence of peripheral polyadenitis, are considered by the same classification to be suffering from 'chronic tuberculous intoxication.' The difficulty of identifying the quantitative and qualitative nature of bronchial gland lesions by physical examination methods and X-ray (see Bronchoadenitis) makes it necessary to take into account with particular care general disturbances of the organism, especially their complex: nutritional status, temperature reaction, morphological changes in the blood, ESR, etc. Thus, symptoms of general disturbance, characterizing the degree of tuberculous toxemia, are a very important supplement to the data of physical examination and X-ray data, allowing, together with them, to have a judgment about the nature of the process. Nevertheless, it must be emphasized that the evaluation of many symptoms, such as: disturbed nutritional status, anemia, as signs of the manifestation of tuberculous intoxication, must be performed very cautiously in view of the tendency of children, especially infants and young children, to develop dystrophy and anemia under the influence of the most diverse alimentary and infectious factors. To the same extent, this applies to older children, especially in the evaluation of unexplained fever and subfebrile temperature, which occurs in inflammatory lesions of the nasopharynx, latent pyelitis, autonomic instability of thermoregulation, etc. The picture of general disturbances in bronchoadenitis is very variegated and polymorphic, yet in many cases of pronounced bronchoadenitis, neither noticeable weight loss, nor anemia, nor temperature reaction is noted. All this has recently caused a skeptical attitude toward the symptom complex of 'chronic tuberculous intoxication.' In any case, the opposition existing in the proposed classification of the IV Congress of forms of tuberculous disease without clearly expressed clinical localization to so-called local forms must be considered unsuccessful, just as the attempt to oppose the group of 'chronic tuberculous intoxication' to 'bronchoadenitis' is inadmissible. This opposition is to a large extent based on the underestimation of X-ray examination in the diagnosis of tuberculosis in children and the overestimation of the diagnostic significance of individual symptoms and their combinations in tuberculosis in children. Tuberculosis of the bronchial glands in the form of extensive and massive lesions, creating conditions for characteristic clinical symptoms and X-ray data, is encountered more frequently the younger the child is (see Bronchoadenitis). In the presence of an obligatory reaction on the part of the bronchial glands in the form of greater or lesser spread of changes across their various groups, sometimes exceeding in their size the lesions in the lung, the most polymorphic picture of pulmonary changes is noted (see Tuberculosis of the lungs, Tuberculosis of the lungs in children). The younger the child, the more sharply expressed is the tendency toward generalization of the process, and we are entitled to consider every severe case of tuberculosis in a young child as a generalized form, in which a significant part of the localization remains hidden. Often, localization in the bronchial and mesenteric glands, solitary tubercles of the brain, parenchymal organs, tuberculosis of the intestine, etc., remain hidden. In children in the first year of life, such forms with hidden generalization often proceed under the guise of severe nutritional disorder, severe atrophy. A classic expression of hematogenous generalization is miliary tuberculosis. According to the course and character of the eruption, acute, subacute, and chronic forms of miliary tuberculosis are distinguished. Acute miliary tuberculosis proceeds under the guise of an acute infectious disease in cases with fresh infection or in cases where it has joined an insignificantly expressed lesion in the lung and bronchial glands. In some cases, it proceeds with pronounced pulmonary phenomena (pulmonary form of acute miliary tuberculosis): dyspnea, cyanosis, with meager percussion and auscultation data and a significant temperature reaction. Radiography in the majority of cases reveals a picture characteristic of miliary tuberculosis of the lungs of disseminated small-focal lesions—'marble lung,' 'starry sky,' etc. (see Tuberculosis of the lungs, Tuberculosis of the lungs in children). Where acute miliary tuberculosis proceeds under the guise of an undefined febrile disease (typhoid form, septic form), an X-ray of the chest also often unexpectedly reveals a picture of disseminated tuberculosis of the lungs. Tuberculous meningitis often quickly cuts short the life of the child in these forms. In other cases of miliary tuberculosis, meningeal phenomena early on come to the fore in the clinical picture, and these forms rightfully bear the name of meningeal forms of acute miliary tuberculosis (see Meningitis, tuberculous meningitis). In cases with a subacute course, along with a clinically often hidden tubercular eruption, pronounced localizations appear in organs: skin tuberculids, solitary tubercles in the brain and parenchymal organs, tuberculous otitis and mastoiditis, etc. In the clinical picture, a wave-like course of the disease is noted, as it were, in the form of periodic exacerbations leading to new eruptions and the appearance of new metastases. Chronic miliary tuberculosis is a rare form with a latent course. Extrapulmonary localization of the tuberculous process, given its tendency to spread in various organs, is frequently encountered in young children. The younger the child, the more sharply expressed is the multiplicity of external localization: cutaneous tuberculosis (scrofuloderma), tuberculous lymphadenitis, bone tuberculosis (spina ventosa), and their combination with intrathoracic lesions—bronchoadenitis and pulmonary lesions, predominantly of an infiltrative nature. External tuberculosis as an independent clinical form is noted more frequently from the age of 2-3 years. Tuberculosis of the skin. Among skin lesions in children, the following are encountered: a) papular, or papulonecrotic tuberculids, b) scrofuloderma, c) lichen scrofulosorum, d) less frequently—nodules of lupus (lupus vulgaris) (see.
Tuberculous skin diseases). Tuberculids erupt on various parts of the skin, preferably on the buttocks, back, on the extensor surfaces of the limbs, on the face, and on the fingers. Tuberculids, according to the observations of Zimbler, especially in infants, often accompany severe forms of tuberculosis and thus have not only valuable diagnostic significance, but to a certain extent, prognostic significance as well. Scrofulodermas, on the contrary, are often combined with other extrapulmonary localizations and with forms of intrathoracic tuberculosis with a favorable course. Tuberculous lymphadenitis. Peripheral tuberculous lymphadenitis in the form of a pronounced, limited lesion of a separate group of lymph nodes as an independent clinical form is encountered mainly in preschool and school-age children. At the same time, an anatomical lesion of the peripheral lymph nodes in severe cases of tuberculosis in children, especially in infants and young children, is encountered, judging by autopsy data, very often. These peripherally affected tuberculous lymph nodes are not always clinically detected, especially the deeper ones that are difficult to palpate. Significantly enlarged and sharply dense lymph nodes palpable in tuberculous children ("pebble glands," as Kisel expressed it) may arouse suspicion regarding their tuberculous nature, but this does not, in any case, give the right to consider that the character of the palpable glands, their size, and density are a pathognomonic symptom for tuberculosis. The uniform polyadenitis described in tuberculosis with equally pronounced density of all or the predominant number of groups of peripheral glands and the picture of micropolyadenitis cannot be considered a pathognomonic symptom for tuberculosis. Thoracic glands are often palpable in tuberculous children, but they are also encountered in children with other chronic diseases of the lungs and pleura. Osteoarticular localization of tuberculosis (see Gonitis, Spondylitis, Coxitis). In early age, lesions of the small bones of the hand and foot are often noted (see Hand, Foot), and not infrequently, lesions of the flat bones of the skull and face, and in many cases, widespread lesions of many bones, both tubular and flat—forms with multiple bone localization. Tuberculous otitis-mastoiditis, which proceeds sluggishly and covertly, are frequent localizations in tuberculous children. Phlyctenular keratoconjunctivitis is an extremely frequent tuberculous manifestation. Keratitis in tuberculosis in children, being distinguished by great persistence, often leads to a decrease in and loss of vision (see Keratitis). Scrofulotuberculosis, scrofulosis. Since Czerny gave a classic description of exudative diathesis, we have begun to distinguish from the mass of "scrofulous children," on the one hand, tuberculous diseases with a predominantly external localization, and on the other, non-tuberculous cases with lesions of the skin and mucous membranes, which we classify as manifestations of exudative diathesis. At the same time, however, this group of tuberculous children for the most part has such a peculiar clinical picture and character of the course of the process that it is quite appropriate in relation to this group of children to retain the name scrofulosis, or, better, scrofulotuberculosis. In these children, along with the extrapulmonary localization of the process—tuberculosis of the lymph nodes, skin, small bones, phlyctenules—non-specific inflammatory changes of the skin and mucous membranes are noted: impetiginous-eczematous skin lesions, runny nose, thickening of the upper lip, giving the child a peculiar habitus—facies scrofulosa. According to the accepted interpretation, these forms represent a combination of tuberculosis with exudative-lymphatic diathesis. Tuberculosis in an exudative, lymphatic individual gives such a peculiar picture of scrofulosis. Without denying the significance of constitutional peculiarities in the manifestation of this peculiar reaction of the child's organism to tuberculous infection, one must still consider that the nature of nutrition—carbohydrate food (bread, potatoes)—and the environmental conditions in which the child resides (pauperism) have a great influence on the manifestation of this peculiar reactivity of the organism and play a not unimportant role in the genesis of these forms of tuberculosis. Diagnosis. 1. An important basis for diagnosis is, first of all, the anamnesis, which often gives indications of contact with tuberculous parents, who often do not know about their tuberculosis, or other family members, not infrequently with tuberculous old people, "senile coughers," or with tuberculous neighbors in the same apartment (apartment contact). A history collected with due completeness, reflecting the mortality of other children in this family, provides not only material for the correct recognition of the disease in the child, but not infrequently reveals a previously hidden source of infection. Anamnestic data about past illnesses, in particular about acute infectious diseases, diseases of the respiratory tract, pneumonia, and about the nature and development of the given disease, are very important for diagnosis and differential diagnosis. 2. Clinical symptoms. The diagnostic significance of clinical symptoms is based not on the assessment of the pathognomonicity of each of them individually, but, as with any disease, on comparing them with each other, with data from the anamnesis, X-ray data, data from tuberculin reactions, and data from other studies. With such a comparison, individual clinical symptoms acquire much greater diagnostic significance than in their isolated assessment. Pronounced fever is far from mandatory even in severe, far-advanced cases of tuberculous disease. Generalized forms, miliary tuberculosis, disseminated pulmonary tuberculosis, and caseous pneumonia often proceed, especially in infants and young children, without pronounced fever, apyrectically (see Pulmonary tuberculosis, Tuberculosis of the lungs in children). The widespread opinion that subfebrile temperature is a frequent, if not constant, sign of latent tuberculosis found its critical assessment among pediatricians much earlier than among therapists. Cough, its duration, and character have great diagnostic significance, often allowing one to even judge the localization of the lesion: a ringing bitonal cough—in bronchoadenitis, with abundant sputum—in bronchiectasis, with abundant purulent discharge—in lung abscesses and suppurating cavities (see), etc. (see Bronchoadenitis, Pulmonary tuberculosis). Dyspnea—both as an increase in the frequency of breathing and a change in its character—attracts attention and in many cases characterizes the form of the lesion: expiratory stridor in tumorous bronchoadenitis, rapid breathing along with meager physical changes in miliary pulmonary tuberculosis, etc. (see Pulmonary tuberculosis). Disorders of digestion and nutrition, which so often accompany tuberculosis in a child, especially in the first year of life, should far from always be regarded as a manifestation of tuberculous disease, but are often caused in tuberculous children by other etiological factors: alimentary, enteral, and parenteral infections, past intercurrent diseases, etc. Far from always does a pronounced and widespread tuberculous disease, even in a young child, lead to a sharp disturbance of the child's nutrition, to pronounced dystrophy. In the presence of a sharply pronounced picture of a disorder of digestion and nutrition—acute or chronic—in a tuberculous child, especially with a poorly expressed spread of the process, one must always think also of another, besides tuberculosis, etiology of these disorders. Along with this, a widespread tuberculous disease often proceeds in a child under the guise of a severe nutritional disorder, and in some cases of such severe atrophy, a significant part of the localization of the tuberculous process remains hidden: intestinal localization of the process, lesion of the mesenteric glands (tabes mesaraica of old authors), hidden universal tuberculous lymphadenitis (see Tabes mesaraica). Percussion and auscultatory data in their comparison with each other and subsequent comparison with data from fluoroscopy and radiography have great diagnostic significance (see Pulmonary tuberculosis, Tuberculosis of the lungs in children). 3. Fluoroscopy and radiography (see Pulmonary tuberculosis, X-ray diagnostics, Tuberculosis of the lungs in children). 4. Tuberculin diagnostics. A positive tuberculin reaction means that the given child is infected with tuberculosis, but it does not testify that the given child is sick with tuberculosis; it does not provide a basis for judging the degree of spread of the tuberculous process in the organism, about its "activity," nor does it provide a basis for a prognosis. However, the circumstance that the numbers of those infected and those sick with tuberculosis diverge sharply only in older children, but converge and approach each other in children of the first years of life, gives the tuberculin reaction great diagnostic significance precisely in early childhood. The younger the child, the more likely it is that this or that lung lesion, bone lesion, or other unexplained disease turns out to be tuberculous in the presence of a positive tuberculin reaction. The older the child, the more often we encounter phenomena of non-tuberculous disease in a child infected with tuberculosis in cases difficult to diagnose. A negative tuberculin reaction does not always mean that the child is free from tuberculosis.
The reaction may be negative: a) in an infected tuberculous child in the pre-allergic period (see above); b) in a tuberculous child with a far-advanced process of caseous pneumonia, generalized tuberculosis—'negative anergy' (in contrast to 'positive anergy,' when the organism, being in a good state, ceases to react to tuberculin, which is observed, for example, after tuberculin therapy); c) in a tuberculous child during an acute infectious disease, especially measles, but sometimes also with pertussis, diphtheria, etc. Occasionally, one has to state a temporary anergy in tuberculous children without being able to find any explanation for it. It is often possible to note a positive Pirquet reaction only after repeating it a week later. In some cases, with a pronounced tuberculous disease, only the intradermal Mantoux reaction persistently turns out positive, while the Pirquet reaction remains negative for a very long time. Explanations for all these facts must be sought in the state of the autonomic nervous system, which plays a large role in the mechanism of allergy. Of the proposed methods of using tuberculin for diagnostic purposes, Zimbler uses only the cutaneous (see Pirquet reaction) and intradermal (see Mantoux reaction) reactions; the subcutaneous reaction (Hamburger) is superfluous and not harmless. It is recommended to perform the intradermal reaction (Mantoux) only after it has been clarified that the cutaneous reaction is negative; otherwise, not knowing the degree of allergy, by starting immediately with the intradermal reaction, one can obtain a sharply pronounced general (fever, malaise), local (large redness, swelling, lymphangitis, regional lymphadenitis), and sometimes even a focal reaction (exacerbation in the lung). The Mantoux reaction is performed starting with a dilution of 1:10,000 (No. 4), increasing the concentration of tuberculin in the event of a negative reaction at intervals of 5-7 days in the following order: 1:1,000 (No. 3), 1:100 (No. 2), 1:10 (No. 1). The greater sensitivity of the intradermal reaction in comparison with the cutaneous one is its significant advantage, but at the same time, it is necessary to treat its evaluation with great caution and consider only clearly expressed papules and redness, significantly exceeding the control reaction, as a positive Mantoux reaction; the size of the redness and papule should be no less than 10 mm. As a liquid for control, it is best to use condensed broth diluted according to the tuberculin dilution with physiological saline solution, or a 0.25% solution of Acid. carbolic in physiological saline. The age of the child and his condition cannot serve as a contraindication for performing the Pirquet reaction; a severe condition and high fever with a strong suspicion of the tuberculous nature of the disease may be a contraindication for performing the Mantoux reaction. 5. Examination of sputum for Koch's bacilli is an exceptionally important and valuable method, the data of which often allow for a final decision on the diagnosis in favor of tuberculosis. 6. The morphological composition of the blood and the erythrocyte sedimentation rate (ESR) serve as an aid for characterizing the process, its activity, the degree of intoxication, predetermine the approach to therapy, and provide material for prognosis, but the direct significance of these data for diagnosis should not be overestimated. Tuberculosis in childhood does not belong to anemia-causing diseases; moderate anemia in it develops slowly, a sharp degree of anemia, especially with an unpronounced tuberculous disease, is always associated with another etiology besides tuberculosis and often finds its explanation in the presence of a secondary infection. 7. Serological reactions with complement deviation have not found their practical application in the diagnosis of tuberculosis in children. Therapy. The basis of treatment for tuberculosis in a child is a rational hygienic-dietary regimen. Rational feeding and nutrition, which constitute the main prerequisite for the proper growth and development of the child, occupy an important place in this regimen. Diet therapy, built on the principle of preferring one food ingredient to the detriment of another, has not found its application in tuberculosis in children. The important physiological significance of carbohydrates for a growing organism does not give the right to limit their intake at the expense of increasing the amount of protein and fat. At the same time, taking into account especially the arguments put forward recently in favor of the specifically beneficial effect of food protein in tuberculosis (increasing the buffer capacity of the organism), one must strive to ensure at least 20% protein in the child's food. Along with complete proteins, it is necessary to provide food with fat containing additional factors A and D. Therefore, the administration of cod liver oil is mandatory for a tuberculous child. Food should also be rich in other vitamins (C), and in view of persistent anorexia in the majority of tuberculous children, it should be tasty and contain a certain amount of fiber (fruits, vegetables). Proper care and regimen, hygiene in the child's environment, and maximum use of fresh air are also the basis of treatment for a tuberculous child. There are no contraindications for treating a tuberculous child with fresh air that depend on the child's condition, just as there should be no contraindications depending on weather conditions. Tuberculous children use fresh air regardless of the air temperature and other meteorological factors, provided they are protected from overheating or excessive cooling in a place sheltered from sharp wind, snow, and rain. The number of hours spent in the air varies depending on climatic conditions, the time of year, and meteorological conditions from 3-6-8 hours to staying in the air around the clock. The favorable effect of aerotherapy comes down to the impact on the child's metabolism, an increase in oxidative processes in the organism, and an improvement in the child's appetite, sleep, and mood. The effect of aeration is more noticeable and intense with the simultaneous direct exposure of the child's skin to a significant amount of reflected sunlight, during air baths. Heliotherapy, i.e., the use of direct sunlight, should be treated as a significantly harsher physical agent, in relation to which there are its own indications and contraindications. Caution in sun treatment for young children is dictated first of all by the danger known to everyone of overheating with all the consequences resulting from it for children of this age. Sun treatment is contraindicated in cases of a tendency toward dissemination of the process, in hemoptysis, etc. Heliotherapy is especially indicated for extrapulmonary tuberculosis: bone-articular, skin tuberculosis, lymphadenitis, etc. For these same forms, the use of a mercury-quartz lamp is indicated, while caution is necessary for pulmonary forms. Indications and contraindications for any other irritation therapy (Reiztherapie), to which various modifications of protein therapy can be attributed, including treatment with sera, hemotherapy, etc., are based on this same approach. Specific irritation therapy, to which tuberculin therapy belongs, finds few supporters in tuberculosis in children. Drug treatment for tuberculosis comes down to the use of a limited arsenal of symptomatic agents: narcotics—belladonna, codeine, luminal—for severe coughing and pronounced phenomena of compression in tuberculous bronchoadenitis; iron and liver preparations for concomitant anemias. The popular use of calcium preparations does not rest on a sufficiently solid theoretical foundation, if only because it is difficult to imagine to what extent demineralization and decalcification in tuberculosis, based on a deep disturbance of intermediate metabolism, can be corrected by a simple increase in the amount of calcium received by the child. This favorable influence on mineral metabolism and an increase in calcium retention should rather be expected from the use of ultraviolet rays, preparations of irradiated ergosterol, or parathormone. According to Zimbler's observations, the use of vigantol and parathyreocrin with the simultaneous administration of calcium preparations has a favorable effect in some forms of tuberculosis, especially in bone-articular tuberculosis. For methods of collapse therapy, see Artificial pneumothorax, Phrenicoexeresis, Thoracoplasty. Prevention of tuberculosis in children is expressed: 1) in measures aimed at protecting the child from infection, and 2) in measures aimed at raising the child's resistance in the fight against the infection that has penetrated his organism. The severe course and high mortality among children infected with tuberculosis in the first years of life, especially children in the 1st year of life, bring to the fore the protection of children of this age from infection, which occurs in the overwhelming majority of cases from contact with a sick family member or a sick tenant of the apartment (intrafamilial, intra-apartment contact). This places first and foremost before the consultation for women and the tuberculosis dispensary the task of careful accounting and identifying pregnant women who are sick with tuberculosis and are in contact with bacillary and active tuberculous patients. Newborns from bacillary, severely ill mothers must be separated from the latter immediately after birth and placed in an infant home.
No smaller percentage of infection in nursery-age children occurs not from sick mothers, but from sick fathers and other family members, which compels the anti-tuberculosis organization to raise the issue of widespread hospitalization of tuberculosis patients with severe forms of tuberculosis. Isolating an infant from the source of infection remains the most important link in the prevention of tuberculosis in children of this age. This separation, even if short-term (6 weeks to 2 months), from a bacillary patient is also necessary for newborns vaccinated according to Calmette, because immediately after vaccination, a certain period is required for the development of immunity. The danger of infection not only from family members, but also outside the family, from chance encounters and from unidentified sources of infection, which increases with age, forces us to concentrate attention on the hygienic environment surrounding the child, to sharpen attention during patronage, and to devote attention to this issue in the sanitary-educational work of the consultation center. Another side of preventive work, along with the fight against infection, is the fight for the proper growth and development of the child, ensuring the necessary resistance of the organism to infection. This side of prevention is fundamental and decisive in all periods of childhood. All measures to create an environment, care conditions, and rational nutrition that are as favorable as possible for the child become the most important link in the prevention of tuberculosis in children. The creation of a healthy children's collective, the deployment of a wide and high-quality nursery network, the deployment of differentiated nursery beds, the work of consultation centers, health-improving work in kindergartens and schools, the creation of differentiated groups in the latter, and a network of health-improving schools thus constitute the basis of all anti-tuberculosis work. The presence of a large number of hidden bacillus carriers among young children with various forms of tuberculosis, proven by experiments on guinea pigs and cultures on special media, forces us to separate tuberculous children of young age and those with poorly expressed signs of the disease in the children's collective and in nurseries from the uninfected by organizing separate sanatorium groups for such children. Anti-tuberculosis institutions for children of different age periods, see above - Organization of the fight against tuberculosis. Vaccination according to Calmette (BCG). The high mortality rate among children infected with tuberculosis in the earliest period of childhood has long forced a search for ways of prevention through active immunization using one vaccine or another. Of the attempts available in this regard, the most successful has been vaccination according to Calmette (see above - Causative agent of tuberculosis and Bacteria, Calmette-Guérin bacilli). In our country, vaccination is carried out in accordance with the decree of the Council of People's Commissars in 14 cities of the RSFSR (Moscow, Leningrad, Ivanovo, Saratov, Voronezh, Gorky, Rostov-on-Don, Smolensk, Kuibyshev, Sverdlovsk, Kazan, Ufa, Yalta, Alma-Ata), as well as in some large industrial centers of the Moscow Region (Kalinin, Tula, etc.) and in large cities of the Ukrainian SSR.
Related articles
Mentioned in
- Acid-Fast Bacteria
- Actinomycosis
- Agglomeration
- Bacterial Extracts
- Bacteriolysis
- Braxton Hicks Version and Hermann Brehmer
- Cavities
- Cirrhosis (of the liver are degenerative processes,)
- Cornet's Law
- Culture Media (artificial media of various compositions)
- Erythema Induratum of Bazin
- Gamaleya
- inoscopy
- Iodophilia
- Meningitis
- Metritis
- Microbial Association
- Pfeiffer Phenomenon
- Pirquet Reaction
- Pyosalpinx
Cite this page
“Tuberculosis.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/tuberculosis/