Testis
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia provides a comprehensive overview of the testis, covering its comparative anatomy, embryological development, and human microscopic structure. It details the physiological role of the testis in spermatogenesis and its anatomical relationship with the epididymis and the excretory system.
Encyclopedia article (1928–1936)
TESTIS, the testicle (testis, testiculus), is the male reproductive gland of animals, in which the formation of male germ cells—spermatozoa—occurs. In invertebrates, it sometimes has a tubular or saccular structure and possesses its own excretory ducts. In animals with a secondary body cavity, the testes develop in the wall of the body cavity as dense organs. Mature reproductive products fall into the body cavity and are then excreted to the outside through excretory or separate reproductive tubules (annelid worms). In vertebrates, the testis is a fairly compact paired organ, always showing a close connection with the excretory system. The testis, like the ovary, develops as a paired fold in the wall of the embryo's body cavity, on the sides of the dorsal mesentery, in the region of the primary kidney. Primary germ cells, which form much earlier, migrate toward these primordia and embed themselves in the genital folds. The latter consist of an outer layer of thickened "germinal" epithelium and an inner mass of embryonic connective tissue. From the germinal epithelium, cellular cords containing primary germ cells grow into the connective tissue, subsequently forming the seminiferous tubules and ampullae of the testis. Epithelial cords also grow from the Malpighian corpuscles of the primary kidney into the primordium of the reproductive gland, connecting with the seminiferous tubules and forming the efferent ductules (vasa efferentia). The latter pass directly into the tubules of the primary kidney. Thus, in vertebrates, the characteristic connection of the male reproductive gland with the primary kidney is established, through which mature reproductive products are excreted to the outside via the primary kidney (Wolffian) duct. This connection develops partly at the expense of cords of the germinal epithelium of the gland, and partly at the expense of cords growing from the epithelium of the excretory tubules, and in different vertebrates, the significance of each of these components varies. In lower vertebrates, the testis sometimes has a complex system of internal tubules developing at the expense of cords growing from the primary kidney, while the germinal epithelium forms only ampullae opening into these tubules, in which the formation of spermatozoa takes place. In mammals, all the tubules of the testis itself develop from the germinal epithelium, while the tubules of the epididymis (epididymis) consist of convoluted tubules of the primary kidney and their primary kidney (Wolffian) duct. In lower vertebrates (fish and amphibians), semen is conducted through the indicated connecting tubules (vasa efferentia) into a certain number of tubules of the primary kidney and then into the primary kidney duct, which consequently plays the role of both a urinary duct and a vas deferens (ductus deferens). However, in many fish and some amphibians, a certain differentiation occurs within the primary kidney, and the reproductive function is then carried only by some (usually anterior) tubules, which then usually lose their excretory function. Similarly, a separation of the vas deferens from the urinary duct is sometimes observed. In all higher vertebrates, starting with reptiles, a secondary, pelvic kidney develops as a permanent excretory organ, with its own separate ureter, and only its reproductive section remains from the embryo's primary kidney, consisting of a more or less significant number of tubules, and the primary kidney duct, which now acts exclusively as the vas deferens (ductus deferens). These channels acquire a highly convoluted form and lie as a fairly significant mass near the testis, forming its appendage (epididymis). In mammals, as in lower vertebrates, the testes develop in the abdominal cavity at the level of the primary kidney; however, later in most mammals, they move backward (downward) into protrusions of the abdominal cavity (processus vaginalis) that grow into the scrotum, which is located outside behind the copulatory organ (descensus testiculorum). In insectivores and some rodents, the testes descend into the scrotum only during the mating season, after which they are retracted back into the abdominal cavity.
I. Schmalhausen. The human testis consists of the testis (testis, testiculus, orchis, didymis) and the epididymis (epididymis, paratestis, parastata cirsoides, s. varicosa). The testis is the size of a walnut, somewhat compressed from the sides. It has two surfaces—facies lateralis et medialis (flattened)—two margins (margo anterior et posterior), and two ends, or poles (extremitas superior et inferior). The dimensions and weight of the organ vary: in an adult, the longitudinal dimension is 4–5.5 cm, the sagittal is 2–3.5 cm, and the transverse is 1.8–2.4 cm; the weight is 25–30 g, with the left and right testes usually having unequal weight. When standing, the upper pole is slightly tilted forward and outward, and the lateral surface is turned slightly backward. Usually, the left testis is lower than the right. The lower pole and the anterior margin of the testis are free; in the posterior part of the upper margin, the efferent pathways of the reproductive gland (ductuli efferentes) begin, and the entire posterior margin of the testis is occupied by the epididymis located there. The surface of the testis is smooth and shiny like a mirror, whitish, because it is covered by a serous layer (tunica vaginalis propria) belonging to the protrusion of the abdominal cavity; the tunica albuginea shines through it. Vascularization: A. spermatica int. begins from the abdominal aorta near the site of the reproductive gland's formation; it usually anastomoses with the a. deferentialis. A. spermat. ext. (from the a. epigastrica) and a. pudenda ext. (from the a. femoralis) supply only the membranes of the testis. Veins collect into the plex. pampiniformis, from where the left ones drain through the vv. spermaticae sin. via the v. renalis sin., and the right ones drain directly into the v. cava inf. Lymphatic vessels from the testis, epididymis, and d. deferens head through the inguinal canal to the lgl. lumbales (aorticae). Innervation of the testis is from the Dx; sympathetic and parasympathetic fibers pass through the nn. splanchnici minores, plex. coeliacus, aorticus, and renalis. P. Karuzin.
Microscopic structure. The surface of the testis is covered by the tunica albuginea, with which the visceral layer of the serous membrane of the testis (tunica vaginalis) adheres. Figure 1. Cross-section of the testis and its membranes (after Kölliker).
The cavity of the tunica vaginalis propria, which does not exist in life.
The cavity of the tunica vaginalis propria, which does not exist in life.
The inner layer of the propria, fused with the albuginea.
Fused with the albuginea.
Transition of the propria to the epididymis.
The testis, where the epididymis adheres.
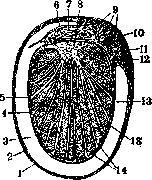
On the posterior margin, the tunica albuginea forms a thickening that protrudes into the testis by 6–9 mm in the form of a vertically standing sheet 2–2.7 cm long, the so-called mediastinum testis or corpus Highmori; from it, septa (septula testis) go into the testis, dividing it into lobules of conical shape (lobuli testis), numbering 100–250. Inside each lobule are convoluted seminiferous tubules (tubuli contorti seminiferi), from 1 to 3, which, repeatedly dividing and twisting, fill its cavity; in the pointed end of the lobule, they pass into straight tubules (tub. seminiferi recti), which, penetrating into the corpus Highmori, form the rete testis, s. Halleri there.
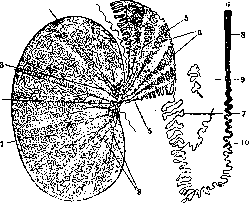
Figure 2. Diagram of the tubules of the testis (after Ebert): 1—lobules of the testis, separated by connective tissue septa extending from the tunica albuginea to the corpus Highmori (2); it contains straight tubules (3) and the rete testis (4); 5—efferent ducts; 6—vascular cones of the epididymis; 7—canal of the epididymis; 8—vas deferens; 9—organ of Giraldes; 10—lower aberrant tubule.
From the upper end of this network, 7–15 efferent ductules (ductuli efferentes, s. Graafiani) emerge, which pierce the tunica albuginea and pass into the epididymis (Fig. 2). The tunica albuginea, 0.4–0.6 mm thick, consists of dense connective tissue.
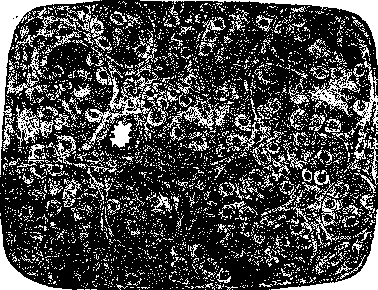
Figure 5. Section of the testis of an 8-month-old fetus (after Prenant): in the convoluted tubules, round, light germ cells and dark follicular cells (Sertoli) are visible; groups of interstitial cells are visible between the tubules.
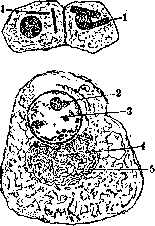
the fibers of which interlace in various directions parallel to the surface; between them are placed networks of elastic fibers; the inner layer of the tunica albuginea, containing a large number of vessels, is distinguished by some authors as a special vascular coat (tunica vasculosa). The tunica vaginalis propria is closely fused with the tunica albuginea and cannot be separated from it; it represents a layer of peritoneum that covers the testis during its development and is covered on the surface by endothelium. The mediastinum testis (corpus Highmori) is formed by a thickening of the tunica albuginea and is also constructed of dense fibrous connective tissue, as are the plates of the septa. Conversely, the connective tissue lying inside the lobules between the convoluted tubules has a loose character, contains many capillaries, lymphatic vessels, and, along with ordinary stable connective tissue cells, special interstitial cells (syn. Leydig cells, Waldeyer's plasma cells) (Fig. 3). These are angular cells, 14-21 µ in size, with a round nucleus, next to which is located a granular sphere with a centrosome; in the protoplasm, inclusions of a lipoid and fatty character are noticeable, larger around the nucleus, as well as pigment; in fixed preparations, it acquires a cellular structure. These cells are located in cords or groups around vessels, under the capsule, and between the tubules. In humans, special protein crystalloids in the form of rods, described by F. Reinke, Lubarsch, and others, are found in the interstitial cells (Fig. 4). These cells were previously considered connective tissue, then a gland with internal secretion (see Interstitial gland); recently, their glandular nature has been disputed (Stieve). In homosexuals, Steinach discovered Leydig cells of particularly large size. The parenchyma of the testis is formed of convoluted seminiferous tubules 0.13-0.28 mm in diameter, which form a large number of bends, sometimes branch and connect with each other; the length of the tubules in the testis on macerated preparations is determined to be 70-80 m (Sappey). The sheath of the tubules (membrana propria) in humans is quite thick (5-11 µ according to Kölliker), has a layered structure, and consists of plates of connective tissue, the bundles of which run predominantly circularly and contain thin elastic fibers; the innermost sheath represents a thin elastic membrane; between the layers of the sheath are located flat cells of an endothelial character. The lumen of the tubule is lined with cells of two kinds: 1) follicular epithelium or Sertoli cells (Sertoli, 1865) and 2) germ or seminal cells. Before the onset of sexual maturity, there are primary seminal cells in the form of rounded, light-colored cells, which are located in small numbers between the follicular epithelium (Fig. 3); with the beginning of spermatogenesis (see), the number of seminal cells increases, and they are arranged in several rows, producing spermatozoa, with the Sertoli cells located
between them in the form of columns. In their protoplasm, fatty inclusions appear
in the form of small droplets, which is especially clearly noticeable when examining a convoluted tubule in a fresh state. In old age, with the cessation of spermatogenesis and the disappearance of seminal cells, the walls of the tubule are lined only with Sertoli cells, which take on the appearance of cylindrical epithelium. The convoluted seminiferous tubules pass into straight ones and through them into the rete testis (rete Halleri) (Kölliker). Figure 4. Interstitial cells of the human testis (after Ebner): 1-Reinke's crystalloids; 2-centrosome; 3-sphere.
0.02-0.09 mm in diameter, are lined with low cylindrical, cuboidal, or flattened epithelium, often with polymorphic nuclei, which differs sharply from the follicular epithelium of the end of the convoluted tubules; the rete testis is lined with the same epithelium. The latter does not have its own sheath but represents tubules and lacunae of various diameters (from 3-4 µ to 0.1-0.3 mm) of irregular shape, excavated in the dense connective tissue of the mediastinum testis (Fig. 5); it contains smooth muscle fibers and dense networks of elastic fibers, which pass into the elastic networks of the septa and the tunica albuginea. The epididymis (Fig. 2), which forms the main mass of the seminal ducts, consists of a head (caput) and a tail (cauda) and lies closely against the mediastinum testis and the posterior edge of the testis. It takes its origin from the efferent ductules (ductuli efferentes), which emerge from the rete testis in its upper part, numbering from 7 to 15; each of them first goes straight, then begins to make bends of greater and greater magnitude, which in their aggregate form a lobule of the epididymis (lobulus epid.) of a conical shape (conus vasculosus Halleri); after this, each efferent ductule empties at a right angle into the duct of the epididymis (ductus epididymis), which curves around the outer edge of the head of the epididymis. This duct, descending downward, itself begins to twist, forming the tail of the epididymis, and passes into the vas deferens. The epididymis is covered by a dense connective tissue capsule, which gives off septa between the conical lobules; inside the lobules, between the tubules, is loose connective tissue. By histological structure, the efferent ductules (tubules of the head) differ sharply from the duct of the epididymis and can be easily distinguished on sections (Fig. 6). The epithelium of the efferent ductules has an uneven contour and is provided with bay-like depressions, with the protruding parts formed by cylindrical cells with a ciliary covering, strongly staining with eosin, and the depressions by lower, cuboidal-shaped cells without cilia and light-colored; both contain lipoid granules and pigment; according to Schaffer, the depressions represent intra-epithelial glands. In contrast to this, the epithelium of the duct of the epididymis is high (45-50 µ), double-layered, with long non-ciliated hairs, which stick together in bundles (stereocilia). Both types of tubules have their own sheath and a circular layer of smooth muscles, which is thicker in the duct of the epididymis. Associated with the epididymis are rudimentary organs, which represent the remains of the tubules of the Wolffian body (see) (Fig. 2). These include: 1) aberrant ducts (ductuli aberrantes
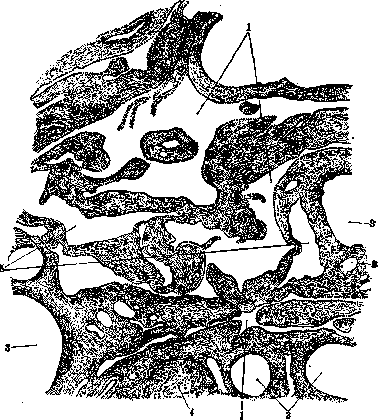
Fig. 5. Tangential section of the mediastinum testis with the rete testis (after Kölliker): 1-tubules of the rete; 2-artery; 3-veins; 4-convoluted tubule; 5-lymphatic vessels.
Halleri), tubules connected to the duct of the epididymis and ending blindly, and 2) the organ of Giraldes (Giraldes, 1857), syn. parepididymis (Henle) or paradidymis (Waldeyer), representing one or several tubules, blind at the ends, which coil into glomeruli located between the head of the epididymis and the vas deferens. The tubules are covered by a connective tissue sheath with smooth muscles and are lined with ciliated epithelium. The third rudimentary organ is the remnant of the Müllerian duct (see Morgagni's hydatids) (appendix testis) ~
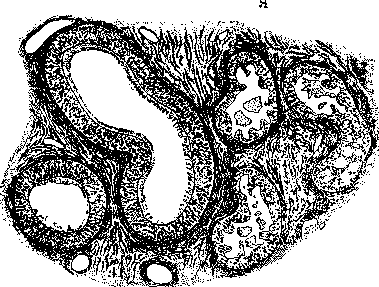
Fig. 6. Section of the epididymis (after Schaffer); on the right, a section of the efferent ductules; on the left, the duct of the epididymis.
is abundantly supplied with vessels, blood and lymphatic, of which the former form capillary networks around the convoluted tubules, and the latter form a plexus under the tunica albuginea.
V. Karpov—Pathological anatomy and clinical presentation. Atrophy of the testis is a frequent phenomenon, usually arising from secondary causes, from debilitating diseases, from disturbances of endocrine correlations, diseases of the thyroid gland (dysthyroidism, cretinism), the pituitary gland (acromegaly, nanosomia), lesions of the base of the diencephalon, as well as the peripheral nervous system (n. spermatici, plexus mesentericus). Histologically, such testes are characterized by a predominance of connective tissue over the tubules. The latter are also narrower. Spermatogenesis in hypoplastic testes occurs later. Bilateral hyperplasia of the testis does not possess characteristic anatomical signs, although clinically such a condition is recognized. Some authors consider premature maturity in disease of the gl. pinealis as a phenomenon of hyperplasia. Unilateral hypertrophy is observed as vicarious in the case of atrophy or removal of one testis at an early age. A hypertrophied testis can reach a volume several times larger than normal. Histologically, such testes are characterized by wide lumens of their tubules (255-270 µ). Abnormal displacement of the testis is called ectopia. Depending on the position, femoral, perineal ectopia, and a very rare form, ectopia testis transversa, are distinguished, when both testes are located on one side of the scrotum with separate epididymides and seminal ducts or a common v. deferens (Merkel). In all cases of ectopia transversa, the testes were located in the scrotum on the right. The most frequent cause of circulatory disturbance in the testis is twisting of the spermatic cord, associated with abnormal structure and position of the testis. Such testes are weakly fixed and can rotate around their horizontal and vertical axis. With vertical rotation by 90-180°, twisting of the spermatic cord occurs, compression of the vessels, and associated hemorrhagic infarction and necrosis of the testis. Torsion occurs more often with the inguinal position of the testis, but it can also occur when it is in the scrotum. Less common is hemorrhagic infarction of the testis from thrombosis of the plexus pampiniformis, after trauma, after a varicocele operation, from incarceration of the testis in the inguinal canal, and from unknown causes. Hemorrhagic infarction should be distinguished from hemorrhages occurring in the testis during scurvy, hemophilia, infectious and septic diseases, as well as during birth trauma in newborns, especially in breech presentation. Metabolic disorders strongly affect the testis. Avitaminosis causes degeneration of the seminal epithelium in rats. Unilateral nutrition leads to the same state. Feeding with cholesterol, extirpation of the adrenal glands, accompanied by a disturbance of fat metabolism, cause strong changes in spermatogenesis, disintegration of seminal filaments, spermatids, and spermatocytes. Disturbance of salt metabolism acts in the same direction. The introduction of iodine in animals causes degenerative changes in the seminiferous tubules. In severe anemias, hemochromatosis, bronze diabetes, iron-containing pigment is deposited in the seminiferous tubules and in the interstitial tissue. Spermiogenesis suffers as a result. Prolonged intoxications with morphine, nicotine, alcohol are accompanied by atrophic processes in the seminiferous tubules. X-rays have a strong effect on the seminal epithelium. In guinea pigs, the seminal epithelium disappears under the influence of X-ray irradiation; only the walls of the tubules with Sertoli cells remain. With the cessation of the action of the rays, the epithelium regenerates quickly. With repeated and prolonged action of X-rays, atrophy of the testis occurs (Kyrle). Psychic factors influence spermatogenesis. Under the influence of strong emotional shocks, the formation of sperm can cease in completely healthy men. Acute infectious diseases—typhus, relapsing fever, typhoid fever, articular rheumatism, etc.—are accompanied by the appearance of irregularly shaped seminal filaments in the tubules, and subsequently by their disappearance. Spermatids, and in more severe cases spermatocytes, disintegrate; only Sertoli cells and spermatogonia remain in the tubules. In the lumen of the tubules, the disintegration of the seminal epithelium is accompanied by the appearance of eosinophilic cells with a pyknotic nucleus and peculiar forms of giant cells. At the height of disintegration, the latter fills the lumens of the tubules of the rete testis and the epididymis. Among the products of disintegration, cells of the macrophage type are found, containing sperm (spermiophagy). Especially devastating are often orchitis in smallpox (necrosis of the parenchyma, infiltrates, etc.)—see also Orchitis. In gonorrhea, thickening of the epididymis is observed. In acute cases, a serous exudate containing leukocytes and cells of desquamated epithelium of the membranes appears between the membranes of the testis. In chronic cases, the layers of the testis can be fused together over a considerable extent. Lime is often deposited in these adhesions. Histologically, in acute cases, the testis may not participate in the gonorrheal process at all or participate very weakly. The process is predominantly localized in the efferent ducts of the testis. If the testis participates in the process, the part adjacent to the rete testis and to the tunica albuginea is usually affected. In these places, there is a proliferation of interstitial tissue and in the tubules—disintegration of the seminal epithelium (see Orchitis). All chronic infectious diseases and intoxications without exception cause changes in the testis in the form of proliferation of connective tissue, death of the seminal epithelium, followed by hyalinosis of the tubules and fibrosis of the interstitial tissue (spermatoangiitis fibrosa obliterans). The starting point can be both inflammatory processes in the interstitial tissue and degenerative changes in the seminal epithelium. Such a morphological state is called fibrosis of the testis, regardless of the cause that caused it. Fibrosis of the testis (fibrosis testis) is often the case with syphilis. Unlike other processes, in syphilis there is a diffuse increase in connective tissue with round-cell infiltrate in the testis in the absence of similar changes in the epididymis. However, for a more accurate diagnosis, it is necessary to detect syphilitic changes in other organs as well. Fibrosis of the testis is characterized by the presence of grayish-whitish cords penetrating the entire organ on cross-section. Scars can occupy the entire organ or only one section of the testis. Upon microscopic examination, the tubules are partly completely obliterated, partly they still retain epithelium from indifferent cells. Near the hyalinized tubules in the interstitial tissue, there are foci of Leydig cells. The interstitial connective tissue is increased in mass, the elastic tissue in the wall of the tubules is preserved for a long time. Among the fibrous tissue, there may be areas with normal spermatogenesis. Tuberculosis of the testis usually originates from a lesion of the epididymis. The latter turns into a sausage-shaped formation, filled with a cheesy mass on cross-section. When the process spreads to the testis, nodules first appear in the mediastinum testis, but can be scattered over the entire surface of the testis. The testis can also be affected primarily by the metastatic route. In the latter case, the miliary form of tuberculosis is more common. Morphologically, intracanalicular and interstitial forms of tuberculosis are distinguished. In the former, the epithelium of the tubules multiplies strongly with the formation of giant cells. The contents of the tubules then undergo necrosis. From one tubule, the process passes to another. The elastic tissue of the tubule walls is preserved for a long time, indicating the boundaries of the former tubules. In metastatic tuberculosis, the process is initially localized in the interstitial tissue, but subsequently passes to the tubules (Baumgarten). Syphilis of the testis rarely spreads to the epididymis. In the testis, syphilis occurs in two forms: in the form of interstitial fibrous and in the form of gummatous orchitis. In the first form, the testes are small, dense. In the interstitial tissue, there is a diffuse inflammatory process in the form of proliferation of connective tissue; the tubules are compressed, and the seminal epithelium undergoes necrobiosis. Subsequently, fibrosis of the testis (fibrosis testis) occurs with thickening and hyalinosis of the walls of the tubules up to their obliteration. In gummatous orchitis, the development of gummata is observed in the form of single or multiple nodules of a yellowish color, with a necrotic center and small-cell infiltrate of lymphocytes, plasma cells, and giant cells along the periphery. In leprosy, leprosy bacilli are excreted from the blood into the seminiferous tubules, produce a destructive effect on the seminal epithelium, therefore, in leprosy, spermatogenesis ceases early. Leprous cells appear in the seminiferous tubules and in the interstitial tissue. In advanced cases, a picture of fibrosis of the testis develops with the deposition of hemosiderin. Along the course of the testis and the spermatic cord, single and multi-chambered cysts are often found, filled with transparent or milky-colored contents, in which sperm are often present. In the latter case, they are called spermatocele (see Spermatocele). Serous cysts are more common in the epididymis than in the testis. They are lined with low epithelium, but in some cases with ciliated or squamous epithelium, which arose on the basis of metaplasia of the cells of the covering epithelium (Mayer). These cysts lie between the serous and tunica albuginea. Their origin is associated with inflammatory processes. Tumors affect the testis rarely, they are also found in childhood.
Fibromas and lipomas are rare. Chondromas of the testis are most often in combination with elements of other tissues. They apparently belong to teratoblastomas. Myomas and rhabdomyomas are encountered rarely, the latter more often as part of mixed tumors. In general, mixed tumors are not uncommon in the testis. They often contain myxomatous tissue. Many mixed tumors are, in essence, teratoblastomas developing unilaterally. Sarcomas of the testis can be round-cell, polymorphic-cell, or spindle-cell, often in the form of a mixed tumor. Carcinomas usually originate from the epithelium of the tubules and the rete testis. Carcinomas consisting of small round cells (so-called seminomas) are frequently encountered, while carcinomas of the adenocarcinoma and scirrhus type are rarer. Dermoid formations in the testis are encountered relatively rarely; one is predominantly dealing with teratoblastomas (malignant teratoma) of the testis. Teratoblastomas of the testis are more often on the right side than on the left and prefer a certain age—from 20 to 40 years. Macroscopically, teratoblastomas in the initial stages appear as a small tumor of dense consistency, containing cysts of various sizes on cross-section. The cavities of the cysts are lined sometimes with cylindrical epithelium, sometimes with cuboidal, and in places, stratified squamous epithelium is also encountered. Around these cavities, smooth muscle fibers, hyaline cartilage, and sometimes nerve bundles and ganglion cells are found. The tumor soon invades the tissue of the testis. Metastases appear very early, first of all in the retroperitoneal glands, then in the lungs, brain, and other organs.
3. Morgenshtern. Congenital abnormalities. Monorchidism (syn. monorchism), unilateral cryptorchidism (see). Anorchism (syn. aplasia), absence of both testes. It is more common for both testes not to have descended into the scrotum and to be located in the abdominal cavity, and they are usually atrophied; in such cases, the external genitalia are often underdeveloped (see Eunuchoidism). Polyorchism (syn. polyorchidism), an excessive number of testes. An extremely rare phenomenon. Usually, what was assumed to be an extra testis turned out to be either an encysted hydrocele, funiculocele, or a cyst, or an omental hernia. Synorchidism (fusion of the testes with each other, usually within the abdominal cavity), an extremely rare anomaly. Inversio testis, abnormal position of the testis: 1) horizontal, in which its upper end is located at the bottom, so that the efferent duct, which is shorter in these cases, departs from the epididymis, the tail of which is located at the top; 2) vertical, in which the testis is rotated around its longitudinal axis. Inversion can be complete or incomplete. The cause is unknown. Retention of the testis (retentio, or ectopia testis) can occur anywhere along the path from the lower pole of the kidney to the scrotum and can be unilateral or bilateral. Up to the age of 10, there are no subjective sensations. Later, painful sensations usually appear, especially during sharp movements, gymnastics, etc. Upon palpation, the patient feels pain at the site of the testis retention, and sometimes an underdeveloped testis that has not descended into the scrotum can be felt, the absence of which in the latter is easily determined. Along with a whole range of methods for bringing down and fixing the testis (see Cryptorchidism), the operations of Nicoladoni and Longard are also recommended. The former, after detaching and bringing down the testis, fixed it by suturing the lower part of the tunics surrounding the testis to the skin of the perineum. Longard uses prolonged traction of the testis for the same purpose, connecting its tunica albuginea with interrupted sutures to the skin of the scrotum. These threads are left long and, for the purpose of traction, are attached with adhesive plaster to the inner surface of the thigh for 8-10 days. Torsion of the testis, rotation around the longitudinal axis, occurs during torsion of the spermatic cord. This rare affliction usually occurs in individuals with a retained testis, more often on the right side. In all cases, the epididymis is more enlarged than the testis, which is sometimes little changed, and sometimes can be dark and gangrenous. With torsion of the testis, pain and swelling in the corresponding groin appear suddenly, often accompanied by vomiting. The diagnosis is based on the swelling of the spermatic cord located between its healthy part and the testis, and on the position of the epididymis in front of the testis. Treatment, if recognized early, consists of untwisting the testis; if late, surgery, usually in the form of removal of the gangrenous mass. Spermatocele, a cystic tumor of the testis filled with semen. A spermatocele arises from the blockage of a seminiferous tubule as a result of one process or another, most often an inflammatory one, leading to narrowing or even complete blockage of it. Continued semen secretion dilates the seminiferous tubules, forming retention cysts of the secretion. The starting point of their formation is predominantly either the place where the tubules of the testis enter the rete testis, or the rete testis itself, or the place where the vasa efferentia enter the canal of the epididymis. Spermatocele is found more often in individuals under 40 years of age. On cadavers, they are found significantly more often than in the living, due to the absence of any clinical phenomena (according to Hochenegg, they are found in 20% of autopsies, more often on the right than on the left). Spermatocele, depending on their location outside or inside the tunica vaginalis of the testis, are divided into extravaginal and intravaginal. The walls of the cyst consist mainly of connective tissue elements covered with flat, and in young people, cylindrical epithelium. The fluid inside the cysts is transparent or cloudy, yellowish-green in color, and often contains spermatozoa. From a clinical point of view, a spermatocele represents a uniform, slowly developing formation, the first symptoms of which in the form of a tumor and unpleasant sensations usually manifest in old age. Their size is usually from a pea to a cherry, rarely up to a small apple. The consistency is soft and elastic. Treatment consists of puncture followed by a pressure bandage. Kocher recommends the injection of tincture of iodine. The most rational treatment consists of radical removal of the spermatocele by operative means. Hydatidocele, cystic enlargement of the accessory formations of the testis, sitting either directly on it or on a stalk. They are usually small in size. Seminoma, a malignant cancerous tumor of the testis, previously mistaken for sarcoma, consists of cells morphologically similar to germ cells. On cross-section, it appears grayish-white with frequently encountered necrotic and softened areas. Seminoma primarily affects the testis, subsequently spreading to the epididymis. As it enlarges, it grows through the tunica albuginea and other tunics of the testis. Subsequently, it perforates the skin or spreads upward along the spermatic cord, metastasizing not only to the glands but also to distant organs (brain, liver, etc.). Seminomas are encountered predominantly at a young age, during the period of sexual maturity. Upon palpation, there is a dense tumor that increases rapidly and after some time replaces the entire parenchyma of the testis. It must be differentiated from a benign tumor, tuberculosis, and syphilis of the testis. The sluggish course of the process and other phenomena of a general nature distinguish these afflictions from seminoma (see below, syphilis of the testis). The prognosis, even with early removal of the testis, is not always favorable. Treatment is operative with subsequent X-ray irradiation of the corresponding lymph glands. Fungus testis benignus is observed after the spontaneous rupture of a testicular abscess to the outside with the formation of a fistula, around which granulation and even fungus-like growths later form (see Orchitis). Stones of the scrotum are formed by the deposition of salts from urine that has penetrated into the scrotum during the rupture of an abscess, or by the deposition of salts along a fistulous tract, or, forming in the urethra, they subsequently penetrate into the scrotum. They consist of uric acid or calcium phosphate. Stones of the scrotum, due to the continued deposition of salts from the urine, increase in size, sometimes reaching large dimensions. Graefe reported a case of a stone weighing 26 ounces, which spontaneously ruptured through the scrotum to the outside. Stones of the scrotum cause pain during urination, upon trauma, and even upon being touched. Treatment is operative, consisting not only of removing the stones but also of eliminating the cause that provoked them. Syphilis of the testis (orchitis luetica) can be of congenital or acquired character. The latter is observed in the secondary and tertiary stages, manifesting predominantly in two main forms: in the form of gummatous nodes (orchitis gummosa) or in the form of interstitial fibrous orchitis (fibrosis testis syphilitica, s. orchitis fibrosa). Congenital syphilis of the testis can be observed already in the first days of a boy's birth or manifests itself up to the age of 2-3 years. The gummatous form is characterized by the appearance of initially small nodes in the parenchyma of the testis, which, partially merging with each other, increase the testis, often to the size of an adult man's fist. Gummata cause a nodular surface of the testis. Upon section, their outer shell is dense, grayish or yellowish in color, and inside there is often caseous degeneration and decay. Interstitial fibrous orchitis is a chronic inflammation of the interstitial connective tissue. It is characterized by the presence of dense callous indurations, especially in the mediastinum testis, from where they diverge in a fan-like manner toward the surface of the tunica albuginea. Often, formations of a similar character take place in the parenchyma of the testis. Progressing, the inflammatory process turns into fibrous tissue, which, contracting, gives rise to cicatricial degeneration, shrinkage, and finally atrophy of the organ. The clinical picture boils down to a slow, gradual enlargement of the testis. It has a rounded or pear-shaped form, sometimes a smooth, more often a nodular surface, is painless upon pressure, and is increased in weight. The scrotum is usually not affected, except in cases where a hernia of the testis is formed. The efferent duct and the epididymis of the testis almost always remain untouched by the process. A slight hydrocele is often observed. Sometimes one, sometimes both testes are affected, either sequentially or, less often, simultaneously. The diagnosis of syphilis of the testis is based on the corresponding anamnesis, general phenomena of syphilis, a positive Wassermann reaction, the presence of specific changes in the cerebrospinal fluid, as well as on local changes in the testis. Differential diagnosis with acute orchitis, hydrocele, hematocele, and even with tuberculous lesions does not present particular difficulties. Differential diagnosis with a malignant neoplasm of the testis is of great importance. If the diagnosis is difficult, it is recommended to conduct specific treatment. Regression of the process speaks in favor of syphilis; in doubtful cases, a biopsy should be performed, and in extreme cases, the affected testis should be removed. Treatment consists of the combined use of mercury iodide and salvarsan; the fistula is treated according to the rules of surgery. Tuberculosis of the testis.
(Tuberculous orchitis) occurs rarely in isolation from the epididymis. Usually, the process spreads from the affected tuberculous epididymis to the testis. For etiology and routes of penetration, see Tuberculous epididymitis. Tuberculous foci in the testis, beginning with the formation of tubercular tissue, later undergo caseous degeneration, first in the center, then at the periphery. With further development of the process, fistulous tracts appear. Tubercular nodules in the form of millet seeds are found on the surface of the testis even in the initial stage of the disease. The course of the disease is usually slow, chronic, without sharp subjective disturbances, and only pain from an accidental injury or pressure may attract the patient's attention and force him to see a doctor. Often, with tuberculous lesions of the testis, there are foci in the efferent duct, seminal vesicles, and prostate. For treatment, see Tuberculous epididymitis. Orchovasoanastomosis, a connection of the vas deferens with the testis or efferent pathways; proposed by Scaduto and Razumovsky. It is used after an operation to remove the epididymis to restore patency for spermatozoa. According to Razumovsky, the healthy vas deferens is split and its flattened wall is sutured with fine catgut in the region of the rete testis. Above this place, the tunica albuginea of the testis is sutured, so that the implanted efferent duct is located as if in a groove. When only the tail of the epididymis is removed, the efferent duct can be sutured into the head of the epididymis. Pascal, in cases of a suspicious tuberculous efferent duct, recommends creating an anastomosis between both testes. For this purpose, he excises the septum of the scrotum, dissects the tunica albuginea of both testes, and sutures the latter together so that the parenchyma of both testes are in contact with each other. Testicular transplantation was first successfully applied by Berthold on roosters. The effect caused by the transplantation does not last equally long. According to Voronoff, the transplant persists for 14 months. He transplants the graft into the scrotum; other authors transplant onto the scarified musculature of the abdominal walls (Haberlandt). The best results are given by pieces of healthy testis 1/2-1 cm in size. In young animals, transplantation is more successful. With human material, the results are much worse. The transplant is resorbed. Histologically, the process proceeds in such a way that initially the germinal epithelium dies, while the Sertoli cells prove to be more resistant. They proliferate with the formation of giant cells. The walls of the tubules subsequently undergo hyalinosis, and the entire transplant turns into a fibrous cord.
M. Zaigraev.
Related articles
Mentioned in
Cite this page
“Testis.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/testicle/