Strongyloidiasis
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article describes strongyloidiasis, a helminthic infection caused by the nematode Strongyloides stercoralis. It details the parasite's life cycle, including both direct and indirect development, clinical symptoms, diagnostic methods like the Baermann technique, and treatment options available in the 1930s.
Encyclopedia article (1928–1936)
STRONGYLOIDIASIS (anguillulosis, angiostomosis), a helminthic disease of humans and certain other mammals, as well as birds, caused by a nematode of the genus Strongyloides Grassi, 1879, belonging to the suborder Rhabdiasata and the family Rhabdiasidae. The genus Strongyloides includes a whole series of species that are parasites of mammals and, more rarely, birds; although many of these species are poorly differentiated from one another morphologically, it is nevertheless considered that they are independent species, more or less stenoadaptive, i.e., specific in relation to their hosts. It is believed that monkeys have their own species (Strongyloides cerjus Darling, 1911; Strongyloides fulleborni Linstow, 1905), as do a whole series of other animal species [in dogs—S. canis Brumpt, 1921; in cattle—S. vituli Brumpt, 1921; in sheep, goats, rabbits, etc.—S. papillosus (Wedl, 1856); in horses—S. westeri Ihle, 1917, and others]. The human form, Strongyloides stercoralis, can infect a dog, cat, or monkey, in which the infestation usually lasts no more than a few months, after which the parasites die out. Other authors deny the possibility of such

Figure 4. Strongyloides stercoralis: 1—sexually mature female of the parasitic stage; 2—male of the free-living stage; 3—female of the free-living stage; 4—spicule and gubernaculum of the male; 5—rhabditiform larva.
infestation.—Strongyloides stercoralis [synonyms: Anguillula stercoralis and Anguillula intestinalis Bavay, 1877; Strongyloides intestinalis (Bavay, 1877); Rhabdonema strongyloides Leuckart, 1883; Rhabdonema intestinale Blanchard, 1886, and others]. It was first discovered by Normand in 1876 in the feces of French soldiers returning from Cochinchina who were suffering from diarrhea. Bavay (1877) described these nematodes under the name Anguillula stercoralis. Some of these soldiers died, and upon autopsy, parasites were discovered that did not resemble those previously found in the feces at all, so they were described as a special form, Ang. intestinalis Bavay, 1877; it was suggested that both species were the culprits of the observed disease, which Bavay called "Cochinchina diarrhea." Later, Leuckart (1882) proved that both forms, described under different names, were merely different stages of development of a single species, the biology of which is characterized by so-called heterogony (see). Thus, it was established that the parasitic stage is represented only by a single hermaphroditic female inhabiting the upper sections of the small intestine (Figs. 1 and 2). This female is 2.2 mm long and 0.030–0.075 mm wide and is characterized by a cylindrical esophagus reaching 1/3 of the body length; the vulva is at the border of the middle and posterior thirds of the body. The females penetrate into the thickness of the mucosa, into the Lieberkühn glands (Fig. 3), where they lay eggs measuring 0.050–0.058 mm in length and 0.030–0.034 mm in width; they usually mature right there, so that the larva hatches while still in the human body (Fig. 4), emerging into the intestinal lumen and then being expelled with the feces; more rarely, the larvae emerge in eggs (Fig. 5) that have not yet hatched. The larvae, reaching 0.200–0.250 mm in length and 0.016 mm in thickness upon hatching and growing rapidly, are characterized

Figure 3. Strongyloides stercoralis in the human small intestine. Adult female in an intestinal gland.
by a so-called "rhabditiform" esophagus, i.e., equipped with an elongated anterior part and a posterior pear-shaped expansion (bulb). Further development can proceed in two ways: with direct development (homogony), the rhabditiform larvae, through further transformation, turn into so-called "filariform" larvae, which are already characterized by a cylindrical esophagus. These larvae, having reached their larval maturity ("infectivity"), can cause a new infection in a human or another animal. With indirect development, the larvae in the external environment turn within 30 hours into a dioecious generation of males and females (heterogony), which differ sharply morphologically from the females of the parasitic stage: both the male and the female have a rhabditiform esophagus; the male has an unpaired spicule and a gubernaculum. The female lays eggs in the external environment, measuring 0.070x0.040 mm. The larvae hatching from these eggs, with a rhabditiform esophagus, molt and in 3–4 days turn into filariform infective larvae. Infective larvae infect humans (and other animals) percutaneously, and upon oral penetration, they perform a migration cycle, penetrate into the mucosa of the upper part of the intestinal tract, enter the venous system, the right heart, and the pulmonary circulation, from where they pass from the pulmonary capillary network, disrupting the integrity of the vessels and alveoli, into the lumen of the lungs; from here, the larvae rise up the respiratory tract, enter the oral cavity, are swallowed, and settle in the small intestine, where, having penetrated into the thickness of the intestinal wall, they grow into sexually mature females. When infective larvae are swallowed, the latter can also enter the small intestine directly, where they reach sexual maturity without migration. From the moment of infection until sexual maturity is reached and rhabditiform larvae appear in the feces, about 17 days pass. Many authors believe that in some cases, rhabditiform larvae, having hatched in the animal's body from eggs, can, without leaving the intestine, turn into infective filariform larvae and in this way give rise to so-called autoinfection (Skryabin and Wagner, Nishigori, and others). This apparently explains the cases of detecting Strongyloides larvae in the blood, urine, and sputum (Fróes, 1931). S. stercoralis, inhabiting the thickness of the intestinal walls, penetrates to the submucosa, invades the chyle vessel, and affects the Lieberkühn glands; in this process, a catarrhal state of the mucosa, swelling of the follicles, and ulceration are observed; apparently, intoxication also takes place. The main complaints in strongyloidiasis consist of painful phenomena from the gastrointestinal tract: abdominal pain, nausea, flatulence, tenesmus; diarrhea is observed most often, frequently with an admixture of blood. Among general phenomena, it is necessary to note headaches, dizziness, fainting spells, anemia, and exhaustion, up to cachectic states. Eosinophilia can be of varying intensity: from 2.5% to 76%. When parasites are introduced from the outside through the skin, they cause various skin symptoms: itching, urticaria, papules, and edema, which can last up to a month.—Diagnosis is based on finding a typical rhabditiform larva or eggs; it is easier to detect these elements after a vigorous laxative. In milder cases of infestation, the so-called Baermann method is used, thanks to which the larvae are concentrated in greater numbers.—Drug therapy is unreliable; it is considered that good results are given by thymol, male fern extract, chenopodium oil, gentian violet, and others.—Prophylactic measures in their main features coincide with those for ancylostomiasis (see Ancylostoma, ancylostomiasis). The geographical distribution to a significant degree coincides with that of ancylostomiasis, since
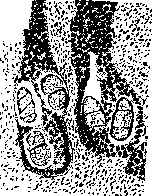
Figure 5. Eggs of Strongyloides stercoralis in the glands of the small intestine.
strongyloidiasis is encountered predominantly in tropical and subtropical countries, where the percentage of infection reaches up to 35. Sporadic cases of strongyloidiasis have been repeatedly detected on the territory of the USSR—in Central Asia, Armenia, Azerbaijan, and Ukraine.
Related articles
Mentioned in
Cite this page
“Strongyloidiasis.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/strongyloidiasis/