Splanchnoptosis
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Splanchnoptosis is a medical condition characterized by the downward displacement of internal organs, historically associated with constitutional asthenia and mechanical factors. This 1930s encyclopedia entry details the development of the concept from Glenard's early theories to later understandings of abdominal mechanics and constitutional types.
Encyclopedia article (1928–1936)
SPLANCHNOPTOSIS, splanchnoptosis [syn. enteroptosis, Glenard's disease] (from Greek splanchnon—viscera and ptosis—falling), a falling of the viscera—a concept under which is understood a whole series of conditions, the common and characterizing sign of which is a lower position of one or many internal organs compared to the norm (partial and general splanchnoptosis). Usually, by splanchnoptosis, one understands the falling of organs only of the abdominal cavity, although it may also concern the lungs, heart, testicles, uterus, and other organs lying outside the abdominal cavity. History. Already in Morgagni, in his work De sedibus et causis morborum, one can find indications of a change in the position of the viscera in humans compared to the norm; Virchow pointed to this as well, noting the close connection of splanchnoptosis with various dyspeptic and nervous phenomena. S. P. Botkin likewise attached very great importance to the falling and excessive mobility of the kidneys in the development of various pain syndromes and all kinds of psychoneurotic states. However, Glenard was the first in the mid-90s of the 19th century (Les ptoses viscerales) to develop a preliminary methodology for systematic palpation of the abdominal cavity, and then the clinical symptomatology of the falling of the viscera, calling this condition enteroptosis, or splanchnoptosis; Glenard described it as a separate, more or less clearly defined disease, to a significant degree explaining nervous dyspepsia. Glenard assumed that depending on the insufficient nourishment of a person, suffered severe diseases, and various congenital anomalies, there occurs, as a result of the relaxation of the apparatus suspending the viscera, a falling of the right flexure of the colon, which also pulls along the right kidney and the duodenum, contributing thus to the formation of kinks in the loops of the intestines and the stasis of their contents, on the basis of which dyspepsia and a neurotic state develop.
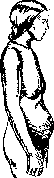
The teaching of Glenard quickly gained fame in the entire medical world and was subjected to comprehensive, thorough criticism (Ewald, Landau, Obraztsov, and others), which forced a serious analysis of those causes and conditions on which the falling of the viscera depends, as well as to clarify the influence of the latter on the development of a whole series of painful phenomena. Landau believed that splanchnoptosis develops secondarily in women who have given birth under the influence of excessive stretching of the abdomen during pregnancy and the separation of the rectus muscles, as a result of which the abdomen becomes pendulous and a falling of the viscera occurs. The significance of the state of the abdominal musculature became the subject of further study, and it was clarified by Curschmann, Lindner, and many others that the falling of the viscera, especially the kidneys, is observed not only in women who have given birth, but also in those who have never been pregnant, as well as in men. This observation required the study of those factors on which the normal position of the human viscera depends. The works of Russian researchers—Lesgaft and especially Volkov and Delitsin—deserve special attention. In their remarkable work dedicated to the question of the floating kidney, Volkov and Delitsin presented the mechanics of the abdominal cavity in the following form: the abdomen represents a closed cavity, limited on all sides by muscular walls—the abdominal wall, the diaphragm, and the musculature of the pelvis, in which is placed a second balloon, consisting of the peritoneum; in the latter, in turn, is enclosed a third balloon, consisting of the muscular hollow organs. The muscular walls of the abdominal cavity and the muscular internal (third) balloon are in changing interaction in relation to each other. If the outer balloon (abdominal press) contracts, then the inner balloon (abdominal cavity organs) is automatically compressed, and, conversely, if the inner balloon is stretched, then the abdominal walls automatically relax and become softer. Intra-abdominal pressure, which has the greatest significance in the statics and position of the organs of the abdominal cavity, depends on the correct function of the muscles in the walls of these balloons. These same authors first clarified the significant dependence of the position of the diaphragm, and consequently of the viscera, on the traction of the lungs. Subsequently, Mathes also began to attach great importance to the elastic traction of the lungs among other causes on which the position of the viscera depends. Parallel to these studies, which investigated mechanical influences on the position of the viscera, another point of view developed, according to which hereditary and constitutional moments were given the greatest importance in the development of splanchnoptosis.

Weakness of tissues, easy extensibility of supporting ligaments, and congenital biological inferiority of the organism began to be considered those factors on the basis of which splanchnoptosis can develop (Glenard, Tuffier, Obraztsov, and others). An extreme view of this order was expressed by Stiller, who believed that the statics of the abdominal cavity in the development of splanchnoptosis have secondary significance, and the main cause of splanchnoptosis is general congenital asthenia, determining both the structure of the body and the position of the viscera, as well as various deviations in the functions of individual organs and entire systems. The teaching of Stiller, having found many adherents and having been subjected at the same time to criticism, undoubtedly contributed to the clarification of some aspects of the pathogenesis of splanchnoptosis, which in modern illumination can be presented in the following way: insufficient strengthening of internal organs, especially the liver, the right kidney, the duodenum, with which a child may be born, gives cause for the falling of the viscera subsequently, when the child begins to walk. The direct cause of such unstable strengthening is in the majority of cases the insufficient fusion of the cecum and ascending colon along their posterior surface with the posterior abdominal wall, in view of which these sections of the colon receive a mesentery, which is a continuation of the mesentery of the small intestines, and become mobile. Subsequently, thanks to the accumulation in them of stagnant fecal masses and gases, as well as the ever-increasing stretching of ligaments during intensified peristalsis of the intestines, parts of the colon under the action of gravity fall downward, pulling along with them the right kidney and liver. A similar anomaly of the attachment of the ascending colon is observed in 20% of people, occurring mainly in individuals of asthenic constitution. The indicated developmental defect contributes to the gradual formation of splanchnoptosis in adulthood.
Two types of splanchnoptosis are distinguished: constitutional and acquired splanchnoptosis. The first form is always connected with a special, abnormal structure of the body, weak development of musculature, with its perverted innervation and tone, and usually insufficient nourishment and inferiority of the elastic elements of the organism, which in general are characteristic features of the asthenic constitution. A narrow, long, often pear-shaped (thorax piriformis) chest with a large inclination of the ribs and wider intercostal spaces, an acute epigastric angle, sometimes with a clearly expressed thoracic kyphosis, developing as a result of the weakness of the musculature and its insufficient innervation, characterize the asthenic constitution. The described body structure is connected with a low standing of the diaphragm, appearing as a result of the insufficiency of the elastic tension of the lungs, excessive mobility of the lower opening of the chest, and flaccidity of the abdominal press, which cannot exert, together with the poorly developed and insufficiently innervated musculature of the pelvis, resistance to the pressure of the abdominal viscera, because of which the latter fall, and the abdomen in profile takes on the characteristic form of the pendulous abdomen of young women (Fig. 1). In this regard, the falling of the small intestines, which in the norm fill the entire abdominal cavity, giving it a normal rounded form, has essential significance. The wearing of an old-fashioned corset or excessively tight lacing, as well as emaciation connected with the disappearance of fat in the abdominal cavity and with the sequential change of intra-abdominal pressure, contributes to the development of splanchnoptosis. The constitutional form of splanchnoptosis is most often observed among women, but sometimes it is also encountered in men of tall stature.
Acquired Splanchnoptosis develops as a result of the relaxation of the abdominal wall; therefore, it is observed primarily among women, in whom, after repeated pregnancies and births, there often remains an enlargement of the abdomen, diastasis of the rectus muscles, and relaxation of the musculature of the abdomen and pelvis. This condition is facilitated by insufficient care for the abdominal wall in the last months of pregnancy and after childbirth, as well as heavy physical labor shortly after delivery, when the stretching of the abdominal muscles has not yet subsided and the normal tone of its musculature has not been restored. In men, due to the absence of the aforementioned factor, acquired splanchnoptosis is encountered significantly less frequently or develops exclusively as a result of sharp emaciation in obese subjects, especially in the presence of pulmonary emphysema, as well as after the drainage of long-standing ascites or after the removal of a very large tumor. Of course, these same factors play a significant role in the development of enteroptosis in women as well, contributing to the formation, due to the prolapse of the viscera with a flaccid abdominal wall, of the characteristic form of an acquired pendulous abdomen (Fig. 2). Symptomatology. Many cases of Splanchnoptosis are completely asymptomatic. This is most often observed in mild degrees of constitutional Splanchnoptosis or in acquired Splanchnoptosis. Often, the only sign of Splanchnoptosis is merely a tendency toward constipation. The constitutional form of Splanchnoptosis often presents a diverse clinical picture, which is explained not so much by the Splanchnoptosis itself as by the dysfunction of a low-value nervous system. Occasionally, pronounced symptoms may also be observed in young, nervous women with acquired splanchnoptosis. The main symptom of splanchnoptosis is a tendency toward constipation, which depends not so much on the prolapse of the large intestines—coloptosis—and the formation of kinks in them, which mechanically hinder the movement of fecal masses, as on the disorder of the innervation of the intestinal musculature, the consequence of which is spasms or atony of the large intestines, and sometimes simultaneously spasms in some areas and atony in others (dyskinesia). Simultaneously with constipation, various dyspeptic disorders often arise. Contributing to constipation are Figure 2. 84v

Figure 3.
and dyspepsia, various anomalies and deviations in the secretion of digestive juices, causing an abnormal course of the processes of digestion and assimilation of food. Prolonged, persistent constipation favors the development of enterocolitis, sometimes membranous colitis, accompanied by sharp pains and contributing to persistent nausea, loss of appetite, and all kinds of painful reflexes, sometimes accompanied by severe painful sensations, such as cardialgia, sometimes palpitations, esophageal spasms, etc. Due to these sensations, patients completely lose their appetite, lose weight, feel tired, exhausted, become hypochondriacs, and begin to suffer from headaches and insomnia—thus, various nervous disorders develop. In individual cases, it reaches a true hysterical state, when patients, especially women, completely refuse to eat, suffering severely from spasmodic pains, nausea, and vomiting after almost every meal. To these general phenomena, symptoms from individual organs are often added, which, by virtue of certain local anomalies in their attachment or after special circumstances, e.g., trauma, have prolapsed more than neighboring organs. In severe gastroptosis, such patients are tormented by a sensation of fullness in the epigastric region, which remains for a very long time after the introduction of food into the stomach, pains in the left hypochondrium, cardialgia, and esophageal spasms, as well as constant eructation (see Stomach, Eructation). A relatively rare prolapse of the cecum is observed with its excessive mobility; according to Wilms, its prolapse depends either on the excessive extensibility of the connective tissue behind the intestine, or on its congenital elongation, or finally on the preservation of the mesentery in the ascending colon; patients suffering from constipation are often troubled by a sensation of bloating and fullness in the right iliac region, dull pains in the same place—from the distension of the cecum and its catarrhal inflammation, which often spreads to the mucous membrane of the vermiform appendix. Through the works of Obraztsov, Hausmann, Wilms, Strazhesko, Klose, and others, special attention was drawn to this condition of the cecum in view of the fact that it often gives rise to the development of the described clinical symptom complex, which often leads to the confusion of a "mobile cecum" (coecum mobile) with appendicitis. Its excessive mobility also predisposes to the stasis of fecal masses and sometimes to specific painful attacks in the right iliac region, resembling attacks of acute appendicitis. Sometimes symptoms of intestinal obstruction are added to them, which de-
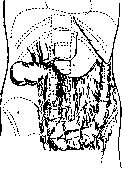
Figure 5. pends on kinks of the long intestine or its partial twisting (Strazhesko) or even its complete volvulus (Zoege von Manteuffel) (Fig. 3). The hepatic flexure of the large intestine (flexura hepatica), thanks to the weak ligaments that strengthen it, and in the presence of such a heavy organ as the liver above it, often lies lower than normal. According to Glenard, every Splanchnoptosis begins with the prolapse of the right flexure of the large intestine; on the contrary, other authors believe that the right kidney prolapses first and it involves the intestine covering the kidney in the process of prolapse, as a result of which a certain difficulty in the passage of intestinal contents through the right flexure may occur, which favors stasis of the ascending colon and, consequently, contributes to the onset of catarrh in it. Much more common is an anomaly in the position of the transverse colon, which, having a congenitally greater length and greater width of the mesentery, easily prolapses and acquires a U-shape, often becoming fixed by adhesions in the pelvic region (Fig. 4), to which Virchow first drew attention (1890) and which was subsequently confirmed by Curschmann and Simmonds. These adhesions are formed as a result of local peritonitis, the cause of which is a past colitis or appendicitis, in women a disease of the appendages, trauma to the abdominal cavity, etc. Such anomalies of the position of the transverse colon, especially when it is excessively long and is arranged in the form of parallel loops, favor the stasis of intestinal contents and often the development of severe suffering in the form of attacks of intestinal colic, sometimes even with symptoms of obstruction, and in rare cases contribute to the volvulus of the transverse colon (Fig. 5). The splenic flexure of the large intestine, being firmly strengthened by ligaments, is rarely displaced, and thanks to this, with a sharp prolapse of the transverse colon, severe disorders easily occur from a kink in this place, the typical clinical symptomatology of which was described by Payr. The stasis of intestinal contents, already physiologically delayed in the region of the splenic flexure, is significantly intensified, and then conditions are created for the development of an inflammatory local process—pericolitis, due to which the prolapsed left knee of the transverse colon and the descending colon, lying side by side, often grow together. As a result of the adhesion, an even greater difficulty occurs in the passage of contents through the flexure; fecal masses accumulate behind the narrowing in the prolapsed transverse colon, weigh it down, and contribute to the intensification of coprostasis, sometimes extending to the Bauhin valve itself. The developing stasis causes not only constipation, periodically alternating with diarrhea due to the accompanying enterocolitis, but also constant pains in the left hypochondrium in the form of stabbing or dull pain, with a sensation of constant heaviness and bloating in the umbilical region, which is sometimes accompanied by reflex angina-like cardiac attacks, headaches, and general lethargy. The condition of patients improves only after the passage of gas and feces. The "transversitis" that easily arises under these conditions makes the existence of such patients burdensome (see Colitis). Sometimes to these symptoms
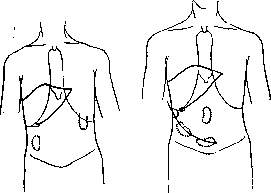
Figure 6. Prolapse of the kidney.
Figure 7. Wandering kidney. True attacks of obstruction-intestinal crises often occur, frequently at night, beginning with painful colic throughout the abdomen, which depends on the intensified peristalsis of the intestines filled with gas and contents, and is sometimes accompanied by nausea, urges to vomit, elevated temperature, and pain in the right iliac region. After several hours of suffering, all these phenomena can quickly disappear if gases pass and there is an abundant stool, then the patient seems to recover, only to repeat the above-described attack after some time.--Op u she niye S-Romani occurs when it is congenitally elongated and provided with a broad mesentery, which easily leads to retention of solid fecal masses in it-constipation develops, which eventually leads to inflammation of the mucous membrane-sigmoiditis (see). In this case, the previously observed feeling of heaviness in the left iliac region is complicated by pains and periodic diarrhea with the excretion of large amounts of mucus, sometimes with an admixture of blood. A long S-Romanum often gives rise to partial twisting of it, accompanied by abdominal bloating, intestinal colic with elevated temperature, and sometimes to complete volvulus and the development of an attack of complete intestinal obstruction, requiring surgical intervention. On the prolapse of the kidney (figs. 6 and 7)-see Kidneys, changes in the position of the kidney. The liver is fixed in its position, on the one hand, by pressure on it from the viscera and fat pads, which in turn are supported by the tonic tension of the abdominal muscles, and on the other hand, by its own ligaments. Depending on the body build, the liver occupies different positions (fig. 8), because the spatial relationships in the right hypochondrium vary with different structures of the chest cavity, which with more or less the same volume of the liver causes different positions of it and variations in the size of the area of the upper anterior surface of the liver not covered by the bony skeleton. Under physiological conditions, the liver descends in the vertical position of the human body and during deep inspiration. In pathological cases, it can change its position secondarily-in various diseases of the thoracic and abdominal organs. An increase in the volume of the right lung in emphysema, accumulation of fluid or gas in the right pleural sac contribute to the descent of the liver, while accumulation of fluid or the presence of a large tumor (pregnant uterus, cyst, etc.) in the abdominal cavity causes it to rise. In other cases, the descent of the liver may be primary. This hepatoptosis can be complete or partial. The descent of the entire liver (hepatoptosis totalis), when it becomes so mobile that it even deserves the name wandering, is relatively rare (fig. 9). Hepatoptosis is most often observed in women with general S. A flabby body build, sedentary lifestyle, lack of physical exercise, repeated pregnancies, wearing unhygienic old-fashioned corsets that constrict the waist, rapid and significant weight loss-are the main factors contributing to the development of total hepatoptosis.
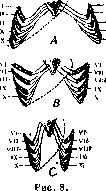
But in practice, partial descent of the liver (hepatoptosis par-tialis) is much more common, being a manifestation of general S, in which either only the lower edge of the liver descends and forward, while its posterior edge is elevated, or the left lobe of the liver descends in isolation, reaching the level of the navel, while the right remains almost in place, or finally the right lobe descends predominantly. In all these cases Figure 9. Descent of the li- simultaneously with the descent of the liver, its deformation and a significant increase in its mobility in the lateral direction, its mobility during inspiration occur, why the liver begins to ballot. A slight hepatoptosis may not give any symptoms and is discovered only upon physical examination of the abdomen. With more significant hepatoptosis, patients often complain either of dull sensations in the form of heaviness or of sharper pains in the area of the liver with their irradiation into the shoulder, under the right scapula or into the spine. These unpleasant sensations usually decrease when the liver is lifted by hand and when wearing appropriate belts.
Significant descent of the liver, causing difficulty in portal circulation and free entry of bile into the intestine, contributes to the development of various dyspeptic conditions, disturbances of intestinal function, and, mainly, the occurrence of various nervous phenomena, such as headaches, dizziness, noise in the ears, and even various mental disorders. Glenar attributed all these symptoms to disturbances of various liver functions and various reflexes coming from the liver, calling this condition hepatism. However, in most cases it is difficult to determine to what extent all these phenomena depend on the descent of the liver and to what extent on general S, accompanying hepatoptosis. Other organs of the abdominal cavity may descend, such as the spleen (see).
liver: 1-right lobe; 2-gall bladder; 3-stomach; 4-cecum; 5-sigmoid colon; 6-transverse colon
its mobility in the lateral direction, its mobility during inspiration occurs, why the liver begins to ballot. A slight hepatoptosis may not give any symptoms and is discovered only upon physical examination of the abdomen. With more significant hepatoptosis, patients often complain either of dull sensations in the form of heaviness or of sharper pains in the area of the liver with their irradiation into the shoulder, under the right scapula or into the spine. These unpleasant sensations usually decrease when the liver is lifted by hand and when wearing appropriate belts. Significant descent of the liver, causing difficulty in portal circulation and free entry of bile into the intestine, contributes to the development of various dyspeptic conditions, disturbances of intestinal function, and, mainly, the occurrence of various nervous phenomena, such as headaches, dizziness, noise in the ears, and even various mental disorders. Glenar attributed all these symptoms to disturbances of various liver functions and various reflexes coming from the liver, calling this condition hepatism. However, in most cases it is difficult to determine to what extent all these phenomena depend on the descent of the liver and to what extent on general S, accompanying hepatoptosis. Other organs of the abdominal cavity may descend, such as the spleen (see).

/-3'
its mobility in the lateral direction, its mobility during inspiration occurs, why the liver begins to ballot. A slight hepatoptosis may not give any symptoms and is discovered only upon physical examination of the abdomen. With more significant hepatoptosis, patients often complain either of dull sensations in the form of heaviness or of sharper pains in the area of the liver with their irradiation into the shoulder, under the right scapula or into the spine. These unpleasant sensations usually decrease when the liver is lifted by hand and when wearing appropriate belts. Significant descent of the liver, causing difficulty in portal circulation and free entry of bile into the intestine, contributes to the development of various dyspeptic conditions, disturbances of intestinal function, and, mainly, the occurrence of various nervous phenomena, such as headaches, dizziness, noise in the ears, and even various mental disorders. Glenar attributed all these symptoms to disturbances of various liver functions and various reflexes coming from the liver, calling this condition hepatism. However, in most cases it is difficult to determine to what extent all these phenomena depend on the descent of the liver and to what extent on general S, accompanying hepatoptosis. Other organs of the abdominal cavity may descend, such as the spleen (see).
Related articles
Mentioned in
Cite this page
“Splanchnoptosis.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/splanchnoptosis/