Eck Fistula
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
The Eck fistula is an experimental surgical procedure, first proposed by Nikolai Eck in 1877, used to create an anastomosis between the portal vein and the inferior vena cava to bypass the liver. This article details the surgical technique, including modifications by Fischler and Schroeder, and discusses its application in physiological research on liver function.
Encyclopedia article (1928–1936)
Eck fistula, an experimental method of partial exclusion of liver function, first proposed by Eck (1877). The method consists of the operative formation of an anastomosis between the inferior vena cava and the portal vein, with simultaneous ligation of the latter above the anastomosis, as a result of which the blood flow, bypassing the liver, is directed directly into the inferior vena cava. In its original form, the application of an Eck fistula was a very difficult operation, as it required specially manufactured instruments (e.g., a special design of miniature scissors) and great technical skill. Subsequently, in view of the special importance of the Eck fistula as a method of studying liver function, attempts were made to improve and simplify the technique of its application, as a result of which Fischler in collaboration with Schroeder in 1909 published a simplified method of the Eck fistula operation, which over time was only slightly improved by him. In the latest modification, the operation of applying an Eck fistula consists of the following. The skin incision is made in a semi-oval line, starting with the upper end in the region of the left hypochondrium 3-4 cm away from the midline. Then the incision crosses the latter and, having described a semi-oval, descends downwards for 6-7 cm, almost in a straight line. If, upon opening the abdominal cavity, access to the inferior vena cava and portal vein is difficult (the abdominal wound cannot be widely spread), the incision is continued further for the necessary distance. When the abdominal cavity is opened, the abdominal organs are pushed to the sides with gauze sponges so that wide access to the above-mentioned veins (v. cava inf. and v. portae) is opened. Then, by blunt dissection, they are carefully separated from the adjacent tissues in a space sufficient for their free approximation close together. When this is achieved, a long ligature is passed under the v. portae, at the place of its entry into the porta hepatis, with a Deschamps needle, the ends of which are grasped with Kocher or Pean forceps and brought out.
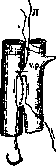
Figure 1. First connecting suture; arrows show the direction of the cutting ligature (c. l.): V. c. inf. - inferior vena cava; V. p. - portal vein.
outside the abdominal cavity, leaving them free (Fig. 1, l). After this, as high as possible (as close as possible to the porta hepatis), the first suture is applied between the veins, tightly fixing their walls to each other (Fig. 1). Usually, 7 such sutures are applied, which occupies a space on average of about 2.5-3 cm. Then, on a round needle, from bottom to top through the entire thickness of the wall of the v. portae between and at the levels of the 2nd upper and 6th lower sutures, a so-called cutting ligature (made of relatively thin but strong silk) is passed, which, upon exiting the lumen of the v. portae at the level of the 2nd upper suture, is thrown to the side of the v. cava inf. and at an equal distance from the sutures connecting both veins, is passed in the same order, but only from top to bottom through the wall of the v. cava inf. and is brought out with its lower end to the outside (Fig. 1). The next stage of the operation is the closure of the cutting ligature in such a way that it ends up between the tightly pushed-together walls of the v. cava inf. and v. portae. The latter is achieved by applying a second row of sutures to the inferior vena cava and portal vein, symmetrical to the first, but located on the other side of the cutting ligature (Fig. 2). The last (7th) suture is not tied with a knot and remains temporarily free. Then, when this is achieved, the ends of the cutting ligature are grasped firmly and, by means of rapid sawing movements, it is pulled out. At this moment, both walls of the sutured veins turn out to be cut through, and a connection (anastomosis) is established between them, as a result of which blood from the portal vein begins to flow into the inferior vena cava. The formation of the anastomosis is indicated by bleeding from the lower corner of the unfastened connecting suture (the 7th), which is immediately tightened, and the bleeding stops. Then the ligature, previously freely applied to the v. portae (Fig. 1, l), is tied tightly, as a result of which the blood now rushes completely from the v. portae into the v. cava inf. On this, the operation of applying an Eck fistula ends. The precautions that must be observed during the Eck fistula operation mainly boil down to avoiding significant bleeding, which is achieved by careful selection of surgical instruments and especially needles. The latter must be of small size, round in cross-section, and steeply curved. The size of the silk is selected according to the available needles with the calculation that it should be slightly thicker than the eye of the needle. Bleeding from the sutures is stopped by tamponade. The Eck fistula operation is usually performed on dogs weighing 15-16 kg. Of particular importance is the choice of the animal, which should have a wide chest, a flat abdominal wall, and, if possible, a wide subcostal angle. All
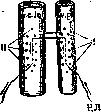
Figure 2. Method of suturing the cutting ligature (c. l.): I - first row of connecting sutures; II - second row of connecting sutures.
these features of body build ensure a low position of the liver, which significantly facilitates access to the inferior vena cava and portal vein. Among suitable breeds, one can point to bulldogs, pugs, and especially a cross between a dachshund and an ordinary mongrel. Females are more suitable for an Eck fistula than males. In the postoperative period, the animal should receive a carbohydrate-milk regimen. Meat and, in general, the abundant introduction of animal protein are excluded in view of the rapid development of symptoms of poisoning. The operation of the so-called "reverse" Eck fistula, proposed by Fischler, is performed similarly to the "direct" Eck fistula, with the only difference that it is not the portal vein that is ligated above the anastomosis, but the inferior vena cava. The reverse Eck fistula serves to obtain pure hepatic blood with the help of deep catheterization (through the v. jugularis) of the inferior vena cava at the level of the entry of the hepatic vein into it (Fischler). The latter operation (reverse Eck fistula) as a preparatory stage was used by Mann and Magath for their famous operation of complete exclusion of the liver. The Eck fistula, despite its shortcomings in a physiological respect (incomplete exclusion of hepatic circulation, since the a. hepatica remains intact), still has great importance in experimental physiology and pathology of the liver.
Physiology of the liver, ibidem, v. LXIX. S. Chechulin.
Related articles
Mentioned in
Cite this page
“Eck Fistula.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/zkovskaya-fistula/