Speech
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet medical encyclopedia discusses the physiological and evolutionary origins of human speech, linking it to the development of the brain, the use of tools, and the evolution of expressive movements. It explores the connection between speech, thinking, and the functional asymmetry of the brain.
Encyclopedia article (1928–1936)
SPEECH. Vocal speech represents the highest form of symbolic-expressive functions; more elementary manifestations of these expressive functions serve as affective exclamations, mimicry, and gesticulation. In contrast to the latter, which have the character of automatic reactions, vocal or verbal speech represents a cortical-associative function acquired during individual life. Like all other manifestations of the activity of the nervous system, the speech act can be identified with a reflex process, in which the receptor (afferent) function is represented by the process of hearing (understanding) words, and the effector (efferent) function by the process of pronouncing words. By its physiological mechanism, the process of perceiving verbal symbols represents one of the forms of gnosia, and the process of pronouncing words—one of the forms of praxia. The close connection of the speech function with the process of thinking, the specificity of this function for man—all this served as a reason for attributing to the speech function an essential role in the process of anthropogenesis. The view has been repeatedly expressed regarding the dependence of thinking on the speech function and even regarding the complete identity of thinking and speech. This idea found its sharpest expression in the teaching of Max Müller: "Reason and language are identical." "Language represents our Rubicon, and no animal dares to cross it." Such assertions led M. Müller and some other thinkers to the erroneous point of view that the presence of speech in man could serve as proof against the origin of man from anthropomorphic primates: "the transition from animal to man is incomprehensible; in man there is something that he could not have inherited from an ape." In contrast to this, the correct view was expressed that verbal speech is a product of the evolution of expressive movements and that its presence in man not only does not contradict the theory of evolution, but is a confirmation of this theory: speech represents not only a product of evolution, but itself is an essential factor of anthropogenetic evolution. Three moments are usually cited as the most essential factors of anthropogenesis: 1) the vertical position of the body with the complete liberation of the anterior (upper) limbs from supporting the body and their adaptation to work; 2) the speech function; and 3) the strong development of the association areas of the cerebral cortex. To each of these factors, various studies have attributed more or less essential significance for the process of anthropogenesis. Attempts to attribute an exclusive role in anthropogenesis to any single one of these factors, and in particular attempts to make the latter dependent exclusively on the speech function, can hardly be recognized as correct. The factors of anthropogenesis are very complex and diverse, but the strong development of the cortex in the anthropomorphic ancestors of man, the liberation of the hands with their adaptation for fine movements, and speech occupy the main place among these factors. The question of the interrelation of these factors and the question of the development of speech in the process of anthropogenesis have very important significance for clarifying the entire mechanism of the speech function. As was already indicated above, speech, by its genesis, can be considered as one of the forms of expressive movements; the most elementary form of the latter are affective exclamations, which are characteristic of very low stages of phylogenetic development. With the development of mobile facial musculature, mimic expressive movements appear. The latter have the character of reflex and concomitant movements and do not bear the traits of conventionality or symbolism. Only secondarily can they take on the character of relative conventionality; thus, the mimic movements of the muscles of the mouth for expressing pleasure and displeasure represent nothing other than an arbitrary reproduction of those movements which arise reflexively during pleasant and unpleasant taste sensations. Although thanks to such a "transfer" of mimic movements the sphere of what is expressed by these movements expands somewhat, it nevertheless remains very limited compared to other expressive movements. The content of mimic expressive movements consists exclusively of the quality and intensity of sensory experiences. Extrasensory manifestations of the psyche, the "expression of thoughts" in the broad sense, are inaccessible to mimic expressions. Everything said about mimicry is also applicable to expressive body movements (threatening postures, etc.). The next degree of evolution of expressive movements is constituted by gesticulations. Although gesticulatory movements, like mimic ones, have a close genetic connection with emotions, the sphere of what is expressed by means of gesticulations is significantly wider: by means of gesticulations, not only emotive experiences can be expressed, but with the perfection of the development of gesticulatory speech, as is observed, for example, in the deaf-mute, gesticulatory movements, "drawing in the air" certain images, can express corresponding concepts. Gesticulatory movements could naturally appear in the human ancestor only after he adopted a vertical position. This period of "gesticulatory speech" is of interest not only as one of the forms of movement specific to man, but also as a factor that determined certain anatomical-physiological features of the vocal speech that developed later. As is known, speech belongs to the number of asymmetric cortical functions: the cortical innervation of speech appears to be unilateral, and specifically in all right-handed people, who constitute 95% of people, the cortical speech centers are localized in the left hemisphere. The origin of the asymmetry of cerebral functions in general and the speech function in particular must be explained in the following way. In the period when man adopted a fully vertical position, and his hands, having been freed from supporting the body, began to be adapted for work, the necessity arose for the preferential use of one hand. During the fine movements that man began to perform with his hands, it was expedient to perfect one hand or the other, and to use the other as a support for the object being worked on. The preferential use of the right hand for fine movements or those requiring great muscular tension is explained by the fact that the left hand, with its somatic nerves, is connected in the spinal cord with the nerves innervating the left heart; muscular tensions of the left hand reflect to a greater degree on the activity of the heart. The preferential use of the right hand served as the beginning of the functional asymmetry of the brain, because it led to a greater development of the left hemisphere of the brain compared to the right. In this same period, parallel to the development of human intellect, the "spirit of sociality" began to develop rapidly. The need for human communication with those around him and the necessity of developing methods for this communication grew more and more. The first of these methods were gesticulatory movements, which, together with affective exclamations, could be the only method of communication for people in this period. Since by this period right-handedness had already been developed, man used his right hand predominantly during gesticulatory movements. Thus, the left hemisphere of the brain became the area regulating expressive movements in the form of gesticulations and the affective exclamations accompanying them. When, as the spiritual world of man expanded and became enriched, exclamations and gestures alone proved insufficient for the expression of his concepts, and when man began to use conventional sound symbols to express his thoughts, the innervations corresponding to the realization of these sounds were localized in the left hemisphere, already prepared for this by the preceding stage of the evolution of expressive movements. The use of the right hand for drawing and writing contributed even more to the connection of the speech function with the left hemisphere of the brain. As for the process of the development of verbal-symbolic speech, both anthropologists and linguists consider onomatopoeia to be its beginning: to express a concept of a known object, a sound characteristic of that object is reproduced. Such onomatopoeic formation of words is undoubtedly a very important source of vocal speech. Due to the transformations to which words were subjected over millennia, and due to the conventional symbolic transfer of them from one object to another, the primary source of the onomatopoeic origin of words can in many cases be discovered only with great difficulty. If it is not difficult to discover the onomatopoeic origin of such words as "noise," "thunder," "whistle," "to groan," etc., then at first glance it may seem strange to assert that such words as "cockade" or "coquetry" have an onomatopoeic origin. Meanwhile, according to the assertion of lexicologists, both these words have a connection with the French word "coq"—rooster; this word is produced onomatopoeically from the cry of a rooster (in French pronunciation "coquerico"). Further, this root "kok" (coq) was transferred to a motley decoration of headwear ("cockade") and to the desire to decorate oneself motley-ly ("coquetry").
However, in modern speech, along with secondary sound symbols that have a more or less distant connection to onomatopoeia, there is undoubtedly a very large number of primary symbols, i.e., such sound signs that are entirely conventional, are artificially connected with known concepts, and have no connection with the images corresponding to these concepts. Thus, the consistent evolution of speech on the path of anthropogenesis can be characterized by the following stages: 1) affective exclamations and gestures, 2) onomatopoeic word formation, and 3) primary symbols. Of especially great importance for the assimilation of the mechanism of speech function is the analysis of the development of speech on the path of ontogenetic development. The human individual comes into the world with elementary affective exclamations in the form of crying. A certain significance is attributed to infant crying for the subsequent development of speech: during crying, the child makes short inhalations and long exhalations, i.e., becomes accustomed to those disturbances of the respiratory rhythm that are necessary for the speech act. In the next period of infancy, the child, while in a good mood, along with other motor acts, attempts from time to time to put his vocal musculature into action. These sounds cannot, of course, be attributed entirely to expressive movements; they belong rather to the category of reflex or concomitant movements. The character of expressive movements can be attributed to them only in the sense that they are an expression of contentment in contrast to crying, which is an expression of a negative sensory tone. By the nature of the sounds produced by the child, this so-called babbling consists of the vowels a and e, and among the consonants, labials (b, p, m), labiodentals (v, f), and anterior linguopalatals (d, l, t) predominate; the sound r in babbling is represented in the form of a guttural (burred) r. The predominance of these sounds is explained by the fact that the vowels a and e are the easiest to pronounce, requiring only the opening of the mouth and the vibration of the vocal cords without special changes and contractions of the musculature. As for the consonants, the consonants pronounced in babbling (labials, linguodentals, and anterior linguopalatals) require for their execution the action of those muscles that appear fully formed in the infant, since it is precisely these muscles that participate in the act of sucking during breastfeeding. Forming syllables from these sounds, the child pronounces these syllables repeatedly during babbling; thus, the most typical sounds of babbling turn out to be: "pa-pa-pa," "ma-ma-ma," "ba-ba-ba," "te-te-te," etc. This repeatability is explained by the fact that it represents the simplest and easiest form of innervation of the vocal musculature and does not require for its execution those coordinative sounds that are necessary for the pronunciation of sounds consisting of different vowels and consonants. The aforementioned predominance of certain sounds in infant babbling is the reason why, among all peoples, the designations for those closest to the infant are denoted by the words mama, papa, baba, deda, tetya, etc. Those around the infant utilize the ability of sounds existing in babbling and artificially make words out of them, connecting with them concepts about those closest to the child. The phenomena observed in infant babbling are not devoid of a certain significance for pathology. Thus, the repetition of syllables during babbling has a relation to the development of stuttering, and the insufficient transformation of the babbling (guttural) r into a linguopalatal r is the basis of a burr. Thus, through the artificial connection by those around the child of certain images with the sounds produced in babbling, the child's first words are formed. Thus, being essentially reflex, automatic phenomena, the sounds of babbling are transformed into the first conventional-symbolic signs. So, hearing the word "mama" constantly upon seeing the mother, the child connects with this auditory impression other impressions emanating from the sight of the mother, her embraces, feeding, etc.; thus, a connection is established between a certain auditory impression and the corresponding image according to the general law of conditioned reflexes or an established associative connection. Upon the establishment of this connection, the child, when an image of the mother arises in his representation under the influence of some external stimulus, according to the same principle of an established associative connection, puts his motor vocal apparatus into action corresponding to the vocal reproduction of the sound corresponding to the given image. Thus, the beginning of the sensory function of speech (the process of understanding sound signs) is laid, and in parallel with this, the rudiments of motor (spontaneous, voluntary) speech arise. Subsequently, the child "learns" speech. In the sensory sphere, this learning is based on the establishment of a connection between audible sound impressions and the images corresponding to them according to the general principle: "the more often a known object is presented together with the sign corresponding to it, the more firmly they are connected" (mechanisms of the formation of conditioned reflexes). In the assimilation of the motor speech function, a very essential role belongs to imitation: the child strives to repeat the words he hears; this striving for imitation, which has at its base a process analogous to a reflex act (motor reaction to an auditory stimulus), has important significance as a factor in exercising the speech musculature and as a factor in strengthening the connection between auditory and motor innervations corresponding to the sound symbols of words. It should be noted that in the process of speech development in children, there is a tendency toward onomatopoeic word formation (cow-"moo-moo," dog-"bow-wow," etc.). At the same time, the invention of primary symbols is also often observed, i.e., the arbitrary designation of various objects by words invented by the child himself. Thus, the ontogenetic development of speech as if repeats the stages of phylogenetic evolution: affective exclamations, onomatopoeic word formation, and the invention of primary verbal symbols. But the main role in the process of learning speech by a child is, of course, played by the assimilation of verbal symbols from those around him. The anatomical-physiological basis of the assimilation and formation of the speech function consists of the following moments. The process of learning speech begins with hearing words as sounds that do not have the meaning of symbols of certain concepts. The cortical area of perception of these sounds is the superior temporal gyri. As this verbal-sound impression is connected with other impressions emanating from the corresponding object, a connection is established between various areas of the cortex and the auditory area. In view of the aforementioned fact of the asymmetry of cortical innervation of speech in the sense of the predominance of the left hemisphere, the connection of the auditory area with other parts of the cortex occurs through the left superior temporal gyrus. The posterior part of the left superior temporal gyrus represents that area through which the connection between the auditory sphere and other parts of the cortex is established: this connection is necessary so that upon hearing a verbal sound, the understanding of the word occurs, i.e., the traces of impressions that acted in the past experience of the given individual simultaneously with the hearing of the given verbal sound are revived. This area—the posterior part of the left temporal gyrus—is designated by the term "auditory center" of speech or "Wernicke's center," also "sensory speech area" (see figure, 4). The integrity of this area is necessary for the process of understanding words. Damage to this area leads to phenomena of so-called sensory aphasia, or Wernicke's aphasia, the essence of which consists in the loss of the ability to understand speech while maintaining the perception of words as sounds. Since the sensory center is formed first in the process of development of the speech function, it forever remains dominant over other speech functions. Therefore, with damage to this center, i.e., with sensory aphasia, there are always more or less sharply expressed disorders on the part of other speech functions (motor function of speech, writing, reading). The important role of the sensory speech area for the entire speech process is manifested, among other things, in the syndrome of so-called "temporal speech akinesia," consisting in the loss of the motor function of speech upon damage to the posterior parts of the superior temporal gyrus at its border with the occipital lobe. Scheme of the speech mechanism. Receptor (sensory) function of speech: auditory stimuli propagate along the cochlear nerve (1) to its nucleus (VIII); from here along the fibers of the lateral lemniscus (2) to the cortex of the superior temporal gyri (3) and further to the sensory speech area (4), which, by means of association connections (a), is connected with various areas of the cerebral cortex. Effector (motor) function of speech: impulses arising in the cortex corresponding to the motor images of words propagate along association fibers (b) to the motor speech center (5); from here to the motor cortical centers (6) in the lower part of the anterior central gyrus and further along the corticobulbar tract (?) to the nuclei of the X and XII nerves and along these nerves (8 and 9) to the muscles of the larynx, tongue, etc.
In parallel with the formation of the auditory speech center, a cortical-associative center of motor speech function is also formed. The cortical region of elementary movements of the speech musculature is the lower section of the anterior central gyrus. The connection of this region with the rest of the cerebral cortex is carried out through the frontal association area, specifically through the posterior section of the third frontal gyrus (see figure, 5). The integrity of this region, designated by the term "motor speech center" or "Broca's area," is necessary for the pronunciation of words as symbols, i.e., for the execution
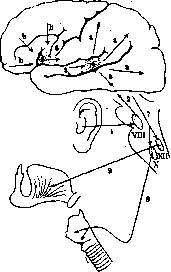
of those vocal movements which, as sound symbols, correspond to a specific image or representation. Upon damage to Broca's area, due to the resulting disconnection of the lower section of the anterior central gyrus from the remaining areas of the cortex, the subject, while retaining the ability to produce elementary vocal sounds, proves unable to pronounce words. Such a disorder of speech—the inability to pronounce words while retaining elementary movements of the speech musculature—bears the name "Broca's aphasia" or "motor aphasia."
The associative apparatus of Speech represents the highest regulatory mechanism of the speech function. The initiative for speech expressive movements arises in various parts of the cerebral cortex under the influence of external irritations. The corresponding impulse through Broca's area spreads to the lower parts of both anterior central gyri. From here begins the second part of the speech 'paths' or conductors of speech motor innervation; this part can be designated as the projection or cortico-bulbar pathway; its initial stage consists of the cells of the cortex of the lower parts of the anterior central gyri and its terminal stage is the nuclei of the medulla oblongata (nuclei of V, VII, X, XI nerves). With lesions of this pathway (tr. cortico-bulbaris), the associative function of Speech is not impaired; the process of evocation of word symbols, i.e., the process of the emergence of word images under the influence of corresponding irritations, remains intact; what is impaired is the innervation of contractions of speech muscles in the form of their central paralysis or paresis (see Pseudobulbar paralysis). Finally, the third, last part of the speech pathways are the peripheral conductors of speech musculature, i.e., the V, VII, X and XII pairs of cranial nerves from their nuclei to their terminations in the corresponding muscles. Lesion of this third part of the speech pathways leads to a flaccid peripheral paralysis of the speech musculature, or so-called bulbar paralysis (see). In contrast to aphasias, which represent non-paralytic associative disorders, disorders of Speech depending on central or peripheral paralysis of speech musculature are designated by the term dysarthrias or -articulatory disorders of Speech. The essence of these disorders consists in the incorrectness or impossibility of the realization of the word sound as a complex of simpler sound elements, consisting of syllables, which in turn are articulated from vowel and consonant elements (letters). The extreme degree of dysarthric disorders is represented by inarticulate Speech, consisting in the complete loss of the ability to realize letter sounds and articulate them into syllables and words. An example of this is anarthria (see), in which patients emit only moaning sounds in which it is impossible to distinguish not only words, but also syllables or letters. The area of dysarthric or articulatory disorders of Speech is extremely extensive and diverse. It includes defects in the pronunciation of individual letter sounds, their combinations in syllables and words. In general, it can be recognized that articulatory disorders more often affect consonants. This fact is explained by the fact that vowels, which are tones produced by vibrations of the vocal cords, require less complex innervation than consonants, for the production of which more complex coordinating innervations, strictly calculated forms of constrictions in various parts of the epiglottic tube are required (consonants are noises produced by friction of air in constricted spaces of the pharyngeal, nasopharyngeal and oral areas - the so-called 'articulatory constrictions'). In their nature, articulatory disorders can be subdivided into organic and functional. It goes without saying that the classification of these disorders into the functional group appears artificial and conditional, since in most cases of this kind, the denial of structural deviations from the norm, i.e., the denial of the presence of organic changes, is conditioned only by the impossibility of detecting them by modern research methods. To the area of organic disorders, in addition to the already mentioned bulbar and pseudobulbar Speech disorders, belong Speech disorders in cerebellar lesions; the ataxia developing in this case also affects speech movements; the 'atactic' Speech in cerebellar diseases is characterized by the following features: slowness, trembling of the voice, scanning, i.e., the distinct articulation of individual syllables, a nasal timbre to the voice due to hypotonia of the soft palate musculature, incorrect modulation of the voice; explosiveness, i.e., periodic sudden intensifications of sound as a result of dysmetria. Especially marked degrees of slowing of Speech - bradylalia or bradyarthria - are observed in states of parkinsonism as a manifestation in the speech musculature of general stiffness and slowness of movements. From other organic diseases, bradylalia is usually observed not in very marked forms in athetosis, chorea, brain tumors, meningitis; in states of general weakness, bradylalia is also often present. The terms bradylalia and bradyarthria are used by some as symptoms of bradylalia and bradyarthria. Others apply the terms bradylalia and bradyarthria to such cases of slowness of Speech, which do not depend on a disorder of innervation of speech musculature, but on the state of the psyche, i.e., to cases where the slowness of Speech depends on a depressed mood or difficulty in thinking processes. - A typical disorder of articulation is observed in paralytic dementia (progressive paralysis); this disorder is designated by the term paralytic Speech and is characterized by a trembling timbre of the voice, omission of letters and syllables, as well as stumbling on syllables, i.e., difficulty in transition from one syllable to another, which is expressed in indistinctness, 'smudging' of a certain sound; earlier and most markedly stumbling is observed in the pronunciation of the sound r. In far-advanced forms of progressive paralysis, a complete loss of Speech develops - the so-called 'alalia', in the development of which both paretic weakness of the articulatory musculature and the absence of speech initiative due to the profound disintegration of intellect play a role. To this can be added disorders of an aphasic character. Sometimes in deep stages of progressive paralysis, the symptom of 'monophasia' is observed - the restriction of Speech to a single word or one phrase. In addition to the organic dysarthrias mentioned above, there exists a whole series of defects of articulation, classified as functional. As already indicated above, most of these disorders are in reality organic and are classified as functional only because the underlying structural changes have not yet been precisely established. For the designation of these forms of articulatory disorders, various terms have been proposed, used as synonyms. The most common general term for various articulatory disorders is the term 'dysarthria'. A large group of functional dysarthrias, characterized by the inability to correctly pronounce certain speech sounds, in the absence of clear signs of organic disease, can be subdivided into two main forms: syllabic dysarthria (dysarthria syllabaris), a typical representative of which is stuttering (see), and letter dysarthria, concerning individual elementary sounds (letters) - so-called letter dysarthria (dysarthria litteralis). As synonyms for the latter term, the following designations are also used: 'dyslalia', 'amelia of letter coordination', or 'amelarthria', 'habitual dysarthrogenesis', 'lallation', 'idiotoglossia'. Regarding the pathogenesis of these disorders, the most significant role is attributed to the underdevelopment of the speech apparatus (speech infantilism); this assumption is all the more probable that certain forms of these disorders are observed as physiological phenomena in childhood; insufficient attention from those around who do not correct these defects, as well as from the patients themselves, can contribute to the fixation of such physiological defects. A certain role must also be attributed to neuropathic organization. Sometimes the speech defects in question are inherited (by imitation). Cases of combination of various forms of idiotoglossia with other functional defects (left-handedness, hidden or obvious) are not uncommon. From the large number of forms of idiotoglossia, we note the main ones. The most marked form of idiotoglossia is Hottentotism (see), in which patients use only one consonant. In contrast to the rarity of this form, dyslalias concerning a single letter are very frequent. For the designation of corresponding disorders of Speech, Greek names are used for those letters whose pronunciation appears incorrect or completely impossible. Such are the terms lambdacism - incorrect pronunciation or complete inability to pronounce the letter l; sigmatism - the same with respect to the letter s; gammacism - of the letter z; mytacism - of the letter m; under the term rotacism is meant lisping, i.e., the inability to pronounce the correct (linguo-palatal) r and its replacement by a guttural r; it should be noted that lisping in some dialects is physiological. By pararthrias or paralogias are meant such articulatory disorders in which patients replace a sound inaccessible to their pronunciation with another, quite definite sound. In the group of paralogias, the following varieties are distinguished: paragammacism (instead of g and k); paralamdacism (instead of l-zh, t, r, e, v); pararotacism (instead of r-l), observed very frequently in children; parapsittacism (instead of s-f).
Under barigl or bariphrazia is meant unclear, 'clumsy' speech, characterized by slowness and insufficient clarity of pronunciation. Treatment of articulation disorders consists of systematic exercises. The area of dislalies also includes nasal speech (rhinolalia). As is known, when pronouncing all vowels and consonants except m, the posterior nasal openings must be closed. Violation of this function of regulating communication between the vocal tube and the nasal cavity leads to disorders of pronunciation of vocal sounds, which manifest in two forms. Open rhinolalia (rhinolalia aperta), caused by the inability to close the nasal openings due to paralysis of the palatal curtain, manifests in that all sounds acquire a nasal tone—'nasalness'. The most severe forms of this disorder are observed in paralysis of the palatal curtain (diphtheritic paralysis; bulbar paralysis); this disorder manifests with particular clarity when attempting to pronounce the labial sounds b and p, which turn out to be completely impossible for patients and are replaced by the sound m: the sounds b, p, m are identical in terms of articulation, and the difference in their pronunciation consists only in the fact that b and p are pronounced with closed choanae, while m with open ones; when it is impossible to close the choanae, an attempt to pronounce the sound b or p leads to the formation of the sound m. Sometimes such patients are able to pronounce b and p while in a horizontal position if they throw their head back, because in this case the choanae are passively closed by the hanging palatal curtain. Under closed rhinolalia (rhinolalia clausa) is meant the state opposite to the one just described: due to the closure of the choanae by inflamed swollen mucous membrane or other processes, the penetration of air from the vocal tube into the nasal cavity becomes impossible, and patients lose the ability to pronounce nasal sounds; when attempting to pronounce m, they get the sound b or p. In the act of word production, an essential role belongs to phonation, i.e., the formation of vocal sounds. Disorders of this function, denoted by the term dysphonia, can be observed independently of the function of articulation. Complete loss of voice, known under the name aphonia, is observed besides paralyses of the recurrent nerve (bulbar paralysis, postdiphtheritic paralysis) as a manifestation of hysteria. Dysphonias, i.e., partial violations of vocal production, can manifest in various forms and have different origins. Here primarily belong the so-called 'mutational' disorders, depending on deficiencies in physiological transformations of the voice; an example of this can be the falsetto voice in men due to delay of the high voice, which is subject to transformation into a low one during the period of sexual maturation. An abnormal timbre of voice for a given sex can also depend on endocrine disorders (high voice in men, low in women with hypogenitalism). Among various causes of loss and difficulties of speech, a certain role belongs to functional weakness of the voice, denoted by the terms mogiphonia or phonasthenia. The essence of the disorder consists in rapid fatigue of the voice, expressed in weakening of its intensity, pains in the area of the speech apparatus, feeling of fear, palpitations. This disorder represents one of the varieties of professional neurosis and is observed in representatives of professions requiring voice strain; accordingly, the following forms of phonasthenia are distinguished: resoastenia of orators, lecturers, klezeastenia—command phonasthenia, and diaodia—singer's phonasthenia. Usually in phonasthenia it is only a matter of weakening of the voice; for extreme degrees of it in the form of complete loss of voice, the term phonocollapse was proposed. Phonatory and articulatory anomalies can also be a manifestation of tic. Speech tic is most often expressed in the pronunciation between words or syllables of any sounds in the form of individual vowels or syllables. A more severe form is represented by the so-called exclamatory tic—an obsessive urge to shout out individual words, entire phrases or sounds that reproduce cries of various animals. To the area of tic can also be angophrazia (see) and embolalia or embolophrazia—the insertion at the end or beginning of phrases of various words or certain sounds. In some people, the habit of excessive use of words 'that is', 'you see', 'so to speak' etc. takes on the character of embolalia. One of the features of normal phrase construction is a certain accentuation of individual words, the so-called intonation, on which depends the expressiveness, and sometimes the meaning of the pronounced phrase. Among disorders of intonation should be mentioned the monotonous speech, observed in parkinsonism, disseminated sclerosis. Besides the above-mentioned disorders of speech in the form of violations of the structure of word sounds, should be mentioned disorders of speech in regard to the content of speech utterances. Quantitative changes of speech in the sense of decrease of speech manifestations can reach various degrees. The phenomenon of monophasia, mentioned above as one of the manifestations of paralytic speech, can also be observed in other diseases; among other things, in motor aphasia patients sometimes retain the ability to pronounce one particular phrase or one word. Monophasia can also be a manifestation of speech stereotypy in schizophrenia. Among the disorders characterized by limitation of speech manifestations belongs also oligophasia—reduction of speech initiative. Oligophasia is observed in some organic diseases of the brain (motor aphasia in the stage of recovery, parkinsonism), as well as as a consequence of psychic anomalies (depressive state, weakening of intellect). Complete cessation of speech of psychogenic origin, mutism (see), is most often a symptom of hysteria; mutism can also be caused by delusional ideas (depressive states, paraphrenia). Increase of speech initiative, speech excitement is observed in manic states; rapid abundant speech of manic patients is denoted by the term logorrhea. Extreme degrees of acceleration and increase of speech manifestations, accompanied by rapid change of the content of speech ('flight of ideas'), are denoted by the term 'confused speech' (tumultus sermonis); a severe degree of speech confusion, taking the form of an incoherent jumble of words, is denoted by the term 'word salad'. Anomalies of speech in regard to its content are denoted by the term dyslogia (incorrect judgment); one of its varieties is paralogia—the appearance in speech of words or phrases that have no relation to the meaning of what is being said; however the terms paralogia and dyslogia are also used as synonyms. The degree of perfection of speech ability is, as is known, subject to significant fluctuations and within physiological limits; speech or linguistic giftedness is determined by the following signs: perfection of phrasing (the process of transforming ideas into word symbols), speed of assimilation of speech symbols, correctness of articulation and phonation, imagery of speech, i.e., perfection of selection and combination of word symbols for expressed thoughts. Development of these features of speech giftedness does not always go in parallel: good phrasing can be combined with defects of articulation and vice versa. To the number of linguistically gifted can be partly included polyglots—subjects possessing a large number of languages; polyglots can be deprived of other features of speech giftedness, for example not possessing highly developed diction or imagery of speech. The anat.-physiol. basis of speech giftedness constitutes the functional plasticity of the cerebral cortex, ease and speed of establishment of associative connections and ease of flow of the associative process, sufficient development of the apparatus of coordination of movements. All these properties can be to a certain extent cultivated by exercise. Culture of speech from the neurological point of view should consist in establishing and spreading data on the ways of occurrence of speech defects and methods of their elimination. In general it should be borne in mind that defects of speech arise in the period of its development, i.e., in childhood; having become fixed, they can later be eliminated only with great difficulty; therefore elimination of speech defects should occur in childhood, before these defects have become fixed. In upbringing of correct speech and elimination of speech defects should be borne in mind not only the elementary mechanisms of speech function but also that role which belongs in the process of speech to psychic moments, especially to the influence on the speech process of emotional factors. As one of the questions of speech culture should be mentioned the development of bilateral cortical speech centers. As was indicated above, the formation of speech centers depends on the function of the hand: normal localization of speech centers in the left hemisphere is connected with right-handedness. Symmetrical departments of the cortex of the right hemisphere appear however also as potentially speech centers; in them speech functions can be developed on condition of functional predominance of the left hand.
In connection with this, the view was expressed that it would be expedient to create speech centers in both hemispheres through the uniform exercise of both hands (so-called ambidexterity, i.e., 'bilateral right-handedness'). The possibility of artificially creating functional symmetry of speech centers cannot be doubted, but as for its expediency, there are certain disagreements in this regard. In general, it should be recognized that the expediency of this proposal has not been proven; there is even a view not without foundation about the harm of developing 'bilateral right-handedness' due to its inconsistency with the innate predisposition of the cerebral cortex to certain functions.
Related articles
Mentioned in
Cite this page
“Speech.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/speech/