Rudolphi, Karl Asmund / Hand
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This entry covers the life and work of Karl Asmund Rudolphi, a founder of helminthology, and provides a detailed anatomical and pathological overview of the human hand, including congenital anomalies, occupational injuries, and clinical deformities.
Encyclopedia article (1928–1936)
RUDOLPHI, Karl (Rudolphi Karl Asmund, 1771–1832), founder of helminthology; graduated from the philosophy and medical faculties in Greifswald, and held the chair of anatomy and physiology in Berlin for 22 years. He became interested in helminthology while still a student; his first two helminthological works were his dissertations for the degrees of Doctor of Philosophy and Doctor of Medicine. In 1808–1810, a two-volume monograph, "Entozoorum, sive vermium intestinalium historia naturalis" (Amstelodami), was published, in which 603 species of helminths were described. This major work of Rudolphi had the same significance for helminthology as Linnaeus's "Systema naturae" once had for zoology. It concentrated all material on helminthology, described a multitude of new forms, and provided a critical analysis of the entire helminthological literature, which consisted of 629 bibliographic titles. Rudolphi divided all helminths into 5 orders: Nematoidea, Acanthocephala, Trematoda, Cestodes, and Cystica. The latter group included bladder worms (echinococcus, cysticercus), the cestode nature of which had not yet been deciphered. In 1819, his second remarkable work, "Entozoorum synopsis" (Berolini), was published, in which data on 981 species of helminths were summarized. As the founder of helminthology, Rudolphi left behind many works in the fields of anatomy, physiology, anthropology, botany, veterinary medicine, and even mineralogy. He was a corresponding member of the Russian Academy of Sciences and was invited to St. Petersburg as an academician.

Figure 1. Left—Aran-Duchenne hand. Right—Preacher's hand.
Correspondingly, anomalies are encountered more frequently in the latter than in the former. According to Starkov, developmental defects can be viewed as phenomena of the loss or duplication of one of the 5 rays of which, according to Gegenbaur, the skeleton of the hand consists. The main ray, according to Gegenbaur, consists of the humerus, radius, part of the triquetrum, the hamate, the 5th metacarpal, and the three phalanges of the little finger; the 1st lateral ray consists of
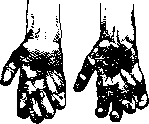

Figure 2. Main simienne avec griffe cubitale (Simian hand with ulnar claw).
Figure 3. Wrist drop in hemiplegia.
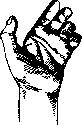
Figure 4. Hand
the radius, scaphoid, trapezium, 1st metacarpal, and two phalanges of the thumb; the 2nd lateral ray—of the lunate, trapezoid, 2nd metacarpal, and three phalanges of the index finger; the 3rd lateral ray—of part of the triquetrum and capitate bones, 3rd metacarpal, and three phalanges of the middle finger; the 4th lateral ray—of part of the hamate bone, 4th metacarpal, and three phalanges of the ring finger. In the 1st lateral ray, complete loss is observed more often, but partial loss also occurs, where the radius is present but the thumb is absent. With the loss of the 2nd, 3rd, or 4th lateral rays, the absence of the index, middle, or ring finger occurs. Underdevelopment of the 3rd lateral ray produces a "split" hand (main fourchue). Loss
of the main ray leads to the complete absence of the hand or hands, which can be combined with the absence of the lower extremities (see Amelia). Opposite developmental defects consist of the duplication of one or several rays, usually expressed only in the distal sections (see Polydactyly). Complete duplication of a ray is described as a rarity. The weakest manifestation of splitting is the duplication of the nail phalanx, most often encountered on the thumb. Partial fusion of two rays with each other results in syndactyly (see). Diseases of the hand. Shoulder, Forearm, Hand, individual joints and nerves of the hand, as well as: Clubhand, Kienböck's disease, Panaritium, Tenovaginitis, Aran-Duchenne hand, Morvan's disease, Dupuytren's contracture, Contractures, Dactylomegaly, Paralysis agitans, Infantile paralysis, Athetosis, Amyotrophic lateral sclerosis, Syringomyelia, Arthritis, Rheumatism. Occupational injuries and diseases of the hand are very numer
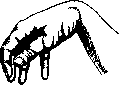
Figure 5. Wrist drop in paralysis of the radial nerve.

Figure 6. Hand clenched into a fist.
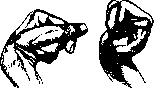
Fig. 7. Hand clenched into a fist (fakir's hand). ous. The distal parts are injured most frequently, the proximal parts less frequently. By severity of injury, traumas are grouped in reverse order, i.e., traumas of the proximal parts are generally more severe. According to statistics from Moscow and the Moscow Governorate in 1925/26, hand injuries accounted for 62% of all occupational traumatism in men and 57.1% in women. According to the same statistics, hand injuries are distributed by severity of disability as follows: Group I—1%, II—12%, III—31%, IV—35%, other groups—15%, not recognized as disabled—5%. It should be noted that the determination of disability often presents very great difficulties due to the fact that one must take into account the possibility of full-value work even in the presence of serious defects in the same profession with different equipment or in other professions. In Germany (Braus), the loss of the right hand (in left-handed people, the left) is estimated as a loss of working capacity of 75% (i.e., more than the loss of one eye—33 1/3%, deafness in both ears—50%, muteness—66 2/3%, and a forced semi-flexed position as a disability of 60%). It is difficult to establish any legislative norms in this very important and very frequent practical question, and it has to be decided individually. Occupational diseases of the hands are expressed in neuroses, e.g., writer's cramp (see), contractures, calluses (see Callosity), and deformities (see below). Deformities. The normal configuration of the hand depends on the harmonious development of its constituent parts—bones, muscles, joints, tendons; the position it assumes both during movement and in a resting state depends on the complex and simultaneous action in various segments of the hand skeleton and in various muscles. Disease of even one of the constituent parts of the hand causes a change in the function of the hand and its configuration, due to which the semiology of hand disease is very complex. Diseases of the muscles causing changes in the hand can be of three kinds—atrophy, paralysis, and contracture of the hand muscles. These changes can exist separately or together, and can arise simultaneously or sequentially one after another. It must be noted that one and the same position of the hand can be caused in some cases by paralysis, in others by atrophy, and in third cases by contracture. Revealing the cause of various changes is of great importance for diagnosis (see table on pp. 411–414).
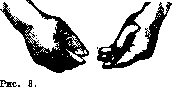
Hand, pill-rolling.
Various deformities of the hand. Various types of hand deformity. Cause of deformity. Clinical manifestation. In which diseases it occurs. Monkey hand (main de singe). Claw hand, synonym: talon hand (main en griffe). Simian hand with claw (main simienne avec griffe). Skeleton hand (main de squelette). Obstetrician's hand (main d'accoucheur). Hammer hand (main en battoir). Hand in flexion (main en flexion). Trident hand (main en trident). Cubital claw hand (main en griffe cubitale). Median claw hand + monkey hand (main en griffe médiane + main de singe). Morvan's hand (rhumatisme analgesique de Morvan). Edematous hand (main succulante). Drooping hand (main tombante). Flat hand. Atrophy of thenar muscles. Atrophy of hypothenar and interosseous muscles. Atrophy of thenar, hypothenar and interosseous muscles. The thumb is in the same plane as the other fingers and cannot oppose them. The fingers are adducted, the first phalanx is extended, II and III are strongly flexed. Combination of changes. In monkey hand and in claw hand (figs. 1 and 2). In far-advanced cases of the previous form. Contracture in the small muscles of the hand. Increase in the bones of the hand and fingers. Paralysis and contracture of the muscles of the hand, forearm and shoulder. Insufficient development. Paralysis of the muscles of the forearm and hand innervated by the ulnar nerve. Paralysis of the muscles of the forearm and hand innervated by the median nerve. Trophic disorders. Vasomotor disorders. Paralysis and atrophy of the muscles innervated by the radial nerve. Paralysis and atrophy of the muscles of the hand, forearm, shoulder. Without contractures. The thumb is in a state of forced adduction, all fingers are tightly pressed against each other in a semi-flexed state, the palm forms a depression due to the approximation of its edges. Increase in the hand without any deformities: the hand is wide and thick, without change in length, the fingers are short, thick, in the form of sausages (doigts en saucisse). The shoulder is adducted, the forearm, hand and fingers are in a state of flexion. Various variations (fig. 3). II, III and IV fingers are little separated from each other, as a result of which the hand resembles a trident. Only IV and V fingers are in a state of flexion (griffe), II and III remain extended, as their lumbrical muscles are innervated by the median nerve. Sensory disturbance on the palmar and dorsal surface of the hand (fig. 4). Changes in monkey hand, flexion of III and II fingers, inability to flex and pronate the hand. Sensory disturbance. Absence of one or two phalanges on one or several fingers, thickening of the skin, disturbance of all types of skin sensitivity. The hand is edematous, cold, bluish in color. Hypertrophy of subcutaneous tissue, often with muscle atrophy. Flexion of the hand and fingers and inability to extend them: sometimes II and V fingers, which have their own extensors, remain extended - the patient seems to make horns (fig. 5). Severe emaciation of the muscles, so that all the elevated places and roundnesses on the hand are smoothed out a) In various diseases of the spinal cord, in lesions of the anterior horns at the level of C8 and D1 (place of departure of fibers for innervation of the corresponding muscles) - poliomyelitis chronic and acute, syringomyelia, hematomyelia, tumors, amyotrophic lateral sclerosis, traumatic diseases of the spinal cord; b) peripheral diseases of the roots, plexus and peripheral nerves - median and ulnar nerves, observed in diseases of the spine, in cervical ribs, diffuse paralyses, in neuritis - traumatic, infectious, intoxication. In tetany. In acromegaly. In central hemiplegias. Achondroplasia. In diseases of the ulnar nerve on the forearm or above - infectious, toxic, professional neuritis (in work requiring support on the inner half of the elbow or on the hypothenar - bakers, shoemakers, printers). Diseases of the median nerve - trauma, nerve transection, toxic and infectious neuritis. Syringomyelia, leprosy (leprosy). Syringomyelia, hemiplegia, myopathy. Diseases of the radial nerve - various neuritis (more often mercury poisoning); disease of the spinal cord (D1), brachial plexus. In central hemiplegias (more often in childhood forms).
Various types of hand deformity. Cause of deformity. Clinical manifestation. In which diseases it occurs. Preacher's hand (main de prédicateur). Hand with large thumbs (chiromegalie, s. macrochirie). Hand with fingers in the form of drumsticks (doigts en baguettes de tambour). Hand with reduced fingers (sclerodactylie). Hand clenched in a fist (main en poing fermé). Fakir's hand (main de fakir). Hand rolling pills. Paralysis and atrophy of the muscles innervated by the median and ulnar nerves. Trophic disorders of the bones of the hand. Trophic disorder of the bones. Trophic disorders of the bones of the hand. Contracture in the flexors of the fingers. Contracture of interosseous and lumbrical muscles. Flexion of the last two phalanges and hyperextension of the first and hand (fig. 1). Increase in the hand, especially the fingers (one or several), which become thick, round. The hand is increased in width, thickness and length, the fingers are elongated, flattened, and expanded at the ends. The fingers are thinned, reduced in volume, change in the bone-articular apparatus of the joints. Resorption of the III phalanx is possible. Hyperflexion of all phalanges of the fingers to such an extent that the nails cut into the skin (figs. 6 and 7). Slight flexion of the I phalanx, extension of II and III; adduction of the fingers, the thumb in a state of extension and hyperadduction - rests on the outer surface of the II finger (fig. 8). The change is characteristic for pachymeningitis cervicalis hypertrophica, but occurs in syringomyelia, poliomyelitis, central hemiplegias and in lesions of nerves at the elbow level. In syringomyelia. In chronic diseases of the lungs. Scleroderma. In paralysis agitans, hysteria, syringomyelia.
In paralysis agitans.
Related articles
Cite this page
“Rudolphi, Karl Asmund / Hand.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/rudolphi/