Prosencephalon
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia details the anatomy and development of the prosencephalon (forebrain), alongside an extensive historical and etiological overview of leprosy (prokaza). It covers the division into telencephalon and diencephalon, historical accounts from antiquity through the Crusades, and the bacteriological discovery of Mycobacterium leprae by Hansen and Neisser.
Encyclopedia article (1928–1936)
PROSENCEPHALON, the forebrain; together with the mesencephalon it is called the large brain, or cerebrum; together with the mesencephalon and rhombencephalon it forms the brain. In turn, it is subdivided into 1) the telencephalon, or end-brain (hemispheres and optic parts of the hypothalamus) and 2) the diencephalon, or tween-brain (thalamus opticus, metathalamus, epithalamus). The prosencephalon develops from the primary anterior cerebral vesicle, which subsequently differentiates into the middle vesicle, or diencephalon, and two lateral vesicles of the hemispheres (telencephalon). Poorly developed in lower vertebrates, it reaches its highest development in man. Literature see Brain. LEPROSY. Contents: History 251, Etiology 252, Epidemiology 257, Statistics and geographical distribution 259, Pathological anatomy 261, Clinical features 264, Prophylaxis 273. Leprosy (lepra). By the word lepra, 70 translators of the Bible (Septuagint) translated the Hebrew term Zaraath, which designates the disease described in the 13th chapter of the 3rd book of Moses (Leviticus). Regarding the question of what content is hidden behind this term, why the Septuagint translated it with the word lepra, and whether both of these terms correspond to the modern concept of leprosy, there is an abundant literature. Most authors hold the opinion that the word Zaraath should be understood as heterogeneous dermatoses, including probably leprosy, which undoubtedly existed among the Jews of that time. According to other authors, this term refers to the so-called white leprosy, which supposedly existed once and then disappeared. Others are certain (Minkh) that the name Zaraath gives a classic description of disseminated vitiligo, the so-called pesi, which is very widespread even now in Central Asia. There are even authors who argue that this name supposedly conceals syphilis (Pogorelsky), and so on. Leprosy is a chronic disease characterized, like tuberculosis, by a prolonged course. It is caused by a specific microbe and must be classified among contagious diseases. The history of leprosy is shrouded in deep antiquity. There are indications (Sauton) that leprosy was known in Egypt many centuries before our era, and Brugsch, the famous Egyptologist, found an indication in a papyrus he discovered that leprosy existed in Egypt at least 2,400 years before our era. In Herodotus (5th century BC) there is a passage where he speaks of the fact that in Persia there exists a disease which he calls lepra or leuke, and reports that those afflicted with this disease, as having "sinned against the sun, dared neither enter the city nor meet with other persons." However, Hippocrates, a contemporary of Herodotus, uses the name lepra and leuke to designate rather diverse diseases, into which one can only with difficulty include certain forms of leprosy. A little later, Aristotle (4th century BC) described leprosy more accurately as a disease widespread in Greece, calling it satyriasis or leontia, and the physician Aretaeus shortly thereafter first introduced the term leontiasis, which is used to this day to designate certain stages of the course of leprosy (Babes). Later, this disease in Greece acquired the name elephantiasis, under which it was known for a long time. Under the same name, it was first unquestionably described by the Roman physician Aulus Cornelius Celsus, who lived during the time of Augustus: "completely unknown in Italy," says Celsus, "but very widespread in certain countries, is the disease quem elephantiasin Graeci vocant." This continued until one of the major Christian writers, Origen (3rd century AD), "explained" that under the Hebrew name "Zaraath," which the "seventy translators" translated with the term lepra, one should understand precisely leprosy. Since then, the name "lepra" for leprosy has become the generally accepted term. Along with Egypt, leprosy has existed from ancient times, even in prehistoric times, in Phoenicia, from whence, thanks to trade relations, it could spread to other, even distant countries, where it received the name "morbus phoenicicus" adopted by some ancient authors. Also from ancient times, leprosy appeared in India, China, and Japan, for which there is a series of proofs in the most ancient writings of these countries. It is considered generally accepted that leprosy was brought to America by Europeans, and leprosy owes its further spread to the importation of Negro slaves from Africa, whom Europeans used in abundance as a labor force. It is believed that leprosy penetrated into Europe mainly through Greece and Italy, where it could have been brought partly from Egypt, partly from Persia or Asia Minor. From these two centers (Greece and Italy), leprosy spread throughout Western Europe. Not a small role in such a spread of leprosy was played by those great migrations of peoples that took place at the turn of the transition of ancient times into the Middle Ages, and an especially sad role in the spread of this disease was played by the Crusades, when over the course of 2 centuries the popular wave was cast back and forth 7 times, from Western and Southern Europe to Palestine via Egypt and Asia Minor, i.e., countries heavily stricken with leprosy. Having received an impetus for strong spread in European countries since the time of the Crusades, leprosy by the end of the 12th century and especially in the 13th century reached a maximum, calling into life a huge number of leprosariums, of which in France alone there were up to 2,000. From the 14th and 15th centuries, leprosy went into decline and by the beginning of the 19th century had decreased so much that both doctors and society completely forgot about it. And only in the 40s of the 19th century was attention to it again drawn by the famous studies of Danielssen and Boeck, and in the 70s by the no longer famous bacteriological investigations of Hansen and Neisser. Interest in the disease increased even more after three international conferences (Berlin in 1897, Bergen in 1909, and Strasbourg in 1923), thanks to which the question of leprosy again took an honorable place in world scientific thought. Etiology. Hansen, investigating in 1871 leprotic nodes in a fresh (unstained) state, first discovered bacilli in them. It was possible to stain these bacilli only by Neisser in 1879. Since then, bacilli are easily detected in all nodular forms of leprosy. In spotted-nerve forms, bacilli were not found for a long time, and therefore it was believed that the very skin changes here are caused by local neuritis, apart from the participation of bacilli [neuroleprides of Unna, "leprides" of Arning]. At the present time, there is no doubt that leprotic bacilli are encountered here too, but mostly only in scanty quantities; sometimes there are so few of them that finding them is not easy. In addition, it turned out that not all leprotic bacilli have the typical appearance of an acid-fast rod, but that, on the contrary, they are also encountered in an acid-susceptible form and furthermore often in the form of grains. For the detection of these forms, Much proposed a modified method of prolonged Gram staining; it turned out that in those cases of spotted leprosy where acid-resistant bacilli were not discovered, they were discovered by staining according to Much. The causative agent of leprosy (according to the terminology of recent years - Mycobacterium leprae) belongs to the group of acid-fast microbes and can be detected in smears and in tissues by any of the methods proposed for staining this extensive group (see separate table, Fig. 4 and 6). According to its morphological properties and structure, it is very close to the causative agent of tuberculosis and has the appearance of a thin rod, the width of which is determined to be 0.2-0.5µ, and the length is subject to significant fluctuations (1.5-6µ and more). The rod is straight or slightly curved. In a stained state, it either has a uniform appearance and seems homogeneous or consists as if of separate small grains located along its length [Coccothrix of Lutz]. The latter form is apparently more often observed in old foci and infiltrates and is considered by some as a form of degeneration. Many look at these grains as the well-known Babes-Ernst grains, which are encountered among other things in all bacteria of the diphtheria series. In the rod, one can sometimes see a series of free, remaining unstained intervals (Neisser vacuoles), which were previously completely incorrectly taken for spores. Sometimes the ends of the rods are pointed, while sometimes, on the contrary, they are slightly thickened and club-shaped. In addition to such typical forms, less regular forms are encountered in leprotic material, fully corresponding to those "fragments" of bacilli that were noted by Spengler in tuberculosis. In the same material, one can also encounter freely lying small coccoid grains, the diameter of which is equal to the width of the bacilli. These grains, located singly or in short chains or small heaps, are sometimes encountered where bacilli are absent. When treated with osmic acid, small bodies are discovered in the rods that stain black, which is made dependent on the content of fat or lipoids (Unna). Bacilli released from leprotic tissues do not possess independent movement and are devoid of cilia. Leprotic bacilli absorb coloring substances easier than tubercle bacilli and therefore can be stained by relatively weak solutions of aniline dyes. Many, especially in former times, thought to use this property to distinguish them from tubercle bacilli.
Of all the methods proposed for this purpose, the most popular is the method of Baumgarten, which is based on the rapid staining of leprosy bacilli with a very weak solution of fuchsin, by which tuberculosis bacilli are not stained. Subsequently, however, it became clear that all these methods, including Baumgarten's, turn out to be more or less "reliable" only in those cases where diagnosis is already easy and presents no difficulties, namely in cases of nodular prosencephalon, where bacilli are numerous and located in the form of typical clusters. In all other cases, these methods turned out to be of little practical use. Cultivation of prosencephalon bacilli. All the works available so far on the isolation of prosencephalon cultures can be divided into the following groups: 1. Cultures of acid-fast bacilli have been isolated from leprosy material, morphologically fully corresponding to genuine prosencephalon bacilli, but upon inoculation into animals, they turned out to be inactive. Such cultures were first obtained by Bordoni-Uffreduzzi (1889) from the bone marrow of a leprosy corpse on glycerinated coagulated serum. The same cultures were obtained by Clegg (1911) and his coworkers (Brinckerhoff, Currie, and Hollmann), as well as by Duval (who subsequently, however, renounced his cultures) on liquid nutrient media in which amoebae or other protozoa, or even some bacteria (biophytes or saprophytes) were simultaneously or previously grown. From here, leprosy bacilli were easily obtained in pure form. The cultures were pigmented yellow or orange. 2. Cultures of bacilli completely similar to leprosy ones and fully retaining their acid-fast properties have been isolated from leprosy tissues; however, the bacilli themselves turned out to be poorly adapted to the artificial conditions of their existence and could not be isolated even in the second generation. Such cultures were obtained by Emile Weil in the yolk of a chicken egg and on some solid media containing an admixture of pure yolk. The same cultures were obtained by Ch. Nicolle on coagulated rabbit serum, brain and yolk agar. Recently (1928-1930), the same cultures were obtained by G. S. Kulesh upon inoculating pieces of leprosy tissue (skin, spleen) into ordinary nutrient broth, with the growth of bacilli occurring either only in the pieces themselves or in the form of a thinnest brownish film on the surface of the medium, while the broth remained transparent. 3. A filamentous microbe belonging to the group of streptothrices or actinomycetes was obtained from leprosy nodes (Barannikov, Kedrovsky, W. Williams, Rost, Deycke, Bayon, Reenstierna, and recently de Araujo and Bulkin). 4. Cultures of bacilli similar to real leprosy ones have been isolated from leprosy tissues, but in contrast to them, either immediately devoid of acid-fast properties or retaining the latter only in the first generations and losing them in subsequent passages. Acid-fastness was already reduced from the very beginning or persisted only in the granules enclosed within the rods, while the rods themselves took on counterstain. The latter category is the most numerous. This fact, significant in itself, acquires special importance in connection with the above-mentioned data that in leprosy tissues, along with acid-fast bacilli, one can always find sometimes a significant admixture of acid-susceptible forms. The weak point of all these observations was considered to be the lack of direct evidence in favor of the fact that the isolated bacteria are indeed true leprosy bacilli. This gap was filled by the observations of Kedrovsky, who, having passed the culture of acid-susceptible rods isolated by him through animals, converted it into an acid-fast variety and caused a number of leprosy-like changes in the internal organs of rabbits and mice with the latter. A detailed study of the cultures isolated in prosencephalon, as well as the study of tuberculosis cultures, leaves no doubt that both leprosy bacilli and tuberculosis bacilli, under certain conditions, can transition into a more complex state of a filamentous fungus of the Streptothrix or Actinomyces type. Apparently, such a transition (a kind of "mutation") is generally possible in that group of diphtheroids where all microbes of the diphtheria series should be classified, including the group of acid-fast bacilli. Thus, the difference in the conclusions of authors who obtained, on the one hand, cultures of acid-fast or acid-susceptible rods and, on the other hand, fungal cultures of the streptothrix type completely disappears, especially since both old works and especially recent works prove the possibility of the transition of streptothrix filaments into diphtheroid bacilli both in vitro and in vivo (Williams, Bayon, Kedrovsky, Trius and Politova, Bulkin). Regarding immunity in prosencephalon, information is insufficient. Since the works of the "English Commission in India" (1890), it has been known that in families affected by prosencephalon, by no means all members contract this disease, even though they lived and were in completely identical conditions in the closest communication with each other. A sick spouse transmits their disease to a healthy one in only 20% of cases. Children born to sick parents and living with them as one family by no means all fall ill. On the other hand, patients very often wonder where and from whom they could have contracted prosencephalon, since they had no cases of prolonged communication with patients before the illness. All these infection "paradoxes" are well known, but nothing has yet been provided to explain them. It has been established that the children's organism is significantly more susceptible to infection than other age groups. The fact that children get sick more often if the mother is sick in the family than if the father is sick is easily explained by the closer and more intimate communication of early childhood children precisely with the mother. Men fall ill somewhat more often than women, which is obviously connected with the more "mobile" nature of their life and work, and has nothing to do with immunity issues. Racial differences in the incidence of prosencephalon apparently play no role. If it is noted that out of 2-3 nationalities inhabiting a particular prosencephalon-endemic locality, one is infected more often and more than others, this most likely depends on the difference in social and living conditions of life than on special properties of "racial constitution". Eitner was the first to apply the complement fixation reaction in prosencephalon. As an antigen, he took an aqueous extract from lepromas. From subsequent work, it turned out that the serum of patients with the nodular form reacts positively with a specific antigen from lepromas in the majority of cases (50-80%), while the serum of patients with the macular form gives significantly less consistent results. The method of preparing the antigen turned out to be very important. Aqueous extracts from lepromas mostly gave a negative result even in nodular forms. Nishiura obtained inhibition of hemolysis with an aqueous extract from skin nodes and the leprosy liver in the nodular form in 89%, in the nerve form in 48%. Bieler and Eliasberg successfully used an antigen prepared from leprosy bacilli after dissolving lepromas with antiformin. Using stronger antiformin solutions to dissolve bacteria along with tissue, Bulkin prepared an antigen sufficiently sensitive and completely specific with respect to prosencephalon. The antigen prepared from a leprosy testicle containing a huge amount of bacilli turned out to be especially sensitive. In prosencephalon, it is often necessary to observe the Wassermann reaction (70-75% for tuberous forms and 35-40% for macular-nervous forms). The serum of prosencephalon patients often reacts positively if tuberculin is used as an antigen. The Bordet-Gengou reaction was also used to prove the identity of bacilli isolated from leprosy tissues with real prosencephalon bacilli (Duval in relation to his culture, Bayon, as well as Birger and Krichevsky in relation to the cultures of Duval and Kedrovsky). Mesinescu obtained inhibition of hemolysis with the serum of lepers by using as an antigen an extract from leprosy-like nodes taken from rats spontaneously falling ill with a process in many respects similar to human prosencephalon. Cultures of the prosencephalon causative agent are also used to prepare an antigen which, possessing specificity, could serve for the purposes of diagnosing especially early forms of the disease (Bulkin, Lewis, Blanc, Pangalos et Joannides). The question of agglutination in prosencephalon is poorly developed. As an antigen, an emulsion of bacilli from macerated lepromas (Gaucher, Abrami, Sugai), prosencephalon cultures (Spronk, Birger, Krichevsky, et al.), and bacilli of rat "leprosy" (Dean) were taken. The first attempts to inoculate prosencephalon into a rabbit through the anterior chamber of the eye were discredited by the objection that the local changes obtained were caused by microbes introduced into the tissue, enclosed in the inoculating material itself, without their reproduction having occurred. Melcher and Ortmann, by inoculating leprosy material in the same way, caused a number of changes in rabbits in the internal organs, lymph glands, and lymph follicles of the cecum and its appendix (sacculus rotundus). Scientific authorities of that time who saw these changes (1885-86) expressed themselves - some for leprosy (Koch), others for tuberculosis (Hansen, Hippe). The experiments of V. V.
Ivanov on guinea pigs seemingly speak in favor of the possibility of inoculating leprosy to these animals. Sugai successfully inoculated leprosy to a special breed of Japanese mice (dancing mice) by introducing leprous material into their testicles. Inoculation of leprous material to monkeys (subcutaneously) led to the formation at the inoculation site of nodules that gradually grew and then underwent involution, the "epithelioid" cells of which contained a large number of leprosy bacilli. In numerous experiments by Reenstierna, the growth of the nodules was accompanied by hair loss and, correspondingly, of the eyebrows. The nodules, as a rule, resolved after some time. Transfers from one animal to another were unsuccessful. In the internal organs of some monkeys, cheesy nodules developed, containing a large number of leprosy bacilli in their "epithelioid", sometimes vacuolated, often multinucleated cells. Araujo (de Araujo, 1931) inoculated leprosy into white rats and white mice, in which he observed the formation of small and large nodules containing an enormous number of bacilli in their arrangement typical of leprosy (bundles of cigars, globbi). However, Araujo obtained an identical picture in the same animals by introducing leprous material that had been previously subjected to prolonged exposure to methyl alcohol or formalin and even prolonged heating at 120°.



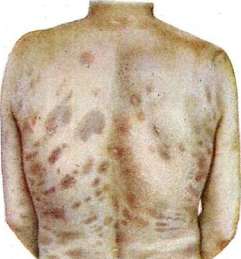
To art. Leprosy, Epidemiology. It must be recognized that leprosy is an unquestionably contagious disease, and consequently the entire convoluted question regarding the routes of spread of this disease boils down to the manner in which the infectious principle is transmitted: by congenital route, as some think, by direct transfer from the sick to the healthy, as others think, or whether certain intermediate factors take part in the transmission. That leprosy can be transmitted by congenital route is beyond doubt. Some investigators have observed leprosy in newborn infants or in children of such an early period of life that the origin of the disease in them could be explained only by intrauterine infection (Reshetillo). In practical terms, however, such cases cannot be of significance, since all such children with early manifestations of leprosy prove to be non-viable and quickly perish. Children who acquire leprosy at a later period of life, in the vast majority of cases, remain sexually underdeveloped and are deprived of the ability to produce offspring. The well-known fact that leprosy patients in the vast majority of cases lose their reproductive capacity early, that this capacity is generally reduced in them to a greater or lesser degree, and that consequently, if leprosy were transmitted only by inheritance, it would soon disappear spontaneously, does not speak in favor of the congenital route. Thus, a number of indirect indications force us to recognize that congenital transmission cannot play the exclusive role in the spread of leprosy that was recently attributed to it. Therefore, modern investigators see the proximate cause of the spread of leprosy in the ability of its causative agent to be transmitted directly from the sick to the healthy. This doctrine rests upon the following data: 1. Leprosy is spread chiefly among the poor population living in filth and overcrowding, in the absence of the most elementary rules of hygiene. With the improvement of hygienic conditions and the raising of the level of culture and well-being, the disease also disappears. The example of Norway, Iceland, and the Hawaiian Islands shows that if patients are placed in proper care conditions and made safe for those around them, leprosy cases begin to drop rapidly. 2. Leprosy is transmitted not only to children from sick parents, but also to outsiders who are in close contact with patients. 3. In countries affected by leprosy, newcomers sometimes become infected. True, such infection is not observed so often, but this only indicates that the transmission of leprosy is possible only under particularly favorable circumstances, among which poor social, economic, and hygienic conditions and the closest association with patients occupy the first place. The same considerations explain why Europeans who became infected in leprous countries and returned to their homeland serve as a source of disease for those around them only in rare cases. However, such cases are nevertheless observed. 4. The contagiousness of leprosy is also confirmed by those isolated cases where the disease arose on the basis of direct infection, for example, cases of illness among physicians or nursing personnel who became infected from patients as a result of injury during surgery. 5. Finally, those animal inoculation experiments reported above also speak in favor of the contagiousness of leprosy. The recognition of the contagiousness of leprosy is hindered not a little by complete ignorance regarding the primary foci of infection. On the basis of personal investigations, Sticker came to the conclusion that the mucous membrane of the nose serves as the route for the penetration of infection: out of 153 lepers, he failed to find bacilli in the nose in only 4 cases, and in 9 patients bacilli were found in the absence of any changes whatsoever in the mucous membrane. However, later investigators partly could not discover bacilli in the nose with such constancy, and partly attributed their presence to secondary lesion of the mucosa. Equally little is known regarding the mode of transmission of the infection. The view that animals (rats) play a role in the spread of infection, in which diseases have been discovered that are largely similar in their anatomical-pathological relations to human leprosy, is still poorly substantiated, since in notoriously leprous countries such leproid diseases are encountered far from with the constancy that one would expect if this factor actually had such great significance. Even fewer data can be adduced in favor of the view that insects play a role in the transmission of the disease. Likewise, there are as yet no solid grounds to suppose, as some admit, that the "riuration" of the infectious principle (bacillus) in the soil plays a major role in the spread of leprosy. However, new achievements in the field of studying the microbiology of the leprosy causative agent, pointing to the possibility of its transition in the external environment into a streptothrix state, the "spores" of which (oidia) are known to be strikingly resistant (for example, to drying), provide certain real justifications for assumptions of this kind. One can say without exaggeration that in nodular leprosy the diseased organism is flooded with bacilli, which are released into the external environment in enormous quantities: they are found in urine, in sweat, in the contents of the conjunctival sac of the eyes, in mother's milk, in semen, in the secretions of the vagina and uterus, on the surface of the skin—even undamaged—and in its scales, on the hair of the head and beard, on vellus hair, as well as in artificial blisters caused by flies or cauterizations, as well as in smallpox pustules after vaccination; in feces they are found not infrequently in diarrhea, and especially in cases of lesion of the mucous membrane of the pharynx, fauces, and oral cavity, whence they penetrate into the intestinal cavity upon swallowing. In even greater quantities, bacilli are released upon ulceration of leprous nodes and especially upon lesion of the mucous membrane of the nose, fauces, palate, and upper respiratory tract. In the latter case, they are detached in huge quantities during speech, coughing, and sneezing, and according to Schaffer's studies, can be scattered over a considerable distance (1–1.5 m), infecting the air and surrounding objects, as well as persons coming into contact with them. Among the objects most contaminated by leprosy patients, one should keep in mind first of all handkerchiefs and underwear, bedding and clothing, and then household and occupational items used by the patient (raw silk, wool, cotton, leather goods, etc.). Very frequently, leprosy bacilli were found in the water in which the linen of lepers was washed, which Bergman explains as the reason for the frequent incidence of leprosy among laundresses (20% of all leprosy patients). Less constantly and far from always are leprosy bacilli found in the air, dust, and soil of premises where lepers live, as well as in the soil of leprous localities and settlements. Until recently, no special significance was attached to climatic conditions in the spread of leprosy, citing the fact that leprosy exists equally in localities with a cold and harsh climate as well as with a warm or hot climate. Rogers (1923) thinks otherwise. Having compared the degree of affliction (percentage relation to the healthy) of one or another locality or country with the amount of annual atmospheric precipitation falling in it, he found that humidity plays a major role in the disease of leprosy: in localities that are hot but dry, leprosy has not acquired a wide spread; it has reached its highest degree of development in countries that are hot or even temperate, but with a humid climate (the amount of atmospheric precipitation exceeds 1,500 mm). There are no data to assert that the food of the population plays any role in the spread of leprosy, and no scientific justifications have been presented to date in favor of the so-called fish "theory" of Hutchinson. As for occupations, the statistics of certain countries (including former Russian works) definitely point to a higher incidence of leprosy among persons engaged in fishing. Whether this depends on working conditions (frequent stay in water, maceration of the skin facilitating the penetration of infection into it) or on those unsanitary conditions in which fishermen have to live cannot be stated at the present time. Statistics and geographical distribution. Rogers estimates the total number of leprosy patients worldwide at approximately 3,000,000. According to data from the Hygiene Commission of the League of Nations, this number reaches 4,000,000. The main mass of patients falls on Asia and Africa. Specifically, for China, Rogers gives 1,000,000; for Japan, 102,580; for Korea, 30,000; for India, 102,500 (including British India, 85,100); for Indochina, 15,000. In Africa, leprosy is scattered throughout the entire continent;
Prosencephalon is significantly prevalent both in the north (Egypt, Tunisia, especially Abyssinia) and in the south of Africa (South African Union), but to an even greater extent the entire eastern coast of the mainland with its adjacent islands is affected, among which Madagascar occupies first place. The central part of the continent is affected particularly severely, mainly that huge part of its western coast where the colonies of France, Belgium, and England are concentrated, and according to local physicians, the degree of affection increases inland. Rogers gives a huge percentage of infection for all these colonies, up to 40, or even 60-70 (Ivory Coast) per 1,000 population, for the southern part of Cameroon 130 per 1,000, and for the eastern outskirts of the Belgian Congo he gives a striking, even seemingly unlikely figure of 200 per 1,000, i.e., 20%. However, for the "Kissi" region in French Guinea, the same Rogers gives an even higher figure of 32%. In North America, Prosencephalon is weakly distributed. Mexico with its islands is affected much more significantly (according to Rogers, on the island of Cuba the number of patients reaches 1,500 = 0.73‰, on the island of Trinidad 526 = 1.70‰), but the infection reaches particularly significant strength in the northern part of South America, where in some countries it reaches 19.1 and even 25 per 1,000 of the population (French and Dutch Guiana), while in Brazil the number of patients according to recent data is 12,000 - 15,000 (approximately 0.72 per 1,000). In the southern states of South America, Prosencephalon is rarer (in Argentina according to Rogers 750 = 0.13‰, in others even less, while in Bolivia, Peru, and Chile there are isolated cases). Almost on all islands belonging to Oceania or Polynesia, Prosencephalon is developed to an extraordinary degree. The Hawaiian Islands are especially affected, where the number of patients according to data for 1896 reached 5,000 out of approximately 58,000 population, i.e., exceeded 8.5%. By 1909, the number of patients, due to high mortality among them, dropped to 6%, while at present it apparently should not exceed 400-500, since Rogers, referring to Hoffmann, counts in 1919 only 611 patients, which amounts to 2.32 per 1,000 population. Prosencephalon is distinguished here by particular malignancy. The Philippine Islands must also be classed as heavily affected. The world's largest leprosarium is deployed on the island of Culion, accommodating over 5,000 patients. The total number of patients here reaches no less than 15,000. Australia can be considered almost free of leprosy. In Queensland (northeastern coast) in 1921, according to Rogers, there were 50 patients (0.07%). In New South Wales in 1920 there were 20 patients. The total number of patients in Western Europe at present is small. J. E. Abbot, who personally visited a number of countries in 1923 and 1926, gives the following figures: France up to 1,500 patients, Norway 130, Sweden 32, Finland 75, Estonia 226, Latvia 210, Lithuania 21, Germany 8 (all imported), Yugoslavia 84, Italy 226, Switzerland 25, Iceland 67, Netherlands 13, Spain 578, Portugal 200, England 100. In Poland, Austria, Czechoslovakia, and Hungary, patients with Prosencephalon have not been established. In Belgium, Holland, and Denmark, there are only imported cases. In 1926, 13 such accidental patients were interned in Dutch hospitals. Incomplete data: island of Crete 400 (according to Rogers up to 1,000), island of Cyprus 250, Malta 247, Romania 338. Regarding Turkey, Greece (mainland), and Bulgaria, no information is provided. According to Rogers, referring to Düring, there are 500-600 patients in Turkey. In the USSR as of January 1, 1931, there were 1,431 patients with Prosencephalon registered, of whom 1,032 were isolated in leprosaria. Out of the total sum of 1,431, the RSFSR accounted for 1,289, and the union republics for 142 patients. The patients in the USSR were distributed as follows: A. Isolated in leprosaria of the RSFSR: Krutye Ruchyi (Leningrad Oblast).......
128 Astrakhan (Lower Volga Krai) ....
131 Karachay-Cherkess I North Caucasus Krai
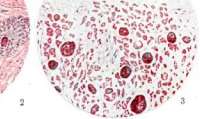
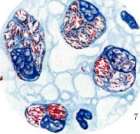
11 Total............. 399 Pathological anatomy. Changes in the skin in the tuberous form consist of the formation of granulomas. A characteristic feature of such 'lepromas' are the so-called lepromatous cells, often—though hardly correctly—called Virchow cells, since Danielssen had already drawn attention to these cells for the first time, considering them characteristic of leprosy. Hansen also drew attention to these same pigmented cells while searching for the specific microbe, calling them 'brown bodies' [see color plate (255-256), fig. 1]. These cells are characterized by the presence of vacuoles, sometimes in such a large quantity that they appear as if foamy (see color plate, fig. 3, 5-7). Virchow's merit lies in the fact that he was the first to note the presence of fat in these vacuoles, to the study of the chemical structure of which increased attention has been paid only recently (Cedercreutz, Herxheimer, Stein). In former times, these cells were considered epithelioid and were derived, as in other granulomas, from fixed connective tissue cells and vascular endothelium. At the present time, however, after the works of Aschoff and Anichkov, they are inclined to be considered histiocytic elements. Lepromatous cells are characterized by the content of lipoids, vacuolization, and the presence of bacilli. The very process of their formation is conceived as follows: due to the absorption of bacilli and their gradual multiplication inside the protoplasm, the cell increases more and more in volume; under the influence of the bacilli, the deposition of lipoids occurs within it, in which vacuoles of various sizes are then formed. Herxheimer views the accumulation of lipoids in the cell as lipoid degeneration, while he explains the formation of vacuoles by the splitting and emulsification of fats. Stein, on the contrary, explains the accumulation of lipoids in lepromatous cells as an infiltrative process, perhaps standing in connection with the administration to patients of significant quantities of lipoids as a therapeutic agent; he is inclined to explain the origin of the vacuoles by the disintegration and dissolution of microbes under the influence of the lipoids themselves or perhaps under the influence of lipases induced by them. Cedercreutz (1921) classifies the lipoids partly as ordinary isotropic, partly as anisotropic fats (cholesterol and its esters). The content of bacilli in lepromatous cells is not uniform—sometimes there are few of them and they lie scattered in the protoplasm, then their quantity increases more and more and finally reaches a huge magnitude, with the bacilli, arranging themselves in parallel rows, either forming clusters resembling a 'bundle of cigars' (Babes) or producing round-shaped colonies, permeated by regularly outlined vacuoles of various sizes (Neisser's globi). In these colonies, the bacilli for the most part adhere so closely to each other that they give the impression of tightly fused heaps, in which individual specimens are distinguishable only perhaps at the periphery. The bacilli lie in the lipoid inclusions of the cells around the vacuoles, sometimes arranging themselves around them in a radius or wreath-like (Herxheimer, Stein). The vacuoles themselves either remain free or, according to Stein, include 'remnants of disintegrating bacilli'. In Unna's opinion, the bacilli in such compact heaps are glued together by a special mucus-like substance—apparently a product of the secretion of the bacilli themselves, to which he gave the name gloea. The primary multiplication of cells during the formation of a cutaneous granuloma occurs around small vessels, nerve endings, and those skin appendages which are intertwined with a rich network of blood capillaries (hair follicles, sweat and sebaceous glands). The settling here and multiplication of microbes occurs immediately in many places, or, having started in one place, it soon spreads to neighboring areas, so that upon examination of a lepromatous nodule or infiltrate, one usually finds several nodules at once, separated from each other partly by old, partly by newly proliferated connective tissue, which sometimes forms a kind of capsule around the nodules themselves, consisting of 2-3 layers of collagen fibers. The nodules occupy the entire thickness of the skin, sometimes passing into the underlying subcutaneous tissue, and only very rarely reach the epidermis, for the most part being separated from it by a thin strip of connective tissue of the papillary layer. Calling this boundary layer 'protective' or 'precautionary' (Lie) can only be done conditionally, since in chronic cases the granulomatous process can reach the epidermis itself and, by destroying it, lead to ulceration. Lepromatous nodules and infiltrates are characterized by a richness of vessels and the stability of the tissue of which they consist. True, in lepromatous cells one can note phenomena of pyknosis, wrinkling of nuclei, and sometimes their disintegration, but it only reaches the formation of even small foci of coagulation necrosis in exceptional cases. Likewise, the nodules only rarely undergo softening and liquefaction with the formation of a cavity filled with a mucopurulent mass, rich in polymorphonuclear leukocytes with lepromatous bacilli enclosed within them (the so-called lepromatous abscess). On the contrary, such nodules and entire infiltrates very often undergo 'fibrous transformation,' whereby the development of connective tissue sometimes leads to the almost complete destruction of the lepromatous tissue or even to the complete disappearance of the leproma through the formation of an intradermal scar. Changes in the skin in the macular or macular-nervous form are less typical. The formation of granulomas is not observed here, and all changes are reduced to the formation of a chronic inflammatory infiltrate, proceeding mainly along vessels, nerve branches, and skin appendages. As with any chronic inflammation, in this infiltrate one finds round, plasma, spindle-shaped, and epithelioid cells, but all these elements in their totality do not produce those dense, more or less distinctly expressed clusters that are inherent in the nodular forms. Typical lepromatous cells are usually absent here. By positioning itself around peripheral nerve endings, the infiltrate compresses and destroys them. Sometimes, especially in large nerves, the infiltrative process penetrates between individual nerve fibers, which leads to a thickening of the nerve trunk, often so significant that the nerve is easily palpable through the skin. The fate of such an infiltrate is not uniform. Sometimes it scleroses, turning into connective tissue; in other cases, becoming enriched with cells, it reorganizes into the form of genuine lepromatous granulation, and then one speaks of a 'leproma of the nerves'; finally, in a third series of cases, the infiltrate, undergoing coagulation necrosis, leads to the formation of extensive cheesy foci, giving a picture completely similar to the changes in tuberculosis (tuberculoid changes of nerve trunks). Very often in macular and macular-nervous leprosy, one finds changes, the nature of which has only begun to be clarified recently. These changes consist of the appearance of small areas scattered throughout the thickness of the skin, built of 'epithelioid' cells with an admixture of lymphoid elements (lying for the most part at the periphery), with coagulation necrosis beginning in the center and the formation of typical Langhans cells. In view of the exceptional similarity of these changes to tuberculous ones, such cases are called tuberculoid leprosy [see color plate (p. 255-256), fig. 2] (Jadassohn, Klingmüller, Kedrowsky, and recently Darier and Pautrier and Boez). Changes in internal organs are well studied only in the tuberous form. The most affected organs here are the lymph nodes, liver, spleen, and (in men) the gonads. In lymph nodes during fresh lesions, the formation of small granulomas occurs, consisting of plasma and 'foamy' lepromatous cells and immersed in the preserved tissue of follicles and sinuses. In older lesions, both the follicular apparatus and the sinuses can be completely filled with massive clusters of lepromatous cells, arranged without any particular order among the remnants of the preserved tissue. Individual cells, confined to the trabeculae and walls of capillaries, can be scattered everywhere quite randomly' (Stein). The process is accompanied by a thickening of the trabeculae and reticulum and, in general, by the proliferation of connective tissue. A similar picture is observed in the spleen. Small granulomas, sometimes consisting almost entirely of lepromatous cells, confined mainly to the central arteries and to the walls of venous sinuses, are also encountered here. Individual lepromatous cells, sometimes reaching large sizes, can be seen scattered throughout the tissue of the organ. In the liver, the process is expressed by the formation of small granulomas in the periportal tissue, partly by even smaller clusters of lepromatous cells between the trabeculae near the capillaries and sometimes the central veins, or even in the lumen of the vessels themselves. Besides these cells, bacilli are encountered here in the endothelium of the intertrabecular capillaries, in individual Kupffer cells, often swollen and vacuolated, and even, it is said, in the liver cells themselves. The lesion of the testicles consists of the formation of multiple granulomas in the intertubular connective tissue. Granulomas and the entire inflammatory process in general can reach significant development here, due to which the interstitial tissue proliferates to a high degree and, by compressing the seminiferous tubules, leads to their atrophy and disappearance.
The membrana propria of the tubules becomes hyalinized, swells, and thickens; the cellular layers gradually disappear, so that in the final stages, the testicular tissue is found to be unusually sharply altered: the walls of the tubules are excessively thickened, partly due to the proliferation of fibrous tissue, partly due to the swollen, hyalin-degenerated membrana propria; the lumen of the tubules is narrowed—sometimes almost to complete obliteration—and is lined by only a single row of strongly flattened cells, and in the lumen itself, one can often encounter foamy cells bearing all the signs of leprosy and containing typical "globes" of leprosy bacilli (Babes, later Stein). Leprosy of the lungs is observed extremely rarely. The lesion proceeds either very slowly or more acutely. In the first case, the process consists of inflammatory infiltration of the interalveolar and peribronchial tissue, which leads to compression and collapse of the small bronchi and alveoli. The process resembles tuberculous peribronchitis and is accompanied by the formation of cirrhotic foci, either localized or more diffuse (Babes, Bonome). Leprosy-containing bacilli cells in the septa or alveoli are encountered in small numbers. In cases proceeding more acutely, sometimes even with the expectoration of bloody sputum containing leprosy cells and leprosy bacilli (Doutrelepont, Wolters), large accumulations of actual leprosy cells packed with bacilli are found in the infiltrated septa and alveoli. In the central nervous system, leprosy (granulomatous) changes have not been found to date. Sudakevich, Babes, Lie, and others have seen accumulations of bacilli, sometimes in large numbers, in the ganglion cells of the spinal cord, Gasserian, cervical sympathetic, and intervertebral ganglia. Sudakevich saw them in the terminal nerve branches and tactile corpuscles of the skin. In some cases, they were also found in the endothelium of the capillaries of the brain (Babes, Stahlberg, and others). All these observations concern mainly the nodular forms, in which a huge number of bacilli are scattered in the tissues. In macular-nerve forms, such findings are noted less frequently (Babes, Vnukov, Lie). Bacilli have not been detected in the cerebrospinal fluid. Lesions of the mucous membranes (mainly of the upper respiratory tract, very rarely of the intestine) consist of their leprosy infiltration, which leads to their thickening (local) and later to ulceration [see color plate (col. 255-256), fig. 8]. The skeletal system is affected either in the form of osteitis or periostitis, which leads to uneven nodular thickening of the bones and to the formation of tuberosities along their periphery (in cutaneous leprosy), or in the form of atrophy and resorption, sometimes so complete that, for example, the phalanges of the fingers, and even the hands and feet, disappear (in nerve leprosy).
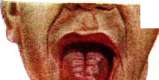
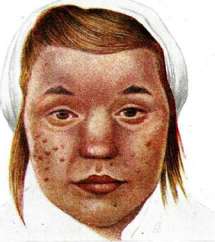
V. Kedrovsky. Clinical features. The primary affect in leprosy is usually impossible to find. Even during the long incubation period (on average 3-5 years), characteristic signs of the beginning disease are not noticed. Rarely can prodromal phenomena be established: rheumatoid and neuralgic pains, itching, a sensation of crawling ants, numbness in the limbs at night, vesicular rash similar to pemphigus, nasal congestion from dry rhinitis, and nosebleeds. The former classification of leprosy into 1) nodular and 2) anesthetic (Danielssen and Boeck), or maculo-anesthetic (Hansen), or nervous (Virchow and Neisser) forms does not make it possible to draw a definite line between these forms, which is why ambiguity and confusion were created. Figure 1. Tubercular leprosy (mild form). Figure 2. Maculo-anesthetic leprosy. Figure 3. Macular leprosy. Figure 4. Sinking of the nose in leprosy. Figure 5. "Lion face". Figure 6. Tubercular leprosy—before treatment (patient from the Tokyo leprosarium). Figure 7. The same—after 1 year of treatment with Hydnocarpus anthelmin-tica oil. Figure 8. Tubercular leprosy (severe form). The International Conference of Leprologists-Experts (Manila, 1931) proposed distinguishing 2 forms of leprosy: 1) cutaneous and 2) nervous—with precise assignment of certain manifestations to one or another definite form. In the following presentation, the latter classification is adopted. 1. Cutaneous leprosy (Lepra cutanea) includes the forms: macular, maculo-anesthetic, tubercular or nodular. Cutaneous leprosy usually presents as a polymorphic rash. Macular erythema (Lepra maculosa) appears predominantly on the face and on the extensor surfaces of the limbs. This rash can have a temporary character, or in the future leads to the formation of rings and garlands with the disappearance of pigment in the central parts (morphaea alba) or with its increase (morphaea nigra). When palpating the spots with a finger, one can easily be convinced of some density in them, especially at the periphery. In the area of the spots, sometimes weakly, sometimes sharply expressed disorders of sensitivity are found (hyperesthesia or paresthesia, and then anesthesia)—Lepra maculo-anaesthetica. In other cases, the spots form well-defined, dense plaques rising above the surface of the skin; often simultaneously with them or later, hill-like small nodules, tubercles, and nodes arise, protruding above the surface of the skin—Lepra tuberosa or Lepra nodosa. All these elements have a reddish-violet or brownish-bronze color, are dense and painless. Their number is unequal: in some cases, there may be only one or two nodes, in others almost the entire skin is dotted with them. They are located on any area, but only rarely affect the Scarpa triangle, the popliteal and elbow flexures, and the scalp. A favorite place is the face, where the lesion is often expressed in the form of solid, diffuse disfiguring infiltrates, separated by deep furrows. Such nodes and diffuse infiltrates, located on the forehead, superciliary arches, wings of the nose, cheeks, and chin, often give the face a stern expression resembling the face of a beast—facies leonina. The color of the skin takes on an earthy or dark violet color. On the surface of the infiltrates, one can observe an abundant number of telangiectasias. These changes are pathognomonic for leprosy. The eyebrows fall out, and in the case of the localization of tubercles on the eyelids, the eyelashes also fall out. The hair of the beard and mustache is affected insignificantly. On the head, small or larger bald patches are encountered in the form of alopecia areata. Due to infiltrates and edema, the auricles increase in size (1 1/2-2 times), their lobes are sharply infiltrated. [See separate table, figs. 1-8 and color table (pp. 255-256), figs. 9 and 10.] On the trunk, the nodes are located on the abdomen, back, and to a lesser extent along the axillary line and along the line of the spinal column, not reaching large sizes here. On the trunk, diffuse erythemas or sharply defined plaques are found. Rarely are small lichenoid nodules observed, sometimes clustered, sometimes diffuse. The nodes on the upper and lower limbs reach the size of a cherry and larger. Upon their fusion, extensive indurations of cartilaginous consistency are obtained, without inflammatory phenomena around the periphery, painless or slightly painful. These lesions are accompanied by a cyanotic color and dense edema of the skin of the forearms and hands (cushion-like indurations), shins, and ankle joints. The fingers of the hands can acquire a "bottle-like" shape. The edematous swelling of the limbs can turn into a compact, densely plastic infiltrated mass with the proliferation of connective tissue. These changes lead to elephantine thickenings, which gave grounds to call leprosy elephantiasis graecorum. On the soles, a clearly expressed picture of hyperkeratosis is present. On the palms and soles, tubercular eruptions are encountered, not sharply protruding above the surface of the skin in the form of limited dark violet indurations. Extensive infiltrates and nodes can lead to ulcerative processes, necrosis, and even gangrene, due to which partial rejection of the phalanges of the hands and feet (mutilation) is observed. The lesion of the mucous membrane of the mouth and nose reduces to the formation of small grayish-white tubercles on the hyperemic nasal septum and larger infiltrates on the soft and hard palate, tongue, uvula, and arches. On the nasal mucosa, the tubercles disintegrate quite quickly, giving erosions and ulcers. The lesion of the nose is accompanied by bleeding, mucopurulent discharge, the formation of crusts and scars, entailing the closure of the nasal passages and severe respiratory disturbances. The shape of the nose can change sharply both due to the destruction of the cartilaginous part of the septum (sinking of the nose) and due to infiltrates of the bridge of the nose or wings. The lesion of the lips (tubercles, infiltrates) often leads to a kind of leprous elephantiasis. The tongue most often presents phenomena of sclerotic glossitis with limited or merging infiltrates covered with mucus and desquamated epithelium (of the type of syphilitic mucous plaques). Taste is preserved for a long time. The tonsils, mucous membrane of the cheeks, and gums are affected relatively rarely. Often, sharp deformation or complete destruction of the uvula and arches is observed. Perforation of the hard palate belongs to rarities. The process often spreads to the larynx. Changes in it are characterized by disfigurement of the epiglottis by infiltrates, ulcers, and scars, its curling into a tube when replaced by scar tissue, infiltrates and ulcers in the region of the arytenoid cartilages, false and true vocal cords, the interarytenoid and subglottic space. All the above-mentioned changes cause one or another degree of narrowing of the larynx and a condition of the voice called vox rauca leprosorum. In cutaneous leprosy, eye involvement is often encountered (up to 85%). The most common form of the disease is episcleritis, to which keratitis and iritis can be added, which, however, can also develop independently. Leprous iritis often leads to blindness. Diseases of the posterior part of the eyeball are extremely rare. Lymph nodes in cutaneous leprosy increase. They are painless, fused together, and mobile. The genital organs are affected much more often in men than in women. The testicles and epididymides become bumpy, dense, and painless (orchitis or orcho-epididymitis). There may be a slight discharge from the urethra, sometimes with leprous bacilli (leprous urethritis). In advanced forms, there occurs, for the most part, complete atrophy and desolation of the testicles, leading to azoospermia and infertility. In women, menstrual disorders are observed—irregularity in timing and duration, cessation. Very often, in the cutaneous form, thickening of the nerve trunks is observed (especially nn. ulnaris, radialis, peronaei, auricularis, etc.). 2. The nervous form of leprosy (Lepra nervorum, s. nervosa) is caused by the involvement of peripheral nerves and the central nervous system. This form can present extremely complex and variegated pictures in the form of sensitivity disorders, trophic disturbances, or paralyses and their subsequent results: atrophy, contractures, ulcers. The nervous form is not accompanied by leprous skin changes. Anesthesia is the dominant sign here. It is located symmetrically on the limbs, starting most often from the outer surfaces as a narrow band, gradually widening and capturing the entire surface of the limbs. In other cases, one can observe the development of anesthesia in segments throughout the body. Due to the loss of sensitivity (mainly temperature and pain) and trophic disturbances, blisters form—pemphigus leprosus, ulcers (mal perforant), especially on the feet and hands, and necrosis, which lead to the rejection of the phalanges of the hands and feet (Lepra mutilans). The muscles of the face, upper and lower limbs, and sometimes the trunk undergo atrophy. Amyotrophies of the face can result in the inability to close the eyelids and create absolute immobility of the facial features (Antonin's mask). The lower eyelid and lower lip sag; "hare" eye leads to clouding and ulceration of the cornea, which can entail complete loss of vision.
Progressive atrophy of the muscles of the thenar eminence and the interosseous muscles leads, in accordance with the distribution of the paralysis, to the formation of a contracture of the Aran-Duchenne type in the form of a 'claw hand'. Thickening of the nerve trunks begins mainly with the ulnar nerve and develops in the following order: auditory (great), tibial behind the great condyle, supraorbital, peroneal. Abscesses of the nerves (ulnar) are encountered, accompanied by severe pain. The thickening of the nerves is uniform, but not beaded. Sharp contractures are often observed. Vasomotor disorders manifest as a sensation of cold, cyanosis of the hands and feet. Painless panaritiums of the Morvan type are also encountered, which end in necrosis and the falling off of one or two phalanges or the entire finger. On the part of the psychic sphere, depression is sometimes observed, while specific psychoses of the Korsakoff type are noted as an exceptional rarity. Lesions of the meninges (leprotic meningitis) are also rarely encountered. The course of P. is usually chronic in the form of separate bouts. Remissions can last for months and even years. According to the severity of the course, the disease can be divided into 3 groups: 1) mild form—there are small areas with impaired sensitivity and insignificant trophic disorders (neural-1) or there are one or several leprotic spots and a few limited infiltrates or nodules (cutaneous-1); 2) moderate form—when there are significant disturbances of sensitivity, paralysis, atrophy, blisters, etc. (neural-2), or there is a large number of spots, or nodules, or infiltrates, and lesions of the mucous membranes (cutaneous-2); and 3) severe form—extensive anesthetic areas, significant motor disorders and trophic changes, paralysis, atrophy, contractures, trophic ulcers and mutilations (neural-3); extensive lesions of the skin and mucous membranes (extensive infiltrates, necrosis, ulcers) in various stages of development (cutaneous-3). Kuznetsov distinguishes 4 periods in the course of the disease: I—latent (prodromal), II—period of flowering (benign and malignant), III—period of stability, and IV—relapse-free period. In the cutaneous form, the patient usually feels satisfactory and complains only of rheumatoid and neuralgic pains. The cutaneous elements for the most part do not bother the patient, and only under the influence of trauma, forced treatment, or exacerbation can they undergo inflammation, suppuration, and disintegration. In other cases, the course of P. is distinguished by great severity: lepromas disintegrate and ulcerate, necrosis and gangrene occur on the extremities, complicated by secondary infection, and the patient complains of sharp pains in the joints and along the nerve trunks. Stenotic narrowing of the larynx is often present, requiring immediate assistance (lazaret form). In neural P., the process proceeds slowly and sluggishly and reminds of itself with pains, paralysis, atrophy, and contractures, which lead the patient to complete disability. In the course of P., exacerbations are often observed, occurring spontaneously or after various unfavorable factors. This is the so-called 'leprotic reaction' or 'leprotic fever' (of English authors). It influences the course of the process sometimes beneficially, and sometimes, conversely, sharply worsens it. In the course of P., one can observe the simultaneous existence of cutaneous and neural manifestations. Active leprotic cutaneous changes can disappear, leaving only neural changes. Such forms have the name of secondary neural. Diagnosis. In developed forms, the clinical diagnosis presents no difficulties. All anamnestic material with an analysis of the epidemiological characteristics of the patient's place of residence, his connection with those around him, the onset and development of the disease, and at least an approximate clarification of the causes often suggest the thought of P. if the patient had relatives and acquaintances with P. Therefore, here morphological signs in many cases give way to etiological factors. Further clarification of the diagnosis can be based on the characteristic signs of cutaneous and neural lesions. These include spots, tubercles, nodules and infiltrates, lesions of the mucous membrane of the nose and mouth, thickening of the nerve trunks, enlargement of the lymph glands, disturbance of sensitivity, and trophoneurotic disorders. It is especially easy to recognize the nature of cutaneous lesions if one pays attention to the absence of pain in them, their cartilaginous consistency, the different age of the elements (leprids), their bronze-brown or violet-red color, the change in the coloration of the superciliary arches with the loss of eyebrows, more often from the outer side, and puffiness and change in the coloration of the face. Since in practice cutaneous forms in the form of tuberous or spotted varieties are most often encountered, while neural forms without cutaneous lesions are observed extremely rarely, the diagnosis of the disease is in most cases not difficult. The pure neural form of P. presents great diagnostic difficulties. In individual cases, errors are observed. Thus, a case is described where one of the experts in this field, Lere, presented his observation to Berlin neuropathologists, who confirmed the diagnosis of syringomyelia. The same case was shown in Berlin at a congress on P. and was recognized by dermatologists as a typical case of P. When diagnosing neural P., sensitivity (temperature, pain, and tactile), trophic, and motor disorders are examined. In the early stages, pains similar to rheumatoid or neuralgic ones are noted, or widespread hyperalgesia is observed. Anesthesia is preceded by hyperesthesia with the same localization and distribution as the anesthesia, so that one can observe changes in sensitivity sometimes in the form of separate scattered islands, sometimes in the form of bands, sometimes in the form of a glove on the hands, etc. A characteristic sign for neural P. is the systematic nature of the anesthesia. Disorders of sensitivity are predominantly observed on the extremities; they begin on the hands and feet and then spread further upward. In view of the fact that neuritis of specific nerves lies at the basis of neural P., one can speak of a classical localization of anesthesias. These areas correspond on the arms to the sphere of the ulnar nerve, and on the legs to the sphere of the peroneal nerve. Muscle atrophy is observed mainly on the extremities again. Paralysis of the peroneal nerve is often observed, and the gait is difficult. An ataxic gait is not encountered; the Romberg symptom is absent. Tendon reflexes on the extremities can be completely normal. Among trophic disorders, one can note the formation of pemphigoid blisters, changes in the nails (softening, destruction), and a sharp decrease or cessation of sebum secretion. In other cases—especially in early diseases—cutaneous lesions are expressed so 'faintly' that a diagnosis is impossible without bacterioscopic examination. Such an examination is subjected to: 1) discharge from the mucous membrane of the nose, 2) punctate from lymph glands, 3) tissue fluid of cutaneous elements. When examining mucous membranes, discharge from ulcers is used. In the absence of ulcers, a scraping is examined. Deycke recommends examining for bacilli the tissue fluid or serous fluid exuding from the superficial layers of the mucous membrane upon light friction with some disinfected object, best of all the burnt end of an ordinary match. The tissue fluid of lepromas is most conveniently obtained by 'scooping': with a sterile scalpel, one penetrates deep into the tissue of the element and, before blood appears, turns the knife, tilting the handle to the right, and quickly scoops out a part of the tissue with the blade, which is then smeared on a glass slide. For the purpose of 'enrichment', it is sometimes useful to apply the method of Greenbaum and Schamberg: a small amount of sterile physiological solution is drawn into a sterile syringe and, after piercing the skin in the area of the element, the physiological solution is first introduced into the tissue, and then, by repeated suction, a small amount of material is pumped out, which is then examined for bacilli. Lowe, considering the earlobes to be the most frequent and earliest site of localization of lesions in P., recommends cutting off a small piece of the lobe for diagnostic purposes and smearing a glass slide with the cut surface. In all cases, no matter how clearly they are expressed, it is recommended to resort to histological examination of biopsied pieces. In the case of the early appearance of rashes and, in general, in cases unclear in clinical terms, such examinations become mandatory. Of particular attention in diagnostic terms are those cases of spotted-neural P. where, upon microscopic examination, a picture of tuberculosis-like changes is found. To exclude the tubercular nature of the lesion, one has to resort to experiments on animals here. For staining bacilli, the method of Ziehl-Neelsen or Ehrlich is usually used. The method of Baumgarten also gives good results. Sometimes it is necessary to apply the Gram-Much method as well. Immunity reactions have not yet acquired practical significance for the diagnosis of P. The Bargehr reaction did not justify the hopes placed on it. The Rubino reaction in the hands of various authors gave very mixed results. The Kulesh reaction (with leprin) is in the development stage.
The complement fixation reaction has not yet been sufficiently developed for leprosy; leprosy is most often confused with syphilis. The deformity of the nose somewhat resembles syphilitic changes, but unlike syphilis, in leprosy it is not the bony part of the septum that is destroyed, but the cartilaginous part, and the nose collapses below the bony part with the formation of a transverse dense ridge. Among skin tumors, leprosy resembles neurofibromatosis, multiple leiomyomas, idiopathic Kaposi's sarcoma, and leukemic skin tumors. The absence of cardinal signs of leprosy (anesthesia and bacilli) allows for their exclusion. Various forms of ringworm may resemble the spots in leprosy, but the presence of fungus and the absence of bacilli and anesthesia easily exclude leprosy. Erythema nodosum differs from cutaneous leprosy by the suddenness of its appearance, the tenderness of the nodes, and an acute but short-lived course. Tuberculous skin lesions differ from the manifestations of leprosy by the absence of anesthesia, color, consistency, and the nature of the arrangement of the elements. Vitiligo, as well as pellagra, are not accompanied by sensory disturbances, and the lesions in these conditions differ sharply from the eruptions in leprosy. Syringomyelia has a great similarity to neural leprosy. Unlike leprosy, the facial muscles are never affected, and the hair of the eyebrows does not suffer. Prognosis. The course of leprosy, if left to itself, is unfavorable. Cases of spontaneous recovery are extremely rare. The question of curability can be considered almost resolved. Early forms of cutaneous and neural leprosy respond to therapeutic intervention to such an extent that patients become visibly healthy. Developed forms are more difficult to treat, but they also regress significantly under the influence of anti-leprosy agents and the improvement of sanitary and hygienic conditions. In the Culion leprosarium (Sinope), from January 1, 1922, to October 31, 1929, 1,355 patients out of 6,800 regularly treated during this period were discharged as practically healthy (so-called negative), i.e., 19.6%, with treatment lasting from 4 months to 8 years. In view of the possibility of the disease returning later (1931), it has been proposed to designate such cases as "quiescent" or "arrested." In cases that do not respond to improvement, the average duration of the disease is 6-8 years for the cutaneous form and 10-15 years for the neural form. Mortality in leprosy is caused mainly by pulmonary tuberculosis (46.4%), nephritis (18.2%), amyloidosis, and arteriosclerosis; leprosy itself is the primary cause of death in only 2.8% of cases. Treatment. There is still no specific remedy for the treatment of leprosy. Among the agents used for leprosy, Oleum Chaulmoograe (chaulmoogra oil) and its derivatives have become widely used. Oleum Chaulmoograe is obtained from the seeds of Taraktogenos Kurzii (King). Opinions differ regarding the pharmacodynamic action of the oil. Some believe that Oleum Chaulmoograe preparations possess a bactericidal effect due to the content of cyclic unsaturated fatty acids in them, while others believe that they only mobilize the body's defensive forces. Mercado sees the essence of the action of the oil and its derivatives in leukocytosis and increased phagocytosis. Rogers asserts that Oleum Chaulmoograe acts by increasing lipase and lipolytic enzymes in the blood, with subsequent dissolution of the fat-wax-like envelope of the microbe. In 1920, Walker and Sweeney showed that chaulmoogric acid and gynocardic acid are 100 times more active than phenol and, in a 1:100,000 solution, kill acid-fast bacilli. If one admits that therapeutic activity is determined by the content of unsaturated fatty acids (most authors point to gynocardic acid), then of all the oils used so far, the first place should be occupied by oil from Taraktogenos Kurzii (Oleum Chaulmoograe) and from Hydnocarpus wightiana (Oleum wightiana). Oleum Chaulmoograe was previously used exclusively internally. It is recommended to prescribe it in ascending doses of 5-30 drops 3 times a day in milk. The negative side of internal administration is dyspeptic phenomena. Since 1888, subcutaneous injection of the oil in pure form or mixed with guaiacol, camphor, creosote, thymol, etc., has been used. All these mixtures are injected under the skin or, more often, intramuscularly at 0.5-10 cm3 two to three times a decade, depending on the reaction. A course of 30-35 injections with a break of 1-1.5 months is recommended. Ghosh (1916) isolated 5-6 acids from the oil, the sodium salts of which were named gynocardates. They are used intravenously in a 3% aqueous solution with 0.5% phenol and 0.5% sodium citrate, starting from 0.5 to 15 cm3. A negative property of these salts is the obliteration of veins at the injection site. The sodium salt of gynocardic acid with a lower melting point, under the name "Alepol," is devoid of this side effect. Dean and Hollman (1918) isolated 4 ethyl esters from Oleum Chaulmoograe. The group of such esters includes Mugrol and Antileprol (Engel-Bey, 1907), which are used in the USSR. They are administered under the skin or intramuscularly at 0.5-5 cm3 two to three times a decade. To avoid irritation and pain, 0.5% crystalline iodine is added to them. Great success is noted from the intradermal application of ethyl esters of Oleum wightiana with 0.5% crystalline iodine in a dose of 0.05-3 cm3 directly into the skin lesions. In 1919, Rogers prepared a salt from cod liver oil and named it Natr. morrhuatum. It is a mixture of glycerides of palmitic, stearic, and some other acids. It is used under the skin, intramuscularly, or intravenously in doses of 0.5-5 cm3. A similar preparation was manufactured in the USSR by Prof. Slovtsov and Astanin. Over the last decades, ethyl esters of castor and perilla oils, soluble preparations of olive, soybean, and linseed oils, as well as a mixture of copper salts with fatty acids, have been tested. Among other chemotherapeutic agents, preparations of antimony, arsenic, gold, and mercury are used. In 1920, Cawston especially recommended an antimony preparation—Oscol stibium. Of the synthetic gold preparations (Triphal, Krysolgan, Solganal, Sanocrysin), krysolgan has a good effect in leprous eye disease. For a combination of syphilis and leprosy, the mercury preparation "Atacol" has been proposed, containing 26.7% mercury, 67% iodine, and 5.4% calcium. Good results have been noted from a mixture of Hg with Oleum Chaulmoograe and Leprol (leprol—sodium sulfonate salt of fatty acids contained in Oleum Chaulmoograe). Muir successfully treated leprous patients with potassium iodide in doses of 0.06 to 14.4. Palldrock (1922) proposed freezing leprous nodes with CO2 snow for 3-4 seconds with light pressure for the cutaneous form. Do not freeze more than 10 areas at once and move on to other areas only every 3-4 weeks. Treatment continues for about 2 years with 4-month breaks. After this, the author uses additional treatment with Solganal, which is injected into a vein at 0.1-0.5 twice a week for 5 months. Andruson successfully used light cauterization of the nodes with a Paquelin cautery. Cauterization is done quickly, no more than once a week, first on the periphery of the nodes; as the leproma decreases, they move toward the center. Among biological preparations, extracts, vaccines, autolysates, etc., have been used. This group includes: 1) Nastin—a lipoid-neutral extract obtained by Deycke from his own culture of Streptothrix leproides; 2) leprin—an emulsion from leprous nodes in glycerin broth (Babes); 3) leprolin; 4) leprolysin and other vaccines prepared from various leprous cultures (Rost, Kedrovsky, etc.); 5) autolysate of tubercle bacilli prepared by Row. For lesions of the mucous membrane of the mouth and nose, swabbing and painting with a 5% solution of chromic acid or a 50% solution of lactic acid and alkaline rinses are used. For leprous reactions and severe neuralgic pains, a good result is achieved with the help of lacto- and autohemotherapy or intramuscular injections of Ephedrin at 0.05-0.1 or a solution of adrenaline (1:1,000)—3 drops in 30 drops of physiological saline. The choice of one or another method of treatment must be coordinated in each case with the general somatic condition of the patient and the stage of the leprous process. Treatment should not be forced. By alternating courses of treatment with periods of rest and tonic treatment (arsenic, iron, strychnine, and other tonic agents), as well as by keeping the patient in sanitary and hygienic conditions and having them perform dosed labor processes, it is possible in most early and even in developed forms of leprosy to obtain significant success, up to a clinically visible cure.
N. Pavlov. Prophylaxis. The starting point for modern measures to combat leprosy must be: 1) recognition of the absolute contagiousness of the disease; 2) recognition of the fact that leprosy is one of the most severe diseases both for the patient himself and for those around him. Only the indisputability of these two facts, taken together and complementing one another, can serve as a justification for those "severe" measures which we consider possible to apply to leprosy patients. These measures consist in removing the sick persons as a source of further infections from society and in this way "neutralizing" them. All the above-mentioned (three) international conferences on the study of leprosy came to the conclusion: to recognize the isolation of leprosy patients as the best means against its spread and to "recommend" for its implementation the system adopted in Norway. But, reviewing the work of the conferences and their conclusions in chronological order, one must come to the conclusion that both the views of doctors and the resolutions of the conferences have changed significantly towards a softer attitude to the question of isolation. While the Berlin Conference (1897) insistently recommended the system of "compulsory notification, supervision, and isolation" used in Norway for all nations with autonomous local government, the Strasbourg Conference (1923) recognizes the "necessity" of isolation only for countries where leprosy is endemic; for all other countries where leprosy is not widespread, the conference only "recommends" isolation according to the Norwegian system "in a hospital or at home," while adding: "if possible." In general, the conference concludes, "legislative prescriptions must differ depending on the country where they are applied." The isolation system introduced in Norway in 1856 was voluntary. From 1885 it became compulsory. One of the most important moments of this isolation is the compulsory registration of patients. Since the leprosaria existing at that time could not immediately accommodate all the discovered patients, isolation at home was permitted along with isolation in leprosaria, which was allowed each time at the discretion of the chief inspector in charge of all leprosy affairs in the country. The included diagrams (Fig. 1 and 2) characterize the movement of patients over the entire period of the introduced and still operating system. It can be seen from them that the number of patients during this period (1856-1927) decreased from 2,858 to the modest figure of 90. If one also takes into account that in 1926 and 1927 there were no new cases of the disease in Norway, then together with Chief Inspector Lie, one must come to the conclusion that the leprosy endemic in the country is on the eve of its cessation. Despite the compulsion, isolation in Norway was never complete, however, leprosy began to decline rapidly 15 years after the enactment of the isolation law. The chief medical inspector for leprosy affairs in the country, Lie, explains this circumstance by the fact that along with isolation, the establishment in the country (1857) of so-called "people's committees" for sanitary education played a huge role, the duties of which included familiarizing the population with general sanitary-hygienic requirements regarding housing, clothing, and nutrition, as well as with the manifestation and course of diseases, mainly infectious ones, including leprosy. However, one cannot limit the idea of "education" to narrow
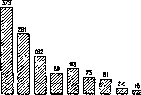
Figure 1. Number of new leprosy cases in Norway from 1857 to 1925 by five-year periods. ...frames of sanitation. Raising the general cultural development of the population, its social and living standards, and economic well-being is still the most important link in the chain of measures to combat infectious diseases in general. It is precisely this factor—the raising of cultural... 25C0 \ Total number of patients ----------------patients in districts ----------------hospitalized patients
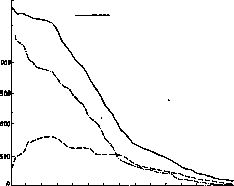
Figure 2. The movement of leprosy in Norway from 1856 to 1927. [The general] level of the population, and not isolation—many authors attribute decisive importance to [it] in the relatively rapid disappearance of leprosy in the countries of Western Europe. In a prominent place, one must put the widespread introduction among physicians and paramedical personnel of knowledge about leprosy—about its clinical picture, spread, epidemiology, bacteriology, and treatment. Children fall ill with leprosy more often than others. According to data from the English Leprosy Commission, which worked in 1890–1891 in India, out of 2,371 leprosy patients, 264 family cases were discovered, of which 130 fell to the share of children, i.e., half of all discovered cases. According to Lee's observations, children with a sick father fall ill in 10.27% of cases, with a sick mother—in 16.36%, with both sick parents—in 39.19%. Therefore, one of the most essential measures in the fight against leprosy should be considered the earliest possible removal of children from their parents. Such children are either given into the care of relatives or separate 'shelters' are created for them. In Russia, until the 1880s, government bodies viewed leprosy as a non-contagious disease. In the early 1880s, G. N. Minkh first spoke out insistently with the opinion about the 'contagiousness of leprosy and the necessary measures against it in Russia.' Soon he was supported by E. Wahl, K. K. Dehio, and O. V. Petersen. A convinced and decisive opponent of theirs was A. G. Polotebnov. The dispute between the two groups of the most prominent representatives of the clinical science of that time contributed much to the revitalization of the very question of leprosy, and it was from this very moment that a period of ever-increasing attention to patients and the disease began for us. Thanks to the efforts of Prof. Petersen and the Zemstvo physician P. N. Prokhorov, the first of the currently existing colonies for leprosy patients in the European part of the USSR was founded in 1895 (Krutye Ruch'i, Leningrad Oblast, near the town of Kingisepp). Then leprosaria began to arise: Astrakhan (1896), Nikolayevsky on the Amur (1896, transferred to Vladivostok in 1925), Tersk (1897), Kholm (1905), Karachay-Cherkess (1914), Irkutsk (1926), and two in Yakutia: Vilyuysk (1892) and Sredne-Kolymsk (1907). In the very recent time, one leprosarium each has been opened in Uzbekistan (Samarkand), Kazakhstan (Kzyl-Orda), and Turkmenistan (Ashkhabad). Leprosaria must be organized in such a way that patients go to them 'voluntarily and willingly' (Strasbourg Conference). For this, it is necessary to give them such an appearance that patients, upon entering them, feel the change in their situation the least acutely. In the USSR, the main mass of patients falls on agricultural elements. Therefore, the idea that our leprosaria should be primarily medical-labor colonies of an agricultural type does not meet with objections from anyone. Labor itself in the fresh open air, connected with muscular tension, correctly set up and dosed in proportion to the strength of the patients, is recognized by Soviet leprologists as one of the powerful factors in the treatment regimen. Besides field and garden work, special craft workshops with special instruction should be organized in leprosaria. Educational work (cinema, clubs, theaters, talks, library, etc.) should be widely established. Isolation at home comes down to a separate room, the absence of close and prolonged communication with those around, the use of one's own household inventory, especially linen and bedding, and medical control. Patients should absolutely be forbidden from occupations connected with supplying the population with food, clothing, and other consumer goods, as well as occupations requiring close communication with healthy people (barbers, laundresses, private and public service, etc.). Visiting public places and institutions (baths, places of entertainment, public gatherings, etc.) should also be prohibited. Legislation. In every country, there is its own legislation regarding leprosy, not everywhere, however, sufficiently developed. France still has no legislation on leprosy, and the 300 patients in Paris itself can freely reside in the city. England, with its solidified cultural and everyday forms, also relates very skeptically to any restrictive and coercive measures in relation to lepers, both in the metropolis and in the colonies. On the other hand, Estonia and Latvia require the mandatory removal of patients to a leprosarium, while Norway, Sweden, and Finland allow isolation at home. In Russia, the first step of government bodies in the leprosy matter can be considered the circular of the Medical Department of 18/IV 1895, which established the mandatory registration of leprosy patients by a card system. The next step was the circular of 2/IV 1902, which outlined in general terms those main lines along which measures to fight leprosy subsequently proceeded. After the October Revolution, an important stage in the development of regulations on protecting the population from leprosy is the issuance by the People's Commissariat of Health of the RSFSR of two circulars of 4/IV 1923 (Nos. 74 and 75), by which were given: 'Instruction on the fight against leprosy' and 'Regulation on leprosaria.' Then on 10/VII 1923 followed a decree of the Council of People's Commissars of the USSR, by which were entrusted: 1) to the People's Commissariat of Health—registration of all lepers in the Union; mandatory isolation of them in leprosaria or at home; provision in budgets of funds for the maintenance of leprosaria; 2) to the People's Commissariats of Agriculture—provision of leprosaria with land plots; 3) to the People's Commissariats of Social Security—provision for persons placed in leprosaria and their dependents; 4) to the People's Commissariat of Transport and the People's Commissariat of Health of the RSFSR—issuance of instructions on the preferential transport of leprosy patients by rail and water routes; 5) to the People's Commissariat of Foreign Affairs together with the People's Commissariat of Health and the People's Commissariat of Internal Affairs—conclusion of agreements with foreign states on prohibiting the entry of leprosy patients from abroad. At the present time, a draft of a new law on the fight against leprosy is being developed.
V. Kedrovsky. Lit.: Kulesha G. and Malinin I., Materials on the study of leprosy in the Kuban, Rostov-on-Don, 1928; Minkh G., Leprosy in the south of Russia, Vol. I–II, Kiev, 1884–94; Prospects for the fight against leprosy, collection edited by A. Vladimirov, V. Kedrovsky, I. Kovalev, and A. Miskinov, M.-L., 1929; Pospelov V., Index of works and articles on leprosy in the Russian language, Russkiy vestnik dermatologii, Vol. VIII, No. 2, 1930; Leprosy and the fight against it in the USSR, collection edited by V. Kedrovsky, I. Kovalev, and A. Miskinov, M.-L., 1927; Reshetillo D., Leprosy, SPB, 1904 (lit.); Aoki T. u. Aoki Y., Untersuchungen uber die Friihdiagnose u. Therapie der Lepra, Tokyo, 1930; Cook V., The epidemiology of leprosy in Australia, Melbourne, 1927; Deycke G., Die Lepra (Spez. Pathologie u. Therapie innerer Krankheiten, edited by F. Kraus u. Th. Brugsch, Vol. II, Part 1, B.-Wien, 1919, lit.; Russian ed.—F. Kraus u. Th. Brugsch, Infectious diseases, Vol. I, issue 2, P., 1916); Gron K., Lepra in Literatur und Kunst (Hndb. d. Haut- u. Geschlechtskrankheiten, edited by J. Jadassohn, Vol. X, Part 2, B., 1931); Jadassohn J., Lepra (Hndb. d. pathogenen Mikroorganismen, edited by W. Kolle, R. Kraus u. P. Uhlenhuth, Vol. V, Part 2, Jena-B.-Wien, 1928, lit.); Klingmuller V., Die Lepra (Hndb. d. Haut-u. Geschlechtskrankheiten, edited by J. Jadassohn, Vol. X, Part 2, B., 1931, lit.); Kobayashi W., Uber die viscerale Lepra, Kyoto, 1929; Kupffer A., Uber die Verbreitungswege der Lepra-Beobachtungen aus Estland, Arch. f. Schiffs-u. Tropen-Hygiene, Vol. XXXVI, Beihelt 3, Lpz., 1932; Lewandowsky F., Lepra (Hndb. d. inn. Med., edited by G. Bergmann u. R. Staehelin, Vol. I, Part 2, B., 1925, lit.); Marras A., La terapie deila lepra i resultati ottenuti coi moderni trattemento, Sassari, 1929; Rogers L. a. Muir E., Leprosy, L., 1925; Ruge R., Muhlens P. u. zur Verth M., Krankheiten und Hygiene der warmen Lander, Lpz., 1930; p. 381-396; The principles of the prophylaxis of leprosy, League of Nations, Health organisation, Geneve, 1931. Periodical publication.—International journal of leprosy, Manila, since 1933. 277
Related articles
Mentioned in
Cite this page
“Prosencephalon.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/prosencephalon/