Progenia, Prognathia
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet medical encyclopedia defines and classifies prognathia and progenia, discussing their physiological, pathological, and racial origins. It also details the complex surgical and orthodontic methods used for their correction, including various osteoplastic procedures.
Encyclopedia article (1928–1936)
PROGENIA, PROGNATHIA

is secondary as a result of retrogenia (see). True prognathia can be 1) physiological, when it is a racial trait (e.g., in Negroes); in such a case, both jaws are equally strongly developed and functions are performed normally. 2) Prognathia can represent a developmental anomaly of one or both jaws; as a result of such an anomaly, functions are impaired to a greater or lesser degree. 3) Prognathia can have a pathological origin, e.g., in acromegaly. In prognathia, the anomaly can extend either to the entire jaw or to its parts. The latter, in turn, can be either developed more than the norm or can be displaced in the sagittal direction. Thus, cases of protrusion of the intermaxillary bone or the alveolar process are observed.
Cases where the anomaly is caused by the forward protrusion of teeth are more correctly called prodentia.
The indicated types of anomalies rarely have an exclusively sagittal direction; usually, they are mixed; thus, for example, the protrusion of the upper incisors is most often combined with compression of the jaw in the premolar region. The displacement of teeth can occur either parallel to their physiological axes (bodily protrusion) or at an angle to them (coronal protrusion). In Fig. 1, the normal inclination of the physiological axes of the incisors is shown in a 5-year-old child (a—orthognathic position), in an adult representative of an orthognathic race (b—a more prognathic position than in the child), and in a representative of a prognathic race (c). Establishing the presence, degree, and type of prognathia pursues different goals. Anthropology, while conducting racial studies, studies the facial profile. The latter is determined by the facial angle or the angle of prognathia. The profile angle, according to Martin, is formed by the sagittal line of the profile (nasion-prosthion) and the Frankfurt horizontal line (Fig. 2). Measurements, according to Martin, are performed with a sliding caliper with a goniometer. The smaller the facial angle, the greater the degree of prognathia. The following degrees of prognathia are distinguished: hyperprognathia > 69.9°, prognathia 70.0–79.9°, mesognathia 80.0–84.9°, orthognathia 85.0–92.9°, hyperorthognathia 93.0–x. An indicator of the degree of prognathia on the skull is also the alveolar or jaw index: the ratio of the distance from the basion to the prosthion to the distance from the basion to the nasion, with the latter distance taken as 100. The following variations of prognathia are distinguished: 1) complete prognathia of both jaws (observed in lower races); 2) prognathia of the nasal and alveolar regions (in Negroes); 3) prognathia of the alveolar region (in Chinese, etc.). As for European nationalities, they are characterized by an orthognathic profile. Orthodontics, establishing the presence of prognathia, has in mind primarily malocclusions. The latter are reflected in chewing, breathing,
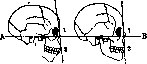
Figure 2. a—prognathic profile, b—orthognathic profile; AB—Frankfurt horizontal; 1—nasion; 2—prosthion.
phonation, and the appearance of the subject, and orthodontics considers primarily the influence on function. Therefore, establishing the presence of prognathia is for the orthodontist only a partial indicator, since the characterization of the occlusion is not determined by it. With significant prognathia of both jaws, function can be performed normally—here orthodontic treatment is not needed. On the other hand, a small degree of P. can lead to significant functional disorders, especially in the presence of retrogenia—then treatment is needed. G. Berkovich. Treatment of progenia and prognathia. Operative correction of these deformities is indicated only in those cases when conventional orthodontic treatment becomes inapplicable: in extremely sharply expressed degrees of deformity and at an age older than 20 years. The goal of treatment is to restore the correct contours of the face and a satisfactory, in functional terms, occlusion of the teeth. The most suitable age for operative treatment is from 20 to 30 years. Correction of jaw deformities is one of the most complex branches of maxillofacial surgery, as it requires the combined use of special treatment methods. The entire treatment plan must be strictly thought out and built on measurement data. The relationships of the dental arches of the upper and lower jaw are checked on plaster models made with the help of Simon's gnatostat. The models are sawed at the site of the intended osteotomy, the individual parts are moved to a new position, and the possibility of tooth occlusion is checked. If, during such trial movement, the dental arches of the upper and lower jaw do not correspond to each other, then it is necessary to first perform orthodontic correction of the entire arch or change the position of individual teeth so that during the operation, after osteotomy or bone resection and after moving the segments, one can immediately achieve correct tooth occlusion. After the completion of orthodontic treatment, wire splints are made, fixing the teeth in the new position in the dental arch and simultaneously serving as a support for intermaxillary traction with rubber rings, for fixing the entire moved jaw segment as a whole. The splints are attached to the teeth on the eve of the operation. Depending on the individual characteristics of each case, various osteoplastic operations can be used. The largest number of different plastic operations has been proposed for the correction of progenia. Ziepfel, Jaboulay and Berard, Berger, Dufourmentel (Ziepfel-1886, Jaboulay, Berard, Berger, Dufourmentel) proposed performing bilateral resection of the condylar heads with subsequent moving of the entire lower jaw posteriorly (Fig. 3). Lane, Babcock, Lindemann, Ernst, Pichler (Lane-1905, Babcock, Lindemann, Ernst, Pichler) perform bilateral horizontal osteotomy of the ascending rami. It is necessary to cut the bone in the region of the upper third of the ascending ramus, above the opening of the mandibular canal. Lindemann makes a skin incision near the earlobe and saws the bone with a hacksaw. Pichler and Kostecka pass a Gigli saw through two small skin incisions. In cases of sharply expressed progenia, when operative treatment is especially indicated, the above-mentioned methods do not provide sufficient space for shifting backward. Therefore, it is better to expose the ascending ramus through a skin incision below the angle of the lower jaw and, after horizontal osteotomy in the above-mentioned place, resect the posterior edge of the ascending ramus below the line of bone intersection, so as not to press on the soft tissues and to preserve the angle of the lower jaw in place (Limberg). Harsha, Cryer, Ernst (Harsha, Cryer, Ernst) propose plastic osteotomy in the region of the angle of the lower jaw. Blair, Eiselsberg, Pichler, Pickerill, Schultz, and others (Blair, Eiselsberg, Pichler, Pickerill, Schultz) used bilateral resection of pieces from the horizontal ramus. The latter methods are difficult to perform without violating the integrity of the neurovascular bundle. After the operation, immobilization of the lower jaw is necessary for 1–2
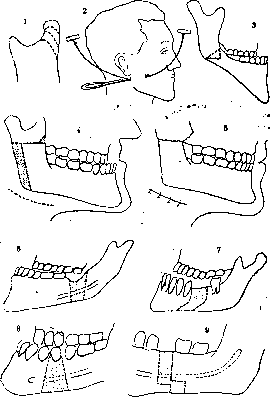
Figure 3. Osteoplastic operations for the correction of progenia: 1—Dufourmentel; 2—Kostecka; 3—Ernst; 4 and 5—Limberg; 6—Harsha; 7—Pichler; 8—Angle; 9—Faderspiel.
months. Untimely application or insufficient strength of fixation of the jaw segments can be the cause of severe inflammatory complications with subsequent bone necrosis (Angle) and the formation of pseudarthroses. With any large displacement of the horizontal part of the lower jaw backward, it is necessary to take into account the resulting sinking of all soft parts of the floor of the mouth and, along with this, the root of the tongue and the epiglottis, as a result of which difficulties in the function of these organs may arise. Operative correction of prognathia is rarely used. Sometimes it is possible to perform a fracture of the anterior section of the alveolar process with subsequent mo

vement of it into a more correct position.
Figure 4. Movement of the mobilized alveolar process of the upper jaw. A canine or a premolar is removed on both sides, the sockets are resected in a wedge shape, and then the base of the alveolar process is fractured. Conn-Stock drills the base of the alveolar process on the right and left and saws it in vertical planes with a Gigli saw. Then the cortical plate is fractured with a chisel, and the entire anterior section of the alveolar process is fractured and moved inward (Figure 4). Technical difficulties consist in not damaging the maxillary sinus and the roots of the teeth, not crushing the bone, and preserving sufficient blood supply to the fragment through the surrounding soft tissues. The unsightly forward protrusion of the anterior section of the alveolar process and the teeth of the upper jaw is safer to correct by removing teeth and subgingival resection of the edge and anterior wall of the alveolar process with subsequent insertion of a dental prosthesis.
Related articles
Cite this page
“Progenia, Prognathia.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/prognathism-2/