Acromegaly
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
A clinical form first described by Pierre Marie in 1886, associated with pituitary disease and characterized by abnormal growth of extremities and body parts. The article discusses its etiology, pathology, anatomical changes, and characteristic symptoms.
Encyclopedia article (1928–1936)
ACROMEGALY (from Greek akron-extremity and megas-large), first described in 1886 by Pierre Marie, is a new clinical form associated with disease of the pituitary gland. The author considered this disease purely morphological, characterized by the marked development of the extremities and all distal parts of the body (nose, jaws, ears, etc.). At present, this disease is interpreted much more broadly, as it is associated with the enlargement of internal organs (splanchnomegaly) as well as with metabolic disorders. The etiology is unknown. Recently, great emphasis has been placed on the constitutional factor (cases of A. in several members of the same family; the existence of a special hyperpituitary constitution, etc.). Provoking factors: psychological trauma, infections (syphilis, epidemic encephalitis, etc.), disorders of the activity of endocrine glands (pregnancy, castration, thyroidectomy, etc.). Pathological anatomy and pathogenesis. In most cases of A., there is an adenoma of the anterior lobe of the pituitary gland (struma pituitaria), less frequently-ordinary hyperplasia of this lobe, and in rare cases-adenocarcinoma. Of the cellular elements of the anterior lobe, the number of chromophilic (eosinophilic) cells is most frequently increased, less frequently-chromophobic (basophilic) cells. These hyperplastic-productive changes are associated with increased activity of the anterior lobe. A number of arguments are raised against the hyperpituitary theory of acromegaly. There are cases where neither X-ray nor autopsy reveals this hyperplasia. However, in these cases, there are either microscopic hyperplastic adenomatous changes (Benda), or an increase in embryonic accessory pituitary glands belonging to the so-called pituitary tract (see)-in the pharynx, in the cavity of the os. sphenoidalis near the anterior lobe of the pituitary gland, in the so-called prehypophysis. The operative successes observed in A. speak in favor of the hyperpituitary theory. Depending on the size and tendency to growth of the pituitary tumor, symptoms from individual parts of the pituitary gland, infundibulum, and basal centers may be added to the specific picture of A. Such secondary symptoms are obesity, hypoplasia of the sexual organs, symptoms of diabetes insipidus, the transition of A. to cachexia. To what extent the true acromegalic phenomena are connected with the trophic brain centers of the base of the brain is still unclear. The pathogenetic connection of A. with hypogenitalism has also not been proven, since 1) not all cases of A. show symptoms of hypogenitalism-in the initial period, hypergenitalism is often observed; 2) in the skeleton of castrates, the epiphyseal sutures remain open for a long time, whereas in 24$

A., on the contrary, the sutures close early, as a result of which growth occurs in width. The changes in the skeleton in A. are so characteristic that sometimes a diagnosis can be made from the external appearance. A. is characterized above all by a change
in the shape of the face (see Figure 1), which acquires coarse features due to the growth of protruding parts. The nose becomes thick (rarely-long); the supraorbital arches protrude significantly forward due to the enlargement of the pneumatic cavities; the cheekbones protrude strongly due to the well-developed proc. zygomaticus; the lower jaw protrudes forward (so-called prognathism), and the lower lip bulges. Prognathism is an early symptom. Due to the growth of the lower jaw, gaps are formed between the teeth, the so-called "diastema".-The growth of the ears is also noted. The symptom of macroglossia (large tongue) is very characteristic, which also contributes to prognathism. The growth of the uvula and vocal cords is often observed-the voice acquires a low timbre. The entire face takes on an elongated-square shape. There are fewer changes on the skull, where the temporal tubercles and the bones of the cranial vault protrude sharply. The volume of the head is significantly increased both due to the thickening of the soft parts and due to the deposition of bone substance (patients have to change hat sizes).-As for the extremities, characteristic changes are only present in the distal parts. The more common type is the so-called "type en large" (Marie), consisting of the "spade-like" expansion, growth of the hands and feet, with wide, cylindrical, "sausage-like" fingers of the hands and feet. Bone participates in this growth, but mainly the soft parts. Exostoses may sometimes be present on the phalanges. Patients cannot wear their own rings, are forced to change shoes, gloves. Less frequently, mainly in cases where the period of skeletal growth is not completed, we have the "type en long", when the hands and feet are elongated in length.-The trunk also participates in the general growth. The sternum, clavicles, ribs are powerfully developed. On the chest, a cervico-dorsal kyphoscoliosis and lordosis in the lumbar region are often observed (see Figure 2). In connection
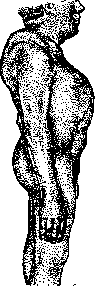
Figure 2.
Along with this, there is an abdominal type of breathing. In far-advanced cases, regressive bone changes are observed: osteoporotic atrophy and loosening of the spongy bones. The skin is usually thickened, folded, dry, less often edematous. Fibromas and warts are often noted. The hair is thick, coarse; it is dense on the head and eyebrows. On the limbs and trunk, there is hypertrichosis, especially pronounced in women, with the hair growth being of the male type (male hair distribution on the pubis, around the anus, hair on the chin). Whether hypertrichosis depends on the increased function of the pituitary gland or the adrenal glands, which are often found to be enlarged in acromegaly, or on both glands, is unclear. The increase in size also concerns the internal organs—the heart, liver, spleen, kidneys, stomach, etc. This symptom is called 'splanchnomegaly'. Whether the enlargement of the endocrine glands (thyroid, adrenal, etc.) is a particular symptom of splanchnomegaly or is connected with other changes has not been clarified. Exceptions to the general splanchnomegaly are the brain, which remains normal in weight, and the sexual organs; in no less than 30-40% of cases, there is atrophy of the sexual organs, amenorrhea, and a decrease in sexual desire and ability (at the beginning of the disease, on the contrary, an increase in them may be observed). Atrophy of the external sexual organs is not observed; at the beginning of the disease, there is sometimes even an enlargement of these organs. Some authors (Falta et al.) do not consider disorders of the sexual sphere to be a pituitary symptom, but associate them with the pressure of the tumor on the vegetative centers in the tuber cinereum. Some authors consider this disorder to be primary, causing acromegaly, which seems unlikely. Metabolic disorders. Whether these disorders depend on the hyperfunctions of the anterior lobe of the pituitary gland or its other parts, or on the regio subthalamica, is still unclear. The basal metabolic rate is often increased, which depends, among other things, on the participation of other endocrine glands in the clinical picture of acromegaly. For example, if there is a combination with myxedematous signs, then an increase in the basal metabolic rate is not observed. The assumption that the basal metabolic rate is regularly increased in acromegaly, and decreased in dystrophia adiposogenitalis, similar to how it is in hyper- and hypothyroidism, has not found full confirmation. The results of the basal metabolic rate depend, among other things, to a significant degree on the stage in which the disease is. Of interest, in connection with bone changes, is the often observed retention of calcium and phosphorus in the body. The most significant disorders concern carbohydrate metabolism. The assimilation limit for carbohydrates is lowered: after the injection of adrenaline, sharp glycosuria occurs. In 30-40% of cases, there is alimentary glycosuria or constant glycosuria (an important differential sign—a distinction from pituitary tumors that do not cause acromegaly). Only in a part of the cases is it possible to explain the glycosuria by C 59 insufficiency of the pancreas; in other cases, this gland is not damaged. It is also impossible to explain the glycosuria by the pressure of the pituitary gland on the sugar centers (regio hypothalamica), because pituitary tumors without acromegaly provide not a lowered, but even an increased tolerance to carbohydrates. Glycosuria is apparently directly caused by the tumor of the anterior lobe of the pituitary gland and disappears with the destruction of this lobe. This explains why, in far-advanced cases, the lowered tolerance to carbohydrates can change into an increased one. Incidentally, according to Kraus, there are changes in the pituitary gland in diabetes. Polyphagia should be considered a persistent symptom in acromegaly, and polydipsia and polyuria (with the involvement of the diencephalon) are less common. As for the hematological picture, as in other endocrine diseases, lymphocytosis is often observed, and eosinophilia is not infrequent. The vegetative nervous system does not show characteristic changes (sometimes excitability is increased; constipation is frequent). The animal nervous system reveals a number of characteristic disorders: rheumatoid pains, especially in the back, acroparesthesia, neuralgia (so-called pseudotabes acromegalica), associated with the pressure of growing bones and deformed vertebrae on nerve pathways and roots. Herzog considers hyperextension of the finger joints to be characteristic of acromegaly. Almost always, signs of arteriosclerosis are found. Blood pressure is often elevated. In the later stages of the disease, degenerative-atrophic changes are found in the muscles, which is associated with increased fatigue. Cerebral symptoms. These primarily include phenomena of increased intracranial pressure: headaches (mainly in the occipital part), dizziness, vomiting, and more rarely, epileptoid seizures. In 50% of cases, there are visual disturbances. They can, as in other brain tumors, be caused by papilledema, but here they are more often a direct consequence of the tumor's pressure on the chiasm and optic nerves, which is why bitemporal hemianopsia, usually starting from the upper outer quadrant, often in the form of a paracentral scotoma, is especially characteristic of acromegaly. Unilateral hemianopsias are also encountered—in cases of asymmetric position of the chiasm. If the pituitary gland grows towards the os sphenoidale, then there are no sharp visual disturbances. Visual acuity decreases gradually (fluctuations are possible). For diagnosis and for monitoring the course of the disease, one of the most important measures is perimetry. Sometimes hemianopsia is preceded by achromatopsia, which is why it is necessary to perform perimetry for colors as well. X-ray reveals a number of characteristic changes, primarily the enlargement of the sella turcica. It is not always possible to draw a conclusion about the enlargement of the pituitary gland based on the enlargement of the sella turcica; thus, in individual cases at autopsy, one finds even a decrease in the pituitary gland despite the enlargement of the sella turcica. In acromegaly, X-ray often reveals an enlargement of the pneumatic cavities and thickening of the phalanges. The question of the psyche in pituitary disorders is complicated by the proximity of the pituitary gland to the diencephalon (the possibility of pressure on the brain, due to which some authors attribute part of the psychic symptoms, namely apathy, indifference, slowness, drowsiness). Some authors associate the indicated symptoms of acromegaly with disorders of sexual functions, emphasizing that where there are no sexual disorders, there are no psychic anomalies. An important symptom should be considered the inability to concentrate attention. In 15% of cases of acromegaly, a decrease in memory and intellectual abilities is noted. Sometimes there is a depressed, irritable state, especially in the initial stage. As for psychoses, almost all types are encountered, most often manic-depressive. Cases have been described where, under the influence of pituitary therapy, the depressive state disappeared. Nevertheless, one must think that acromegaly is only a provoking moment for the development of psychoses and that there are no specific psychoses in acromegaly. The lethargic states described in acromegaly are explained by pressure on the diencephalon. Course. Acromegaly begins gradually, usually at the age of 20-30 years; individual symptoms sometimes exist from early years. Some authors distinguish a separate form of early and pubertal acromegaly. Cases of early acromegaly are very rare; pubertal ones are encountered more often. During the period of puberty, coarsening of facial features and distal parts of the body may appear; with age, these symptoms gradually smooth out. A transient form of this kind is the acromegaly of pregnancy, which, incidentally, sometimes gives an impetus for the development of true acromegaly. The matter can here reach the point of bitemporal hemianopsia, in rare cases even to amaurosis. Erdheim described the so-called pregnancy cells in the pituitary gland, which atrophy after childbirth; some of these cells remain, which is why, with the help of microscopy of the pituitary gland, one can diagnose a past pregnancy. Recently, Hirsch has distinguished another special form of 'benign acromegaly,' in which there is no disorder of vision and sexual glands, but there are, mainly, disorders on the part of the ectoderm: hypertrichosis, hyperhidrosis, increased activity of the sebaceous glands (hence acne), acne, thick skin, thick tongue, defects in the enamel of teeth and nails. Headaches and alimentary glycosuria are very characteristic. This form is close to the so-called forme fruste, to acromegaloidism, in which there is no progressive process and which is characterized by diastema, large ears, a long and large face, headaches (mainly at night), insomnia, fibromatosis, hypertrichosis, etc. Finally, they also speak of the so-called acromegaloid or hyperpituitary constitution; these are individuals of tall stature, with large bones, a large jaw, large supraorbital ridges, a skull of vast dimensions, nose, lips, and limbs. Under the influence of irritants, this constitutional form can turn into true acromegaly; such cases have been described after extirpation of the uterus. Finally, the so-called partial acromegaly, affecting only the tongue, fingers, foot, etc., deserves mention. Zondek explains these cases by the physicochemical peculiarities of the given peripheral area, which is more sensitive to the influence of the pituitary gland. The diagnosis does not present great difficulties, as there is an extensive and vivid symptom complex. It is necessary to keep in mind the frequent combinations of acromegaly with dystrophia adiposogenitalis, Basedow's disease, and myxedema.
In the initial stage, diagnosis is less simple; sometimes there is only a headache, rheumatoid pains, lethargy. Acromegaly differs from Paget's disease in that in the latter, mainly the cranial vault and the diaphyses of long bones are involved; in acromegaly, it is the face and fingers. Prognosis is connected with the nature of the tumor. If there is a benign adenoma, the disease can drag on for decades; if the tumor is malignant, the course is acute and death occurs with symptoms of cachexia. Treatment. Organotherapeutic treatment at the present time finds almost no application. Pituitary preparations are far from always satisfactory. Trendelenburg recognized only 4 out of 17 preparations from different firms as genuine. In individual cases, pituitary preparations, in particular pituitrin, give a temporary therapeutic effect (reduction of headaches, etc.). It is possible that this preparation compensates for the posterior part of the pituitary gland, which is weakened due to the growth of the anterior lobe. Significantly better results are given by the operative method (see below). Recently, radiotherapy has been competing with the operative method, especially indicated where there is no absolute necessity to operate or where the disease has relapsed after surgery. Radiotherapy is not radical and is a palliative. Usually, the parietal fields are subjected to irradiation. Flawless equipment is necessary, since the rays have to penetrate through a layer of 7 cm. Under the influence of this therapy, a weakening of headaches, improvement of vision, and expansion of the visual field are observed. It is rarer to manage to influence the actual symptoms of acromegaly. With the passage of time, a relapse usually occurs. When judging the success of therapy, it is necessary to take into account the possibility of spontaneous remission, as well as fluctuations in the patient's condition. Sometimes simple bed rest can give significant improvement, primarily of vision.
M. Sereysky. Surgical treatment of acromegaly. The current state of the question regarding the pathogenesis of certain types of acromegaly has logically led to surgical intervention in this disease (especially in the presence of severe symptoms, such as visual impairment, which sometimes depends on the pressure of the expanding tumor on the chiasm or is a consequence of increased intracranial pressure). If acromegaly depends on an adenoma growing in the pituitary gland, then the task of eliminating the cause of the disease, i.e., removing the adenoma, is put forward before the surgical clinic in the matter of treating acromegaly. And indeed, after operative removal of the tumor, an improvement in clinical symptoms occurred, such as: thinning of the skin, reduction of prognathism and extremities (though not to the norm!), refinement of the face, appearance of sexual function, and other symptoms. Surgical successes (Schloffer, Eiselsberg, Cushing, Krause, Hochenegg, Hirsch, Rose, Bogoyavlensky, Fedorov, and others) served as proof of the connection of acromegaly with the pituitary gland, and in view of the histological structure of the pituitary tumor, one had to think about the hypersecretory genesis of acromegaly. Surgery gave an impetus to major experimental-biological studies (Cushing, Aschner, Camus, Roussy, and others), which played an exceptional role in the question of the loss of pituitary function. Despite the favorable results of operative intervention for acromegaly, indications for surgery in acromegaly are established with extreme caution, since at the present time various types of acromegaly are known, and in some of its forms, patients live to a ripe old age. This operation is relatively indicated, in the absence of severe cerebral symptoms and visual impairment, in the case where the patient wishes to somewhat improve their external appearance or restore at least partially sexual function. In these cases, patients must be warned about the possibility of an unsuccessful outcome. Before proceeding to the description of the operation, it is necessary to give a brief outline of the normal and pathological anatomy of both the bed and the pituitary gland itself. The appendage of the brain fills the sella turcica and is enclosed by the leaves of the dura mater. Of these, the lower leaf, which is thinner, lines the entire floor of the sella turcica, and the upper, thicker one closes the sella turcica from the cranial cavity, leaving a small opening through which the infundibulum passes, connecting the pituitary gland with the tuber cinereum. In front of the infundibulum lies the optic chiasm. A pituitary tumor that has caused acromegaly, growing in the cavity of the sella turcica, pushes its walls apart in all directions—both in the direction of the floor of the sella and in the direction of the tegmentum. In the latter case, the tumor must, firstly, press on the optic chiasm located directly here, causing a number of anatomical and functional changes—neuritis optica, choked discs, atrophy of the optic nerves, which is clinically expressed by weakening of vision, hemianopsia, mostly bitemporal, with these phenomena progressing to complete amaurosis. Not infrequently (in 31 cases—28 times, according to Uthoff), phenomena from the eye muscles are noted. Secondly, by pressing towards the base of the brain, the enlarged pituitary gland can cause an increase in intracranial pressure with all the resulting clinical symptoms (headache, vomiting, slowed pulse). These two moments now play a dominant role in the indication for surgery. The sella turcica in acromegaly expands so typically that in many cases one can confidently diagnose acromegaly from a radiograph. In figure 3 it is visible

Figure 3.
normal sella turcica. In Figs. 4 and 5, acromegalic sellae are visible—a volumetric increase of the sella with an undoubted change in its configuration. The floor shows a slightly wavy unevenness, which does not have the character of erosion, but rather resembles pressure atrophy; the tuberculum and dorsum of the sella turcica are pushed apart and thinned, with the tuberculum with the anterior processes being preserved the most. The dorsum, even with a relatively short existence of the disease, undergoes noticeable atrophy, which brings the clivus to sharp thinning (see figure 4), and at the end of this thinning, like a pinhead, sits the posterior clinoid process. This is the most characteristic radiograph. On some radiographs, the head of the posterior clinoid process disappears (see figure 5), but the clivus still remains in the form of a narrow, more or less long strip. The size of the tumor and, in connection with this, the expansion of the sella turcica vary in significant sizes. Incidentally, the intensity of the phenomena of pressure on the brain and chiasm often does not correspond to the size of the pituitary tumor. Operative methods of approach to the pituitary gland are very diverse, and their application is distinguished by great subjectivism. In general, all methods are divided into two groups. The first group consists of
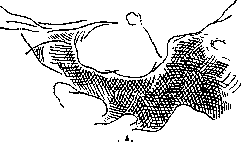
approaches from the side of the cranial vault, the so-called intracranial methods: the temporal route (Horsley), the frontal route (Krause). The second group consists of approaches from the side of the base of the skull—or transsphenoidal methods: the nasal route—with an external incision and folding the nose to the right (Bruns-Schloffer), upwards (Kanavel), downwards according to Ollier (Proust), the endonasal route (Hirsch), the sublabial (Halsted, Cushing); the jaw route: a) the route through the hard palate (König, Lowe); the route with separation of the lower parts of the alveolar processes of the maxillary bones together with the hard palate (Partsch). The route through the pharynx with preliminary pharyngotomy above the hyoid bone (Lowe—1909, Shevkunenko—1918, Biel—1912). Of the indicated intracranial approaches to the pituitary gland, the temporal (Horsley) has been abandoned by almost all authors due to the colossal difficulties caused by the need to displace the entire middle part of the brain upwards and the easy possibility of injuring the sinus cavernosi and the carotid artery located here on the way to the pituitary gland. The second route goes through the frontal region (P. Krause). The operation is performed as follows: a skin-bone flap as voluminous as possible, preferably with a pedicle in the temporal region (Tandler-Ranzi). The skin incision runs along the supraorbital arch, skirts the frontal sinus, rises along the midline of the skull to the bregma, and from there is brought down to the top of the ear. In these dimensions, the skull

Figure 5.
The bone is sawed through, and the skin-periosteal-bony flap is turned aside. After this, Krause recommends making a flap-like incision in the dura mater (this is how Borchardt and Bogoyavlensky operated). The frontal part of the brain is lifted with a broad mirror hook, and in the depth a triangle is discovered, formed in front by the clivus and on the sides by the optic nerves converging toward the chiasm. In this triangle the extrasellar part of the pituitary tumor should lie, which is carefully removed from here with a narrow spoon. Then follows the suture of the dura mater and fixation of the skin-bony flap. Tandler and Ranzi do not make a flap from the dura mater; on the contrary, they follow Krause's earlier proposal and, after forming the osteoplastic flap, do not open the dura mater, but separate it from the floor of the anterior cranial fossa and lift the brain with the dura mater upward. The latter is cut transversely directly in front of the optic foramen, corresponding to the small wing of the sphenoid bone (one must avoid injuring the sinus of the small wing located here). A spatula inserted into the dural incision opens access to the chiasm. The advantage of the frontal approach lies in the aseptic conditions of the operation. But it also has enormous disadvantages. As already stated, operations on the pituitary in A. are indicated only when intracranial symptoms are present, consequently, when the brain is in a state of increased pressure. Under such conditions, upon opening the dura mater, the brain tends to free itself from pressure through the opening formed. This circumstance sometimes makes access to the pituitary impossible (Borchardt, Fedorov). In two cases Rose could not approach the chiasm. The pressure is so great that the brain literally protrudes into the opening, and when attempting to lift the brain with a broad hook there is danger of rupture, crushing of the brain substance (Church's case). The second disadvantage is that however careful the movements of the spoon removing the tumor between the optic nerves may be, the possibility of slight damage to them cannot be excluded. If one takes into consideration that the optic nerves are already in a state of atrophy under the influence of pressure from the tumor, then it becomes understandable that the slightest trauma to the already affected optic nerves will accelerate the development of blindness. The second group of approaches to the pituitary from the base of the skull goes through the sphenoid sinus, which serves as a landmark for access to the floor of the sella turcica. Before proceeding with the operation by the transsphenoidal route, it is necessary to study in detail on X-rays the relationship of the position of the sphenoid sinus to the floor of the sella turcica, otherwise it is difficult to orient oneself during the operation in the location of the sella turcica to be opened. The operation should be performed under X-ray control. One cannot approach the sella turcica without widely opening the sphenoid sinus. Therefore, all paths to the pituitary going from the base of the skull are called transsphenoidal. Of the transsphenoidal methods, the nasal route with temporary turning of the nose to the right (Bruns), upward (Kanavel) and downward (Ollier) has become most widespread. The most common method is Bruns'. The operation is performed by most authors under general anesthesia, but it can also be performed without it, using at the same time conduction anesthesia of the second branch of the trigeminal nerve and local anesthesia of the incision line (1% novocaine with adrenaline - partly to reduce abundant bleeding) and the nasal mucosa (5% cocaine). Before the operation, Bellocque's tamponade of the nasopharyngeal space is applied (see Bellocque's sound). To hold the tampon, it is better to use a flexible wire rather than a thread, since during operative manipulations the thread can be inadvertently cut. Tracheotomy is excluded. The technique of the nasal route has undergone many modifications from the very complex method first proposed by Schloffer to a more or less simplified, generally accepted method at present. When the nose with most of the septum is turned to the right side, the remainder of the nasal septum, the middle and superior conchae are removed (under artificial light); the rostrum is exposed, upon removal of which the anterior wall of the sphenoid sinus is opened. From here the sinus is widely exposed. Here it is necessary to strictly adhere to the midline and, only after carefully checking on the X-ray the relationship of the sinus to the sella turcica and the distance of the floor of the sella turcica from any reference point, for example, from the nasal bridge, can one place the chisel on the floor of the sella turcica and open it with light hammer blows. Often the floor of the sella is thinned, and bony plates of the floor can be easily stripped off with forceps. Sometimes one has to bite off the floor with Luere's forceps. The opening in the floor of the sella should be wide. Now there lies before us the grayish-white capsule of the pituitary. Before opening the capsule, it is anesthetized with 5% cocaine. With a cruciate incision (long, along the strict midline, and short transverse - to avoid possible bleeding) the capsule is opened, and through the opening immediately begins to protrude with pulsating thrusts, following the heartbeats, a soft tumor mass; remnants of the tumor are extracted from the depth with careful movements of a spoon flexible at the end. One must avoid pressure on the tegmentum, as patients then experience very severe headache. A cigarette drain with thin viroform gauze or gauze moistened with Peruvian balsam is inserted into the capsule opening for 6-7 days. The drain is brought out into the left nostril. The nasal cavity is filled for 4-5 days with a separate strip of viroform gauze, brought out into the right nostril. The nose is fixed with sutures, Bellocque's tampon is removed. A light dressing applied to the nostrils is changed 2-3 times a day. The nasal route has the undoubted advantage over the frontal one in that it gives the surgeon more confidence in the possibility of accessing the pituitary tumor and removing it. Is the pituitary adenoma radically removed by the endonasal method? Rose had the opportunity to check three of his cases that ended fatally: in two cases the tumor was removed down to the normal glandular part of the pituitary, in the third case the tumor was removed only to 1/4 of its size. But even if the tumor is not radically removed, the operation achieves a direct reduction of pressure on the chiasm, improvement of vision. Furthermore, the adenoma in A. is always an intrasellar tumor by its genesis and can grow gradually into an extrasellar tumor, pushing the tegmentum of the sella turcica upward. But never yet in A. has a tumor growing exclusively extrasellarly been observed. Therefore there is always more confidence in reaching the tumor from below than from above. The disadvantage of the nasal method can be considered that the operation is performed here through a knowingly infected cavity and, consequently, infection of the meninges may occur. Of Rose's three fatal cases, only in the first did death result from purulent meningitis. The danger of meningitis is probably not so great if the author of the frontal method F. Krause himself calls his method - 'the last resort' ('letztes Hilfsmittel'), when transsphenoidal methods, which are much safer, do not give the desired result. To avoid infection from the nasal cavity, methods proposed by Hirsch and Cushing, based on Killian's method of submucosal removal of the nasal septum, have been suggested. Hirsch makes an incision in the mucous membrane of one nostril along the anterior edge of the quadrangular cartilage, removes the septum according to Killian up to the attachment of the vomer to the anterior wall of the sphenoid sinus, which is also opened submucosally. Cushing performs the operation as Hirsch does, but with a sublabial incision, displacing the spina nasalis anterior. The duration of these submucosal operations, especially according to Hirsch's method, is very long. Hirsch performs the operation with special instruments either in several stages or over several hours. Cushing's method gives somewhat more room than Hirsch's method. The mortality rate for Hirsch's method is 11.5%, for Cushing's method (on 157 operations) 13.7% (according to Zesas) or 9.6% (according to Shevchenko); general nasal methods give about 26% mortality (Eiselsberg); intracranial access (according to Walton) - 30%. The long-term results of operations performed for A. by the frontal method are still little known. The results of operations performed by the nasal method are very good in 75%. According to Rose's material, of 8 patients who survived, about 6 (observation period 5-17 years) can give the most encouraging information: vision did not deteriorate in any of them; in the 7th case it was necessary after 6 years to repeat the operation due to worsening of vision, and in the last 8th patient a recurrence appeared after 27 1/2 years.
Related articles
Mentioned in
Cite this page
“Acromegaly.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/acromegaly/