Otolithic Apparatus
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This 1930s encyclopedia article details the anatomical structure, innervation, and static-kinetic functions of the otolithic apparatus within the inner ear, referencing classical experiments and physiological theories by Breuer, Magnus, and de Kleijn.
Encyclopedia article (1928–1936)
OTOLITHIC APPARATUS, elevations-spots (maculae staticae) on the walls of the sacs (utriculus and sacculus) of the vestibule of the ear labyrinth (see Inner ear and Fig. 1). In humans
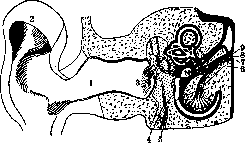
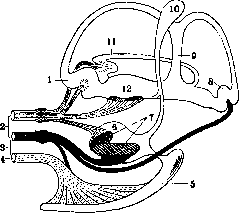
Figure 1. Diagram of the external, middle, and inner ear (cochlea and labyrinth): 1-porus acusticus ext.; 2-cochlea; 3-membrana tympani; 4-tuba Eustachii; 5-m. tensor tympani; 6-aquae-ductus cochleae; 7-n. cochlearis; 8-porus acusticus int.; 9-n. vestibularis; s-sacculus; u-utriculus.
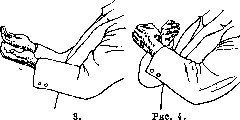
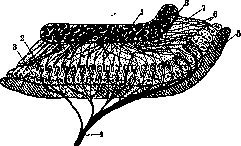
there are two in each ear (otolithic apparatus of the utriculus and sacculus). The otolithic apparatus of the utriculus is also called lapillus (stone), and that of the sacculus-sagitta (arrow). Their structure is identical, but their shape and arrangement in the skull are different (Fig. 2). It is easy to imagine the topographical position of the utriculus and sacculus in the human cranial cavity if one uses a mnemonic rule based on a special position of the hands (Fig. 3 and 4). From these figures, it can be seen that the lapilli (Fig. 3) are located horizontally and in the sagittal plane, while the sagittae (Fig. 4) are located almost vertically and in the frontal plane. These topographical relations are of cardinal importance for elucidating the function and mechanism of examination of the otolithic apparatus (see below). Histological structure of the otolithic apparatus (Fig. 5). In the region of the macula on the membranous wall of the sacculus and utriculus, lined with columnar epithelium, there are supporting cells, hair cells (neuroepithelium connected with the endings of the vestibular nerve), a gelatinous mass, the otolithic membrane, and crystals (otolith). The otolithic membrane, together with the crystals, covers the entire surface of the macula and thus determines its shape. The length of the crystals (aragonite - calcium phosphate-carbonate) in humans reaches from 1 to 11 µ, and the width from 2 to 5 µ. The conglomerate of crystals is held by the otolithic membrane, forming a continuous mass. The innervation of the otolithic apparatus (Fig. 6) is closely related to the innervation not only of the semicircular canals, but partly also of the cochlea. This connection indicates functional interrelationships between the semicircular canals and the otolithic system.
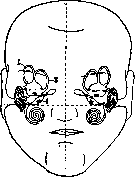
The concept of the function of the otolithic apparatus is based on an analysis of its anatomical and histological structure, its topographical arrangement in the skull, and the results of experiments performed on them. Sewall (1883) was the first to perform otolithotomy in fish and established the disturbance of equilibrium. Thus, a simple opening of the utriculus in rays does not cause functional changes, but after the removal of the otoliths, a tendency to describe circles towards the operated side and to go to the bottom is observed; after bilateral removal of the otoliths, the animal goes to the bottom, sometimes turning somersaults in the vertical plane. The phenomena are even more effectively expressed after damage to the floor of the vestibule with the end of a scalpel. That the above-mentioned phenomena are caused exclusively by damage to the otolithic apparatus and not to the semicircular canals is evident from the fact that isolated damage to the latter is not accompanied in rays Figure 2. Arrangement of otoliths in the skull: 1-canalis ant.; 2-canalis post.; 3-utriculus (lapillus); 4-sacculus (sagitta).
by a disturbance of equilibrium. Similar results were noted in experiments with sharks. The circumstance that animals naturally devoid of the ability to move freely have no otoliths leads to the attribution of a static-kinetic function to the otoliths. A coherent theory of the static function of the otolithic apparatus was first published by Breuer (1891); with minor adjustments introduced by the Utrecht school (Magnus, de Kleijn, Quix), it remains to this day the only one that has received general recognition.
Figure 5. Diagram of the otolithic organ: 1-otolithic crystals; 2-ciliated cells; 3-supporting cells; 4-vestibular nerve; 5-membranous wall; 6-threads; 7-gelatinous mass; 8-otolithic membrane.
According to Breuer, otoliths are organs serving for the perception of straight-line movement and head positions in space during rest and movement. Breuer was led to this concept by the following train of thought: otoliths, floating in a fluid that is specifically lighter, tend to constantly sink, thereby maintaining a continuous stimulus in the terminal nerve apparatus, which is transmitted to the brain. Pressing on the hair cells by inertia during rectilinear movement, or shifting due to the development of centrifugal
Figure 6. Innervation of the labyrinth and cochlea: 1-ampulla ant.; 2-n. vestibularis; 3-anastomosis; 4-n. cochlearis; 5-ductus cochlearis; 6-sacculus; 7-macula sacculi; 8-ampulla post.; 9-crus communis; 10-sacculus endolymphaticus; 11-ampulla horizontalis; 12-macula utriculi.
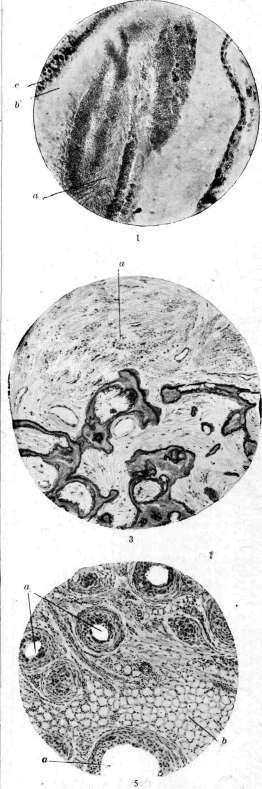
force during rotational movements, or pressing on the hair cells by their own weight at rest, otoliths cause us to feel movement and the sensation of a resting head position, and by downward pressure make it possible to determine the vertical direction. Breuer's assumption about the movement of otoliths was confirmed by Kubo's experiments (1906-1908) by placing fish in various positions, such as head up, down, belly down, and up. The same author established the deviation of the eyes upon damage to the otoliths. The disturbance of the sensation of the ver
tical gland.
tical during rotation, caused in Breuer's opinion by the displacement of otoliths, was established in humans by Kreidl (1893). A more in-depth study of animals after destruction or damage to the otolithic apparatus established (Fröhlich, 1904) hypotonia, increased reflexes, weakened respiration, and the disappearance of compensatory wheel-like eye movements (see below). These disturbances largely constitute the elements that make up the complex phenomenon of static disturbance. The mechanism of action of these individual elements and the manifestation of the latter in the form of reflexes in mammals were studied by Magnus and de Kleijn on decerebrate animals (see Decerebration, decerebration rigidity). In such a decerebrate animal, a state of 'rigidity' is noted, manifested in the tonic contraction of those muscles whose function is to + 90o + 135 -
G. Zimmerman
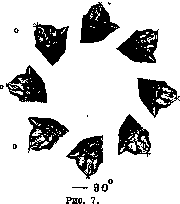
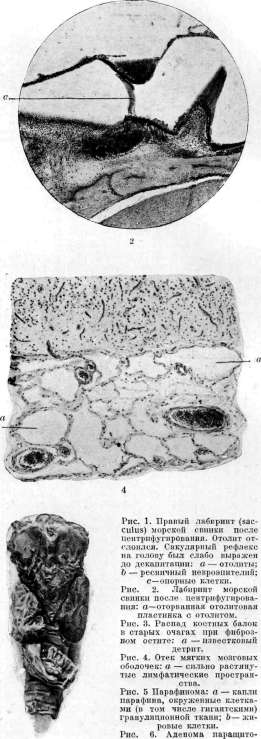
o - to counteract gravity (extensors of the limbs, those lifting the neck, extensors of the trunk, those lifting the tail in animals, and the adductors of the lower jaw). In this case, it turns out that the tone of the extensors is influenced by various positions of the animal's head. However, not only the position of the head in space is of importance, but also the position of the head relative to the trunk. Therefore, it is necessary to make a distinction between otolith (labyrinthine) and neck reflexes (see Magnus-De Kleijn reflexes). Having induced decerebrate rigidity in a rabbit or cat and then setting the head crown-up (180°) and rotating the animal around the bitemporal axis along the circle line, it can be established that the limbs assume maximal extensor tone when the head is positioned between 0° and +45° [the otoliths of the utriculus (lapilli) hang down], and minimal between 180° and 135° (in this case, the otoliths of the utriculus press on the underlying macula statica) (Fig. 7). This observation gave Magnus and De Kleijn reason to recognize that the irritating factor in the mechanism of excitation of the otolithic apparatus under physiological conditions is not pressure, as Breuer once assumed and Quix currently asserts (see below), but hanging down. Quix, proceeding from the above-described histological structure and topographical arrangement of the otolithic apparatus, conceives the function of the otolithic apparatus as follows: if the otoliths approach the macula, i.e., exert pressure on the gelatinous mass, this pressure is transmitted to the hairs of the neuroepithelium (see histological structure); they are irritated, the process is transmitted to the sensory cells and connected nerve fibers of the vestibular nerve and goes further into the centers of the brain stem. If, however, the otoliths move away from the macula, i.e., hang down, they do not cause physiological irritation. Physiological excitation is caused only by such a displacement of the otoliths in which a change in pressure occurs. The above-described Magnus-De Kleijn reflex, caused by a certain position of the head, was named by Magnus the positional reflex (Lagerreflex). That it is actually caused by the otolithic apparatus of the utriculus is indicated by the fact that upon centrifugation of the animal, during which the utricular otolith is torn off (see separate table, figure 2), the indicated reflex on the limbs disappears. All positional reflexes originate from the otolithic apparatus and affect not only the limbs, but also the eyes and the neck. The peculiarity of otolith reflexes is that they are tonic, i.e., they last as long as this or that position of the labyrinth lasts, whereas reflexes caused by the semicircular canals are short-lived, rapidly passing. That tonic reflexes on the neck are also caused by the utriculus follows from the analysis of phenomena in rabbits after unilateral removal of the labyrinth; after this, a turn of the head towards the damaged labyrinth is observed. This turn is caused by the fact that the muscles turning the neck towards the preserved labyrinth are deprived of their usual tone (due to the loss of labyrinth function), while the neck muscles of the other side, having retained normal tone and being deprived of antagonists, contract maximally. Consequently, each utriculus is functionally connected with the neck muscles of the opposite side. Tonic labyrinthine reflexes (predominantly on the forelimbs), as well as their dependence on the pressure and hanging of the otoliths, are clearly visible in the following experiment (Fig. 8). When bending the head forward
Figure 8.
by 30°, the otoliths produce maximum pressure, resulting in the flexion predominantly of the forelimbs, whereas when the head is lifted and thrown back by 45°, the otoliths hang down and result in extension of the limbs. A similar phenomenon is noted in the so-called elevator reaction, which consists in the fact that when the elevator descends, due to the lagging of the otoliths, the animal rises (extension of the limbs), and when ascending, the otoliths press and the animal lowers (flexion of the limbs). In humans, this reaction is manifested by the sensation of a downward movement after the stop of an elevator moving from bottom to top, and the sensation of an upward movement after the descent of the elevator. At the heart of this phenomenon lies predominantly the mechanism of pressure and lagging of the otoliths. Deaf-mutes, deprived of functioning otolithic apparatuses, do not experience these sensations. However, the participation of the mechanism of endolymph flow in the semicircular canals in this reaction is not excluded, which should be assumed from the corresponding experiment (on models of semicircular canals) of Magnus and De Kleijn. Thus, the semicircular canals and the otolithic apparatus react to angular and translational acceleration, but the degree of participation of these organs under corresponding irritations is such that the semicircular canals are more sensitive to angular acceleration, and the otolithic apparatus to translational. From the analysis of elevator reactions, it follows that under physiological conditions, the irritating factor is pressure and hanging down. However, in animals and humans, when the head is in a position normal for them (for example, vertical for humans), the otoliths are located so that they press on the underlying macula. Since in this position animals and humans retain the correct sensation of the position of the head in space, it is natural to consider this mechanism of irritation as specific, and not the one (hanging down) that acts in unusual positions of the head. This argumentation disputes (Quix) the theory of Magnus and De Kleijn (see above). Utricular tonic reflexes on the neck in humans are observed only in pathological cases, while on the limbs in a healthy person, according
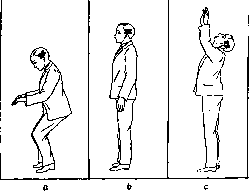
Figure 9. Utricular reflexes on the limbs and eyes: a - tilting the head forward causes maximum pressure of the lapilli on the macula, and as a result, flexors are brought into action on the limbs and trunk, and the superior rectus muscle in the eyes; b - normal position of the utriculus with a vertical head position; c - tilting the head back causes maximum hanging of the lapilli on the macula, and as a result, extensors are brought into action on the limbs and trunk, and the inferior rectus muscle in the eyes.
to Quix, can be reproduced (as seen from Fig. 9) if a change in the position of the utricular otoliths (lapilli) is induced. The indicated change occurs as the head begins to move from the median position in the sagittal plane (see above - topographical arrangement of lapilli), i.e., forward and backward. The change in the position of the saccular otoliths (sagittae) occurs as the head begins to move from the median position in the frontal plane (see above - topographical arrangement of sagittae), i.e., when tilting to the side. Only then does the function of the sagittae manifest itself. Saccular reflexes in man, according to Quix, are presented in Fig. 10. In animals, tonic reflexes, named by Magnus righting or postural reflexes (Stellreflexe), are easily elicited from the otoliths of the sacculus. The purpose of these reflexes is to return the animal to a normal position after it has been removed from it. This category of reflexes includes reflexes to the head and
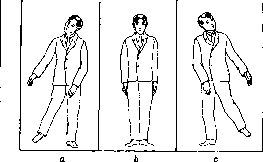
Figure 10. Saccular reflexes on the limbs and eyes: a - right sacculus upon tilting the head to the left shoulder (maximum pressure) causes abduction of the right limbs, adduction of the left, and counter-rolling of the eyes to the right; b - normal position of the sacculus with a vertical head position; c - left sacculus upon tilting the head to the right shoulder causes abduction of the left limbs, adduction of the right, and counter-rolling of the eyes to the left.
eyes; their examination in animals is performed as follows: if one holds an animal by the pelvis with the head up, then regardless of which lateral position the animal is in, its head will always assume a vertical position. In the lateral position, the sacculus is stimulated, contributing to the rotation of the head into the normal position (in this position, one sacculus, lying below, hangs down, while the other, lying above, presses on the neuroepithelium). Damage to the indicated otoliths causes the disappearance of the reflex to the head (see separate table, Fig. 1). It has been established that each position of the head in space corresponds to a definite state of contraction of the eye muscles, i.e., a definite position of the eyes, and the position of the eyes remains constant as long as the head retains its position. The biological meaning of the indicated reflex consists in compensating by the rotation of the eyes for the deviation of the field of vision caused by the rotation of the head, which is why the indicated deviation of the eyes is called compensatory. Since the deviation of the eyes is always directed in the direction opposite to the deviation of the head, the entire phenomenon is called compensatory counter-rolling of the eyes. Compensatory deviation of the eyes is easily observed in humans and animals; it manifests particularly easily in animals with a lateral arrangement of the eyes (rabbit, guinea pig). Wheel-like and vertical counter-rolling are distinguished 24f» The first is observed during the rotation of the head around the bitemporal axis in the sagittal plane and is caused by the stimulation of the otoliths of the utriculus, bringing into action the superior oblique and inferior oblique muscles (Fig. 11). The second is discovered during the rotation of the head around the body length in the frontal plane and is caused by the stimulation of the otoliths of the sacculus, bringing into action the superior rectus and inferior rectus muscles (Fig. 12). By the method of decerebration, it has been established that the centers of the indicated reflex arcs are located in the brainstem, starting from the upper cervical segments up to the anterior part of the corpora quadrigemina. Within this region, there are centers located in three


Figure 12. Vertical deviation of the eyes when lying on the side.
Figure 11. Wheel-like counter-rolling of the eyes in a rabbit during rotation around the bitemporal axis. groups: 1) for otolithic reflexes on the limbs and neck - in the region posterior to the site of entry of the trunk of the vestibular nerve; 2) for the otolithic reflex on the eyes - between the region of entry of the acoustic nerve and the nuclei of the oculomotor nerves; 3) centers for righting reflexes on the head - in the region of the midbrain. The physiological significance of the latter consists in obtaining an idea of the true position of the head in space; of the centers of reflexes on the eyes - in maintaining the optical space; of the centers of reflexes on the muscles - in maintaining equilibrium. In the light of the indicated experiments, it is easy to understand a whole series of facts. Thus, for example, the estimation of the degree of inclination of the head in relation to the vertical line becomes less accurate as the head deviates more and more backward. An inclination of 75° is accepted as a horizontal position, i.e., as 90°. In this case, an increased stimulation of the otoliths of the utriculus occurs. By a similar mechanism of stimulation or damage to the otolithic apparatus, the disturbance of the perception of the vertical by pilots during flights is explained, as well as the appearance of a whole series of reflexes that together constitute the symptom complex of aviators' disease. It is known that when the head is in a certain point (for example, during the movement of the head along the bitemporal axis), the sense of orientation in relation to space will be completely absent, and the otoliths in relation to the maculae in this case are in a state of hanging down; this point in space is called the blind spot of the static organ (Quix). Opposite this blind spot in space, there is a region in which position of the head the otoliths produce pressure and orientation in space is preserved - the yellow spot of the static organ. Impaired excitability of the otolithic apparatus in the sense of an increase or decrease causes a deceptive sensation of the relationship between the personality and the surrounding space, and as a result - dizziness, accompanied sometimes by pallor of the face, vomiting, nausea, sweating as a consequence of the reflex stimulation of the vagus and sympathetic nerve systems. The mechanism of the appearance of the indicated (otolithic) dizziness is analogous to the mechanism of the vestibular syndrome observed in seasickness. The dependence of the appearance of the indicated disease on abnormal stimulations of the otolithic apparatus is established by the analysis of the movement of the vessel during pitching (pitching - movement of the vessel from top to bottom and bottom to top - the action of the utriculus otoliths; rolling - the action of the sacculus otoliths), as well as by the fact that deaf-mutes, deprived of functioning labyrinths, do not suffer from seasickness. On the indicated data obtained experimentally in animals and noted by observations, the clinic of diseases of the otolithic apparatus is based mainly. However, the indicated data obtained in animals cannot be unconditionally transferred to humans. Thus, in all cases of isolated disease of the otolithic apparatus in humans described in the literature, it is not the compensatory movement of the eyes caused at a certain position of the head that is indicated, but nystagmus, i.e., that which we usually consider caused from the semicircular canals, and only the circumstance that this reaction is tonic, prolonged, forces us to consider it otolithic. This is explained by the fact that in lesions of the otolithic apparatus in humans, it is necessary to admit the appearance of not only com
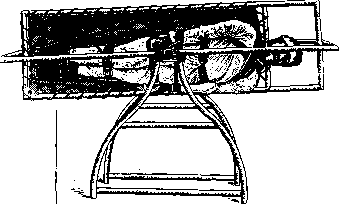
Fig. 1. Positional nystagmus and dizziness at a certain position on the Barany vestibular table.
pensatory eye movements, but also nystagmus, for which there are prerequisites in the innervation of the labyrinth (see above) that indicate a functional interaction between the semicircular canals and the otolithic apparatus. The nature of the indicated interaction has not been finally elucidated. It is assumed that unusual stimulations of the otolithic apparatus are sometimes reflexly transmitted to the semicircular canals, as a result of which the so-called "otolithic nystagmus" is obtained (Khilov). Symptoms of a disease of the otolithic apparatus: 1) dizziness at a certain position of the head (Schwindellage) with or without the appearance of nystagmus (Lagenystagmus); 2) past-pointing with direct and lateral positions of the head; 3) disturbance of counter-rolling of the eyes. Research methodology. 1. Upon establishing from the anamnesis complaints of dizziness, the patient is laid down in turn on all four sides (on the back, on the abdomen, on the right and le- \.

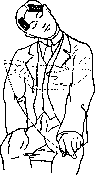
Figure 14. Figure 15.
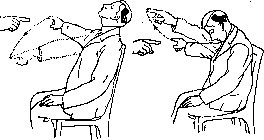
Figure 16. Figure 17. right side) and when lying down in each of the indicated positions, they wait 10-15 seconds, during which the patient is examined for spontaneous nystagmus, asking them to look straight, to the sides, up and down (rotatory nystagmus is more often noted), while at the same time the patient is asked whether they experience dizziness (Figure 13). 2. The pathology of otolithic reflexes in the limbs in lesions of the otolithic apparatus is manifested in the form of past-pointing during the pointing test. - The pointing test experiment: the patient sits opposite the seated physician. The physician asks them to extend their arm at the shoulder joint in the medial direction and, with eyes closed, make vertical movements with the index finger from their knee until meeting the extended index finger of the physician. Then this experiment is repeated while the subject tilts their head to the right and left shoulder (Figs. 14 and 15). Next, a similar experiment is performed, but the finger moves in a horizontal plane from the outside and inwards both with a straight head position and with the head tilted forward and backward (Figs. 16 and 17). A normal person with closed eyes always hits the investigator's finger. By tilting the head forward, maximum pressure of the otoliths (lapilli) of the utriculus is achieved, causing flexion of the arms, and by throwing it back - maximum sagging, causing extension (i.e. arm movements must occur in the sagittal plane). The impairment of lapilli function during their lesion is manifested during the pointing test performed in the horizontal direction with the noted head position by the fact that the test subject's finger will miss in the vertical direction and in the sagittal plane (the plane of the lapilli location), i.e., up or down. From the analysis of clinical material (Quix), it follows that tilting the head to the shoulder causes irritation of the sacculus otolith (sagitta) of the opposite side, causing abduction of the limb on the side of the irritated otolith and adduction of the opposite one (i.e., arm movements must occur in the frontal plane). The impairment of sagittae function during their lesion is manifested during the pointing test performed in the vertical direction at lateral head positions by the fact that the test subject's finger will miss in the horizontal direction and in the frontal plane (the plane of the sagittae location), i.e., outward and inward (Figs. 14 and 15). The diagnostic significance of this test is significantly inferior to a more objective method - the study of ocular counterrolling. 3) The study of ocular counterrolling is performed using a special apparatus (Figs. 18 and 19) in the following manner. The telescope (1) is positioned on the iris, magnifying it 6 times. The measurement of eye movement is carried out by the displacement of the iris when the head is tilted. For this purpose, it is necessary that the pupil of the subject be at rest, which is achieved by instilling into the corresponding
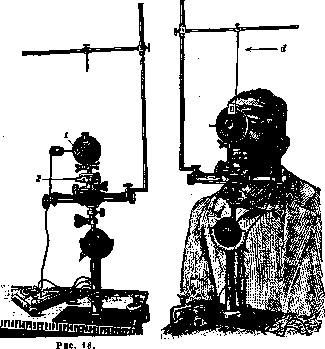
Fig. 19
eye 20 minutes before the study two drops of a 1% pilocarpine solution. As a result, the pupil narrows as much as possible, does not react to light, and the pattern of the iris appears more distinctly. A more clearly expressed stripe is chosen on the iris, serving as a landmark for measurement. A movable thread is arranged in the telescope, which is set parallel to the indicated landmark stripe on the iris, and its position is marked on a board with divisions connected with the eyepiece thread. To set the telescope on the iris, it is necessary to fix the head and eye of the patient in relation to the telescope, which is achieved by fixing with the teeth a small board with a stent (2) attached to the rod on which the telescope rests. The authors listed below (according to Kompaneyets) obtained different angles of counterrolling in normal people at different head tilts. Authors Head tilt 30° 35° 45° 60° Houben u. Struycken . 6° 2°-5° 10° 8° In pathological cases with reduced function, significantly smaller figures are obtained. This is especially evident in the difference between head tilts in both directions, for example, in disease of the left otolithic apparatus (sacculus) in the sense of a decrease in function when the head is tilted to the right, counterrolling to the left is equal to 10°, when the head is tilted to the left, counterrolling to the right is equal to 2°. This research method is exceptionally valuable in cases with symptoms of dizziness with a normal reaction from the semicircular canals. To determine the degree of excitability of the vestibular system in general and the otolithic one in particular, as applied for the professional selection of pilots (a method of little use for the clinic of otolithic system disease), the following research method is used (Voyacek-Khilov, Fig. 20): the subject sits in a Bárány chair, closes their eyes, bends their head and torso down, approximately at an angle of 90°. In such a position, the subject is first rotated to the right at a speed of one revolution in 2 seconds for 10 seconds, i.e., 5 revolutions are made; then the chair is stopped and, without changing the position of the subject, they wait for 5 seconds, after which the subject is asked to straighten up. At the moment of change of position, a reaction occurs, expressed in the inclination of the body and head to the side, of one degree or another (weak, moderate, or strong). A few minutes later, the experiment is repeated, rotating the subject in the opposite direction. The past-pointing and falling reaction is conditionally divided by strength into 3 degrees: from 0° to 10° the reaction is considered weak, from 10° to 20° - moderate, and from 20° to 45° and more - strong. Etiology. The causes of diseases of the otolithic apparatus appear to be quite diverse: acute, chronic inflammatory and non-inflammatory diseases of the middle and internal ear, infectious, traumatic, and toxic neuritis of the otolithic nerves, as well as vascular, infectious, tumor-like diseases of the brain in the area of the otolithic pathways (medulla oblongata and pons). - Treatment should be conducted in two directions: 1) depending on the elucidated etiology, therefore causal, and 2) symptomatic, i.e., along the line of action on the vagosympathetic component of the vestibular syndrome. At the time of the seizure: subcutaneously atropine (Sol. Atropini sulfurici 1:1,000.0 pro dosi 1.0) (in the absence of a therapeutic effect, subcutaneously Sol. adrenalini 1:1,000 from 0.3 to 0.5 every two days one injection), a hot water bottle
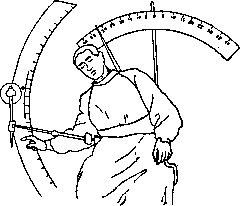
Figure 20.
to the feet, cold compresses (ice) to the head, large doses of bromine internally (Sol. Natr. bromati 12.0:200.0 - 1 tablespoon three times a day). As the intensity of the seizures decreases, the dose of bromine is reduced to 1.0 per day, and in the post-seizure period for 5-6 days, bromine therapy is continued in combination with 35° bath treatments every other day.
Related articles
Cite this page
“Otolithic Apparatus.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/otolith-apparatus/