Nystagmus
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
An extensive overview of nystagmus from the 1930s Great Medical Encyclopedia, detailing its classifications, physiological mechanisms, and historical experiments on the vestibular system.
Encyclopedia article (1928–1936)
NYSTAGMUS, nystagmus (from Greek nystagmos - nodding), a rapidly repeating movement of the eyeballs (eye tremor); it occurs both spontaneously and artificially (experimentally induced). According to the number of tremors per second, 3 degrees of nystagmus are distinguished - very fast, moderately fast, and slow. According to the amplitude of movements, nystagmus is distinguished as fine-, medium-, and coarse-amplitude. According to the type of movements - pendular (undulating) and jerk, wherein in pendular nystagmus the eye movements, originating from a single point, occur in both directions at the same speed, while in jerk nystagmus the eye movements in one direction occur slowly and in the other quickly. Nystagmus can be binocular, more rarely monocular (in one eye); if the direction of nystagmus in both eyes is the same, it is called conjugate (associated) nystagmus, and if different - dissociated (observed rarely). Associated nystagmus can be: horizontal, rotatory, horizontal-rotatory, vertical, diagonal, wheel-like, and elliptical. Spontaneous nystagmus is usually a pathological phenomenon. Nystagmus, being predominantly a reflex to irritation, bears the name of the organ by whose irritation it is caused. Thus, nystagmus caused by irritation of the semicircular canals is called labyrinthine, that caused by irritation of the vestibular nerve outside the labyrinth - vestibular, by irritation of the optical apparatus - optical; the latter manifests in the form of optokinetic or fixation nystagmus (see below). Finally, positional nystagmus is distinguished, which is a consequence of a disturbance in the respective cortical centers that keep the eyes in complete rest during any deviation. The mechanism of nystagmus was first elucidated on the basis of studying experimentally induced nystagmus. For the first time, experimental labyrinthine nystagmus was induced by Flourens (Flourens, 1828). After sectioning the lower vertical semicircular canal of a pigeon, Flourens noticed that the eyeball and eyelids produced continuous, sharp movements. In subsequent years (1870-80), a number of authors (Hogyes, Breuer, Bornhardt) induced labyrinthine nystagmus in animals, using heat, cold, rotation, and electric current as stimuli. In 1892 Ewald, experimenting on pigeons, used pressure and rarefaction as stimuli. Having exposed the right membranous horizontal canal in the pigeon over a small space, Ewald then
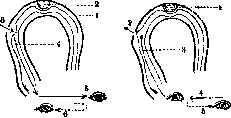
Figure 1.
Figure 2.
Figures 1 and 2. Ewald's experiment. Figure 1: 1 - bony wall of the right horizontal semicircular canal; 2 - seal between the bony wall and the membranous wall of the membranous semicircular canal; 3 - direction of pressure by the piston; 4 - direction of the displaced endolymph to the left; 5 - slow component to the left, in the direction of endolymph movement (away from the ampulla); 6 - direction of the fast component to the right (toward the ampulla). Figure 2: 1 - seal; 2 - direction of the suction action of the piston; 3 - direction of endolymph flow to the right; 4 - slow component to the right - toward the ampulla; 5 - direction of the fast component to the left - away from the ampulla. this canal was tightly closed. Pressing with a special piston on the parts of the canal lying between the seal and the ampulla, he thereby caused a flow of endolymph toward the ampulla (Figure 1). As a result of the pressure increase, a regular horizontal movement of the head and eyes occurred in the direction of the endolymph movement (away from the ampulla), in this case to the left; immediately following this deviation, the head and eyes returned by a fast movement to their original position, i.e., in this case to the right (toward the ampulla). When pulling out the piston, suction occurs and as a result a reverse flow of endolymph, causing weaker movements of the eyes and head than during pressing (Fig. 2), directed once again in the direction of the endolymph movement, i.e., in this case to the right; as in the first case, following this deviation the eyes and head returned by a fast movement to the initial position, i.e., to the left (away from the ampulla). The first eye movement caused by the endolymph flow is called the slow component, the second - the fast component of nystagmus. A similar phenomenon can be reproduced in a patient with a fistula of the semicircular canals (see Labyrinthitis); if the bony wall of, for example, the right horizontal canal at some point is destroyed by caries, then mechanical pressure on this fistula and even an increase in pressure in the right external auditory meatus by pressing a finger on the tragus usually causes a brisk ("pressor") nystagmus toward the labyrinth affected by the fistula, i.e., to the right, while a pressure decrease by suction causes nystagmus toward the healthy side, i.e., to the left. Since it is easier to observe the fast component, the direction of nystagmus is designated by the direction of the latter, i.e., if the fast component is directed to the right, it is customary to designate that nystagmus is present to the right. It is sufficient to remember Ewald's law so that in each individual case of labyrinth irritation caused by endolymph flow (during rotation, cooling, heating) one can predict in which direction the nystagmus will be directed. This law states: an endolymph flow directed toward the ampullary end causes nystagmus in the direction of this same ampulla, whereas an endolymph flow directed away from the ampulla, i.e., toward the smooth end, causes nystagmus in the direction of the unirritated labyrinth. By analogous experiments on the anterior and posterior vertical canals, it was established that the aforementioned Ewald's law has the opposite effect in relation to these canals, namely: an endolymph flow toward the ampulla causes nystagmus in the opposite direction, with nystagmus always occurring in the plane of the stimulated canal. Thus, upon irritation of the horizontal semicircular canals, horizontal nystagmus is obtained, of the frontal ones - rotatory, of the sagittal ones - vertical, and sometimes diagonal (Fig. 3). To explain these phenomena, it is most probable to assume that in each of these cases different nerve endings in the ampulla are irritated, transmitting impulses along fibers connected to different nerve centers of the extraocular motor nerves. Thermal action on the labyrinth (temperature below and above the animal's body temperature) results in the appearance of a similar endolymph flow, and depending on the direction of the endolymph flow toward the ampulla or away from the ampulla, nystagmus is obtained in the corresponding direction according to the regularity stemming from the above-mentioned Ewald's experiment. Barany first systematically produced thermal (caloric) irritation of the labyrinth in humans and introduced it into
Figure 3. Graphical designa- T
vertical upwards; 4 - verti- _/ N
cal downwards; 5 - rotatory S %
nii to the left; 8 - rotatory-hori- E -----,
zontal to the right with predomi- V \ - 4
nant component; 9 - wheel-like ni -----_z _-----,
etagmus; 11 - elliptical ni- O
stagmus horizontal to the left; II
12 - elliptical nystagmus f .„
diagonal to the right. the methodology of otoneurological examination. It is based on Ewald's law, as well as on the physical law of the change in specific gravity of liquids at different temperatures. Thus, for example, if 20 cm3 of water at a temperature of 27° is poured into the right ear of a person in a vertical position of the head and one imagines the places of the labyrinth that have undergone cooling (Fig. 4), it can be seen that the anterior vertical and horizontal canals fall into the region of the water jet. Due to the cooling of the walls, the adjacent lymph will also cool and as a result move downward, i.e., in the anterior vertical semicircular canal toward the ampulla, and in the horizontal one - away from the ampulla. According to Ewald's law, the lymph flow away from the ampulla in the horizontal semicircular canals causes nystagmus in the direction opposite to the endolymph flow, i.e., in this example nystagmus will result to the left and horizontal, since the horizontal semicircular canal was irritated. In the vertical semicircular canal, however, the lymph flow will be directed toward the ampulla, but Ewald's law
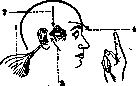
Figure 4. Scheme of caloric nystagmus and technique of its observation: 1 - infusion of 20 cm.3 of water (27.5°) with a syringe into the external auditory meatus along the posterior-superior wall; 2 - direction
of the endolymph flow in the right v relation to the ver-tical semicircular canals states that nystagmus is directed in such cases in the opposite direction, i.e., to the left. Thus, caloric stimulation of the right ear with cold water should produce horizontal and frontal nystagmus to the left, which is indeed what is obtained, but the frontal one, appearing together with the horizontal, together produce horizontal-rotatory nystagmus. However, this view is not universally recognized: phenomena in a living organism are subordinated not to physical, but to more complex physiological regularities, in particular, in this case, vascular phenomena play the main role; during caloric stimulation of the ear with cold wa
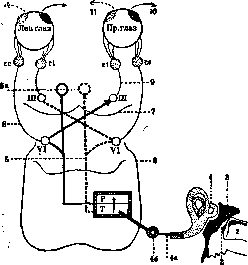
Fig. 5. Scheme of the central mechanism of labyrinthine horizontal nystagmus (nystagmus caused by cold water): 1-direction of the cold water jet; 2-tympanic membrane; 3-tympanic cavity; 4-horizontal semicircular canal; 4a-labyrinthine nerve; 4b-gangl. Scarpae; 5-vestibular fibers composing the posterior longitudinal fasciculus; 5a-nuclei of the posterior longitudinal fasciculus; 6-floor of the fourth ventricle; 7-posterior colliculus; 8-n. abducens (VI-its nucleus); 9-n. oculomotorius (III-its nucleus); 10-direction of the slow component; 11-direction of the fast component; P and T-centers of the fast and slow components (vestibular nuclei of the medulla oblongata and pons); re-m. rectus externus; ri-m. rectus int.
in the part directly adjacent to the irrigated region, superficial ischemia occurs, while in the deep vessels of the labyrinth there is collateral hyperemia; due to the dilation of vessels, an outflow of endolymph occurs, and the intralabyrinthine pressure drops, which serves as the source of nystagmus. In other words, temperature acts on the endolabyrinthine environment through the mediation of vasomotor nerves. According to recent research, the mechanism of the onset of labyrinthine nystagmus appears as follows. Under the influence of the endolymph flow, freely oscillating hairs of the neuroepithelium (cupula; see Inner ear) are set in motion, which causes irritation of the peripheral ending of the vestibular nerve. Under the influence of the endolymph flow, the impulse is transmitted along the nerve to its nuclei (see Vestibularis nervus and Fig. 4). Two centers are located in the nuclei, of which one causes the slow component and the other the fast component. From these centers, the impulse travels along fibers located homo- and contralaterally as part of the posterior longitudinal fasciculus to the oculomotor nuclei; from the latter, the impulse is transmitted to the oculomotor muscles, the contraction of which causes the corresponding eye movements. The slow component is elicited first, and then from the center of the latter, the impulse is transmitted to the center of the fast component. The impulses, alternating now in one and now in the other center, alternately cause either the fast or the slow component (Fig. 5). Mechanism of origin of vestibular nystagmus. For rotatory, horizontal, and vertical movements; 2-area of vertical nystagmus; 3-area of horizontal nystagmus; 4-area of rotatory nystagmus; 5-coch
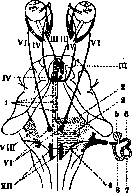
may also be caused by the irritation of individual areas in the region of the vestibular nerve pathways
in the brainstem up to globus pallidus. Horizontal nystagmus is caused predominantly from the area between the caudal beginning of Deiters' nuclei, approximately up to the genu of the facial nerve, rotatory nystagmus predominantly from the most caudal parts of this area, and vertical nystagmus from the anterior parts. These relationships, established in the rabbit, are also observed in man (Fig. 6). Experiments with subcutaneous injections of poisons have shown that disorders of labyrinthine function (disturbance of statics, nystagmus, vertigo) are caused by the selective lesion of the just indicated areas (statokinetic centers in the region of the medulla oblongata, pons, and midbrain). The vestibular symptom complex observed in botulism is also caused by lesions of the designated sites in the brainstem; thus, labyrinthine-vestibular nystagmus is a reflex consisting of an afferent segment (membranous labyrinth, vestibular nerve) and an efferent segment (three pairs of oculomotor nerves with muscles), as well as central connections extending from the nuclei of the vestibular nerve to the superior colliculus (nuclei of the vestibular, abducens, trochlear, and oculomotor nerves) (see Vestibularis nervus). Labyrinthine-vestibular nystagmus possesses a definite biological significance. If the eyes remained at rest during a head rotation, the image would shift from the corresponding point of the retina, but head movement causes a simultaneous flow of endolymph and, consequently, a corresponding displacement of the eyes. Optokinetic nystagmus. To clarify the essence of the optokinetic reflex, the following must be noted. The eye has 3 accommodation devices: 1) accommodation to distance (functions of the lens and convergence of visual axes), 2) accommodation to light intensity (function of the iris), and 3) accommodation to the movement of a fixed object (optokinetic nystagmus). The latter occurs as follows: let us imagine that the eye has been fixing a certain number of moving objects to the left and follows them, turning in the direction of their movement, i.e., to the left. A moment will come when it is necessary to transfer fixation to the next point of the object approaching from the right, i.e., to turn the eyes to the right. This movement must be fast, otherwise some points will manage to escape fixation. The first turn of the eye (to the left) corresponds to the slow component of nystagmus, and the second (to the right) to the fast component. By repeating these movements, the eye gains the ability to examine the largest possible number of flashing objects (a similar phenomenon occurs when viewing objects from the window of a moving train, which is why the designated nystagmus was first called railway nystagmus). This constitutes the biological meaning of the optokinetic reflex. Experimentally, optokinetic nystagmus is elicited in the following manner (Fig. 7). A rotating cylinder covered with colored stripes is placed in front of the subject at a distance of 50 cm. When the cylinder rotates to the right, the test person fixes one of the stripes, and the appearance of horizontal nystagmus in the direction opposite to the cylinder rotation is immediately noted; when rotating upward, downward nystagmus occurs; when rotating downward, upward nystagmus occurs. Since optokinetic nystagmus cannot be elicited without fixation, this nystagmus is essentially fixational. Most likely, the afferent part of this reflex arc, beginning in the retina, ends in the occipital lobe; its center is the region from the occipital lobe to the anterior central gyrus, from where the efferent pathway to the nuclei of the oculomotor nerves begins. If there is a lesion (irritation, destruction) in one of the sections of the designated reflex arc, spontaneous optokinetic nystagmus or, respectively, the loss of experimental optokinetic nystagmus may occur. In addition, it should be borne in mind that the rest of the eye, which we objectively observe, is only apparent. In reality, even normally, the eyes make a whole series of nystagmus-like movements that are macroscopically unnoticeable. Various adverse conditions affecting the tone of the eye muscles (decreased visual acuity, lack of light) can reduce the frequency of nystagmus and increase its amplitude, thus turning a latent nystagmus into manifest or kinetic. Setting nystagmus. According to some authors, 70% of healthy people exhibit nystagmus at a 50° deviation and even more frequently at extreme abduction of the eyes. In most cases, this nystagmus is horizontal, fine- or medium-amplitude
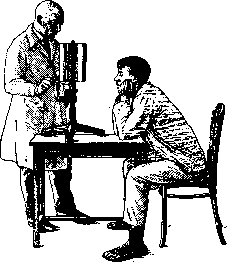
Fig. 7. Apparatus and its setup for the study of optokinetic nystagmus.
steady and significantly less often jerky. It is caused partly by weakening of the tone of the eye muscles, and partly by weakening of the cortical postural centers. The methods of investigating N. consist of nystagmoscopy (observation of N. by ordinary external examination of the eyes) and nystagmography (recording of N. by a writing instrument), which is a more perfect method of investigation. The presence or absence of N. is determined depending on at what angle of eye deviation it appears. Often it can be noticed already with direct gaze, but more often only after deviation of the eyes to the sides. For observation, a certain point on the surface of the eyeball should be chosen, e.g., a vessel of the conjunctiva or a sharply defined place on the iris. Vestibular N. is especially sharply revealed if the subject wears biconvex glasses (+20D) - Bartels glasses. This achieves almost complete elimination of fixation, which acts as a brake on the course of labyrinthine N. Nystagmography more accurately establishes the characteristics of N. In the basis of some nystagmographs is the principle of transmitting the movement of the eyeball through the eyelid by means of a lever system (fig. 8), in others--through the eyelid by means of compressed air (fig. 9) (Pneumonystagmograph), in thirds--through reflected light: a small mirror is placed on the eyelid of the closed \ eye, onto which a beam of light from an electric lamp falls; the reflected beam is transmitted to a drum covered with light-sensitive paper (Voyacek). The most perfect, but very expensive, is the Dohlman nystagmograph: a concave mirror is fixed on a suction cup made of rubber; the cup is attached to the edge of the cornea by light pressure; thus, the mirror follows all the movements of the eye. The mirror weighs 0.6 g. The light source directed at the mirror reproduces the reflected light point, perceived by the light-sensitive paper. N. can also be recorded cinematographically. The nystagmogram recorded by the Ohm instrument gives a clear idea of the frequency, amplitude, and course of N. On the curve, the slow and fast components of labyrinthine N. are sharply marked, whereas nystagmus caused by eye diseases or caused by a violation of posture appears on the curve in the form of equal height ascents and descents in the form of a wave (fig. 10).
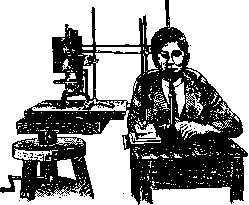
Figure 8. Ohm's nystagmograph.
Etiology of N. The basis of the pathogenesis of spontaneous N. is a violation of the harmonious interaction of the centers and pathways forming the reflex arcs of labyrinthine, vestibular, optokinetic or postural N. This violation is caused by various reasons. Thus, with inflammatory diseases of the middle ear, extending to the labyrinth, sinuses, meninges or to the entire inner ear, as well as with non-inflammatory diseases of the inner ear, labyrinthine N. is observed. When processes extend to the area of the posterior cranial fossa (due to pressure, the presence of otogenic encephalitis in the area of vestibular nuclei, etc.), a large-amplitude vestibular nystagmus is observed. The latter is also observed with organic diseases of the central nervous system along the path of the vestibular system. Among these diseases, necrotic foci in the area of the brain stem, infectious encephalitis (typhus, typhoid, relapsing fevers, erysipelas, etc.), toxic encephalopathies (lead poisoning, botulism), multiple

Figure 9. Buys' nystagmograph.
sclerosis (predominantly pendular N., sometimes dissociated N. is also noted), syringobulbaria (rotatory coarse N.). Coarse vestibular nystagmus, observed in cerebellar diseases (tumors), is the result of remote action on the vestibular system located in the medulla oblongata, since experimentally from the side of the cerebellar substance, N. has not yet been obtained. Tumors of the cerebrum can cause vestibular nystagmus, since through remote action they cause increased pressure in the posterior cranial fossa. In addition to the above-mentioned etiological factors, pareses and paralyses of the oculomotor nerves can also be the basis of positional N. Positional nystagmus caused by these causes is fine and very frequent, directed in both directions, but is more often observed on the side of the affected nerve. Since positional nystagmus is caused by a violation of the setting of voluntary movements, it should be expected that N. in such cases can also be caused by diseases of the central mechanisms regulating the voluntary setting of the eyes (gyrus angularis, second frontal convolution, parietal, occipital lobes). Positional spontaneous N., observed with extreme abduction, is the only form that is observed in neurotics in 75% of cases. Diseases and anomalies of the eye, as well as degenerative lesions of the optic pathways and centers, cause optical spontaneous nystagmus. It can occur in the following diseases and developmental anomalies of the eye: microphthalmia, coloboma of the iris and vascular tunic, congenital absence of the iris, central cortical cataract, pronounced anomalies of refraction, complete blindness, as well as color blindness with accompanying phenomena of pigmentary retinitis, then acquired in early childhood diseases of the cornea. N. in the mentioned diseases is pendular, and with extreme eye abduction it becomes jerky and disappears in the dark. In the mentioned diseases, horizontal N. is most common, but rotatory, vertical, and diagonal N. are also observed, as well as dissociated and monocular N. Monocular N. is more often vertical and is often accompanied in children by a nodding movement of the head (spasmus nutans). In the latter, it is caused by staying in poorly lit dwellings. In terms of amplitude, it is usually medium-coarse, while fine N. is very rarely observed. Spontaneous optical N., caused by the above-mentioned causes, is sometimes observed as a familial disease. Latent N. also belongs to the group of optical spontaneous nystagmus, characterized by the fact that when one eye is closed, a medium-coarse N. appears on the open eye, and it is directed towards this same eye. With binocular vision, the mentioned N. disappears. The mechanism of latent N. has not been clarified, just as the mechanism of reflex N., caused by irritation of the trigeminal nerve in conjunctivitis and irritation of the nasal mucosa in operations on the nasal septum and turbinates. The next etiological factor causing the appearance of spontaneous optical N. is many degenerative brain diseases. Spontaneous N. is very rare. Persons who can voluntarily cause N. could often equally cause the contraction of other muscles, usually not allowing isolated voluntary contractions. A special disease is the so-called nystagmus-myoclonia of Lenoble and Obin (nystagmus myoclonica). It is characterized by pendular, less often rhythmic N. with rotatory, diagonal, most often with horizontal direction. This N. is accompanied by trembling of the head muscles (tremor of the head), increased reflexes, intellectual and vascular disorders. Spontaneous nystagmus in tower skull is most likely caused by phenomena accompanying reduced vision. N. of coal miners. N. is very common among miners, thus being their professional disease. Thus, in the USSR in the Anjero-Sudzhensky district of the Tomsk region, Sergeeva found among miners from 12% to 22% nystagmatics. This figure, as well as similar statistical data noted by authors in other countries, justifies the attention paid to the professional hygiene and pathology of nystagmus of coal miners. In Germany, England, Belgium, since 1913, governments have established special commissions consisting of representatives from miners, the coal industry, specialist physicians - otoneurologists and ophthalmologists for the study of nystagmus of miners. In Liege in 1908, a special clinic was founded for the purpose of studying and treating N. In 1927, at a scientific conference of physicians in the city of Stalin, a resolution was passed to organize a commission for the study of nystagmus of coal miners similar to analogous organizations in other countries. In 1931, at a conference of the Stalin Institute of Pathology and Occupational Hygiene, a plan was developed for organizing a collective expedition for the study of N. of coal miners. The expedition began work in May 1931. Not all categories of workers engaged in underground work are equally affected by N. Miners are in first place (75% of all cases of N. of coal miners). Loaders, scrapers, sled runners, tunnelers give a significantly smaller percentage of diseases. The close connection between the occurrence of nystagmus in miners and their professional activity is evident from the table (Table 1), where the percentage of nystagmatics increases with the length of service in underground work. However, the fact that among miners in the USA and South America N. is not observed contradicts the position that this N. is caused exclusively by working conditions in mines. The observation that a Scottish miner suffering from N., after moving to work in mines in the USA, ceased to suffer from the mentioned disease and upon returning to working conditions in Scottish mines fell ill again, indicates that not all causes of N. in mine working conditions have been sufficiently studied. Table 1. (Borrowed from Vigdorchik). Length of underground work Less than 2 years From 2 to 5 years 6 to 10 years 11 to 15 years 16 to 20 years 21 to 25 years Percentage suffering from N. 1.0 1.6 3.9 12.0 24.0 29.0 Length of underground work From 26 to 30 years. 31 to 35 years ! 40 years ! 45 years ! 50 years ! 55 years ! 36 V 41 V 46 V 51 Percentage suffering from N. 39.0 45.0 43.0 65.0 20.0 10.0 Most often, workers aged 25 to 40 years get sick. Cases of illness in adolescence are not uncommon, after three months of underground work. Clinical picture.-The professional disease of workers manifests itself not only with N., but also with trembling of the head, eyelids, extremities and a number of phenomena from other organs (see below). N. in this disease is only the first and more pronounced symptom. N. of coal miners belongs to the category of optical N. However, the clinical picture of N. of coal miners is extremely varied, which complicates differential diagnosis between it and other categories of N. (see below). Similar diversity is also observed with respect to the speed of N. (32-517 per second). N. manifests itself at a certain angle of eye deviation. N. is especially easily caused when looking up. By establishing the limits of eye deviation in all directions in which N. appears, the so-called tremor field is determined. The patient, in order to avoid this field, holds his head tilted accordingly. Nystagmus of coal miners sometimes manifests itself in the dark, and when the patient moves into a lighted room, it disappears. Consequently, dimming has an irritating effect on N., while illumination has a calming effect. In myopic nystagmatics, after applying corrective glasses, N. becomes significantly weaker. These observations lead to the establishment of preventive and therapeutic measures. Movements and changes in head position intensify N. of coal miners. In 2,000 cases (Llewellyn), N. of coal miners in 501 cases was noted with spasm of the eyelids, in 628 cases - trembling of the head. In addition to tremulous phenomena, increased excitability of the sympathetic nervous system, disruption of tendon and skin reflexes, slow gait and speech, a persistent feeling of fear, headaches, heavy sleep, loss of appetite, arrhythmic pulse, depression of the psyche, photophobia are noted. Cessation of work in underground conditions leads to the disappearance of the noted symptoms; after resumption of work in mines, relapses often occur. A predisposition to the disease is noted in certain families and among some peoples; thus, Slavs get sick more often than other races. Of the unfavorable working conditions that can be considered causes of the disease, two moments deserve attention: insufficient lighting in mines and the twisted position assumed by the miner during work with strained upward deviation of gaze. However, the possibility of the pathogenic effect of inhaling gases from certain types of coal is not excluded, which is indicated by the absence of nystagmus of coal miners among workers in the USA working under otherwise equal conditions with Scottish workers. Methods of lighting mines at present are as follows: safety lamps - oil and gasoline, candles and open lamps, electric and acetylene lamps.
Their brightness in units is indicated in Table 2. Table 2. Brightness of various light sources used for illuminating mines (according to Natanson). Light source Brightness in units Oil lamp..... Gasoline lamp . . . . . Candle and open lamp Electric lamp . . . Acetylene lamp . . . 0.5 1.01 0.7 1.75 8-15 From Table 3 it is seen the influence of the type of lighting on the number and character of N. disease. Improvement of lighting conditions has a beneficial effect on reducing diseases and the character of nystagmus. Table 3. (According to Natanson.) Method of lighting Number of severe cases per 1,000 coal miners Safe oil ! lamp......1
35 Safe gaso- ; line lamp . . . .
0 Electric lamp .......... Acetylene lamp Number of pronounced diseases per 1,000 coal miners 57 44 13 All these data with sufficient convinciveness indicate the role of mine lighting in the disease of coal miners with N. A twisted position of the body contributes to irritation of the vestibular organ,-as a result of which vestibular N. appears. But pathological changes in this system in coal miners are rarely observed, although it is quite possible that in persons with increased excitability of the vestibular system due to the twisted position, vestibular N. is added to N. in coal miners. This is indicated by the recording curve of N. in coal miners, containing elements of labyrinthine N. However, the appearance of N. due to insufficient lighting is still difficult to explain, and regarding its mechanism there are several theories: 1) theory of fatigue of eye muscles; 2) connection with poisoning by mine gases; 3) theory of violation of balance centers of eyeballs; 4) theory of counter-rotation of eyes; 5) labyrinthine theory;. 6) lighting theory. Of all theories, the lighting theory best explains the mechanism of N. in coal miners. The similarity of N. in coal miners with non-professional N., for example experimental N. from darkness, N. in children growing in dark rooms (spasmus nutans), and N. in people with weakened vision (p. amblyopicus) speaks in favor of this theory. Differential diagnosis of N. in coal miners. When set at a close distance, N. in coal miners weakens the phenomenon opposite to that observed in labyrinthine N. In terms of direction, amblyopic N. usually proceeds uniformly, most often in the horizontal direction; vertical tremor and wheel-like tremor are very rarely observed, whereas circular and elliptical tremors noted in N. of coal miners are not observed at all in amblyopes. Amblyopic N. more often proceeds concomitantly than N. in miners. Congenital tremor occurs at all angles of eye deviation, whereas N. in miners occurs at a certain angle. Moreover, congenital N. does not depend on a certain position and movement of the body. Professional N. most often proceeds with phenomena of apparent movement of surrounding objects, whereas in persons with congenital N. this is not the case, and most often N. is accompanied by weakened vision. It is very difficult to confuse congenital N. with N. observed at extreme positions of the eyes, proceeding in jerks and in the horizontal direction. Intense convergence prevents the appearance of N. in coal miners. It is necessary to keep in mind that pendular movements of the eyes (the right eye moves up and inward, the left-down and outward) also occur in hemianopia. Preventive measures are as follows: it is necessary to improve the lighting conditions in mines, then before ascending from the mine to wear smoked glasses to avoid a rapid transition from darkness to light. It is necessary to carry out systematic otoneuro-ophthalmological examination to detect the latent form of the disease.-T r e a t m e n t. If the disease has already developed, it is necessary to remove coal miners from underground work. More severe forms are subject to treatment by physical methods in a sanatorium-resort setting.
G. Zimmerman. NITRATES, salts of nitric acid, see Saltpeter.
Related articles
Mentioned in
- Acute Ataxia
- Aniridia
- Aplasia Axialis Extracorticalis Congenita
- Bárány's Method of Investigation
- Bard's Sign
- Belous Symptom
- Deiters' Nucleus
- Dejerine-Sottas Disease
- Duchenne Syndrome
- Dyssynergia
- Galvanic Reaction
- Horner's Syndrome
- Labyrinth
- Lobar Sclerosis
- Methods of Medical Examination
- Multiple Sclerosis
- Occupational Diseases
- Otorhinolaryngological Instruments
- Parinaud Syndrome
- Rossolimo Neuritis
Cite this page
“Nystagmus.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/nystagmus/