Opto- and Orthodiagraphy
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article defines the prefix "opto-" and describes the technique of orthodiagraphy, a method for measuring body organs (primarily the heart) using parallel X-rays. It details the technical requirements for accurate measurement, compares the method to teleradiography, and discusses the historical development of the equipment.
Encyclopedia article (1928–1936)
OPTO- (from Greek orthos—straight, correct), a prefix often used in pathology with various meanings. Thus, one speaks of orthostatic albuminuria, referring to the appearance of protein in the urine when the body transitions from a lying to a standing (straight) state; one speaks of orthognathism, referring to the straight state of the teeth; when speaking of orthophoria, one imagines a completely correct (parallel) position of the visual lines of both eyes. See also the articles Orthography, Orthopedics. In organic chemistry, the prefix ortho- has a specific designation—see Organic Chemistry. ORTHODIAGRAPHY (from Greek orthos—straight, correct, dia—through, and grapho—I write), a method of measuring the body by sketching and measuring the contours of its shadow obtained by illumination with parallel X-rays. This is achieved in the following way: during fluoroscopy with X-rays, the point of incidence on the screen of the so-called central ray, i.e., the one of the rays emanating from the anticathode which is strictly vertical to the plane of the screen, is marked in one way or another. For this purpose, a crosshair of thin wire or another object that casts as small but distinct a shadow as possible on the screen can be fixed immovably to the tube in the path of this ray. The tube on the corresponding stand must be movable in a plane strictly parallel to the plane of the immovably fixed screen. Then, the shadow of the central ray marker is successively set on the screen at various points of the boundary of the shadow of the measured object, and these points are marked on the screen. If one thus traces the contours of the shadow of the measured body with the shadow of the central ray marker, marking all points of the shadow contour on the screen, an image of the silhouette of the measured body is obtained on the screen, which was obtained by illuminating it with parallel rays; this silhouette will correspond exactly in its size to the dimensions of the examined body in a plane parallel to the plane of the screen.
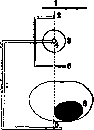
By giving the object a different position in relation to the screen and sketching its shadow each time in the same way, one can measure this body in all planes. Instead of sketching the silhouette of the measured body on the screen, one can fix the screen on the same movable stand that holds the tube, immovably relative to the tube and movably together with it in planes strictly perpendicular to the central ray; the point of incidence of the central ray on it is marked on the screen in one way or another, or a small screen with a diameter of 2–3 cm is taken, the center of which corresponds exactly to the central ray. Paper is fixed on a frame (behind the tube or somewhere nearby) immovably, but in a plane strictly parallel to the plane of movement of the tube and screen, on which the contour of the shadow of the measured object is sketched using a recording device fixed on the same movable frame of the stand to which the tubes and screen are attached. This principle was first implemented in a special device—the orthodiagraph according to Groedel (see Diagram of Groedel’s orthodiagraphy: 1—paper; 2—pencil; 3—X-ray tube; 4 and 5—central ray; 6—blende; 7—stand; 8—heart). To sketch the shadow contours, instead of a pen or pencil that pops out when pressing a bulb, one can use, by stretching paper in a frame, a needle (according to Schick) that pierces the paper when the bulb is squeezed, or even better, an electric spark jumping between two electrodes moving on both sides of the paper (according to Kharakhorkin). The paper is burned through by the spark with small holes (the possibility of recording an orthodiagram in several copies simultaneously). Groedel’s orthodiagraph is the most widely used. But if one adapts a recording device according to the principles just indicated to a movable stand of the 'clinoscope' type by Veifa or 'universal' by Siemens, then one can turn each such stand into an orthodiagraph that meets all requirements. The basic conditions for obtaining correct results in orthodiagraphy are as follows: 1) the plane of movement of the tube (and screen) must be a) strictly parallel to the screen and the plane on which the sketching occurs, and b) perpendicular to the central ray; 2) the patient must be immobilized in the position given to him. Failure to comply with these conditions leads to errors, and the method then not only loses its meaning but also causes harm, creating an illusion of accuracy where there is none. Orthodiagraphy was first implemented and developed by Moritz after the corresponding efforts of Rosenfeld, Payne, and Levy-Dorn. It is used mainly for measuring the size of the heart, less often for determining the size of foreign bodies that have entered the body, and very rarely for determining the sizes of the stomach (with filling it with contrast food), liver, and spleen. Recently, special attention has been paid to the orthodiagraphic measurement of the aorta. The heart can be orthodiagraphed in both a standing, sitting, and lying position of the patient. Each position has its advantages and disadvantages. In the lying position, it is easier to immobilize the patient, but due to the elevation of the diaphragm, the heart changes its shape and its contours become less distinct, especially the apex; in addition, severely ill cardiac patients cannot always tolerate a prolonged lying position. Orthodiagraphy in the sitting position is the most common at the present time.
A silhouette of an object that significantly approaches its true dimensions can also be obtained by teleradiography. This method has the advantage over orthodiagraphy of complete objectivity and does not require the researcher to spend a relatively long time in the rays (2–3 min). But teleradiography of the heart requires powerful equipment, special devices, and the expenditure of photographic materials. In addition, teleradiography of the heart still gives some magnification of its shadow and usually does not provide accurate data in oblique positions due to the obscurity of the boundaries of the heart shadow as a result of its fusion with the shadows of the chest wall. In teleradiography of the heart in the dorso-ventral position, the boundaries of the cardiac apex are not obtained if they are located below the left dome of the diaphragm, as is often the case with a short chest and high standing of the diaphragm. Furthermore, a great advantage of measuring the size of the heart by means of orthodiagraphy is that, by the difference in character, one can accurately distinguish the various arcs of the heart shadow from one another, which is necessary for a more detailed measurement of the orthodiagraphic silhouette of the heart. Therefore, orthodiagraphy for measuring the size of the heart and accurately determining its configuration deserves preference over teleradiography in most cases. It is believed that errors in sketching the boundary of the heart shadow by means of orthodiagraphy in an experienced researcher do not exceed 3 mm.
Related articles
Cite this page
“Opto- and Orthodiagraphy.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/ortho/