Blood Pressure
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia covers the physiological definition, historical measurement methods, and clinical techniques for determining arterial blood pressure.
Encyclopedia article (1928–1936)
BLOOD PRESSURE is the pressure that blood exerts on the walls of blood vessels (so-called lateral blood pressure) and on the column of blood that fills the vessel (so-called end blood pressure). Depending on the vessel in which blood pressure is measured, a distinction is made between arterial, capillary, and venous pressure. I. Arterial pressure. Methodology of measuring arterial pressure. Methods of measuring arterial pressure. Blood pressure was first measured by Stephen Hales in 1727 by tying glass tubes into vessels and determining blood pressure by the height to which the blood rises in them. Accurate measurement of arterial pressure is greatly hindered by constant, significant fluctuations, particularly pulse fluctuations. Therefore, for an accurate measurement of arterial pressure, it is necessary—with the aid of an appropriate manometer—to record it with all these fluctuations over a certain period of time in such a way that on this record (curve) its height can be determined at every moment of that period. Using a planimeter on such a curve, one can also accurately determine the magnitude of the mean level of arterial pressure over a given time. Arterial pressure at the peak of pulse waves is called maximum or systolic pressure; the lowest pressure between pulse waves is minimum or diastolic pressure; and the difference between maximum and minimum pressure, i.e., the amplitude of pulse oscillations of arterial pressure, is pulse pressure. The measurement of arterial pressure is further complicated by the fact that blood is in rapid and pulsating motion within the arteries. Usually, to transmit arterial pressure to the recording device—the manometer—a cannula is used, which is tied into the central end of a severed arterial branch. In this case, the blood flow in this branch ceases, and the lateral pressure in the artery from which this branch originates is measured at the site of this branching. However, pulse waves continue to penetrate into the branch in which the cannula is inserted (respectively, into the cannula itself) and strike the blind end of the manometer. Consequently, a phenomenon similar to the so-called hydraulic shock develops here, significantly distorting the true values of arterial pressure fluctuations and, in particular, strongly increasing the so-called maximum pressure (Muller, Fabre). This artificial increase in maximum arterial pressure must be taken into account in all measurements of arterial pressure by blood methods, when the cannula is inserted into the central end of a severed artery, and in all determinations of maximum pressure by clinical methods, since with these methods the maximum pressure is determined at the moment of complete or almost complete closure of the lumen of the corresponding artery. The distortion of the arterial pressure value from hydraulic shock is undoubtedly reduced if, in the experiment, T-shaped cannulas tied into the severed artery (A. Muller) are used to transmit the arterial pressure to the manometer, or if a cannula is inserted into the arterial branch so that the end of the cannula is located right at the site of origin of the arterial branch from its trunk (Frank). With the latter method, a branch with a small diameter compared to the diameter of the trunk should be chosen for measuring arterial pressure. Still, even with this method and when using a T-shaped cannula, an ideally accurate recording of the lateral blood pressure at a given point in the arterial system is not obtained. These inaccuracies of physiological methods for measuring arterial pressure must always be taken into account when evaluating the results of these measurements. Various manometers are used as devices for recording arterial pressure. The oldest and most commonly used of them is a simple mercury U-shaped manometer. Characterized by significant inertia, it reproduces the pulse oscillations of arterial pressure in a completely distorted scale, but on the other hand, it gives a certain idea of the average level of arterial pressure. For this purpose, the mercury manometer is quite suitable and is still commonly used in experiments to record arterial pressure over longer periods of time. For a more accurate registration of arterial pressure with all its fluctuations, and pulse fluctuations in particular, a number of manometers have been proposed in which springs, levers, pistons sliding in cylinders, or membranes are used to transmit pressure to the recording device. To record the movements of the manometer, various levers are used that record the arterial pressure curve on a rotating drum, or mirrors attached to the end of the lever or to the membrane of the manometer: the beam of light reflected by them records the movement of the mirror and, consequently, the pressure fluctuations on a moving strip of photographic paper (photographic kymography). In a simple mercury manometer, a float with a vertical wire rod is placed on the surface of the mercury at the free end of the manometer, to the upper end of which a pen is attached, recording the movements of the float on a rotating drum. For accurate recording of arterial pressure fluctuations, all these spring, piston, membrane, and mirror manometers must possess certain qualities: the greatest possible sensitivity, the shortest possible natural oscillation period, and a smaller mass, etc. All aspects relevant to the correct design of such manometers were subjected by O. Frank to a detailed theoretical and experimental analysis and corresponding laws expressed in formulas were established. At the present time, the design of devices for recording arterial pressure is guided by these laws, thanks to which modern manometers for measuring blood pressure have achieved significant perfection. Among them, the spring and mirror manometers of O. Frank and the spring and membrane manometers constructed by A. Muller must be mentioned. Opening arteries for direct measurement of pressure inside the arteries in humans is not applicable in medical practice, and therefore one has to use various indirect methods, with these clinical methods being more or less limited to determining only the maximum pressure. In all these clinical methods of measurement, the pressure in a given artery is judged by the pressure that needs to be exerted on the artery from the outside to obtain certain signs indicating its compression. Usually, the clinical measurement of arterial pressure is performed in such a way that the artery is first compressed with such force that all pulse phenomena disappear peripheral to the compression site—i.e., with a force exceeding the maximum pressure—and then the pressure is gradually reduced until the first appearance of the aforementioned signs of the pulse wave passing through the compression site. The pressure exerted on the artery at this moment is considered the corresponding maximum pressure. Only certain peripheral arteries are accessible to this method of measuring arterial pressure. Previously, corresponding pads (usually rubber bulbs) (apparatus of Basch and Potain, Sabli) were used for their compression, but this method is applicable only to arteries that lie on a solid (bony) base, are covered only by skin, and are not surrounded by soft parts. These requirements are best met by the radial artery, which is the chosen artery for measuring arterial pressure by these methods, and to some extent also the temporal artery. Nevertheless, these methods of measurement are nowadays almost abandoned, because the compression of arteries and, in particular, the registration of the corresponding pulse phenomena by such methods are technically difficult and imperfect. At present, another method of arterial compression to determine arterial pressure is universally accepted, namely the cuff method. When using the cuff method of arterial compression, almost exclusively the brachial artery is used, because only it is located in relation to bones and soft parts in such a way that its compression by a cuff is not difficult. The width of the hollow cuff for compressing the brachial artery should be no less than 12 and no more than 14 cm, since both larger and smaller widths give less accurate data (Recklinghausen). It would be best to use in each case a cuff of a width that would be in a proper ratio to the circumference of the arm of a given person. The side of this cuff adjacent to the skin of the subject should be made of elastic rubber, approximately 1/2–1 mm thick, and the other of non-yielding fabric. Compression of the artery by the cuff is produced by pumping air into it through a corresponding rubber tube using a double bulb or other pressure pump. The pressure in the cuff is measured using a mercury or spring manometer showing pressures up to 300 mm Hg. The simplest way to determine the first pulse waves is by palpation (the method of Basch, Potain, Riva-Rocci, etc.)—the so-called palpation method. The appearance (resp. disappearance) of pulse waves can also be determined by the appearance (resp. disappearance) of fluctuations of the needle of the manometer measuring the pressure in the cuff—the so-called oscillatory method.
Mercury manometers are unsuitable for this method due to their inertia, which is why Bourdon, spring, or other manometers sensitive to rapid pressure fluctuations in the cuff are used (Recklinghausen, Raspopov, Pachon, and others). These pressure fluctuations in the cuff can also be recorded with appropriate devices (Uskov, Recklinghausen, Plesch, and others). Finally, the penetration of pulse waves into the segment of the artery under the cuff can also be determined by auscultating the sound phenomena—arterial tones—that appear in the process (Korotkov's sound method). For this purpose, the end of a stethoscope is applied to the location of the artery below the cuff. To determine the maximum arterial pressure at the present time, the palpatory or sound method is used almost exclusively, measuring the pressure in the brachial artery by means of a cuff. Also worthy of mention is the method for determining maximum arterial pressure in the digital arteries proposed by Gärtner, because it makes it possible to measure arterial pressure in more peripheral arteries. Having placed a small hollow cuff on the finger at its base, the finger is exsanguinated and air is pumped into the cuff to such an extent that it prevents blood from entering the finger. Then, measuring the pressure in the cuff with the aid of a mercury manometer, it is lowered until the first appearance of coloration in the finger. Determining the minimum pressure is somewhat more complex. For this purpose, use is made of those greatest oscillations either in the volume of the brachial artery or in the tension of its wall, which occur when the cuff exerts a pressure on the artery that slightly exceeds the minimum pressure within it. At such a pressure in the cuff, the artery in the interval between two pulse waves should collapse until its walls touch each other, and during the passage of the pulse wave, expand almost to its usual volume. Simultaneously, the greatest oscillations of its wall tension will also occur—from complete relaxation to tension by the full pressure of the pulse wave. If the pressure in the cuff is only slightly lower than the minimum arterial pressure, the artery between the pulse waves will no longer collapse, and the oscillations of its volume and the tension of its walls depending on the pulse waves will be comparatively small. Due to this, with a rapid decrease in the cuff pressure below the minimum, a sharp decrease in the oscillations of the arterial volume and the tension of its walls immediately occurs. To illustrate the phenomena that occur in the artery when measuring the maximum and minimum arterial pressure by the sound and oscillatory methods, a diagram is given here (Fig. 1) of an oscillogram as it is obtained when measuring arterial pressure, with parallel schematically depicted Korotkov sound phenomena.
Phase I.
Phase II.
Phase III.
Max. Min. - I tones
I tones with murmurs and murmurs Figure 1. As indicated above, arterial pressure is usually measured by first raising the pressure in the cuff above the maximum and then gradually lowering it. The negative side of this procedure is that the pressure is measured after stasis has already been created in the arm by the compression of veins. But in practice, it is easier to catch the transitions that determine the maximum and minimum pressure with falling pressure in the cuff than with rising pressure. As can be seen from the figure, small fluctuations in cuff pressure are also recorded at a pressure level exceeding the maximum arterial pressure. This is the result of pulse waves striking the upper edge of the cuff. But at the level of the maximum pressure, the fluctuations become distinctly larger and at the same time the tones of the so-called first phase of Korotkoff's sound phenomena appear. At a pressure 5-10 millimeters lower, a palpable pulse also appears in the radial artery. With a further decrease in cuff pressure, the oscillations recorded by the oscillograph gradually become larger, but the tones are soon replaced by the murmurs of the so-called second phase of Korotkoff's sound phenomena. Whereas the tones of the first phase are regarded as manifestations of the initial tensions of the arterial wall by the tips of the pulse waves penetrating under the cuff, the murmurs of the second phase must be considered a manifestation of the penetration of pulse waves through the segment of the artery narrowed under the compressing cuff into its distal, uncompressed part. With a further decrease in cuff pressure, the oscillations of the oscillogram become gradually and uniformly even larger, and the murmurs are again replaced by tones; these tones—the third phase of Korotkoff's sound phenomena—increase in their intensity in parallel with the increase in the oscillations of the oscillogram, acquire significant loudness and, at the cuff pressure directly preceding the minimum arterial pressure, reach maximum intensity simultaneously with the maximum magnitude of the oscillogram oscillations and then, together with a rapid decrease of the latter, disappear immediately or after a rapidly increasing attenuation. The moment of transition from the maximum oscillations of the oscillogram to their decrease and the moment of the first attenuation of the tones of the 3rd phase with the pressure decreasing in the cuff determines the minimum arterial pressure. The phase, usually consisting of several fading tones, which is sometimes caught after the tones of the 3rd phase, is designated as the 4th phase of Korotkoff's sound phenomena. Occasionally, under certain conditions not yet fully understood, the tones of the 4th phase are audible at a considerable distance when the pressure in the cuff drops even below the minimum arterial pressure, and the transition of the tones of the 3rd phase to the tones of the 4th is indistinct. In such cases, the determination of the minimum pressure by the sound method gives incorrect, too low numbers. The determination of maximum pressure is associated with a whole series of inaccuracies. Mention has already been made above of the increase in the maximum pressure measured by clinical methods due to the so-called hydraulic shock. There are as yet no methods to clinically determine the magnitude of this hydraulic shock. It must be assumed that it will be greater, the greater the living force of the pulse wave arising in the aorta is, and the more rigid the arterial wall is. The living force of the pulse wave arising in the aorta is determined by the amount of blood ejected by the corresponding systole of the left ventricle into the aorta (the so-called Schlagvolumen—systolic blood volume) and the speed imparted by this systole to this mass of blood. Regarding the pressure developed by the hydraulic shock of the pulse wave when measuring arterial pressure in humans by clinical methods, we have an idea only on the basis of measurements by Merke and Müller (Merke, Müller) in two patients in whose cases lateral pressure was measured by the bloody method using appropriate methods, and at times the brachial artery was compressed in an appropriate manner below the measurement site. The increase in maximum pressure from hydraulic shock in one case was 38 mm Hg, and in the other case 43. The second source of inaccuracy in determining the maximum arterial pressure stems from the circumstance that in all the described methods for determining maximum pressure, it is measured by the pressure necessary to stop all pulse phenomena peripheral to the site of compression. This pressure on the artery, necessary for the complete or almost complete closure of its lumen, must overcome two obstacles: 1) the blood pressure in the artery, and 2) the resistance offered to the compression of the artery by its walls (AW — Arterienwandspannung). To determine this latter quantity separately is possible by clinical methods only indirectly and even then only approximately. Under normal conditions, it is apparently equal to 8-15 mm Hg. Arteriosclerotic changes in the arterial wall, contrary to generally accepted views, apparently do not have a great influence in terms of increasing AW; the degree of tonic contraction of the arterial musculature has a significant influence on AW; with its enhancement, AW reaches 30-40 mm Hg, and with its decrease, 2-5. The extent to which the minimum pressure measured by clinical methods corresponds to the true minimum lateral pressure in a given artery has not been sufficiently elucidated. Since the measurement of the minimum arterial pressure is carried out with the arterial lumen closed only in the interval between two pulse waves, it must be assumed that the influence of the hydraulic shock is less here and that therefore the minimum arterial pressure measured by clinical methods is closer to the true one than the maximum arterial pressure measured by these methods. Comparison of the results of arterial pressure measurement obtained in parallel using bloody methods and clinical methods on humans (in a small number of experiments) by O. Müller, Merke, and A. Müller nevertheless shows a significant approximation of the numbers obtained by clinical methods to the numbers obtained by bloody methods. Of course, for the maximum arterial pressure determined by clinical methods, a significant increase due to hydraulic shock remains. Arterial pressure under various physiological conditions. Arterial pressure in large arteries drops only slightly and gradually, and only in the precapillaries does a sharp drop occur. An idea of the change in maximum and minimum arterial pressure separately along the path from the aorta to the capillaries is given by a comparison of the results of arterial pressure measurement in various arteries performed by Klisiecki. From these data, it is evident that towards the periphery, the maximum arterial pressure decreases, and the minimum gradually increases somewhat. Correspondingly, the amplitude of pulse pressure fluctuations gradually decreases toward the periphery and peters out in arteries with a diameter of 0.2-2.3 mm. If in previous measurements (Spengler, Volkmann, and others) in individual experiments in the arterial branch, a somewhat higher maximum pressure was sometimes obtained than in the overlying trunk, this is partly explained by the fact that the hydraulic shock in more distal arteries gives a higher pressure rise than in more central ones (see the results of Merke, Müller, Fabre), and partly by the fact that the arterial pressure in peripheral arteries fluctuates within wide limits as a result of temporary local vasomotor influences. Therefore, in individual measurements, higher numbers for arterial pressure can be obtained in more peripheral arteries compared to central ones.
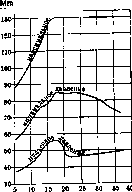
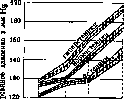
Figure 3. Changes in arterial pressure in youth and middle age. As for the level of arterial pressure in various animals, the curves of Klisetsky give an idea of the arterial pressure in a dog. In the horse, the average arterial pressure is 155 mm, in the guinea pig - 75 mm Hg. As these examples show, there is no proportionality between the magnitude, resp. body weight, and arterial pressure in various animals. This confirms, among other things, the fundamental proposition of hemodynamics that the level of arterial pressure does not in itself determine the intensity of blood circulation, as measured, for example, by the amount of blood pumped by the heart in a unit of time. (A basin located at a very high altitude does not yield a greater amount of water per unit of time if the pipe is narrow.) Factors determining the level of arterial pressure. In humans, the level of arterial pressure depends on sex and age (see table and Figs. 3-6, as well as blood pressure in children below. The indicated arterial pressure is the average for a given sex, age, etc.). Deviations from these average values within 10-20 mm Hg should still be considered normal. Change in arterial pressure in old age (according to Richter). This fact of the coincidence of the increase in arterial pressure in women with menopause is the most convincing example of the influence that internal secretion has on blood pressure. During pregnancy, starting from the 5th month, a slight increase in arterial pressure is observed (on average no more than 10 mm Hg). Childbirth is accompanied by a significant rise in arterial pressure, but after its completion, the pressure rapidly drops by 10-20 mm Hg below the initial level; this drop sometimes reaches even 50 mm Hg. In old age, a decrease in minimum arterial pressure and an increase in the amplitude of pulse oscillations of arterial pressure should be noted, apparently as a result of aortic sclerosis (see below). (On the influence of constitution on arterial pressure, see the table, as well as the curves of Alvarez-Zimmermann - Fig. 7.) Influence of constitution on arterial pressure (according to Larimore). Constitution Quantity Maximum pressure Minimum pressure Pulse pressure Body surface in m2 M. F. M. F. M. F. M. F. Stenics ....... Hypostenics .... Asthenics ...... 65 62 15 68 55 51 126.3 116.3 106.8 118.4 115.6 105.7 78.8 71.7 63.3 73.4 72.3 68.2 47.5 44.6 43.5 45.0 43.3 37.5 1.81 1.61 1.67 1.539 1.66 1.516 Age...
__________ women Figure 4. Changes in maximum arterial pressure by age (according to Saller). There is none. Worthy of attention are the increase in pulse pressure oscillations during puberty (Fig. 3) and the steep rise in arterial pressure in women after 40-45 years. The greater a person's height and weight, the higher their average arterial pressure. On the influence of climatic conditions and the time of year on arterial pressure - see Hypotonia. Fluctuations in arterial pressure during the day in normal conditions usually do not exceed 10-20 mm Hg, but are distinguished by a certain regularity. Arterial pressure reaches its lowest level during the deepest sleep, towards morning, and gradually rises during the day to reach a maximum in the afternoon and evening. After eating, the maximum arterial pressure also rises by about 10 mm, while the minimum arterial pressure does not rise, but even falls, as a result of which the amplitude of pulse pressure oscillations clearly increases. This increase in arterial pressure with a simultaneous increase in pulse rate is a manifestation of the increase in the minute volume of blood after eating (see Blood circulation, physiology). In the standing position, the pressure (maximum - 119, minimum - 80) is slightly higher than in the lying position (115 and 72). The experiments of Liljestrand and Stenstrom give a good idea of the influence of muscle work on arterial pressure (see table). There are sharp fluctuations in arterial pressure (Griesbach) and elevated arterial pressure is encountered more often than among other professions (Gelman). A tendency to hypertension is also noted among brewery workers and aniline (dye) production workers. Mental work also causes an increase in arterial pressure, but to a significantly lesser extent than physical work. In general, it also gives Influence of muscle work on arterial pressure (according to Liljestrand and Stenstrom). Position Average speed in m per min. Systolic pressure in mm Hg Standing .................. During walking ...........} During running ...........) 78.3 95.3 113.0 184.5 236.6 264.3
age These changes in arterial pressure during muscular work are determined by an increase in the minute volume of blood. Since the degree of decrease in the total resistance to the outflow of blood from the central arteries to the periphery lags behind the degree of increase in the minute volume, arterial pressure rises, with pulse pressure growing the most. The more accustomed the physical movement, resp. the better the training, the smaller the increase in the average level of pressure, but the greater Figure 7. Change in arte-the increase in pulse rial pressure in women of various constitutions. pressure,
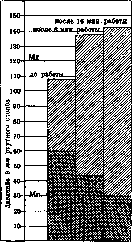
THIS DEPENDS ON THE FACT that the greater the training, the smaller the heart rate acceleration during a given physical work and the greater the increase in the systolic stroke volume (Schlagvolumen). The increase in arterial pressure caused by physical work passes quickly after the cessation of work in healthy people - within a few minutes - and the sooner, the lighter the work was. After prolonged and heavy work, a period of its decrease immediately follows the increase in arterial pressure. The external conditions under which work takes place have a significant influence on the change in arterial pressure due to physical work. At a high external temperature (e.g. under the working conditions of foundry workers), physical work causes a particularly strong decrease in the minimum arterial pressure and, as a consequence, a very sharp increase in pulse pressure. As an example, Figure 8 shows diagrams of changes in arterial pressure in a drawer worker of a foundry after 8 and 16 minutes of heavy work near the furnace (Stozhkova-Goldfarb). From the as yet few observations on the influence of various professions on arterial pressure, it follows that foundry workers in particular exhibit 124.6 132.5 134.2 142.3 161.5 168.6 164.0 Diastolic pressure in mm Hg Pulse pressure in mm Hg 95.0 94.1 98.6 97.5 101.7 102.4 35.8 37.5 40.1 43.7 64.0 66.9 61.6 Pulse rate 73.8 88.8 92.4 94.8 127.2 141.3 153.4 O2 consumption (in cm3) per min. 270 1,010 1,330 1,860 3,120 3,390 3,650 the greater the increase, the less familiar it is and the more difficult. But arterial pressure rises particularly sharply under the influence of any psychological excitement, and especially one that is accompanied by negative sensations (anger, fear, etc.). This influence of psychological factors must be taken into account with every measurement of arterial pressure, since the measurement process itself, especially if it is unfamiliar to the given person, causes greater or lesser excitement and, thanks to this, a certain increase in arterial pressure. The influence of relatively small changes in atmospheric pressure on arterial pressure is clearly noted only immediately after its change, and both its decrease and increase cause a rise in arterial pressure. With a significant decrease in atmospheric pressure, for example at high mountain altitudes (4,000 - 5,000 m), a tendency toward a persistent increase in arterial pressure is observed, reaching a level 40-50 mm Hg above normal. Physical work at high altitudes causes a sharper rise in arterial pressure than the same work at sea level. The tendency for arterial pressure to rise at high altitudes is especially pronounced in elderly people. This increase in arterial pressure at mountain altitudes is the result of a lack of O2, as it disappears under the influence of O2 inhalation (Loewy). Between arterial pressure, cerebrospinal fluid pressure, and intraocular pressure under physiological and pathological...
Figure 8.
conditions, a certain parallelism can be noted in the sense that an increase in arterial pressure is accompanied by a certain rise in the pressure of both cerebrospinal fluid and intraocular pressure. On the other hand, an increase in intracranial pressure usually causes a rise in arterial pressure in the initial period. Blood pressure is the transformed energy of cardiac contractions; it in turn is transformed into the energy of blood motion and into the energy of tension of the arterial walls; the latter during ventricular diastole is again transformed into blood pressure and its motion. Blood pressure is an indispensable intermediate phase in the conversion of a significant part of the energy of cardiac contractions into the energy of blood motion. Consequently, a known level of arterial pressure is an indispensable condition for adequate circulation. Due to the intermittent character of the pumping work of the heart, constant fluctuations in blood pressure and a rhythmic alternation of the indicated energy transformations occur in the arterial system. In addition to pulse waves depending on the work of the heart and called 1st-order waves (about them see Pulse), 2nd-order waves are also observed in the arteries. These include fluctuations in arterial pressure synchronous with respiration. These fluctuations occur as follows: at the beginning of inspiration, arterial pressure drops and already at the beginning of inspiration reaches a minimum, followed by a rise which continues during the entire remaining part of inspiration and reaches its highest height at the beginning of expiration. Then in the remaining part of expiration the pressure drops to again reach a minimum at the beginning of inspiration. Consequently, inspiration corresponds mainly to an increase in arterial pressure, and expiration to a decrease, but these respiratory fluctuations in arterial pressure lag somewhat behind the respiratory waves, and this lag is stronger the faster the respiration rhythm. Respiratory waves of arterial pressure are the result of the merging of a whole series of arterial pressure waves arising in various ways in connection with the phases of respiration. We distinguish 1) respiratory fluctuations of arterial pressure of mechanical origin. They are of a twofold origin: a) as a result of those movements of blood that occur during respiratory movements of the chest cage due to a decrease during inspiration in the pressure on the heart, aorta, and large veins and due to an increase in this pressure during expiration, and b) as a result of the suction of blood into the thoracic cavity during inspiration (with simultaneous compression of veins in the abdominal cavity) and as a result of the delayed entry of blood into the thoracic cavity during expiration. Mechanical influences of the second category have a decisive influence on the character of the respiratory waves of arterial pressure and determine the lag of these waves compared to the phases of respiration. 2) Respiratory fluctuations of arterial pressure of nervous origin: a) Traube-Hering waves (Traube, Hering); they arise as a result of the spread of periodic excitations of the respiratory center by irradiation to the vasomotor center; these waves have a character opposite to the respiratory waves of arterial pressure of mechanical origin and, being weaker than the latter, obviously contribute to a certain weakening of them; b) Fredericq waves depend on the influence on arterial pressure of the acceleration of the heart rhythm during inspiration and its slowing down during expiration (see Pulse). 3rd-order waves, or Siegmund Mayer waves. These fluctuations in arterial pressure do not depend on either cardiac or respiratory functions. They are observed with a frequency of 6–9 per minute, can be very regular, but also completely irregular both in terms of height and length. The height of these waves in rabbits can reach 40 mm Hg. These waves are often obtained in a pronounced form on human plethysmograms as well. They are regarded as the result of independent fluctuations in the tone of vasomotor centers, causing periodic contractions of blood vessels in extensive areas of the body and thereby fluctuations in arterial pressure. Significance of changes in arterial pressure for judging the circulation. The level of arterial pressure is determined by the amount of blood ejected by the heart per unit time into the aorta and by that resistance which the movement of blood encounters mainly at the periphery of the arterial system in the form of friction. Of decisive importance for the magnitude of this friction is the lumen of the small precapillary arteries as a whole (see Blood circulation, physiology). Consequently, the level of arterial pressure is determined by the ratio between the degree of constriction of peripheral arteries and the work of the heart, measured by the minute volume of blood. The level of arterial pressure is regulated by the vasomotor nervous system and is established by it depending on the necessity of adapting circulation to the demands of organs and tissues in the sense of greater or lesser blood supply determined by their functional state. However, the rise and fall of blood pressure is not the main method used by the body to change circulation and blood supply to organs. Conversely, by changing the distribution of blood and the speed of circulation, the body rather strives to maintain as far as possible the normal level of arterial pressure. Thus, for example, during increased muscular work, the amount of blood ejected by the heart into the aorta per unit time increases up to 10 times, while arterial pressure rises by only 1/3. Regarding the vasomotor nervous system, see Blood circulation, Vasomotors, and Autonomic nervous system. In addition to the vasomotor nervous system, the function of regulating arterial pressure is also attributed to the system of endocrine glands, of which the adrenal medulla, pituitary gland, ovaries, and other glands secrete, as evidenced by numerous experiments and clinical observations, secretions that undoubtedly affect the tone of arterial musculature. On the basis of these same observations, the impression is obtained that the correct interrelation of the functions of these various glands maintains a normal 745
blood level of arterial pressure. But for now, the prevailing view is that the regulation of arterial pressure by these increts still occurs through the mediation of the vasomotor nervous system; the latter, like the entire autonomic nervous system with endocrine glands, is connected into a complex but functionally unified apparatus regulating autonomic functions, including arterial pressure. In particular, the vasomotor nervous apparatus under normal conditions coordinates the work of the heart and arterial pressure primarily for the purpose of an adequate blood supply to the tissues. Therefore, with a primary increase in the tone of the musculature of peripheral arteries, i.e., with their constriction in extensive areas of the body, arterial pressure rises, since the work of the heart increases in order to ensure an adequate blood supply to the tissues through compensatory acceleration of the flow through the constricted peripheral arteries. With a weakening of the tone of the musculature of peripheral arteries, i.e., with their dilation, arterial pressure drops, and at the same time, by increasing the frequency and force of the heart's work, the level of arterial pressure necessary for a sufficient flow of blood in the capillaries is maintained as far as possible. But since the intensification of the heart's work is possible only with an adequate supply of blood, and with significant dilation of vessels in extensive areas of the body—in particular in the region of the abdominal viscera—the supply of blood to the heart decreases, then often under these conditions arterial pressure still drops, and a picture of circulatory insufficiency develops as a result of vascular insufficiency as a primary phenomenon and cardiac insufficiency as a secondary one. With an intensification of the heart's work, if the vasomotor nervous apparatus is working normally, an increase in arterial pressure does not occur, because peripheral vessels dilate to a corresponding degree and the blood flow increases. With a weakening of cardiac activity, i.e., when the heart ejects an insufficient amount of blood into the aorta per unit time, arterial pressure does not drop if the vasomotor apparatus is working normally, because it (the vasomotor apparatus) strives to maintain the level of arterial pressure necessary for a sufficient blood supply to the organs most vital to life, mainly the heart and brain, by increasing the tone of the arterial musculature. Since blood passes from arterioles into capillaries, a rise in arterial pressure is also theoretically quite possible as a result of the narrowing of the lumen of all capillaries as a whole. Such an origin of the rise in arterial pressure is assumed by some authors in certain pathological states and in particular in acute nephritis. They view the latter not as a local kidney disease, but as a disease of the capillaries of the entire body, leading to an increase in resistance to blood flow in them (Frank, Kylin). Such a point of view is not yet generally accepted, and the possibility of a rise in arterial pressure as a result of changes in capillaries has not been elucidated. In comparison with the lumen of arterioles and capillaries, other factors that could affect the magnitude of friction and consequently BLOOD PRESSURE
sequently, for the resistance to the outflow of blood from the arterial system, they are of no essential significance, since they can easily be compensated by a change in the lumen of small vessels. Thus, in particular, blood viscosity has no effect on blood pressure when the vasomotor apparatus correctly regulates the lumen of small vessels. The level of arterial pressure gives no opportunity whatsoever to judge the useful work of the heart, the speed of circulation, the degree of blood supply to tissues, and the minute volume of blood in particular. The amount of blood pumped by the heart per unit of time into the aorta can be large even at low pressure (e.g., in anemia) and small at high pressure (e.g., in hypertension with cardiac insufficiency). Conversely, at high arterial pressure, the minute volume of blood can be large (e.g., during heavy physical labor) and at low arterial pressure small (e.g., in vascular insufficiency). A high level of arterial pressure only gives the right to judge that the left ventricle ejects a certain amount of blood into the aorta with each contraction, but it is completely impossible to judge this amount on the basis of the level of maximum and minimum arterial pressure separately. Some idea of this amount is rather given by the pulse pressure, since its magnitude undoubtedly depends on this stroke volume. But since the magnitude of the pulse pressure is also determined by the second factor, specifically the elasticity of the walls of the central arteries, one can judge the magnitude of the stroke volume from the pulse pressure only by taking this second factor into account, which, however, is far from easy. Nevertheless, a high maximum arterial pressure and a large pulse pressure give the right to assume a heart muscle contracting with considerable force; but we still do not have the right to assume that such a muscle is completely healthy, since an altered heart muscle, yet working with all its reserve force, can maintain a high arterial pressure for a certain time. If a high arterial pressure persists for several weeks, one can assume the presence of left ventricular hypertrophy. All attempts by comparison in the form of formulas (Strassburger, Erlanger, Nikolayev, Kabanov, and others) to extract more precise indications of the functional state of the circulatory organs from the data of blood pressure measurements (maximum, minimum, and pulse pressure) and pulse rate have not proven justified in practice and are theoretically incorrect, since for the above-stated reasons, blood pressure and pulse rate do not give the right to judge the adequacy or inadequacy of circulation. The level of minimum arterial pressure depends mainly on the rate of blood outflow from the arterial system. This rate of blood outflow is determined first of all by the width of the lumen of the small arteries. Consequently, the minimum arterial pressure gives some right to judge the degree of tonic contraction of the peripheral arterial musculature. When assessing the significance of pathological changes in arterial pressure, it is necessary first of all to take into account the influence on it of the heart rate. It has an effect on arterial pressure in the sense that maximum arterial pressure decreases with an increased pulse rate, minimum pressure increases, and pulse pressure decreases. In bradycardia, opposite changes in these values are observed. The effect of bradycardia on arterial pressure is especially characteristic in transverse heart block, when the maximum pressure is increased, the minimum decreased, and the pulse pressure increased to a significant degree. The indicated influence of pulse rate on the maximum, minimum, and pulse pressure takes place, of course, only under otherwise equal conditions and, in particular, if the amount of blood pumped by the heart into the aorta per unit of time does not change. A certain height of the blood pressure level is usually attributed to the so-called physiological constants, i.e., to such constant physiological phenomena that are necessary for the proper function and life of the entire organism. In this respect, blood pressure is compared with body temperature. This comparison is quite appropriate, since indeed significant deviations of arterial pressure from the normal level, just like significant changes in body temperature, are incompatible with life. And just as the organism tolerates significant rises in body temperature relatively easily, it also easily tolerates significant increases in arterial pressure, even increases of it to double the normal, whereas corresponding drops in arterial pressure, as well as significant decreases in body temperature, are not observed or are observed only shortly before death. In general, however, arterial pressure under various physiological and pathological conditions gives fluctuations, and often very significant and prolonged ones. Regarding long-term changes in arterial pressure both in the direction of increase and in the direction of decrease, see Hypertension and Hypotension; regarding changes in arterial pressure in arteriosclerosis, see Arteriosclerosis; in nephritis, see Nephritis. Pathological changes in arterial pressure. Short-term increases in arterial pressure are observed with strong pain sensations, with asphyxia, lead colic, tabetic crises, in some cases of angina pectoris during the attacks themselves (angina pectoris vasomotorica), in the so-called vascular crises of Pal (see Crises), with an increase in intracranial pressure, under the influence of epinephrine injections, and so on. Short-term decreases in arterial pressure are observed in humans with vascular insufficiency, with collapse (see Circulation, pathology), after heavy blood loss, with acute weakening of cardiac activity. All indicated acute rises in arterial pressure are the result of a rapid increase in the tone of the arterial musculature, predominantly of central origin. With acute drops in arterial pressure, as they are observed in the most pronounced form in collapse, there is, conversely, a decrease in the tone of the arterial musculature, predominantly in the region of the abdominal viscera. In this case, the dilatation of capillaries of the same region, caused by the influence of substances acting similarly to histamine directly on the capillaries, may also participate or even have main significance; the plexuses of small veins also participate in the dilatation of vessels; the so-called reserve blood reservoirs are filled (see Circulation). Large losses of blood lower arterial pressure apparently not by a direct decrease in the blood mass, but by causing a paretic state of the vasomotor centers through the disruption of their blood supply. Blood loss up to 1/2 liter in humans usually does not cause a drop in arterial pressure. In general, even relatively large changes in the total blood volume, as experimental observations show, do not significantly change arterial pressure as long as the vasomotor nerve apparatus responds normally. Thanks to it, the vascular system, by changing the tonic contraction of its musculature, quickly changes its capacity without letting blood pressure drop or rise. Among the clinical facts proving the ability of the circulatory system to adapt without a change in arterial pressure to fluctuations in the total blood volume, one can point to polycythemia and the algid period of cholera, which as a rule are not accompanied by significant changes in arterial pressure. Drinking large amounts of quantities of fluid with a normally functioning vasomotor apparatus also does not cause significant changes in arterial pressure. But in hypertensive states, when the vasomotor apparatus does not respond normally, drinking 1 to 1.5 liters of water, for example, during the so-called water test to determine the functional abilities of the kidneys, often gives very strong rises in arterial pressure. In valvular heart defects, in arteriosclerosis of the heart, arterial pressure is on average somewhat below normal. If cardiac insufficiency develops in these diseases, the pressure does not change or rises slightly. This latter phenomenon was noted by Sahli (Hochdruckstauung). With an improvement in cardiac activity, arterial pressure in these cases decreases somewhat. The absence of a drop in arterial pressure or even a certain increase in it despite the insufficiency of heart work, i.e., despite the decrease in the minute volume of blood, is explained, as already indicated, by the corresponding vasomotor reaction. A strong drop in arterial pressure in diseases of the heart itself is usually observed only shortly before death or upon the addition of vascular insufficiency, for example, upon the addition of one or another infectious process. The only exception in this regard among the diseases of the heart itself is acutely developing myocardial infarctions due to coronary artery thrombosis; their development is accompanied by a strong decrease in arterial pressure, which does not correspond to the temperature rise usually observed in these cases. Edemas do not affect the level of arterial pressure. Ascites, in general the accumulation of fluid in the abdominal cavity and an increase in intra-abdominal pressure, undoubtedly cause an increase in arterial pressure. With compensated valvular heart defects, the pulse pressure exhibits partly typical
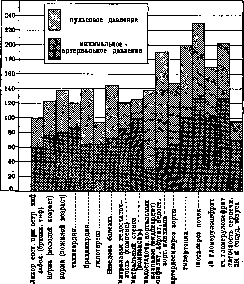
Figure 9. Scheme of changes in arterial pressure under various pathological conditions (in mm of mercury).
changes that also have diagnostic significance. Thus, in pure mitral stenosis, the pulse pressure is as a rule decreased, and the degree of this decrease, other things being equal, is proportional to the degree of stenosis. In aortic insufficiency, on the contrary, an increase in pulse pressure is highly characteristic, mainly due to a decrease in the minimum arterial pressure. This increase in pulse pressure is usually more pronounced in aortic insufficiency of endocarditic origin than in aortic insufficiency of syphilitic or arteriosclerotic origin. The increase in pulse pressure in aortic insufficiency is explained by the fact that the systolic volume of blood is increased and the outflow of blood from the aorta is enhanced due to the reflux of part of the blood from the aorta back into the left ventricle. The degree of increase in pulse pressure in aortic insufficiency also makes it possible to assess to some extent the magnitude of the insufficiency (Figure 9). Vascular insufficiency (see Blood circulation, pathology) is accompanied by a drop in arterial pressure. In its most pronounced form, as already indicated, it is observed in collapse and anaphylactic shock. In the clinic, vascular insufficiency is observed as a rule in infectious diseases; in typhoid and typhus fevers and in severe influenza, it is most pronounced and gives the decrease in arterial pressure characteristic of these diseases in the period of the most severe condition and in the period of temperature drop. In this case, the pulse pressure is also decreased. At the onset of infectious diseases, arterial pressure may even be somewhat elevated, especially during chills. Among chronic infectious diseases, tuberculosis is distinguished by a tendency towards a decrease in arterial pressure. This decrease usually corresponds to the degree of pulse acceleration. Among diseases of the endocrine glands, Addison's disease gives a characteristic decrease as a manifestation of insufficiency of the chromaffin system and the consequent loss of the stimulating effect of adrenaline on the vasomotor nervous system. Diseases of the thyroid gland, myxedema, and Basedow's disease also give characteristic changes in arterial pressure. For myxedema, a certain decrease in arterial pressure with a decrease in pulse pressure is typical; for hyperthyroidism, on the contrary, there is a tendency towards an increase in arterial pressure and, in particular, towards an increase in pulse pressure. These changes in arterial pressure in hypo- and hyperthyroidism are fully explained by those circulatory changes that accompany the corresponding disturbances of thyroid function: in hyperthyroidism, accelerated circulation with an increase in minute volume due to both tachycardia and an increase in systolic volume; in hypothyroidism, on the contrary, a slowing of the circulation. In severe anemias, certain changes in arterial pressure are also observed as a rule—an increase in pulse pressure with a tendency towards a decrease in the average level of arterial pressure (F. B. Greenberg). These changes are also explained by an increase in the velocity of circulation due to an increase in systolic volume with a tendency towards a decrease in vascular tone.
Blood pressure in the pulmonary circuit is significantly lower than in the systemic circuit; the average blood pressure in the pulmonary artery corresponds approximately to 1/3-1/7 of the aortic pressure; for the dog, it fluctuated in numerous determinations around 15-20 mm Hg, differing by significantly less constancy than the arterial pressure in the systemic circuit. The maximum pressure in the pulmonary artery in the dog averages 43.3 mm Hg, the minimum 11.9 (Wiggers), and the pulse pressure 24 mm Hg. The pulse pressure in the pulmonary artery is also distinguished by significant lability. The magnitude of blood pressure in the pulmonary artery, depending on the phases of respiration, fluctuates in the dog during natural breathing in such a way that at the beginning of inspiration a drop in pressure occurs, which is replaced at the end of inspiration by an increase; during expiration, the pressure po
Figure 10. rises, and only at the end of expiration or during the respiratory pause does the drop in pressure begin again. Capillary pressure—see Capillaries, physiology. II. Venous pressure. Venous pressure is measured in animal experiments using either a tube tied into a vein or a cannula inserted into a vein of such thickness that the blood flow in the vein is not disturbed. Usually, a water manometer is used, because venous pressure is so low and its fluctuations are so small that they cannot be accurately measured with mercury manometers. Frequently, for the same reason, venous pressure is expressed in mm of water column (to convert to a mercury column, it is necessary to divide by 13.5). In humans, venous pressure is measured either by a direct (cruent) or indirect method. The first method, proposed by Moritz and Tabora, is entirely analogous to the experimental method for determining venous pressure in animals. As there, it is necessary to pay special attention that the site of the vein where the venous pressure is measured is exactly at the level of the right atrium; this is necessary to exclude the influence of hydrostatic pressure, which, with generally low venous pressure, has a most essential influence on the height of the latter. In humans, venous pressure by the cruent method is usually measured in the veins of the cubital fossa. Non-cruent, or indirect clinical methods for measuring venous pressure are based on the principle of determining the external pressure required to cause the collapse of a superficial vein. The most common method consists in hermetically fitting a bottomless capsule with a glass lid over a superficial vein of the arm and increasing the pressure in this capsule until the vein collapses. The pressure in the capsule is measured by a water manometer attached to it. The magnitude of venous pressure in the dog is represented by the figures obtained by Burton-Opitz (see table).
Venous pressure in the dog (according to Burton-Opitz). mm Hg
fem. dextra. . 0,4 »
saphena sin. . »
renalis .... 5,4 7,4 3,9 8,9 14,7 10,1 10,9 V. facialis sin. . . » jug. ext. sin. . » » » dextr. . . 0,1 » cav. sup. (peripheral segment) . . . 1,4 » cav. inf. (central part) .......2,8 » fem. sin.......5,4 When measuring venous pressure under normal conditions using direct and more advanced methods, the following figures were obtained (see table). In the veins of the lower extremities, venous pressure in the recumbent position does not differ significantly from the venous pressure in the veins of the antecubital fossa; in the standing position it increases significantly, but data regarding the degree of this increase diverge. Under complete rest and other equal conditions, the venous pressure in one and the same individual represents an almost constant value. Age and sex have no significant influence on venous pressure. Muscular work as a rule increases it, and this increase can reach 100%. The negative pressure inside the thoracic cavity, the so-called Donders pressure, has a significant influence on venous pressure. As a result of opening the thoracic cavity in Burton-Opitz's experiment, the pressure in the superior vena cava of a dog rose from - 30 mm of water to + 32.4, i.e., by 62.4 mm H2O. Correspondingly, respiratory movements cause significant fluctuations in venous pressure, the magnitude of these fluctuations being directly proportional to the depth and speed of the respiratory movements. But these respiratory fluctuations in venous pressure are expressed only in the central veins; here they reach 70 mm H2O, and during inspiration a negative pressure is produced in these veins, which, as is known, can cause air aspiration into the vena cava when it is opened. In the veins of the lower extremities, the respiratory fluctuations of venous pressure have a character exactly opposite to those observed in the upper half of the body, i.e., in the veins of the lower extremities, venous pressure rises during inspiration and falls during expiration. This is explained by the fact that the inferior vena cava during inspiration is under increased intra-abdominal pressure. Towards the periphery, the respiratory fluctuations of venous pressure are smoothed out relatively quickly, and in the antecubital vein during normal breathing with a wide cannula (greater than 0.5 mm in diameter) they do not exceed 0.5-2 mm H2O, and with the strongest breathing - 5-8. If under normal conditions an increased inspiratory movement cannot cause a corresponding decrease in venous pressure in the veins of the antecubital fossa, then prolonged difficulties in the entry of air into the lungs, as we observe them in pulmonary emphysema, in pleural adhesions, in rigidity of the chest wall, in kyphoscoliosis, etc., by lowering Donders' pressure, can significantly lower the venous pressure measured in the peripheral veins. This factor, which significantly influences the level of venous pressure, must be taken into account when evaluating other pathological deviations of venous pressure (Kroetz). In general, the level of venous pressure is determined primarily by the difference between the level of blood pressure in the capillaries and the level of blood pressure in the right atrium. The level of blood pressure in the capillaries depends on the central arterial pressure and on the lumen of the precapillary arteries and capillaries or on the total number of open capillaries. This latter factor—the degree of opening of the precapillaries and capillaries, varying in various organs and departments depending on their functional state—can determine a different level of venous pressure in the corresponding peripheral veins. During muscular work, to this factor, which locally increases venous pressure, is added the influence of the mechanism of muscular contractions and venous valves. The level of pressure in the right atrium depends on the relationship between the inflow of venous blood to the heart and its functional capacity, measured by the amount of blood pumped by it per unit of time further into the pulmonary artery. Another main factor determining the level of venous pressure is the degree of tonic contraction of the venous musculature. The smaller this tone, the greater the total lumen of all veins and the lower, other things being equal, the venous pressure will be. Apparently, the venous system, presenting—especially in the periphery—numerous and richly developed networks, possesses the ability to vary its capacity within very wide limits, and correspondingly the amount of blood contained in it can also vary. A part of these venous plexuses can apparently to a certain extent, by narrowing the corresponding branches, become isolated from the main venous branches and trunks. This must also, by changing the amount of circulating blood, influence blood pressure in general and venous pressure in particular. The tone of the venous musculature, just like the arterial musculature, is determined by the chemical composition of the blood, in particular its CO2 content (Henderson), and partly by vasomotor innervation. All these numerous and complex factors determining the level of venous pressure are still not amenable to sufficiently precise calculation, and therefore the pathogenesis of changes in venous pressure observed in various pathological states does not always lend itself to exact analysis. It has been most definitely ascertained that cardiac insufficiency is accompanied by an increase in venous pressure. This increase goes more or less parallel to other manifestations of blood stasis in the systemic circulation, enlargement of the liver, renal stasis, edema, etc. It is most sharply expressed in patients with mitral valve defects, in whom during decompensation the venous pressure rises to 200-312 mm H2O; followed by arteriosclerotic cardiosclerosis and aortic insufficiency. During compensation, mitral defects yield an average figure of 103 for venous pressure, cardiosclerosis—72, hypertension—78, syphilitic aortitis—70, aortic insufficiency—66 mm H2O. Of particular note is the fact that in heart diseases, the level of venous pressure in each case changes, as a rule, under other equal conditions, in strict proportion to the degree of decompensation. Curves (Pavlovskaya and Soboleva) (Figure 10) give an idea of these fluctuations and corresponding changes in other manifestations of heart failure. Eyster points out the practical significance of measuring venous pressure in order to establish more precise indications for bloodletting in severe heart failure and to control the effect of this therapeutic method. Bloodletting of 350-600 cm3 gives in suitable cases of heart failure an immediate decrease in venous pressure by 100-200 mm H2O. The effect of vascular insufficiency on venous pressure has been studied in less detail (see Circulation, pathology). But on the basis of existing experimental observations and clinical data, for pure vascular insufficiency, along with a drop in arterial pressure, a drop in venous pressure is also particularly characteristic. Thus, in histamine shock (see Circulation, pathology) and in severe acute infectious diseases, a drop in venous pressure is observed as a rule; towards the end of typhoid fever, for example, the venous pressure usually drops to 20-40 mm of water column (Waldmann).
Lang. III. Blood pressure in children. Arterial blood pressure in children generally obeys the same conditions as in adults; its height fluctuates at lower figures, but the fluctuations themselves are more significant, which is explained by the influence of the nervous system, increased reflex excitability of the vascular musculature, further by the influence of hormones of the endocrine glands, which are in the period of growth and development, and in particular by the change in anatomical and functional correlations between the heart and the vascular system during the period of the child's growth. The gradual increase in arterial blood pressure with the growth of the child may depend partly on the increase in the strength of the heart muscle (Benjamin). In determining arterial blood pressure in children, the same methodology and apparatus as in adults are generally used. As for the sound method of Korotkov, it is fully applicable in children, and with skill and some patience can give sufficiently reliable figures of systolic blood pressure even at a very earliest age; as for diastolic blood pressure in very small children, this is far from always successful. In infants, a cuff with a width of 41/2-6 cm is used, in older children a wider one, but not wider than 12 cm. The state of excitement of the child - crying, screaming, movements - produce a short-term but quite significant increase in arterial blood pressure, while food intake, as well as the transition from a sitting position to a lying position, do not have a special effect; during sleep, blood pressure is usually somewhat lowered. To avoid errors, several determinations of blood pressure should be made in a row and the average taken: it has been noticed that during subsequent measurements the figures are somewhat lower. Arterial blood pressure in newborns fluctuates, according to Seitz, between 175 and 100 mm Hg; according to Neu, it is on average 90 mm (Gartner's apparatus); on average it is 80 mm Hg. Blood pressure in premature infants is even lower; according to Trumpp, it does not exceed 60-70 mm Hg. With age, arterial blood pressure increases. This increase, proceeding unevenly, is most intense in the 1st year of life: during this period the addition is the same as for the subsequent 12 years of life. In addition to infancy, the greatest intensity of blood pressure increase falls on the age from 6 to 10 years. According to Popov, arterial blood pressure on average increases by 2 mm monthly during the 1st year, reaching 100 mm by the end of it. Bauchwitz, Trumpp, Feer, Bruning, Rominger and others give an average figure of 80 mm up to 6 months of age and 90 mm up to 2 years. Systematic studies of arterial blood pressure in healthy infants gave the following average figures (according to Korotkov): from 3 to 6 months - 84.7 mm Hg, from 6 to 12 months - 92.5 mm Hg, from 1 to 2 years - 97.5 mm Hg. The amplitude of fluctuations in this case is significant; thus, blood pressure at the age of 3 to 6 months fluctuates between 73 and 100 mm; from 6 to 12 months between 81 and 100 mm, from 1 year to 2 years - between 85 and 105 mm (Sokolov and Rozental). The figures of blood pressure in older children can be taken from the summary of data by Potain, Nobecourt and others, obtained by Potain's apparatus. All these data relate to the brachial artery. When measuring blood pressure in the digital arteries with Gartner's apparatus, lower figures were found: in infancy - from 64 to 82 mm, from 1 year to 16 years - 82-108 mm (Trumpp, Sladkov). There are formulas for calculating the average height of arterial blood pressure for a given age; thus, Katzenberger gives a formula (up to 13 years of age): 80 + 2x, where x is the number of years. This formula, however, does not give sufficiently correct figures, especially for an early age. According to Popov, the blood pressure of children up to 1 year can be determined by the formula: 76 + 2n (n is the number of months of life). Maslov gives the formula: 100 + n, where n is the number of years. As for the minimum, diastolic blood pressure, by the end of the year it averages 49 mm, reaching 88 mm by 15-16 years (Maslov). Determining it in small children is associated with technical difficulties and is not always reliable. It can be considered that in healthy infants it is not subject to large fluctuations and is approximately equal to 35-45 mm (data of Rozental according to Korotkov method). Pulse pressure in early age is relatively large - approximately 50-60 mm; with age it decreases. Arterial blood pressure experiences a decrease or increase in a wide variety of diseases; thus, sharp drops in blood pressure are described with significant dehydration of the body, with jaundice, anaphylactic shock, etc.; low blood pressure during diphtheria, indicating myocardial damage, serves as a poor prognostic sign. An increase in blood pressure takes place in pneumonia, meningitis, etc.; it is especially persistent in chronic nephritis, in acute glomerulonephritis, in scarlet fever, where this phenomenon may be one of the early signs of kidney damage. It must be emphasized, however, that in the same disease, blood pressure can turn out to be increased, normal, and even lowered, depending on how much the mechanisms on which blood pressure depends are involved in the suffering; for example, in a child with pneumonia, blood pressure is often increased; but if (as often happens with the so-called cardiac form of pneumonia) there is simultaneously damage to the heart muscle or paresis of the precapillary network, then blood pressure may be lowered. However, certain pathological conditions are characterized by persistent changes in blood pressure; for example, in physically and mentally retarded children, blood pressure is lowered (Strokova); low blood pressure figures are apparently characteristic of lymphatic children; in neuropathics and spasmophilics, on the contrary, it is rather higher than normal. Likewise, in children with exudative diathesis, with and without eczema, blood pressure often gives persistent increases. Venous pressure in small children has not yet been studied. Capillary pressure (according to Frontali; Kylin's apparatus) for infancy fluctuates between 100 and 160 mm of water column, from 2 to 10 years - between 90 and 160 mm. A. Sokolov.
Related articles
Mentioned in
Cite this page
“Blood Pressure.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/blood-pressure/