Torsion Spasm
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This 1930s encyclopedia article discusses torsion spasm (torsion dystonia, dystonia musculorum deformans), a chronic progressive neurological disease characterized by abnormal muscle tone and peculiar involuntary movements. It covers the history of its clinical description, symptomatology, types of involuntary movements, disease course, familial and hereditary factors, and ethnic distribution.
Encyclopedia article (1928–1936)
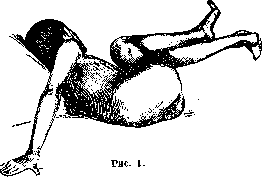
TORSION SPASM (torsion neurosis of Ziehen, dystonia musculorum deformans or dysbasia lordotica progressiva of Oppenheim, torsion dystonia, progressive torsion spasm of children, pallidum spasmus) is a chronic progressive disease, the most characteristic symptoms of which are changes in muscle tone and peculiar involuntary movements. The first description of this disease belongs to Schwalbe and Ziehen (1908–10), who considered it, as indicated by the name they gave it, "tonic torsion neurosis," to be a severe functional disorder. In 1911, Oppenheim first pointed out the organic nature of this disease; in 1919, a major comprehensive work by Mendel appeared, covering 33 cases of torsion spasm and summarizing the knowledge on this subject at that time. Subsequently, important works were published by Flatau and Sterling, Bregman, Frenkel, Thomalla, Foerster (Flatau, Sterling, Frankel, Thomalla, Forster), Davidenkov, and others. Movements in torsion spasm represent, according to Mendel, a mixture of choreatic, athetotic, tic-like, hemiballistic, and parkinson-like movements, resembling in part each of these diseases, but not completely coinciding with any of them. Especially typical are rotational movements of the trunk and extremities, to which torticollis-like curves of the neck are often added. Into these pulling-rotational movements, which proceed rather monotonously, jerk-like and throwing movements suddenly break in, leading to peculiar, bizarre, elaborate postures of the body, abduction of the upper extremities, aimless liftings of the trunk, leg, etc. (Fig. 1). Violent movements are most pronounced in the proximal joints, but the distal ones are not free from them either; they reach their greatest development, however, in the trunk. In this connection, significant lordosis, scoliosis, and pelvic displacement can develop, caused by abnormal muscle tension, which almost completely disappears at rest. In some muscles, a tendency to prolonged tonic contractions is observed, whereas in others, hypotonia is often noted, frequently associated with a decrease in tendon reflexes.
The disease usually begins at the age of 10 to 13 years, sometimes earlier, less often in adolescence. The first phenomena are usually observed in one of the lower extremities, sometimes in both, less often in the upper extremity or cervical musculature. Very rarely, crossing upper and lower extremities are affected at the beginning. Often at the beginning of the disease, gait disorders are noted in the form of clumsiness, in which convulsive states may play a certain role. At rest, as well as during distraction, violent movements usually weaken or disappear completely. During sleep and in hypnosis, they cease. In severe cases, however, convulsive states are also observed at rest, most strongly expressed in the spine in the form of extreme extension, flexor spasm, etc. The facial muscles are usually not affected, but some authors (Maas, Wartenberg, and others) noted violent movements in them as well; others, on the contrary, note amimia. Spram-like movements in general have an uneven character; they are not identical in different parts of the body, nor are they rhythmic. In many cases, patients are able to suppress both violent movements and the propensity for hypertonia by adopting peculiar, sometimes very bizarre postures, in which they prefer to remain. In some cases, movements that are usually impossible are performed quite easily under resistance or under the influence of various irritations (sensory, electrical), under pressure, etc. Pyramidal symptoms, pareses, disorders of sensitivity and pelvic organs, and epileptiform convulsions are not observed. Plastic tone is normal. Sometimes, however, paresis of the lower branch of the facial nerve and the Babinski sign (Davidenkov) were noted, occasionally nystagmus, dysarthria, dysphagia, attacks of convulsive laughter, tremor, and also pain. Some authors noted phenomena of the so-called paradoxical kinesia, when patients could, for example, unexpectedly walk well backwards or dance, play ball, etc. In some cases, unilateral development of symptoms was observed. The psyche does not suffer; sometimes patients even show a very high intellectual development. A sharp delimitation of the disease picture on the basis of clinical symptoms cannot be made at present. Rosenthal points out that at the height of its development, the disease in individual cases shows significant deviations. According to this author, two types of torsion spasm can be distinguished. In the first, position anomalies, especially of the head and trunk, come to the foreground, standing out sharply during walking (Fig. 2) and standing. Rosenthal calls this type the dysbatic-dystatic form of torsion spasm. In the second type, general restlessness with or without the participation of facial muscles is noted mainly. In view of the proximity of this picture to double athetosis, Rosenthal, on the basis of his latest research, is inclined to consider it an idiopathic form of double athetosis. Almost all cases described earlier belonged to Jewish families originating from Poland, Galicia, and the western regions of the USSR. In recent years, however, cases of demonstrably non-Jewish origin have been encountered. Thus, the disease has been observed in Frenchmen, Germans, Danes, Swedes, Brazilians of both pure origin and mestizos, Argentines, and North Americans. There are indications of the significant frequency of this suffering in North America (Austregesilo).
For a long time, this disease was not considered hereditary. Mendel in his monograph points out that heredity apparently plays no role in the etiology of this disease, and in the review by Austregesilo and Marques (1928), nothing is said about the heredity of this disease at all. In reality, however, quite a few cases of the familial appearance of this affliction have been described. In addition to the cases of Schwalbe-Ziehen and Bernstein, familial cases have been described by Dzerzhinsky, Wechsler-Brock, Davidenkov-Zolotova, Mankovsky-Cherny, Regensburg. In the majority of cases, it is a matter of disease in children of healthy parents, and heredity thus has a recessive character. Those few cases where the form of inheritance was dominant had a clinically atypical character. Thus, one has to come to the conclusion that at present the existence of a recessive clinically pure group of cases of torsion spasm has been precisely proven (Davidenkov). Sometimes various anomalies were noted in healthy relatives. Thus, alcoholism, schizophrenia, hemiplegia, migraines, and psychopaths were observed. In others, symptoms suspicious of a mild manifestation of the same gene are sometimes encountered, for example, tremor, tics, violent movements, etc. (Davidenkov).
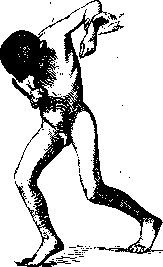
The nature of the disease is unknown. It is undoubtedly an organic disease, most likely in the area of the subcortical ganglia. Ferster assumes the isolated loss of certain inhibitory elements of the striatum for certain muscle groups, due to which the corresponding elements of the pallidum are disinhibited, while others are inhibited. The prognosis quoad vitam is favorable. In general, the disease gradually progresses, but significant remissions are noted. Usually, the disease, after reaching a certain stage of development, stops. Patients can reach a very advanced age, for example, one of Regensburg's patients was 71 years old. Wimmer drew attention to the fact that many cases ended with extrapyramidal immobility with Parkinsonian tremor. The pathological-anatomical picture of T. s. is far from being clarified. The number of autopsies is small and their data have not led to uniform results. In the cases of Tomall (atypical) and Wimmer, cirrhosis of the liver and changes in the striatum, observed in diseases of the Wilson group, were found. Tomall found necrotic phenomena in the striatum, the putamen appeared macroscopically shrunken and softened, the fibers of the corpus Luysii were poor and it was reduced in size. In Wimmer's case, a macroscopically normal brain contained Figure 2. v25 diffusely located Alzheimer's i cells, mostly in the striatum. Other authors also saw changes typical of hepatolenticular degeneration. Richter, however, found changes in the same areas as in Tomall's case, but having the characteristic of chronic progressive chorea (death of striatal cells without predominant damage to small cells with indistinct proliferation of glia with less severe changes in fibers). Intensive cellular changes were also found in the case of Marinescu-Nicol escu. Bels hovsky in the case of Cassirer found phenomena of brain edema, expansion of perivascular lymph spaces, and swelling of myelin. In the ganglion cells - phenomena of disintegration. All changes are equally expressed in the cerebral cortex and in the striatum. Thus, it can be considered established that the anatomical basis of T. s. cases can be different processes, and therefore it must be assumed that there are symptomatic and genuine forms independent of each other, and the external similarity can be so complete that it does not allow them to be separated from each other (Davidenkov). This situation has led to the fact that at present, authors adhere to opposite points of view on this issue. While some (Wimmer) do not recognize T. s. as a disease sui generis, others (Lotmar) consider it a completely independent disease. Sterling considers it necessary to separate the cases of T. s. sui generis from symptomatic forms and proposes the term dystonia for the first, and dystonism for the second. - Diagnosis in general is not difficult. Differential diagnosis must keep in mind chorea, paralysis agitans, Wilson's disease, double athetosis, hysteria, and epidemic encephalitis. Against double athetosis speaks the usual onset in one limb, the peculiar rotational character of the forced movements, the predominant involvement of the trunk, the non-involvement of the face, normal intellect. In the diagnosis, nationality may also be of importance. Against hysteria speaks the uniformity of motor disorders, against other diseases - the characteristic symptoms of the latter. - Therapy is fruitless. Hypnosis sometimes gives transient improvement. Sometimes surgical intervention in the sense of tendon lengthening gives some effect. Regensburg applied daily systematic injections in combination of 0.0003-0.0005 scopolamine and 0.003-0.005 morphia and thereby achieved complete rest and normal gait. Upon cessation of treatment, however, the forced movements reappeared.
I. Prishmin.
Related articles
Mentioned in
Cite this page
“Torsion Spasm.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/torsion-spasm/