Tablets
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article describes the production, advantages, and disadvantages of medicinal tablets as a dosage form in the 1930s. It covers the technical aspects of tableting, including granulation and the use of excipients, as well as storage requirements and alternative forms like lozenges and gelatin lamellae.
Encyclopedia article (1928–1936)
TABLETS (from Latin tabula—small board, tile), a dosage form obtained by compressing powders. At present, tablets occupy a dominant place among dosage forms of mass (factory) preparation, accounting on average for up to 40% of all prescriptions. The manufacture of tablets in artisanal conditions is possible by manually compressing weighed
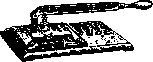
Figure 1.
doses of powders in a special (usually lever-operated) press (Fig. 1), developing a pressure of up to 100 kg per 1 cm2. In mechanized production, where individual doses are not weighed but measured by a machine at a speed of up to 10 doses per 1 second, the powders must be appropriately prepared. Only a few powders, easily soluble in water and possessing a crystalline form, can be pressed directly. All other substances, and especially mixtures of powders, must be subjected to the following operations: 1) binding the material into uniform-composition and even granules (granulation) (Fig. 2); 2) adding disintegrating (swelling) substances (starch, gelatin, dried yeast, pectin, casein, agar-agar, etc.), which ensure the rapid disintegration of tablets in water; 3) adding lubricating substances, which ensure the uniform sliding of the powder in the measuring devices of the machines, without which the tablets, during the rapid operation of the machine, would result in different

Fig. 2. Granulating machine.
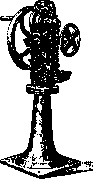
Fig. 3. Tablet-making machine.
weights. As lubricating substances, the Pharmacopoeia of the USSR (FUP) permits talc. Tablets possess a number of advantages over powders. 1) The possibility of mechanizing the tableting process (Figs. 3 and 4). Modern machines produce up to 400,000 tablets per working day with one operator; from this follows the economic profitability of the work. 2) Cleanliness and hygiene of the work. In the production of tablets, manual labor and such procedures as kneading pills, filling powders into capsules, etc., are eliminated. 3) Significant accuracy of dosage; fluctuations in weight for tablets are permitted only within the limits of ±2%, while for powders and pills they are set at ±5%. 4) Compressed medications occupy less volume; they are portable, and it is convenient to use them in the army, while traveling, etc. A pharmacy, having ready-made tablets, can dispense medicine to a patient without delay. A doctor can carry a set of compressed medications when visiting patients, which is significant, for example, in rural areas remote from centers. 5) The composition of compressed tablets is less exposed to the harmful influence of external conditions, e.g., moisture, air, light, dust, etc. Apomorphine, diuretin, and other medications are preserved better in tablets than in powders. 6) When taking tablets, the unpleasant or bitter taste characteristic of certain medicinal substances (e.g., quinine) is significantly weakened. P
surface of the tablet can, in addition, be covered with various protective coatings, e.g., sugar, chocolate, gelatin, salol, etc. 7) In the form of tablets, one can also administer many preparations that cannot be turned into powder at all or are difficult to turn into pills. 8) On tablets, one can press inscriptions that replace labels, which eliminates one of the possibilities for errors (Fig. 5). Among the negative aspects of tablets, the following should be included: 1) with improper manufacture, many tablets do not disintegrate in the gastrointestinal tract (this is eliminated by the correct selection of the tableting formula and careful work); 2) children and many adults do not know how to take tablets; 3) many preparations cannot be taken in the form of tablets because, when taken in a dry or concentrated form, they can cause irritation in the stomach (e.g., potassium iodide, potassium bromide, sodium bromide, etc.) and even cauterization of the mucous membrane (salicy
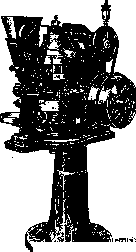
Fig. 4. Rotary machine. ...licylic acid); such preparations can be dispensed in tablets on the condition that they will be dissolved in water; 4) many medications cannot be directly converted into tablets, e.g., tinctures, liquid extracts, etc.; these preparations can, however, in most cases be dried, and the dry residue converted into tablets; 5) with many tablets, various extraneous (ba
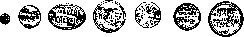
Fig. 5.
llast) substances, e.g., starch, talc, sugar, etc. The technical criterion for the suitability of tablets is their solubility or complete and rapid disintegration in water. Uncoated tablets must dissolve or disintegrate in warm water (36–37°) with agitation within no more than 5 minutes. Coated tablets, with the exception of those coated with keratin, must dissolve or disintegrate at 36–37° with agitation within no more than 30 minutes. A very important drawback of tablets is that the physician does not exactly know either the composition of the tablets or their physical properties (disintegrability, quality of binding, disintegrating, and lubricating additives, fineness of the powders included in the composition). When working on high-speed machines, the pressing parts heat up noticeably. This heating depends to a certain extent on the degree of tightening of the compressor (the device regulating the pressure during compression); sometimes it can bring the compressed material to fusion (salol); such tablets are extremely difficult to disintegrate and, especially in gastric diseases (ulcer!), can cause significant harm. It is also necessary to mention that some compositions in tablet form spoil faster (e.g., a mixture of Aspirin + Coffein. natr.-salicyl.) due to the close contact of mutually reacting components. A very important role in ensuring the value of tablets is played by the method of their storage. Tablets must be stored in a dry place at ordinary temperature in well-stoppered glass jars or tubes. Many tablets harden upon contact with air and lose their ability to disintegrate in water. Tablets made from insufficiently dried materials or stored in a damp place often become damp or swell by themselves or crumble upon shaking. Therefore, tablets, more than powders, require storage in well-stoppered vessels and as much dryness as possible. When prescribing tablets, it is often recommended to either dissolve or crush them upon administration. Along with tablets, other forms for replacing dosed powders have been proposed; among them should be noted: 1) lozenges (pastilles, pastillae, or trochisci), obtained by cutting or forming from a dough-like mass; 2) sugar discs (rotulae), made by pouring drops of boiling, highly concentrated sugar syrup onto cold tin or marble, followed by moistening such lozenges with a solution of the medicinal agent and further drying; 3) gelatin lozenges, obtained by pouring a thick gelatin jelly containing an admixture of the medicinal agent onto a board divided into equal parts; upon solidification, rectangles are obtained (if they are very thin, they are called lamellae), containing exactly equal doses of the medicinal substance and easily soluble in warm water. Such lamellae are common in the USA and England, where they are especially used for insertion into wounds, into body cavities, onto the conjunctiva of the eyes, or for preparing eye drops or injection liquids at the patient's bedside or in outpatient practice. A patented form of this kind has been released in Germany under the name Gelonida; under the same name, powders in gelatin capsules have also been released.
I. Oberhard. TABOPARALYSIS, taboparalysis. Given the common syphilitic origin of tabes and progressive paralysis, a combination of both forms in the form of T. is often observed. The somewhat inaccurate position of Möbius that progressive paralysis is tabes of the brain, and tabetic-paralysis of the spinal cord, forms the basis of the view that T. is a homogeneous process spread in both the brain and spinal cord. On this basis, the diagnosis of T. is made in all cases of complication of paralysis with spinal cord symptoms resembling tabes. However, this approach requires corrections. It is undeniable that in progressive paralysis, spinal cord damage is a frequent phenomenon, but it cannot always be identified with tabes. The paralytic changes in the spinal cord in T. are more diffuse, less selective, and as a rule do not have such a slow chronic course as in tabes. If sometimes in progressive paralysis predominant damage to the posterior columns is observed, then unlike tabes, the damage is localized not only in the exogenous, originating from the root systems, but also in the endogenous pathways (ventral field of the posterior columns, Redlich's dorso-medial bundle, Flechsig's main field, etc.). In general, the spinal cord changes in progressive paralysis are partly the result of secondary degenerations (due to damage to nerve cells in the brain). At present, only those cases should be classified as T. when clinically tabes with all its characteristic symptoms precedes the development of progressive paralysis (often by many years). Theoretically, of course, the simultaneous onset of both forms and even a later onset of tabes is possible, but in such cases, due to the more rapid and malignant course of progressive paralysis, the latter dominates too much in the picture of the disease, and the slower tabetic process does not have time to fully develop. From the standpoint of symptomatology, T., in addition to the presence of tabetic phenomena (ataxia, absence of knee reflexes, sensory disturbances, atrophy of the optic nerves), differs from ordinary paralysis by a slower course of mental degradation, more frequent hallucinations (especially optical), and paranoid delusional ideas. However, in T., other clinical forms characteristic of ordinary paralysis (expansive, agitated, depressive, etc.) are also possible. The Wassermann reaction in the fluid in T. is often less pronounced than in ordinary paralysis (a positive result sometimes only with high concentrations of fluid). The onset of progressive paralysis in a tabetic patient is often marked by a stroke. The differential diagnosis of T. may present difficulties in distinguishing it from tabetic psychoses. The latter are relatively benign, episodic, and do not have some of the characteristics of paralysis of the cerebrospinal fluid (Lange curve). The pathological anatomy of T. consists of tabetic and paralytic lesions. Treatment - as in ordinary progressive paralysis (malaria, etc.). Lit.-see lit. to the article Tabes dorsalis, Progressive paralysis.
Related articles
Mentioned in
Cite this page
“Tablets.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/tablets/