Syphilis
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This part of the comprehensive article on syphilis from the 1928-1936 Soviet Medical Encyclopedia covers its history, examining the debate between the American origin theory and the antiquity hypothesis, and its dramatic epidemic spread across Europe following the late 15th century.
Encyclopedia article (1928–1936)
SYPHILIS. Contents: I. History of syphilis ............... 515 II. Epidemiology .................. 519 III. Social significance of syphilis ........ 524 IV. Spirochaeta pallida .............,, 527 V. Pathological anatomy ........... 533 VI. Experimental syphilis ......... 536 VII. Clinic and diagnosis of acquired syphilis ...................... 545 VIII. Visceral syphilis .............. 562 IX. Treatment of acquired syphilis ...... 570 X. Personal prophylaxis ............. 588 XI. Congenital syphilis ............. 589 Syphilis (syphilis, lues, lues venerea), a chronic infectious disease caused by the pale spirochete; transmitted predominantly through sexual contact, it is one of the most important diseases in the group of so-called venereal diseases (see). Proponents of the "American" origin of syphilis in Europe (I. Bloch, H. Hauenstein) associate the emergence of syphilis with the campaign of Charles VIII in Italy (1494-95), whose army, consisting of mercenaries of various nationalities (French, Swiss, Dutch), came into contact with Spanish soldiers who arrived from Barcelona, where in 1493 they returned from a voyage with Columbus. The Spanish physician Diaz de Isla (1462-1542) points out that Columbus's sailors brought syphilis to Spain from the island of Espanola and rapidly disseminated it in the coastal cities of Spain. Charles VIII's campaign through Italy, especially his stay in Rome, where, according to Delicado, there were 14,000 Spanish prostitutes at the time, contributed to the spread of syphilis both in Italy itself and in the countries to which the mercenary troops rushed after the defeat of Charles VIII. Milan, Venice, Germany, and also Spain, which sent reinforcements by sea from Barcelona to Naples, took part in the expulsion of Charles VIII from Italy. The armies of the victors entered cities whose population had already fallen victim to syphilis, which had spread among them with extreme rapidity, since the army of Charles VIII indulged, according to historians of the time, in unbridled debauchery. By the beginning of the 16th century, syphilis had become known on almost the entire continent of Europe. The spread of syphilis in Europe was facilitated by the social shifts of the era of nascent capitalism: the ruin of the peasantry, the growth of cities, the development of trade relations and, in particular, navigation, and the proletarianization of artisans. Syphilis spread rapidly along maritime trade routes outside of Europe as well. By the beginning of the 16th century, syphilis became known throughout South and Southeast Africa, from where it was soon introduced to China and Japan (1512). The development of the syphilis epidemic was also favored by the lifestyle of the Middle Ages, its morals, the almost unlimited freedom of the sexual life of men, the presence of so-called public bathhouses, which served as places of outright debauchery, and the legalization of brothels maintained not only by private individuals but also by city communities and even the clergy. Due to these reasons, syphilis assumed an epidemic spread, which during this period was characterized not only by mass dissemination among all strata of the population, but also by a particularly severe course. The Italian physician of the time Summarina writes: "No words and no pen can depict the sufferings caused by this new disease." "Instead of a latent stage lasting for several weeks," writes W. Boeck, "between the appearance of the primary ulcer and the secondary manifestations, the primary period lasts only a few days, accompanied by headaches, tearing pains in the joints, general weakness, and insomnia; 8-14 days after infection, the head and then the trunk are covered with a rash that leaves deep ulcers or rapidly disintegrating tumors, bone destruction, and often gangrene." The relatively quickly recognized connection between this severe disease and sexual life gave reason to call syphilis the "sexual plague." Regarding the degree of spread of syphilis in this first epidemic, one can judge by the fact that from 1495 to 1497, as documented by Iv. Bloch, cases of syphilis were discovered. I. History of syphilis. The significant spread of syphilis throughout the world and the severe consequences caused by it both to individual individuals and to society prompted many historians of medicine to study the question of the time of the emergence of syphilis in Europe. This study of the history of syphilis divided medical historians into two camps: adherents of its existence among the peoples of Europe in the most ancient times and so-called "Americanists," who believed that syphilis appeared in Europe only after the discovery of America. Defenders of the first assumption were, among a number of other authors, Hensler, Proksch, Sudhoff. In their opinion, the boils and ulcers in the mouth, larynx, alopecia, eye inflammation, condylomas in the genital area, etc., described by Hippocrates can be recognized as manifestations of syphilis. Proksch in his "History of Venereal Diseases" notes as proof that Hippocrates had specifically syphilis in mind, the consistency in the description of pathological phenomena. The causal relationship between nasal lesions and genital diseases is mentioned by Dioscorides, Galen, Paul of Aegina, Celsus, although the direct causes of nasal defects are indicated neither by Celsus nor by Susruta. Just as proofs, anatomical findings are cited: the child's skull found by Parrot and the famous skeleton of Solutré. However, Virchow asserted that he did not know a single case of bone syphilis that dated back to the period preceding its first and sufficiently well-studied epidemic in Europe at the end of the 15th century. Finally, individual authors (Sudhoff) cite documents on the basis of which they judge the existence of syphilis in Europe prior to the end of the 15th century: this includes the edict of German King Maximilian I allegedly issued in 1493 on blasphemy punishable by syphilis; the protocol of a court session in Dijon in 1463 on infection with an infectious disease; and the Ordonnances des rois de France of March 25, 1493, as evidence of the presence of syphilis in Paris prior to Charles VIII's campaign in Italy. These documents have recently been studied by H. Hauenstein, who proved in his monograph (Die Frühgeschichte der Syphilis 1495-1498) that King Maximilian's edict was actually published only in 1497, i.e., upon the return of German soldiers from the campaign in Italy; that the so-called Dijon protocol speaks not of syphilis, but apparently of a case of epilepsy; that the Ordonnances des rois referred to by Sudhoff are actually a police regulation of June 25, 1498, in the following places in Germany: Bamberg, Bayreuth, Breslau, Erfurt, Frankfurt am Main, Hamburg, Hildesheim, Cologne, Munich, Lower Rhine, Oldenburg, East Frisia, Nördlingen, Nuremberg, Prague, Strasbourg, Vienna, Würzburg. In 1496-97, syphilis was already known in the Netherlands, England, Denmark, Scotland. One can judge the introduction of the disease from one locality to another by the folk names of syphilis: thus, along with names of syphilis based on its clinical manifestations (Blattern, Pustulen, Pok, Bubus, grosse Blattern, pestis inguinalis, etc.), the French called it mal de Naples, passio italica, morbus hispanicus; in Germany, Italy, Spain, England, Ireland, and Switzerland—morbus gallicus, mal francoso, lues aetica; in Poland—deutsche Krankheit (German disease); in Portugal—Castilian disease; in Japan—Portuguese disease, disease from China (Tô-Kasa), disease from the Liu-Kiu Islands (Liu-Kiu-Kasa); in Persia—Turkish disease; in Russia—Polish or French disease. In these very folk definitions of syphilis, some authors (Proksch) see proof that syphilis was known to these peoples before the discovery of America, since no nation called syphilis morbus americanus, and the name morbus gallicus was the most widespread even among physicians. In reality, however, the folk definitions of syphilis were explained by the fact that medieval medicine knew nothing about this new disease, that when turning to ancient authors, it found no exact description of the disease and measures for its treatment, and that the mass character of the spread of syphilis was quite obviously associated with military campaigns into new countries, from where the disease was brought. It is precisely for this reason that the Spanish physician Diaz de Isla, a contemporary of the first epidemic of syphilis, calls it the "disease of the island of Espanola" (discovered by Columbus); similarly, other Spanish contemporaries, Oviedo and Las Casas, who gave a detailed description of the lands discovered by Columbus, call syphilis the "West Indian disease." In their descriptions of syphilis, they note not only the very fact of the "American" origin of syphilis, but also its milder course in natives compared to that in Europeans who contracted syphilis. Las Casas, a participant in Columbus's second voyage, was on the island of Haiti in 1498 and, questioning the natives about the antiquity of the existence of syphilis among them, established that syphilis existed there long before the arrival of the Spaniards—"from time immemorial." As the first and most formidable wave of the syphilis epidemic subsided and the severity of clinical phenomena weakened in the middle of the 16th century under the influence of the widespread use of mercury and guaiac, the folk definitions also disappeared: Bethencourt introduced the name lues venerea, and Girolamo Fracastoro introduced syphilis (after the hero of his work "Syphilis, sive morbus gallicus").
The first epidemic of syphilis, which led to its introduction into all parts of the world, ended with its widespread dissemination, the creation of a whole series of endemic foci from which syphilis was introduced into new places and, over time, increasingly turned into a disease inextricably linked to the conditions of the capitalist economy. Both in the Middle Ages and in modern times, the existence of prostitution, inevitable under the conditions of capitalist exploitation, served as the main source of the spread of syphilis (for the spread of syphilis in Western Europe and other parts of the world, see Venereal diseases). Russia was a country where endemic syphilis was particularly widespread, having first penetrated there during the years of its first epidemic. According to Haeser, syphilis was brought from Italy by a certain woman to Krakow in 1495; according to Strykowski, in 1493; and in 1495 and 1496 it was spread by troops throughout Poland, which bordered Russia. "One must think that this woman was the ancestress of syphilis in Russia," writes Gertsenshtein, pointing out that the appearance of syphilis "alarmed" the Moscow government of the time to such an extent that in 1499 the Grand Duke Ivan Vasilyevich instructed his Lithuanian ambassador, the boyar son Mamonov, on his way to Lithuania to verify the existence of syphilis in Vyazma, namely: "Did anyone arrive with that disease in which sores break out? And it is called the French disease, and they say it was brought from Vilna." There are no descriptions of syphilis in Russia prior to the Petrine era, since the influx of doctors from Western Europe began only under Peter I, and if individual foreign doctors previously served only the court, under Peter I they were intended mainly for the army and navy he was creating, and only later for the rest of the population. Despite the absence of medical descriptions of syphilis in Russia in the 16th to 18th centuries, Gertsenshtein rightly considers that syphilis "took firm root" in Russia by virtue of incessant wars, the absolute lack of medical care for the sick, the low cultural level of the masses, the patriarchal way of life in large families, and the continuous replenishment of troops with new layers of the population; under such conditions, once introduced, syphilis turned individual families and villages into foci of its endemic spread. The extent of the spread of syphilis can be judged by the fact that the treatment of this disease occupied the largest place among quacks of all nationalities of the country, as well as by individual later descriptions of the introduction of syphilis from Russia into other countries. Thus, according to Lancereaux, syphilis was brought by sailors of a Russian ship to Egersund and Stavanger (Norway) in 1710, where it assumed an endemic distribution under the name of the "unclean" disease "radesyge," studied in 1758 by Honoratius Bonvie. K. Grøn cites van Swieten, who points out that syphilis was widespread in Siberia in 1715–16; he believes that Swedish prisoners of war interned in Tobolsk after the defeat at Poltava brought the disease with them from Saxony. The first statistical data on syphilis in Russia date back to the mid-19th century, whereas morbidity in the 18th century can be judged both from the publication of special manuals, for example, the "Lchebnik o venericheskikh boleznyakh dlya narodnogo upotrebleniya" (Medical Book on Venereal Diseases for Popular Use) by S. A. Venechansky, chief physician of the St. Petersburg Land-Forces Hospital, in 1755, and from the "measures of struggle" to which the government was forced to resort. Thus, in 1762, the Senate (cited by Gertsenshtein) proposed the establishment of special hospitals in cities for the treatment of syphilis: in provincial capitals with 100 beds, in district towns with 50, with doctors, pharmacies, baths, and the like, indicating "the possibility and necessity of free treatment for patients." In the following year of 1763, in view of the significant spread of "French-venereal disease" (syphilis) among soldiers, the Senate ordered the exile of all identified sick women to Nerchinsk; in 1783, a secret hospital for male and female syphilis patients was opened in St. Petersburg. The extent to which syphilis had penetrated the peasant strata of the population at that time can also be judged by Gertsenshtein's indication that in the Little Russian provinces, when hiring workers, a certain portion of their wages was withheld "for the treatment of their French-venereal disease." The "measures of struggle" undertaken by the government against syphilis naturally proved impotent: serfdom, poverty, and the ignorance of the numerous rural population, and the absence of systematic medical care—all this could not weaken the endemic spread of syphilis, which, when introduced into new areas, caused severe disasters there. The population of the national regions suffered to the same extent as the rural population, and sometimes even more. Tarnowski, in a note to Lancereaux's manual (Uchenie o s [The Doctrine of Syphilis], 1876, St. Petersburg), points out that "in 1850 among the Kirghiz, Bashkirs, and Meshchers of Orenburg Province, syphilis spread to such an extent that, according to reports by local authorities, many clans were universally infected, with the disease assuming an extremely severe character." The emancipation of the peasants and the subsequent development of capitalism in Russia caused a significant development of seasonal migrant labor by peasants to the cities, where they came into contact with regulated prostitution, among which syphilis was extremely widespread. Similarly, military service, with the prolonged separation of conscripts from their families, was a factor contributing to the introduction of syphilis into the villages. Introduced into the villages by migrant workers and soldiers in the second half of the 19th century, syphilis found peculiar ways of spreading there: the backward way of life of the village, the lack of elementary hygienic habits, superstition, quackery, which reinforced the popular view of syphilis as a pathetic and shameful disease—all this contributed not only to sexual but also to extremely strong non-sexual transmission of syphilis. The close connection of syphilis in tsarist Russia with the way of life of the rural population defined it as "household" syphilis. The presence of endemic foci of "household" syphilis was a factor causing the steady growth of syphilis, which can be judged from the last quarter of the 19th century, i.e., from the time of the first publications about it in the statistical reports of the Medical Department of the Ministry of Internal Affairs. II. Epidemiology. The epidemiological feature of syphilis in pre-revolutionary Russia—from its first detailed descriptions, i.e., from the middle and end of the 19th century, until the October Revolution of 1917—is its endemicity, i.e., the detection of new cases of the disease in certain, sometimes limited areas, the infection of all ages, sometimes entire villages or a whole series of families, with "household" transmission being the main route. In endemic foci, the primary source of infection could be sexual transmission, but further spread as a rule proceeded by non-sexual means. Descriptions of individual, sometimes rapidly passing endemics of syphilis are found in the history of almost all European countries both shortly after and many decades after the first epidemic (pandemic) of syphilis described above. Thus, Konrad Meyer-Arens describes an endemic outbreak of syphilis in the Canton of Bern (Switzerland) in 1570, which prompted the issuance of special government orders on the isolation and treatment of patients; in 1592 and 1602 these orders were repeatedly confirmed. Among the oldest outbreaks of syphilis is also that described by Gilchrist and Benjamin Bell in 1771, which then raged in the 17th and 18th centuries in Scotland as an endemic of syphilis called sibbeus (apparently named after one of Cromwell's generals whose troops brought syphilis to Inverness). According to Willemoers, the reason for the significant spread of syphilis, especially among highlanders, was widespread hospitality, sharing a bed with strange travelers, smoking shared pipes, and eating from shared bowls with shared spoons. The endemic outbreaks of 1760–70 also include the so-called Canadian syphiloid—a disease that became widespread in Baie Saint-Paul (now Murray Bay) and was introduced, according to Proksch, by the English or Germans (mal anglais, maladie allemande). Under the name morbus dithmarsicus (Dithmarschen disease or Jutland syphiloid), an endemic of syphilis in Denmark is described, the beginning of which dates back to 1757; the disease assumed such formidable proportions that, at the government's suggestion, a special survey of the affected areas was organized in 1813. Among the endemic outbreaks of syphilis in Norway, Grøn also includes the so-called radesyge—the aforementioned infection of the population in Stavanger by Peter I's sailors and in Egersund by Danish sailors (1709–10), which gave rise to the long-term existence and widespread dissemination of the infection. In 1778, a commission established by royal rescript for the investigation and treatment of syphilis developed measures among which it is interesting to note the following: in the affected areas, marriages of persons suspected of having syphilis were prohibited without a prior medical examination; priests and other officials were required to report twice a year on the number of patients they had; conscripted recruits had to be examined for the presence of syphilis; indications of the indisputable non-sexual nature of the infection also date to this time. Endemic syphilis in the Balkans is distinguished by the greatest severity both in terms of distribution and duration of existence. According to descriptions by the Franciscan monk I. F. Jukić (cited by K.
Syphilis was introduced into Bosnia in 1780 by the Turks, where it received the name skerljevo (in Croatian; or scherlievo in Italian, mal di Fiume, Grobbing disease, mal di Fuccine, mal di Radugusa, etc.), and spread comparatively rapidly through all the Balkan countries. The severity of the syphilis endemism in these countries can be judged by the fact that after the retreat of the French (1814), Emperor Francis I of Austria himself visited in 1816 the localities affected by the skerljevo disease, and by his decree in 1818 a mass examination of the population was carried out in 11 districts under the protectorate of Austria; all residents were subjected to examination, regardless of property status, sex, and age, with the exception of the aristocracy of the city of Fiume, for whom only a certificate from a family doctor was required. For the isolation and treatment of patients, hospitals were opened in Fiume and Castel Nuovo with 1,000 beds each. Until 1859, through the hospital in Castel Nuovo, i.e., over the course of 41 years, about 190,000 patients passed. Along with hospitalization, preventive measures were also carried out: some areas were cordoned off by troops for quarantine, restrictions on the right to marry were introduced, all houses and utensils after the removal of patients were subjected to disinfection, and some belongings were even destroyed. Thanks to the involvement in subsequent years of an increasing number of doctors and professors (e.g., Siegmund, Hebra, and others) in examinations, the organization of hospitals, and permanent observation of foci of syphilis, the endemism of the latter began gradually to fade, especially in Trieste, Carniola, and Croatia. The next outbreak occurred in Brenotal in 1860, with infections transmitted during vaccinations with lymph from children who had died in infancy. In 1880–1881, the number of patients in Dalmatia increased so sharply that special preventive measures were again required (compulsory hospitalization of patients in necessary cases). Syphilis spread especially widely in Bosnia and Herzegovina, since these regions, which were under Turkish rule until 1878, almost completely lacked medical care; the epidemic state of these countries was completely unknown. The severity of the endemism and the degree of the spread of syphilis in these culturally backward countries can be judged by the fact that within a single decade (up to 1889), 11 special hospitals were opened in Dalmatia. Endemic syphilis in Bosnia and Herzegovina was the subject of special examinations by such prominent Austrian syphilidologists as Auspitz, I. Neumann, and M. von Zeissel almost until the end of the 19th century. However, even at the beginning of the current century, endemic syphilis in Bosnia and Herzegovina affected entire villages. The prolonged existence of the infection necessitated the steady expansion of free medical institutions, both stationary and outpatient, the publication of popular literature in national dialects distributed by rural teachers, people's judges, and others, as well as systematic house-to-house examinations, sometimes accompanied by on-site treatment. As a result of these measures, according to L. Glück, a whole series of small endemic foci was eliminated in 1903, and cases of tertiary gummatous syphilis became less frequent. Periodic observations of the foci of syphilis in Bosnia and Herzegovina were nevertheless carried out right up to the beginning of the imperialist war of 1914. The colonial policy of the capitalist countries of Europe turned conquered countries into significant foci of endemic syphilis; thus, Herzenstein cites in his work on syphilis in Russia (1885) Rohlfs' data on syphilis in Morocco: "The local name of this disease, mird el kebir (the great disease), indicates the population's view of it. Jackson asserted that in Morocco it is difficult to find a subject whose blood is not infected with this poison. At present, syphilis mird frendji (the French disease) is the most widespread." Leo says that "perhaps only a tenth of the population is free from it." Thus, already in the first years of the official registration of syphilis in Russia, its enormous scale of spread and its main endemic feature—the significant infection rate of the rural population—were revealed. The latter is confirmed both by the registration of syphilis in medical institutions and by data from house-to-house and family-by-family examinations. Summarizing the reporting data on syphilis for 1878, 1879, and 1880, Herzenstein comes to the conclusion "that approximately 2 million of the population of European Russia are afflicted with this ailment." Chistyakov (1880), having examined 25,050 people in Krasnoslobodsk Uyezd, Penza Governorate, found among them 4.73% of syphilis patients even with far from perfect research methods under conditions of house-to-house inspection. The number of syphilis patients among those treated at medical districts was also significant: D. Sandberg (1893) found among outpatient patients in Kozlov Uyezd, Tambov Governorate, 20.6% syphilis patients; Barsukov (1878) in the same governorate—18%; Nikolsky (1886)—15.7%; Maslovsky (1890) determined the infection rate of the entire population of the governorate to be 2.5%. Somewhat later, Dovodchikov, during the examination of 51,077 peasants in Yaroslavl Governorate, revealed 3.2% syphilis patients, and Lifshitz in the former Lithuanian Governorate, out of 40,027 examined, found 4% syphilis patients. Such a significant infection rate of the rural population was explained by the ease of its non-venereal transmission in the conditions of village life. Uvarov reported at the congress to discuss measures to combat syphilis (1897) that "in Kostroma Governorate, syphilitic ulcers were observed in the mouth in 221 cases, on the lips and cheeks in 141 cases, on other parts in 246 cases; if lesions on the genitalia are also placed in the latter category, infections through everyday intercourse must still significantly predominate." Kalmanovsky in Lodeynopolye Uyezd, Olonets Governorate (1903), out of 1,082 syphilis patients who sought help, found sexual transmission in only three cases. On the spread of syphilis in the USSR, see Venereal diseases—spread in the USSR. The deployment of special measures to combat syphilis in the countryside and the widespread use of salvarsan preparations for its treatment led, along with a decrease in the saturation of syphilis in individual families, to significant changes in the clinical picture of domestic syphilis, which, according to data from the late 19th and early 20th centuries, was characterized by the predominance of gummatous tertiary forms of syphilis over primary and secondary ones. According to Herzenstein, the ratio of condylomatous and gummatous forms is 13% and 87%; according to Chistyakov, 32.6% and 67.4%; according to Dovodchikov, 14.0% and 86%; according to Lifshitz, 30% and 70%. Primary scleroses were especially rare: out of 523 cases of syphilis, Sandberg found only 4 primary scleroses (all of non-venereal localization), i.e., 0.8% with 21.7% condylomatous and 72.1% gummatous forms of syphilis. A significant change in the ratio of forms of syphilis was noted by Halperin and Isaev already from their processed comparative registration data for 1913 and 1924, and they revealed the preponderance of primary and secondary forms over tertiary ones even in governorates with the highest registration of syphilis. Based on the analysis of data from house-to-house and family-by-family examinations for 1925–1926, Halperin stated that primary and secondary syphilis averaged 56.3%, and tertiary syphilis 43.7% of all detected syphilis cases; according to data for 1927–1928, they were 62% and 38%, respectively. In foci with a significant spread of syphilis, one of the characteristic features of domestic syphilis was still preserved in 1925, namely the predominant oral localization of syphilids. Thus, Lepukali and Aubrecht, among 1,640 registered cases of syphilis, found oral localization in 52% of them. The possibility of wide detection of manifest forms of syphilis in its endemic foci also facilitated their timely sterilization with salvarsan and thereby the gradual extinction of a whole series of endemic foci. Observations of subsequent years, with significantly improved statistics, show a significant decrease in the number of syphilis patients among the rural population: from 1913 to 1931, the per-mille registration of syphilis here decreased from 53.7 to 22.3. Among 20,713 people examined by venereal detachments of the State Venereological Institute of the People's Commissariat of Health in 1930–1931 in various regions of the RSFSR, 2.45% of syphilis patients were found, compared to 4.9% (according to mass examination data of 1927–1928). The examination data of 1930–1931 revealed at the same time the again-emerging preponderance of tertiary (latent) syphilis over primary and secondary: in relation to the entire examined population, secondary syphilis accounted for 0.65% (0.3% active and 0.35% latent forms), and tertiary syphilis for 1.8%. With a general decrease in the number of syphilis patients, the indicated predominance of tertiary forms testifies to the full coverage of patients and the dying out of infectious foci. "Domestic" syphilis disappears in the countryside as patriarchal individual life in the peasant family is replaced by new socialist forms of collective labor and life. In contrast to "domestic" syphilis in the pre-revolutionary countryside, among the urban population syphilis usually spreads through sexual contact. The sexual route of syphilis transmission remains dominant in the spread of infection among the urban population in Soviet Russia as well. With the development of dispensary care, the percentage of non-venereal infections is significantly reduced; this is also explained by the development of medical care in rural areas, since a significant number of rural patients began to be registered in the first years of Soviet healthcare in urban venereological institutions.
The percentage of extragenital infections is higher among women than among men; a relatively high percentage of unidentified infections is also mainly accounted for by women; among the latter, the so-called unknown syphilis (syphilis ignorata) is relatively frequent, when syphilis is diagnosed as the cause of diseases of the internal organs, the central nervous system, etc., unexpectedly for the patients themselves, most frequently in women in connection with the course and outcome of pregnancy, especially during periodic serological examinations. Wein and Silbermann, out of 4,670 cases of syphilis (latent, gummatous, and of the nervous system) registered in 1926, 1927, and 1928 in two venereological dispensaries in Moscow, revealed 24% (1,146 cases) of unknown syphilis, with women accounting for 33.5% and men for 18.5%; according to other authors, an even higher percentage of unknown syphilis falls to the share of women: according to Meshchersky it is 45.6% among women, according to Shestakova—67.5%, according to Shoikhet—46.69%, according to Rossiyansky and Gitman—41.6%, according to Levenson and Goldberg—from 25% to 62.1%. Morozova and Yukelis, among 6,000 pregnant women who underwent clinical and serological examinations, found 2% of patients with syphilis, among whom there were active manifestations in 10 cases, while all the rest were latent cases, of which 65–70% constituted unknown syphilis. The predominance of unknown syphilis in women is also in accordance with the fact that they apply significantly less often than men regarding primary syphilis; Levenson and Goldberg, out of 4,047 cases of syphilis among women, registered primary syphilis in 2.8%, Galperin and Isaev out of 5,107 cases in 2.2% (among men, 10.8%). The years of Soviet public health are characterized by a significant attraction of women to treatment in the secondary, i.e., socially more dangerous, period of syphilis: thus, according to Batunin and Malkov in the Kazan Clinic of Skin and Venereal Diseases from 1889 to 1913, the highest percentage of treated women falls on tertiary syphilis (61.9%); on primary and secondary syphilis, a total of 38.1%; according to the summary data of Galperin and Isaev (1924–1925), primary and secondary syphilis accounted for 68.05% of treated women, and tertiary syphilis for only 21.95%. In the epidemiological characterization of syphilis in the cities of the USSR, it is necessary to note significant changes in the sources of its spread. The main source of syphilis among the urban population in the capitalist countries of Western Europe and tsarist Russia was prostitution (see Venereal diseases, social causes of the spread of syphilis). In the USSR, the role of prostitution in the spread of syphilis is steadily declining. Along with the main factors that caused a sharp change in the epidemiological curve of syphilis in the USSR towards its steady decline (the growth of the material and cultural level of the working people, the wide development of preventive measures based on the self-activity of the working people, the creation of a powerful network for the free treatment of patients, the huge sanitary and educational work carried out in the field of combating syphilis), the sharp decline in prostitution as the main source of syphilis contributed to an intensive decrease in the incidence of syphilis among the urban population. Thus, according to the State Venereological Institute of the People's Commissariat of Health in Moscow, per 10,000 population there were patients with syphilis: in 1926—84.0; in 1927—57.3; in 1928—46.3; in 1929—44.3; in 1930—38.5; in 1931—31.0; in 1932—21.9; in Leningrad, respectively: in 1927—48.1; in 1930—31.1; in 1932—30.2. The intensity of the decline of syphilis among the urban population is expressed more strongly than that of other venereal diseases. Thus, in Moscow, per 10,000 population, syphilis decreased from 1926 to 1932 from 84.0 to 21.9, i.e., by 77.4%, gonorrhea—from 77.0 to 37.7, i.e., by 50%; soft chancre—from 7.0 to 3.4, i.e., by 51.4%. Calculated per 10,000 of the entire population of the RSFSR, over the 4-year period 1928–1931 alone, syphilis decreased by 43%—from 42.8 to 24.7. For statistics on syphilis, see also Venereal diseases. III. Social significance of syphilis. The social significance of syphilis is determined both by the degree of its spread (see above) and by its significance for the patients themselves, their offspring (see below, congenital syphilis), and the collectives in which these patients live and work. The significance of syphilis for the patient is determined by the severity and duration of the clinical manifestations of the disease (see below, clinical aspects of syphilis), the possibility of both early and late damage to vital organs by syphilis, leading to temporary or permanent disability and significantly increasing mortality among individuals who have had syphilis. On the organization of the fight against syphilis, see Venereal diseases. In fact, the majority of patients with open forms of syphilis are temporarily disabled in the USSR, since in the interests of social prophylaxis of syphilis they are hospitalized until the danger of their transmitting the infection in the conditions of their labor and everyday life disappears; thus, the Soviet state assumes the hospital maintenance of the specified group of syphilis patients and through the social insurance organs pays them temporary disability benefits (for the period of hospital, and in some cases outpatient, treatment). Atarov, based on the materials of the North Caucasian Regional Insurance Fund for 1927, 1928, and 1929, taking disability for all types of diseases as equal to 100, established a relatively low specific weight of syphilis as a cause of temporary disability—0.18% with 0.29% of days of disability; however, the average duration of temporary disability in each individual case of syphilis is significant; according to Borzov and Larisman, the duration of disability in syphilis averages 20.7 days and stands in second place after pulmonary tuberculosis (22.4 days), according to Atarov—14.45 days. It is necessary, however, to take into account that the cited data indicate fresh forms of syphilis; the significance of syphilis in the issue of temporary disability increases if we take into account a whole range of diseases in the etiology of which syphilis has a dominant significance. Syphilis as a cause of death is determined by studying autopsy material and processing statistical data from insurance companies registering all causes of death among the persons insured by them. Thus, Runeberg (1898; cit. according to Gaushtein) found, based on the materials of the Finnish insurance company "Kaleva" among 734 cases of death of the insured, syphilis as a cause of death in 11.4%; Bruhn-Fahraeus (1902) based on the materials of the Swedish company "Nordstjernan" out of 1,569 cases—6.8%, Lenmalm (1922) based on the materials of the "Thule" company out of 10,554 cases—3%. Kleinschmidt (1906) based on the materials of the German company "Vaterländische Versicherungs-gesellschaft" out of 2,503 cases—6.2%; Blaschko (1904) according to the data of the "Victoria" company—6% and according to the materials of two English companies—6 and 10%. According to the data processed by Florschütz of the Gotland Insurance Company for 44 years (cit. according to Oppenheim), it turned out that if the mortality of all insured persons is taken as 100, then the mortality of syphilitics rises to 168; thus, for all age groups of syphilis patients, an excess mortality of 68% is obtained; the maximum excess falls on the age from 36 to 50 years (86%). Matthes (1901), out of 160 deceased syphilitics in clinical institutions of Jena, found syphilis as an undisputed cause of death in 15% and a probable one in 12%. Grøn, out of 3,729 autopsy cases in the city of Oslo (for the period 1871–1895), found syphilis as an undisputed cause of death or "incidental autopsy finding" in 96 cases, probable syphilis in 47 cases, inaccurately established syphilis in 19 cases, a total of 4.3%; in the same place Harbitz, out of 6,529 autopsies for the period 1900–1927, found syphilis as a cause of death in 4.68% (303 cases), and taking into account "incidental findings"—in 5.6%. Gaushtein processed the statistics of 11,376 autopsies in Ullevål (Norway), without cases of congenital syphilis, among which there were 465 undisputed and 50 probable cases of syphilis, i.e., a total of 515, or 4.53%; and syphilis as a cause of death among these 515 cases was present in 247 cases, i.e., 2.17%; comparing the number of new cases of syphilis with the annual general mortality and the cited calculations of mortality from syphilis, Gaushtein believes "that 7.06% of those contracting syphilis must die from the syphilis they acquired." Along with these data characterizing syphilis as a cause of death among adults, it is also necessary to take into account syphilis as a cause of mortality among newborns. Gaushtein cites the following data expressing the high specific weight of syphilis in mortality among newborns. Thus, in Switzerland for the 10-year period 1910–1920, there were a total of stillbirths: Stillbirths in cantons, in cities. Absolute number... 58,271 including: syphilis... 913 (1.56%), macerated fetuses | 2,516 (4.32%), 12,791, 574 (4.48%), 1,061 (8.29%). Total (syphilis and macerated fetuses)...
Among illegitimate stillbirths, the percentage of syphilis and macerated fetuses is significantly higher: in cantons, a total of 13.72%; in cities, 22.48%. Over the indicated decade, for every 10,000 births, there were stillbirths from syphilis: from 1901 to 1905—16.9%; from 1906 to 1910—17.2%; from 1911 to 1915—20.4%; from 1916 to 1920—21.5%. While among older ages mortality increases from diseases that are consequences of syphilis, at an early age, especially in the first year of life, mortality is a consequence of congenital syphilis (see Table 2), with the highest percentage occurring in the first three months of life; thus, according to Gaushtein, in Berlin among those who died in the first year of life from congenital syphilis, it was by months: from 0 to 3 months—3.60%; from 3 to 6 months—0.64%; from 6 to 9 months—0.15%; from 9 to 12 months—0. Table 2. Mortality from syphilis and subsequent diseases in Berlin in 1913 (by age). According to data from N. Morozova and I. Yukelis (Moscow), who examined 304 pregnant women suspected of having syphilis, in 50 cases the pregnancy ended with the birth of a macerated fetus; in the same maternity hospital out of 788 autopsies of fetuses as a result of pathological births during 5 years of prosectorate work, syphilis was found in 16.5%; among 108 pregnancies ending in the birth of a premature fetus, syphilis was found in 19.5% (21 cases); out of 46 full-term stillbirths, syphilis was found in 29% (13 cases). Regarding the effect of syphilis on offspring, one can judge by the data of Pick and Bandler (cited by Gaushtein), who tracked the fate of 528 children born in syphilitic marriages; they found 37 stillbirths; 95 children died in the first year of life, then soon another 21 from syphilis of the brain and nervous system, 28 from paralysis, 23 from tabes, 33 from heart and vascular diseases, 15 from liver and kidney diseases; thus, out of 528, 252 died. These data indicate the enormous social significance of syphilis, its impact on the fate of the patient, their offspring, marriage, family, and society. According to Moscow prosectorates for 1923–1927 (cited by Davydovsky), out of 37,899 autopsies, syphilis as the primary disease was registered in 3.15% of all cases, and as a concomitant disease in 1–1.5% of the remaining cases.
S. Halperin. IV. Spirochaeta pallida. The pale spirochete (Spirochaeta pallida), the causative agent of syphilis, was discovered in 1905 by Fr. Schaudinn jointly with Erich Hoffmann. In view of some differences from true spirochetes (absence of an undulating membrane), it was later assigned to the genus of treponemes (Treponema pallidum). The pale spirochete has been found in the pathological products of all stages and forms of acquired and congenital syphilis in humans and experimental syphilis in animals (monkeys, rabbits, and others)—in the lymph of scleroses, papules, condylomas, in the organs and blood of hereditary syphilitic fetuses, in the brain and cerebrospinal fluid of paralytics (see separate table, figure 6). Schaudinn, like most other researchers, classifies the pale spirochete among protists (presence of an axial filament, absence of a membrane); however, individual authors (Meirowsky) tend to consider it a mold fungus (presence of true branches or lateral buds, absence of a differentiated nucleus). From these data, it is evident that it occupies an intermediate position between protozoa and molds. The pale spirochete, depending on observation conditions, can exhibit varying morphology: in the lymph of syphilitic products in an untreated form or in physiological NaCl solution when observed in a dark field, it has the appearance of a pale gray corkscrew on a dark background; its coils (waves) are very delicate, thin, deep, uniform, and their tips are rounded; the number of coils ranges from 3 to 25 (on average 8–10); its ends are pointed and sometimes resemble flagella. The anatomical structure has not been definitively established: most researchers recognize the presence of an axial filament (Ciarla) connected to a terminal flagellum (Schwanzenende-Oelze), which performs the functions of its organ of motion; an undulating membrane has not been proven; the presence of branches, spores, or buds is disputed (Sobernheim); a formed nucleus has not been discovered, but nucleus-like formations of a volutin character (a special nucleoprotein) have been described by some researchers (Zuelzer). The pale spirochete possesses motility characterized by the following features that distinguish it to a certain extent from similar saprophytic spirochetes (Sp. refringens, Sp. microdentium, Sp. balanitidis, Sp. calligyra, and others) and stand out clearly in a dark field: 1) insignificant progression, 2) rotational movement, 3) pendular movement, 4) a certain rhythmicity of bending movements (at its midpoint). Microkinematic study of the pale spirochete has shown the presence of sharp changes in its morphology during moments of movement that are not captured by conventional methods. The pale spirochete, in view of the peculiarities of its chemical structure, is difficult to stain without mordants. Its staining is most characteristic when using the Giemsa method and similar dyes (azure); with this method, it acquires a clear pink color, whereas saprophytic spirochetes acquire a violet tint of coloration (Sp. refringens, Sp. balanitidis, Sp. Vincenti, and others) and are generally easily stained with ordinary aniline dyes (gentian violet, fuchsin, and others). Its morphology is well preserved with this method. The long-held opinion about the exclusively longitudinal division of the pale spirochete (Schaudinn, Prowazek, Noguchi, and others) has now been shaken by facts also speaking in favor of its transverse division (Hoffmann, Levaditi, Mühlens, and others); at the site of impending division, a thread-like flattening of the waves has been described (Zwischenfaden, Schellack), and sometimes point-like nodules (sporenartiges Körchen Meirowsky); during transverse division, the mother spirochete may disintegrate not only into two, but into three or even more daughter individuals (Hoffmann, Zuelzer). The question of the cyclicity of its development remains open even now, since the various forms of so-called cyclicity described by various authors (ring-shaped, spermatozoon-like—Kristalovich and Sedletsky, granule-containing or coccoid, described in lymph glands as pre-spirochete stages—Levaditi and Cesari) can rather be explained as degeneration of the spirochete under the influence of various conditions—artificial medium, host immune properties [small short forms in the ventricular fluid of paralytics, thread-like forms in the ventricular fluid of rabbit-neuroletics (Finkelstein)]. The morphology of the pale spirochete on artificial media presents certain deviations—in liquid and semi-liquid media, small and thread-like forms disintegrating into 3–4 daughter individuals (Zuelzer) with terminal flagella; some specimens resemble "refringens"; on the surface of blood agar (according to Förster), there are many long specimens (Hovhannesyan). The morphology of the pale spirochete in the organism of luetic animals (monkeys, rabbits) does not present any characteristic regular differences from that in humans. The pressing question of the multiplicity of the pale spirochete has been resolved in the negative sense: there is a single race of spirochetes which, depending on living conditions (artificial medium, passage, host constitution), can be more or less dermato-neurotropic or affect other organs (eyes, blood vessels, liver, etc.). The assertion of the Levaditi school and some German researchers (Plaut, Mühlzer) about a special mutation race giving cerebrospinal fluid changes in rabbits, being based on insufficiently precise experiments, has been refuted both by German researchers (Prigge) and by extensive experiments of the State Venereological Institute (Finkelstein, Bobykina-Strelinskaya, Gurevich) on rabbits and mice.
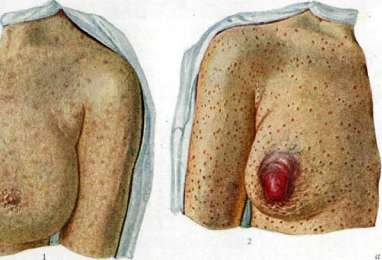

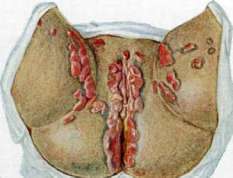
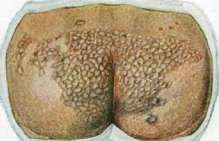
Figure 1. Syphilitic roseola. Figure 2. Hard ..... papular syphilide. Fig. 3. Hard chancre (primary syphilitic lesion). Fig. 4. Hypertrophy ..... of moist papules of the genitalia. Fig. 5. Rupia following tuberculoid syphilide. Fig. 6. Spirochaeta pallida [staining: a-according to Levaditi; b-in dark-field illumination; c-according to Giemsa]. Figure 7. Spirochaeta ..... altefc a-in culture; b-pus. Fig. 8. Spirochetes thermal death: a-capsulation form; b-in tissue; c-old; d-young. The culture of the pale spirochete can be obtained, although with great difficulty and not regularly, on various protein media under conditions of relative anaerobiosis and a definite active acidity (pH = 7.2-7.8, Weiss and Wilkes-Weiss, Krantz); the following have been proposed: a) liquid media [Kroo-Schultze: rabbit serum and Normosal (1:10) - 100 cm3, boil guinea pig sterile liver 3 days in a row for 6 hours in a water bath at 50°, filter, pH = 7.5, pour sterile paraffin]; b) semi-solid medium of Shereshevsky - see Culture media; c) solid media: Forster's blood agar - 2% weakly alkaline agar + 20% whole rabbit juice. Many other formulas have been proposed that do not, however, guarantee certain success. Of the newest cultivation methods, Forster's method is interesting in principle - growth on the surface of blood agar in hermetically sealed Petri dishes; anaerobiosis is achieved by conducting the cultivation in the vicinity of an oxygen-absorbing microbe (Bac. prodigiosus) on the same surface of an agar plate divided along the diameter by a groove (a strip of agar is cut out along the diameter!); on one half of the agar surface the spirochete is inoculated, on the other - Bac. prodigiosus; the seam between the lids of the Petri dish is hermetically sealed with plasticine. It has already been indicated above (Hovhannisyan) that this yields abundant growth of long spirochetes, non-pathogenic for animals; spirochetes, especially in impure culture, may possess pathogenicity for rabbits (Levaditi, Tomaszewski, Noguchi, etc.). According to its chemical composition, the pale spirochete contains many lipoid substances, since it does not undergo pepsin-hydrochloric acid digestion, but dissolves in alcohol, saponin, bile (sodium taurocholate); in addition, a small amount of proteins of an alkaline character (lipoprotein) has been found in it (Schumacher, Bergel, Zuelzer) and it contains almost no nucleic acid. The pale spirochete is capable of reducing arsenic preparations (especially organic ones), which explains its salvarsan resistance; besides arsenic preparations (salvarsan, stovarsol, ocapsol), it is also resistant to antimony (stibosan), which is related to arsenic, to mercury, iodine, and bismuth. The pale spirochete is poorly resistant in vitro to various other harmful agents, for example, to drying; a temperature of about 50° is fatal to it within 1 hour, about 10° - after 20 hours; in pieces of tissue in the cold it survives up to 58 days; in cadaveric material it, according to Armuzzi, survived up to 110 days [cases of infection through cadaveric material are known (Hoffmann and others)]; in lymph in sealed capillaries it, according to Shereshevsky, survives for several days. Ultraviolet rays are fatal to it, X-rays are ineffective. Noguchi and Bronfenbrenner give the following figures for the death of the spirochete (2 strains) under the influence of minimal solutions of various substances: sublimate - 1 : 200,000-500,000; As2O3 - 1 : 20,000-30,000; tricresol - 1 : 500; phenol - 1 : 200; saponin - 1 : 5,000-7,000; sodium taurocholate - 1 : 1,000-2,000; NaOH - n/81; HCl - n/320; alkaline solution of Neo 1 : 125 does not kill the spirochete (in vitro) within 12 hours; it is very resistant to hypertonic NaCl solution, since it is incapable of plasmolysis. The pale spirochete does not form a true toxin in a liquid medium; the products elaborated by it in the organism are of an endotoxic character; filterable forms have not been proven for it. The pale spirochete possesses antigenic properties in relation to the human and animal organism: in the serum of animals and man under its influence, properties appear that are complement-fixing (Wassermann, Citron, Klopstock, etc.), precipitating, agglutinating (rather agglomerating), lytic (Gurevich, Timokhina), opsonizing. Bacterioscopy. The primary condition for the detection of the pale spirochete in pathological materials is the correct collection of material from the main seat of infection - the lymphatic pathways - syphilitic elements. Method of collecting material: 1) The primary ulcer or other element is freed from external dirt and coating using a cotton swab (sterile) moistened with physiological NaCl solution or, better, a hypertonic solution (1.5-2%) of NaCl, as it enhances secretion and facilitates the removal of detritus and coatings. 2) Irritation of the ulcer to enhance the secretion of lymph containing spirochetes is performed with some sterile instrument - a sterile platinum loop or spatula, glass spatula (Elce model), the edge of a coverslip or glass slide (ground). Bloody material is unsuitable for investigation, since blood generally contains few spirochetes. Lymph usually appears 1-2 minutes after the beginning of irritation. 3) A healed epithelialized ulcer or non-ulcerated efflorescence is carefully scarified before irritation with the blade of a sterile scalpel until the lymphatic pathways are opened; avoid opening blood vessels. The appearance of lymph can be accelerated by compressing the ulcer from the sides, as well as by applying small Bier cups. 4) An important auxiliary method is sometimes the puncture of regional lymph glands, which is performed as follows: the skin over the corresponding gland (most often inguinal) is sterilized with iodine and punctured with a steeply beveled sterile needle (preferably platinum) mounted on the cannula of a 5-10 gram syringe (Record) with a tightly moving piston; upon penetration of the needle into the underlying subcutaneous tissue, the needle is advanced to the gland fixed between the thumb and forefinger of the left hand and inserted into the cortical part of the latter; then several (5-6) careful aspirations are made with the syringe piston; after this, several drops of gland secretion, consisting of lymph, lymphocytes, and a small number of erythrocytes, usually appear in the needle, provided the puncture is made correctly. In such material, the spirochete is successfully found in 60-70% of cases when they are absent in the healed ulcer. The material obtained in the indicated manner from any pathological efflorescence is investigated either in an untreated state to detect living spirochetes or in a treated state to detect them in a dead condition. Most often, practically both methods are used: 1) one part of the material (1-2 drops) is applied directly to the surface of a well-washed glass slide (preferably ground) or into a previously applied drop of physiological NaCl solution, covered with a clean, flamed coverslip and examined in a dark field (see Microscopic technique). 2) Thin smears are prepared from the other part of the material on clean glass slides (preferably ground); the spreading of the material is performed with the edge of a coverslip or a ground glass slide; with a certain amount of skill, good preparations are obtained by spreading with a platinum loop. The still wet preparation is fixed with the vapors of osmic acid (1%) or pure formaldehyde (in a Gamma apparatus) for 1-2 minutes. One can also fix with a mixture of alcohol and ether (equal parts) for 15 minutes or with methyl alcohol for 10 minutes. Some authors consider alcohol fixation less acceptable, since due to the extraction of lipoid substances from the spirochetes by alcohol, the latter stain worse and fewer spirochetes are detected in preparations than with other fixation methods. About a hundred methods of staining and processing preparations containing spirochetes have been proposed; in general, these methods represent 4 types: a) silver impregnation methods (modified Levaditi method - relatively simple according to Fontana), b) Giemsa-type methods (see Giemsa, Giemsa staining), c) staining with other dyes (the simplest method is the fuchsin method according to Schmincke), d) negative methods (with colloidal suspensions of India ink, silver, etc.). Of these methods, the most practically tested are the following: 1) Staining according to Giemsa (accelerated modification of Shereshevsky); onto the preparation fixed with osmic acid or formalin and passed 3 times through a flame, the Giemsa stain solution is poured (1-2 drops of commercial stain per 1 cm3 of 0.5% glycerin water, prepared ex tempore and boiled until clear; the stain is poured 3 times and washed off with distilled water; it is dried and examined microscopically. Pale spirochetes in such a preparation are clearly pink; saprophytic spirochetes (Sp. refringens, etc.)
Vincenti and others) with a clearly violet nuance. 2) Negative methods of processing preparations with colloidal suspensions of certain substances creating a specific background against which unstained spirochetes and formed elements are visible: a) treatment with India ink, according to Burri: a drop of so-called bacteriological, finely ground India ink (brand "Pelikan"-Günther-Wagner) is applied to a clean glass slide, a drop of lymph from the pathological affect is introduced into it, mixed with the ink, and then smeared across the slide with the edge of a coverslip or glass slide; the preparation should be of medium thickness; the preparation is dried in air and after that, without any fixation, is ready for microscopy. b) Collargol method (Nitsche's method). A smear is prepared from tissue fluid; after it dries in air, a 2% collargol solution is poured over it in a thick layer; after 3 minutes, the collargol is drained; upon drying, the smear is examined in immersion. Other substances have also been proposed for negative processing (opalblue, cyanochin). When treated with collargol, gray (colorless) spirochetes of fairly typical morphology are visible in the preparation against a reddish-brown background. - Of the indicated methods, the dark-field method should be placed first in terms of its practical significance, in which the pale spirochete is studied under conditions closest to natural, and where not only its characteristic morphological features appear, but also the features of its movement. In second place are staining methods of the Giemsa type, in which the characteristic relation of the spirochete to the azur of the stain is revealed, distinguishing the pale spirochete from vulgar spirochetes - the pink coloration of the pale spirochete and the violet tint of the coloration of vulgar spirochetes. In third place should be placed the so-called negative processing methods, of which the most satisfactory results are obtained with the collargol method. Staining of sections and pathological material is best performed according to the combined Levaditi-Manouelian silvering method. In peripheral conditions (rural social sectors, expeditions, new construction sites, etc.), the simplest and fastest of the indicated methods (India ink, collargol, fuchsin) will certainly have the greatest application. It is rarer to manage to use the Giemsa stain, which is generally quite labile in quality; it is even more difficult and rarer to apply the dark-field method, which requires rather complex and expensive equipment and electrical energy, which cannot always be had in peripheral work conditions. Differential diagnosis. On both normal and diseased skin and mucous membranes (especially the genitals and oral cavity), spirochetes are encountered that have a certain morphological similarity to the pale spirochete and therefore must be taken into account in the differential diagnosis of syphilis. Of these, the so-called Sp. refringens (Schaudinn), described by Donné under the name Sp. lineola, is most often detected; its features: it is considerably thicker than the pale spirochete, contains 3-8 irregular flat bends, stains with Giemsa into a reddish-violet color, and also by usual methods (solutions of methylene blue, fuchsin, gentian). Of other spirochetes, one can point out Sp. calligyra (Noguchi) and a whole series of as yet insufficiently differentiated spirochetes (Tr. balanit., Tr. genital., Tr. urethrae, Tr. vaginal., etc.) encountered in various materials (in smegma - especially with balanitis, in the oral cavity, on the tonsils, etc.). Their pathological significance has not been established. Most of the indicated spirochetes are easily distinguished from the pale spirochete both by morphology (coarser, different character of coils) and by relation to stains (easy stainability with usual solutions of aniline dyes), as well as by a different type of mobility in the dark field. Among the spirochetes of the oral cavity (Tr. microdent. and Tr. macrodent. - Noguchi, Tr. medium, Tr. mucos.), one has to keep in mind most of all in differential diagnosis the small spirochete of dental plaque (Tr. microdent.). The difference of these spirochetes is as follows: 1) the dental spirochete is shorter and thicker than the pale one; 2) the dental spirochete has sharp, angular zigzag coils, the pale one - regular arcuate ones; 3) the dental one performs a few bending non-rhythmic movements; 4) the dental spirochete looks brighter and more light-refracting in the dark field than the pale one. To avoid admixture of vulgar spirochetes when examining efflorescences of the oral cavity, preliminary thorough mechanical cleaning of them is necessary (toothbrush, indifferent rinsing) to remove surface deposits, with which saprophytic spirochetes are also eliminated in most cases. In general, with regard to the diagnosis of the pale spirochete, the so-called "Hoffmann rule" still remains in force: "in preparations from syphilitic secretions, the pale spirochete is reliably diagnosed only when there are no spirochetes of a close morphological type in them besides the characteristic spirochetes; in such cases, repeated examination is necessary while observing the precautions indicated above." Incidentally, practically for an experienced researcher, only one spirochete, Castellani (Sp. pertenuis framboesiae), is completely indistinguishable morphologically and coloristically from the pale spirochete. Cultures of starting material on artificial media for detecting the pale spirochete are of no practical significance at the present state of the technique of its cultivation, since it is only exceptionally grown from pathological material. Such cultures so far have only theoretical interest for studying the properties of various strains of the pale spirochete maintained on artificial media, and partly for the manufacture of so-called luetin, occasionally used for a skin reaction (in tertiary syphilis). In rare cases, e.g., when deciding the question of the cure of syphilis after prolonged therapy, one can, upon the suggestion of Mulzer, also apply animal experiments. For this purpose, the rabbit is used, as is known, highly susceptible to syphilis; in such cases, blood or semen from men, and from women, besides blood, the secretion of the cervix uteri and vagina, are injected into the testicles of the rabbit. Yu. Finkelstein. V. Pathological Anatomy. Schematically, the course of syphilis, as indicated above, breaks down into three periods. The most important factor of the primary period is the formation of a hard sore (ulcus durum). The development of the ulcer is preceded by the formation of a papule. The ulcer usually has the appearance of a superficial defect or abrasion, its edges and bottom are somewhat dense, parchment-like; sometimes the excoriation itself is barely noticeable, inflammatory edema and induration of the surrounding tissue - the so-called primary sclerosis - predominate. Relatively rarely, ulcers are multiple. As a rule, the ulcer is accompanied by the development of buboes, i.e., swelling of regional lymph glands, e.g., inguinal (lymphadenitis). The ulcer and the lesion of regional glands can be considered as a primary syphilitic complex by analogy, e.g., with the primary tuberculous complex. Microscopic examination of the hard sore reveals pictures of subacute inflammation with a vivid predominance of proliferative phenomena on the part of adventitial and endothelial vascular elements, which is why the vessel walls appear loosened, while their lumina are often narrowed. In the infiltrate, an abundant amount of lymphoid cells is found, with a few polymorphonuclear ones; later, young fibroblasts, lymphocytes, plasma cells predominate. The superficial layers of the ulcer usually represent a continuous cellular infiltrate; deeper, the latter is concentrated mainly along the course of the vessels; often the infiltrate follows the vessels into the limits of the superficial fasciae, e.g., into the region of the cavernous tissue of the penis. Special processing reveals an abundance of spirochetes in the infiltrate. The healing of the ulcer occurs with the development of a delicate, slightly depressed, flat, whitish (depigmented) scar, and micrography does not at all always reveal the smoothing of papillae, as takes place in vulgar scars of the skin; the elastic tissue in the papillary layer is also preserved, and fiber regeneration apparently also occurs. In the lymph nodes, vulgar hyperplastic processes on the part of follicles and medullary cords predominate with desquamation and proliferation of the sinus endothelium; suppuration as a rule does not occur. The existence of suppurative and necrotic processes indicates the presence of another or mixed infection (soft chancre, inguinal lymphogranulomatosis, etc.). The following (second) period of the disease, designated as the period of generalization, is expressed not only in a number of usual general infectious phenomena of a clinical character, but also in certain morphological changes, mainly on the part of the skin, mucous membranes, lymph glands, spleen. Delicately roseolous, as well as papular and pustular rashes on the skin (syphilids), subacutely catarrhal processes on the part of the mucous membranes, especially the pharynx, nose, larynx, characterize the second period. From the histological side, the syphilids of the secondary period do not represent anything specific. Against the background of vascular hyperemia of the subpapillary region, loosening of the substrate, perivascular infiltrates (insignificant in roseolae, expressed in papules) of lymphoid cells with an admixture of polynuclears are noted; sometimes degenerative changes on the part of the epidermis.
The presence of significant exudative and destructive phenomena serves as a prerequisite for the development of pustular and pemphigus-type syphilids, which in turn can develop into syphilitic skin ulcers with drying crusts upon them, so-called rupiae. Especially acute and diffuse inflammatory phenomena with extensive detachment of the epidermis are observed in newborn syphilitics. Pustular syphilid, arising by way of suppuration of the papular one, often indicates particularly malignant forms of the disease. On the palms and soles, in particular on the heels, papular eruptions are accompanied by a powerful development of horny layers resembling callosities (so-called syphilitic psoriasis). The intensity of the skin manifestations of the generalization period fluctuates extremely; in some cases these manifestations are significant, in others extremely limited, and in individual cases apparently completely absent, which, however, has its analogies in other "rash" infections as well. The third period of syphilis is generally designated as the gummous period, precisely because it is accompanied by the development in various organs and systems of so-called gummas (see). In the necrosis itself, it is erroneous to see a mere circulatory disturbance on the basis of obliterating processes in the vessels of the gumma; necrosis, like further disintegration, constitutes an inseparable stage in the development of the gumma, they enter into the essence of the process itself. Moreover, the very process of gumma formation can begin with the necrosis of anatomically intact tissues, and granulomatosis and scars can only be subsequent moments. On the other hand, the onset of scleroses is a usual prerequisite for the development of new necroses, including the formed scars and vessels. The alternation of the phases of necrosis and granulomatosis, which can be repeated several times, lies at the basis of the growth of the gumma; it also nourishes the clinical and anatomical symptomatology of the tertiary period, inasmuch as the idea of necrosis is associated with the idea of functional loss (e.g., gummas in the conducting system of the heart, in the nervous system, etc.), and the idea of granulomatosis and scarring with the idea of chronic inflammation, irritation, scleroses, etc. The clinical and anatomical significance of gummas also stems from the fact of their tumor-like nature and from the inevitable end of any gumma and gummous infiltrate—sharp and extensive cicatricial changes in the tissues at the site of the gumma. As a result of these changes, there often arise various deformations and disfigurements of organs (e.g., sinking of the bridge of the nose), the development of their pathological lobularity (hepar lobatum, pulmo lobatus, etc.), strictures of canals, e.g., the trachea, larynx, stomach, etc. The very disintegration of the gumma, insofar as it concerns the structural elements of the organ, can lead to the development of ulcers, perforations, e.g., of the palate, nasal septum, etc. Gummas are observed in various tissues and organs (meninges, liver, muscles, skin, etc.). Rarely, however, at autopsy is gummous syphilis of many organs found; rather, conversely, the development of gummas in any one organ to a certain degree as it were guarantees against their development in other places of the organism. The next feature of the III period is the development of so-called diffuse syphilitic scleroses (or cirrhosis) on the basis of chronic specific inflammation; sometimes such scleroses are accompanied here and there by the development of gummous infiltrates. Cirrhoses are most often observed in the liver (both of adults and newborns), in the pancreas, adrenal glands, lungs, testicles. It must be confessed, however, that the specification of such cirrhotics requires considerable caution, and in all relevant cases it is necessary to pay special attention to differential diagnosis. With the development of syphilitic cirrhotics in children, especially in congenital syphilis, the phenomena of cirrhosis proper are often combined with significant defects in the general development of the organ. A very important feature of the same period should be considered the development of syphilitic vasculitis, chiefly along the course of the arterial system [see separate table (p. 591–592), fig. 2, 4, and 5]. Finally, as a fourth variety of pathological processes in late periods of syphilis (so-called parasyphilis or metasyphilis), one should point to diffuse and predominantly degenerative processes on the part of the nervous system. These include first of all tabes and progressive paralysis. In general, it must be emphasized that syphilis, like any other infection, can, along with extremely characteristic pictures and even instead of them, yield atypical and completely vulgar and therewith rather acute processes of a degenerative-inflammatory nature. Among such, along with the catarrhs of the II period, one can name, e.g., fibrinous-purulent peritonitis in newborn syphilitics, diffuse leukocyte infiltrates of organs in the same cases, osteoplastic periostitis, etc. Syphilis as a chronic infection is frequently accompanied by profound and progressive metabolic disorders. Disturbances of protein metabolism can be expressed in amyloidosis of internal organs (spleen, kidneys, liver, intestines). As a manifestation of a disturbance of lipoid metabolism, one can consider the lipoid (often chronic) nephrosis of syphilitics; sometimes a mixed "amyloid-lipoid" nephrosis is observed. Disturbances of both protein and lipoid metabolism are especially frequent in young syphilitics, in particular in lues congenita tarda. Private pathological anatomy of syphilis—see the respective Organs.
Davydovsky. VI. Experimental Syphilis. The first reports on the possibility of infecting monkeys with syphilis appeared at the end of the 19th century: Klebs in 1871, and in 1886–1888 the St. Petersburg physician Sperk and other authors reported on infecting monkeys with syphilis using material from sick people and on the development of syphilitic ulcers (chancres) and rashes in monkeys. These isolated successful experiments, however, were lost among a mass of negative results from inoculating animals with syphilis and were not duly appreciated by contemporaries, just like the undoubtedly successful infection of rabbits in the eye by Hansel in 1881. In December 1903, Metchnikoff and Roux published the results of their famous experiments on 2 chimpanzees: they inoculated a female in the fold of the praeputii clitoridis with material taken from a syphilitic patient. After this, works by a whole series of researchers (Neisser, Finger and Landsteiner, Nicolle, and others) appeared, not only confirming the infectivity of syphilis for monkeys, but also clarifying a whole range of questions concerning this phenomenon. It turned out that with appropriate technique, infection succeeds in all cases without exception. Not only various species of higher anthropoid monkeys (chimpanzees, orangutans, gibbons), but also lower ones (Macacus, Cercopithecus, Cynocephalus) contract syphilis. In the latter, however, susceptibility is somewhat weaker than in higher animals, as shown by the necessity to use material with a large number of spirochetes for their infection; spirochetes appear in very small numbers in their syphilitic chancres, and the infection itself succeeds only in certain skin areas. The most reliable results of monkey infection are given by skin inoculations via intensive rubbing into scarified skin. Infection through undamaged epithelium is not successful. Neisser did not obtain infection even when rubbing virulent material into the nasal mucosa, the surface of the tonsils, or into the conjunctivae. Subcutaneous infection, according to reports by the majority of authors, is unsuccessful (Metchnikoff, Roux, Neisser, and others). The same applies to intravenous and intraperitoneal infection and to infection through the cornea. However, Salmon reported positive results of infection through the cornea, and Tomashevsky succeeded in infecting monkeys with syphilis by introducing material under the skin of the eyelid. Infection by inoculation into the testicle was obtained by Hoffmann, Löhe, Mulzer, and some other authors. Passages of the virus from lower monkeys often give poorer results, but Neisser, Finger, Landsteiner, and others believe that this depends not on the weakening of the infectious principle (virus) in lower monkeys, but on the smaller number of spirochetes in the material, which primarily determines the strength and speed of manifestation of the infectious process. Infection succeeds best when inoculating material from a fresh primary sclerosis or glands or from manifestations of secondary syphilis (papules, condylomas). Products of tertiary syphilis do not always yield infection; Neisser, Hoffmann, and others described positive results alongside negative ones. Experiments on infecting with the blood of syphilitics also succeeded only in a small percentage of cases, apparently due to the low content of spirochetes in the blood. Hoffmann managed to infect a monkey with the cerebrospinal fluid of a syphilitic. Syphilis was successfully inoculated into monkeys upon the introduction of blood and mush from the organs of congenital syphilitics. The manifestations of the disease in monkeys are generally similar to those observed in man. Scarifications at the site of inoculation first heal, and only after a more or less prolonged incubation period do specific changes appear, even in the case where the inoculation site was excised a few hours after infection. The duration of the incubation period is 3–4–5 weeks (from 15 to 65 days according to Neisser, Baermann, and Halberstädter), on average 30 days (Metchnikoff and Roux). Primary lesions have a diverse appearance: either a dark blue hard infiltrate or an ulceration with breakdown, sometimes they have a papular character or completely resemble a human primary sclerosis; the character of the primary lesion does not depend on the animal species. Phenomena of secondary syphilis were observed in all species of monkeys. In higher animals, especially chimpanzees and gibbons, secondary phenomena in the form of cutaneous papular rashes are mostly clearly expressed. In the orangutan and lower monkeys, they are encountered significantly more often and are completely denied by many authors. But other authors (Zabolotny, Hoffmann, Löhe, and others) describe spotted and papular rashes on the skin and papules on the mucous membranes in lower monkeys as well. The internal organs of monkeys (spinal cord, liver, lungs, muscles, and adrenal glands), according to Neisser's studies, turned out to be uninfectious upon passage to other monkeys, but the spleen, bone marrow, lymph glands, and testicles sometimes caused infection. The presence of spirochetes in the spleen and bone marrow of lower monkeys, despite the absence of secondary phenomena, indicates the generalization of the virus in these animals. Worms proved the presence of infection in monkeys (Rhesus) infected with syphilis but showing no external disease manifestations by inoculating the inguinal glands into rabbits 6.5 months after infection with a positive result, and thus established the presence of asymptomatic infection in monkeys (see below). According to histological structure, the syphilitic lesions of monkeys are analogous to the corresponding lesions in humans. Spirochetes in syphilis-infected monkeys were detected in smaller numbers than in cases of syphilis in humans. In higher monkeys, significantly more spirochetes were usually found in syphilitic lesions than in lower species; in the latter, the presence of spirochetes can always be demonstrated in lymph glands. In 1906, Bertarelli repeated Hansel's experiments (1881) and proved that rabbits can also be infected with syphilis. By inoculating syphilitic material onto the cornea or introducing it into the anterior chamber of the eye, after a rather long incubation period he obtained inflammation of the cornea of a syphilitic character, which was proved by the histological picture and the presence of spirochetes. Other authors confirmed Bertarelli's data; both Bertarelli and other authors proved the translatability of syphilis from rabbit to rabbit and to monkeys. Infection is produced by introducing small pieces of tissue containing spirochetes into the anterior chamber of the eye or by rubbing material into the scratched cornea. Schellack, Brown, and Pearce obtained infection by simple instillation of material containing spirochetes into the conjunctival sac. Syphilitic keratitis in the rabbit, obtained by inoculation of syphilitic adrenal glands, juice from lung tissue, and products of tertiary syphilis, has been described. The incubation period lasts 4–6 weeks, but a later infection—2–3 months and even 150 days after infection—has also been described. Usually, the following phenomena are observed: first, inflammation develops at the site of inoculation with clouding of the cornea and vascular injection, sometimes with suppuration; after 5–10 days complete healing sets in with clearing of the cornea, and after a more or less prolonged incubation period, phenomena of parenchymatous keratitis of varying strength develop—from clouding to suppuration and breakdown. Papular and gummatous formations on the cornea are described. The iris is also involved in the process (Tomashevsky, Finkelstein). Syphilitic keratitis in the rabbit usually heals after some time; relapses are quite frequent (Grigoriev, Yarysheva, Batrachenko, Kashinsky, and others). Uhlenhuth and Mulzer reported most recently that they never had to observe the generalization of the process after inoculation of syphilis into the rabbit cornea. However, Grouven, Shereshevsky, and Hoffmann reported on phenomena of general body lesion observed by them (after inoculation into the eye) in the form of skin lesions, hair loss, and disturbance of the general condition of the animals. Grigoriev reported the transmission of syphilis to offspring by a female rabbit infected with syphilis in the eye. The syphilitic virus transmissible to the rabbit does not lose its virulence for monkeys, which has been repeatedly proved experimentally by various authors. By introducing the syphilitic virus into the testicle and onto the scrotum of the rabbit, it is possible with great consistency to obtain both local and general specific changes. Testicular syphilomas represent material extremely rich in spirochetes and easily accessible for experiment. This method was developed in a series of works by Uhlenhuth and Mulzer; its application for studying experimental syphilis was widely carried out in the studies of numerous authors. Material for inoculations can be spirochete-containing tissue juice from a chancre, weeping papules, or pieces of a chancre or papules. This material is introduced with a pipette or syringe into the thickness of the testicle or under the skin of the scrotum. Pieces of tissue are best introduced into incisions of the skin (skin pockets) of the scrotum. Infection can also be obtained by rubbing into the scarified skin of the scrotum. Intradermal infection with a positive result was described by Chesney. When inoculating material from a human, a positive result is obtained in a smaller number of cases (8–25%) than with passages from rabbit to rabbit.
The passage virus acquires increasingly greater virulence upon successive inoculations, and its inoculability becomes absolute, reaching 100%; at the same time, the time of appearance of primary lesions (the incubation period) decreases; the latter also become sharper and more severe. The results of inoculations also depend on the method of inoculation, the nature of the material, and the breed of the rabbit. As with syphilitic keratitis, the virus retains its virulence for humans in this case as well; this has been proven by several cases of laboratory infection of humans from syphilitic rabbits. Infection resulting from inoculation in rabbits can manifest in various forms: 1) in the form of ulcers on the skin of the scrotum (typical chancre or atypical ulcerations); 2) in the form of inflammation of the testicle and epididymis (syphilitic orchitis); 3) inflammation of the testicular membranes (syphilitic periorchitis). Spontaneous healing of these syphilitic lesions usually occurs very slowly; chancres can persist from 4 to 8 months. From an anatomical-pathological point of view, the described lesions are granulation tumors consisting of lymphoid cells and, in the central part, of tissue resembling embryonic connective tissue. Necrosis or caseous decay does not occur in them, unlike in the syphilitic lesions of adult humans. Based on the histological picture and the extraordinary abundance of spirochetes, rabbit syphilis is compared with the congenital syphilis of the human fetus. As the primary phenomena gradually disappear, generalization of the virus throughout the entire organism ensues, expressed by the swelling of lymph nodes, disease of the second testicle, changes in the cornea; the virus can be found in the spleen, liver, bone marrow, aorta, heart muscle (Grigoriev, Yarysheva). Secondary syphilitic phenomena upon infection of rabbits into the blood and upon infection by inoculation into the testicle turned out to be completely similar to those observed in secondary syphilis in humans and consist of specific changes in the skin, mucous membranes, bones, nails, etc., changes in the nasal cartilage and the tip of the tail. The frequency of appearance of general syphilitic phenomena, according to Grosman, is 56.5% with inoculations into both testicles. Bone changes were studied using X-rays and were found in more than 50% of cases as a very early sign of syphilis. In addition to syphilitic conjunctivitis, keratitis, and iritis, diseases of the fundus oculi (choroiditis, chorioretinitis) have been described, occurring upon infection with certain strains in 70-95% of cases. Lesions of the central nervous system in rabbit syphilis have been established with certainty in recent times. Histological changes of the brain substance and pia mater (Steiner, Biach, Jakob) speak with certainty for the participation of brain tissue and membranes in the syphilitic process in rabbits. Snesarev and Finkelstein observed clinical symptoms of cerebellar damage in a rabbit inoculated in the testicle, and upon autopsy discovered a cerebellar gumma with changes in the membranes and degeneration of conducting nerve pathways. In addition, pathological changes in the cerebrospinal fluid have been described in syphilitic rabbits, expressed by an increase in the number of cells and globulins and in the appearance of a specific colloidal reaction of the cerebrospinal fluid (Goldsol and Mastix reaction). However, work in the experimental departments of the State Venereological Institutes in Moscow and Odessa did not confirm this. In addition to inoculations of the syphilitic virus into the testicle and under the skin of the scrotum, other inoculation methods were also studied. Inoculations on the skin outside the genital area yield significantly poorer results. However, Uhlenhuth and Mulzer managed to obtain primary syphilitic lesions in a rabbit after scarification of the eyebrows, and Kolle, Ruppert, and Moebius managed to obtain infection upon infection with a virulent strain (100 passages) under the skin of the back. Infection by introducing the virus under the dura mater or inside the brain was rarely successful. The possibilities of transmitting rabbit syphilis sexually are still in doubt: in the few cases where a positive result was obtained, one must keep in mind the possibility of error—confusion with spontaneous rabbit spirochetosis. Experimental study of the transmission of syphilis from parents to offspring has not yet yielded completely definite results. There are isolated observations (Wiman, Grigoriev) on syphilitic phenomena in offspring when mothers are infected. Experimental rabbit syphilis has repeatedly been used for the diagnosis of human syphilis, for determining the content of the virus in various parts of the organism. Uhlenhuth and Mulzer were very heavily engaged in studying the blood of syphilitic patients. They inoculated 2 cm3 of defibrinated blood of a patient into the testicle of a rabbit and often obtained positive results. In cases of secondary syphilis—in 75%, in latent syphilis—significantly less often. Out of 8 cases of tertiary syphilis, blood infection succeeded in only one. The blood of children with early congenital syphilis gives infection to rabbits, while the blood of patients in the late stages of congenital syphilis does not cause infection. Inoculations of urine, saliva, and sweat of syphilitics in the secondary period of the disease always yielded a negative result. The presence of spirochetes in the milk of syphilitic wet nurses has been proven by inoculation experiments performed by Uhlenhuth and Mulzer; Finger and Landsteiner upon inoculating milk into monkeys, and Schwarz and Schubert into rabbits and upon microscopic examination did not find spirochetes. Semen taken at the height of the syphilitic infection yielded infection in two cases out of 6 (Uhlenhuth and Mulzer). Cerebrospinal fluid does not always cause infection: according to Chesney and Kemp, in the early stage of syphilis in clinically unchanged cerebrospinal fluid, spirochetes can be found in 15% of cases. Successful infection of rabbits with blood and cerebrospinal fluid has been repeatedly performed by many authors, although Uhlenhuth, Steiner, and Mulzer in 19 cases of tabes dorsalis and progressive paralysis did not yield infection from inoculations with cerebrospinal fluid. Expansion of the base of experimental syphilis by infection of other animals. Experiments with cold-blooded animals (frogs), birds, various mammals (dog, cat, sheep, and especially the pig) yielded negative or insufficient results for practical application. Only data obtained on guinea pigs and mice have some significance. In experiments on infecting guinea pigs with syphilis (Bertarelli, Truffi, Tomashevsky, and others), keratitis, infiltrates, and primary sclerosis on the testicles were obtained. Passages were rarely successful, but the virulence of the virus did not increase in the process. Recently, Kolle and Evers showed that infection of guinea pigs in the absence of external manifestations of the disease yields a latent infection, which can be detected by inoculating the lymph nodes of the infected animal into rabbits. By this same method, Kolle and Schlossberger discovered that by inoculating pieces of chancre into mice or rats under the skin, one can obtain an asymptomatic, latent infection in these animals. The presence of the syphilitic virus in them 3–4 months after infection can be proven by inoculating their glands, spleen, or brain into rabbits. Great interest was aroused at one time by reports from Argentine researchers Jauregui and Lancelotti on the high susceptibility of the llama to syphilis. After inoculation of human material, a chancre appears after 14 days, then a secondary stage rapidly ensues, manifesting in the form of roseola, papules, etc., as in humans. This is followed by a tertiary stage with gummata of internal organs, bone and brain lesions. The animals die after 3 years. Transmission to offspring was observed. However, upon verification by a number of researchers (Hoffmann, Zurhelle, Kolle, Mulzer, and others), these data were not confirmed; the llama turned out to be insusceptible to human and rabbit syphilitic virus, and the serum of the inoculated animal has no therapeutic effect whatsoever, as asserted by the aforementioned Argentine authors. The significance of the experimental study of phenomena was particularly manifested in the development of the interesting and complex question of immunity in syphilis. Until the end of the 19th century, the view established by Ricord dominated, that syphilis leaves behind a long-lasting immunity, after which the number of observations on reinfection with syphilis in humans constantly increased. The resolution of the question became possible only with the development of methods of experimental syphilis. Experiments were conducted along the lines of studying the phenomena of superinfection and reinfection. Bruck, Finger and Landsteiner, and Neisser performed a large number of studies on monkeys. They found that superinfection performed shortly after the first infection (9–14 days) yields typical primary sclerosis. Gradually, as the virus becomes generalized, the capacity for reinfection weakens, so that superinfection may not manifest at all. Kolle studied this question in very great detail on rabbits. He infected rabbits with syphilis using the Truffi strain, and then at various periods after infection superinfected them with the same strain. Within 60 days after the first infection, superinfection was successful in 50–60% of cases, and between the 60th and 90th day—only rarely; typical chancres appeared at the site of superinfection. After the 90th day and up to several years after the first infection, superinfection was never successful.
To further clarify the question of immunity in syphilis, Colle undertook additional studies, modifying them in that he performed superinfection not with the same strain by which the rabbit was infected for the first time (homologous), but with another (heterologous), e.g., the Nichols strain after a primary infection with the Truffit strain, the Kuznitzky strain after the Nichols strain, etc. This kind of superinfection, performed 4-5 months after the initial infection, in a significant number of cases (28.5 - 62.5%) gave a positive result, manifesting as typical chancres, while controls (superinfection with the homologous strain) gave a negative result in all cases. From these experiments, Colle concludes that in rabbits infected with syphilis, a "panimmunity" against all syphilitic strains is not always developed, but only a "monoimmunity" against the specific strain with which the animal is infected. In humans, according to Colle, there is "panimmunity," as indicated by the rarity of secondary infection in syphilitic individuals who frequently come into contact with heterologous syphilitic strains. Chesney believes that man does not possess panimmunity, and the rarity of reinfection depends on the insignificant amount of infectious material with which he comes into contact. Verification work by Prigge and Rothermundt showed that an insignificant amount of infectious material is sufficient to infect a rabbit. On the substance of the matter, it must be said that it is hardly possible in this regard to establish a difference in the nature of immunity between humans and rabbits, since in the latter as well, heterologous strains do not always cause superinfection (in 28.5-62.5%). It must be noted that the studies described deal only with the so-called "chancre immunity," i.e., a state of the organism protecting it from the appearance of a primary skin lesion—the chancre. At the same time, the question remains open whether the organism is protected from a new penetration of syphilitic spirochetes into it (see below). New and interesting circumstances concerning immunity were discovered during the treatment of infected rabbits. Colle treated infected syphilitic rabbits in the first 45 days after infection. Repeated infections at late periods (more than 90 days after the initial infection) mostly caused the appearance of typical chancres in them. Colle believed that this infection is a reinfection, which indicates the complete sterilization of rabbits with the early administration of the medicinal substance. Brown and Pearce, when treating syphilitic rabbits with non-sterilizing doses of salvarsan, observed a delay in the development of chancre immunity in them. Buschke and Kroo, working with relapsing fever spirochetes, came to the conclusion that the sterilization of spirochetal diseases by chemotherapeutic drugs is generally impossible. In their opinion, treatment can only destroy the clinical manifestations of the disease and retard the development of immunity, but the causative agents of the disease nevertheless remain in a latent state in the organism, and therefore reinfection is only a superinfection, not a reinfection, and does not prove the complete sterilization of the organism. Colle treated syphilitic rabbits with large doses of salvarsan after the 45th day of the disease; upon re-infection of such rabbits, chancres mostly did not appear. On this basis, Colle concludes that late treatment with large doses is not able to sterilize the syphilitic infection. All these data shed light on the nature of immunity in syphilis. Colle believes that in this case there is not a true active immunity, but an "infectious" immunity, i.e., such a state of the organism when, in the presence of infection within it, it is protected from reinfection by the same virus; infectious immunity depends on the presence of the infectious agent in the organism and disappears upon complete cure. Chesney and Kemp confirmed Colle's data, but disagree with his explanation of the nature of immunity. In their opinion, a true active immunity arises in syphilis, and therefore they consider sterilization of the organism possible with late treatment, and view the absence of reinfection as an indicator of active immunity, but not of the presence of the causative agents of the disease in the organism. Uhlenhuth and Grossmann also joined Chesney's views. However, these views are insufficiently substantiated by experimental material, whereas data on spirochetal infections in general and on asymptomatic syphilis in particular (see below) contradict them. Pearce and Brown in 1922 showed that in untreated syphilitic rabbits, a long time after the disappearance of all symptoms of the disease in the period of developed immunity, the presence of virulent spirochetes can be detected in the popliteal lymph nodes: inoculation of these nodes into healthy rabbits causes the appearance of typical chancres. The application of this method for detecting the syphilitic virus has acquired great importance for experimental syphilis. Colle and Evers used this method to study the speed of the spread of infection in the organism. It turned out that after infection into the scrotum, the presence of spirochetes in the inguinal glands can be demonstrated in a rabbit after 30 minutes, and in a guinea pig even after 5 minutes. Prigge found virulent spirochetes in the popliteal glands two weeks after infection. In Colle's experiments, in rabbits injected with an insoluble bismuth compound ("bismuth depot") and then infected with syphilis, typical chancres did not form. To test whether bismuth kills the introduced spirochetes, the popliteal glands of such rabbits were inoculated into the scrotum of healthy animals, and a positive result was often obtained. It turned out that, having delayed the manifestation of external symptoms, bismuth does not kill the spirochetes; thus, a latent, asymptomatic general infection was obtained in the rabbits receiving bismuth. Proceeding from this fact, Colle and Evers checked whether there is a similar asymptomatic infection in untreated rabbits. When rabbits are infected with syphilis, 90% of them give typical chancres, and 10% do not react with clinical symptoms to the infection, despite the fact that the pieces of syphilitic tissue introduced into them contain a huge amount of spirochetes. It was believed that these rabbits remain healthy because the spirochetes in their organism die for one reason or another. Such rabbits received the special name "Nuller". Colle and Evers inoculated the popliteal glands of such rabbits into the scrotum of healthy animals and in almost 100% of cases obtained typical chancres. Thus, it was established that rabbits not reacting with clinical symptoms to infection with syphilis, as a rule, contain virulent spirochetes in their lymph nodes, and the so-called Nullers almost constantly have an asymptomatic syphilitic infection. The method of inoculating the lymph nodes of syphilitic animals made it possible to study the questions of superinfection and immunity in syphilis in even greater detail. By combining in various ways during the superinfection of infected rabbits the lymph nodes containing heterologous and homologous strains of the virus, Colle and his co-workers discovered the simultaneous presence in superinfected rabbits of both the spirochetes introduced during the first infection and the spirochetes introduced during superinfection, even in those cases when the latter did not manifest itself by any external signs. Thereby, a positive asymptomatic superinfection in syphilis was proven. By inoculating the glands of rabbits treated with large doses of salvarsan and then reinfected, the possibility of asymptomatic reinfection was also proven. On the basis of all these data, it can be considered with certainty established that there is no true active immunity in syphilis that would destroy spirochetes entering the organism, protecting it from infection by the latter; these facts indicate that the observed phenomena of immunity represent only a (apparent) cutaneous chancre immunity. The question of the biological characteristics of various races of the pale spirochete also belongs to the field of experimental syphilis (see above). Chemotherapy of experimental syphilis. In the chemotherapy of syphilis, the most important are organic compounds of arsenic—salvarsan ("606") and neosalvarsan ("914"). Both preparations can produce complete sterilization of the organism (from spirochetes) when administered in an amount of 0.01-0.015 g per 1 kg of animal weight in the early stage of the disease (no later than 2-3 weeks after the appearance of the chancre). Their chemotherapeutic index in syphilis—the ratio of the maximally tolerated dose per 1 kg of weight to the minimum therapeutic dose per 1 kg of weight—is equal to 10, and according to American data even higher (between 10 and 20; Kolmer). When treated at later dates or with smaller doses, sterilization of the organism is not always successful, but an extremely favorable therapeutic effect is noted, expressed in the attenuation of clinical phenomena even in malignant forms of the disease or in cases unresponsive to other methods of treatment. Of particular interest are arsenic preparations—stovarsol, spirocid, stovarsolan, the advantage of which is that they can be administered per os. 0.4 g of the preparation per 1 kg of rabbit weight cures the external manifestations of syphilis in these animals.
In recent years, thanks to the work of Levaditi and his school, it has become clear that bismuth compounds (see) are of great importance for the chemotherapy of syphilis, among which the most important is trepol, a basic potassium, sodium, and bismuth tartrate. Bismuth preparations possess a very strong and prolonged prophylactic effect due to slow absorption from the depot. The administration of trepol to rabbits in an amount of 0.056 g of metallic bismuth per 1 kg of body weight exerts a prophylactic effect lasting not less than 152 days. According to the research of the French school, tellurium compounds act similarly to bismuth compounds. It was believed that antimony compounds, which play a significant role in the chemotherapy of protozoal diseases, are ineffective in spirochetoses. However, the work of Krichevsky, Pines, and Veyn (1933) showed that the antimony preparation stibosan, in experimental syphilis in mice and rabbits and in the treatment of humans, exhibits a stronger therapeutic effect than bismuth. The mechanism of action of chemotherapeutic preparations is still not entirely elucidated. Most arsenic and bismuth compounds do not act on spirochetes in vitro.
E. Geronimus. VII. Clinic and Diagnostics of Acquired Syphilis. Syphilis, being a chronic infectious disease, has a more or less definite course, characterized by specific clinical manifestations depending on the period of the disease and certain other causes. Its clinical manifestations most frequently affect the skin and mucous membranes, as well as the lymphatic system, but in almost any period manifestations on the part of the musculoskeletal system, internal organs, central and peripheral nervous system, and sensory organs may be observed. The general course of syphilis is conventionally subdivided into periods: primary, secondary, and tertiary, subdividing each of the periods into manifest, when disease manifestations are present, and latent, when these manifestations are absent. A period of usually late specific lesions of the central nervous system called meta- or parasyphilis is also noted. Such a subdivision of syphilis is, of course, conventional and needs some modification and supplementation. The general course of syphilis can be reduced to the following: as an infectious disease caused by a specific agent—the pale spirochete—syphilis requires special conditions for the transmission of infection from a patient to a healthy person. An indispensable condition for syphilis infection is the penetration of the pale spirochete into the organism through a damaged cornified layer of the epidermis or the surface of a mucous membrane, although other routes of transmission are also possible (cases are known, for example, of syphilis transmission during blood transfusion, and in such cases clinical phenomena developed directly from the secondary period, while the primary lesion—the hard chancre—was not observed in such patients—syphilis d'emblée). We are speaking, of course, of acquired syphilis, since for congenital syphilis there are special conditions for the transmission of syphilis from mother to foetus (see below—Congenital Syphilis). Infection with syphilis can occur through sexual intercourse with patients (sexual transmission) or by other means (e.g., during kissing, when breastfeeding a child, when using certain objects that were directly used by a patient immediately before, such as a cigarette, toothbrush, etc.—this is the so-called non-sexual syphilis, or syphilis of the innocent [syphilis insontium]). Cases of infection of medical personnel during work are known (infection of midwives, gynecologists surgeons, etc.), and sometimes of patients from medical procedures (e.g., earlier, cases of infection were noted during smallpox vaccinations, when the vaccination material was taken from the pustules of vaccinated children who turned out to be sick with syphilis—syphilis vaccinata). After infection, the development of the disease proceeds generally in the following order: initially after the moment of infection, objectively no syphilitic symptoms are noted at the site of infection, and this period takes a more or less prolonged interval (on average 2–3 weeks, although cases of a duration of 8 days are known, and on the other hand, 78 [Wolf], 90 [Meshchersky], and even 100 and 110 [Gougerot] days; in the latter two cases, such a long period could depend on prophylactic salvarsan injections). This period is called the first latent period of syphilis. Subsequently, the first signs of the disease begin to appear at the site of infection in the form of the so-called primary lesion or hard chancre (ulcus durum, s. induratum), which is a reaction to the pale spirochete that has penetrated and managed to multiply at the given site. The primary lesion has its own cycle of development, reaching maximum development in approximately 2 weeks, then remaining in the flowering period also for about 2 weeks, in order to subsequently undergo reverse development and healing also in approximately a 2-week period. This period of time from the appearance of the hard chancre to healing is called the primary period of syphilis, with a total duration of about 6 weeks (such terms are conventional and can fluctuate in one direction or another). The primary period of syphilis is presently subdivided into 2 periods: the primary seronegative period—from the moment of the appearance of the hard chancre to the moment of the appearance of a positive blood seroreaction (this interval fluctuates in time due to various causes and in particular the localization of the hard chancre, but in general it is equal to 2–3 weeks) and the primary seropositive period—from the moment of the appearance of a positive blood seroreaction to the healing of the hard chancre. After the healing of the hard chancre until the appearance of a rash on the body, i.e., until the appearance of the so-called secondary period of syphilis, a certain interval of time passes again, called the second incubation period of syphilis, or the second latent period; this term fluctuates in individual cases up to 2–4 weeks. Subsequently, abundant rashes on the body usually in the form of a spotted rash may appear in the patient, and from this moment the secondary period of syphilis sets in, with the initial appearance of the rash referring to the fresh secondary period of syphilis (syphilis condylomatosa recens) in contrast to rashes noted in the further course of secondary syphilis and appearing at various times, and such rashes belong to the secondary recurrent syphilis (syphilis condylomatosa recidiva). The secondary period can last quite a long time (2–3 years, and sometimes 5–10 and more years), at times producing outbreaks of external manifestations of syphilis on the part of the skin and mucous membranes, and at times remaining without clinical manifestations—the so-called secondary latent period of syphilis (syphilis condylomatosa latens). Usually, in the secondary period of syphilis, an abundant rash initially appears, and in further relapses an increasingly sparse rash, often arranged in the form of separate groups, frequently in the form of rings or arcs, and the rash is often localized in atypical places. The intervals of the latent period between individual relapses in the further course of syphilis become more and more prolonged, and then a very long latent period may result, following which manifestations of a completely different character can develop, usually in the form of deeply situated nodes of a specific infiltrate, the so-called gummas, which already refers to the tertiary, or so-called gummatous period of syphilis (syphilis gummosa). The tertiary period of syphilis can stretch for an indefinitely long time, giving certain manifestations at times (syphilis gummosa manifesta) or remaining in a latent state for a more or less prolonged period (syphilis gummosa latens). The peculiar course of syphilis with an incubation period, the peculiarity of manifestations in various periods of both the manifest and latent period is explained by the biological conditions of the pathogen of syphilis in the patient's body. As clinical and experimental observations show, the pale spirochete initially begins to proliferate at the site of its introduction; when its proliferation reaches a significant degree here, the first clinical signs of syphilis in the form of a hard chancre begin to appear at the given site. The entry into the lymph and blood stream and the transport of spirochetes into various organs and tissues usually occurs from the moment of maximum development of the hard chancre, although in some cases such transport of the pathogen into distant organs can occur from the moment of the initial introduction of spirochetes into the body. This is supported by experimental experiments with the inoculation of the pale spirochete followed by the surgical removal after a few hours of the skin area where the inoculation was made, as well as clinical observations on the appearance of early (preroeolic) nephritis, meningitis, the appearance of a positive reaction in the cerebrospinal fluid earlier than in the blood, etc. In the blood, the spirochete is an accidental guest, since it is a tissue parasite, which is why its presence in the blood is detected with difficulty; experimental inoculations of patients' blood give a positive result in various periods of syphilis, and for a successful inoculation one has to take a comparatively large amount of blood. The hematogenous dissemination of spirochetes, taking place in the primary stage, creates foci of spirochetes in various organs and tissues that can cause specific tissue changes in the further course of syphilis. Not only various skin manifestations of fresh and recurrent syphilis, but also lesions of internal organs and the central nervous system, including progressive paralysis and tabes dorsalis, can be explained by the proliferation of spirochetes brought here back in the primary stage of syphilis. Of course, repeated transport of spirochetes from active foci of secondary syphilis is also possible, but at the same time newly brought spirochetes cannot take root at the given site (Engmann, Eberson) until the organism has freed itself from the primary infection, which is supported by experimental observations on animal superinfection (see above—Experimental Syphilis). With such inoculations, it is not possible to obtain a characteristic primary lesion; at the site of inoculation, a papule of the same character is usually obtained as with the luetin or pallidin skin reaction (see below), and subsequently those phenomena that are characteristic of primarily inoculated syphilis are not obtained, i.e., it is not possible to obtain generalization of syphilis. The abundance of the rash in fresh secondary syphilis and its scarcity in relapses, especially repeated ones, can be explained by the fact that in fresh secondary syphilis, proliferation of the spirochete occurs in a large number of foci of its initial introduction.
As a result of the subsequent skin reaction in the form of a roseola at a given site, due to the immunobiological properties of the skin, the spirochete can no longer multiply and dies, and the skin acquires local immunity. Therefore, during relapses, a annular arrangement of eruption elements may appear due to the surviving spirochetes that have begun to proliferate and were located at the periphery of the initial eruption elements. The conditions of local immunity of the skin can also explain the greater and greater scarcity of eruption elements during repeated relapses, as well as the fact that during late relapses the rash is often located in places not typical for a fresh secondary syphilis. The onset of the latent, or latent period of syphilis can also be explained by immuno-reactive phenomena on the part of the organism, as a result of which the surviving spirochetes temporarily become non-virulent. The peculiarity of the phenomena of the tertiary period, i.e., the formation of gummatous changes, can be explained by the allergic state of the skin after the past phenomena of the secondary period. This is also supported by the fact that sometimes at the site of the former primary lesion a powerful infiltrate (reinduratio) arises again, which can ulcerate, and such an ulcer has a great resemblance to a gummatous one (ulcus redux, s. pseudogummosum). General course of syphilis. Syphilis in individual cases proceeds differently. Sometimes cases are noted with normal more or less correctly alternating relapse phenomena and intervals of the latent period. Sometimes cases are noted with a sluggish course, with scant manifestations and prolonged latent periods. In some cases, the course is stormy with an abundance of pustular phenomena and frequent relapses, as well as with a tendency to the appearance of gummatous lesions along with phenomena of the secondary period (galloping, or malignant syphilis - lues maligna). Very often, a sluggishly proceeding syphilis almost without relapses entails the development in the future of symptoms of organic lesion of the central nervous system, which gave reason to admit the possibility of the duality of the syphilitic virus: dermo- and neurotropic (see above - Experimental Syphilis). Primary period of syphilis is characterized by a single manifestation in the form of a primary lesion, or affect (hard chancre - ulcus durum, s. induratum), and a somewhat later developing lesion of the regional lymph glands. As clinical observations and experimental inoculations show, after the incubation period, a red spot appears at the site of infection, which soon takes on the character of a papule, first peeling, and then becoming moist on the surface or covered with a crust, under which a superficial erosion or, much more rarely, a superficial small ulcer is discovered, gradually increasing in size with the simultaneous development of a dense infiltrate of its bottom. A typical hard chancre is a rounded or oval erosion resting on a dense infiltrate, without acutely inflammatory phenomena in the surroundings [see separate table (p. 527-528), fig. 3]. The size of the erosion ranges from several millimeters ("dwarf chancre") to 1 cm in diameter, and sometimes larger or even very significant sizes. The edges of the erosion are usually even, not undermined, sometimes slightly elevated above the level of the erosion. The bottom is red, sometimes covered with a small "sebaceous" coating, does not fester. The discharge is serous fluid; after irritation of the erosion by friction, the discharge appears in an abundant quantity, the so-called Reizserum, which is used for examination for pale spirochete. The induration of the bottom gives a tactile impression of cartilaginous density; depending on the localization of the chancre and some other causes, this compaction may be weakly expressed; sometimes it is very flat, superficial, giving a tactile impression of a plate of parchment paper - the so-called "parchment chancre" (chancre parchemine, s. papyrace). Varieties of the typical hard chancre depending on localization are as follows: on the glans penis usually in the form of a rounded erosion with parchment induration; in the external opening of the urethra also in the form of an erosion on one or both lips, with some compaction and protrusion of one or two lips, sometimes creating difficulty in urination; in the urethra itself (usually in the navicular fossa) the chancre can have significant induration, simulating a paraurethral infiltrate, more often it is in the form of a superficial erosion diagnosed by a urethroscope; in the corona glandis the chancre is in the form of a typical erosion with very strongly expressed cartilaginous induration; the erosion usually has a bean-like shape, with the concave side located in the groove, and the convex toward the prepuce; on the frenulum the chancre has slit-like outlines, sometimes in the form of a small ulcer, not giving, unlike the soft chancre, perforation of the frenulum; on the inner leaflet of the prepuce the chancre with the character of a parchment one; on the free edge of the prepuce the chancre of the form of a crack running across the free edge from the inner leaflet of the prepuce to the outer; sometimes several chancres are noted, diverging radially from the opening of the preputial sac (in patients with congenital phimosis), and from constant irritation by urine, inflammatory phenomena may join, amplifying the phenomena of phimosis; on the skin of the genital organ the chancre usually has rounded outlines with parchment compaction and with discharge drying into a crust; on the skin of the scrotum also in the form of a parchment chancre, reaching here often large sizes and resembling an erosion from a second-degree burn (ulcus induratum combustiformis). In women on the labia majora from the inner side, the chancre is in the form of a rounded erosion, sometimes with a somewhat elevated bottom covered with a "sebaceous" coating, with a clearly expressed induration; sometimes a special form of chancre is noted here (the so-called indurative edema of the labium majus - oedema indurativum), characterized by a sharp increase in the lip, as if its edema, and significant compaction, and the initial erosion can completely epithelialize and not be detected upon inspection; on the labia minora the chancre usually has the appearance of an erosion with parchment induration, which is more clearly seen when the chancre is localized on the edge of the lip; on the clitoris in the form of an erosion with parchment induration; on the prepuce of the clitoris the erosion can have a fairly significant compaction; in the opening of the urethra, the erosion can protrude outward due to the infiltration of its bottom and bleeds easily; on the posterior commissure of the labia majora, the chancre has the appearance of a superficial erosion or small ulcer with parchment induration; at the entrance to the vagina (usually on the remnants of the hymen) in the form of a parchment chancre; on the vaginal mucosa the chancre is rare, usually in the form of an erosion; on the uterine cervix the chancre is often of rounded outlines, usually in the form of an erosion, sometimes in the form of a ring surrounding the uterine os; the chancre of the mucous membrane of the uterus cannot be seen clinically; in such cases, only the examination of uterine mucus for pale spirochete can give grounds for the diagnosis of a chancre. In the area of the mouth, the chancre has a different shape depending on localization. On the red border of the lips, it appears in the form of an erosion or superficial ulcer, usually covered with a crust of dried discharge, without noticeable compaction of the bottom of the ulcer, and sometimes with a sharp thickening and compaction of the entire lip of the character of indurative edema; in the corner of the mouth, the chancre often appears in the form of a fissure-like ulcer, painful and bleeding; on the oral mucosa, usually in the form of a rounded or oval erosion, and on the frenulum of the tongue, sometimes in the form of a slit-like ulcer, and sometimes in the form of ulcers on the lateral surfaces of the tongue, easily bleeding, painful and complicating chewing. On the tonsils, various forms are found, more often in the form of an ulcer covered with plaque or decay with a more or less sharply expressed compaction of the tonsil; the so-called diphtheroid, ulcerative or gangrenous chancre is often noted. On the wings of the nose, an erosion or superficial ulcer is accompanied by swelling and compaction, and on the nasal mucosa the chancre is usually in the form of a rounded erosion. In the region of the eye: on the edge of the eyelids in the form of an elongated erosion with swelling and compaction of the edge of the eyelids; in the corners of the eye, the chancre sometimes has a Y-shape; on the conjunctiva in the form of an erosion, sometimes rising above the level of the surrounding parts and ending with sharp boundaries at the cornea, if the erosion reaches it [see separate table (p. 551-552), fig. 2]. At the anus, the chancre has the appearance of a fissure-like ulcer with thickened edges, sometimes it captures several folds of the anal opening (rugose chancre); defecation is accompanied by significant pain and bleeding. In the area of the nipple [see separate table (p. 527-528), fig. 2], the chancre is often found in the form of a fissure-like ulcer at the base of the nipple, on the nipple itself and in the surrounding parts - usually in the form of an erosion or superficial ulcer covered with a crust. On the fingers, the chancre has the appearance of an ulcer, often accompanied by inflammatory phenomena in the surrounding parts from secondary infection.
On other parts of the body, the chancre appears as an erosion or a superficial ulcer covered with a crust, with a more or less pronounced induration of the base, and sometimes with inflammatory phenomena in the surrounding area. A complicated hard chancre is observed under various conditions: with secondary infection, from irrational treatment with caustic substances, and sometimes from local conditions. As special forms, the so-called gangrenous and phagedenic chancres are noted; in the first, the appearance of gangrenous areas of the base and edges of the chancre is noted in the form of dirty brown or black disintegrating necrotic foci with sharp reactive phenomena in the surrounding area and a constant increase in the size of the ulcer along the periphery and into the depth from the rejection of dead parts by demarcation inflammation. In the phagedenic chancre, the growth of the ulcer occurs as a result of the constant disintegration of the base and edges of the ulcer in small areas ("molecular disintegration"). With such forms of chancre, the search for the pale spirochete is difficult, since an abundance of various bacteria (Bac. pyocyaneus, Spiroch. refringens, etc.) is usually noted and there is a symbiosis of the pale spirochete with Vincent's fusiform bacillus (fusispirillosis). - The mixed chancre appears as a result of simultaneous infection with the streptobacillus of soft chancre and the pale spirochete, with the clinical picture of soft chancre developing initially, and after the expiration of the incubation period, the phenomena of hard chancre begin to join with the characteristic induration of the base. Changes in the lymphatic system in the primary stage begin to be noted 1-3 weeks after the appearance of the hard chancre; first of all, the lymphatic vessels leading from the site of the primary lesion to the nearest (regional) lymph glands turn out to be affected. Clinically, the lymphatic vessels turn out to be somewhat thickened and indurated, which is sometimes ascertained by palpation. The lymph glands always turn out to be noticeably changed: they are enlarged, dense, not fused with each other and with the surrounding tissues, completely painless, and mobile. Acute inflammatory phenomena are absent; they can appear only in the presence of a secondary infection, and then soreness and even an outcome into purulent adenitis may appear. Characteristic of the specific lesion of the lymph glands (scleradenitis) is the multiplicity of the lesion of the glands. In the further course of the primary period, specific changes also occur in other lymph glands more distant from the primary focus, and by the time the secondary period sets in, the lymph glands accessible for palpation usually turn out to be changed everywhere (polyadenitis specifica). The diagnosis of hard chancre is based on the clinical picture of the lesion and is finally confirmed by bacterioscopic examination for the pale spirochete. Anamnestic data can only have secondary importance. In some cases, with a suspicion of a hard chancre and the absence of spirochetes in the discharge, which often happens with an already healing or complicated chancre, as well as with a chancre of the oral cavity, where during a bacterioscopic examination, a dental spirochete (Spirochaeta dentium) simulating the pale one may appear, one has to resort to puncture of the lymph gland to study its juice. - Differential diagnosis of hard and soft chancre is based on the comparative distinguishing features of the ulcer of soft and the erosion of hard chancre (base, edges, discharge); on the presence in soft and absence in hard chancre of inflammatory phenomena in the surrounding skin; on the multiplicity and appearance of new ulcers in soft and the singleness or simultaneous appearance of several erosions in hard chancre; on the absence or appearance of a single, moreover painful, with acute inflammatory phenomena and a tendency to transition into an abscess of the affected lymph gland in soft chancre and on the multiple characteristic regional scleradenitis without a tendency to acute inflammatory phenomena in hard chancre; on the results of bacterioscopic examination for streptobacillus in soft and the pale spirochete in hard chancre. Large diagnostic difficulties in gangrenous or phagedenic, both soft and hard chancre, can be resolved by a thorough bacterioscopic examination. Tuberculous ulcers differ from hard chancre relatively easily by an uneven, covered with pus and disintegration, easily bleeding base, slow development, multiplicity of small ulcers, the presence along the periphery of unulcerated tubercles, a chronic course, as well as by the data of the general state of health and bacterioscopic examination for the tubercle bacillus. Epithelioma is easily distinguished from hard chancre by an easily bleeding base, thickened edges, a slow course, and appearance in elderly persons. In difficult cases, a histological examination of the biopsied tissue is performed. Erosions of herpes zoster are distinguished by the polycyclicity of the outlines of the edges as a result of the close arrangement of a group of vesicles, and the absence of hardening. Scabietic excoriated nodules are distinguished by multiplicity and the presence of signs of scabies in the patient. Basal erosions of the uterine cervix are located more often on the posterior lip and appear as if flowing out of the uterine os, whereas hard chancre is more often eccentric in relation to the uterine os. Other erosive processes, as well as ulcers and fissures, differ from hard chancre by the absence of signs of chancre and regional scleradenitis, as well as the presence of the main signs of a given disease. The secondary period of syphilis ("secondary S.") is characterized by clinical manifestations mainly from the skin and mucous membranes in the form of rashes from various morphological elements, the so-called syphilids. The appearance of the rash is often preceded by symptoms of a general character in the form of malaise, a febrile state, headaches, and pains in the bones of the extremities, intensifying at nights. A wide variety of rash elements can be reduced to three main forms: 1) macular, or erythematous syphilid (syphilis cutanea maculosa, s. roseola syphilit.); 2) papular (syphilis cutanea papulosa), 3) pustular (syphilis cutanea pustulosa). Each of these forms in its turn gives a variety of varieties of rash elements, which may partly depend on the localization of the rash elements, their duration, the duration of the disease (fresh or recurrent S.) and other causes. - The general characteristic of the rash elements boils down to the following: the color is red with a bluish or brownish tint, but not a bright inflammatory one; it depends on stagnant hyperemia and infiltration, as well as on the impregnation of the tissue with the coloring matter of the blood, which is especially noticeable with the long-term existence of the rash elements. The shape of the syphilids is generally roundish with fairly sharply expressed boundaries. Their size is diverse - from a millet grain
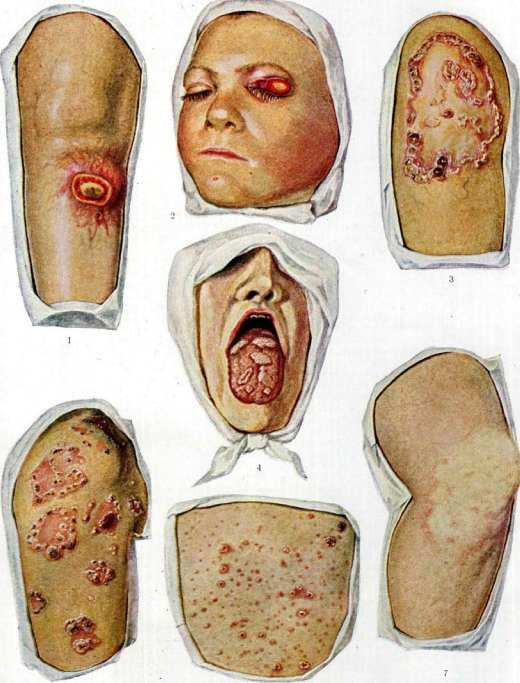
Fig. 1. Syphilitic gumma. Fig. 2. Hard chancre of the palm. Figure 3. Papular syphilid (after Finger). Fig. 4. Syphilitic papule
Fig. 7. Lenticular (tertiary) syphilids, the size of a lentil, and sometimes of larger dimensions. Usually the size of individual elements is uniform in each individual case, which is why a distinction is made between small-spotted, small-papular, small-pustular syphilid or large-spotted, large-papular, large-pustular. The surface of the syphilids remains smooth until secondary changes appear on them from the formation of scales, crusts, etc. The localization of the eruption elements is characteristic of fresh forms of syphilis: the lateral surfaces of the trunk and the flexor surfaces of the extremities with frequent extension to the palms and soles with a symmetrical arrangement of the rash; the face is affected less often; in recurrent forms, especially in late relapses, the rash is scarcer and its localization becomes atypical (sometimes on the extensor surfaces of the extremities), and symmetry is often lost. It is considered characteristic of syphilis to have a variety of eruption elements in each individual case (polymorphism of the rash), for example, along with a spotted rash, a papular rash (syphilis cutanea maculo-papulosa), or a papular and pustular rash (syph. cutanea papulo-pustulosa), or all three types of secondary rash (syph. cutanea maculo-papulo-pustulosa). In addition to true polymorphism, one should note the so-called false polymorphism, when in the presence of uniform syphilitic efflorescences, secondary changes (crusts, scales, etc.) are noted on some of them. The course of syphilids varies depending on various conditions. Sometimes the eruption elements disappear independently: the roseola leaves no trace, while the papules leave behind pigmented spots that completely correspond in shape and size to the former papules. In other cases, the eruption elements persist stubbornly, sometimes increasing in size and taking on hypertrophic forms or giving vegetations. With specific treatment, they rapidly undergo reverse development, and often at the very beginning of treatment, especially after the use of salvarsan, a reaction is noted on the part of the eruption elements in the sense of a more distinct, sharp protrusion of them; they become brighter, the roseola sometimes takes on an urticarial character, and new eruption elements that were previously unnoticeable appear. This reaction (the Jarisch-Herxheimer reaction) usually occurs within the first day from the start of treatment and lasts a few hours or about a day, and then disappears, and the eruption elements subsequently quickly begin to undergo reverse development. The spotted, or erythematous, syphilid is characterized by the manifestation of a spotted rash or syphilitic roseola (syphilis cutanea maculosa, s. roseola syphilitica) [see separate table (p. 527-528), figure 1]. These spots appear weakly expressed, reddish in color with indistinct boundaries, irregularly rounded in shape, measuring in some cases only a few millimeters in diameter (small-spotted roseola), and in others of larger dimensions (large-spotted roseola). The former is usually encountered in fresh secondary syphilis, the latter in relapses. On mucous membranes, the spotted rash is clearly noticeable in the form of sharply outlined red spots. Varieties of syphilitic roseola: roseola elevata—spots are somewhat elevated above the skin level like wheals (often roseola becomes such during the Jarisch-Herxheimer reaction); roseola annularis—spots of annular outlines (usually in relapses); roseola configurata—spots in the form of an open ring or oval, form various figures, touching with their ends neighboring spots; roseola granulata—a roseolous spot on the surface of which an abundance of minute nodules in the region of the skin follicles is noted. The diagnosis of spotted syphilis is based on the morphological features of syphilitic roseola, typical localization, the absence of subjective symptoms, and the presence of other signs of syphilis (remnants of primary sclerosis, scleradenitis, etc.). Differential diagnosis with acute infectious diseases (measles, rubella, typhus, etc.) is easily carried out on the basis of the nature of the eruption elements and data on the general state of health. Toxic or medicinal rashes are easily distinguished by their morphological features, preferential localization on the extensor surfaces of the extremities, general phenomena, anamnestic data, and the absence of indications of syphilis. Urticaria differs from wheal-like roseola by the variability and inconstancy of the rash, chaotic localization, the presence of burning, itching, and dermographism. Blue spots (maculae coeruleae) from pubic louse bites are easily distinguished from roseola by their color, they do not disappear upon pressure, and the producing cause, i.e., pubic lice, is easy to find. Pityriasis rosea of Gibert, although it may completely correspond in its localization to syphilitic roseola, is easily distinguished from it by the diversity of the size of the eruption elements, bay-like outlines of the spots, the presence of a central scale and a mother plaque. Cutis marmorata can only resemble syphilitic roseola by its bluish tint, but it gives a picture of a peculiar reticular network that does not occur even with annular roseola. The papular syphilid (syphilis cutanea papulosa) is most frequently encountered in relapses of secondary syphilis and is characterized by the appearance of infiltrated, rounded nodules of a red-brown color [see separate table (p. 551-552), fig. 6]. Over time, desquamation may appear on the surface of the nodules (syph. cutanea papulo-squamosa), sometimes crusts appear (syph. cutanea papulo-crustosa) or pustules are formed (syph. cutanea papulo-pustulosa), and other changes are also noted (see below) depending mainly on localization. The main varieties of papular syphilis are small- and large-papular syphilids. The small-papular syphilid (syphilis cutanea papulosa miliaris, s. lichen syphiliticus) is characterized by the appearance of nodules the size of a poppy or millet seed, sometimes slightly larger, usually located in groups on various parts of the body surface, mainly on the trunk. The nodules are of a rather dense consistency, located in the region of the hair follicles; scales or crusts or small pustules are noted at the apex. This syphilid is more often encountered as a relapse and usually in persons with data on scrofuloderma or tuberculosis, resembling scrofulous lichen. The large-papular, or lenticular, syphilid (syphilis cutanea papulosa lenticularis) is characterized by the appearance of infiltrated brownish-red nodules ranging in size from a hemp seed to a lentil seed or larger dimensions, in abundant quantities or scattered as single elements, sometimes in combination with roseola in fresh secondary or early recurrent syphilis. In late relapses, this syphilid gives a group arrangement of papules in the form of rings, arcs, etc. In the further course, scales, crusts may appear on the nodules or pustules may form. Varieties of the papular syphilid depend on various causes and in particular on localization: syph. cutanea papulosa nummularis—large papules the size of a 10- or 20-kopeck coin; syph. cutanea psoriasiformis—abundantly desquamating papular elements of large dimensions, resembling psoriatic foci; syph. cutanea papulosa corymbiformis—group arrangement of papules, with a large papule located in the center of the group, and numerous small ones around it like a halo (cockard syphilid, or Bombensyphilid); papulae orbiculares—in persons with seborrhea, sometimes in the form of pinkish rings with a somewhat elevated periphery and a sunken center with radial folding, sometimes in the form of larger rings covered with greasy scales; sometimes in the form of elongated nodules (e.g., in the folds of the alae nasi), also covered with greasy scales; sometimes in the form of flat nodules of a whitish, pearly tint—papulae nitidae; syph. cutanea verrucosa—papules with papillary growths on the surface, covered with abundant horny layers; syph. cutanea framboesiformis—vegetating papules with a red, shiny moist surface, resembling raspberry berries; psoriasis palmaris et plantaris—papular syphilid of the palms and soles, desquamating on the surface; sometimes in the central parts the scales fall off, exposing the red surface of the skin, and in the peripheral parts the scales remain in the form of a border or cuff, hanging over the exposed part; clavi syphilitici—nodular elements on the palms and soles, covered with tightly adhering horny masses; keratodermia syphilitica—keratinization on extensive infiltrates having scalloped outlines at the periphery (group arrangement of papules merged with neighboring ones), with localization also on the palms and soles. Palmar and plantar syphilids usually appear in recurrent syphilis, sometimes being the only, but very characteristic, sign of syphilis.
On the hair-bearing parts of the skin, the following forms of papular syphilis are distinguished: impetigo capitis specifica—papules covered with crusts; syph. papillomatosa capillitii—vegetating papules. On "moist areas of the skin" subject to the irritating influence of sweat, urine, etc., papules take on a weeping character or an erosive appearance due to the maceration and shedding of the horny layer of the epidermis. Not infrequently they proliferate, taking on a hypertrophic character—papulae hypertrophicae, s. condylomata lata. Such papules are usually localized in the region of the anus and genitals, more rarely in other places where skin surfaces touch [see separate table (p. 527–528), Fig. 4]. On mucous membranes, flat papules with a whitish surface (plaques muqueuses), erosive and hypertrophic papules are encountered; sometimes the surface of the papules breaks down and they turn out to be covered with a grayish-dirt coating (diphtheroid papules) [see separate table (p. 551–552), Fig. 4]. The diagnosis of papular syphilis is based on clinical data of both the eruption elements themselves and the concomitant signs of syphilis (polyadenitis, etc.). In difficult cases, resort is made to bacteriological examinations for Treponema pallidum of the discharge from weeping papules or of expressed juice from a papule after scraping off the horny layer of the epidermis. Serological examination of the blood also takes place. The differential diagnosis of small-papular syphilis and lichen scrofulosorum is carried out on the basis of the distinguishing features of the latter: yellowish-red color, insignificant infiltration of the nodules, arrangement in groups of rounded outlines, localization usually on the trunk and extremely rarely on the extremities, uniformity of individual elements, and absence of false polymorphism. The course of lichen scrofulosorum with its simultaneous appearance of groups of nodules, absence of a tendency to the formation of pustular elements, and simultaneous regression without leaving pigment spots also serves as an essential sign for differential diagnosis. Lichen scrofulosorum usually appears in childhood, and in adults it occurs as an exception. Large-papular syphilis has to be differentiated from lichen ruber planus, which by its localization and leaving behind of pigment spots resembles papular syphilis, but differs from it by a yellowish- or bluish-red color, shiny surface, polygional outlines of the nodules with umbilication of the center, grouping, etc. When localized on the genitals, lichen ruber often gives annular formations simulating recurrent papular syphilis, but differing from it by the absence of scalloped outlines, pearly color, and the presence of polygonal nodules arranged in a ring. It is somewhat more difficult to differentiate hypertrophic lichen ruber (e.g., in the femorogenital folds) from hypertrophic papules, but even in such cases a bluish-red color with opalescent papillae on the surface and the absence of a tendency to weeping speaks in favor of lichen ruber. Psoriasis vulgaris differs from scaling syphilitic papules by the absence of a brownish tint and noticeable infiltration, as well as by the presence of characteristic symptoms of psoriasis and an abundance of silvery-white small scales easily removed by scraping with the phenomena of "stearin spot" and "punctiform capillary bleeding." Parapsoriasis (parapsoriasis en gouttes) is very similar to papular syphilis, but the absence of other signs of syphilis and the presence of characteristic scales in the form of "wafers" (especially distinct when scraped with a fingernail), as well as the appearance of petechiae in the surrounding skin, gives grounds for the diagnosis of parapsoriasis. Urticaria pigmentosa is not accompanied by infiltration; rubbing with a finger gives a characteristic wheal-like protrusion of the skin in the area of the pigment spot. Papulonecrotic tuberculid (folliclis, acnitis) is easily distinguished from papular syphilis by its chronic course, the presence of superficial necrosis, and characteristic scars. Weeping papules are distinguished from erosions of other origin by the presence of an infiltrate, regional adenitis, and examination of the discharge for Treponema pallidum. Hypertrophic papules are easily distinguished from pointed condylomas (condylomata acuminata) by their broad base, comparatively smooth surface, color, and rounded or scalloped outlines of the base. Vegetating pemphigus (pemphigus vegetans) develops at the site of a former blister, remnants of which are often visible in the form of a peripheral cuff; loose vegetations and the presence of initial blisters in the absence of signs of syphilis serve as distinguishing features of vegetating pemphigus. Bromoderma (bromoderma tuberosum) and iododerma (jododerma tuberosum) are easily distinguished from broad condylomas by their nodular-tumor-like character, soft consistency, papillary proliferations, rapid onset with proliferation along the periphery and a tendency to merge with neighboring formations, as well as diverse localization. Papillary carcinoma (carcinoma papillare) is easily distinguished from broad condylomas by its slow course, solitary lesion, massiveness, and appearance in elderly individuals. In the differential diagnosis of papules of the mucous membranes, it is necessary to take into account their clinical features. Erosions of herpes labialis, due to arising from a group of closely spaced blisters, usually have scalloped outlines, they are painful, and remnants of blister roofs are present at the periphery. Erosions after other vesicular lesions (erythema exudativum multiforme, pemphigus) are diagnosed by the remnants of blister roofs and vesicular elements on other parts of the mucous membranes or skin. Aphthae and aphthous stomatitis (aphthae, stomatitis aphthosa) differ from syphilitic papules by their morphological features (aphthae have the appearance of superficial ulcers with sharply outlined margins, a yellow floor, and a bright inflammatory halo around, and are painful). Accidental erosions and ulcers (burns, trauma) have irregular outlines, are painful, and have a causative factor noted with them (carious tooth, whooping cough—in the case of ulcers of the frenulum of the tongue in children, etc.). Lichen ruber planus, usually located on the buccal mucosa, the dorsum of the tongue, etc., differs from syphilitic papules by its shagreen-like surface, annular or figured outlines, and whitish, shiny color. Leukoplakia (leucoplakia) differs by its localization (on the buccal mucosa along the line of tooth occlusion, on the lateral surfaces of the tongue in the anterior two-thirds, its dorsum, on the lip mucosa, absence on the soft palate, faucial arches, and uvula), diverse shape with distinct tortuous borders, milky-white color, slow development, and chronic course. Geographic tongue (lingua geographica) is easily diagnosed thanks to annular or figured outlines with constant variability of configuration and a chronic course. Other diseases of the mucous membranes differ from syphilitic papules by clinical phenomena, course, and in difficult cases by bacteriological examination of the discharge or histological examination of biopsied pieces of tissue. Pustular syphilis (syphilis cutanea pustulosa) is usually an expression of a more severely proceeding syphilis. It usually arises through pustulization, as a result of suppuration in the initially appearing papular eruption. Depending on the size of the pustular elements, small- and large-pustular syphilis are distinguished. Small-pustular, or acneiform syphilis (syphilis cutanea acneiformis, s. acne syphilitica) is characterized by the appearance of small, pinhead-sized pustules on a dense infiltrated base, having as its starting point the area of the skin follicle. Initially, a nodule (papule) arises here, passing within 2–3 days in its upper part into a pustule, which rather quickly dries into a crust. Sometimes the phenomena develop acutely with an elevated temperature, giving an abundant widespread eruption (acne syphilitica conferta), located preferentially in those places that are favorite sites for vulgar acne eruption (face, chest, scapular region), but frequently capturing other places as well as the extremities. Large-pustular syphilis (syphilis cutanea pustulosa varioliformis, s. variola syphilitica) is characterized by the appearance of large pustules resembling smallpox pustules, sitting on an infiltrated base. Sometimes an abundant eruption appears with an elevated temperature (up to 40°). Subsequently, more and more new pustular elements appear, while the old ones dry into crusts and then heal, leaving a pigment spot in their place. Impetiginous syphilis (impetigo syphilitica), like pustular syphilis, generally has as its starting point a papule that breaks down with the formation of a pustule drying into a crust [see separate table (p. 551–552), Fig. 5].
It is not infrequently encountered in fresh secondary syphilis on the scalp (impetigo capitis specifica). Ecthymatous syphilid (ecthyma syphiliticum) is essentially a pustular element of larger dimensions than the pustular, dried-into-a-crust elements. Beneath the crust, an ulcerated surface is exposed, healing with scar formation. Syphilitic rupia (rupia syphilitica) also represents a pustular syphilid, gradually expanding peripherally and in depth, with the resulting crust also gradually increasing in size, assuming a lamellar character and resembling a stack of coins gradually increasing in size downwards (rupia-moneta). Beneath the crust is a rather deep ulcer, leaving a scar upon healing. The diagnosis of pustular syphilid is based on the morphological features of the elements and the accompanying signs of syphilis. The differential diagnosis between small-pustular syphilid and vulgar acneiform eruption is easy. Vulgar acne has as its starting point a comedo, upon the suppuration of which a rather significant inflammatory redness appears; they appear in certain areas, usually at a young age, and have a chronic course. Medicinal acne (from iodine or bromine preparations) and occupational acne (from lubricating oils, etc.) also have the sebaceous plug as their starting point. The anamnesis and the absence of indications of syphilis provide the basis for diagnosing non-syphilitic acne. The differential diagnosis between large-pustular syphilid and smallpox is carried out on the basis of the characteristic features of both diseases. In addition, in syphilis there is false polymorphism, whereas in smallpox all elements are at the same stage of development. The localization of the eruption elements generally also has great diagnostic significance (in smallpox, pustules prefer the extensor surfaces of the limbs, including the back of the hands and feet, as well as the face, which is not characteristic of pustular syphilid). Chickenpox is easily distinguished from syphilid by its clinical signs and course. Vulgar pustular eruption (pyodermia) is also easily distinguished from pustular syphilid by acute inflammatory phenomena, the variety of sizes of individual elements and their course, as well as disorderly or focal localization. The differential diagnosis of impetiginous syphilid from vulgar impetiginous eruption (impetigo vulgaris) is carried out on the basis of the absence of acute inflammatory phenomena (characteristic of the latter), the uniform size of individual elements, and the presence of a dense brown infiltrate characteristic of syphilitic elements. Contagious pustular eruption (impetigo contagiosa) begins with the formation of a vesicle that rapidly dries into a crust, has a tendency to peripheral growth and the disorderly appearance of new elements, often fusing with each other, which distinguishes it from impetiginous syphilid. Impetiginous eczema (eczema impetiginosum) is easily distinguished from impetiginous syphilid by its diffuse inflammatory process with sharp reactive phenomena. The differential diagnosis of syphilitic ecthyma and vulgar ecthyma (ecthyma vulgare) is carried out on the basis of the inflammatory phenomena characteristic of the latter and the absence of a brown base infiltrate. The differential diagnosis of syphilitic rupia and the atypical form of psoriasis (psoriasis rupioides) is easy, because in the latter there is not a true crust, but the so-called crusta lamellosa. Beneath the crust, not an ulcerated surface is exposed, but the surface characteristic of psoriasis. Late secondary syphilis, i.e., its late recurrent manifestations, is characterized by a tendency to the group arrangement of eruption elements in the form of rings and arcs, and such groups are often arranged asymmetrically and not in the typical places for fresh syphilis. Late roseola often has an annular shape [see separate table (p. 551-552), Fig. 7], the papular eruption sometimes bears the character of an abortive, weakly expressed eruption, and sometimes the papules have a character resembling the tubercular syphilid of the tertiary period of syphilis (so-called tertiary papules - papulae tertiariae). Late pustular eruption is rarer and presents no special features. The tertiary period of syphilis is characterized by the appearance of nodular lesions of the skin and deeper tissues and organs (subcutaneous tissue, periosteum, bones, internal organs, and the central nervous system). Regarding the skin, two main forms are distinguished: 1) superficial cutaneous gummas or the so-called tubercular syphilid (syphilis cutanea tuberculosa, s. tuberosa) and 2) deep gummas (gumma syphiliticum) arising in the subcutaneous tissue or in deeper lying tissues. Tubercular syphilid represents dense, sharply demarcated infiltrates ranging in size from a hemp seed to a lentil, located in the thickness of the skin. The color of the nodes is red-brown. These nodes are located singly or in groups. In their course, they often disintegrate in the central parts and then resolve, leaving in their place a certain depression of the skin (subcutaneous scarring) and brown pigmentation, or the disintegrated node opens outward, forming ulcers (syphilis cutanea tubero-ulcerosa). Usually, tubercular elements are arranged in groups, and the previously appeared tubercles may undergo regression, while at their periphery new tubercular elements arise and the process assumes a serpiginous character (syphilis cutanea tubero-serpiginosa). Sometimes such a serpiginous spread is also noted in nodes disintegrating with the formation of ulcers (syphilis cutanea tubero-ulcerosa serpiginosa), and sometimes disintegrated nodes produce an ulcer that heals partially and at the same time grows in the opposite direction, producing a kidney-shaped form of ulcer, which can also assume a serpiginous character (syphilis cutanea ulcero-serpiginosa). In some cases, tubercular elements produce vegetations on their surface (syphilis cutanea tuberculosa vegetans). Sometimes the tubercles have insignificant dimensions (dwarf) with sufficient density, and sometimes they are soft, resembling true lupus tubercles (syphilis cutanea tuberculosa lupoides). On mucous membranes, tubercular syphilid generally can produce pictures of the same character as on the skin. The diagnosis of tubercular and tubercular-ulcerative syphilid in typical forms is easy (presence of characteristic elements arranged in groups with scalloped borders or serpiginous growth, brownish pigmentation, dense infiltrate, etc.) [see separate table (p. 551-552), Fig. 3]. Differential diagnosis with lupus vulgaris (especially the lupoid form of tubercular syphilid) is based on the features of clinical signs, a more chronic course, and the tendency of lupus vulgaris to appear in childhood. The character of lupus scars (delicate scars permeated with telangiectasias and often the presence of new lupus nodules on them) also differs sharply from the scars of tubercular-ulcerative syphilid [see separate table (p. 527-528), Fig. 5]. Localization is also of essential importance (e.g., in the area of the nose, lupus begins from the integuments, whereas tubercular syphilid more often from the mucous membrane side). Nodular leprosy (lepra tuberosa) is easily distinguished from tubercular syphilid by the presence of soft tubercles of normal skin color or yellowish tint, developing extremely slowly without a tendency to ulcerative disintegration and with a characteristic localization. Cancroid (ulcus rodens) differs from ulcer-serpiginous syphilid by the singularity of the lesion, an easily bleeding base, a peripheral ridge of the neoplasm, a slow course, and a tendency to appear in certain places in elderly persons. Papulonecrotic tuberculid (folliclis, acnitis) is easily distinguished from tubercular syphilid by the absence of group arrangement and serpiginous spread, the presence of necrosis on the surface, and characteristic scars. Gummatous syphilid and gummatous ulcer. Syphilitic gumma of the skin appears as a deep node, somewhat flattened spherical in shape, ranging in size from a pea to a walnut, with a tendency to disintegration in the central part and then of the entire node, opening outward with a single perforation hole that gradually increases in size and turns into a crateriform ulcer leading into the cavity of the disintegrated node [see separate table (p. 551-552), Fig. 1]. The ulcer subsequently increases in size, sometimes far beyond the boundaries of the original node, sometimes healing with a scar in one place while serpiginously spreading in the opposite direction. Gummatous nodes are usually single, and the starting point for them is the subcutaneous tissue, periosteum, lymph glands, etc. Disintegration of the node may entail destruction of the periosteum with the formation of a sequestrum of the underlying bone. Not infrequently, gummatous lesions are located in the region of the nose (see), soft palate (see Pharynx).
Diagnosis of gummatous syphilid and other nodular skin lesions is carried out on the basis of clinical data of these diseases.--Differential diagnosis of gummatous and scrofulous nodes and ulcers (scrofuloderma) fundamentally boils down to the fact that a scrofulous node disintegrates in various places and opens outward through multiple perforation openings; the softened node lacks a dense infiltrate around its circumference; the scars of healed scrofulous ulcers include remnants of undamaged skin in the form of papillae, bridges, or bars, which is the result of multiple perforation openings that did not completely destroy the skin in the area of the softened node. A slow course and young age of the patients are also distinguishing features of a scrofulous lesion. Varicose ulcers of the lower leg (ulcus cruris chronicum), cancerous ulcers (carcinoma cutis), ulcers of blastomycosis (blastomycosis), sporotrichosis (sporotrichosis), actinomycosis (actinomycosis), leishmaniasis (leishmaniasis), Bazin's erythema (erythema induratum Bazin), etc., differ from gummatous ulcers in clinical signs and course; in difficult cases, diagnosis is resolved by bacteriological, serological, and histological studies of biopsy tissue. It is also necessary to carry out diagnostics with respect to gummatous nodes and inflammatory processes of the skin (e.g., rhinoscleroma) and neoplasms (lipomas, atheromas, fibromas, sarcomas, etc.). Syphilitic nail lesions are observed as lesions in the area of the nail folds (see Onychia).--For syphilitic hair lesions see Alopecia.--Changes in skin pigmentation in syphilis are observed either in the form of hyperpigmentation at the sites of former syphilitic manifestations, or around the circumference of scars after syphilitic ulcers, or in the form of so-called syphilitic leukoderma (see).--For syphilis of individual organs see the corresponding organs.
M. Demyanovich. Laboratory diagnostics of syphilis - see Wassermann reaction, Precipitation, and Luetin reaction. VIII. Visceral syphilis. Visceral syphilis unites lesions of internal organs caused by the syphilitic infection, in contrast to lesions of the skin and mucous membranes, on the one hand, and of the nervous system (neurolues), on the other. Such a division of the single process of the organism's syphilitic infection into three parts does not correspond, of course, to modern concepts of infection as a disease of the entire organism and entirely reflects both the historical stages of the development of the doctrine of syphilis and the localistic thinking of Morgagni and Virchow (Morgagni, Virchow), which excluded diseases common to the entire organism. 1. History and evolution of the doctrine of visceral syphilis. In the 15th and 16th centuries, when syphilis raged epidemically in Europe, it was described only as a disease of the skin and bones, and Paracelsus in 1536 was perhaps the first to mention syphilitic liver disease and syphilitic jaundice. Lieutaud (1770), studying pathological-anatomical material, was the first to substantiate morphological lesions of internal organs in syphilis, which is why in the 17th and 18th centuries physicians admitted the possibility of visceral syphilitic diseases. Subsequently, these views were undermined for a long time by the doctrine of Hunter, who taught that syphilis affects only the skin, mucous membranes, and bones and does not touch internal organs. Hunter's authority was so great that it took almost a whole century until Ricord, and then Fournier, having accumulated a large series of pathological-anatomical and clinical facts, showed the artificiality of Hunter's doctrine and refuted it. However, even after this, starting from the end of the 19th century, the doctrine of syphilitic lesions of the nervous system was created first T the doctrine of visceral syphilis was limited only to the accumulation of morphological and clinical observations and received its full substantiation only since the discovery of the pale spirochete by Schaudinn made it possible to experimentally study the evolution of syphilitic infection in the animal organism and to prove the specificity of the process in individual organs in humans. And yet, a coherent doctrine of visceral syphilis and its evolution, starting from the moment of infection in the way this has been done for the skin and mucous membranes, on the one hand, and for the nervous system, on the other, has not yet been created. This explains first of all why, when speaking of visceral syphilis, people still have in mind only gross morphological changes in the internal organs of the late, tertiary period, where sometimes decades separate the disease of a particular organ from the moment of general infection. These late syphilitic lesions of internal organs - gummatous and sclerogummatous - and often already sclerotic consequences as a result of the reverse development of the process that destroyed part of the organ, are most often the subject of study by pathologists and clinicians. We still know relatively little about the early and reversible processes of syphilitic infection, and functional disorders of organs in the early stages of syphilis have been studied very little. Therefore, we know significantly more about the statics of visceral syphilis, 588 syphilis than about its evolution and dynamics from the standpoint of the modern doctrine of functional pathology, which establishes the clinic of diseases of internal organs and systems in their closest connection with the endocrine, autonomic, and central nervous systems. 2. Pathology of visceral syphilis. The clinic and pathological anatomy of syphilitic lesions of individual organs are set forth in the relevant articles, and we shall dwell here only on the pathological and clinical data concerning visceral syphilis as a part of the general infection of the organism. From the portal of entry, the causative agent penetrates very early via lymphatic pathways into the general bloodstream; spirochetemia leads immediately to the generalization of syphilis, with the possible appearance of "minimal early diseases" (Golay). Already in this stage, the syphilitic virus can become fixed in one or another organ and cause corresponding reactive phenomena in it. As is known, in congenital syphilis in the fetus, the skin and mucous membranes, on the one hand, and the internal organs, on the other, are affected equally, with certain internal organs, such as the liver, being affected predominantly. When contracting syphilis in postnatal life, although the organism as a whole is subjected to the action of the infection, visible clinical lesions are localized mainly on the skin and mucous membranes. This, of course, does not mean that the internal organs remain spared by the infection. We have a number of pathological-anatomical, experimental, and clinical data indicating that already from the very beginning the syphilitic infection affects all systems and organs and localizes in them. Not to mention the fact that in the earliest stages of syphilis such general reactions of the organism as febrile temperature rises, changes in the blood picture, the chemistry of gastric secretion, etc., have been noted, there are quite definite observations of early eruptions on the mucous membranes, in the liver, of early albuminurias as an expression of nephropathies, etc. However, these early forms of infection are not typical for visceral syphilis. The clinical concept of visceral syphilis mainly includes pathological processes developing as a result of the late reproduction of the spirochete in one or another internal organ when the early localizations of the infection in the skin and mucous membranes have long since disappeared or even been forgotten. Visceral syphilis is still considered to be diseases of the tertiary period or metasyphilitic processes. By this name must be understood the sum of reactive processes on the part of the mesenchyme leading to sclerotic phenomena with the destruction of the specific parenchyma of the affected organ. Thus, syphilis of the internal organs manifests itself: 1) in early specific diseases of the primary and secondary stages of infection, 2) in late specific gummatous, sclerogummatous lesions, and 3) in non-specific connective tissue lesions of the organ cirrhosis type. It is not without interest that the state of the internal organs may in turn have a certain influence on the manifestation and course of the syphilitic infection; thus, in thyroidectomized animals, Pearce and Allen saw a significantly more severe course of experimental syphilis than in control animals; similar observations have been made regarding the extirpation of the thymus gland. It is very likely that the different results of the treatment of syphilis in humans are related to this influence of the endocrine apparatus on the course of the infection. It is also not without interest that other diseases of the internal organs exert an influence on the course of the syphilitic infection. Thus, tuberculosis worsens the course of syphilis and significantly complicates its treatment; on the other hand, acute infectious diseases, such as influenza and scarlet fever, favorably influence the course of the syphilitic infection, with eruptions disappearing and the Wassermann reaction temporarily becoming negative. Clinical observations on the treatment of certain forms of syphilitic infection with malaria and relapsing fever speak of a certain antagonism between syphilis and acute infections. Regarding the localization of the process in visceral syphilis, we have data only concerning the late, tertiary forms of syphilitic infection. Regarding the early stages of visceral syphilis, there are only fragmentary clinical observations, while pathological-anatomical pictures have been described only singly and as a great rarity. In examining 414 cases of visceral syphilis, Schrumpf found lesions of the cardiovascular system and especially of the aorta in 56.76%, lesions of the nervous system in 23.43%, the liver in 8.45%, the lungs in 3.14%, arthritis in 0.72%, the kidneys in 0.48% (without definite localization - 2.9%). Out of 280 patients with visceral syphilis, Luria saw diseases of the circulatory organs in 38.3%, the nervous system in 19.7%, the liver in 18.9%, without definite clinical localization in 11.1%, arthritis in 2.6%, kidney diseases in 3.1%, and the gastrointestinal tract in 2.6%. Relative as these data may be, all authors unanimously note that most frequently visceral syphilis is localized in late stages in the cardiovascular system, predominantly in the aorta and in the liver; gummatous lesions are also encountered in all other organs, but significantly less frequently. Of some interest is the comparison of the frequency of internal organ lesions in syphilis with the results of experiment. The influence of syphilitic infection on internal organs is not exhausted, as we have seen, by specific lesions thereof; it is also necessary to keep in mind the non-specific influence of the virus and its toxins on the tissues, i.e., not purely syphilitic, but syphilogenic processes of chronic infection of internal organs with various morphological changes thereof. The significance of syphilis in the etiology of internal organ diseases, according to Wittgenstein and Brodnitz, is exceptionally great; thus, among 90,553 patients of the Charité polyclinic in Berlin, they found syphilitic infection as the cause of internal diseases in 7.54%.
Leredde, studying the mortality causes of the population of Paris, found that out of 45,814 deaths, in 3,414 cases, i.e., in 7%, syphilis was the cause of death due to visceral lesions, with angina pectoris noted in 3/4 of the cases, vascular diseases in half of the cases, organic heart diseases in 1/3 of the cases, and death resulting from chronic nephritis and liver cirrhosis in 1/6 of the cases. Bayet gives 11% for the mortality of the population from visceral syphilis in Brussels. According to data from the Gotha Life Insurance Society based on 44 years of material, mortality among syphilitics was 68% higher than among non-syphilitics; according to American insurance companies, mortality among insured syphilis patients is at least 50% higher than among uninfected individuals. These facts are quite sufficient to illustrate the huge role of visceral syphilis as a social disease. 3. The clinical picture of visceral syphilis is extremely motley and diverse as a result of a whole series of very different pathological processes caused by the pale spirochete in various stages of the disease. The specific manifestations of syphilis alone—beginning with the allergic processes of the early stages of the disease to syphilides and gummatic infiltration in later ones, mesenchymal reactions—all these closely intertwined pathological processes cannot produce a uniform clinical picture. To this must be added the pluriviscerality typical of syphilis, i.e., the multiplicity of localization simultaneously in a number of organs and systems, including the endocrine glands, the autonomic and central nervous system. All this taken together creates the conditions for the most diverse and sometimes very bizarre combinations of organic and functional disorders, which in turn are inextricably linked and very closely intertwined. This imprints a stamp of peculiarity on the clinic of visceral syphilis and makes it impossible to draw a clinical picture common to all these diseases. Descriptions of individual organ diseases as a result of syphilitic infection are available in the relevant chapters; they are elaborated mainly in relation to late, tertiary, or metasyphilitic forms; the clinical picture of early visceral lesions disappears from the field of vision of the therapist already because observations are conducted by a venereologist specialist, occupied mainly with the cutaneous localization of the infection. These early forms of syphilitic infection of internal organs are especially difficult to recognize, since it is almost exclusively a matter of functional disorders, of changes in the behavior of the organ. Thus, on the part of the cardiovascular system, there are sensations of pressure in the heart region, palpitations, precordial anxiety, and objectively—tachycardia or, conversely, bradycardia and heart rhythm disturbances. Some tend to view these phenomena not so much as the result of anatomical changes, but as functional ones resulting from toxemia (Citron); it is hardly possible, however, in the secondary period to completely deny the possibility of the appearance of organic heart lesions—myocarditis, or more correctly pancarditis (Pletnev). Regarding blood vessels, if one takes into account the vasotropism of the syphilitic virus, endarteritis and especially endophlebitis can sometimes be observed in the first stages of infection, with syphilitic phlebitis occurring more often in women than in men. It is precisely these early lesions of the vascular system that explain the early appearance in syphilitics of profound circulatory disturbances in the heart—angina pectoris, myomalacia of the heart—or in the central nervous system—thrombi and hemorrhages in the brain. On the part of the respiratory apparatus, apart from early rashes in the larynx, specific bronchitis and pleurisy appear with a positive Wassermann reaction in the punctate; lung tissue lesions in the form of small consolidation foci have been established radiologically already in the secondary period (Groedel). Regarding the digestive tract, there is data on gastric processes in the early stages of infection, expressed, besides dyspeptic phenomena, in the reduction of the secretory activity of the stomach up to achylia inclusive. It is very interesting that these inflammatory and functional lesions of the stomach in early stages are reversible under the influence of specific therapy (Hausmann, Luria). Will found roseolas and papules in the intestines during the secondary period, and Hayem and Tissier found ulcerative processes; hence it is not surprising that even in these early stages of infection one can expect the appearance of diarrhea of both functional (allergic) and organic origin (enterocolitis). Of particular interest are syphilis lesions of the liver in the early periods of infection and above all early syphilitic jaundice (icterus syphiliticus praecox). This form of jaundice can appear already during the primary affect; however, it is more often encountered during the first rashes. Of great interest are early syphilitic kidney diseases (see Kidneys, syphilis of the kidneys). With such a disease totius substantiae as syphilis, diseases of the endocrine apparatus are of exceptional interest, yet data on their behavior in the early stages of infection are still very insufficient. That these glands, possessing an especially abundant network of vessels, must be affected during spirochetemia can hardly be doubted; thus, there are indications of early strumitis, as well as phenomena of irritation and swelling of the thyroid gland in the initial stages. Data on early syphilis lesions of other glands are still very scant. From this brief enumeration of internal organ lesions in the early stages of syphilitic infection, it is completely obvious how incorrect it is to consider visceral syphilis as a disease only of the late, tertiary stage of syphilis, and the therapist's task is precisely in the first weeks and months of the infection to seek those often subtle functional disorders of the organism which are the result of superficial, and therefore reversible, syphilitic and syphilogenic lesions of internal organs. Organizationally, this requires the closest coordination of the work of the venereologist and the therapist, starting from the moment of infection of the syphilis patient. In view of the fact that lesions of the internal organs of the tertiary period of syphilis and their metasyphilitic diseases are detailed in the corresponding chapters, we shall dwell here only on two syndromes of visceral syphilis representing its reflection as malum totius substantiae—on blood changes and on syphilitic fever. Blood changes in syphilis have been known for a long time, and in the early stages of infection, old physicians described specific anemia under the name of "syphilitic chlorosis." In the primary stage, a decrease in hemoglobin without oligocythemia is described; in the secondary stage, phenomena of typical secondary anemia with oligochromemia and oligocythemia, disappearing upon the transition of syphilis into a latent form. Specific, especially mercurial treatment improves the blood picture. On the part of white blood, a slight leukocytosis is noted, with the number of neutrophils decreased and mononuclear cells increased; in late stages of syphilis, as well as in other chronic infections, relative mononucleosis is observed. Great disputes are aroused by the question of the relationship between syphilis and hyperchromic anemias of the anaemia perniciosa type, and the opinions of authors on the role of syphilis in the etiopathogenesis of malignant anemia diverge greatly. While some authors (Fr. Müller, Grawitz, Schlesinger, and others) believe that the toxic effect of the syphilitic virus on the bone marrow causes the picture of progressive pernicious anemia, others (Ehrlich, Lazarus, Pappenheim) deny the genetic link between malignant anemia and syphilis. Although individual observations speak in favor of the fact that blood transfusion followed by antisyphilitic treatment yields exceptionally brilliant results in almost hopeless cases of anaemia perniciosa (Schlesinger), the question nevertheless remains open, and all authors unanimously speak out against vigorous specific treatment in anaemia perniciosa and demand great caution in dosage, especially of salvarsan. Of the general phenomena caused by syphilitic infection, fever deserves attention; according to clinical manifestations, the following forms are distinguished: 1) Fever accompanying syphilitic rashes in the secondary and tertiary periods of infection; it is especially pronounced in severe cases of syphilis and is more common with pustular skin efflorescences. 2) Fever appearing with gummatic lesions of individual organs. This includes first of all syphilis of the liver, very often accompanied by very stubborn temperature fever movements (according to Talke-qvist in 50% of all cases); the fever here proceeds periodically, sometimes of an intermittent type, giving grounds to speak of malaria, typhoid, and septic processes, less often it has a remittent character. Syphilis of the spleen, accompanied by fever, has more than once been confused with malaria, Maltese fever, and kala-azar; syphilis of the lungs very often runs febrile and has therefore long been considered tuberculosis; syphilitic lesions of the peritoneum with fever have been described, also mistaken for peritoneal tuberculosis.
Finally, late syphilitic joint lesions (arthrolues tardiva) often proceed with a persistent, remittitent, and even hectic fever lasting for weeks and months, providing grounds to erroneously suspect true rheumatism or sepsis. 3) Fever resulting from therapeutic intervention provoking the Jarisch-Herxheimer reaction; it occurs sometimes after the first injections of mercury, salvarsan, or bismuth in 3 to 10 hours and lasts for 2, 3, and even 4 days, reaching 39-40°. 4) Finally, the last and most interesting form is essential syphilitic fever; not a few cases of a prolonged, lasting for months, febrile course of the disease have been described, which gave grounds to make all sorts of diagnoses and was cured by specific therapy. These cases are of great theoretical interest and are explained by pathological processes in the nervous and endocrine systems that do not lend themselves to localization. At the same time, they always present very great diagnostic difficulties. 4. The recognition of visceral syphilis in the early stages of infection presents great difficulties, since functional disorders of organs in the majority of cases do not differ in any way from pathological states of another etiology, and only in individual cases during endoscopy (bronchi, rectum, and sigmoid colon) is it possible to see typical syphilitic eruptions. Recognition of late forms of visceral syphilis presents considerably fewer difficulties, especially when it is localized in organs most frequently affected by the sclerogummatous process, such as the cardiovascular system or the liver. However, even in these cases, the differential diagnosis with malignant neoplasms is not always successful even at laparotomy, when the surgeon can both see and palpate the pathological process, or in the lungs, when it is easy to fix on a radiogram. Besides local symptoms providing supporting points for differential diagnosis (see Stomach, Lungs, Liver, and other organs), the clinical picture of visceral syphilis nevertheless presents a number of features, the knowledge of which significantly facilitates the recognition of syphilitic lesions of internal organs. Visceral syphilis runs an atypical course, often not fitting into the forms of internal organ diseases usual for the physician. This gave grounds for numerous and very apt clinical aphorisms, both old: «in dubio suspice luem» (in doubtful cases suspect syphilis), and later ones: «la vérole vieille a la mine honnête» (Ricord) (syphilis, as it ages, assumes a respectable appearance), or, as Sigmund said, «die Syphilis ist die Affe unter den Krankheiten» (syphilis is the ape among diseases). All these empirically developed clinical rules fully correspond to the clinical picture and course of visceral syphilis and find their explanation in the combination of very different pathohistological processes in the organs: gummatous lesions in various stages—formation, softening, scarring of the gumma,—destruction of the parenchymal tissue of the organ and sclerotic processes of the mesenchyme, damage to the vascular system of the organ—endarteritis, endophlebitis, specific and non-specific changes in nervous tissue, and so on and so forth. On the other hand, this atypicality of the clinical picture of visceral syphilis is explained by the pluriviscerality of the disease typical of it, when a number of organs and systems are affected simultaneously precisely because syphilis is a disease not of a single organ, but malum totius substantiae. Thus, syphilitic diseases of the aorta in no less than 1/3 of cases are combined with neurosyphilis and in 1/2 of cases with tabes; according to Pletnev, 40% of cardiovascular syphilis is combined with syphilitic lesions of other organs; Luria in 48 cases of heart and vascular syphilis saw 26 lesions of the nervous system, 21 lesions of the liver, 3 lesions of the endocrine glands; in a number of stomach diseases of syphilitic origin, diseases of the heart, liver, and central nervous system were noted simultaneously. Of course, besides multiple lesions of internal organs, it may also be a question of traces of tertiary skin and bone lesions—periostitis, scars, etc. But, as is known, over the past decades syphilis, especially in cities, has lost its dermotropic character and therefore combinations of visceral and cutaneous-osseous syphilis are encountered less and less frequently, which may be related to the immunobiological properties of the skin in the sense of esophylaxis (Hoffmann). All the more important is the study of small but essential symptoms resulting from previous lesions of other systems. This mainly includes isolated symptoms on the part of the eyes—anisocoria, anomalies of the light reflex of the pupils with preservation of their reaction during convergence (Argyll Robertson sign) and fading of the irises of the eyes (Darkshevich). In a number of diseases of internal organs, these isolated symptoms on the part of the eyes without other visible lesions of the central nervous system were observed in various forms of visceral syphilis and were a symptom that led to the correct recognition of the nature of the disease (Luria); this symptom is stable, does not disappear after specific treatment, and is the result either of a latently proceeding basal meningitis in the secondary stage of infection (Forster) or of a specific lesion of the vegetative system (Laignel-Lavastine). These pupillary symptoms, on the other hand, are a valuable confirmation for the diagnosis of visceral syphilis. The presence of a positive Wassermann reaction speaks, of course, of syphilitic infection, but does not yet decide the syphilitic nature of the given visceral disease, especially since so-called hybrid forms are not infrequently encountered, i.e., banal diseases in syphilitics—cancer, stomach ulcer, nephropathy, pulmonary tuberculosis, etc. On the other hand, a negative Wassermann reaction does not yet provide grounds to exclude visceral syphilis, especially if it is a matter of a reaction only in the blood and not in the cerebrospinal fluid; thus, Stokes-Brown found a positive Wassermann reaction in the liquor in 59% of visceral syphilis, whereas in the blood it was obtained in only 44% of all cases; on the other hand, cases of a negative Wassermann reaction with the presence of Spirochaeta pallida in the tissues have been described. Also of great importance for diagnosis is the unfortunately rarely practiced Wassermann examination of pleural and ascitic fluid and joint effusions. Thus, the Wassermann reaction for the diagnosis of visceral syphilis has only relative significance, especially since in a number of cases it appears only during or even after specific treatment. Anamnesis has an even more conditional significance for the diagnosis of visceral syphilitic diseases. If the patient had syphilis, this only makes the physician think of the possibility of visceral syphilitic processes; if there is no syphilis in the anamnesis, then in 57.4% of women it can be a matter of syphilis ignorée (Marschalko, Fournier). The doctrine of "silent" infection and multiplying observations of cases of undoubted syphilis without a definite localization of the primary infect give sufficient theoretical justification for this fact. The old method of recognizing visceral syphilis by the results of trial specific treatment is permissible, but with essential reservations of careful study of the patient during treatment; not infrequently, brilliant results of treatment reinforce the recognition of visceral syphilis, and the appearance at the same time of a previously absent positive Wassermann reaction makes the assumption an undoubted clinical fact. Thus, the atypicality of the clinical picture, the pluriviscerality of diseases, the presence of isolated symptoms on the part of the eyes, the Wassermann reaction in the blood, cerebrospinal fluid, and effusions, the study of anamnesis, and sometimes the results of specific treatment—these are the supporting points for the diagnosis of visceral syphilis. The prognosis in visceral syphilis depends, of course, first of all on the early recognition of the true essence of the disease, its syphilitic origin; in late stages of syphilitic infection, it is especially essential to apply treatment before the fibroplastic irreversible process ends. Syphilis of the heart and large vessels gives an especially unfavorable prognosis and not infrequently an unexpected fatal outcome. 5. The treatment of visceral syphilis is for the most part a rewarding task and is facilitated by the fact that the localization of the syphilitic process plays a subordinate role here, because antisyphilitic agents act not directly on the local process, but by way of mobilizing the immunobiological adaptive mechanisms of the organism. However, in the treatment of visceral syphilis even less than in the treatment of its skin manifestations is a standard system of treatment, identical for all cases, permissible. Thus, for example, in syphilitic kidney diseases, caution is required in the administration of mercury—regardless of whether in the form of injections, inunctions, or internal intake of mercurial preparations; the same applies to bismuth preparations and salvarsan, and therefore treatment must be begun with the administration of iodine preparations internally or in the form of injections in relatively small doses, and only after the disappearance of edema should one cautiously transition to treatment with neosalvarsan.
In syphilis of the liver, iodine preparations in large doses are tolerated excellently; mercury in small and medium doses also yields good results, as do bismuth preparations (bijochinol); however, it is better to refrain from salvarsan preparations, since they frequently produce a violent Jarisch-Herxheimer reaction here. Syphilis of the stomach and intestines responds well to any antisyphilitic treatment. Incidentally, iodine preparations, which are poorly tolerated by patients with common diseases of the stomach, are tolerated excellently by them in diseases of the stomach of syphilitic origin, which can sometimes be used for diagnostic purposes as well. In treatment with salvarsan, great caution is required in view of the possibility of profuse gastric hemorrhages. Therapy for cardiovascular syphilitic diseases requires special caution; quite a few cases of severe complications and even sudden death are known when large doses of salvarsan are prescribed all at once. This caution in the treatment of visceral syphilis with specific agents is dictated by the fact that the physician cannot in each individual case account for the magnitude of the Herxheimer reaction and, consequently, the scope and results of the loss of function of the diseased organ. In addition to modern methods of therapy for syphilis, as experience teaches, visceral diseases often respond well to old methods of therapy, especially mercurial ointment rubs in combination with large doses of iodine internally. Very good results have also been described with the prescription of the old Zittmann decoction and sarsaparilla decoction. There are indications of a favorable effect on the course of visceral syphilis from malaria inoculation; however, anginose phenomena with fatal outcomes have already been noted, for example, in the treatment of syphilitic mesaortitis with these inoculations (Jagic, Spengler). In addition to specific therapy for visceral syphilis, balneological treatment is also indicated, mainly resorts with sulfur springs (Pyatigorsk, Sergievsk mineral waters, Matsesta, Sernovodsk), though taking into account all anatomical and functional disorders and with strict individualization of each individual case. Specific and spa treatment in visceral syphilis must, of course, be combined with dietary, physiotherapeutic, and medicinal therapy according to the indications in each individual case.
S. M. Luria. IX. Treatment of acquired syphilis. In the treatment of syphilis, so-called specific agents are used mainly, which include arsenic, mercury, bismuth, and iodine preparations. Experimental data and clinical observations at the present time increasingly reinforce the view that specific agents are not directly spirocheticidal. Acting on the cells and tissues of the body, they produce changes in their biochemical state that stimulate immunobiological reactions to the invading infection. By virtue of this, the state of individual organs and systems in the course and treatment of syphilis is of colossal importance, and in cases of non-specific functional impairment of them, it is necessary to carry out non-specific treatment simultaneously with specific treatment in order to restore the impaired function. Although in everyday practice we see patients in whom, despite inadequate treatment or its complete absence, syphilis manifests itself in no way for decades, nevertheless, the majority of them turn out to be sick either serologically or in terms of the cerebrospinal fluid, women give birth to children sick with syphilis, and predominantly from this contingent of patients are recruited aortics, tabetics, progressive paralytics, and other patients with late manifestations of visceral syphilis and syphilis of the central nervous system. Thus, immunobiological processes alone are insufficient to combat the syphilitic infection, and only intensive and systematic treatment with specific agents can provide a complete cure for syphilis and is the best prophylaxis for visceral and central nervous system syphilis. The discovery of the pale spirochete, the serological reaction of the blood, and salvarsan introduced into the therapy of syphilis, especially in combination with mercury and bismuth, made it possible with early and intensive treatment to abort syphilis, which is why modern therapy for syphilis is based on the principle of the earliest possible, intensive, and systematic treatment carried out without disrupting the general state of the body and the functions of its individual organs. It is superfluous to cite all the existing treatment options for syphilis developed by individual syphilidologists on the basis of personal observations. The difference lies mainly in the use of single and total doses of the applied medicaments in various combinations thereof and various periods between injections and individual courses, and in the total duration of treatment. It is necessary to note only the basic provisions of the methodology of treatment and the use of specific agents in various periods of syphilis. They consist of the following: 1) Specific treatment should be started as early as possible, in the primary seronegative period, immediately after the bacteriological diagnosis is established. The earlier treatment is started, the greater the chances for complete sterilization of the organism. 2) The less time has passed since the moment of infection, the more intensive the treatment should be with respect to the use of single and total doses per course, and the shorter the intervals between courses should be. The greater the duration of the infection, the less intensive the specific treatment should be with respect to an individual course, but on the whole more prolonged. 3) The total doses of specific agents in the first courses of treatment of fresh syphilis should be brought to the limits of the body's endurance, but not to the detriment of its general condition. For an adult, the average therapeutic dose of novarsenol is 0.1 pro die, mercury 0.01 Hg met., bismuth 0.02 Bi met. The course dose of novarsenol is on average 5.0-6.0, mercury 0.3-0.5-1.0 Hg met., bismuth 1.0-1.5 Bi met. In the tertiary period of syphilis, these doses can be reduced. 4) In the primary seronegative period of syphilis, treatment can begin directly with an infusion of novarsenol; in subsequent periods, to avoid sometimes severe phenomena of the Jarisch-Herxheimer reaction, with injections of bismuth or mercury preparations; and in the tertiary period, with the use of iodine preparations either in pure form or together with mercury or bismuth preparations. 5) Since in each of the specific agents individually there may be a latent refractoriness of the syphilitic virus, the strongest treatment is alternating mixed salvarsan-bismuth and salvarsan-mercury courses. Even in those cases where salvarsan proves ineffective, success can be obtained from mercury and bismuth, and in the tertiary period from iodine. For the purpose of a more prolonged therapeutic effect in combined salvarsan-mercury treatment, it is better to use insoluble mercury preparations. With mercury-only treatment of fresh syphilis with contagious manifestations, it is best to start treatment with injections of soluble preparations or even intravenous infusions in view of their faster action with this method of administration. Upon the liquidation of contagious manifestations of syphilis, it is advisable to switch to insoluble preparations, which act longer. Soluble preparations, being more easily tolerated and more evenly and rapidly eliminated than suspensions, are more applicable to weak organisms or when the function of visceral organs is impaired. In view of the therapeutic significance of the local application of specific agents in the secondary period of syphilis, it is advisable to carry out one or two courses of treatment with frictions of mercurial ointments, and in case of specific lesions of the gastrointestinal tract, by the internal administration of mercury preparations. 6) Intervals between courses, if there are no special contraindications to this, should not exceed 4-5 weeks in the treatment of fresh syphilis and 2-3 months in tertiary syphilis. Systematic courses with short breaks best ensure the absence of clinical relapses, persistent negative serological reactions, and normal cerebrospinal fluid. 7) Iodine therapy is usually prescribed from the second year of infection, and at an elderly age at the very beginning of it. In the tertiary period of syphilis, it should be the most intensive and prolonged. Mixed treatment with iodine and salvarsan, bismuth, or mercury has a stronger therapeutic effect than each agent separately, but iodine treatment alone in the tertiary period of syphilis, used after the completion of salvarsan-bismuth-mercury treatment, has great prophylactic significance. 8) Treatment should strive to achieve the persistent disappearance of clinical symptoms, persistent negative serological reactions, and the recovery of the cerebrospinal fluid, which is why it should be carried out under the control of blood serological reactions and cerebrospinal fluid examination. After the disappearance of clinical and serological phenomena of syphilis, treatment should continue in the form of so-called consolidation courses in greater numbers the later it is started. 9) If after systematic intensive treatment in an amount of not less than 5-6 courses the serological reactions remain positive, salvarsan, bismuth, and mercury treatment should be discontinued, leaving only iodine in the amount of 2-3 courses per year. It is highly desirable in such cases to join physiotherapy, balneotherapy, and aerotherapy. 10) With pathological cerebrospinal fluid in cases analogous to the previous one, it is advisable to prescribe 1 or 2 salvarsan-bismuth or mercury courses per year and in the intervals between them iodine treatment. Such cases serve as an indication for the use, where the state of the body permits, of malaria therapy together with salvarsan-bismuth treatment (regarding malaria treatment, see Progressive Paralysis). 11) Upon the appearance of clinical symptoms of syphilis in the cases indicated in paragraphs 9 and 10, systematic mixed treatment is carried out in an amount of not less than three courses, according to paragraphs 5 and 6. 12) The application of the above provisions must be strictly coordinated with the individual endurance of the organism in relation to the applied medicaments and their doses, with contraindications to their prescription, age, general condition, and functional activity of individual organs. Patients should be thoroughly examined before prescribing treatment, and treatment should be individualized in relation to each patient. In all cases of relative contraindication to the use of specific agents, they are prescribed in reduced doses, both single and total, the intervals free from treatment are increased, and non-specific therapy is applied to strengthen the general condition of the body and correct the impaired function of one or another organ. 13) Overwork, prolonged nerve strains, sexual excesses, alcoholic beverages, and drugs react unfavorably on the course of syphilis, lowering the natural immunity of the organism and causing intolerance to specific preparations, especially salvarsan. Moderate physical labor, gymnastics, and light sports as improving metabolism are very desirable. 14) Upon completion of treatment, the patient should be under clinical, serological, and cerebrospinal fluid control, and the longer so, the later the treatment was started. Of the treatment methods for syphilis used at present, the following can be indicated: The use of only one of the specific agents, predominantly salvarsan and its derivatives, mainly in the abortive treatment of syphilis, in the amount of one or several courses. To the detriment of pure salvarsan treatment, one can put, firstly, the rapid elimination of salvarsan from the body and, as a consequence, the short duration of its therapeutic action, and secondly, the possibility of relative, difficult-to-calculate refractoriness of spirochetes to it.
As a result of this, when using salvarsan treatment alone, clinical, serological, and cerebrospinal fluid relapses are observed significantly more often than after mixed treatment. Treatment of fresh syphilis with mercury alone, due to its weak therapeutic effect at present, must be considered insufficient. Only isolated authors consider it possible to use bismuth alone. 2) Combined treatment with salvarsan, bismuth, mercury, and iodine preparations in various combinations depending on the period of syphilis, the general condition of the organism, and its individual organs. From this group, the most widespread is the "chronically intermittent" or "preventive" method of treatment developed by Fournier and Neisser in the middle of the 19th century. This method supplements the inadequate treatment of the once popular "symptomatic method," reinforcing it with repeated courses during the latent state of the disease. At the same time, thanks to the intervals between courses, it does not disturb the general condition of the organism, as was the case with the "continuous" or "tonic" method. The principles of this method are recognized even now by the majority of syphilologists. Some authors carry out mixed courses according to this method, alternating single doses of salvarsan, bismuth, or mercury; others alternate courses, each of which is carried out with one of these preparations. In both cases, intervals in treatment are made between courses to avoid an excessively large load on the organism from the administered preparations and, as a consequence, a decrease in its resistance to the virus. 3) The permanent method of treatment (Almkvist, Mühlpfordt). In this method, salvarsan, bismuth, and mercury are used in the form of separate courses, following one after another without interruption and constituting separate cycles. Such cycles are repeated without interruption, depending on the period of syphilis, for several months (from 31/2 to 14 according to Almkvist). The method of continuous use of specific agents is based on not allowing spirochetes to become activated, which, according to the authors using it, occurs during treatment intervals in the chronically intermittent Fournier-Neisser method. 4) The method of treatment with so-called "blows," consisting of salvarsan and bismuth (Scholtz, Spiethoff) or mercury (Stern, Silberstein, Pollitzer) series. In this method, salvarsan preparations are applied daily for several days in a row in increased doses compared to usual. These series, with various rest intervals, are repeated several times depending on the course of syphilis and its periods. The method is based, according to the authors using it, on the fact that to a stronger blow of specific agents the organism reacts with a stronger reaction, contributing to a quicker and stronger therapeutic effect. In view of the high intensity of this method, it is applicable only to robust, young patients with normal functions of visceral organs and mainly in abortive treatment. 5) The treatment method consisting in the simultaneous combined application of preparations of the neosalvarsan type and soluble mercury preparations in one syringe (Linser's method) is based on the assumption that mercury preparations activate the therapeutic effect of salvarsan. Preventive treatment of syphilis, i.e., the application of treatment in cases where it is assumed that infection has occurred but has not yet manifested itself either clinically or serologically, became possible only thanks to salvarsan. The principle of preventive treatment is the same as in abortive treatment: early therapeutic intervention, which best ensures sterilization of the organism. The main motivation to start treatment even before clinical manifestations of the disease is the significant percentage of failures of abortive treatment, according to some authors reaching 15%, started even in the period of seronegative chancre. Cases of probable infection suitable for preventive treatment must be considered the following: 1) after intercourse with syphilitic individuals with contagious manifestations on the genitals. Only with positive serological reactions without manifestations of syphilis on the skin or mucous membrane in the partner is preventive treatment not indicated. 2) After a healthy woman nurses a child with active manifestations of syphilis on the face or in the oral cavity, or a child suckling a syphilitic woman with contagious manifestations on the mammary glands. 3) For the purposes of public prophylaxis, during close non-venereal contact of persons with contagious manifestations of syphilis when there is reason to assume the possibility of transmission of the infection. Preventive treatment should not be carried out on persons frequently exposed to the possibility of syphilis infection. Clinical experience shows that the earlier preventive treatment is started, the greater the chances of success. Simon considers prophylactic treatment effective if it is started within 3 days after probable infection; Meschersky, up to 6 days; Nikolsky and Kozhevnikov, up to 7 days; Nicolau considers 8–9 days after infection the most favorable period; Brin and Legrain, 8–10 days; Gallais lengthens it to 14 days. Reports of failures of preventive treatment are still rare, but the later it is started and the weaker it is administered, the more frequent the failures. It is more correct to limit the period for cases suitable for preventive treatment to 6–7 days from the supposed infection. After this period, patients should be left without treatment, but under careful clinical and, in view of the possibility of lues ignorata (especially in women), serological observation for 3–4 months. For preventive treatment, the strongest antisyphilitic agents should be used—arsenic preparations in the form mainly of infusions of novarsenol 3.0–6.0 (in greater amounts the more time has passed since the onset of infection). In cases where infusions are impossible, one can use intramuscular or subcutaneous injections of Myosalvarsan or Sulfarsenol, or preparations of the Osarsol type in an amount for a complete course of 30.0–40.0. Most authors limit themselves in preventive treatment to a single salvarsan course. Some advise performing several pure salvarsan courses (G. I. Meschersky) or a combined bismuth-salvarsan course (A. P. Jordan, Gougerot, etc.). Abortive treatment. All attempts to abort syphilis by local measures—excision of the chancre (Tarnovsky, Pospelov, Fournier, etc.) and even regional glands, the use of mercury preparations in the form of injections into the tissue of the chancre or between the chancre and the groin (Hunter) or arsenic ones (Hallopeau)—are based mainly on the erroneous belief that during the primary manifestation the virus remains localized only in it and in the surrounding tissues and in the nearest glands, and they have completely failed or given a very small percentage of successes, which would be safer to attribute to the latent state of the infection. Numerous attempts undertaken even before the advent of salvarsan to abort syphilis with general treatment by mercury, and later also by bismuth, have likewise remained fruitless. With the discovery of salvarsan, a new era in the abortive treatment of syphilis opened up. The hope for abortization was so great that attempts at treatment with this preparation bore the character of therapia magna sterilisans. From the very beginning of the appearance of salvarsan, it was considered possible to abort syphilis not only in the seronegative stage of the primary manifestation, but also in the seropositive stage and in cases of fresh syphilis with secondary phenomena. However, subsequent observations, numbering a large number of relapses in the latter two stages of syphilis, forced a narrowing of the framework of cases suitable for abortive treatment down to the seronegative primary manifestation. According to the material of the international questionnaire of the State Venereological Institute on the abortive treatment of syphilis, processed by V. I. Feldman, the best moment for the application of abortive treatment is considered by the majority of authors to be a primary seronegative chancre with a duration of infection from 4 to 5 weeks and no more than 5–7 days of existence of the chancre, provided that the negative seroreaction persists during the first weeks of treatment, especially after the first salvarsan infusions. Since regional glands are the most refractory to specific agents, it is completely understandable that the condition for abortive treatment—the absence of their enlargement—is of very essential significance. Most of the observed failures of abortive treatment fall on cases with markedly pronounced gland enlargement. The general condition of the organism and its ability to react to the invading infection are also of great importance. The greatest success can be expected at the age of 20–30 years (Jordan). At present, the majority of authors consider it necessary to carry out combined, alternating salvarsan-bismuth or salvarsan-mercury treatment in several (3–4) intensive courses according to the intermittent Fournier-Neisser method. But besides this method, others can also be successfully applied, among which one can point out the permanent method of Almkvist-Scholtz and the method of maximal early treatment of Hoffmann (see below). In view of the fact that even after several courses of combined treatment virulent spirochetes may remain at the site of the primary lesion, it is advisable, where possible according to the topography of the chancre, to excise it or in any case to apply careful local treatment.
Abortive treatment must be accompanied by serological tests before, during, and at the end of it for at least 3 years and, in the event of even a temporary positive seroreaction, must be considered unsuccessful. At the end of the 2nd year of the disease, an examination of the cerebrospinal fluid must be performed. Treatment regimens. Although treatment should be carried out individually for each patient in accordance with their general condition and the state of individual organs, taking into account the environment and living conditions of the patient, in view of great discrepancies in treatment methodology among individual authors, it is practically advisable to follow regimens applicable to the majority of patients whose health status does not deviate from the norm. Brychev adheres to the following treatment setup for syphilis in its various periods, carried out by him at the clinic of the State Venereological Institute: S. I seronegativa. With an infection duration of not more than 4-5 weeks, a chancre of 10 days, and absent or weakly expressed regional glands, abortive treatment is carried out according to the chronically intermittent method in the amount of 3 courses. 1st course: mixed treatment with novarsenol and bismuth. Treatment begins with an initial dose of novarsenol of 0.3; on the 4th day, 0.45; then every sixth day 0.6 up to a total dose of 6.0 for men. In women, the initial dose is 0.15; the highest does not exceed 0.45, and the total is 5.0. Injections of bismuth suspensions (bioquinol, bismoverol, etc.) are given in the intervals between novarsenol infusions; in robust individuals with healthy visceral organs, they can also be given simultaneously. The total dose per course should be brought up to 1.0-1.5 Bi met. Single doses and intervals between injections—see Bismuth. After 0.5-0.6 Bi met., in order to prevent kidney irritation, it is recommended to take a break in injections for 7-10 days while continuing novarsenol infusions. At the end of the course, a treatment break of 3-4 weeks is taken. 2nd course consists of novarsenol infusions in the same doses as in the previous course, and mercury injections. For mercury injections, it is better to use insoluble preparations—a 10% suspension of salicylic mercury, for a course of 1.5-2.0 of the salt (0.8-1.0 Hydr. met.), divided into 15-20 or more injections at the rate of 0.02 of the salt per day, or a 10% suspension of calomel, 0.5-0.9 of the salt (0.42-0.76 of mercury), divided into 10-15 injections at the rate of 0.02-0.015 of the salt per day. If patients do not tolerate insoluble preparations, soluble salts with a high percentage content can be used: 40-45 injections of a 1% Sol. Hydr. sublimati of 1 cm3 daily or 20-25 injections of a 2% solution of the same salt of 1 cm3 every other day (0.29-0.37 Hydr. met. per course), 40-45 injections of a 1% solution of Hydr. oxycyanati daily of 1 cm3 or 20 injections of a 2% solution of the same salt of 1 cm3 every other day (0.34 Hydr. met.), 40 injections of 2% Hydr. bijodati of 1 cm3 daily or every other day (0.34 Hydr. met. per course). Inunctions of gray ointment during abortive treatment may be permitted only in extreme cases, provided they are performed by experienced, specially trained medical personnel. When using soluble mercury salts or gray ointment inunctions, it is better to make 1-2 courses more than when injecting insoluble salts. It is desirable to adhere to the given scheme of alternating the use of bismuth in the 1st course and mercury in the 2nd, but in case of poor tolerance to one of these preparations, both courses can be carried out with one of them. 3rd course: 1-1.5 months after the end of the 2nd course. Mixed treatment with novarsenol and bismuth or mercury is carried out in the same doses as in the previous courses. In view of the possibility of positive serological reactions appearing during the course of treatment, it is desirable to perform blood serum examinations after the 1st and 2nd infusions, and in the middle and at the end of the course. In cases where positive seroreactions do not appear, there is no enlargement of regional glands and no induration at the site of the chancre, treatment ends after the 3rd course, and the patient is subsequently subjected to clinical and serological observation for at least 3 years. At the end of the second year of the disease, it is necessary to perform an examination of the cerebrospinal fluid, which is desirable to repeat in the third or fourth year of the disease. If before the start of treatment the duration of infection in patients with a primary affect exceeded 4-5 weeks, the chancre 10 days, and in cases of extensive and sharply expressed sclerosis or the presence of enlarged regional glands remaining after treatment, another 1 or 2 courses of the same intensity are added with intervals between them of 2-3 months. At the 1st Moscow State University in the clinic of Prof. G. I. Meshchersky, the following treatment regimen is carried out: Days Preparations Dose Days Preparations Dose 9 12 14 16 19 21 Neo..... Bioquinol.. Neo..... Bioquinol.. Neo ..... Bioquinol.. » . . Neo ..... Bioquinol.. » . . Neo ..... Bioquinol.. 0.3 1 cm3 0.45 1.5 cm3 0.45 2 cm3 2.5 cm3 0.60 2.5 cm3 2.5 cm3 0.60 2.5 cm3 2.5 cm3 27 28 30 34 35 37 40 41 43 47 48 50 Bioquinol Bioquinol » Neo . . . 2.5 cm3 0.60 2.5 cm3 1.5 cm3 0.60 2.5 cm3 2.5 cm3 0.60 2.5 cm3 2.5 cm3 0.60 3 cm3 Bioquinol Neo . . . Bioquinol » Neo . . . Bioquinol Total 9 infusions of neo at a dose of about 5 g and 15 injections of bioquinol at a total dose of about 35 cm3. Abortive treatment of syphilis according to Almquist's method see below. The abortive method of treatment of syphilis according to Scholz's method consists of the following: on the 1st day, an infusion of Alt-Salvarsan is given—0.2-0.3, 2nd day—0.3, 3rd day—0.2-0.3. On the 5th day, injections of Bismogenol or Spirobismol are given 2 days in a row at double the usual dose; the injections are repeated after 8 and 10 days 2 more times in the same doses (Bismogenol 1.5-2 cm3 and Spirobismol 2-2.5 cm3). Then the salvarsan series is resumed in the same doses, after which 2 or 3 bismuth strikes are repeated at 14-day intervals, and in conclusion, the salvarsan course again. If positive Wassermann reactions appear, then another bismuth series and a salvarsan series are added. With his method, Scholz had 100% cures in private practice and 85% in the polyclinic. Spiethoff administers Neosalvarsan infusions at a dose of 0.45 daily for 3 days in a row and combines it with bismuth. Politzer uses 0.9 for 3 days in a row, followed by a mercury treatment course—40 daily injections of a 1% solution of neutral salicylic mercury of 1 cm3. J. Werther administers an infusion of 0.45 three times within 24 hours. Every 8 days, the 2nd and 3rd such series are repeated. Only when a positive RW appears does he use bismuth between salvarsan series. In the seronegative stage of primary syphilis, Hoffmann conducts one combined salvarsan-bismuth treatment course, which consists of 10-12 infusions of neo or sodium salvarsan in single doses of 0.6-0.75 for men and 0.45-0.6 for women and 12 bismuth injections (0.8 of mesurol or 1.0-1.25 of bismogenol), with both neo infusions and injections occurring simultaneously on the same day approximately 2 times a week. In the seropositive period of the primary lesion, a second such course is given after 5 weeks. In secondary syphilis—after 2-3 months, the third course. In case of a serological or clinical relapse, malaria therapy is prescribed with a new cycle of maximum courses. The method of Scholz, somewhat modified in terms of the application methodology of bismuth (Bioquinol), was tested in the syphilidological department of the State Venereological Institute. Good tolerance by patients, more rapid disappearance of spirochetes, and resorption of the infiltrate of primary lesions and regional glands compared to conventional use were noted. The treatment regimen is given on page 579. Thus, for the entire course, 3.15-3.6 of novarsenol and 45 cm3 of Bioquinol are used. In the event of a positive seroreaction, another series of novarsenol and a series of bioquinol are added. On average, over the course of half a year, patients treated according to this method remained free of clinical and serological relapses. Days Preparations Dose Days Preparations Dose Novarsenol 0.3 Bioquinol 5 cm3 » 0.45 » 5 cm3 » 0.45 (0.3) 5 » 5 cm3 Bioquinol 10% suspension Novarsenol 0.3 » 5 cm3 » 0.45 » 5 cm3 » 0.45 (0.3) Novarsenol 0.3 Bioquinol 5 cm3 » 0.45 » 5 cm3 » 0.45 (0.3) » 5 cm3 To convert positive serological reactions to negative ones and to sanitize the pathological liquor, a greater number of treatment courses is usually required than in S. II recens. In case of skin relapses, it is desirable to conduct 1 or 2 treatment courses with frictions of gray mercurial ointment. In cases of persistent positive serological reactions, it is recommended to use injections of a calomel suspension. In general, one is guided by the provisions set forth for S. II recens. Iodide treatment at the end of the salvarsan-bismuth-mercury treatment is best carried out for 3-5 years.
If positive serological reactions or pathological cerebrospinal fluid do not respond to vigorous specific treatment, it must be discontinued and general strengthening spa treatment or physiotherapy applied, after which the resumed specific treatment may have greater success. Recently, treatment with malaria inoculation together with arsphenamine-bismuth preparations has been especially recommended in such cases. Clinical, serological, and cerebrospinal fluid controls are the same as in S. II recens. S. II seronegativa. If treatment was clearly insufficient regarding the doses used, the length of treatment, and its lack of systematic character, it must be supplemented by two, three, or more systematic courses of mixed treatment depending on the previous treatment, followed by iodine treatment. S. III manifesta, S. III latens seroposit, or with pathological cerebrospinal fluid. It is especially important to strictly adhere to the rule of beginning treatment with preparations that do not cause a sharp Jarisch-Herxheimer reaction. In cases of specific involvement of visceral organs or the central nervous system, it is better to start treatment with iodine and soluble mercury preparations and conduct treatment under the constant control of urine, general condition, and the patient's weight. If the treatment is well tolerated, one can switch to suspensions of bismuth, mercury, and novarsenol. There should not be too long breaks between individual courses. Converting positive serological reactions into negative ones and restoring the health of the cerebrospinal fluid is achieved faster and more often with more compressed courses. Brychev recommends for the first three courses making intervals of no more than 1 1/2-2 months, during which iodine treatment is prescribed. In further treatment, intervals can be increased regardless of the state of serological reactions and cerebrospinal fluid. Upon the disappearance of clinical symptoms of syphilis, positive serological reactions, and the restoration of the cerebrospinal fluid, it is necessary to carry out at least three or four more novarsenol-bismuth-mercury courses. At best, treatment should consist of no less than 6 systematic mixed courses of treatment with mercury, bismuth, and novarsenol in various combinations and doses, depending on the tolerability of the preparations, the general condition of the organism, and the clinical manifestations of the disease. If during this treatment the blood serological reactions remain positive, then with a healthy cerebrospinal fluid and the absence of clinical manifestations of syphilis, one can subsequently limit oneself to intermittent iodine treatment, the use of physiotherapy, and spa treatment. In cases where the cerebrospinal fluid remains positive, Brychev recommends for the prevention of clinical manifestations of syphilis. Basic principles of treatment of syphilis in various periods. S. I seropositiva (this category also includes cases in which a positive seroreaction appeared only during treatment). Specific preparations, doses, and methods of their application are the same as in the treatment of S. I seronegativa. Treatment must be brought to negative serological reactions. In addition to this, 3-4 consolidation courses must be carried out. Serological reactions must be performed at the end of each course and, if possible, in the middle of it and before the next course, and subsequently after the treatment for at least 3 years, one to two times a year, preferably after activation according to Milian-Gennrich. Control of the cerebrospinal fluid is performed at the end of treatment and after 3-4 years. S. II r e c e n s. To avoid the Jarisch-Herxheimer reaction, treatment must begin with the use of several (2 - 3) injections of bismuth or mercury preparations. Thereafter, combined treatment of the same intensity as in S. I seropositiva. Upon reaching negative serological reactions, another 4-5 courses are performed, of which 1 or 2 are preferably carried out by frictions of gray mercury ointment (40 frictions of 3.0-5.0 each), provided that one can hope they will be performed with sufficient intensity. With sharply expressed prodromal phenomena, general malaise, headache, joint pain, fever in the first course, iodine treatment is added. In general, it is better to do at least 6 courses, since for the majority of patients, converting the Wassermann reaction to negative requires at least 2 courses. In the intervals between the 4th, 5th, and 6th courses, iodine treatment is prescribed for 1 1/2-2 months, which must also be carried out after the end of the main treatment with arsphenamine, bismuth, and mercury for 2-3 years, 2 times a year. Serological control is performed as in S. I seropositiva, only somewhat longer, approximately for 5 years after the end of treatment. Examination of the cerebrospinal fluid is performed at the end of arsphenamine-bismuth-mercury treatment and is repeated in the fourth year of the disease and in the years of the most frequent development of aortitis, tabes, and general paresis in the 8th-12th year. S. II recidiva manifesta, S. III latens seropositiva, or with pathological cerebrospinal fluid. Treatment is the same as in S. II recens. Iodine treatment begins either simultaneously with the first novarsenol-bismuth or mercury course or after it and is prescribed in every break. For the central nervous system, besides iodine treatment, the use of bismuth and mercury in average doses in the amount of one or two courses per year. In view of the observed cases of death directly related to malaria during inoculation treatment in the late stages of syphilis in elderly patients with a marantic heart and phenomena of its insufficiency, as well as in liver and kidney diseases, one must be very careful. Malaria treatment should be restricted for now by special indications: in stubbornly non-responding specific and non-specific therapy pathological cerebrospinal fluid, progressive paralysis, and the initial stage of tabes dorsalis. S. III latens seronegativa. Taking into account that with negative serological reactions even after several decades severe manifestations of syphilis of the visceral organs and nervous system can occur, patients in whom treatment was clearly insufficient must undergo specific treatment. They need to undergo 3-4 mixed arsphenamine-mercury-bismuth courses with short intervals, iodine treatment between these courses and after their completion on average for 5-6 years. In cases where it is impossible to carry out treatment with novarsenol infusions, it can be replaced by osarsol, a preparation manufactured in the USSR by VOKHIM-PHARM for internal use, analogous to the French stovarsol and the German spirocide. In view of the fact that osarsol has therapeutic... Every five days a break is made for 3-5 days up to a total dose of 30.0-40.0. Each intake of osarsol is washed down with a small amount of water. Regarding side effects and contraindications to the use of osarsol, see Arsphenamine. Of other treatment methods, the permanent method developed by Almquist deserves attention. The principle of this method, unlike the chronically intermittent one, is that treatment is carried out continuously in separate courses with various antiluetic preparations. Treatment begins with neoarsphenamine in the amount of 10 infusions over 1 1/2 months, starting with a dose of 0.3 or 0.45 and reaching 0.9 (according to the latest instruction of the People's Commissariat of Health on the use of novarsenol in the USSR, the initial dose should not exceed 0.15 and the maximum 0.6 for men and 0.45 for women). A bismuth or mercury course of one month's duration in usual dosages is immediately performed. For the mercury course, Almquist prefers a suspension of Hydrargyrum salicylicum. Sometimes bismuth and mercury courses follow directly one after another without intervals. This is followed again by arsphenamine-bismuth and mercury courses. Such alternating courses continue for various periods depending on the duration of the infection and the state of serological reactions. At the end of such treatment, Almquist sometimes prescribes a course of injections of Oleum cinereum, intending to achieve a longer therapeutic effect. In conclusion, designated... Scheme of permanent treatment of syphilis of various durations according to Almquist. Neoarsphenamine 10 infusions 1 1/2 mos. Bismuth 10 injections 1 mo. Salicylate mercury 10 injections 1 mo. Abortive treatment 3 1/2 months. Neoarsphenamine 10 infusions 1 1/2 mos. Bismuth 10 injections 1 mo. Salicylate mercury 10 injections 1 mo. Neoarsphenamine 10 infusions 1 1/2 mos. Bismuth 10 injections 1 mo. Salicylate mercury 10 injections 1 mo. Short permanent treatment 7 mos. Neoarsphenamine 10 infusions 1 1/2 mos. Bismuth 10 injections 1 mo. Salicylate mercury 10 injections 1 mo. Neoarsphenamine 10 infusions 1 1/2 mos. Bismuth 10 injections 1 mo. Salicylate mercury 10 injections 1 mo. Neoarsphenamine 10 infusions 1 1/2 mos. Bismuth 10 injections 1 mo. Salicylate mercury 10 injections 1 mo. Permanent treatment, medium duration 10 1/2 mos. Neoarsphenamine 10 infusions 1 1/2 mos. Bismuth 10 injections 1 mo. Salicylate mercury 10 injections 1 mo. Salicylate mercury 10 injections 1 mo. Neoarsphenamine 10 infusions 1 1/2 mos. Bismuth 10 injections 1 mo. Salicylate mercury 10 injections 1 mo. Neoarsphenamine 10 infusions 1 1/2 mos. Bismuth 10 injections 1 mo. Salicylate mercury 10 injections 1 mo. Neoarsphenamine 10 infusions 1 1/2 mos. Bismuth 10 injections 1 mo. Salicylate mercury 10 injections 1 mo.
Long permanent treatment of 14 months has a weaker effect than novarsenol; in fresh forms of syphilis, when the most intensive treatment is required, replacing novarsenol infusions with it should only be done in extreme cases.
The use of osarsol is most indicated in late periods of syphilis, especially in the tertiary period, in so-called consolidation courses, and in the treatment of children.
A stronger therapeutic effect is achieved with the combined use of osarsol with bismuth, mercury, and iodide preparations.
For adults, osarsol is prescribed on the first day at 0.25, on the second day at 0.25 twice, on the third day at 0.25 three times a day on an empty stomach and 2-3 hours after eating, then at 1.0 per day: in the morning on an empty stomach 0.5 and in the evening after meals 0.5.
Observations on this treatment method revealed a somewhat greater number of side effects with its prolonged use compared to intermittently chronic treatment and the impossibility, due to domestic conditions, of conducting continuous treatment, especially in the summer months.
Treatment of syphilis according to the Linser method. This method, proposed by the author in 1919, consists of the simultaneous combined intravenous use of soluble mercury preparations and neosalvarsan.
The main idea was that the addition of mercury salts to salvarsan preparations enhances the effect of the latter.
Subsequently, this was confirmed by Kolle's experiments on animals.
Taking into account that soluble mercury preparations administered intravenously act faster and more intensely than with subcutaneous injections (Avvakov and Paskhalov, P. A. Pavlov), with the Linser method we have the most active effect of both mercury and salvarsan preparations.
Clinical observations on the effect of this method in the earliest periods of syphilis (primary and fresh secondary) are very favorable.
With it, a more rapid disappearance of spirochetes from infectious manifestations of syphilis is observed than with the use of pure salvarsan in the same doses, and a more intensive effect on the Wassermann reaction.
Its negative side is the insufficient duration of action, causing more frequent clinical and serological relapses than with ordinary combined treatment, and a somewhat greater number of side effects from the kidneys, stomach (nausea and vomiting), and skin (dermatitis).
It can be recommended only in those cases when it is not possible to carry out ordinary combined treatment, in preventive treatment, or in the earliest stages of primary seronegative chancre.
Of the salvarsan preparations for this method, nowadays mainly novarsenol-type preparations are used; previously, Alt-Salvarsan and silbernovarsolan (Brychev) were used.
Among mercury preparations, one should prefer those that do not coagulate protein and contain a high percentage of Hg.
Sublimate and mercuric iodide more often than others cause pain along the venous tract—periphlebitis.
The solution of mercuric chloride and sodium iodide proposed by Scilly and Haller [Hydrarg. bichlorati corrosivi 0.3, Natri jodati 1.4, Aq. dest. 30.0 (Somesin)] for intravenous infusion in a single syringe together with a 10% novarsenobenzene solution also frequently causes compaction of the venous walls (Brychev, Grigoriev) and has no advantages over a mixture of pure mercury solutions and NS according to observations at the State Venereological Institute.
Well tolerated, according to Brychev's observations, are mercury oxycyanide and especially Novoasurol, Embarin (Herbeck), and Cyarsal (Nagel, Oelze).
In total, an average of 8 to 12 mixed infusions of neosalvarsan and mercury solutions are given per course at intervals usual for neosalvarsan.
Neosalvarsan preparations are used in usual doses from 0.15 to 0.3-0.6.
The single dose of a 1% solution of oxycyanide and mercuric iodide is from 0.5 to 3.0 cm3, of a 1% sublimate solution from 0.5 to 2.0 cm3, of solvesin from 0.5 to 2.0 cm3, of novoasurol from 0.5 to 2.0 cm3, of embarin 1 cm3, of diarsal from 0.5 to 2 cm3.
To prepare the mixture, the salvarsan preparation is first dissolved in 5.0-8.0 cm3 of sterilized water, then the solution of mercury preparations in the indicated doses is added to it, and the mixture is shaken.
Upon mixing, a greenish-yellow or olive-green solution is formed, from which, when using sublimate, mercury oxycyanide, and mercuric iodide, small flakes rather quickly begin to precipitate, and therefore the infusion must be performed immediately after preparing the mixture.
In the intervals between infusions of the neosalvarsan mixture, some authors inject intravenously the same mercury preparation that was used for the mixture, in doses usual for each preparation.
Such courses are repeated at the usual intervals of chronically intermittent treatment, or they can be alternated with mercury injections of insoluble preparations, gray ointment frictions, or bismuth suspensions.
It must be kept in mind that the given schemes should be individually modified according to the general condition of the organism, its individual organs, the course of the disease, and the tolerance of individual preparations and their doses.
Treatment of malignant syphilis. Before the introduction of salvarsan and bismuth into the therapy of syphilis, combined treatment with iodide preparations in usual doses and injections of inorganic arsenic preparations was used with great success in the malignant course of syphilis, and upon restoration of the general condition, mercury treatment followed (A. I. Pospelov).
The phenomena of malignant syphilis pass best under the influence of salvarsan preparations used in usual doses.
The first infusion in sharply expressed exhaustion is best started with a dose of 0.15.
According to the observations of some authors (H. Müller, Brychev), bismuth suspensions in their effect on the manifestations of malignant syphilis can be equated to salvarsan preparations.
In some cases, bismuth preparations gave good results when salvarsan remained without any effect on the manifestations of malignant syphilis.
In sharply expressed cachexia, it is best to use the permanent method of administering specific agents to avoid a heavy load on the liver and kidneys: first, a salvarsan course of treatment is carried out, which is immediately followed by a bismuth one.
In cases of failure from specific agents, decoctions should be prescribed, of which the most widespread is Zittmann's decoction, after which treatment with specific agents should be resumed.
Upon the disappearance of the phenomena of malignant syphilis, routine treatment according to the chronically intermittent method should follow.
In cases where patients cannot frequently visit medical stations, the method tested in the clinic of the Regional State Venereological Institute for the simultaneous administration of novarsenol and a 20% suspension of bioquinol can be recommended.
Treatment according to this method can be carried out in adults with unimpaired functions of visceral organs.
With this method, patients are required to visit the medical station only 9 times during the entire course of treatment.
Treatment of syphilis is carried out according to the following schemes:
Scheme 1. Primary seronegative period.
1st day bioquinol 1.5 cm3 + novarsenol 0.3
4th day bioquinol 1.5 cm3 + novarsenol 0.45
7th day bioquinol 1.5 cm3 + novarsenol 0.6
12th day bioquinol 1.5 cm3 + novarsenol 0.6
18th day bioquinol 1.5 cm3 + novarsenol 0.6
24th day bioquinol 1.5 cm3 + novarsenol 0.6
30th day bioquinol 1.5 cm3 + novarsenol 0.6
36th day bioquinol 1.5 cm3 + novarsenol 0.6
42nd day bioquinol 1.5 cm3 + novarsenol 0.6
The total dose per course makes up 25.5 cm3 of a 20% bioquinol suspension and 4.95 of novarsenol.
Scheme 2. Primary seropositive and secondary period of syphilis.
1st day bioquinol 1.5 cm3 + novarsenol 0.3
3rd day bioquinol 1.5 cm3 + novarsenol 0.45
7th day bioquinol 1.5 cm3 + novarsenol 0.6
12th day bioquinol 1.5 cm3 + novarsenol 0.6
18th day bioquinol 1.5 cm3 + novarsenol 0.6
24th day bioquinol 1.5 cm3 + novarsenol 0.6
30th day bioquinol 1.5 cm3 + novarsenol 0.6
36th day bioquinol 1.5 cm3 + novarsenol 0.6
42nd day bioquinol 1.5 cm3 + novarsenol 0.6
Total per course 25.5 cm3 of a 20% bioquinol suspension and 4.95 of novarsenol.
Tertiary period of syphilis.
1st day bioquinol 1.5 cm3
3rd day bioquinol 1.5 cm3
6th day bioquinol 1.5 cm3 + novarsenol 0.15-0.3
16th day bioquinol 1.5 cm3 + novarsenol 0.45
bioquinol 1.5 cm3 + novarsenol 0.6
bioquinol 1.5 cm3 + novarsenol 0.6
bioquinol 1.5 cm3 + novarsenol 0.6
bioquinol 1.5 cm3 + novarsenol 0.6
bioquinol 1.5 cm3 + novarsenol 0.6
bioquinol 1.5 cm3 + novarsenol 0.6
bioquinol 1.5 cm3 + novarsenol 0.6
bioquinol 1.5 cm3 + novarsenol 0.6
0.45-0.6 Total for a course 25.5 cm3 of a 20% suspension of bioquinol and 2.25-3.15 of novarsenol. Instead of bioquinol, one can use a 10% suspension of mercury salicylate in an amount of 1-1.5 cm3 for 6 days. When using the latter drug, it is necessary to monitor the condition of the oral cavity more carefully and, in order to avoid gingivitis and stomatitis, prescribe lubrication of the gums with astringents and rinsing with disinfectants at the beginning of treatment. Treatment with iodine preparations according to the scheme of chronically intermittent treatment can be added to this treatment. Local treatment of manifestations of syphilis on the skin and mucous membranes. Although visible manifestations of syphilis on the skin and mucous membranes very quickly disappear under the influence of general treatment with the introduction of salvarsan into therapy, nevertheless, in order to shorten the period of contagious forms of syphilis as much as possible and eliminate the source of infection, the use of local agents that promote the rapid death of spirochetes and the resorption of specific infiltrates is entirely advisable. Local treatment is especially required for manifestations of syphilis that stubbornly resist specific agents, and cases where it is contraindicated to use their full therapeutic doses in nonspecific diseases of the kidneys, liver, heart, etc. Local treatment of the hard chancre. In view of the presence of virulent spirochetes in the sites of the former chancre even after energetic mixed treatment, local treatment of primary manifestations must be mandatory. In abortive treatment, when the chancre does not exceed ten days of age, if localization permits, it is better to excise it, which should be done beyond the boundaries of the palpable sclerosis and as deep as possible. Otherwise, a specific infiltrate forms again in an even larger size due to the increased activity of spirochetes, remaining in large numbers in the lumen and walls of blood and lymphatic vessels beyond the excision, caused by traumatic irritation. After removing the stitches, it is possible to recommend during the 1st course, for the purpose of complete resorption of the infiltrate, local hot baths followed by the application of mercury plaster 1 or 2 times a day. If excision is impossible, the chancre is destroyed by cauterization with hot air, according to Holländer, or with a galvanocautery. But in most cases, especially when the time for abortive treatment has been missed, they are limited to the local use of disinfectants. It is necessary to make it a rule not to use disinfectants until a bacterioscopic diagnosis is established in cases that are not entirely clear clinically, because later, in the absence of clinical and serological data, it becomes impossible to resolve the question of the existence of infection in a given subject. Before the bacterioscopic examination, compresses from a physiological NaCl solution should be applied to the ulcer. Locally on chancres, it is better to use mercury preparations in the form of ointments or powders. Carbolic-precipitate ointment according to the prescription of Prof. A. I. Pospelov can be recommended: Rp. Hydrarg. pp. albi 0.3, Phenoli puri 0.2-0.5, Ung. ceti 30.0. M.D.S. Ointment. Of the powders, calomel is usually used in a mixture with talc, xeroform, dermatol, Magnes. carbon., etc. For gangrenous and phagedenic chancres, iodoform is added: Rp. Calomelanos 2.0-3.0, Talci pulv., Magnes. carbon. aa 15.0. M.D.S. Powder. Rp. Jodoformii 10.0, Calomel. vap. par. 1.0. M.D.S. Powder. When the chancre is localized in the urethra, after each urination, a cotton wick smeared with precipitate ointment according to the prescription given above, or a suppository with calomel is inserted into the external urethral orifice. Rp. Calomel. 0.1, Butyr. cacao q. s. ut fiat bacillus urethralis. M.D.S. 1 suppository 2-3 times a day. In cases of severe decay or sharply expressed sclerosis, in order to avoid the formation of a stricture after the healing of the chancre, the use of bougies is necessary. For chancres in the oral cavity, frequent rinsing with disinfectants is recommended, preferably with 1 : 5,000-10,000 sublimate solutions. Rp. Hydrarg. sublimati corrosivi 0.5, Aq. menthae piperitae ad 100.0. M. D. S. One teaspoon per glass of water. Chancre erosion is smeared with 5-10% solutions of silver nitrate daily or every other day. In mixed chancre, it is best to use iodoform. Rp. Jodoformii, Pulv. Naphthalini subtil. aa 0.3, Hydrarg. pp. 0.3, Lanolini, Vaselini aa 15.0. M.D.S. Ointment. Rp. Iodoformii, Pulv. Naphthalini subtil. aa 10.0, Calomel. vap. par. 2.0. M.D.S. Powder. For faster resorption of the sclerotic induration remaining after the healing of the ulcer, it is recommended to use warm local baths 2-3 times a day for 20-30 minutes, followed by the application of mercury plaster. In the presence of inflammatory indurative phimosis, washings of the preputial sac with a weak sublimate solution (1.0 : 5,000.0) 2-3 times a day or with other disinfectants are prescribed, followed by lubrication with precipitate ointment, and if a mixed chancre is suspected, with ointment with the addition of iodoform. Only in those cases when sclerosis develops so strongly that it prevents urination, it is necessary to perform splitting of the foreskin with a median incision along its dorsal side. In gangrenous and phagedenic chancres accompanied by severe general phenomena and high temperature, bed rest and the immediate intravenous administration of salvarsan preparations are necessary, regardless of the temperature. Locally, frequent use of warm baths and disinfectants, warming compresses, preferably from 1/4% solution of silver nitrate or sublimate (1.0 : 5,000.0), ointments and powders with iodoform. For chancres in the vagina or on the cervix uteri, douching with a 1 : 1,000-2,000 sublimate solution is prescribed 1 or 2 times a day, followed by the insertion of a calomel globule or one of the powders or ointment indicated above. Rp. Calomelanos 0.2, But. cacao q. s. M. f. globulus vaginalis D. tal. dos. N... D. S. 1 globule 1-2 times a day. Local treatment of secondary manifestations of syphilis. To accelerate the resorption of individual papules on the skin, which is necessary in nummular papules, in papules on the palms and soles covered with a thick horny layer (psoriasis palmaris et plantaris, papulae corneae), warm local sublimate baths are used, or grey or precipitate mercury ointment is rubbed in. Erosive, ulcerous, and vegetative papules on the genitals, circa anum, in the armpits, under the breasts in women, or other places are dusted with calomel according to one of the specified formulas for the treatment of chancre or precipitate ointment is applied 1-2 times a day after preliminary washing or a local bath of a weak solution of potassium permanganate or another disinfectant. With very developed vegetations and organized papules, one has to resort to lubrication with a 10-20% lapis solution every 2-3 days or a lapis pencil. Papules on the oral mucosa are smeared with a 5-10% solution of lapis or chromic acid 1 time a day or a 1% water-glycerin solution of sublimate (Pospelov) or a 1:100-300 salvarsan solution. Patients must observe oral hygiene, brush their teeth, frequently rinse the mouth with disinfectants, remove carious teeth, refrain from smoking, alcoholic beverages, spicy dishes, etc., which contributes not only to the rapid absorption of the specific infiltrate, but also serves as a preventive measure against the formation of gingivitis and stomatitis during treatment with mercury and bismuth. In paronychia syphilitica, usually accompanied by severe pain, especially in inflammatory forms and suppuration, local warm baths are used, followed by the application of mercury plaster in dry forms, precipitate ointment or a warming compress from a 1 : 5,000 sublimate solution in erosive or ulcerative ones. Local treatment of tertiary manifestations on the skin and mucous membranes. Local and general warm baths contribute well to the resorption of tubercles and gummas; the latter are especially indicated for extensive distribution of nodular syphilis on the trunk. On unulcerated tubercles and gummas, mercury plaster is used, local heat in the form of a hot water bottle; on ulcerated syphilides, carbolic-precipitate, iodoform, and other disinfecting ointments are applied. In general, one must carefully take care of the cleanliness of the ulcer, which promotes more rapid growth of granulations and scarring. For this purpose, washing the ulcers with potassium permanganate solutions, hydrogen peroxide, and lubrication with tincture of iodine are used. For painful ulcers, carbolic oil (10-15%) recommended by A. I. Pospelov is prescribed with great success. Most often, local treatment has to be used for ulcerated gummas surrounded over a large area by scar tissue, when often even mixed salvarsan-mercury and bismuth treatment remains completely powerless. In such cases, prolonged local hot baths with disinfectants are prescribed, lubrication of the calloused edges of the ulcer with a lapis pencil 1 or 2 times a week, followed by the application of a warming compress from weak solutions of disinfectants (e.g., 5% boric acid solution) and a hot water bottle.
If scarring still proceeds slowly, one may resort to physical methods of treatment, X-rays, the quartz lamp, or diathermy. When all the indicated methods fail, one must resort to curettage of the ulcer and cauterization with a thermocautery. In the case of ulcerative gummas on mucous membranes, it is best to apply daily swabbing of the ulcers with Lugol's solution and frequent rinsing with disinfecting solutions, or swabbing with 5-10% solutions of silver nitrate or chromic acid.
A. Brychev.
X. Personal prophylaxis. Personal prophylaxis of syphilis can be carried out by the use of preventive measures before or after sexual intercourse; the former include the condom (see), the preventive significance of which with regard to the danger of contracting syphilis is small, since it leaves the pubic and thigh areas unprotected. Relative, but considerably greater significance is possessed by measures applied after sexual intercourse. These include: washing the genitals, thighs, and pubic region with solutions of potassium permanganate or corrosive sublimate (1:1,000); washings with corrosive sublimate must be performed with extreme caution. After washing, ointments should be rubbed in: 33% calomel ointment (according to Metchnikoff and Roux: Calomel, v. h. p., Lanolini, Vaselini fl. aa 10.0); sublimate ointment (according to Neisser-Siebert: Hydrarg. bichlor. or Hydrarg. oxy-cyan. 0.06, Lanolini pur. 15.0); 30% quinine ointment (according to Schereschewsky); calomel ointment with the addition of carbolic acid (according to Walker: 33% Ung. calomelan., Ac. carbolic. 1%, Camphorae 1%). Königsberg (at the State Venereological Institute in Moscow) proposed the preparation oxyviridol synthesized by him. In connection with the introduction of osarsol-type preparations into the therapy of syphilis (see Salvarsan), some authors have recommended their use for prophylactic purposes; thus, Jadassohn recommends prescribing 0.25 g, 3-4 tablets a day for 3 days, then repeating this amount after a 3-day interval; Pincus, 4 tablets every other day for 4 days. The prescription of osarsol for the prophylaxis of syphilis, however, requires medical supervision in view of the possibility of side effects. In cases where the danger of contracting syphilis is aggravated by the presence of infection in one of the partners, it is recommended to carry out a prophylactic course of neo-salvarsan infusions in a total amount of up to 3.0-4.0 of the preparation; Jordan recommends in such cases conducting a combined bismuth-salvarsan course carried out according to the general schemes of syphilis treatment (see above). - Medical supervision in the personal prophylaxis of syphilis, which is of great importance both in the sense of the correct choice of method and means, and, most importantly, in their timely application, is carried out in a number of cities of the USSR at so-called personal prophylaxis stations, where all preventive measures are carried out by medical personnel. The danger of simultaneous infection with gonorrhea is prevented by using, along with the methods indicated above, irrigations of the anterior urethra with warm solutions of potassium permanganate (1:3,000 - 4,000) followed by the injection of 5-10% protargol-glycerin or albargin solutions. Personal prophylaxis of syphilis is used most frequently among men; in women, due to the complexity of the anatomical structure of the genital organs, the use of means for personal prophylaxis is difficult.
S. Halperin. XI. Congenital Syphilis. Congenital syphilis (syphilis hereditaria, lues congenita) became known toward the end of the 15th century, when syphilis spread endemically throughout Europe. Scientists and physicians of that time drew attention to the fact that parents with syphilis give birth to sick children and that the clinical signs of the disease in newborn children, especially rashes, bore a certain similarity to those skin manifestations observed in adults with syphilis. Thus, Torella in 1498, Vella in 1508, and Cataneus in 1516 first pointed out that infection of the child occurs through the mother during childbirth or after birth through infected milk, and sometimes through the affected mammary gland. In 1529, Paracelsus expressed the opinion that syphilis in a child appears in the mother's womb and that fetal infection originates from the father through infected seed, and sometimes the child may be born healthy. In 1533, we find indications in Ferrier that syphilis can be transmitted by the germinal route (by the father or mother), as well as intrauterinely (through the placenta). A little later, Rosenstein noted that parents sick with syphilis can give birth to outwardly healthy children who, after some time, and sometimes after several years, exhibit phenomena of congenital syphilis. An interesting thought for its time was expressed by Raulin (in 1768) when he pointed out that the only prophylactic measure against hereditary diseases that cause miscarriages or the birth of defective children is the treatment of parents before marriage. Thus, in the 18th century, the study of the transmission of congenital syphilis was on the right path. Subsequently, however, Genter's work in England introduced erroneous concepts into the doctrine of congenital syphilis as well. Genter asserted that syphilis in newborns is possible only if the mother had a hard chancre on her genital organs during pregnancy or childbirth. A number of physicians of that time joined Genter's opinion. The second prominent scientist, Ricord, also considered the secondary period non-infectious, yet recognized the existence of congenital syphilis, an opinion shared by many authors despite the rejection of this theory by authoritative scientists of that time. Some authors recognized the transmission of syphilis only on the part of the father, others attributed exclusive importance in the transmission of this infection to progeny to the mother, while others believed that the disease could be transmitted by both the father and the mother. The prominent German scientist in the field of congenital syphilis, Kassowitz, initially recognized exclusively the germinal method of transmission, mainly on the part of the father, while Fournier and his school, along with infection through the placenta, considered paternal transmission possible as well. In 1903, the famous work of Matzenauer appeared, who expressed the view that the only possible method of transmission of congenital syphilis is placental transmission by a sick mother. This opinion is recognized at present by almost all authors, although such scientists as Finger, Hochsinger, and Almquist defend the germinal theory alongside the placental theory, pointing out the possibility of the direct participation of the father in transmitting the infection to the child, while the mother may remain healthy. Thus, views regarding the transmission of syphilis to progeny have undergone constant changes over the past centuries (see Colles' law). The transmission of syphilis to the child through the placenta can occur in two ways. First, the spirochete can be carried into the child's organism in the form of an embolus through the umbilical vein. This method is the most frequent and is confirmed by patho-anatomical data, since spirochetes have often been found in the lumen of the umbilical vessels. In the second method (pointed out by Rietschel as early as 1912), the penetration of spirochetes occurs due to their ability to move in the lymph clefts of the umbilical vessels. Regarding syphilis of the placenta, see Placenta, patho-anatomical changes in certain maternal and fetal diseases [see also separate table (articles 91-92), figures 3 and 6]. Graefenberg found the spirochete less frequently in the placenta (in 40%) than in the organs of the same fetus (in 100%); this indicates that the fetus is a better medium for the reproduction of spirochetes than the placenta. Studies by Manouelian, pointing to the scarcity of the placenta in syphilitic virus, establish intensive phagocytosis of pale treponemes in the placenta, and spirochetes can be detected in the form of rings, granules, and disintegrating clumps. It is possible that the destruction of spirochetes occurs in the placenta. Histopathological changes in the umbilical cord are characterized by lymphocytic infiltration of the vessel walls, mainly the muscular layer (Thomsen). As for spirochetes, they were found in the umbilical cord by many authors in 100%, while their presence in the fetal membranes is noted extremely rarely (Graefenberg, Moun). The fetal membranes give, according to some authors, inflammatory phenomena with infiltration by large embryonic cells in the chorion and amnion. These lesions can entail an increase or decrease in amniotic fluid. The law established by Kassowitz in 1878, stating that the fresher the syphilis in the mother, the more frequently she gives birth to sick children and the stronger the manifestations of syphilis in them, remains valid today, although deviations from it are observed. Most often, syphilis is transmitted in the first 3 years after the parents' infection, with the maximum incidence falling on the first year of the disease, during the secondary period of the mother's syphilis. At this time, the greatest number of abortions and stillbirths is observed. After 3 years, the transmission of infection becomes less regular, but does not fade out completely (see Fetus, fetal diseases). Treatment carried out irregularly and insufficiently explains circumstances of this kind: after treatment, particularly during pregnancy, the birth of a healthy child is possible, while the next pregnancy—without specific treatment—may end in the birth of a sick child. Energetic treatment, however, carried out before and after pregnancy, usually results in the birth of healthy children. It should be pointed out that a parallelism does not always exist between the freshness of the mother's syphilis and the character of the child's syphilis manifestations: mothers with manifestations of syphilis of both the secondary and tertiary periods can give birth to outwardly healthy children, while mothers without visible manifestations of syphilis, but with a positive Wassermann reaction, often give birth to children with severe symptoms of the disease. The course of syphilis in women giving birth to sick children is often peculiar: the disease in some women proceeds without the usual symptoms of acquired syphilis (hard chancre, skin syphilids, mucous membranes, bones, etc.), but is expressed only by a prolonged Wassermann reaction, gradually increasing cachexia, miscarriages, premature births, stillbirths, and the birth of syphilitics. The peculiar course of syphilis in women is attempted to be explained either by the method of introduction of the syphilitic virus (Rietschel) or by the character of the tissue where the spirochete lands (Neisser). If the syphilitic poison gets into the skin, the usual course of the disease is observed with the formation of a hard chancre, whereas if the spirochete gets into the uterus, lined with ciliated epithelium, the infection gives a milder course of the process. It is entirely admissible that the uterine mucosa is not a favorable soil for the reproduction of spirochetes, that the well-developed network of pelvic lymph glands captures the spirochetes, and thus the organism is placed in better conditions and keeps the infection in a latent stage. The question of second-generation syphilis, of the possibility of transmitting infection by congenitally syphilitic individuals to progeny, is at present resolved thanks to the works of Tarnovsky, Barthelemy, Finger, Julien, and Fournier (Barthelemy, Jullien). Almost all authors believe that second-generation syphilis can be spoken of in the presence of the following conditions: 1) that one of the parents has congenital syphilis, 2) that acquired syphilis is excluded in the second parent, 3) that unquestionable signs of congenital syphilis are established in the born child shortly after birth. Especially interesting in this direction is the work of Fournier, published in 1905. The author observed 116 families of congenital syphilitics where lues acquisita can be excluded, and on the basis of his material he believes that second-generation syphilis gives a high mortality rate (two-fifths of all progeny), gives phenomena of dystrophy, just as in the first generation, in a small percentage of cases gives phenomena of florid syphilis, and finally the number of healthy children in second-generation syphilis is small—8.4%. Thus, syphilis of both the first and second generations, according to Fournier, is of two kinds: syphilis with phenomena of dystrophy and syphilis with overt signs; Milian adds a third form—syphilis muette (mute syphilis, or latent). Early congenital syphilis. Congenital syphilis produces lesions of a number of organs and systems, causing its non-viability in a certain significant percentage of cases (see Fetus, fetal diseases). In those children who come into the world alive, clinical symptoms are relatively rarely present at birth. In the majority of cases, the child is born without signs of the disease, and only toward the end of the first month or at the beginning of the second do symptoms appear indicating the presence of syphilis. Most often, the appearance of signs refers to the first 2 months of life.
Finkelstein, distributing his material, notes the appearance of symptoms in the first month 29 times and in the second month 27 times out of 56 children. According to the State Scientific Institute of Maternity and Infancy Protection of the People's Commissariat of Health, the appearance of signs of the disease in the first month was observed in 32%, in the second in 36%, in the third in 16%, in the fourth in 10%, later in 6%, moreover in 3 cases the appearance of symptoms was noted by the 8th and 9th months and in 2 cases at 3 and 4 years. Skin disease in children with congenital syphilis occurs comparatively frequently and takes the most diverse forms. A particularly characteristic and frequent rash in congenital syphilis is the diffuse syphilid, described in particular detail by Hochsinger. Most often this process, according to Kassowitz and Hochsinger, is noted on the soles and palms (in 88.4%), less often on the face and scalp (in 47.2%) and only in 16% on the buttocks, posterior surface of the thighs and legs [see separate table (p. 407-408), Fig. 4 and 5]. Among children admitted with skin manifestations to the syphilitic clinic of the State Scientific Institute of Maternity and Infancy Protection, this rash was observed in 60% in one or more of the above-mentioned places. The diffuse syphilid is usually encountered in the first half-year, with the maximum falling in the first 3 months of life, especially the 6th and 8th weeks. The appearance of this syphilid is preceded by a diffuse erythema or the appearance of separate spots tending to merge. The diffuse syphilid on the face, lips, and chin is particularly typical. The lips are thickened, covered with bleeding fissures that leave deep scars after healing, especially at the corners of the mouth. These scars remain for life and have great diagnostic significance. Maceration and crust formation are frequently observed on the chin. The forehead and cheeks are less frequently affected, and the skin in these places has a brownish-yellow tint. At the border of the forehead and scalp, the induration of the skin takes the form of a seborrheic disease. Affection of the soles and palms by a diffuse process is observed more often than affection of the face and is encountered in an earlier period. Usually, in the presence of skin lesions on the face, infiltrative processes on the soles and palms are also noted, and both the soles and palms present a uniform erythema and continuous induration. In later stages, the soles become shiny,
as if varnished, especially on the heels. Usually the process on the soles and palms ends with desquamation. The diffuse syphilid on the buttocks, on the posterior surface of the thighs and legs takes on a greater spread, and the skin of the scrotum and labia majora is not infrequently subjected to change. In the affected places, desquamation of the skin and a tendency to ulceration are observed, which merge and form bleeding areas devoid of epithelial coverings. These areas frequently have scalloped edges. The second typical rash for congenital syphilis is syphilitic pemphigus, which is observed less frequently than other eruptions and may be present already at birth or appears in the first days after birth. This rash is localized on the soles, palms, passing not infrequently to the legs, forearms, trunk, and face. Syphilitic pemphigus consists of small blisters ranging in size from a pea to a cherry. The contents of the blisters, initially transparent and serous, quickly become turbid and purulent, and sometimes take on a hemorrhagic character. These blisters are surrounded by an inflammatory rim, tend to merge, and, bursting, form erosive surfaces.
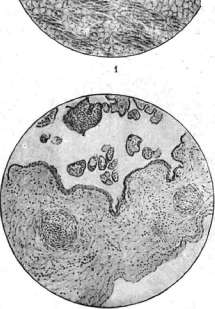
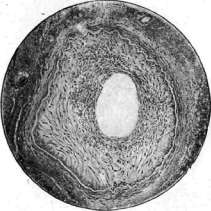
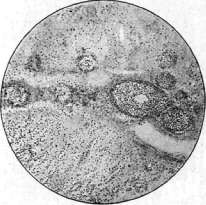
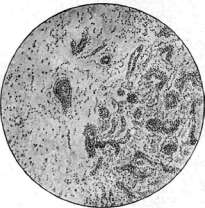
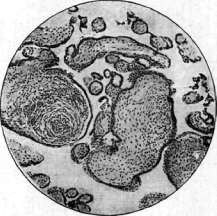
Fig. Fatty infiltration of the myocardium. Figure. Endarteritis in syphilis. Figure. Obliterating
ing syphilitic endarteritis of the placenta. Figure 4. Gummous encephalitis-endo- and periarteritis. Figure 5. Gummous arteritis, verarteriit of the brain. Figure 6, Villous "abscesses" of the chorionic villi. Upon healing, abundant lamellar desquamation is ordinarily noted. This rash contains a large number of spirochetes and is observed simultaneously with involvement of the internal organs, especially the liver and spleen. The majority of infants with pemphigus syphiliticus are born premature and perish (without treatment) in the first weeks of life. Besides the above-described skin lesions in congenital syphilis, a papular rash is frequently encountered, usually 4–6 and 8 weeks after birth, more rarely after 3 months of life. This rash is pink in color, localizing most often on the face, extremities, and buttocks, and frequently on the body, in the form of small flat papules rising above the skin surface, moderately dense, and characteristically shiny. They tend to desquamate, which begins in the center, leaving a clean pink rim at the edges; on the face, the rash frequently transforms into pustular, while on the buttocks and in skin folds it assumes a weeping character, which gives a resemblance to intertrigo, wherein sometimes only the presence of other specific changes determines the true character of the affliction. The papular rash leaves behind pigmentation in the form of brownish spots, which subsequently disappear. Characteristic of congenital syphilis are the various developmental stages of the papular rash in the same child and its polymorphic character. Macular rash is encountered in congenital lues in early infancy rather rarely, appearing on the body, face, and extremities. Its color is pink, frequently with a yellowish tint. Sometimes the rash develops in the first days after birth. Syphilids of the skin are frequently polymorphic. Changes on the part of the skin are not always present in children with congenital syphilis. Müller determines the frequency of skin lesions at 84%, Werner at 65%, Still at 69%. According to data from GNIOMM NKZ, the percentage of children with cutaneous manifestations reaches up to 68. Nail changes in children with congenital syphilis occur (according to Müller) in 25% and reduce, on the one hand, to a disease of the nail itself (tubular nails, nail brittleness, transverse and longitudinal striation, division of the nail by a roller into 2 parts), and, on the other hand, to involvement of the nail folds and nail bed, leading to the formation of fissures and ulcerations—syphilitic paronychia, which may be observed on several fingers simultaneously. Hair coat changes in congenital syphilis reduce to patchy alopecia or general thinning of the hair. Moreover, in infants as a result of diffuse syphilid on the face, there is noted an absence of eyebrows and irregular arrangement of eyelashes. Relapsing phenomena on the skin are usually observed in poorly treated children and are of a large-papular and vesicular character. The appearance of rashes in children with congenital syphilis is frequently accompanied by an elevation in temperature and deterioration of the general condition. Spirochetes are frequently found in skin lesions (in 95% according to V. R. Sklyar). Disease of the mucous membranes. Among mucous membranes in congenital syphilis, the nasal mucosa is most often affected. Syphilitic rhinitis is one of the early and frequent signs of the disease; most often it is discovered in the first weeks of life and frequently already at birth. According to observations by GNIOMM NKZ, syphilitic rhinitis is encountered in 70% of congenital syphilis, and most often develops in the first 4 weeks of life. As autopsies of stillborn syphilitics show, rhinitis begins to develop in the child still in the mother's womb. Syphilitic rhinitis is a chronic disease characterized by inflammation of the nasal mucosa with simultaneous involvement of the nasal conchae. At its base lies mucosal infiltration leading to narrowing of the nasal lumen, owing to which the characteristic snorting during breathing occurs, which is frequently audible from a neighboring room. Mucopurulent or bloody discharge leads to the formation of crusts clogging the nasal lumen, which hinders the infant from sucking the breast. Syphilitic rhinitis is distinguished by a slow course and poorly yields to treatment; it rarely disappears after a single course of treatment, more often only after 2–3 courses. In untreated or poorly treated cases, there is observed a transition of the process to the cartilaginous and bony parts of the nose, their partial destruction, which frequently gives the characteristic saddle-nose shape. The deformation of the nose may also assume sharper forms, especially in the presence of perforation of the nasal septum and loss of the entire osteocartilaginous skeleton. In these cases, atrophic catarrh of the nose is ordinarily observed, frequently accompanied by strong stench. Especially characteristic of congenital syphilis in infancy are the small size of the nose, sinking and widening of the bridge of the nose, and the transition of the bony part into the cartilaginous in the form of a step. Sometimes syphilitic rhinitis is the first and only sign of congenital syphilis and consequently decisive in making the diagnosis. Spirochetes on the nasal mucosa (Sklyar) were found mainly with simultaneous involvement of the skin by a specific process. Besides the nasal mucosa, in children with congenital syphilis the laryngeal mucosa also becomes diseased, which manifests as a hoarse voice, aphonia, and in rarer cases as laryngeal stenosis. Syphilitic stenoses in early age children can simulate diphtheritic stenosis; the duration of the course speaks for the syphilitic character of the affliction. These stenoses on the material of GNIOMM NKZ were noted in 1% of cases. Involvement of the oral and pharyngeal mucosa in congenital syphilis is encountered comparatively rarely; it is observed in the form of erosions and superficial ulcerations. These ulcers are occasionally noted on the hard palate, and in untreated cases the process passes from the mucosa to the bone, producing destructive processes ending in perforation of the hard palate. Disease of the mucosa of the anus in early age children is observed in the form of condylomas and is encountered ordinarily in poorly treated cases. Fissures around the anus most often accompany involvement of the buttocks by a diffuse process. Disease of the internal organs, representing one of the early signs of congenital syphilis, is characterized mainly by a process that leads to diffuse infiltration and proliferation of cellular elements, which is clearly visible upon studying the changes in the visceral organs of syphilitic fetuses, newborns, and infants with congenital lues. Acquired syphilis, as well as late congenital, have, conversely, a tendency to produce focal formations. Besides diffuse changes in the organs of syphilitic children, the presence of gummas is noted, encountered more often simultaneously with diffuse infiltration, less often independently. Gummas have been described (Kraus, Aschoff, Ribbert, Tikhomirov, and others) in the liver, kidneys, lungs, and spleen. Involvement of the liver in children with congenital syphilis is encountered comparatively early and can frequently be discovered already at birth. Spirochetes enter the child's organism mainly through the umbilical vein, which explains the such frequent liver disease. Among clinical symptoms, enlargement of the liver should be placed in the first place, and then its density. Hochsinger in 148 children with congenital syphilis in the first year of life was able 46 times, i.e., in 31%, to clinically ascertain enlargement of the liver. According to GNIOMM data, liver enlargement was noted in 80%, and in children under the age of 4 months this sign was comparatively rarely absent. Not always, however, was the liver sharply densified—in 30% it was possible to note an enlarged, but not dense liver, and after a conducted course of treatment its dimensions reached normal. The liver surface is ordinarily smooth. Liver disease, frequently accompanied by other specific symptoms on the skin and in the skeletal system, does not present diagnostic difficulties. In the absence of cutaneous manifestations, there are almost always present a specific rhinitis, as well as enlargement of the spleen and blood changes. A dense liver, being one of the signs of visceral syphilis, poorly yields to treatment. Alongside liver enlargement, Zhukovsky has described cases of atrophic cirrhosis. These are ordinarily severely ill children, not viable. The spleen in congenital lues is affected just as frequently as the liver, and, as Marfan points out, its enlargement is a constant and one of the early symptoms of congenital syphilis. According to Finkelstein, it is enlarged in 77%, but it is not always possible to palpate it immediately. Usually, enlargement of the spleen is accompanied by its densification, its lower edge is sharp, protruding 2–3 cm from under the costal arch; in more severe cases of visceral syphilis, the spleen reaches the navel and can be palpated in the lesser pelvis. These cases are almost always accompanied by enlargement of the liver and severe blood changes. Sometimes upon palpation of the lower edge of the spleen, one can ascertain unevenness and roughness, indicating the presence of inflammatory processes in the spleen capsule; these phenomena were pointed out in their time by Parrot and Finkelstein. The histopathological process in the spleen, according to Prof. Nikolayev, has an interstitial character or else reduces to the formation of miliary gummas. In the surroundings of follicles and vascular walls, there is observed the development of connective tissue, which contains a large number of cellular elements.
Lung disease in infants with congenital syphilis is of no great significance for the clinician, because the majority of children with this condition die intrauterinely or shortly after birth. They rarely survive up to 3 months. Children with syphilitic pneumonias give the impression of being severely ill. The clinical symptoms of the disease—dyspnea and cyanosis—do not coincide with the percussion and auscultation data. Both dullness and altered respiration are usually absent here. There are likewise no phenomena indicating bronchial inflammation. The observed microscopic proliferation of connective tissue occurs in small areas around the alveoli, leads to their narrowing, and reduces the air content, without producing any changes either in the pulmonary sound or in the respiratory murmurs. Miller's work on the material of the Moscow Foundling Home for the period from 1880 to 1890 indicates the rarity of lung involvement by the specific process in infants. Out of 14,411 cases of pneumonia in infancy with a fatal outcome, verified at autopsy, only 0.7% gave syphilitic changes in the lung tissue. Involvement of the kidneys in children with congenital syphilis occurs, according to the State Scientific Institute of Maternity and Infancy Protection of the People's Commissariat of Health, in 30%. Not infrequently, children with specific rashes exhibit phenomena of nephroso-nephritis, which under the influence of treatment passes away along with the disappearing rash. The urine usually contains protein and formed elements, edema is frequently observed, and in severe cases, uremia. Characteristic of specifically affected kidneys is a high percentage of protein in the urine, reaching 12-14%, in the absence of formed elements. Usually, under the influence of treatment with salvarsan or mercury preparations, these phenomena resolve rapidly, unless the kidney disease is one of the symptoms of general visceral syphilis, which significantly worsens the prognosis. It should also be pointed out that on the basis of congenital syphilis, underdevelopment of the renal parenchyma is noted. Histopathologically, in kidney involvement, interstitial processes and occasionally gummans (see Kidneys) are noted. Disease of the cardiovascular apparatus is noted at an early age in children with congenital syphilis, and (as Hutinel points out) the basis of heart involvement lies in: 1) pathological processes in the heart muscle of both interstitial and parenchymatous character, 2) endocardial changes resulting in valve lesions, and 3) disease of the pericardial sac. Vascular involvement, which plays a major role in the late periods of syphilis, is found in infants more often than was thought hitherto. Autopsies and histopathological studies performed on the material of the State Scientific Institute of Maternity and Infancy Protection (Tikhomirov) show vascular involvement in 94%, with changes in 58% affecting small arteries and expressed as obliterating proliferation of the intima endothelium. In addition, in 70% inflammatory-infiltrative changes were found in the walls of veins, especially of the liver and adrenal glands. Disease of the pancreas on the basis of congenital syphilis gives enlargement of the organ, the basis of which is the proliferation of connective tissue, rich in cells, in the lobules themselves, around them and around the ducts. The thyroid gland presents the same picture. Of the other endocrine glands, the adrenal glands are most frequently affected; according to Levaditi, spirochetes are very often discovered here. In children with congenital syphilis, shortly after birth (in 20%, according to the State Scientific Institute of Maternity and Infancy Protection), testicular disease is noted. This phenomenon has been described by both German (Henoch, Hochsinger) and French (Marfan and Vallery-Radot) authors. Both Hochsinger and Marfan point to the frequent connection between hydrocele of the testis and congenital syphilis, even in cases where disease of the testicular parenchyma is absent. The testis is usually enlarged and strikes by its density. Anatomically, the process reduces to round-cell infiltration and proliferation of perivascular tissue, which leads initially to enlargement and subsequently to shrinking of the organ. Enlargement and density of peripheral lymph glands are noted in children with congenital syphilis relatively frequently, in approximately 70% (data of the State Scientific Institute of Maternity and Infancy Protection). However, literary data on this issue are rather contradictory. While syphilologists believe that polyadenitis, which is a characteristic symptom for adults, may often be absent in children with congenital syphilis, pediatricians like Henoch and Doyen note the comparative frequency of this sign in children with congenital syphilis. The cubital glands are enlarged, according to Hochsinger, in 90%, and according to the State Scientific Institute of Maternity and Infancy Protection, in 50%. Involvement of the bone system—see Bone, clinic of bone diseases, Osteochondritis, Periostitis. The central nervous system suffers in infants with congenital syphilis, as Hochsinger points out, much more frequently than is commonly thought. Almost always, children with fresh manifestations of syphilis show symptoms of irritation from the meninges. The neck rigidity and rapidly passing convulsions frequently observed in this period disappear under the influence of treatment along with skin manifestations. On the other hand, it is not uncommon for newborns and infants, in the absence of clinical symptoms from the nervous system, to show severe inflammatory changes ending in softening in both the meninges and the brain tissue upon autopsy, with spirochetes being found in some cases. One of the early symptoms of nervous system irritation is the child's crying, both day and night, which responds well to specific therapy. Relatively early, sometimes in the first weeks of life, convulsions are noted—rapidly passing, sometimes resembling petit mal. The frequently encountered dilation of veins indicates an increased intracranial pressure. Spinal puncture yields fluid under high pressure. These convulsions at an early age are harbingers of more severe nervous system involvement in older children. A cardinal symptom in lesions of the central nervous system in infants on the basis of congenital syphilis is hydrocephalus or dropsy of the brain, which can proceed acutely and chronically, be congenital or develop some time after birth (see Hydrocephalus). Hydrocephalus is often accompanied by other specific lesions, among which a rhinitis and a sunken bridge of the nose are particularly frequent. Among other diseases of the central nervous system, one can note syphilitic meningitis, developing, like tuberculous meningitis, at the base of the brain. The diagnosis is decided by examination of the cerebrospinal fluid. In addition to meningitides, meningoencephalitides are also observed, giving hemiparesis and hemiplegia, which do not always yield to specific therapy. Of the sense organs in infants, the eye and the fundus oculi are most frequently affected. Quite early, not infrequently already at birth, the retina and choroid, as well as the optic nerve, are altered. These lesions were first described in particular detail by Hirschberg in 1895. Syphilitic chorioretinitis is characterized by the presence at the fundus of the eye of small yellow spots with pigment foci in the form of salt and pepper or "snuff." These changes are localized in the region of the equator and along the periphery of the fundus oculi and are especially typical of congenital syphilis of early childhood. Vision does not suffer. Optic nerve disease gives blurred papillae and vague contours, and these phenomena can be observed simultaneously with retinal disease. Dangerous in the sense of loss of vision is optic nerve atrophy, which can also be observed in children under 3 months of life. However, it is more often encountered after a year and in older children. Inflammation of the iris is less frequently observed in infants. In addition, in young children, parenchymatous keratitis is noted, albeit rarely (according to the State Scientific Institute of Maternity and Infancy Protection of the People's Commissariat of Health, in 1%) (see Keratitis). The pathomorphological picture of the blood in children with congenital syphilis relatively frequently presents phenomena of secondary anemia, the severity of which is in close connection with the involvement of visceral organs and the skeletal system (see Anemia, anemias in children). The physicochemical properties of the blood also show deviations from the norm. Blood enzymes catalase and protease (Walter) give low figures, especially in children with visceral syphilis. The erythrocyte sedimentation reaction in children with congenital syphilis almost as a rule gives an acceleration (Weiss), which is in direct dependence on the severity of the process, the sharpness of manifestations, and the variety of diseased organs. The Wassermann reaction in children with congenital syphilis gives a positive result in a larger percentage of cases shortly after birth. Cases with skin manifestations almost always proceed with a positive Wassermann reaction. Diseases of the skeletal system sometimes give a negative Wassermann reaction in the presence of a specific process (in 6%) (see Wassermann reaction). Late congenital syphilis. Late congenital syphilis (syphilis hereditaria tarda, lues congenita tarda) was particularly studied in detail and described by A. Fournier. Many authors, including Zappert, regard late congenital syphilis as a relapse of early syphilis, the manifestations of which were overlooked. Others, however, like A. and E. Fournier, believe that the congenital infection can remain in a latent clinical state for a long time and manifest itself, albeit in rare cases, not only in mature, but also in advanced age.
According to existing observations, the earliest age at which manifestations of late congenital syphilis have been noted is considered to be the 4th year of life, according to data from GNIOMM, 21/2 years. However, most frequently, late congenital syphilis is encountered at the age of 8 to 14 years, although there are not a few observations where the first signs of fresh late syphilis manifested in older children as well. Anatomopathologically, late congenital syphilis is characterized by chronic inflammatory, gummous, and degenerative lesions of organs and systems with vascular changes. These lesions resemble the changes observed in the tertiary period of acquired syphilis and are sometimes difficult to distinguish from them. Late congenital syphilis, just like early syphilis, can affect all organs and systems of the child's organism, and the manifestations can be divided into 2 groups. To the first group belong phenomena arising in early childhood, the so-called stigmata, which serve as an important aid for recognizing late congenital syphilis (e.g., scars at the corners of the mouth, nasal deformity). To the 2nd group belong signs appearing at a later age. The skin is affected specifically in late congenital syphilis less often than in infancy, and the changes are more persistent and severe. Characteristic of this period are: 1) gummas, which are more frequently encountered on the extremities, having a generally benign course and sometimes bearing a great resemblance to scrofuloderma; the diagnosis is then decided by the Wassermann reaction or the beneficial effect of specific treatment; 2) tubercular syphilides of an ulcerating type, prone to serpigination, leaving characteristic scars with scalloped edges, white in the center and pigmented at the periphery, not uniformly deep everywhere. The nasal mucosa is not infrequently diseased in the form of atrophic catarrh and is sometimes accompanied by perforation of the nasal septum with nasal deformity, more markedly expressed than in early age. Gummous processes with breakdown are encountered on the soft palate, on the tonsils and around them, and not infrequently result in perforation of the soft palate, as well as the hard palate. Gummous infiltrates with a tendency to breakdown are also observed on the tongue. Lymph nodes in late congenital syphilis are changed particularly often in the cervical and submandibular regions; inguinal and axillary lymphadenitis are observed less often. These lesions not infrequently simulate tuberculous lymphadenitis. Specific lymphadenitides, as Meshchersky points out, can proceed without skin involvement, giving slowly developing cell tissue tumors; they can resemble scrofuloderma with subsequent softening, formation of fistulas, periadenitis (sometimes this form represents a hybrid syphilo-tuberculous glandular lesion); they can be accompanied by extensive ulcerations and represent gummous glands, softened and suppurating. This form not infrequently proceeds with splenomegaly and anemia. Bones are affected particularly often in late congenital syphilis (osteomyelitis and osteoperiostitis). In addition, osteosclerosis is noted on the long tubular bones. The tibia is affected more often than others, taking on a saber-like shape pathognomonic for late congenital syphilis. The same shape is observed on the bones of the forearm. Gummous processes with the formation of fistulas are also noted on the bones of the skull. As in early congenital syphilis, multiple bone involvement is encountered here, and simultaneously with phenomena of new growth (periostitis and osteosclerosis), roentgenograms also reveal phenomena of destruction (gummas with sequestration). Some authors have described syphilitic Pott's disease simulating tuberculosis, as well as Paget's disease, in connection with late congenital syphilis (see Osteitis deformans). Among bone dystrophies, dystrophies of the skull should be noted: the Olympic forehead, a skull with prominent frontal and parietal tuberosities, and a puppis-like (clinocephalic/natiform) skull. In connection with late congenital syphilis, congenital absence of the xiphoid process of the sternum has also been described (Landa, Glavche Institute). Joints. A characteristic form for late congenital syphilis is painless fluid accumulation in both knee joints. The joints swell slowly, and movements are not hindered. The diagnosis is made on the basis of the Wassermann reaction and other specific lesions. In addition, massive joint swellings are also observed, especially of the knees, resembling tumor albus and accompanied by bone thickenings; roentgenograms sometimes reveal phenomena of osteosclerosis and osteoporosis. The small degree of pain and insignificant impairment of joint function speak in favor of syphilis. Among joint dystrophies, congenital hip dislocation has been described (Meshchersky). Dystrophies of the teeth are especially frequent and varied; Hutchinson's teeth are particularly characteristic (see Hutchinson's triad). Among other dental dystrophies, atrophy of the permanent molars should be noted, as well as cup-shaped atrophy of the first permanent molar. In addition, teeth in late congenital syphilis change their shape, have an atypical appearance, are distinguished by small size, and sometimes excessive size; the absence of one or both upper lateral incisors has also been described, as well as anomalies in tooth arrangement. The eye is affected more frequently than other organs in late congenital syphilis, with parenchymatous keratitis occupying the first place, which is pathognomonic for this disease and was included by Hutchinson in his triad (see Hutchinson's triad). Among other eye diseases on the basis of congenital syphilis, one can note iritis, iridocyclitis, chorioretinitis, optic nerve atrophy in connection with syphilis of the central nervous system, strabismus, congenital nystagmus, and dacryocystitis (Odintsov), arising on the basis of specific bone lesions. The ear is affected in late congenital syphilis less often than the eye, but disease of the labyrinth and auditory nerve is just as typical as parenchymatous keratitis (see Hutchinson's triad). Hutchinson's triad is observed in its entirety relatively rarely. Most frequently, as Meshchersky points out, deafness drops out of the triad. Deafness carries a poor prognosis, because it is almost unresponsive to specific therapy. Late syphilitic lesions of the larynx are encountered not infrequently and result in the formation of small tumors, especially on the epiglottis; perichondritis with destruction of individual parts of the larynx and edema of the vocal cords is sometimes noted. Clinically, a hoarse voice and difficult breathing are observed. Lung disease is observed rarely and is difficult to diagnose. Pulmonary and pleural fibrosis on the basis of syphilis in children has been described by Hutinel. Heart diseases in children with late congenital syphilis have been described in the form of valvular insufficiency, myocarditis, and endocarditis. There are also indications that congenital narrowness of the aorta, stenosis of the mitral valve, and stenosis of the pulmonary artery are characteristic of late congenital syphilis. Liver and spleen involvement are observed in late congenital syphilis as a syndrome associated with Banti's disease (see Banti's disease). Specific cirrhosis of the liver is also encountered, and in severe cases, nodular swellings are observed, indicating the presence of limited hepatitis and gummas. Kidney disease in late congenital syphilis is observed rarely and yields no characteristic signs. Hutinel points to the connection existing between renal aplasia and late congenital syphilis. Orthostatic albuminuria is sometimes noted in such children. Paroxysmal hemoglobinuria observed with this disease responds well to specific therapy (Meshchersky, Rahr). The blood in late congenital syphilis presents phenomena of secondary anemia. Polyglobuly, improving under the influence of salvarsan treatment, is also described (Shulman) as a symptom of late congenital syphilis. Disease of the testes and ovaries is observed rarely. Infantilism, more frequent in girls, which is characterized by delayed menstruation and slow sexual development, is placed in some connection with genital gland disease in late congenital syphilis. Late congenital syphilis relatively frequently causes disease of the nervous system, which sometimes remains the sole sign of the disease and is characterized by the persistence of symptoms and the protracted course. As precursors of severe brain diseases, Fournier points to headaches, as well as generalized convulsions observed at the beginning of the disease. Jacksonian epilepsy, characterized by convulsive seizures of one extremity or more rarely half of the face, indicates a local cortical disease (Fischl, Erlenmeyer) based on a gummous process or limited meningitis. Mental retardation and mild forms of dementia are also noted in children with late congenital syphilis. According to E. Müller's data, among children with congenital tardy syphilis, 1/3 have normal psychics, 1/3 weakened, and 1/3 show a significant lowering of intellect. Disease of the brain and spinal cord in late congenital syphilis produces phenomena of hemiplegia (Marie), and not infrequently spastic paralysis or Little's disease (Babonneix, Tenissier) (see Little's disease / Infantile cerebral paralysis). Tabes dorsalis in children with late congenital syphilis produces mainly ocular symptoms, optic nerve atrophy, and the Argyll Robertson pupil in mildly expressed disorders of the motor and sensory spheres.
Romberg's symptom is usually absent in children. Urinary incontinence is frequently noted. Progressive paralysis in children can be observed as early as five years of age (Zappert) and is characterized by dementia (disorders of memory, speech, and delusional ideas), ocular symptoms (pupillary rigidity, optic atrophy), and later by paralysis and seizures, which are frequently the cause of death. Diseases of the endocrine glands in children, as indicated by a number of authors, in some cases are also based on late congenital syphilis. It should not be overlooked, however, that a number of dystrophies affecting individual organs and systems, noted in connection with congenital syphilis, may occur: 1) on the basis of other chronic infections, such as tuberculosis, alcoholism, and lead poisoning; 2) may be observed in families where there are no indications of syphilis or the aforementioned infections. However, according to statistics, the largest percentage of dystrophies falls on children with congenital syphilis. Fournier divides dystrophies into 6 categories: dystrophies of the: 1) skull, 2) teeth, 3) eyes, 4) nervous system, 5) endocrine glands, and 6) rachitic properties. These dystrophies must be taken into account alongside other phenomena. Diagnosis of congenital syphilis. Congenital syphilis does not always present obvious specific changes in organs and systems, and therefore its recognition can present great difficulties even for an experienced physician. Meanwhile, early diagnosis is of great importance not only for the child, but also for the mother, who often does not suspect the existence of this disease in herself. Obvious symptoms of early congenital syphilis include rashes, specific rhinitis, a large dense liver and spleen (Parrot's disease). Supplementary data for diagnosis are a suspicious obstetric history (late miscarriages, premature births, stillbirths), data from the birth period (large placenta, hydramnios), as well as signs concerning the child itself: a) lack of appetite, b) slow weight gain or its arrest during breastfeeding and in the absence of gastrointestinal disorders, c) presence of epitrochlear glands, d) presence of a dense enlarged testicle, sometimes simultaneously with hydrocele of the testicle, unilateral, and long-persisting, e) a whole range of phenomena from the nervous system indicated above. The combination of several of the listed signs makes it possible to make a diagnosis and begin treatment. For the diagnosis of late congenital syphilis, stigmas remaining from congenital syphilis suffered at an early age are also of great importance among other signs: 1) scars at the corners of the mouth, 2) nasal deformity, 3) ocular phenomena (parenchymatous keratitis), 4) saber shins, 5) dystrophies of the teeth and skull, 6) Hutchinson's triad, 7) serpiginous and deep skin ulcers, etc. In the diagnosis of congenital syphilis, of enormous importance are furthermore: 1) laboratory studies - Wassermann reaction, blood sedimentation reactions, morphological blood picture (anemia) and its physicochemical properties, as well as examination of the cerebrospinal fluid; 2) examination of the skeletal system with X-rays (see above); 3) examination of the eyes and fundus. The prognosis of congenital syphilis, both early and late, depends on a number of conditions. The prognosis is significantly worsened by: 1) recent syphilis in the parents, 2) their poor treatment before conception of the child and inadequate treatment of the mother during pregnancy, 3) early appearance of signs of syphilis in the child, as well as their intensity (especially manifestations of visceral and neural syphilis). Breastfeeding and hygienic living conditions significantly improve the prognosis. Early and energetic treatment of the syphilitic child, both with and without manifestations, is of great importance for the prognosis. Prophylaxis. The reduction of congenital syphilis in the USSR in recent years is closely connected with the reduction of syphilis among adults; however, the percentage decrease in contagious forms of congenital syphilis, according to Volpyan (Moscow), significantly lags behind compared to adult syphilis. This is explained by the circumstance that latent syphilitics, poorly treated, often give birth to sick children with obvious signs of syphilis. Thus, prophylaxis of congenital syphilis should be reduced to: 1. Energetic systematic treatment of future parents before child conception. Women with syphilis should be treated even in the absence of clinical symptoms. 2. Early detection of syphilis in pregnant women and their early and energetic treatment (with salvarsan preparations + Bi) (2-3 courses), which guarantees the birth of a healthy child. Work on detecting syphilis in pregnant women is carried out in women's consultation clinics. 3. Early and energetic treatment of children, not only with manifestations but also without visible signs, born to poorly treated syphilitics, especially if the mother did not take courses during pregnancy. Only early and energetic treatment (with preparations of salvarsan + Bi + Hg) protects children from manifestations of late congenital syphilis and protects the collective (nurseries, orphanages) where the child of syphilitic parents ends up from infection. 4. And finally, it is necessary to strictly monitor the implementation of the decree on compulsory treatment.
Treatment. In the treatment of both infants and older children, neosalvarsan (novarsenol), bioquinol, mercury, and iodine are used, with the best results given by combined courses. Each course consists of 10-12 novarsenol infusions and 12-15-20 injections of bioquinol or mercury. Novarsenol is administered to infants at the rate of 0.01-0.03 per 1 kg of the child's weight, and the dosage is gradually increased. For children after 3 years of age, infusions begin at 0.1 and are brought up to 0.3; after 12 years, the single dose can be brought to 0.4 if novarsenol is well tolerated. Infusions are made into the head vein, elbow, and jugular veins. This method of administration is the best for children in view of its painless nature, but is sometimes difficult in mass treatment. Then one has to resort, especially in infants, to intramuscular and suprafascial administrations of novarsenol. Intervals between infusions are 4 days. Bioquinol is injected into the muscles of the buttocks at the rate of 0.01, and mercury at 0.001 per 1 kg of the child's weight. For children after 3 years of age, bioquinol injections are given at 1.0, 15-20 times. During treatment, the urine must be strictly monitored, examining it at least once every ten days, since bismuth and mercury preparations frequently give renal complications, most often in the form of albuminuria. Bismuth, like mercury, is administered to children every other day. Mercury is administered intramuscularly as an injection of a 1% sublimate solution or 1% Hydrarg. cyanati, since internal intake and rubbing are methods of low energy. Complications observed under the influence of treatment boil down to the appearance of protein in the urine, a slight increase in temperature, and gastrointestinal disorders. All these complications usually resolve within a few days and interfere little with treatment. Contraindications in children to novarsenol infusions are acute infectious diseases, frequent stools with admixture of blood and mucus; for kidney disease, it is recommended to use mercury preparations or small doses of novarsenol. A child with congenital syphilis receives from 4 to 6 of the above-mentioned combined courses (10-12 novarsenol + 12-15-20 Bi or Hg) depending on the intensity of manifestations and the course of the process. In the intervals between courses, children after 3 years of age can receive iodine preparations. Novarsenol can sometimes be replaced by osarsol, giving it in combination with bioquinol or mercury. Under the influence of the above treatment, skin manifestations disappear relatively quickly; where changes in internal organs are absent, the general condition rapidly improves, weight increases, the color of the skin becomes less pale; a hoarse voice, absence of voice, and stenosis phenomena also subside after 2-3 novarsenol infusions. Syphilitic rhinitis is slow and stubborn in responding to treatment, but here too, by the end of the course, the discharge decreases, and snorting breathing disappears sometimes only after 2 courses of treatment. Just as slowly as rhinitis, the size of the liver and spleen decreases in syphilis of the internal organs, and such children develop poorly and their weight increases only by the end of the first course or after its completion. Lesions of the skeletal system, severe gummatous processes, and erosion of joint ends respond well to treatment. Diseases of the nervous system also show improvement by the end of the first course, unless there are deep destructions in the brain tissue. The blood composition and its physical properties, which give severe changes in congenital syphilis, improve in most cases under the influence of treatment. M. Rayit.
Related articles
Cite this page
“Syphilis.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/syphilis/