Staphyloma
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928-1936 Soviet Great Medical Encyclopedia details staphyloma, the pathological protrusion of the cornea or sclera of the eye. It covers the classification into total and partial forms, clinical manifestations, complications such as secondary glaucoma and infection, and various historical surgical and conservative treatment methods.
Encyclopedia article (1928–1936)
STAPHYLOMA (from Greek staphyle - grape), in ophthalmology, the so-called protrusion of the cornea and sclera.
Staphyloma of the cornea is formed after perforating corneal ulcers from its remnants and prolapsed iris. In the process of healing of the ulcerated cornea in the anterior section of the eye, scar tissue arises, which possesses high compliance and stretches and protrudes under the influence of increased intraocular pressure. Total staphyloma (staphyloma corneae totale) is distinguished when the protrusion occupies the entire region of the cornea (Fig. 1), and partial staphyloma when the protrusion is limited to only one area of the cornea (staphyloma corneae partiale) (Fig. 2). In complete staphyloma, one speaks of a cicatricial sac filled with aqueous humor and occupying the anterior section of the eye. The inner surface of this sac is almost always lined with an atrophied iris (Fig. 3). Sometimes the cavity of the sac is divided by adhesions of the iris with the lens into a series of separate cavities, and the surface of the staphyloma becomes nodular due to the simultaneous development of new protrusions, thus resulting in a lobular staphyloma (staphyloma racemosum). A long-standing staphyloma becomes covered with fairly large blood vessels; yellow spots - hyaline-degenerated areas and white calcified foci - appear on its surface. Corneal staphyloma acquires either a conical shape (staphyloma conicum) or a hemispherical shape (st. sphericum). Depending on the thickness of the staphyloma wall, its color changes from white and slate-gray to bluish-black. Staphyloma of a bluish-black color bears a resemblance to a grape, hence the name. Frequently, the staphyloma projects from the palpebral fissure to such an extent that closure of the eyelids becomes impossible. In this case, the surface of the staphyloma becomes dry and uneven, its apex acquires a leathery appearance, and ulcers may appear on it.

Figure 1. Complete anterior staphyloma.
Figure 2. Partial staphyloma.
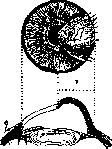
Figure 3. Total staphyloma of the cornea: 1 - conjunctiva; 2 - sclera; 3 - ciliary body; 4 - ciliary processes; 5 - zonule of Zinn; 6 - conjunctiva; 7 - staphyloma.
Figure A. Total staphyloma of the cornea: 1 - conjunctiva; 2 - sclera; 3 - ciliary body; 4 - ciliary processes; 5 - zonule of Zinn.

Staphyloma leads to a significant decrease in visual acuity, sometimes only to light perception, and the latter is also often lost. In the process of staphyloma formation, closure of the angle of the anterior chamber occurs, which causes an increase in intraocular pressure, glaucomatous pains, an increase in protrusion, and thinning of the walls. The latter may burst, the staphyloma collapses, and then fills with fluid again. The thin walls of the staphyloma frequently serve as a gateway for intraocular infection, the outcome of which is shrunken eyes. Partial staphyloma develops from partial prolapses of the iris in the absence of increased intraocular pressure. In this case, there is a sharply demarcated whitish-gray or slate-gray hemispherical elevation in the peripheral zone of the cornea. Visual acuity is reduced due to significant astigmatism resulting from the curvature of the part of the cornea adjacent to the staphyloma. Partial staphyloma can also serve as a gateway for intraocular infection, since the epithelium covering it is thinned and easily desquamated. The formation of a staphyloma can be represented as follows. After the perforation of an ulcer, prolapse of the iris occurs, which is also involved in the inflammatory process and covered with fibrinous exudate. Obliteration of the pupil occurs, and the prolapsed iris adheres to the edges of the ulcerated cornea. Dissociation of the anterior and posterior chambers ensues. The former gradually decreases and completely disappears due to the pressing of the iris against the angle of the anterior chamber, which already entails the closure of the outflow pathways of the intraocular fluid. At this time, the posterior chamber expands significantly. At the beginning of the development of the staphyloma, its compliant walls stretch, thereby compensating for the increase in intraocular pressure. Later, when the prolapsed iris with corneal remnants turns into dense scar tissue, signs of glaucoma appear with all the consequences characteristic of it: excavation and atrophy of the optic nerve head. Bearing in mind the occurrence of staphyloma after perforation of corneal ulcers and iris prolapse, which is especially facilitated by an increase in intraocular pressure, preventive measures should be directed at eliminating the causes of increased intraocular pressure. Usually, when applying atropine for corneal ulcers, the state of intraocular pressure and the depth of the ulcer are monitored, and with an increase in the former and the tendency of the ulcer to perforate, atropine is canceled and replaced with physostigmine. The patient is prescribed rest, timely bowel evacuation is monitored, and avoiding any physical exertion is recommended. A moderately pressure bandage is applied to the eye. If, despite these measures, there is a tendency on the part of the cornea and iris to form a staphyloma, a wide iridectomy is indicated. However, performing the latter is quite difficult due to severe inflammation of the conjunctiva and significant flattening of the anterior chamber. Of the surgical methods for treating staphyloma, the simplest is the removal of the entire protrusion (staphylotomy); Beer after such excision of the staphyloma did not apply sutures, removed the lens, and left the exposed vitreous body to independent cicatrization. This method requires strict postoperative rest, prolonged use of a pressure bandage, and does not guarantee against recurrence and intraocular infection (Fig. 4).
Figure 4. Staphylotomy according to Beer.
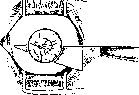
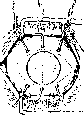
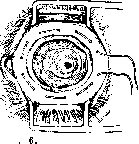
Figure 5. Staphylotomy according to Critchett. Critchett proposed his own method of staphyloma removal. It consists in excising the staphyloma with the placement of sutures on the scleral wound: first, 4-5 needles with threads are passed into the base of staphyloma from top to bottom, and the needles are not withdrawn, but remain under the staphyloma, then the latter is removed, the lens is also removed, the needles are pulled out, and each thread is tied in a knot, whereby the scleral wound is closed (Fig. 5). Critchett's method does not guarantee against relapses, and passing sutures through the ciliary body leads to its inflammation and even to the occurrence of sympathetic ophthalmia. With the aim of eliminating the possibility of sympathetic ophthalmia, de Wecker modified Critchett's method: he dissected the conjunctiva around the cornea, applied a purse-string suture to it, which was tightened after excising the staphyloma (Fig. 6). Kuhnt recommends closing the gaping wound after staphylotomy with a flap of fascia lata. Elschnig with the same purpose transplants lip mucosa. Kankrov recommends his keratoplastic method of staphylotomy. Its essence boils down to the fact that the wound gaping after excision of the staphyloma is closed at the expense of a flap from the densest part of the staphyloma. This flap is...
PlIC
P. Arkhangelsky
Staphylotomy according to Wüsker is performed in such a way that it remains in one place in connection with the limbus of the cornea, and in three areas it is sutured with three sutures passing through it and brought out through the scleral attachments of the three rectus muscles and the scleral conjunctiva. The previously dissected conjunctiva is drawn together with a purse-string suture so that it covers the edges of the flap. The above-mentioned surgical methods for treating S. are not always accompanied by the desired success, and sometimes one has to face the risk of recurrence, panophthalmitis, or sympathetic ophthalmia. This compels many to offer patients enucleation or evisceration of the eyeball instead of staphylotomy. However, patients often refuse to undergo such radical operations. Both of these together have been the reason for proposing a method of bloodless treatment of anterior S. by injecting 10% sodium chloride into the vitreous body. Usually, a day after the injection, in the absence of any irritation, a significant decrease in intraocular pressure is observed, and after several days, flattening of the S. occurs (Koyanagi, Solovyev).-Partial S. can be excised and Kalt sutures applied to the corneal wound, which capture only part of the thickness of the cornea.-According to Berberov, complete S. and corneal scars are found: after smallpox-in 49%, ophthalmoblennorrhea-in 48%, corneal diseases-in 33%, and trachoma-in 31% of all cases of bilateral blindness on the basis of the indicated diseases (each separately). According to Krivetsky, scar changes and staphyloma are observed in 23.99% of all blind in both eyes. The prolonged existence of S. of the cornea in combination with increased intraocular pressure leads to the appearance of protrusions of the sclera, called scleral ectasias (staphyloma sclerae anticum). The thinned wall of the sclera becomes translucent when strong illumination is directed at the S. According to the location of S. of the sclera, they are distinguished: S. limbal (s. intercalate), located in the circumference of the cornea; S. ciliary (s. ciliare), developing in the area of the ciliary body, and S. equatorial (s. aequatoriale), forming in the area of the equator of the eyeball. The described S. of the sclera belong to the so-called secondary scleral ectasias and develop in the anterior part of the sclera in connection with previous inflammation of it (scleritis) and increased intraocular pressure.-Primary scleral ectasias arise without increased intraocular pressure and previous inflammation. They are localized in the posterior part of the sclera. An example of such a posterior S. is staphyloma verum, which occurs in high degrees of myopia and is visible on ophthalmoscopy. Two forms of staphyloma verum are distinguished: 1. On the nasal side of the optic nerve head, a sharply defined arcuate line, concentric with respect to the head, is visible on ophthalmoscopy. This line sharply limits the area of ectasia, the presence of which is proven: a) by the bending of vessels at the arcuate line, b) by the difference in refraction, with myopia being several diopters higher on the ectatic area, and c) by the lighter color of the ectatic area with translucency of the choroidal vessels. 2. In the second form, the line limiting the

Figure 7. Keratoglobus

Figure 8. Keratoconus.
area of ectasia closes into a complete circle surrounding the optic nerve head and the area of the yellow spot. If staphyloma verum is a sharply limited ectasia, then the so-called staphyloma posticum is an expression of uniform stretching of the entire posterior part of the sclera (see Myopia). The above-mentioned S. of the cornea are as a rule accompanied by more or less significant clouding of it. However, there is a group of transparent S. of the cornea (staphyloma pellucidum), in which the cornea protrudes sharply forward, entirely or partially preserving transparency. To this group should be assigned two classic forms: 1) conical enlargement of the cornea (keratoconus) and 2) spherical protrusion of it (keratoglobus) (fig. 7 and 8). In keratoconus, the cornea takes the form of a blunt cone, on the apex of which there is usually a cloud-like opacity. Keratoconus is an acquired condition, developing slowly between the ages of 20 and 30 years, mostly in women and in both eyes. Some believe that keratoconus results from congenital thinness of the central parts of the cornea. Due to this defect, it easily stretches under the influence of even normal intraocular pressure. Some associate the development of keratoconus with disorders of the internal secretion organs (thyroid, pituitary gland, ovary).-In the early stages of the disease, diagnosis is difficult, and a change in the shape of the cornea can be suspected by the presence of astigmatism, the degree and direction of the axes of which change. Of course, the existing irregular myopic astigmatism in this case sharply reduces visual acuity. In keratoconus, the prognosis is unfavorable both in terms of working capacity and in terms of the possibility of complications - corneal ulceration. Treatment of keratoconus is conservative-organotherapy aimed at stopping the process, and surgical-cauterization of the center of the cornea with a paculum, the task of which is to form a dense opacity preventing further stretching. Transverse cauterization of the apex of the keratoconus or its excision followed by covering with the conjunctiva is also recommended. Improvement of vision is achieved by directly applying so-called contact glasses to the cornea, the posterior surface of which has a concavity corresponding to the conical shape of the cornea. The anterior surface of these glasses is provided with a regular spherical curvature. The space between the cornea and the glass is filled with tears, as a result of which a homogeneous medium with a proper refracting surface is obtained. For the purpose of improving vision in keratoconus, a hydriasiscope is also used (see). Keratoglobus develops with congenital increased intraocular pressure. In it, along with an increase in the diameter of the cornea, an increase of the entire eye is observed-hydrophthalmus, buphthalmus; there are also other symptoms of glaucoma: high intraocular pressure, glaucomatous excavation. The anterior chamber is enlarged, the cornea is cloudy, and on it there are striae-like opacities as a result of ruptures of Descemet's membrane. Increased intraocular pressure ultimately leads to loss of vision. Treatment is little reliable: medicinal remedies are almost ineffective, and operations in the best case only slow down the process.--Keratoglobus must be distinguished from a congenitally enlarged cornea (megalo-cornea), in which no increase in intraocular pressure is observed, and such a condition should be considered as a congenital anomaly of the cornea. Megalocornea is inherited, like hemophilia and color blindness. Partial or complete protrusion of the cornea is observed on the basis of a long-existing trachomatous pannus (keratoectasia ex pannu). The scarred cornea loses resistance even to normal intraocular pressure, as a result of which such keratoectasias develop, accompanied by a severe violation of vision.
Related articles
Mentioned in
Cite this page
“Staphyloma.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/staphyloma/