Soft Chancre
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928-1936 Great Medical Encyclopedia discusses soft chancre (chancroid), detailing its history, the morphology and staining characteristics of its causative agent (Streptobacillus ducreyi), and methods of cultivation.
Encyclopedia article (1928–1936)
SOFT CHANCRE, venereal ulcer (ulcus molle, ulcus venereum), a venereal disease caused by the Ducrey-Unna streptobacillus, transmitted chiefly by sexual contact, easily inoculable from place to place and from person to person; soft chancre has been known since antiquity. Buboes are mentioned by Hippocrates; Galen speaks of them in great detail; he distinguishes hard and soft ulcers and requires different therapy for them; in the Middle Ages, soft chancre was regarded by many physicians as a disease sui generis, but the severe epidemic of syphilis that spread across Europe in the 15th and 16th centuries brought great confusion to the minds of physicians; the subtle distinctions between hard and soft chancre were erased; with incredible rapidity (Vella; 1508), the idea of the identity of hard and soft chancre took root; having the most authoritative followers (Hunter, Ricord), this theory reigned supreme until the middle of the 19th century, when, thanks to the works of Bassereau and others, the distinction between these diseases was finally established. The causative agent of soft chancre (Streptobacillus Ducrey, Bac. Ducrey-Unna-Krefting) was first described by Ducrey in pus (1889) and shortly thereafter by Unna in the tissue of soft chancre. The causative agent of soft chancre was obtained in pure culture by the Russian researchers Istomanov and Askipyants (1897) and independently of them almost simultaneously by Lenglet in France. The m o r p h o l o g y of this microbe, despite its considerable polymorphism, is very characteristic and depends on the environment (pus, tissue, artificial medium); it is well revealed by staining. Ducrey's streptobacillus takes up (though not easily) basic aniline dyes (methylene blue, fuchsin, etc.); it is decolorized by Gram's method. In its classical form, the bacillus of Ducrey is found in pieces of tissue easily obtained with a platinum spatula from beneath the undermined edge of the ulcer (see separate plate, fig. 1); in a less characteristic form, the microbe is observed in pus (extracellularly and intracellularly) (see separate plate, fig. 2). The indicated initial material is carefully smeared on a glass slide with a loop (better still, with the edge of a glass slide), dried in air or in a thermostat, and fixed for 1-2 minutes with formalin vapors or by careful triple flaming. For practical purposes, to reveal morphological properties, the preparation is stained with diluted Ziehl's carbol-fuchsin (1 part stain to 4 parts distilled water) with heating (until the first vapors appear) and then 2-3 minutes in the cold; for differential distinction from other similar microbes, Gram staining is performed (additional staining with heating according to Finkelstein). Finkelstein generally recommends staining Ducrey's bacillus with heating, since this method ensures the revelation of the characteristic bipolarity of Ducrey's bacillus and hard-to-stain degenerative forms (swelling, disintegration). More complex methods have also been proposed (methyl green-pyronin according to Pappenheim-Unna: bacteria reddish, pus cells greenish-blue). In preparations with the indicated stains, one can see various forms of Ducrey's bacillus, representing various stages of its development and degeneration: 1) Rods of various lengths (1-2 µ), located singly, in pairs, in short or long chains, inside (granulocytes, monocytes) or outside cells; oval and navicular forms with clear bipolarity are also encountered. 2) Classical long (ten to fifteen or more segments) streptobacilli arranged in parallel rows (found chiefly in tissue). Ducrey's bacilli have the same appearance in pure culture (see separate table, fig. 3), which has been traced in so-called imprint preparations (Klatschpräparat). In liquid media, Ducrey's bacilli are often elongated into long, non-segmented threads. The method of cultivating Ducrey's bacillus is not yet fully understood; obtaining its pure culture succeeds far from uniformly depending on the methods: most researchers (Moore, Reenstierna) note 5-8% success; individual authors (Saelhof, Deibert) report higher figures (65-85%). In media for growing Ducrey's bacillus, the presence of Hb (hemophile) is mandatory. The most commonly used media are: 1) Blood medium according to Besançon-Reenstierna, for the preparation of which two parts of 3% agar plus one part of defibrinated rabbit water are heated for five minutes in a water bath, poured into test tubes in 5-10 cm3 portions, and slanted; it is necessary to put rubber caps on the test tubes to protect against drying.
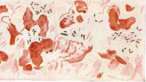
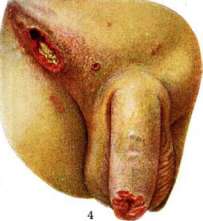




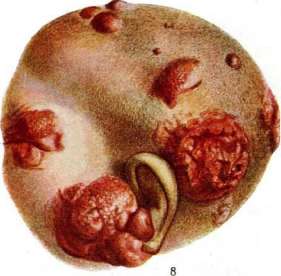
.,- 1) Itto's vaccine from cultures of the soft chancre bacillus: preparation, diluted in alkaline water. Fig. 2. Forms of soft chancre from Ito's atlas: superficial form (a), follicular form (b), ulcus serpiginosum (c). Fig. 3. Smear from culture of the Ducrey-Unna streptobacillus on a blood-agar slant. Fig. 4. Soft chancre ulcers and chancroidal buboes. Fig. 5. Smear of soft chancre on prepuce. Fig. 6. Soft chancre ulcer in the region of the frenulum. Fig. 7. Positive intradermal reaction to soft chancre after injection of Ito's vaccine. Fig. 8. Suprarenal gland: cortex (a)--yellow color, medullar substance (b)--pale gray, in the center are visible blood vessels (c). Figs. 1, 3 - according to Talszczewsky; figs. 2, 4, 6 and 7 - according to Reenstierna). (See Morbus febrilis, Soft chancre, Bibliography). 2) Itto medium with defibrinated sheep blood. 3) Teinat's medium: 1 part rabbit blood and 3 parts agar. 4) Coagulated slanted blood: sheep (Durant), guinea pig (Himmel). 5) Nicolle's medium: agar, rabbit blood, and one percent starch. Most authors note that the growth of the Ducrey bacillus occurs best on media containing blood of young animals. Frey points out the growth-enhancing effect of adding glycerin (one percent), gelatin (one to two per thousand). The active acidity of the medium (pH) ranges from 7.2 to 7.6. A certain humidity is extremely important; temperature about 37°; it develops better in the presence of O2, but relative anaerobiosis is permissible (Frey, Lipinsky); it does not form a true toxin; an endotoxin has been proven; a weak hemolysin has been found in some cultures (Frey, Brahms). Colonies of the Ducrey bacillus (on agar medium) grow within 24-48 hours; they are small, round (diameter 1-2 mm), with smooth edges, whitish-gray (and sometimes brownish). The consistency of the bacterial deposit is mucous-viscous due to the presence of a mucus-like substance (substance glacieuse Lenglet); flocculent formations appear in liquid media. The Ducrey bacillus does not show active motility. The viability of cultures is very varied: the first generations often die off quickly, but after making five to six passages on artificial media, the Ducrey bacillus gets accustomed to the medium and can then be preserved with regular (every 1-2 days) subcultures for months, and according to some authors (Frey, Reenstierna)--even years. The resistance of cultures to disinfecting substances (lysol, sublimate, carbolic acid) in ordinary solutions is insignificant, death occurs in a few minutes; temperature resistance is also not great: at 50° sterilization occurs in 5 minutes, at 42°--in 1-2 hours. The method of cultivating the Ducrey bacillus to the present time cannot be considered as having practical significance.--Of the numerous proposed methods for isolating the microbe in pure form, the most practical one seems to be the two-stage method: primary inoculation onto a semi-liquid blood medium (Durant, Himmel, Davis), bactericidal for accompanying competitor microbes, and then subculturing onto a solid agar medium. By this method, some authors (Brahms, Zelghof) discovered Ducrey bacilli in healthy people, i.e., the question of bacillus-carrying was raised; the latter, as is known, was first discovered in apparently healthy women by Brook. In connection with bacillus-carrying in healthy people, differential recognition of microbes morphologically similar to the Ducrey bacillus acquires topical significance; among the latter are known: 1) Pfeiffer's urethral streptobacillus (Strepto-bac. urethrae Pfeifferi), a Gram-positive microbe, by which it differs from the Gram-negative Ducrey streptobacillus; this urethra saprophyte is often found in the navicular fossa of the urethra in men. 2) The microbe of Lehmann and Neumann, a Gram-positive streptobacillus found in the vagina. 3) Miyahara's streptobacillus (Miyahara), Gram-negative, never forms long chains. 4) Frey's microbe, isolated from a case of gangrenous ulcer; it is much more delicate than the Ducrey bacillus, monomorphic, does not show parallel arrangement. The last two microbes, as Gram-negative, most resemble the Ducrey bacillus and therefore of course are of practical interest; in general, they are still little studied. Inoculation of animals. According to data from both old authors (before the discovery of the Ducrey bacillus) (Auzias-Turenne, Thibierge, Welz) and newer researchers who used pure cultures of the Ducrey bacillus for inoculations, monkeys (macaques) contract a mild form of soft chancre, which proceeds quickly (1-2 weeks) and histologically (superficial process, Reenstierna) differs from the human soft ulcer. In macaques, the entire skin is susceptible, but inoculation is easier and sharper on the upper eyelids; mucous membranes are usually not infected. Among other animals, a rudimentary form of soft ulcers in rabbits was obtained by Fontana (inoculation with corneal pus), Reenstierna (inoculation of pure culture on the scrotal skin), Terebinsky and others. A number of authors reported positive inoculations in cats.--A vaccine from cultures of the Ducrey bacillus is prepared either in the usual way (Ito), from a 24-hour agar culture in the form of an emulsion in physiological NaCl solution, heated to 60° for two hours, or according to Reenstierna; the latter, instead of heating, treats the culture emulsion with 0.5% carbolic acid (per liter) for two weeks. Such a vaccine can be used both for vaccinodiagnosis (intracutaneous reaction) and for vaccinotherapy (see below).
Yu. Finkelstein. Clinical aspects of soft chancre. For the introduction of the virus, damage to the skin covering is always necessary. Infection in the vast majority of cases occurs from a carrier of a similar ulcer. The presence of the Ducrey-Unna streptobacillus bacillus in the urethra, vulva, and cervical canal of clinically healthy women apparently gives the right to speak of bacillus carriers in soft chancre, although this question still requires additional studies (confirmation histologically, by cultures, subcultures) and clinical observations (confrontation--simultaneous examination of the soft chancre patient and the source of his infection). The incubation period is short: on the 3rd-4th day after infection, the ulcer is already fully formed. First (after 12-18 hours), a red spot appears at the site of virus introduction; by the beginning of the second day--a red pointed nodule in the center of the expanding spot; by the end of the second day, a small vesicle appears on the apex of the nodule, turning in a few hours into a pustule, the red spot becomes edematous; the pustule quickly bursts, exposing a small crater-like ulcer. This stage is easiest to observe in autoinoculations and especially CHANCRE
20 but upon inoculations. Upon microscopic examination of the soft chancre in the initial stages, phenomena of purulent infiltration are discovered both in the thickness of the epidermis and subepidermally; two abscesses arise as if connected with each other by strips of the same infiltrate (chancre en bouton de chemise Nicoll’fl); the surrounding skin tissue is hyperemic, with diffuse infiltrates, mainly of plasma cells; there are many streptobacilli lying in chains. The abscesses soon merge into one, and then ulcers arise. Over the course of the next 2–3 weeks, the ulcer continues to increase both in depth and in width, after which within a few days the ulcer cleanses and heals with a scar. At the height of its development, it possesses the following features: shape—initially usually round; then it can take on various outlines; size—from a pinhead to the palm of the hand and larger (in serpiginous forms of soft chancre); edges—perpendicular, undermined, eroded, jagged; the base is usually of soft consistency, quite deep, tuberous, covered with a yellowish-greasy coating and sharply painful upon touch; around the ulcer, an inflammatory halo is often visible, and in rare cases a second, eccentrically located yellowish rim (Petges). The soft chancre is only rarely solitary; usually, several ulcers are encountered, sometimes very many (autoinoculation, «daughter ulcers»), in various stages of development. In the ulcer period, from the central purulent-necrotic focus with streptobacilli and other bacteria, strands of infiltrates stretch in all directions, also with necrobiotic changes and streptobacilli; such a dispersal of infiltrates leads to the fact that the visible border of the soft chancre is not its actual border. Deep in the skin, a dense wall of plasma cells is discovered. Healing proceeds in the usual order with the formation of a small scar. The clinical picture of the soft chancre is influenced by a whole range of factors: the size of the ulcers, their depth, number, localization, combination with other infections (syphilis), arising complications, and treatment. When localized on the frenulum (its frequent rupture), in the coronal sulcus, along the edge of the prepuce [see separate table (p. 15–16), figures 5 and B] and along the ridge of the labia majora, the ulcers often acquire a certain, sometimes significant density; when localized around the anus (most commonly encountered in women), radially arranged ragades are formed that are very painful when walking and especially during defecation, and are difficult to treat with therapy. The lesion usually does not pass to the mucous membrane of the rectum (with the exception of isolated cases). When the soft chancre is localized along the edge of the prepuce, numerous cracks often arise. In women, the soft chancre is localized on the labia minora and majora and in the navicular fossa; lesions on the portio uteri and in the cervical canal have been described; localization on the vaginal mucosa is very rare. Extragenital chancres can be localized anywhere. They arise either primarily (prof. infection on the fingers of physicians and midwives, perverted sexual intercourse) or secondarily (much more often) by inoculation of the virus from the primary focus. Clinically, they do not differ in any way from genital chancres. They are rare: Sinani and Shapiro out of 2,858 cases of soft chancre discovered extragenital localization in 4 cases. In women, extragenital soft chancre is encountered more often than in men (according to Je’s statistics, 14 : 1). The following varieties of soft chancre can be noted: 1) Ulcus molle elevatum—with strong development of granulations of the base; more often than other forms of soft chancre, it is solitary. 2) Ulcus molle folliculare, ulcera mollia miliaria of Vörner—upon penetration of the virus into a sebaceous gland; most often in the coronal sulcus, along the edge of the prepuce and on the labia minora; narrow, deep ulcerations with a dense base. 3) Ulcus molle infundibuliforme—from the base of the ulcer deep into the subcutaneous or submucosal tissue stretches a dense cone; upon superficial palpation, it is easy to confuse with a hard chancre; most often localized in the coronal sulcus. 4) Ulcus molle impetiginosum—a rare form when the pustule dries into crusts. 5) Ulcus molle diphthericum (not to be confused with diphtheritic superinfection)—a pseudodiphtheritic coating on the base of the ulcer. 6) Ulcus molle serpiginosum—a sharp change in the course of the soft chancre; lasts months and years; extremely resistant to treatment; the ulcer scars from one edge and grows from the other, spreading to the scrotum, abdomen, thigh, and sharply changing the clinical picture of the soft chancre: the starting point in the overwhelming majority of cases is a chancroidal bubo; ulcus molle serpiginosum is a rare form usually encountered in irregularly treated patients; the indication of a longer incubation period (8 days) still needs verification; upon inoculations, an ordinary chancre (Reichel) or, more rarely, a serpiginous one (Luithlen) can be obtained; the cause of such a peculiar course of the soft chancre is unknown. 7) Ulcus molle gangraenosum*—an infrequent but very severe complication of the soft chancre, altering both its clinical and microscopic picture beyond recognition; usually begins suddenly, develops rapidly; in a few days, a grayish-black deep scab forms, leading to the loss of entire parts of tissue (prepuce, glans); sometimes the suppurative process goes beyond the fascia, exposing the cavernous bodies; hemorrhages are rare; in the vicinity, strongly expressed inflammatory phenomena (redness, swelling); the general condition of the organism is sharply disturbed (high t°, chills, general weakness, sometimes sepsis); more often encountered in slovenly, untreated individuals, in individuals with a long and narrow prepuce; rapidly complicates with phimosis with abundant foul-smelling discharge; the cause is apparently in fusospirillary symbiosis (in the sense of Plaut-Vincent angina). It is possible that hyperergy factors on the part of the organism itself are of significance here. * Under phagedenism, either a deep ulcerous process (ulc. m. gangraenosum) or a superficial, serpiginous one is described. Frei is therefore right when he proposes to completely abolish the term phagedenic chancre as introducing unclearness. 8) Ulcus mixtum, mixed chancre; sometimes elements of either a soft or a hard chancre predominate, sometimes it has the character of an indifferent ulcer. 9) Combination of soft chancre with diphtheria (confirmed by bacterioscopic examination and cultures); a rare form with the predominance of either a diphtheritic coating or the character of a soft chancre, mostly uncharacteristic, poorly granulating, difficult-to-treat ulcerations. Complications of soft chancre: 1) Phimosis, which in turn extremely adversely affects the course of the soft chancre (duration of the process, development of ulcus molle gangraenosum). 2) Perforation of the prepuce either with an ordinary soft chancre developing in depth, or, much more often, with ulcus molle gangraenosum. 3) Hemorrhages. 4) Lymphangitis either diffuse (in the vicinity and at the base of the ulcer, along the edge of phimosis) or in the form of dorsal and (rarely) lateral strands (bundles), on which small tumors (bubonulus) can develop, which then resolve or open and give deep ulcerations (chancre Nisbet); in women, neither lymphangitis nor bubonulus occurs. 5) Buboes—inflammation of regional lymph glands in response to the penetration into them from the primary focus of Ducrey-Unna streptobacilli; when the ulcer is localized on the genitals, the inguinal glands, especially those closest to the symphysis, become diseased, usually on one side, rarely on both [see separate table (p. 15–16), fig. 4]; buboes have also been observed with extragenital localization of the soft chancre and upon inoculations; the frequency of occurrence of buboes ranges from 8–10% (Wolf and Mulzer) to 28% (Sinani and Shapiro) and 35% (Miekley); the left inguinal glands become diseased more often (Miekley); in women, they arise significantly less often than in men; intense walking, lack of treatment, localization of ulcers on the frenulum, in the coronal sulcus, on the clitoris, phimosis, strong caustic agents can contribute to the formation of buboes. In soft chancre, buboes most often arise in the 3rd–4th week of the chancre's existence, sometimes in the first days of the disease and in rare cases already after the healing of the ulcers; bubo d'emblée without soft chancre, phlegmonous bubo arising many months after the healing of the soft chancre, and recurrent bubo are described. If the bubo arises with an infection mixed with syphilis, it is not acutely inflammatory, initially hard, then slowly suppurates, yields little pus, lasts a long time (mixed bubo of Diday — bubon mixte Diday); sometimes typical scleradenitis sets in only after the disappearance of inflammatory phenomena; the tissue surrounding the gland is rapidly involved in the process in soft chancre (periadenitis); rarely does the matter limit itself to a single gland (monoadenitis); a group of glands is usually captured (polyadenitis et polyperiadenitis). Outcome of buboes in soft chancre: a) a bubo, fluctuating or non-fluctuating, resolves without opening; b) a fluctuating bubo opens and heals with a scar; c) the edges of the opened bubo become chancroidal due to infection of them by Ducrey-Unna streptobacilli; d) proceeding as a cold abscess, the bubo gives long-non-healing fistulas (strumous bubo — an unfortunate term, since it is usually used for tubercular infection of the glands); the average duration of a bubo is 2–3 weeks with large fluctuations in one direction or the other.
Proper behavior of the patient and appropriate therapy, especially vaccine treatment, exert a favorable influence on the course, duration, and outcome of the bubo; some authors (Lennhoff, Frei) note a certain relationship between the bubo and soft chancre in the sense that ulcers heal faster when a bubo develops. 6) Finally, soft chancre can be complicated by eczema, erysipelas, acute condylomas, etc. Diagnosis and differential diagnosis. In typical cases, diagnosis is not difficult. In doubtful cases, inoculation is an excellent, though not always harmless (due to the possibility of serpiginous chancre, buboes, resistance to treatment) diagnostic method, to which one should resort only when clinical and microscopic findings do not resolve the question. After disinfecting the suspected site of inoculation with alcohol, ether, and then physiological solution, several strokes are made, into which pus from the marginal parts of the ulcer is transferred with the same lancet (chancre dermo-papillaire of Collet). The site of inoculation is covered with a watch glass. Fischer recommends making deep incisions and waiting for bleeding to stop (chancre dermique of Collet). Heteroinoculations, i.e., inoculation from person to person, must be abandoned due to the possibility of syphilis infection and the possibility of complications of the inoculated ulcer. Most important in practical terms and often most difficult is the differential diagnosis with syphilis, especially with hard and mixed chancre. Clinical and microscopic findings cannot always give a decisive answer. Then one has to resort to confrontation, inoculations, and sometimes waiting. The Wassermann reaction may (albeit rarely) give temporary positive fluctuations in complicated buboes and sometimes even in uncomplicated soft chancre lasting 14-26 days; therefore, repeated blood tests are necessary; but even repeatedly positive serological reactions do not always resolve the question of the nature of the ulcer (for example, soft chancre in a latent syphilitic with a positive serological reaction); even in undoubted soft chancre, repeated serological examinations for at least 6 months are necessary (this has now become an axiom) due to the possible delaying effect (elongation of the second incubation period) of soft chancre on the syphilitic infection. A single soft chancre can simulate a superficial gumma, but the latter has fewer reactive phenomena, less pain, and a denser consistency. Tuberculoid-ulcerative syphilids, especially if they are serpiginous, can, particularly when localized on female genitalia, also simulate soft chancre; to resolve the issue in such cases, repeated Wassermann reactions are necessary, and sometimes trial specific treatment. Ulcus vulvae acutum (Lipschütz) differs from soft chancre by larger ulcerations and more roll-like edges; examination usually reveals Bacillus crassus. In genital diphtheria (especially in women), the differential diagnosis is resolved by bacterioscopic examination and cultures. Herpes progenitalis, balanitis et vulvitis are easily distinguished from soft chancre due to their characteristic appearance and rapid course. Ulcus simplex Buschke or pseudo-ulcus venereum Jadassohn, with which soft chancre must sometimes also be differentiated, represent superficial erosions without any characteristic appearance and with a rapid course. Differential diagnosis with diabetic ulcers on the genitalia is facilitated by examination of urine and blood. With rapidly onset phimosis and gangrenous processes, it is mostly impossible to immediately establish the starting point (ulcus molle, durum, mixtum, balanopostitis). Buboes are easily distinguished from inguinal hernia, cryptorchidism, aneurysm of the femoral artery; banal buboes in non-venereal lesions run a less acute course, resolve more easily, pus-forming cocci are found in the pus, and the cuti-reaction with streptobacillary vaccine is negative. In typical cases, a soft chancre bubo is easily distinguished from painless syphilitic polyscieradenitis; in doubtful cases (mixed infection with syphilis, superinfection of syphilitic scleradenitis with Ducrey-Unna streptobacillus or other microorganisms) differential diagnosis is sometimes impossible (repeated serological reactions). In the 4th venereal disease of Nicholas-Favre (see Lymphogranulomatosis, Lymphogranulomatosis ing. subacuta) (there is a packet-like swelling of the inguinal and then iliac glands), the cuti-reaction is negative, and Frei's reaction is positive. If rare extragenital soft chancre buboes take a chronic course (fistulae), they may resemble tuberculous ones; in such cases, the general condition, the state of other organs, and a tuberculin test should be taken into account. Extremely interesting theoretically and important practically is the Ito-Reenstierna cuti-reaction with streptobacillary vaccine. In patients with soft chancre and especially with a bubo, after intradermal administration of 0.1 of the vaccine, an urticarial-erythematous spot is obtained with induration and a papular elevation in the center [see separate table (p. 15-16), Fig. 7], reaching maximum development in 24-48 hours and disappearing in 8-10 days; sometimes a slight increase in temperature, lymphangitis, and even lymphadenitis are noted; in healthy individuals who have not had soft chancre, and in persons with other diseases on the genitalia, a small redness appears which disappears after 2-3 days. This reaction is almost absolutely specific; it gives approximately 1% nonspecific results. It appears no earlier than the 6th-8th day after the appearance of soft chancre, gradually intensifies, is most pronounced in patients with a bubo, and lasts for many decades (up to 50 years in Reenstierna's case). It makes it possible in doubtful cases to diagnose soft chancre, without however excluding a mixed infection with syphilis, to differentiate vulgar and other buboes from soft chancre buboes, and to make a retrospective diagnosis of soft chancre many years after infection. It reveals the hypersensitivity that arises in soft chancre and lasts for a long time not only of the skin, but of the entire organism (more violent local and general reaction after intramuscular and especially intravenous administration of the vaccine than in healthy individuals and those who have not had soft chancre); it fundamentally changes the view of soft chancre as a local infection. Cultivation of the Ducrey-Unna streptobacillus and preparation of the vaccine encounter very great difficulties. However, Krichevsky and Sinelnikov (1926) proposed pus-vaccine for diagnostic purposes, i.e., pus of soft chancre buboes diluted 10 times with physiological solution and inactivated. The cuti-reaction with this pus-vaccine proved specific. The prognosis is usually favorable in typical uncomplicated forms of soft chancre. In ulcus molle serpiginosum, in view of the duration of the course, resistance to therapy, the possibility of intercurrent diseases, amyloid degeneration of organs, and in ulcus molle gangraenosum, the prognosis is poor. Phimosis and buboes prolong the course of soft chancre; buboes leave scars, can become the starting point of a serpiginous process, and therefore worsen the prognosis. The patient should be warned about possible complications and the possibility of mixed infection with syphilis. Therapy. The better the outflow of pus, the fewer chances of damage to the lymphatic apparatus; therefore, it is important to change dressings frequently (5-6 times a day), preceding them with baths with potassium permanganate (10-15 min.). In fresh, uncomplicated ulcers without sharp inflammatory phenomena in the surroundings, one of numerous caustic agents can be tried (cauterize the edges and pockets beneath them, but not every day due to the danger of buboes): Acidi carbolici liquefactum, 50% zinc chloride solution, copper sulfate. After cauterization and in between them - dressings. The most energetic, perhaps even specific action is exerted by iodoform; however, its odor sharply limits the scope of its application; immeasurably weaker is the action of its derivatives and analogs: Dermatol, Xeroform, Airol, Vioform, Europhen, etc. A good powder is Natrium sozojodolicum. All these remedies are used in the form of powders, a gruel with physiological solution, alcohol, ether (retained well), emulsions (10% iodoform emulsion in glycerin), urethral pencils and rectal suppositories (2.0 iodoform each), pastes and ointments (2-5-10%). In the State Venereological Institute in Moscow, the following paste is successfully used: Dermatoli, Zinci oxyd. aa 2.0, Natri sozoiodolici 1.0, Acidi carbolici 0.1, Lanolini 10.0. Suteev recommends a 50% pyrogallic ointment (urine control!), Almkvist - a 2-10% ointment from Cuprum amidato-aceticum, Gudelis from the clinic of the 1st Moscow Medical Institute - fatty-acid copper; one can try smearing with a solution of salvarsan, etc. When breakdown stops, granulation-promoting agents are prescribed: 3% boric, 1% silver nitrate ointment, 5% Peruvian balsam ointment, and especially 0.25-0.5% silver nitrate lotions. - When the lymphatic apparatus is affected and in case of sharp inflammatory phenomena, caustic agents are not suitable; lotions are necessary (potassium permanganate 1:1,000, 1:3,000, Argenti nitratis 0.25-0.5%, 3% boric solution, etc.).
Sometimes a good effect is produced by a 10% solution of methylene blue (Brocq) or a solution of 7 parts of carbolfuchsin and 3 parts of a 10% solution of the same blue (Queyrat). Some authors (Schprecher, Kolomoytsev, and others) are generally against cauterization, powders, and ointments, and treat only with lotions. More energetic methods of treatment are more harmful than useful: carbon dioxide snow (del Portillo), galvanocautery and thermocautery, curettage with a sharp spoon, and others; they retain some significance in ulcering serpiginous chancres. In stubborn cases, ultraviolet rays are recommended (small quartz lamp, 10 cm distance, 3-5 minutes, 2-3 times a week - Stümpke); X-rays (1/3 H.E.D., 7a, 1 mm aluminum filter, 2-3 times every 5-6 days); spraying with ethyl chloride for 1-2 minutes 5 times a day for buboes (Dub), for serpiginous ulcers (Wright); hot air (60-70°) or iodine vapors 1-2 times a day for 15 minutes (Muller, Welander, Belot), 2-3 sessions, especially for serpiginous ulcers. Azua reports on the good effect of intramuscular, and Goodman of intravenous injections of a 1% solution of Tart. stibiati; topically, a 1/2% solution thereof was used with success by Rupel. General methods of treatment (see below), used mainly for buboes, also find application in uncomplicated soft chancre. In inflammatory phimosis - hot baths, washings several times a day under strong pressure of the preputial sac (KMnO4 - 1:5,000, Arg. nitr. - 1:1,000, 0.3% hydrogen peroxide solution, etc.) followed by the injection of iodoform emulsion or drainage of the preputial sac with thin moist strips of gauze. Small incisions of the prepuce edge, dorsal incision (up to the coronal sulcus), as well as circumcision, are resorted to only in exceptional cases (danger of chancroidal degeneration of the wound edges). Buboes. Conservative treatment is also desirable for them. Treatment with heat (hot poultices, warming compresses, diathermy) combined with pressure (sandbag) can produce an effect in the initial stages. By adding general treatment to this, one can achieve in many cases the regression even of fluctuating buboes. Autohemotherapy works well (from 3 to 10 cm3 every 2-3 days); lactotherapy is even better (2-3-4 injections of 5.0); Cubero, Sinani and Shapiro, and others report a good effect from tuberculin; intramuscular injections of a 7% iodoform emulsion do not affect buboes (Bugarsky). Injections of oil of turpentine are rather suitable for opened buboes that have become chancroidal; Fay and Gaal injected under the skin pus obtained by puncture from their own bubo (0.25-1.0 every 4-5 days). In clearly fluctuating buboes, the earliest possible aspiration of pus is recommended, followed by the introduction into the cavity of a 5-10% iodoform or iodoform-xylol (10:1:90) emulsion, iodoform ointment, 1-2% ointment of Cuprum amidato-aceticum (Almquist), etc.; in France, filiform drainage (a thread pulled through the bubo using a needle) with a compress on top is recommended; for incisions, the smallest possible incisions (V, 1 cm) are desirable, followed by the introduction of ointment (see above) or drainage with thin moist strips of gauze. Radical operations (extirpation) retain some significance only for stubborn strumous buboes. X-rays (also for chancroidal and fistulous buboes) and ultraviolet rays have a good resolving effect. But a particularly rapid and sure effect, which has made surgical treatment almost unnecessary, is exerted by the intramuscular and even better intravenous introduction of a non-specific (typhoid) and especially specific vaccine (0.25-0.5-1.0 no more than 2.0 pro dosi every 1-2 days); even with clearly fluctuating buboes, 3-4 injections are sufficient. Reenstierna prepared, by the intravenous injection into a sheep for many weeks of killed and live Ducrey-Unna streptobacilli, an anti-streptobacillary serum, 1-2 injections of which (10.0 each) are sufficient for the resolution of even fluctuating buboes; injections are made into the muscles. The undoubted success of vaccine therapy, which shortens the duration of the bubo to 10-15 days (instead of 5-7 weeks with surgical treatment), urgently demands its wider application. Prophylaxis for soft chancre, besides socio-prophylactic measures, consists in hot soapy washings of the genitals after any suspicious intercourse and in the application of other measures of personal prophylaxis, in the earliest possible treatment and in the quickest extraction of all soft chancre carriers. As for the prophylactic treatment proposed by Muller and then Neisser (a course of salvarsan infusions) of any case of soft chancre, such treatment retains its significance only in cases of undoubted possibility of simultaneous infection with syphilis (confrontation). To prevent buboes, Agronik recommends in every case of soft chancre, starting from the very beginning of the appearance of the ulcer, using intramuscular injections of milk.
V. Feldman. Epidemiology of soft chancre. The epidemiological feature of soft chancre is the predominant affection of the urban population by it; in rural localities, soft chancre is as a rule registered significantly less frequently. In the period 1902-1913, a minimum of 37.1 and a maximum of 55.8 cases of soft chancre per 10 thousand of the urban population were registered in Russia; in rural localities, respectively - 1.93-3.22. Soft chancre was registered in the RSFSR (Table 1): Table 1. Years

Thus, in the three-year period 1926-1928, a decrease in the registration of soft chancre is noted compared to the pre-war years, especially sharply expressed among the urban population; in the pathology of the rural population, soft chancre, in view of its extremely rare registration (0.72 per thousand), is of no significance. Equally sharply expressed is the decrease in the registration of soft chancre in the Red Army compared to the tsarist army (for the period from 1888 to 1926 - a decrease of 88%); at present, soft chancre is registered in the Red Army as an extremely rare disease. The predominance of soft chancre morbidity among the urban population is also noted in Western Europe. Haustein provides the following data on soft chancre morbidity in Denmark (Table 2): Table 2. Years 1911 1922 Copenhagen Provincial cities Rural localities Per 10 thousand population 15.0
1.5
According to a questionnaire survey conducted from October 1, 1920, to September 30, 1921, there were registered in Switzerland in cities with a population of over 50 thousand inhabitants - 1.2 soft chancre patients per every 10 thousand; with a population of less than 10 thousand inhabitants and in industrial points - 0.2; in villages - 0.07. Changes in the registration curve of soft chancre among the urban population also occurred in the years of its relatively high registration. Poray-Koshits, observing over 16 years (from 1870 to 1885) the movement of soft chancre in Kharkov, established the "extinction" of soft chancre: in the seven-year period 1870-76, soft chancre made up 13.6% of all registered venereal diseases, in the seven-year period 1879-85 - only 2.4%. At the same time, as can be seen from Table 3 (according to Poray-Koshits), soft chancre, according to Western European and Russian statistics, made up on average more than 1/3 of all registered venereal diseases (Table 3). Table 3. Frequency of registration of soft chancre in the pre-serological era (in %). Authors Gonorrhea According to Mischaud - up to 1865... | 39.7 According to Zeissl-Pio - 1872..... | 37.1 According to Tarkovsky (Petersburg) - 1866-69...... | 49.0 Report of Myasnitskaya Hospital (Moscow) - 1880 According to Poray-Koshits (Kharkov) | 1870/76... (1879/85... According to Grinfeld (Odessa City Hospital) - 1903........ . . 9.1 46.4 42.2 14.2
In later years, the specific weight of soft chancre in the group of venereal diseases decreased: Blaschko, based on an analysis of data from 37 cities in Germany where a special statistical survey was conducted, established that in 1913 soft chancre accounted for 10% of all venereal diseases, syphilis for 20%, and gonorrhea for 70%. The war of 1914–1918 and the immediate post-war years are characterized by an increased registration of soft chancre alongside other venereal diseases. Borchardt notes an increase in soft chancre in Berlin from 1918 to 1920, and Jambon and Tzanck observed the same in France. Gaustein cites data on the trend of soft chancre in Copenhagen from 1907 to 1924 (see figure); the highest increase occurred after 1916 during the period 1919–1920, after which the soft chancre curve dropped sharply. Temporary increases in soft chancre in the post-war years were not of a long-term character, and as a rule, soft chancre is rarely registered among venereal diseases. According to data from venereal dispensaries of the RSFSR in 1924–1925, the specific weight of soft chancre was 1.8% (Galperin and Isayev); in venereological institutions of the Ukrainian SSR for 1924, it was 2.3% (Fedorovsky). These figures are somewhat higher for large metropolitan centers and ports: in Moscow, 25,106 cases of venereal diseases were registered in 1928, of which soft chancre accounted for 5.5% (gonorrhea 52.3%, syphilis 42.2%); in Leningrad in 1928, there were 13,969 cases of venereal diseases, of which soft chancre accounted for 3.1% (gonorrhea 70%, syphilis 26.9%); at the Glavchev Institute in Odessa from 1917 to 1926, a total of 51,279 cases of venereal diseases were registered, of which soft chancre accounted for 7.3% (gonorrhea 33.8%, syphilis 58.9%). Despite the small prevalence of soft chancre compared to gonorrhea and syphilis, epidemic outbreaks of it are of serious importance due to the fact that in such cases an increase in the incidence of syphilis may also occur. The latter is explained by the fact that the main focus of soft chancre—prostitution (see Table 5 below)—is also one of the main sources of sexual transmission of syphilis. The frequency of mixed chancre, arising from such simultaneous infections, ranges, according to various authors, within 13–1% of all cases of soft chancre; however, there are indications that soft chancre can be a mixed chancre in 58%. An isolated epidemic outbreak of soft chancre was noted in 1929: according to Podvysotskaya, through the inpatient department of the Tarnovsky Hospital in Leningrad, there passed in absolute numbers for the year 1928 323 patients with soft chancre (6.5% relative to all hospitalized skin and venereal patients), and for the year 1929 994 patients with soft chancre (33% relative to all hospitalized patients or 60% relative to venereal patients alone). Rottmann observed an epidemic outbreak of soft chancre in the port area of Duisburg-Ruhrort (Lower Rhine region in Germany), where a total of 7 cases of soft chancre passed through the venereal dispensary from March to September 1928 (an average of 1 soft chancre infection per 180 new venereal diseases per month), while from November 1928 to September 1929, 343 patients with soft chancre were admitted (more than 31 new infections on average per month). Rottmann partly explains such a sharp increase in the number of patients with soft chancre by the growth of prostitution among women in port cities; these women infected sick sailors not only in the German port of Duisburg, but also in foreign ports, in particular in the Netherlands, which is also reflected in the increase in the incidence of soft chancre during the navigation period. Among various professional groups of the population, soft chancre is distributed unevenly: railway and water transport workers are the most vulnerable in terms of infection. According to Khodakovsky's data, among the entire population of the city of Rostov-on-Don in 1926, 10.0 cases of soft chancre were registered per 10,000 residents, while among the transport population it was 23.0. With the registration of soft chancre in 1927 being 4.04 per 10,000 urban population, the corresponding amount for the transport population, according to data from 31 medical districts of the North Caucasus Railway, was 6.4. An epidemiological feature of soft chancre is a significantly higher incidence among men than among women, noted both in the pre-serological era and in subsequent years (Table 4). According to Blaschko, in Hamburg, with an average annual incidence of venereal diseases equal to 45.4‰ for men and 10.8‰ for women, the incidence of soft chancre was 7.2‰ for men and 0.6‰ for women. The rare seeking of medical help by women for soft chancre has led to attempts to explain this phenomenon by peculiar bacillus carriage (see above). The smaller number of women with soft chancre can be explained in part by the limited foci of soft chancre, the carriers of which, unlike gonorrhea in particular, are in the overwhelming majority prostitutes (Table 5). Table 5. Sources of soft chancre infections (in %). Authors: Prostitutes, Casual acquaintances, Wives. Khodakovsky (transport population of the Rostov railway) - 56.3, 31.3, 6.2; Frenkel (urban population of Kharkov) - 1924–1926 - 78.9, 15.6, 2.9; Borshchevsky (water transport workers) - 1926 - 77.3, 22.7. The percentage of infections from prostitutes given in Table 5 must be increased to a certain extent at the expense of infections from so-called "casual acquaintances." Thus, according to pre-war statistics by Peterson (cited by Frenkel), when prostitution in Russia was regulated, a survey of 579 soft chancre patients revealed 517 infections from prostitutes (90%). In Vienna, in the period from 1906 to 1910, 1,888 cases of venereal diseases were discovered among regulated prostitutes, of which 458 (24.2%) were soft chancre. The higher incidence of the population of port cities is connected with the large presence of prostitution in these places (so-called port prostitution): according to Borshchevsky, the Odessa Water Transport Outpatient Clinic registered 91 soft chancre infections for 1924–1926, of which 31 (38.9%) occurred in allied and foreign ports, with all infections in foreign ports taking place in brothels. Soft chancre, both among men and among women, is most frequently encountered at the age of 20–30 years. The distribution by sex and age (in absolute numbers of patients with soft chancre registered in Moscow is given in Table 6 (according to data from the Moscow Statistical Bureau). In Table 7 (see page 31) Blaschko presents the distribution of soft chancre incidence by sex and age in 1913 in Hamburg (per 1,000 population). Table 6. Age, 1924, 1927. Excluding age groups below 15 years and above 50 years, Blaschko establishes for the adult population aged 15–50 years, for whom venereal diseases are of the greatest importance, an annual incidence of soft chancre equal to 12.8‰ in men and 1.0‰ in women. Among 400 soft chancre patients registered at the State Venereological Institute in Moscow for 1924–1926, 9.2% were aged 15–20 years, 20—
. 40-50 years 50-60 years above 60 years , Men Women 0.1 6.1 21.8 25.8 18.7 6.7 2.6 0.9 0.2 : 0.1 ! 1.2 2.3 2.2 1.2 0.4 0.1 - 30 years - 65.5%, 30-40 years - 19.2%, 40-50 years - 3.9%, and over 50 years - 2.2%. In childhood (up to 15 years old), soft chancre as a venereal disease, transmitted almost exclusively by sexual contact, is extremely rare. Roeb collected in the literature up to 1920 descriptions of only 6 cases of soft chancre in children. Soft chancre is observed among families relatively less frequently than other venereal diseases; according to Galperin and Isaev, who analyzed the marital status of 6,753 patients with syphilis (1924-25), 57% of the latter were married; among 4,823 patients with gonorrhea, 51% were married; according to Frenkel, out of 308 patients with soft chancre, 34.1% were married. Analyzing the marital status of 1,400 patients with soft chancre separately for men and women, Khatenever and Gutina found that among the former there were: married - 24.8%, single - 76.2%; among the latter there were: married - 67.4%, unmarried - 32.6%. Aside from general factors influencing the spread of venereal diseases, such as war, the movement of the masses associated with it, and the intensification of prostitution in port and railway centers, the spread of soft chancre is also facilitated to a certain extent by the low sanitary level of the population. Frenkel, among 308 patients with soft chancre registered at the Kharkov Venereological Institute for 1923-26, found that 18.8% lived in a separate room, 51.6% in a shared apartment, and 29.6% in flophouses; of all patients, 71.7% did not use a separate bed, towel, or dishes. Consistent with this are the author's indications that 36.9% of all male soft chancre patients were unskilled laborers living predominantly in flophouses. The largest percentage of soft chancre patients are persons with a primary education. According to Khatenever and Gutina for 1924-26, illiterates and semi-literates constituted 11%, those with primary education 72.7%, those with secondary education 15%, and those with higher education 1.3%. - The fight against soft chancre in the USSR is one of the tasks of the venereological organization (see Venereal Diseases). The fight against soft chancre in the USSR is facilitated by the progressive improvement in the socio-economic living conditions of the working people and the elimination, in the process of socialist reconstruction, of all factors causing the periodic growth of soft chancre in capitalist countries. The liquidation of prostitution in the USSR and the gigantic growth of the cultural and sanitary level of the working masses are already at the present time causing a sharp drop in the incidence of soft chancre, which is a rare disease in the USSR.
Related articles
Mentioned in
Cite this page
“Soft Chancre.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/soft-chancre/