Seminal Vesicles
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia details the anatomy, physiology, and pathology of the seminal vesicles. It describes their structure, blood supply, innervation, and the composition of their secretion, while also covering clinical conditions such as developmental defects, cysts, stones, and tumors.
Encyclopedia article (1928–1936)
SEMINAL VESICLES (vesiculae seminales, glandulae seminales) represent a paired organ developing from the Wolffian ducts, consisting of two sac-like formations located between the lower-posterior wall of the urinary bladder and the ampulla of the rectum, above the upper edge of the prostate gland; their longitudinal axis is directed from above and outside downwards and inwards, extending with their apex 4-5 cm above the Lieutaud triangle and the orifices of the ureters. With their lower end, the seminal vesicles extend under the upper edge of the prostate gland, so that the latter overlaps them. The seminal vesicles form a not entirely closed angle with their necks; in newborns and in persons over 60 years of age, it is obtuse, and in mature and elderly age, it is equal to 60-80°. The peritoneum, passing from the urinary bladder to the upper surface of the seminal vesicles, covers them for 1-2 cm, then ascends upwards along the rectum. The seminal vesicles of an adult are usually 4-5 cm long, 1.5-2 cm wide, and 1-1.5 cm thick, representing a winding tube from which 3-5 lateral tubes depart.
The lower edge of the tube, exiting from the neck of the vesicle, forms the excretory duct, which, together with the canal of the ampulla of the vas deferens, forms the ejaculatory duct (d. ejaculatorius). The seminal vesicles are placed in a sac consisting mainly of connective and muscular tissue; their surface is bumpy, their shape is ellipsoidal, slightly flattened in the anterior-posterior direction. Abundant blood supply originates from the hypogastric artery via vessels departing from it: the inferior vesical (a. vesicalis inf.) and the middle hemorrhoidal (a. haemorrhoidal. med.). The artery of the vas deferens (a. deferentialis) is located on its anterior wall and gives off a branch that anastomoses with the middle hemorrhoidal artery and with the lower branch of the testicular artery (a. spermatica int.). The veins generally correspond to the course of the arteries; the vein of the vas deferens, running from the tail of the epididymis, connects with the external testicular vein. These veins form a plexus surrounding the vas deferens and the ampulla, which transitions into the plexus of the seminal vesicles (pl. venosus seminalis) and further into the venous vesico-prostatic plexus (pl. venos. vesico-prostaticus).
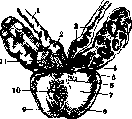
Lymphatic vessels, according to Sappey, are numerous and anastomose densely with each other; gathering then into 2-3 trunks, they flow into the hypogastric lymphatic vessels. The nerves of the seminal vesicles originate from the fibers of the hypogastric sympathetic plexus, partly from the pelvic nerve, forming, together with the spinal nerves, plexuses that encompass the seminal vesicles. The walls of the seminal vesicles consist of three layers: connective tissue, muscular, and mucous membrane. The medial wall, i.e., the one facing the vas deferens, is thicker than the lateral one. The mucous membrane has serrated elevations of the most diverse forms, from small individual protrusions to a reticular structure, in places filling the entire lumen of the seminal vesicles. The epithelium is single-layered cylindrical, partly multi-layered cylindrical; cubic epithelium is sometimes encountered (Zaigraev). The physiological significance of the seminal vesicles has not yet been sufficiently clarified. The secretion of the seminal vesicles is transparent and glassy, sometimes yellowish, odorless, and of alkaline reaction (pH 7.6 according to Armistead). It contains fat-like droplets of various sizes, some 5-10 times larger than leukocytes, viscous, gelatinous lumps called "sago grains." When stained, the latter give a reaction for mucin and a weakly positive one for fat; they dissolve easily in acetic acid and were named simpexions by Robin. According to Cohn's research, the secretion of the seminal vesicles contains crystals of three types: Reinke's, Lubarsch's, and Böttcher's. The purpose of the secretion of the seminal vesicles consists in liquefying the medium, which causes greater motility of spermatozoa, and in nourishing the spermatozoa not only inside the seminal vesicles but also in the semen ejaculated into the vagina. According to the latest research, the seminal vesicles apparently take part in internal secretion. Methodology for the examination of the seminal vesicles—see Vesiculitis and Vesiculography.
Developmental defects of the seminal vesicles are generally rare. Most often, underdevelopment or absence of one seminal vesicle occurs. In these cases, there is usually no corresponding testicle or kidney. Cases of fusion of both seminal vesicles into one, located in the middle, have been observed, as well as cases of the absence of both seminal vesicles. The method of vesiculography has revealed other, smaller developmental defects, such as, for example, the connection of both seminal vesicles to each other by a tube. The practical significance of these anomalies is insignificant. Injury to the seminal vesicles is observed extremely rarely due to their deep position and their easy mobility. Cysts, ectasias, hydrocele, and empyema of the seminal vesicles are observed most often due to blockage or obliteration of the ejaculatory duct as a result of a chronic inflammatory process or in cases of hypertrophy of the prostate gland. Their contents are either clear serous fluid, or cloudy with an admixture of mucus, or pus. The dimensions of these formations are extremely varied—from a small nut to a tumor extending into the pelvic cavity. Thus, Fronshtein described an empyema where the amount of pus in the seminal vesicles exceeded 700 cm³. The diagnosis of these formations does not present difficulties: upon palpation of the seminal vesicles through the rectum, an elastic tumor of the corresponding size is felt. In doubtful cases, vesiculography can be performed, and in extreme cases, puncture of the seminal vesicles. Stones of the seminal vesicles are a relatively rare disease; they are formed due to stagnation of the secretion as a result of narrowing of the ejaculatory duct, more often in old age. They consist mainly of calcium phosphate. Their diagnosis is based on palpation of the seminal vesicles through the rectum, preferably with a curved metal bougie inserted through the urethra, and on radiography. Subjective symptoms are expressed in the form of pain during ejaculation, which can reach the point of spermatic colic (colique spermatique). Other symptoms differ little from the subjective disorders caused by prostatitis, vesiculitis, and posterior urethritis. Treatment consists of an attempt to crush and remove the stone through the ejaculatory duct by pressing on the seminal vesicles through the rectum. For pain, hot sitz baths and even narcotics are prescribed. In severe cases, one should resort to surgical intervention. Tumors of the seminal vesicles, both benign and malignant, are encountered extremely rarely. Most often, cancer of the seminal vesicles is encountered, both primary and in the form of metastases, or growing in from neighboring organs. Their recognition is quite difficult, but pain in the inguinal region, colon, and perineum, and difficulty in defecation and urination should arouse suspicion of this disease. Cystoscopically, there is bullous edema in the region of the corresponding seminal vesicle. Upon palpation through the rectum, a bumpy, enlarged seminal vesicle can be felt. Little is known about the syphilitic disease of the seminal vesicles. Individual cases of this affliction have been described.
Related articles
Mentioned in
Cite this page
“Seminal Vesicles.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/seminal-vesicles/