Scleroma
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
Scleroma (rhinoscleroma) is a chronic infectious disease of the respiratory tract characterized by granulomatous infiltrates and subsequent scar tissue formation causing airway strictures. First described in 1870, it is associated with poor socioeconomic conditions and endemics in Eastern Europe, caused by Klebsiella pneumoniae subsp. rhinoscleromatis (Frisch bacillus).
Encyclopedia article (1928–1936)
SCLEROMA. History. Scleroma was first described by Hebra and Kaposi (1870) under the name "rhino-scleroma", as the process in the nose was taken to be the primary basis of the disease, while accompanying changes in the larynx and other organs appeared insignificant and accidental. Soon, however, other authors (Gerhardt, 1873; Ganghofner, 1880) noted the unity of manifestations of the scleromatous process in different parts of the respiratory tract and the identity of scleroma with the disease that had been described even earlier by Störk under the name "chronic blennorrhea of the respiratory tract". The clarification of the histological structure of scleromatous infiltrates was particularly advanced by the work of Mikulicz (1876), while bacteriology had as its pioneers Frisch and Pelizzari, who discovered a specific microorganism in scleromatous tissue in 1882—Bact. rhinoscleromatis (see Microorganisms). Subsequent works by Cornil and Alvarez, Paltauf, Eiselsberg, and others clarified the details of the morphology and cultivation of the scleroma bacillus. Attempts to induce the scleromatous process experimentally in animals were made starting in 1889 (E. M. Stepanov); positive results were obtained by Kraus, G. E. Zhukov, and Jaeger. In 1909, Goldzieher and Neuber discovered a specific antigen in the blood of scleroma patients, and in 1930 Mantoux and Roux observed an allergic reaction, both local and focal, upon intradermal administration of the antigen. Social significance, geographical distribution, and epidemiology. The gradual spread of scleroma far beyond its endemic foci, the significant increase in the total number of cases, and the undeniable connection with living conditions determine the social character of this pathological entity (Figure 1). Statistics show that scleroma is distributed on the territory of our Union primarily in the Ukrainian SSR and the Byelorussian SSR, where up to 1,000 patients have been registered according to the latest data, while individual cases have been observed in other places, sometimes far removed from the western border, e.g., in Siberia (Pautov), Central Asia (Voyachek), etc. Abroad, scleroma is mainly prevalent in Poland, Czechoslovakia (several hundred cases each), and more sporadically in Romania, Germany, Bulgaria, Switzerland, Italy; isolated cases are encountered in France, the USA, the Sunda Archipelago (Sumatra), and other countries. In total, 2,631 cases have been counted (St. Belinov). Women predominate among patients. Half of all cases occur between the ages of 15 and 35. The disease nests mainly among impoverished strata of the population living in poor hygienic conditions.
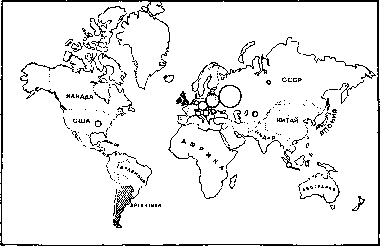
Figure 1. Geographical distribution of scleroma in various countries. Scleroma foci are designated by circles; regions where scleroma is not encountered at all are hatched; places of sporadic cases are marked with black dots (according to data of the II International Congress of Otorhinolaryngology).
The mode of transmission is not precisely known; direct transmission from person to person is unlikely, although not completely excluded. From the "foci" of scleroma, the disease gradually spreads to neighboring localities or, due to migration, is carried in leaps to distant countries. According to A. M. Puchkovsky, wars and associated troop movements also greatly contributed to the dissemination of scleroma. The relationship to living conditions is expressed in the fact that scleroma foci are more frequently found in marshy areas, with population overcrowding and other unhygienic conditions (shared quarters for people and domestic animals, poor nutrition, etc.). Pathogenesis and forms. Scleroma is a chronic infectious disease expressed by the development of granulomas in various parts of the respiratory tract (hence the name scleroma respiratorium) and adjacent organs, which over time transform into scar-degenerated masses causing more or less significant strictures of the respiratory tract. The incubation period is not precisely known. Even children in the first years of life can fall ill. The portal of infection appears to be the upper respiratory tract, but judging by the predominant localization of changes, one must think that the primary focus in different individuals may selectively reside either in the nose, the nasopharynx, or the larynx; three characteristic sites exist where scleromatous granulomas are found most often—the entrance to the nasal cavity, the choanae (rhino-pharyngoscleroma), and the subglottic space of the larynx (chorditis vocalis inferior hypertrophica); recently, frequent involvement of the tracheal bifurcation has also been pointed out (all of these correspond to sites of physiological constrictions). The disease is distinguished by slow progression, but gradually the infiltrates can spread to other organs, involving the walls of the oral cavity, the pharynx, bronchi, external nose, lips, lacrimal passages, Eustachian tube, tympanic cavity, and external auditory canal. Each localization can be designated by adding a prefix to the main term indicating the organ, e.g., "bronchoscleroma" or "otoscleroma". Besides typical scleroma, characterized by moderately developed granulomatous infiltrates and strictures in the region of physiological constrictions, a hypertrophic form is distinguished with the formation of bulky growths (for example, similar to rhinophyma on the external nose) and the opposite—an atrophic form, which clinically differs very little from vulgar atrophic rhinitis or vulgar ozaena. Due to scleromatous infiltration, the involved organs can gradually adhere to surrounding tissues (e.g., the trachea to adjacent cellular tissue) and even skeletal parts (the sternum), but metastases in separate parts of the body and generalization of the process overall are not observed. Pathological anatomy. Characteristic features of scleromatous infiltrates are vacuolated Mikulicz cells scattered throughout the general mass of granulomatous tissue, hyaline Russell bodies (see), which according to Schridde are a derivative of basophilic granules in plasma cells, epithelial cords extending often deep into the infiltrate, and the presence of encapsulated Frisch bacteria in the vacuoles of Mikulicz cells and in the lymphatic intercellular spaces (Figure 2). Infiltrates can have various shapes: diffuse, nodular, lumpy, tumor-like, etc. The diffuse form is often masked by symptoms of atrophic rhinitis—dryness of the mucous membrane covering the infiltrates, mucus, and crusts. If substance defects form on the surface of the affected areas, they are usually not deep (superficial scleromatous abrasions and generally any trauma to infiltrates, even surgical, usually heal without complications). Frisch bacilli in sections stain Gram-positive (although in cultures they prove to be Gram-negative). Three or four stages of infiltrate development are distinguished. In the initial stage, there is an accumulation of small and large lymphocytes, neutrophils, plasma cells of various sizes, fibroblasts, vacuolated cells, and hyaline Russell bodies. Blood vessels are found in large numbers. In the second stage, the number of lymphocytes decreases while plasma cells increase; oval and spindle-shaped forms of them (fibroblasts) are frequently encountered. In

Figure 2. Scleroma bacilli in epithelial cells. In the third stage, the number of Mikulicz cells increases, while plasma cells remain few. In the fourth stage (cicatricial shrinkage), vacuolated cells disappear and collagenous connective tissue forms in large quantities, admixed with elastic fibers. The vessels become obliterated, but Russell's bodies can still be found in places. The epithelium undergoes desquamation and metaplasia from columnar to stratified squamous; epithelial cords penetrate deep into the submucosal tissue. The formation of true epithelial masses has sometimes been observed. In contrast to certain animals, such as mice, in which subcutaneous injection of Frisch's bacilli causes septicemia, in humans scleroma remains a local disease in the sense that it does not metastasize, but it may be accompanied by secondary changes in internal organs, including lymphadenitis (secondary infection), pulmonary emphysema, right cardiac enlargement, pneumonia, lung abscess and gangrene, pericarditis, and pleurisy. In 10% of cases, scleroma was combined with tuberculosis. A combination with syphilitic changes and with tumors has been observed. Experimental pathology. In animals, including monkeys, inoculation with scleroma causes a disease quite similar to the human one, but it runs an acute course, resembling the fresh initial stages of human scleroma, and, in contrast to the latter, shows no tendency to become chronic, likely due to the easy formation in animals of protective bodies specifically acting against the ectoplasm (capsule) of the bacteria; in humans, these bodies are insufficient. Bacteriology and serology. The bacillus that causes scleroma belongs to the Friedländer group (see Microorganisms). Characteristic features of Frisch's bacilli on sloped agar include: they form condensation water in media containing glucose and sucrose, produce acid, and ferment lactose without gas. Salicylic acid in a 1% alcohol-water solution kills scleroma bacilli in 45 seconds; 3% carbolic acid in 7 seconds; mercuric chloride in a 1:1,200 dilution in 5 seconds. The complement fixation test according to Bordet-Gengou was successfully developed and introduced into diagnosis in 1909 for scleroma by Goldzieher and Neuber, and in our country by G. E. Zhukov. Subsequently (1917), Neuber showed that only in very weak dilutions could the serum of scleroma patients also bind with ozena-like antigens, but this plays no role in practice. A serological examination of relatives of scleroma patients showed that most of them gave a positive reaction; therefore, they had to be considered potentially sick as well (Feldmann). According to Elbert, to obtain specific amboceptors it makes no difference whether one immunizes using capsulated or capsule-free bacteria (mutants). The agglutination method for differentiating scleroma bacteria was applied by Kraus in 1897 and Julianelle in 1926. Experiments with precipitation yielded no convincing results. Allergic reactions were tested in various modifications, with the intradermal test giving the most definite results, in which 0.1 cm3 of scleroma antigen produces an edematous, hyperemic halo several millimeters in diameter, replaced after 6–8 days

Figure 3. Alteration of the shape of the soft palate by scleromatous infiltrates.
by a dense infiltrate projecting 1–2 mm above the skin surface and persisting for many weeks. Vaccines from other capsulated bacteria (Friedländer, ozena) did not elicit a reaction and did not affect the course of scleromatous changes. Clinical symptomatology and complications. Typical cases are characterized by the so-called scleroma triad, consisting of narrowing of the nostrils (by infiltrate or already by its scarring), choanal "side-curtains", and subglottic stricture of the larynx (Figures 3–5). In other parts, the mucous membrane of the upper respiratory tract is in a state of chronic catarrh, very often of a dry form, with crusts and fetor (the scleromatous odor somewhat resembles the ozenous one). Patients are most often in the bloom of youth, natives of areas endemic for scleroma, and complain of difficulty breathing (general or nasal only) and hoarseness. If the process also involves visible parts of the face, external objective signs join in, and then often the main complaints of the patients center on the external disfigurement. To this more or less typical clinical picture, symptoms of its further extension to neighboring organs (mouth, lip, nasolacrimal duct, Eustachian tube and tympanic cavity, trachea, bronchi) may be added. Atypical cases are considered to be those where the scleromatous infiltrate is localized primarily not in the sites of the "triad", but somewhere else, e.g., on the skin of the external nose (Figure 6), in the paranasal sinuses, on the tongue, or in the larynx (but not in its subglottic space), or where the infiltrates have an appearance uncharacteristic of scleroma, e.g., covered with deep ulcers, resembling a cancerous tumor, or shaped like a fibroma. When localized in the ear (otoscleroma), the process may manifest, as a case by Voyachek shows, as polypoid growths completely filling the external auditory canal but originating from the tympanic cavity; simultaneously, there is otorrhea and impaired hearing with symptoms corresponding to middle-ear involvement.

Figure 4. Stricture of the nasal vestibule from scleromatous infiltrates.


Figure 5. Subglottic infiltrates of the larynx.
Figure 6. Scleromatous change of the external nose. ... to otitis media. Histologically, these polyps presented a typical picture of scleromatous infiltrates. Purely atrophic processes that clinically give no suspicion of scleroma, or destructive processes on the palate, tonsils, or nasal septum, when at first glance any other possibilities seem more likely, are difficult to diagnose. The same applies to the cicatricial stage of the process, especially if it is localized in deep sections (e.g., in the bronchi). Secondary infection (perichondritis) or applied therapeutic measures (operations, X-rays) can complicate the clinical picture. The general condition in scleroma is often quite satisfactory in terms of general nutrition, sleep, etc., but not infrequently patients become exhausted and lose nervous and physical stability, mainly in cases where respiratory disorders are present. Course and outcomes. Scleroma is characterized, as stated, by an extremely slow course; cases have been described where patients lived with confirmed disease for more than 50 years. An acute course of scleroma is observed less frequently, when, for example, stenosis of the respiratory tract occurs already a few months after the first symptoms. Death occurs from suffocation, more or less gradual, from complications in other organs, or from intercurrent diseases. Diagnosis in typical cases is established by anterior and posterior rhinoscopy and laryngoscopy; often, scleroma can already be suspected from a distance by the characteristic odor, especially if the patient is a young person, a native of a scleromatous area, the onset of the disease was gradual, and its course chronic. The diagnosis is confirmed by bacteriological and serological examination and biopsy. In unclear cases, these methods come to the fore and help differentiate scleroma from syphilis, tuberculosis and lupus, leprosy and other granulomatous forms, neoplasms, and vulgar ozena. Prophylaxis. At the 1st (Copenhagen) Otolaryngological Congress in 1928, an international commission was formed to study all epidemiological questions of scleroma. A draft international agreement on the fight against scleroma was presented by Prof. Barraud. Its main theses are mandatory registration of all scleroma cases using a special questionnaire, mandatory courses of treatment in a specialized scleroma hospital, and subsequent periodic health checks. The draft is subject to development and approval by the International Bureau of Hygiene in Geneva. In the USSR, a committee for the study of scleroma was formed (chairman Prof. L. I. Sverzhevsky); the problem of scleroma is being developed in otolaryngological institutes, with the Leningrad Institute having a stronghold in Smolensk, and the Kharkiv Institute having a scleroma department in Kyiv. In the BSSR, the base for studying scleroma is Minsk. Observations of sporadic cases are conducted by individual otolaryngological clinics. Special questionnaires have been developed for registration.—The question of the extent to which scleroma patients need to be isolated from the rest of the population remains unresolved. In any case, due to the probable contagiousness of scleroma in connection with its negative impact on working capacity and ozena-like symptoms, it has long been included in the list of diseases for which recruits are considered unfit for military service. Treatment. In principle, several lines along which the fight against individual manifestations of scleroma is conducted can be distinguished: 1) Surgical destruction of infiltrates and mechanical dilation of strictures can initially yield dramatic results, all the more so because the corresponding procedures are relatively well tolerated by scleroma patients. This category of therapeutic methods includes, for example, dilation of strictures of the respiratory tract with bronchoscopic instrumentation. However, after a more or less prolonged period, infiltrates recur at the old or adjacent sites, and stenoses also recur, often even in deeper parts of the respiratory tract, which requires repeating the indicated procedures with the risk of ever-decreasing effectiveness. 2) Roentgenization, which is considered by many to be the most acceptable method. According to Kordatova (from the clinic of Prof. L. I. Sverzhevsky), fresh infiltrates regress under the action of rays, denser ones partially disappear and partially scar, while scars remain unchanged. Long-term results of radio- and radiotherapy are not yet sufficiently known; moreover, the negative aspects of actinotherapy—inflammation, edema, perichondritis, sequestra, fistulae, and ulcerations, occasionally with a fatal outcome—are little taken into account. 3) Opinions on diathermy are mixed: some French authors (according to A. A. Zhukovsky) achieved good results, others saw no noticeable advantages. 4) Vaccine therapy is also evaluated differently. According to A. M. Puchkovsky, it is necessary to distinguish the stages of the disease, with vaccine therapy being suitable mainly in fresh cases. 5) Of the drug methods, hopes were placed on Tartarus stibiatus (A. M. Puchkovsky), but its effect was by no means noticeable in all cases. 6) Trials were made with injections of fibrolysin, malaria inoculation, autohemo- and protein therapy, and parenteral administration of ichthyol, but without favorable results. 7) Purely symptomatic treatment consists of measures to combat stenoses of the respiratory tract, especially of the larynx and lower sections. Among these measures, the main role is played by intubation, bronchoscopic dilation, laryngostomy, and tracheotomy.
Related articles
Mentioned in
Cite this page
“Scleroma.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/scleroma/