Radicotomy
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia defines radicotomy (rhizotomy) as the surgical cutting of spinal nerve roots. It details the history, indications (such as severe neuralgia, tabetic crises, and spastic paralysis), surgical techniques, and the varying clinical outcomes associated with the procedure during that era.
Encyclopedia article (1928–1936)
RADICOTOMY, rhizotomy (radicotomia, rhizotomia), an operation for the cutting of the spinal cord roots. A distinction is made between: radicotomia posterior—the cutting of the posterior (sensory) roots, and radicotomia anterior—the cutting of the anterior (motor) roots. The first posterior radicotomy was performed in 1888 by Bennett (W. H. Bennett, England) for a severe form of sciatica. In the same year, Abbe (America), independently of Bennett, successfully performed the same operation in a case of severe neuralgia of the brachial plexus resulting from a previous gunshot wound. Subsequently, radicotomy was repeated by numerous authors (Jones, Groves, Horsley, Chipault, Demoulin, and others). The primary indication for its use was severe neuralgia resulting mainly from cancerous metastases to the spine. Radicotomy gained wider distribution after Foerster (1908) proposed cutting the posterior roots for tabetic crises, as well as for spastic paralysis, particularly in Little's disease (Fig. 1); however, clinical observations showed that a full therapeutic effect as a result of this operation is obtained only in an insignificant percentage of cases; in addition, a rather high percentage of operative mortality was noted. Ruvertoni, in 44 cases of posterior root cutting for neuralgia, obtained good results in only 8 patients, while in 13 cases the outcome was fatal.
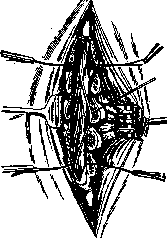
Figure 1. Cutting of the posterior roots of the spinal cord in the lumbar region of the vertebral canal (radicotomia posterior).
outcome (6 times immediately after the operation and 7 times in the near future after it). Similar figures are also cited in the collective statistics of Frazier: in 50 cases of radicotomy, a cure occurred in 7, significant improvement in 7, and some improvement in 5; 10 cases proceeded without improvement, and in 21 a fatal outcome occurred: in 8 of them immediately after the operation and in 13 at later dates. The unsatisfactory results obtained after cutting the posterior (sensory) roots for various kinds of pain led some researchers to assume the presence of additional conducting pain pathways in the anterior (motor) roots. In accordance with this, to enhance the therapeutic effect of posterior radicotomy, it was proposed to also cut the corresponding anterior roots (Foerster, Heymann, Kilvington, Thorburn, and others). However, even such an expanded application of root cutting proved to be of little effect in combating pain, and the exclusion of the anterior roots was accompanied, moreover, by paralysis of the corresponding muscle groups. All this forced a severe narrowing of the scope of application of this modification of radicotomy. Most surgeons have abandoned it altogether. Indications for radicotomia posterior at the present time are: 1) neuralgic pain not amenable to other methods of treatment (physiotherapy, alcoholization, neurotomy), 2) tabetic crises (in a sharply expressed form), and 3) spastic paralysis. Technique of radicotomy. The operation begins with a typical opening of the spinal canal (see Laminectomy) at the appropriate level. The dura mater is incised along the entire length of the operative wound, and its edges are taken up with ligatures. By pulling on the latter, the corresponding edge of the membrane is pulled outward, while simultaneously pushing the spinal cord (or cauda equina) in the opposite direction with a blunt spatula. In this process, the roots become clearly visible and can easily be isolated from one another. For orientation when counting the roots, the following guidelines are useful. For the cervical region: the spinous process of CVII corresponds to the place of exit of the CVIII root from the dura mater; in addition, the VI cervical root is thicker than the remaining cervical and DI roots. For the lumbar region: the spinous process of LV corresponds to the place of exit of the SI root from the dura mater. As for distinguishing the anterior and posterior roots, in the cervical and thoracic regions of the spinal cord, this presents no difficulties, as they are located quite far from each other. The matter is somewhat more difficult in the region of the conus medullaris and cauda equina; here, when differentiating the roots, it is necessary to remember that the posterior root is wider, flatter, and lies posteriorly and outwardly, while the anterior root is thinner and rounder; in doubtful cases, it is useful to use an electrode. Sequentially isolating the found roots onto a special hook, they are cut with a sharp scalpel (but not with scissors). The bleeding that sometimes occurs during this is stopped by light tamponade; the application of ligatures should be avoided if possible. For the sake of greater radicalism, some authors recommend not limiting oneself only to cutting the root, but to excising an entire section of it, i.e., to perform a rhizectomy. The operation ends with the application of layered sutures to the dura mater (continuous), soft tissues, and skin.
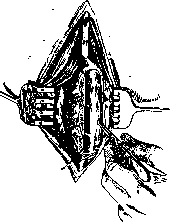
The operation ends with the application of layered sutures to the dura mater (continuous), soft tissues, and skin.
Guleke's operation—extradural cutting of the roots. In order to avoid opening the dural sac and the associated possible trauma to the spinal cord, introduction of infection, subsequent leakage of cerebrospinal fluid, etc., Guleke proposed cutting the posterior roots (as well as the anterior ones) extradurally (outside the dural sac) (Fig. 2). However, this method has not yet received wide distribution. Molotkov's operation—extraganglionic cutting of the posterior roots of the spinal cord (radicotomia post. extraganglionaris). Proceeding from the special importance of the intervertebral ganglia in the origin of vasomotor, trophic, and pain disorders, as well as the failure of other surgical interventions on the nervous system for the indicated diseases, Molotkov, at the 20th Congress of Russian Surgeons (1928), proposed performing the cutting of the posterior (sensory) root immediately distal to the ganglion, where this root has not yet entered into the composition of the mixed nerve. Positive results of this operation were noted by the author in 8 cases, but have not yet been confirmed by other surgeons.
Related articles
Cite this page
“Radicotomy.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/radicotomy/