Penis
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
The penis is an organ with dual physiological functions: sexual intercourse with semen emission and urination from the bladder. This article details its anatomical structure, comparative anatomy across species, embryological development, and topography.
Encyclopedia article (1928–1936)
PENIS, penis (from Latin literally tail), membrum virile, male genital organ. The penis is an organ with dual physiological functions: sexual intercourse with semen emission and urination from the bladder. In the human male penis, a wide posterior fixed end-the root (radix penis) and a free part are distinguished; surfaces-the anterior, or dorsum of the penis (dorsum penis), and the posterior (in the hanging position). The penis consists of two cavernous bodies (corpora cavernosa penis) and the cavernous body of the urethra (corpus cavernosum urethrae), which swells into the glans. (The structure of the cavernous bodies-see Cavernous; the structure of the urethra, seminal tubercle, seminal ducts-see Urethra, Seminal Tubercle, Seminal Duct.) The glans of the penis (glans penis) is shaped like a blunt cone; the anterior end of the connected cavernous bodies of the penis enters into its depression. The protruding part of the base of the glans is called the 'corona' of the penis (corona glandis); behind the corona there is a circular groove (collum glandis). On the free end of the glans, the external opening of the urethra (orificium urethrae externum) is visible; the dilated part of the canal located in the glans is called the navicular fossa (lacuna magna urethrae, fossa navicularis) (see Urethra, fig. 3). The skin of the penis (see Skin - anatomical-physiological features in different parts of the body) at the base of the glans forms a fold-the prepuce (praeputium), which surrounds the glans. A slit-like cavity of the prepuce remains between the glans and the prepuce. Both the length of the prepuce and the size of its cavity are subject to individual variations, which has great practical significance (see Phimosis and Paraphimosis). On the lower side of the penis, the prepuce is connected to the skin of the glans by a vertical fold (frenulum praeputii). Until about 10 years of age, the prepuce still appears as if fused to the glans. On the inner surface of the prepuce, sebaceous glands of various sizes (glandulae praeputiales, s. Tysoni) are located. The secretion of the glands enters the composition of the preputial smegma (smegma, s. sebum praeputii). The main component of 'smegma' are epithelial cells that are shed from the surface of the prepuce and glans of the penis. Comparative anatomy. The penis in animals is constructed very differently, originating from the anterior wall of the cloaca (abbrev.). In turtles, crocodiles, and some bird breeds, the penis, being unpaired, represents a groove-like thickening of the ventral wall of the cloaca. Under this groove lies a fibrous body and a collection of cavernous tissue, which when swollen, the groove turns into a tube. At the end of the tube lies an organ isolated from the cloaca wall, which can protrude like a glans (glans penis). The fusion of the tube of reptiles along the midline gives the penis of egg-laying animals, which in a relaxed state is located in a pocket-like protrusion of the abdominal wall. In viviparous animals, due to the reduction of the posterior part of the cloaca, the penis is located externally. In marsupials, rodents, and insectivores, it is directed backward with its apex, as in elephants, hyraxes, rhinoceroses, and tapirs in a relaxed state, but during swelling (erection) in the latter, it turns forward. The position of the penis with its apex forward in placental animals is caused by the development of the perineum. Also, gradually in a number of animals, the cavernous bodies of the penis develop. It is interesting to note that in marsupials, cetaceans, carnivores, pinnipeds, rodents, bats, and prosimians, and sometimes also in monkeys, there is a unpaired ossification (os penis, s. Priapi) in the terminal part of the copulatory organ (see also Induratio penis plastica). In marsupials, corresponding to the two vaginae of the female, the penis is often bifurcated at the end, and each half of the glans is penetrated by a branch of the bifurcated urogenital canal. The skin forms a praeputium around the hanging penises, which is initially connected to the glans by means of an epithelial layer; the latter, being resorbed, forms a cavity (cavum praeputii). The embryology of the genital organs has great practical significance, because even in the most extreme forms of underdevelopment of the genitals, the individual survives and continues to develop, maintaining his vicious constitution. The penis develops from two primordia: the outer and middle embryonic leaflets of the anterior abdominal wall and from the membrane closing the cloaca (fig. 1). The anterior abdominal wall, as it grows from top to bottom, forms the so-called genital tubercle, hanging over the cloaca, which on the lower-posterior surface of the genital tubercle forms genital folds due to the proliferation of epithelium. Between the genital folds is located the genital groove, reaching the thickened apex of the genital tubercle.
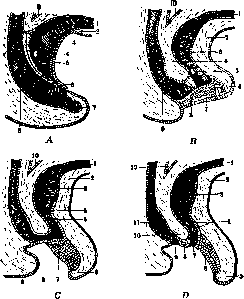
Figure 1. Development of the rectum and bladder: A-1-urachus; 2-epidermis of the anterior abdominal wall; 3-bladder; 4-sinus urogenitalis; 5-cloaca membrane; 6-protrusion of the anus membrane; 7-tail intestine; 8-rectum; 9-peritoneum; B-1-urachus; 2-anterior abdominal wall under the navel; 3-bladder; 4-septum urorectale; 5-opening of the Wolffian duct; 6-genital tubercle; 7-cloaca membrane; 8-fold for the formation of septum urogenitale; 9-rectum; 10-peritoneum; C-1-urachus; 2-anterior abdominal wall; 3-bladder; 4-septum urorectale; 5-opening of the Wolffian duct; 6-genital tubercle; 7-epithelium on the lower surface of the tubercle; 8-cloaca membrane; 9-rectum; 10-peritoneum; D-1-urachus; 2-anterior abdominal wall; 3-bladder; 4-opening of the Wolffian duct; 5-genital tubercle; 6-epithelium of the lower surface of the tubercle; 7-sinus urogenitalis; 8-perineum; 9-anus; 10-septum urorectale; 11-rectum; 12-peritoneum. (According to Corning.)
The genital tubercle proliferates, forming the cavernous bodies of the penis; the thickened peripheral part gives its glans (fig. 2 and 3). The genital folds, fusing along their entire length with the exception of the periphery of the glans, form the urethra. Non-fusion of the genital folds leads to the formation of a number of anomalies (see Hypospadias). The development of the prepuce occurs from a collection of epithelium on the glans of the penis, which is connected with the epithelium of the genital folds. As it proliferates, it separates a part of the tissues from the glans of the penis, which forms the prepuce (praeputium). Delay in this process gives the so-called synechiae (see below clinical part). Topography and syntopia of the penis. In the adult, the penis is located in front of the pubic symphysis and is firmly fixed by the

Figure 2.
Figure 3.
Figure 2. Perineal region of a human embryo 11 mm long: 1-glans penis; 2-orificium urethrae ext.; 3-external meatus ridge; 4-raphe scroti et perinaei; 5-scrotum; 6-anus. (According to Corning.) Figure 3. Longitudinal section of a human penis 12 cm long: 1-praeputium; 2 and 6-epithelial invagination; 3 and 5-epithelial proliferation; 4-orificium urethrae ext.; 7-urethra; 8-corpus cavernosum urethrae; 9-corpus cavernosum penis. (According to Corning.) pubic bones of the penis is attached by means of the suspensory ligament of the penis (lig. suspensorium penis). Even further forward, starting from the rectus sheath and from the linea alba, goes a 'sling-like' ligament (lig. fundiforme penis) that encircles the penis in a loop. With the inner edges of the ischial and pubic bones, the penis is firmly fused with its cavernous bodies, the pointed ends of which (crura penis) fuse with their tunica albuginea with the periosteum of the mentioned bones. The density of fixation is maintained by the muscles surrounding the cavernous bodies (m. ischiocavernosus). In the middle part, the muscle is thick, fleshy, and in the anterior and posterior parts, it is tendinous. Attaching to the ischial bones, it is directed to the dorsum of the penis and passes into the tunica albuginea; by stretching the latter, it contributes to erection. A similar in function muscle, the bulbocavernosus (m. bulbocavernosus), covers the free surface of the bulb of the urethra and is in connection with the fibers of the external sphincter of the anus (fig. 4 and 5). The bulbocavernosus muscle begins at the tendinous raphe of the urethra, its fibers go forward and upward, encircling the body of the penis and ending on its dorsum, in its fascia, which covers the penis with its vessels and nerves. Deeper than the fasciae lies the thick tunica albuginea (tunica albuginea corporum cavernosorum), which covers both cavernous bodies. At their junction, it forms
a layer, a partition (septum penis) (fig. 6). In the groove between the anterior-upper parts of the two connected cavernous bodies of the penis (sulcus dorsalis penis) passes the dorsal vein and 2 arteries and nerves of the same name. Along the posterior-lower part of them in a deep groove (sulcus urethralis) is located the cavernous body of the urethra, on the posterior part of which a longitudinal groove is noticeable; in the cavernous part it corresponds to a poorly expressed partition of the bulb of the urethra (septum bulbi urethrae). Blood and lymph supply. The penis is richly vascularized. It receives arterial blood from the internal pudendal artery (a. pudenda interna), from which the artery of the penis (a. penis) departs, giving the following branches: the artery of the bulb of the urethra (a. bulbi urethrae), the artery of the urethra (a. urethralis), the deep artery of the penis (a. profunda penis) and the dorsal artery of the penis (a. dorsalis penis) (fig. 6 and 7). The two dorsal arteries of the penis go under the fascia along the dorsal side of the penis. They are the main arteries of the glans of the penis. On their way, these arteries give off branches in the form of rings surrounding its cavernous bodies; in the latter they anastomose with the branches of the deep artery. The latter go, included in the cavernous bodies, to
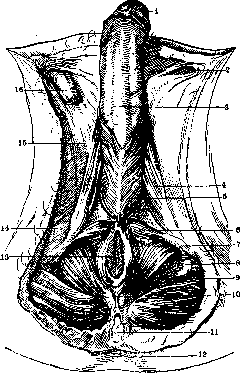
Figure 4. Muscles of the penis: 1-glans; 2- annulus inguinalis subcutaneus; 3-fascia penis; 4-m. ischio-cavernosus; 5-m. bulbo-cavernosus; 6-m. transversus perinaei superficialis; 7-m. le-vator ani; 8-fascia obturatoria; 9-fossa ischio-rec-talis; 10-lig. ano-coccygeum; 11- os coccygeum; 12-foveola coccygea; 13-anus; 14-tuber ischiadi-cum; 15-fascia lata; 16-funiculus spermaticus. (After Spalteholz.)
the anterior end of the penis. During their passage the arteries open into the cavities of the cavernous bodies (see Cavernous).-The veins of the penis are divided into deep and superficial; the latter are located outside its fascia (figure 7); from the root of the penis they go outward and empty into the great saphenous vein. The deep veins, anastomosing with the superficial ones on the glans of the penis, in general correspond to the arterial trunks and flow into the internal pudendal vein (v. pudenda interna). The dorsal vein of the penis (v. dorsalis penis) should be especially highlighted, passing in the groove of the same name (see above). The dorsal vein, being the main vein of the penis, lies between the two dorsal arteries and, passing through the urogenital diaphragm, carries blood into the venous plexus of the bladder (plexus venosus vesicae).-Trunks of superficial lymphatic pathways are formed from plexuses in the prepuce and flow into the inguinal lymph glands. The superficial dorsal trunk can directly through the inguinal canal connect with the pelvic iliac glands. Deep lymph. vessels form a dense network on the
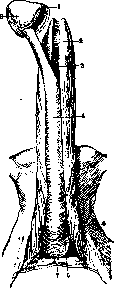
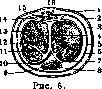
Figure 5.
Figure 5. Corpora cavernosa penis: 1-corona glandis; 2-corpora cavernosa penis; 3-lying of the cavernous body of the urethra (4); 5-m. ischio-cavernosus; 6-bul-bus urethrae; 7-trigonum urogenitale; 8--glans penis. (After Spalteholz.) Figure 6. Cross-section of the penis: 1 - v. dorsalis penis cutanea; 2-skin; 3-tela subcu-tanea; 4-septum penis; 5-fascia penis; 6-tela subfascialis; 7-tunica albuginea; 8-urethra; 9- corpus cavernosum urethrae; 10-v. circumflexa penis; 11-trabeculae; 12-a. profunda penis; 13- corpus cavernosum penis; 14-n. dorsalis penis; 15- a. dorsalis penis; 16-v. dorsalis penis. bed of the penis and at corona glandis "flow into a ring-shaped trunk. The latter on one side communicates with the superficial network of lymph vessels of the prepuce, on the other it passes
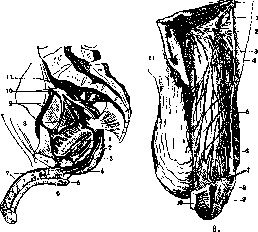
Figure 7.
Figure 7. Vessels of the penis: 1-m. levator ani; 2-m. obturator int.; 3-a. pudenda int.; 4-tuber ischiadicum; 5-aa. bulbi urethrae; 6-a. profunda penis; 7-a. et v. dorsalis penis; 8-a. obturatoria; 9-a. et v. iliaea-ext.; 10-a. et v. hypogastrica; 11-a. et v. iliaca communis. (After Corning.) Figure 8. Nerves of the penis: 1-lig. suspenso-rium penis; 2-n. dorsalis penis; 3-v. dorsalis penis; 4-a. dorsalis penis; 5-cutis; 6-penis; 7- sulcus coron.; 8-praeputium; 9- glans penis; 10- frenulum praeputii; 11-funiculus spermaticus. (After Spalteholz.) into the deep lymph trunk, which together with the dorsal vein goes to the root of the 5. M. E., t. XXVI. penis and flows either into the inguinal or into the external iliac lymph glands.-Nerves of the penis. The main nerve of spinal origin for the penis is the dorsal nerve of the penis (n. dorsalis penis), originating from the common pudendal nerve (fig. 8). Separating from the latter and passing through the urogenital triangle, the dorsal nerve supplies the skin of the dorsal, lateral, and lower parts of the penis, and only a small dorsal part of it is innervated by the ilio-inguinal nerve (n. ilio-inguinalis). Sympathetic fibers for the cavernous plexuses go from the prostatic plexus as part of the major and minor cavernous nerves (nn. cavernosi penis major et minores). The latter, penetrating into the cavernous bodies, anastomose in the area of the glans with the terminal branches of the dorsal nerve of the penis. Its muscles are innervated by branches of the pudendal nerve.
R. Richter. Pathology. The embryonic development of the penis from the genital tubercle (see Genital organs) is quite complex, and a stop in the development of one or another detail leads to congenital malformations. The formation of the glans of the penis is especially complex, therefore developmental anomalies are observed here more often. In relation to the prepuce, it is necessary to note its narrowing (congenital phimosis) and the fusion of its inner leaf with the surface of the glans of the penis (synechiae). These synechiae in the first years of life are not strong, but over time such an intimate fusion occurs that bloody intervention is required.--Hyper-trophic development of the prepuce gives it the appearance of a hanging, long trunk-like appendage. This form of the preputial sac leads to retention of smegma and urine in it and can be the cause of inflammatory processes (see Balanitis and balanoposthitis). Both with narrowing of the prepuce and with its hypertrophy, circumcision is recommended. Synechiae in the initial stages are easily destroyed by spreading the leaves with a probe, later with stronger fusion, circumcision is required.--Dunziger described a case of absence of the glans of the penis with normally developed other parts of it. There are descriptions of complete absence of the penis and its insufficient development. These defects of the penis are combined with other congenital anomalies: deep hypospadias and so-called pseudo-hermaphroditism (see).-Duplication of the penis has been described by a number of authors. It can be complete (diphallus) or partial, when two glans develop on one shaft. In the first case, independent cavernous bodies and functioning urethras can be developed in both organs Figure 9. Duplication of the penis.
(fig. 9).--Abnormal location of the penis on the perineum was described by Meyer (Meyer). Artificial malformations of the penis are found in some semi-wild tribes. Thus, according to descriptions by Miklukho-Maclay, among the natives of the group of islands of Borneo, a tunnel is made through the thickness of the glans of the penis and through it all sorts of ornaments are inserted. These malformations

have on the one hand "cosmetic" purposes, on the other hand they serve as a means of increasing orgasm in the partner during sexual intercourse. Acquired malformations include complications associated with the performance of ritual circumcision, if it is performed without precautions. There are cases of amputation of the glans of the penis, adhesions of the remnants of the prepuce with the glans with the formation of a tunnel under the preputial leaf, etc. (fig. 10 and 11) (Steinberg). Shortness of the frenulum of the penis leads to its tears


during coitus, to the downward bending of the glans of the penis during erection and always keeps the glans hidden under the prepuce, which in turn can lead to inflammations of the preputial sac. Shortness of the frenulum is eliminated by its incision with the application of one or two stitches.-As for the size of the penis, abnormally small size occurs in eunuchs. In mature age, their penis corresponds to the penis of a child of 6-8 years. The practical physician often has to decide on the sufficient size of the penis for sexual intercourse. The question is resolved by determining the ability of the penis to sufficient erection. Complaints about excessive size of the penis (megalo-penis) are heard less frequently, which can lead to disruption of married life. Mkrtchyan noted this anomaly, which was inherited, in a father and two sons.-With hypospadias of the penis and shortness of the urethra, the penis is bent downward and pulled toward the scrotum. When straightening it, a fan-shaped fold of skin stretches between the lower surface of the penis and the scrotum, resembling a palm leaf. Hence the name penis palmatus (fig. 12.) With this malformation, the penis cannot straighten during erection to a normal position. For treatment purposes, it is necessary to incise this fold with the application of stitches.-Inflammatory processes occur either on the skin coverings of the penis or in the cavernous bodies (see Balanitis and balanoposthitis, Cavernitis).
Of the skin diseases of the P. ch., Herpes progenitalis, s.prae-putialis, is most frequently encountered. At first, a limited redness with intense itching and burning appears, followed by the eruption of vesicles with clear content. The vesicles either dry up and become covered with a crust or burst and leave behind erosions. The etiology is not clarified: dietary disturbances with an excess of spices, diatheses-uraturia and oxaluria, trophoneuroses, etc., are presented as causes of the disease. Treatment consists in maintaining cleanliness and the application of drying agents (starch, talc, bismuth ointment). Simultaneously

Figure 12. Penis palmatus.
general treatment is indicated: arsenic, quinine bromide, etc.-The course of erysipelas of the P. ch. does not proceed as it does on other areas of the skin. Here, due to the looseness of the subcutaneous tissue and the thinness of the skin, the vesicular form predominates with extensive edema of the subcutaneous tissue and subsequent partial or widespread gangrene of the skin. The treatment of erysipelas is the usual, but in case of marked edema, early incisions of the skin prevent gangrene. - Phlegmonous processes of the P. ch. are a complication of infectious diseases-typhus, smallpox, etc. Very often, injuries to the P. ch., especially instrumental injuries to the urethra, are the cause of urinary phlegmon of the P. ch. Treatment is surgical-wide incisions of the phlegmonous areas. - Lymphangitis of the P. ch. is usually observed in gonorrheal infection of the urethra and inflammations of the prepuce. They are localized on the lateral surfaces of the penis, then extend to its dorsal surface and often spread to the inguinal lymphatic glands. Symptoms: visible or palpable cords, redness of the skin, edema, signs of phimosis. Treatment- compresses with lead water or Burow's solution at first, then warm sitz baths with potassium permanganate. Thrombophlebitis of the P. ch. The etiology of these remains unexplained. Clinically, on the dorsum of the penis over a certain extent, a dense, painful cord can be palpated, not sharply demarcated from the surrounding tissues. The local manifestations are the same as in lymphangitis. The general condition of the patient does not suffer, but sometimes the pain compels one to seek medical help. Sometimes after the acute phenomena subside, a prolonged edema of the P. ch. remains. Treatment in acute cases-ice, warm compresses, baths, in chronic state-surgical excision of the bundle of obliterated veins, ionotherapy (Zilberman).-Thrombophlebitis of the cavernous bodies-see Caverpit.-Gangrene of the P. ch. can accompany all inflammatory processes. Its etiology does not differ from the etiology of gangrene of other parts of the body. The so-called spontaneous, idiopathic, or spontaneous gangrene (gangrene foudroyante spontanee) is observed much less frequently. Its etiology is not established. The disease develops predominantly in young and completely healthy people, sometimes without any visible causes, more often after a vigorous sexual act. It is associated with infectious diseases of local and general nature. Spontaneous gangrene is localized in the skin and subcutaneous tissue of the penis, extending from here to the scrotum. The cavernous bodies of the penis and the glans are affected less frequently. The course of the disease is severe, having the character of pyemia or septicemia: with high temperature and severe general condition (loss of consciousness, delirium, vomiting) within a few hours (24-36) the skin of the penis swells, at first it reddens, then quickly turns black and is separated by a demarcation line. Then the necrotic areas fall off and the defects are filled with scar tissue. Despite the severe course, the prognosis is favorable: according to the statistics of Dieulafoy, out of 27 cases only 2 ended in death from erysipelas. In 7 cases, necrosis involved the glans of the P. ch. and part of the cavernous bodies, in 20 cases necrosis was limited to the skin only. Treatment-early incisions with removal of necrotic skin areas and further treatment by the usual methods for purulent wounds.-Chronic changes of the cavernous bodies of the penis-see Induratio penis plastica. Injuries to the P. ch. can be closed and open. The effect of trauma on a flaccid penis is significantly weaker than on an erect one. In the first case, the P. ch. easily escapes the traumatizing object. In the second, trauma easily causes rupture of the cavernous bodies, which bears the obsolete name of fracture of the penis. The case histories of causes of fractures of the P. ch. (fractura penis) are very diverse: vigorous sexual act, incorrect position during it, compression by hand during masturbation or to stop erection, blow with a fist to straighten the penis, sharp turns onto the abdomen with an erect penis, blow with a hard object-hoof, horn, etc. At the moment of rupture, the patient feels a crack, sharp pain, and the erection ceases immediately. Very quickly, swelling of the penis develops from the extravasated blood, blue-purple spots appear on the skin, imbibition of the extravasated blood into the tissue of the scrotum, perineum, and pubis occurs. The penis changes its shape: it elongates, curves to one side or another at an angle. In the thickness of the cavernous bodies, crepitus, a defect of tissue, and a hematoma can be palpated. With simultaneous rupture of the urethra, the picture of urinary infiltration is added (see Urethra). The hemorrhage gradually resolves, the edema disappears, but a dense infiltration remains with subsequent scarring and obliteration of the corresponding cavernous body. The consequence of this is a curvature of the P. ch. toward the side of the injury, and the erection is not complete, only up to the site of the fracture, while the segment of the penis in front of it does not become erect. Treatment: emergency operation-incision, removal of blood clots and suturing of the tunica albuginea, then resorbent agents-heat, iodine preparations, ionotherapy. Dislocation of the P. ch. is rarely observed. Among etiological factors are vigorous sexual act, especially in unnatural position-standing, sitting, with the partner on top, as well as strong counter-thrusts with an erect penis. For dislocation of the P. ch. to occur, rupture of the dense cords that connect the roots of the P. ch. to the pubic bones and rupture of the lig. suspensorii penis, which attaches the penis to the pubic symphysis, are necessary. In dislocation, the root of the P. ch. may shift into the thickness of the fasciae and cellular tissue of the perineum and scrotum or under the skin of the pubis. Usually, this is accompanied by avulsion of the skin along the line of the sulci retroglandularis and, as it were, scalping of the shaft of the P. ch. The diagnosis is based on the abnormal position of the P. ch. and the avulsion of the skin, in the sac of which no resistant tissues of the penis are found. Treatment: reduction of the P. ch. through the wound, suturing of the skin wound, exposure of the torn ligaments and fixation of the ruptures with sutures.-Strangulation of the P. ch. The case histories of these are very extensive: both constriction with thread, cord, tape, and the placement of ring-shaped objects (metal rings, nuts, etc.) on the P. ch. are observed. Their purpose is to create an obstacle in urinary incontinence and pollutions, masturbation, enhancement of erection, orgasm, etc. In childhood, such injuries are associated with mischief and pranks. The consequences of strangulation depend on the force of compression and its duration and gra- 11
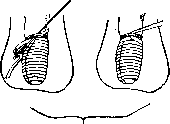
Fig. 13. Liberation of the penis from a constricting ring. [They] range from circulatory disorders and edema to complete gangrene of the peripheral segment. Treatment consists of the fastest possible removal of the constricting ring. With metal rings, one has to resort to the help of a locksmith. Sometimes, a reduction in edema is achieved by bandaging the peripheral end of the penis (Fig. 13). Open injuries of the penis. Lacerated wounds of the penis are usually wide, because the skin has loose subcutaneous tissue, which, upon rupture, contracts and pulls back the edges of the wound. Treatment: suturing. With aseptic suturing, the wound heals; with suppuration and subsequent scarring, defects are created, due to which erection may be hindered. Contused, crushed, and bite wounds of the penis are dangerous not so much for their size and blood loss, but for the involvement of the cavernous bodies and the urethra in the process. Since these wounds are usually infected, healing proceeds with inflammatory infiltration and scarring, which subsequently impairs one or another physiological function of the penis. Puncture and incised wounds of the penis are either accidental or inflicted by the mentally ill, as well as for religious reasons. There are descriptions of cases of complete amputation of the penis in a fit of jealousy (see Castration) or psychosis. Gunshot wounds are not uncommon during war. They may affect only the penis, but more often the wound also involves the urethra and is combined with damage to the scrotum, bladder, and pelvis. In treatment, the main attention should be paid to the state of the urinary tract (see Urethra and Urinary bladder—wounds of the urinary bladder). Burns and frostbite are considered injuries of the penis. Although these types of injuries are mostly casuistic, they must be taken into account due to their consequences. After burns, most often from boiling water, involving the penis and the surrounding skin, large cicatricial defects develop, impairing the physiological functions of the penis. Therefore, in the treatment of burns of the penis, the primary concern should be the elimination of subsequent scarring (skin grafting and plastic surgery). With careless care and treatment, cases of adhesion of the penis to the skin of the pubis (Steinberg) or the scrotum have been described. Here, plastic interventions are inevitable for the purpose of correcting the position of the penis. The same must be said about frostbite of the penis. In a clinical sense, both injuries can have all degrees, as in other parts of the body. Treatment methods are standard. Stones of the preputial sac. When it is impossible to open the glans of the penis and there is a lack of hygienic care for the preputial sac, an abundant amount of smegma and desquamated epithelium accumulates in its cavity. These masses become impregnated with urine and its inorganic salts and cause the formation of stones. Majocchi divides them into: 1) concretions of hardened smegma (smegmolithen) of a horny or waxy consistency, consisting of hyalinized or keratinized epithelium, fat, mucus, and a small amount of salts; 2) true stones (balanolithen), autochthonously formed from urinary salts or retained in the preputial sac while passing from the urinary tract; 3) mixed forms, described by Zahn, consisting of smegma and calcium salts. The number of stones varies: from single ones to dozens and a whole collection with a total weight of 540 g. The patient's complaints amount to sensations of itching, pain, and a feeling of pressure on the glans of the penis. Palpation through the preputial sac gives a sensation of nodularity and dense formations in the cavity of the prepuce. Prophylaxis consists of washing the preputial sac and removing excess smegma. Treatment consists of removing the stones, and if it is impossible to open the glans, a phimosis operation is performed. Neoplasms of the penis can be benign and malignant. The former include cystic formations developing from detached epithelium on the glans of the penis or on its lower surface. The size of the cysts is from a poppy seed and larger; their walls are thin and smooth, and whitish or yellowish contents shine through them. The cysts are usually tense and do not collapse upon pressure. Their contents are of a mucous nature. Besides these purely mucous cysts, cysts of the dermoid type are observed in the same areas. Their size is significantly larger—up to a cherry and larger. Their contents are thick, porridge-like. Treatment of cysts is surgical. Small cysts can be opened with a scalpel, and then their lining is cauterized with a thermocautery. Larger cysts require enucleation together with the contents and the lining, which is performed very easily, as they are not adherent to the surrounding tissues. Other benign tumors—atheromas, lipomas, fibromas, enchondromas of the cavernous bodies, etc.—are encountered significantly less frequently (more often on the prepuce). They are diagnosed on the same grounds as in other areas of the skin and are treated by standard surgical methods. Angiomas, lymphangiomas, varicose veins, and cavernomas are rare diseases of the penis. Their diagnosis is not difficult, as the skin of the penis is very thin and elastic, the subcutaneous tissue is loose, and all these formations shine through the skin quite well and are easily palpable. It must be kept in mind that even small vascular tumors can cause profuse bleeding under the influence of increased blood flow during erection and sexual intercourse. Therefore, even with their insignificant size, their excision is indicated. Neoplasms of the skin of the penis can develop in the form of keratoses up to and including the formation of a cutaneous horn. Gonorrheal keratoses provide a specific form (see Keratoses—gonorrheal keratoses). A cutaneous horn usually develops on the glans of the penis. In appearance, it resembles a hypertrophied nail, dark brown in color; its convex surface (Figure 14. Condyloma acuminatum) is dense and striated with grooves, the concave one is of a more fragile consistency. The size depends on the neglect of the case. Histologically, in a cutaneous horn, hyperplasia of the epithelium is observed with a tendency for its strands to grow into the underlying tissues. Hence, the transformation of a cutaneous horn into an epithelioma is not uncommon. Therefore, in the case of a cutaneous horn, surgical intervention is indicated, and not only the horn but also a certain area of healthy tissue in the vicinity must be removed. Especially frequent, both on the glans of the penis and on the inner layer of the prepuce, are growths of pointed condylomas—condylomata acuminata (Fig. 14) (see Wart). Among malignant neoplasms, cancers of the penis are the most frequent. According to statistics, they account for up to 3% of all cancerous diseases and up to 5% of cancerous diseases in men. The localization of cancer is most frequent on the glans of the penis and on the inner layer of the prepuce. Observations by a number of authors have established that the presence of phimosis predisposes to the development of the cancerous process. Among other etiological factors, injuries, warty growths, psoriasis, and leukoplakia, frequent contamination (chimney sweep's cancer), and venereal diseases with localization on the glans and prepuce are noted. Kaufmann distinguishes papillary cancers and infiltrating ulcerative forms. Cancer begins in the form of an induration, a nodule, a warty growth, or an abscess. Subsequently, if a papillary form develops, delicate or coarse villi grow very quickly. At this stage, they are similar to condylomata acuminata, but the base of the tumor is infiltrated and dense. The similarity to pointed condylomas is sometimes so striking that only a histological examination provides an exhaustive answer (Mayants). For a biopsy, it is necessary to take pieces from the base of the tumor. The growth of papillary cancers is very rapid; they have a great tendency to destroy both the tumor itself and the organ from which they began to grow. Infiltrating ulcerative cancers are encountered less frequently. They begin in the form of an ulcer (at the site of some abrasion), an induration, or a nodule. The ulcer increases rapidly; its edges and base are indurated due to the development of an infiltrate. The surface of the ulcer is whitish-gray in color; in the center of the ulcer, softening develops rapidly, and thick, foul-smelling pus is discharged from the tumor, as if from a sponge. The ulcer bleeds very easily. In this form of cancer, the infiltrating tendency prevails, and growths are not pronounced. In the initial stage, both forms do not cause pain, proceed unnoticed, and attract the patient's attention in the stage of full development. The general course of cancer of the penis is benign. Metastases in distant organs are rare. Cases have been described where cancer of the penis lasted up to 10 years. It should be noted that in cancer of the penis, the inguinal glands enlarge very quickly, but this enlargement is more often associated with secondary infection than with the transfer of the tumor to the lymph glands. Nevertheless, cases of metastases both to the regional inguinal glands and to distant organs are not excluded. Individual cases of cancer of the penis having the character of Paget's disease (see Mammary gland) have been described. Treatment of cancer of the penis in the initial stages yields good results. Here, the use of radio- and radiotherapy is possible with positive success, especially from the former. If these methods fail, amputation of the penis within healthy tissues is resorted to. The lymph glands of the groin, even with the slightest induration or enlargement, must be enucleated.
In view of the fact that the tunica albuginea of the corpora cavernosa of the penis stubbornly resists the spread of cancer to it, one rarely has to resort to complete excision of the penis when the tumor is localized on the glans. If, however, the process has extended to the scrotum and inguinal glands, an operation of complete emasculation is necessary. After the operation, despite its favorable outcome, systematic X-ray irradiation of the surgical field and the surrounding area is necessary. Among other malignant tumors of the penis, sarcomas, melanosarcomas, and endotheliomas of the corpora cavernosa are encountered significantly less frequently. All these forms grow very rapidly but do not affect the skin coverings. In contrast to carcinomas, metastases are more often observed with them, both in the regional glands and in the internal organs. Clinically, these tumors appear as nodular or spindle-shaped tumors of a dense (up to cartilaginous) consistency. Treatment is amputation of the penis. Recurrences are very frequent despite surgical intervention. A separate category of diseases of the penis should include priapism (see). Operations on the penis. The operation for straightening the penis in cases of hypospadias and penis palmatus is very simple. The penis is pulled upward by the glans, and all tissues that fixed the penis downward are stretched. Their dissection reaches the tunica albuginea of the corpora cavernosa. The urethra then retracts posteriorly, and a rhomboid wound forms on the lower surface of the penis, which is sutured in the longitudinal direction. Amputation of the penis (Figure 15) can be performed under local anesthesia. The latter is carried out using the infiltration method at the root of the penis. A rubber tourniquet is applied at the root of the penis. The penis is pulled by the glans, and the skin and subcutaneous tissue are dissected with a circular incision down to the tunica albuginea of the corpora cavernosa. The urethra with its corpus cavernosum remains untouched. The skin is pulled toward the root of the penis, and both corpora cavernosa are dissected at its border. Ligatures are applied to the vessels (dorsal superficial and deep arteries and veins). Then, the incision of the corpora cavernosa is covered with catgut sutures passing through the tunica albuginea and the septum between the corpora cavernosa. The urethra is severed at a distance of 1.5-2 cm anterior to the stump of the corpora cavernosa, the lower wall of the urethra is incised longitudinally for 1 cm, and the mucosa of the urethra is sutured to the nearest areas of skin. After this, the remaining skin defect is sutured in the sagittal direction. The operation of emasculation (complete removal of the penis and scrotum with its organs) is performed for deep lesions of the penis and scrotum caused by cancer, phagedenic chancre, etc. The skin incision is made from the external opening of the inguinal canal on one side to the other
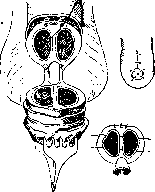
Figure 15. Amputation of the penis.
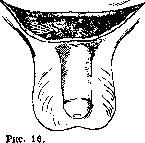
Complete emasculation (I).
with a convexity downward. From the ends of the performed incision at the root of the scrotum, two lateral incisions are made, which meet under the scrotum. The spermatic cords are isolated and ligated at the inguinal canal. The lymph glands are excised. From this incision, the entire scrotum with its contents can be removed. The penis is severed in the following order: first, the suspensory ligament of the penis is cut under the pubic bone, the vessels of the penis are ligated here as well, then the corpora cavernosa are separated by blunt dissection or excision from their attachments to the pubic and ischial bones. The urethra is dissected from the penis for some distance, severed, split along the lower wall, and sutured in an unfolded state into the skin wound. After suturing the skin, a T-shaped suture is obtained (Figures 16, 17, and 18). In cases of large skin defects, which, upon healing by scarring, cause shrinkage or curvature of the penis and impair its physiological function, it is necessary to resort to plastic surgery involving skin grafting. Here, it is possible to take a free skin flap from the preserved preputial sac according to the Dittel method - posthioplasty (posthioplastica). The skin of the prepuce is severed

Figure 17.
Complete emasculation (II). with a circular incision from the side of the defect, the outer and inner layers are split, and the edge of the outer layer is sutured to the edge of the healthy skin, previously severed with a circular incision. The inner layer of the prepuce remains at its natural attachment in the sulcus retroglandularis. Reich proposed an operation for closing skin defects of the penis using a flap from the scrotum - phalloplasty (Figure 19). On the anterior surface of the scrotum at the level of the defect, two horizontal incisions are made, the skin of the scrotum is separated, and the penis is passed into the formed tunnel. The edges of the healthy skin at the border of the defect are freshened, and the scrotal flap is sutured to them. After 10-12 days, when the flap has adhered to the skin defect of the penis, the edges of the flap are severed with parallel vertical incisions and sutured with a longitudinal suture on the lower surface of the penis. In case of insufficient scrotal skin, this operation can be performed according to the Bessel-Hagen method (Figure 20). Here, a flap is cut from the skin of the pubic area. The first incision is made directly above the root of the penis, and the second higher up, as needed. The penis is also passed into the tunnel, but in an upward direction. After separating the flap, the final suture will fall on the upper surface of the penis. The skin defects remaining after either operation on the scrotum or the pubic area are closed by tightening or by transplanting a flap from adjacent areas. In cases of fresh wounds, one can proceed to the skin grafting operation immediately; with old granulating wounds, it is necessary to wait until the wound is cleansed and covered with healthy granulations.
Figure 18. Complete emasculation (III).
Figure 19. Replacement of penile skin.
Figure 20. Formation of a bridge flap from the abdominal skin according to Bessel-Hagen.

For the penis, it is necessary to combat erections, which is achieved
by prescribing bromides, camphor monobromide, and injections of morphine or Pantopon. V. Ilyinsky.
Related articles
Mentioned in
Cite this page
“Penis.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/penis/