Panaritium
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Soviet Great Medical Encyclopedia discusses panaritium (felon), covering its various non-specific purulent infections of the fingers, clinical manifestations, anatomical features, occupational hazards, and surgical and conservative treatment methods.
Encyclopedia article (1928–1936)
PANARITIUM (panaritium), all non-specific purulent processes of the fingers. Not a single organ of the human body is subjected to such frequent injuries and diseases as the human hand. According to Klyucharev, 43.4% of the total number of all injuries in physical laborers involve the hands, with fingers accounting for 32.4%. The entrance gates for infection here are visible and invisible damage to the skin, which open lymphatic clefts or subcutaneous tissue. The most dangerous among these are puncture wounds, splinters, as well as torn or bitten wounds. Based on existing observations, the possibility (Kanavel, Melchior) of bacteria penetrating deeper through the numerous openings and ducts of the sweat glands, with which the palmar surfaces of the fingers and hand are abundantly supplied, cannot be excluded. Even minor injuries to the fingers (abrasions, cuts, scratches, hangnails, prickets, etc.), when treated inattentively and with continued contact with infected material, cause suppurative processes that put workers out of action. In a number of cases, panaritium must be considered an occupational disease. Well-known are the panaritiums of slaughterhouse workers, sausage production workers, cooks, female domestic workers, and fish industry workers (bone prickets), etc. Characteristic of agriculture are panaritiums in persons tending domestic animals (e.g., milkmaid's panaritium). Finally, everyone knows the malignant panaritiums of anatomists, radiologists, surgeons, and medical personnel dealing with purulent patients and purulent dressing material. Staphylococci and streptococci are predominantly found as pathogens. Much less frequently, pneumococci, gonococci, Escherichia coli, diphtheria bacilli, Bacillus proteus, Bacillus pyocyaneus, and others have been encountered. There is no unity of views in the classification of panaritium. When divided by the anatomical principle, 5 groups are obtained: I. Cutaneous panaritium, II. Subcutaneous panaritium (p. subcutaneum), III. Osseous panaritium (p. ossale), IV. Tendinous panaritium (p. tendinosum, s. tendovaginitis), V. Articular panaritium (p. articulare). The palmar surface of the fingers and hand is actually the "working" grasping and holding surface, adapted for grasping and holding objects of the most varied density, and three facts of great practical importance should be taken into account here: a) with the powerful development of the epidermal layer on the palmar surface, it is difficult to rely on the spontaneous breakthrough of pus to the surface of the skin; b) the presence in the subcutaneous layer of peculiar "spring" devices in the form of dense connective tissue cords directed almost perpendicularly from the papillary layer of the skin inwards makes it difficult for the infection to spread in a plane parallel to the skin and, conversely, promotes the movement of bacteria inwards, i.e., to the tendon and bone. This essentially constitutes the peculiarities of the spread of panaritium. c) Due to the scarcity of loose tissue, the individual cells of which are tightly compressed between the connective tissue "springs," and the density of the tissues in general, circulatory disorders dangerous to individual tissues can rapidly set in. It should be borne in, mind that for a correct assessment, the normal state of sensitivity of the patient's fingers and hand, in particular pain and temperature, is important. Organic diseases of the spinal cord (syringomyelia, tabes dorsalis, etc.) can significantly affect the course and recognition of various forms of panaritium. Recently, there has been a tendency (Molotkov, Turner) to isolate the so-called panaritium neuriticum into a special group due to the primary disease of trophic nerves presumed at its base. However, such a proposal is still insufficiently substantiated. I. In cutaneous panaritium, hangnails—small traumatic ruptures or elevations of the epidermis in the periungual skin fold—deserve attention as an entrance gate. Cases of diverse infection of the fingers, especially in persons in contact with pus (surgeons, gynecologists, veterinarians before the widespread use of gloves), usually resulted from the presence of hangnails. Recently, dangerous consequences of manicure infection (Körbl) have also been reported, and the requirement to use sterile instruments during manicure has been put forward. Infection entering the skin of the finger can manifest in the form of a small vesicle filled first with seropurulent and then with purely purulent or bloody fluid. Bacteria, most often streptococci, are located here directly beneath the detached epithelium near the nail bed and are often the beginning of a severe general infection. Such dermatitis bullosa, accompanied by significant pain, sometimes a rise in temperature, and the appearance of lymphangitis, requires rapid surgical intervention, expressed in the careful shaving off of the entire blister and the elimination of all "pockets" where infection could subsequently harbor. After this, for final healing, the application of antiseptic ointment dressings for a few days is usually sufficient. Similarly, in subepidermoid abscess (abscessus subepidermoidalis), proceeding with the same clinical phenomena, the formed pus detaches the epidermis from the corium and accumulates there. Simple shaving off of the entire blister and a dressing with an indifferent ointment is sufficient, provided there is no tiny fistula in the center leading to a deeper-located purulent collection. Dermatitis, minor abrasions, and cracks around the nail bed especially often develop in confectionery production, when sweet food masses (liquid sugar, jam, confectionary dough, etc.), sticking to the fingers and drying out, cause cracks and ulceration of the skin and nail bed. These minor injuries are easily complicated by suppurative processes, panaritiums, and purulent dermatitis, taking the worker out of action for a long time. Constant inspection of workers' hands, gloves, and other protective devices are necessary. In stubborn cases, transfer to another job is required. Among cutaneous panaritiums, suppurative processes in the periungual fold (p. parunguale, s. paronychia, see Onychia) and in the subungual "space" (p. subunguale) are most common. Clinical phenomena in p. parunguale, s. paronychia are expressed in severe, throbbing pains in the tip of the finger, depriving the patient of rest and sleep, temperature rises to 38°, the patient feels broken and cannot work. In view of this, as soon as signs of infection appear, measures should be taken against its spread, which is sometimes successful. Hartel recommends gray mercurial ointment here. Also an effective remedy is the gentle detachment of the skin periungual fold covering it from the root of the nail and the very careful insertion beneath it with the sharp tip of a scalpel as a spacer of a narrow strip of gauze moistened in a 1% solution of Argentum nitricum. If the infection has already penetrated under the root of the nail and p. subunguale has developed, immediate removal of the rejected part or the entire nail in one sitting is indicated (Fig. 1). The most delicate dressings after this are strips of gauze moistened in liquid paraffin. Regeneration of the nail with its complete removal lasts 3-4 months. II. Subcutaneous panaritium usually develops on the palmar surface of the ends of the fingers and at the level of the phalangophalangeal-metacarpal joints. Anatomically and pathologically, subcutaneous panaritium appears as a local acute inflammation (redness, swelling, sensation of heat, and severe throbbing pain) with transition into purulent softening. Not only the dense tissue of the flexor side swells, but even more so the loose tissue on the back of the hand. The edema of the back of the hand can sometimes cause an erroneous localization of the process. The inflammatory process can easily pass to the tendon sheaths, to the bones, and cause lymphangitis and lymphadenitis. Symptoms of subcutaneous panaritium boil down to throbbing pain disrupting sleep, moderate fever, general malaise, loss of appetite, insomnia, and complete loss of working capacity. Treatment. Beginning subcutaneous panaritiums should be tried to be aborted with wet or alcohol compresses, which must be changed every 12 hours. Klapp considers the best treatment to be congestive hyperemia by applying a bandage to the finger itself, or better yet, to the shoulder. In cases where patients apply for panaritium not at the beginning, but already when a suppurative process is present, one has to resort to surgical treatment. At the same time, it is important to take into account three forms of lesion: in the first, dry form, there is no pus, but a peculiar dry necrosis, a "sequestrum" of soft tissues, is formed. A conventional incision is insufficient here: it quickly glues together and does not eliminate the dangers during subsequent purulent melting of the "sequestrum." Therefore, it is necessary to join authors (Klapp) who recommend dissecting out the area with dry necrosis (Fig. 2). In the second, most frequent wet form of subcutaneous panaritium, a simple incision is quite sufficient. A big mistake is to set indications for incision depending on the presence of fluctuation, which on the palmar surface of the fingers and hand can almost never be established with conviction. Therefore, incisions here often have a probationary character. After incisions of subcutaneous panaritium, neither tamponade nor drains are required. In the third, most malignant form, incision is contraindicated.
These are those especially life-threatening cases of infection when there is no clearly expressed local "formation" of the infection, when there is no pus, when the infection immediately generalizes through the blood or lymphatic system. Here, the necessary measures to save the patient are energetic local methods of active hyperemia, absolute immobilization of the entire limb with a Desault bandage with a load on the shoulder of the healthy side, and general therapeutic measures as for a general infection (see Pyemia). - In deep inflammatory processes of the fingers and hand, a warming compress is not advisable, as it enhances exsudation and increases hydrostatic pressure in non-compliant tissues. For the compress, a physiological solution or boiled water is desirable, because cases of soft tissue necrosis have been registered from all antiseptic agents, including Burrow's fluid, especially when the integrity of the skin is broken. - In the topical diagnosis of inflammatory foci of the fingers and hand, a button probe is convenient for palpating the skin, with which it is possible to establish the points of greatest pain with an accuracy of up to 1 mm. Palpation with a finger provides too large a contact surface and obscures the picture. III. If in ordinary acute osteomyelitis of tubular bones the process begins with the bone marrow, then in bone panaritium it happens differently. The infection, which has most often passed from infected and inflamed subcutaneous tissue or introduced through some insignificant puncture wound, goes from the outside inwards and initially affects the periosteum of the phalanx. With the development of the inflammatory process here, a necrotizing periostitis is first obtained with inflammatory thrombosis of the vessels nourishing the bone or their compression as a result of inflammatory "swelling" of the tissues, and further bone necrosis is already a consequence of the destruction of the periosteum vessels. In addition, the harmful effect of bacterial toxins on the bone is also important here. For the same reason, in bone panaritium there can be no formation of a sequestration box, because the periosteum perishes here in the first place. This form of panaritium is accompanied by very agonizing pain sensations, sleepless nights, and the entire clinical picture described above in subcutaneous panaritium. Already a single sleepless night due to severe pain is an absolute indication for surgery here. Most convenient in bone panaritium of the terminal phalanx is an incision in the form of the Russian letter G. Many authors turn it into a horseshoe-shaped one (Fig. 2) in order to turn away from the bone in the form of a flap all soft tissues. In the initial stages of bone panaritium, most often of the nail phalanges, it is more convenient, using bloodless techniques, to initially limit oneself to an incision to the bone and then wait for the spontaneous completion of sequestration. In advanced cases with the presence of fistulas, it is necessary to make wider use of X-rays in order to detail the boundaries of the entire area doomed to destruction. At the same time, it is important to take into account the pronounced anatomical isolation of the blood supply to the diaphysis and epiphysis of the phalanges, especially in growing individuals, thanks to which there is a full opportunity, by cutting the bone along the metaphysis, to preserve the bases of the phalanges. By a similar method on the terminal phalanx, it is possible to keep the attachment of the deep flexor intact and do without opening the interphalangeal joint and the distal pouch-recess of the tendon sheath. Thus, it seems possible to completely abandon undesirable exarticulations on the fingers of the hands. Bone panaritium can sometimes be complicated by septico-pyemia. IV. Of all forms of panaritium, purulent tenosynovitis presents the greatest danger due to its possible extensive spread, significant loss of function, and the threat of general infection. It develops either from direct traumatic damage to the tendon sheath or from the entry of infection from nearby purulent-inflammatory foci, e.g., from soft tissues, bones, joints. In the latter case, the infection is transmitted most often along the lymphatic pathways, but the destruction of the wall of the tendon sheath under the influence of pus enzymes is also possible. For a clear understanding of the picture of the disease, an exact anatomical understanding of the relationships of the tendon sheaths is necessary (Figs. 3, 5, and 11). The impossibility of predicting in advance the architectural variant of the tendon sheaths obliges the surgeon to observe the patient with great attention so as not to open yet uninfected sections during the operation (see Tenosynovitis). The timeliness of surgical intervention is of particular importance. Any incisions can be made, tamponed or not tamponed, but if days and sometimes even hours are missed, the death of the tendon is inevitable. The general condition in purulent tenosynovitis in most cases is sharply disturbed due to the existing febrile state, sometimes with shattering chills. At the same time, patients experience extremely intense pain. - The diagnosis of purulent tenosynovitis is not always simple. In the anamnesis, great importance should be attached to minor puncture wounds along the course of the tendon sheaths. Locally, it is possible to objectively establish an inflammatory painful swelling along the anatomical extent of the affected tendon, the forced position of the corresponding finger in a state of slight flexion, and pain upon pressure (with a button probe) along the course of the tendon sheath. The latter symptom is especially important in places corresponding to the upper or lower recess-dome of the tendon sheath, i.e., in areas remote from the entry gate of the infection. However, according to Sokolov's observations, the most reliable differential diagnostic sign of tenosynovitis should be recognized as the pain of passive extensions of the affected finger. This symptom should be elicited carefully, otherwise pain will also occur with ordinary phlegmon. If the disease is left to itself, all the described phenomena intensify until a rupture of the wall of the tendon sheath occurs with the outflow of pus into the surrounding tissues. After that, the feeling of inflammatory tension decreases, but new phenomena occur, depending mainly on the developing phlegmon of the palmar surface of the hand or forearm. Patients with purulent tenosynovitis require hospital treatment. With an established diagnosis, delay with an incision, not only in days, but even in hours, can lead to the death of the tendon. The continuous median incision along the entire length of the tendon sheath still used by some surgeons and the wrapping of the tendon with tampons must be abandoned, because such methods contribute to the falling out of the tendon into the subcutaneous tissue, its drying, cooling, and subsequent mortification or fusion with it, it must be covered with a piece of oilcloth or rubber, after which it is sometimes possible to save it (Gorodkov). When approaching purulent tenosynovitis surgically, the following conditions must be met: 1) ether anesthesia; 2) Vian's bandage on the shoulder for bloodless surgery according to Esmarch; 3) the presence of an assistant. Failure to meet at least one of these conditions puts at great risk
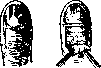

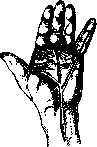
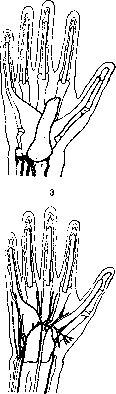
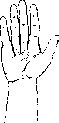
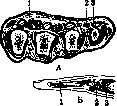


Figure 1. Incision in paronychia. Figure 2. Bivalve incision; on the left - outlining of the arced incision. Figure 3. Tendon sheaths. Figure 4. Incisions along the lumbrical muscles in phlegmon of the middle palmar space and along the interdigital fold. Figure 5. A - cross section through the heads of the metacarpal bones: 1 - fibrous barrier; 2 - lumbrical muscle canal; 3 - tendon sheaths; L - incision through the intermetacarpal space: 1 - subcutaneous tissue; 2 - fibrous barrier; 3 - palmar band of the lumbrical muscle. Figure 6. Arrangement of incisions in phlegmon of the tendon sheaths (according to Lesen). Figure 7. Vascular network. Figure 8. Arrangement of incisions for opening the tendon sheaths and pockets on the forearm. Figure 9. Incisions in tenosynovitis (the dotted line indicates the border of the synovial bursae). Figure 10. Incision in panaritium of the proximal phalanx extending to the palm (the dotted line indicates the line of the incision on the palm). Figure 11. Cross section of tendon sheaths: 1 - vagina fibrosa; 2 - vagina mucosa; 3 - tendon; 4 - mesotenon.
surrounding tissues. It is much more expedient to make separate lateral incisions on each phalanx (Bardenheuer, Bier, Klapp, and others), thanks to which the tendons remain covered by living tissues, i.e., they continue to remain in the moist chamber of the tendon sheath and at body temperature. Furthermore, the indicated incisions spare the palmar transverse creases of the fingers, which correspond to the flexion lines of the interphalangeal joints, and thereby reduce the possibility of the development of function-limiting scars. With lateral incisions, it is necessary to keep the main vessels and nerves undamaged, which can be seen during artificial bloodless surgery, otherwise, there is a threat of gangrene of the finger (Fig. 7). If for any reason the tendon is... the result of the operation. Until the tendon shines with its pearly luster at the bottom of a comparatively deep and bloodless wound, the surgeon cannot be certain that the tendon has been opened and cannot be certain of the diagnosis of tenosynovitis (Sokolov). On the hand, in cases of tenosynovitis and deep phlegmons, wide incisions are necessary with the ligation of the superficial palmar arch (Figures 4, 9, and 10).
In lesions of the ulnar or radial synovial bursae of the hand, incisions on the forearm corresponding to the location of these bursae are mandatory (Fig. 6 and 8). In tenosynovitis of the thumb, it is necessary to preserve as much as possible the motor branch (ramus muscularis) of the median nerve to the thenar muscles (m. opponens!). The function of the opponens pollicis muscle is considered even more important than the function of the flexor pollicis longus muscle. The forbidden zone for the knife in protecting the named nerve branch extends to one breadth of the thumb distal to the cutaneous projection of the transverse carpal ligament. Incisions in tenosynovitis may adhere. To prevent this, many methods have been proposed, up to and including special wooden and metal (Tiegel) spacers. Based on his observations, Sokolov believes that in purulent tenosynovitis, the most important thing is the timeliness and urgency of surgical intervention. Therefore, strips of paraffinized gauze or strips of rubber placed during the operation as spacers, but without contact with the tendon, do not cause harm. These strips are more conveniently placed in such a way that the "rim" of the opened tendon sheath is between them and the tendon. It is desirable not to change spacers of this kind until a stable drop in temperature to normal and not to introduce them anymore in the future.
The basic tenet of purulent surgery—not to proceed with the restoration of function until the danger to life has been eliminated—retains its significance in tenosynovitis as well. In restoring function, hot water or dry-air baths are important. For water baths, a physiological solution is best, because plain water promotes undesirable swelling of the tendons. Active movements of the fingers begin as early as possible, but it is impossible to establish definite periods here for all cases. In the prolonged struggle for the restoration of function in tendinous panaritium, the most important thing is the active self-activity of the patient. One bath or one session of passive gymnastics per day is of negligible importance compared to the active movements that the patient must perform himself. The active work of the patient must continue all the time he is awake. For this purpose, after the temperature has firmly leveled off, a very soft white rubber ball is bandaged in, as shown in Fig. 12. With proper enclosing of the ball by the fingers, the desired average physiological position of the fingers is achieved, and the continuity of the active work of the entire neuromuscular-tendinous-articular apparatus is ensured. If the patient is not educated in this direction, the task of restoring tendon function may be altogether unattainable.
Subsequently, after the healing of the wounds, it is necessary for several months to persistently apply massage, passive gymnastics, active performance of tasks, and exercise in special mechanotherapeutic apparatuses. In purulent lesions of the flexor surface of the hand and forearm, the subsequent scar-contracting process can cause deviation of the fingers and hand in a position of hyperflexion, which is disadvantageous for function in persistent contractures. To prevent this, special splints are proposed that hold the hand in the most physiological position of slight extension. It is simpler to use a plaster splint at an angle of 60°, to which the hand is bandaged, as shown in Fig. 12. As a result of the use of lateral incisions and modern methods of postoperative treatment, the function of tendons after purulent tenosynovitis can currently be preserved in 34% of cases (Sokolov). According to European and American data, the figure of preserved and functioning tendons can be increased under favorable conditions on average to 50%, and in very early cases even to 90% (Klapp).
From what has been said, it can be seen what enormous significance, along with preventive measures, the quality of the treatment itself has. A timely incision shortens the periods of treatment. Moreover, a correctly performed incision, while saving the tendon, saves the working hand and thereby saves the victim from disability. Proceeding from the political significance of reducing morbidity and restoring the working capacity of the worker, the preservation of tendons in purulent tenosynovitis acquires...
tassumes particularly vital importance. For this purpose, exact familiarity with modern methods of treating this disease (panaritium) is necessary for physicians at health posts, outpatient clinics, dispensaries, etc. Figure 12. treatment V. Articular panaritium (panaritium articulare, s. arthritis interphalangea). The greatest danger of infection penetrating into the joint occurs in wounds of the dorsum of the fingers and hand, where the thickness of the soft tissues from the skin surface to the joint cavity is only 2 mm. Frequently, the joint and bone become infected from the inflamed subcutaneous cellular tissue in the presence of subcutaneous panaritium. Clinical manifestations in articular panaritium consist of marked swelling of the joint, pain, and the general phenomena described above for other forms of panaritium. Purulent lesions of the joint are recognized on the basis of localized annular tenderness of the corresponding joint, as well as crepitating lateral movements in the abnormally lax joint. In early cases of purulent interphalangeal synovitis, one should try aspiration of pus and introduction of a few drops of rivanol (1 : 500). After arthrotomy through two lateral incisions along the edges of the extensor tendon, great benefit can be obtained from Bier's hyperemic bandage. In pronounced interphalangeal arthritis, if the tendon is preserved, early resection followed by active work by the patient sometimes even makes it possible to preserve some function of the joint. The performed resection as a rule requires immobilization of the finger with a plaster cast with the expectation of ankylosis, for which it is necessary to give the finger a corresponding average physiological position. After resection of the interphalangeal joints, the French school of surgeons, using a bandage with Peruvian balsam, leaves the plaster cast unchanged for at least three weeks (Iselin). With persistent contractures or ankylosis of the interphalangeal joints in the near future (not earlier than 3 months), operative mobilization of the joints is possible. All operations for suppurative processes of the fingers and hand must be completely painless. Local anesthesia by freezing with a jet of ethyl chloride with high pain sensitivity of the fingers does not achieve the goal. The scope of local anesthesia is limited to lesions of the terminal phalanx. All other interventions proceed under general ethyl chloride or ether anesthesia. 689 With simultaneous lesions of bones, joints, and tendon sheaths, i.e., in so-called pandactylitis, a short amputation on the proximal phalanx with preservation of the base of the phalanx is indicated. Operations of the exarticulation type should be fundamentally abandoned and should not find application in hand surgery. On the thumb, a stubborn struggle must be waged for every millimeter, since the loss of the thumb in human labor is equated almost to the loss of an eye. It should be remembered that immobilization of the fingers and hand is performed in a strictly defined position: in the wrist joint, a position of the hand in an extensor state at an angle of 60° is desirable (Fig. 12). The joints of the fingers are in flexion at an angle of 60°. The thumb in adduction against the III finger is semi-flexed in both joints and slightly opposed. The indicated positions are most advantageous in the event of possible persistent contractures or ankylosis of the fingers and hand. In the treatment of panaritium, starting from the first indications for incision, the attending physician must remember that he is dealing with a finger, i.e., with a working organ, upon the integrity of which depends not only the loss of working days during the treatment period, but also the loss of working capacity (disability) after the end of treatment. Both of these, with the correct organization of medical assistance, must be reduced to a minimum in the USSR. Prophylaxis. Labor processes associated with the possibility of frequent injuries and work in a humid infected environment require particularly careful protection both from the danger of injury and from further infection of an already received wound. Mechanization of production, especially in the field of the food industry and animal husbandry (e.g., electric milking, mechanical cleaning of fish, etc.), eliminating work with hand tools, distances the fingers from direct contact with infected material, thereby reducing the possibility of their injury. Protective devices—gloves, finger cots, etc.—must protect the hand and fingers from secondary penetration of infection into the wound in cases where the initial injury is so insignificant that the victim continues to work. It is the duty of the health post physician, studying minor traumatism in production, to prevent complications through correctly established prophylaxis. Prophylactic measures must proceed in two main directions: 1. In addition to reducing traumatic injuries to a minimum, measures must be taken to ensure that every injury to the finger, even the most superficial, is treated right there on the spot in an appropriate manner (tincture of iodine, bromferron, etc.). 2. After toilet of the skin wound, the finger is placed in a resting state and the patient is advised to stop work for a period of 1 to 3–4 days, depending on the case. By such measures, it is often possible to prevent the appearance of panaritium and return the patient to work as soon as possible.
Related articles
Mentioned in
Cite this page
“Panaritium.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/panaritium/