Morbidity
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the 1928–1936 Great Medical Encyclopedia defines morbidity as the registration of new, previously unregistered diseases in a population, contrasting it with general prevalence. It details the Russian and Western European statistical approaches, the role of medical consultations and dispensaries, and the methods of registration used in the Soviet Union.
Encyclopedia article (1928–1936)
MORBIDITY, a term understood as the accounting of new, previously unregistered diseases in a population (or in its individual groups) and indicating the movement of phenomena in contrast to the terms «prevalence» (see) and pathological involvement, which speak of the state of the phenomenon, i.e., the state of public health at a given time. Until recently, there was no strict demarcation between the terms morbidity and prevalence; in the classical works of the founders of Russian sanitary statistics (E. A. Osipov, P. I. Kurkin) and in the works of almost all Russian sanitary statisticians, the terms morbidity and prevalence are used synonymously. However, modern times, which have created new forms of medical care for the population (treatment-and-prevention - «dispensarization») and extremely expanded the field of sanitary-statistical research, have given rise to a new topic—the definition of the «pathological involvement» of the population—and urgently demand a precise demarcation of these concepts. This demarcation was proposed by S. M. Bogoslovsky (report «Scheme of Sanitary-Statistical Research in the USSR», approved at the conference of medical statisticians, 1927). In the matter of studying morbidity, there are two sharply defined directions formed on the historical basis of the development of the organization of medical assistance to the population: a) the Russian direction, representing the result of the development of public organization of medical aid (Zemstvo in pre-revolutionary Russia and Soviet at the present time) and placing at the forefront the study of the «general morbidity» of the population on the basis of their visits for medical help; b) the Western European direction, according to the scheme of which, outlined by Prinzing, the main sources of morbidity statistics are: 1) cause-of-death statistics, providing information on diseases ending in fatal outcomes (the accuracy of such statistics will be greater the more extensively autopsy control is carried out, i.e., the coverage of corpses by autopsies); 2) hospital statistics, providing materials distinguished by the comparative accuracy of diagnoses of diseases, their course, danger to life, complications, duration, etc.; 3) statistics of infectious diseases, which is legally mandatory for physicians in many states, sometimes according to a broad list of diseases; 4) statistics of diseases of individual population groups (army, navy, etc., or special unions and societies - sickness insurance funds). The most important significance belongs to the observations of insurance funds, relating to vast groups of population and extending to all diseases affecting working capacity. However, when representatives of Western European science became acquainted (through the work of P. I. Kurkin in the journal «Archiv für soz. Hygiene u. Demogr.») with the content of Russian sanitary-statistical research, a trend formed among them (represented by demographer H. Roesle) in favor of establishing the study of general population morbidity by a broad method. This opinion of Roesle is currently being submitted for discussion to the Statistical Council of Experts at the League of Nations. General mass morbidity encompasses all forms of diseases affecting a given population; when it comes to diseases singled out on one basis or another, they speak of special types of morbidity: epidemic morbidity, morbidity from social diseases, occupational morbidity, etc.; the purpose of studying morbidity is to determine the sanitary state of the population; morbidity, determined with possible accuracy and for a sufficient period of time, is considered the most essential and decisive criterion of the state of public health (E. A. Osipov). Morbidity is studied by the statistical method. The unit of research here is each new, previously unregistered disease for which the patient seeks medical help. Each such disease must be registered on a «statistical card» of diseases established for this purpose; these disease cards (also called outpatient cards) serve as the material for statistical processing and characterization of morbidity in numerical expressions. Determining the form of disease and designating it with a scientific, nomenclature-precise term can of course only be done by a physician; therefore, it is accepted that the statistical study of morbidity is based solely on observations ascertained by physicians. Observations of medical assistant (feldsher) personnel are processed only within the limits of the so-called reporting (on their activities). Since, further, only those cases of diseases can be registered for which the sick seek the help of an attending physician, out of the entire mass of diseases affecting the population, only a part of them registered by physicians actually falls into the field of observation; thus, in studying general morbidity, one deals actually only with «detected» morbidity, or with «consultation rates» for medical help, but not with «true» morbidity. With the development of medical care for the population, with the increase in its accessibility and the improvement of its quality, with the rise in the population's awareness of the value of health, the number of registered cases of diseases of course constantly increases, thanks to which «detected» morbidity increasingly approaches «true» morbidity (the so-called «exhausted» morbidity). The growth in the number of requests for medical help over time can be seen from the following example (Moscow Governorate): for 1898–1902, the consultation rate («detected» morbidity) was expressed here by a value of 635.6 per 1,000 population, in 1906–1908—759.3, and in 1926—1,116.8. Thus, morbidity is judged actually by the «consultation rate» and its constituent parts, while some part of the diseases remains unregistered for various reasons (distance from medical institutions, busyness, triviality of the disease, distrust of medical help, etc.). Despite this, however, researchers accept that on the basis of these medical observations, thanks to the accumulation of huge masses of them, one can judge the composition and character of «true morbidity». This is how the creators of morbidity statistics in Russia viewed the matter. Only modern times, which have established a new type of medical assistance in the USSR—specifically «treatment-and-prevention» assistance, which is a synthesis of therapeutic assistance and sanitary assistance established in the Zemstvo period—opens up prospects for studying «exhausted morbidity», at least for certain groups of population taken under so-called dispensary observation (see Dispensarization). This new direction in the organization of medical care also requires new forms of registration of medical observations, specifically those that would make it possible to take into account in chronological order for each person from the group taken under observation all individual cases of diseases affecting them over a known period of time. Since this group of individuals is under constant medical observation, the registration of its diseases in this case closely approaches exhaustiveness, and thus statistics gets the opportunity in the future to study already «exhausted», «true» morbidity in a precisely defined mass of people. Since the material for studying morbidity is the observations of physicians who treat patients applying to them for medical help, the requirement follows that the registration of these medical observations should have a correct statistical setup, that this registration should be entrusted as a general state duty to all attending physicians; that it should be «accurate, complete, systematic, and uniform», i.e., that observations should be registered directly at the moment of the patient's visit, that information should be entered in the full volume of the registration form and in precise expressions without introducing inaccurate and presumptive dates and definitions, that such registration should be conducted consistently, without omissions and in a standardized form. From this, the necessity is clear of establishing a uniform form and rules of registration, which should be applied by all physicians registering diseases. Such «General Rules and Forms of Registration» are currently published by the Central Sanitary-Statistical Commission under the People's Commissariat of Health of the RSFSR and are mandatory for all physicians of the Republic. The best and most convenient system of disease registration for the purpose of studying morbidity is the recording of information about observed diseases on cards, i.e., the so-called «card system» of registration—the system which, during subsequent processing of the material, makes it most easy and convenient to group it in any directions, guarantees greater accuracy of calculations and accelerates them, since cards can be distributed for calculations among several persons. Of course, the card for disease registration as a form of mass accounting must be brief; it should contain only the most necessary questions. The card adopted by the Central Sanitary-Statistical Commission under the People's Commissariat of Health of the RSFSR contains the following questions: No... Male, Female, Primary, Repeat, Uyezd (city)... Outpatient clinic... Year... month... day... 1. Surname... First name... Patronymic... 2. Age (years... months...) 3. Nationality... 4. Whereabouts: uyezd... city... volost... village... factory, yard (barracks)... other places... passerby, etc.... when arrived... 5. Occupation: occupation, position... detailed profession... student... schools. 6. Where he works: at home, at a factory (plant), in a workshop, on the railroad... Name of the factory (plant, etc.)... Department of the factory, shop, etc.... 7. How long sick... 8. Disease...
Doctor's signature... The main element of registration in this case is the disease; hence the necessity of using a single, universally accepted nomenclature of diseases. At the present time, we have adopted the international nomenclature approved by the International Statistical Congress of 1920 in Paris. In order that during the subsequent statistical processing of records, disease forms may be referred to specific groups and departments, a single, firmly established classification of diseases is necessary: this ensures the comparability of the processed materials and makes it possible to summarize homogeneous forms of diseases during compilation.
"Disease" is the result of the impact on a person of an extremely complex combination of the most diverse factors. It can be broken down into the following major categories. A. Factors of an internal order (inherent in the human organism itself—heredity, sex, age, race, physical development, etc.). B. External factors: 1) natural-general biological conditions and 2) conditions arising from the fact of human "sociality": a) social and domestic, and b) occupational. To study morbidity means to identify its causes, strength, nature, and consequently to reveal the pathogenic influence of the aforementioned factors on public health.
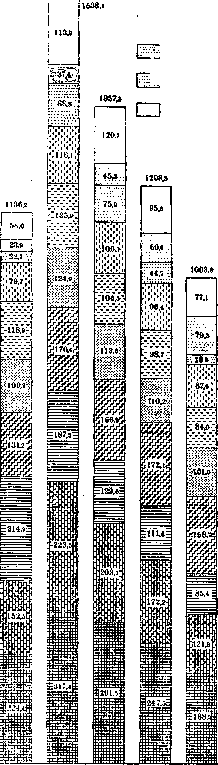
Diseases exhibit, as it were, a selective capacity in relation to sex, age, seasons of the year, as well as in relation to various localities and social groups of the population. Some diseases (e.g., those associated with sexual life) show the greatest predominance in women, others (e.g., traumatism) predominate in men; each age period is distinguished by its characteristic morbidity structure; the morbidity of occupational groups of the population develops differently. As an example, information is given on the morbidity of the population of Moscow Governorate and the city of Moscow in 1926 (see table and diagram).
The scope of the study of morbidity includes determining its strength and character for the entire population of a given locality as a whole, for each sex and individual age groups, for individual months of the year, and so on. Subsequently, when the general morbidity of the population of a territory (region, province, city, etc.) has been determined, the study proceeds to individual social and occupational groups. Of course, the main groupings of the material in these studies must be uniform—otherwise, the comparability of the processed data disappears. The generally accepted age grouping contains the following three age scales, which differ in the degree of detailed age subdivisions.
0-12 months, 1-4 years, 5-9 years, 10-14 years, 15-19 years, 20-29 years, 30-39 years, 40-49 years, 60-59 years [sic], 60 years and older. 0-12 months, 1-4 years, 5-9 years, 10-14 years, 15-19 years, 20-24 years, 25-29 years, 30-34 years, 35-39 years, 40-44 years, 45-49 years, 60-59 years [sic], 60-69 years, 70-79 years, 80 years and older. 0-12 months, 1-4 years, 5-9 years, 10-14 years, 15-19 years, 20-39 years, 40-59 years, 60 years and older.

When studying morbidity, a distinction is made between a) determining the structure (composition) of morbidity and b) its strength and character. The former is obtained when the share of participation of individual disease forms or groups thereof in the total mass of diseases for a given period of time is established; when, in other words, extensional ratios are used (to the total number of diseases taken as 100, 1,000, etc.). The strength (or height) of morbidity is determined when using ratios of the number of cases
Disease A. Absolute numbers, men B. Ratios per 1,000 persons of each sex. Moscow Governorate, City of Moscow, women, Moscow Governorate. Department I. Epidemic and infectious diseases. Including: Group 1. Epidemic diseases...... Group 2. Infectious diseases [ non-epidemic......! Department II. General diseases..... Including: Group 1. Neoplasms . Group 2. General disorders of nutrition, metabolism, and internal secretion . Group 3. Chronic poisonings . Department III. Diseases of the nervous system and sense organs . . Including: Group 1. Diseases of the nervous system. Group 2. Diseases of the organs of vision. Group 3. Diseases of the organs of hearing. Department IV. Diseases of the circulatory organs.......... Department V. Diseases of the respiratory organs.............. Department VI. Diseases of the digestive organs .......... 210,834; 217,686 238,279 39,768 I 56,835 160,625 57,061 55,856 6,825 8,893 47,976 2,034 41,817 69,704 35,389 43,253 3,710 199,184 39,095 134,621 127,611 130 230,523; 184,894 71,766 121,200 37,567
Department VII. Diseases of the genitourinary organs ............ Including: Group 1. Diseases of the urinary organs .............. Group 2. Diseases of the male genital organs ......... Group 3. Diseases of the female genital organs ......... 274,845' 304,698 .990; 11,443 5,301 3,689! 70,426 77,482 37,000 82,597' City of Moscow, Moscow Governorate. 143,433 44,584 80,130 7,360: 72,503 262' | 197,978 69,516 94,454 34,008 49,835: 298,070! 180.3 146.3 34.0 48.5 41.0 1.7 35.8 59.6 30.3 32.9 124.6 235.2
Department VIII. Diseases of pregnancy and the puerperium..... Department IX. Diseases of the skin and subcutaneous tissue ..... Department X. Diseases of bones, joints, and muscles.......... Department XI. Developmental defects . Department XII. Diseases of newborns .............. Department XIII. Senile debility ............. Department XIV. Diseases from external causes............ Department XV. Ill-defined and unspecified diseases Total....... Population according to the 1926 census........ 46,125 1,646 6,385
Figure 1. Morbidity of the population of the city of Moscow in 1926 by age (per 1,000 persons of each age group). Dept. II General diseases. Dept. VII Genitourinary organs. Dept. IV Circulatory organs. Other diseases. Dept. VI Digestive organs. Dept. I Epidemic and infectious diseases. Dept. IX Skin and subcutaneous tissue. Dept. III Nervous system and sense organs. Dept. V Respiratory organs. Dept. XIV Diseases from external causes.
Fig. 2. Morbidity of the population of Moscow Governorate in 1926 by age (per 1,000 of each age group). of diseases to the number of the population (taken as 100, 1,000, etc.) in the environment of which they arose (intensive ratios); the character of morbidity is determined by the ratios of individual disease groups (and so on) to the number of the population. Maps of "new diseases" of the population of a certain locality are developed in their mass to determine "continuous", mass morbidity; with partial development, not all card material is used, but a known, sufficiently powerful part of it, capable of displaying the structure of morbidity on known grounds—then they speak of a "sample" investigation (see Sampling method). At the present time, the question of sample investigation of morbidity seriously occupies the minds of sanitary statisticians in the USSR in view of the fact that for very many local sanitary-statistical centers of the Union, a continuous investigation of morbidity is unaffordable. The XI All-Union Congress of Bacteriologists, Epidemiologists, and Sanitary Physicians in the spring of 1928, considering the question of applying the sample method in processing materials on the morbidity of the population, decreed: "1) The main method of investigating the general morbidity of the population is recognized, as before, to be the continuous processing of the card material relating hereto; due to its difficulty, it cannot be carried out annually, but is performed periodically, every 5-10 years, and as far as possible in the years of general demographic censuses. 2) Conducting at least a single continuous investigation of the morbidity of the population is accepted as an important condition for the correct formulation in the future of a shortened investigation of morbidity. 3) The shortened investigation concerns only the moment of processing, but does not affect the moment of registration; the general system of registration of all medical observations on statistical cards according to accepted rules is preserved." At the present time, it is recommended to apply the sample method according to the mechanical principle for processing materials on the morbidity of the urban population, and for rural localities—to begin processing materials from point settlements (i.e., those settlements where a medical institution is located), assuming that the latter will provide sufficiently large material; where possible according to the conditions of the collected material, in determining the morbidity of the rural population, to carry out the same method of mechanical sample investigation as for the urban population. The statistical study of general morbidity in Russia was first initiated by E. A. Osipov. In 1875, he presented to the Moscow Gubernia Sanitary Commission the "Program for the Sanitary Investigation of the Gubernia"; by it, the systematic regular registration of all forms of diseases observed by Zemstvo physicians was established; by the adoption of this program, a new branch of statistical investigation of the population was organized, namely—the statistics of morbidity. The investigation of general morbidity in the period 1880–1890 is characterized "as a general, continuous, and uninterrupted determination of the mass morbidity of the population" according to a single program for all localities and in the same volume from year to year. The system of investigating general morbidity laid down by Osipov had no models or precedents anywhere up to that time. The analysis of the collected morbidity materials for 1876–1885 made it possible to draw a number of capital-importance conclusions. For subsequent years up to 1908, the analysis of general morbidity materials was carried out by Osipov's successor, P. I. Kurkin. When by 1909 a large amount of information on general morbidity statistics had accumulated, the gubernia sanitary organization recognized it as timely, in view of the enormous importance for the gubernia of the question of occupational morbidity, to undertake the investigation of the latter. The study of general morbidity in other parts of Russia followed the models of Moscow Governorate. A further development and deepening of the investigation is the study of the morbidity of the individual, family, group of families, etc.: here, the unit of investigation is no longer the "case of disease", as takes place in mass morbidity statistics, but the "individual" suffering from various forms of diseases along their life path. This study is based on observations collected through the so-called "individual-family" registration conducted in medical institutions. Individual cards relating to a single family are collected in a family cover; in addition to general questions, the individual card contains notes on anamnesis, heredity, family diseases, changes in family status, occupation, place of residence, the outcome of the disease, etc. In these cards, clinical material is collected, enabling the physician to monitor the course of the disease during repeated visits of the patient, to catch the connection between individual diseases of the same person, between diseases of members of the same family, to catch their hereditary transmission, and so on. However, this is still the statistics of the future, which up to the present time remains in its initial stage. In view of the important significance that infectious-epidemic diseases have in the life of the population, the current statistics of epidemic morbidity from the very beginning stood out into a special department. Although the main method for accounting for acute infectious diseases is their registration on general statistical cards (as for all diseases in general), nevertheless, for organizational and practical purposes, the necessity of a special, emergency registration of the main acute infectious forms on "emergency notification" cards for cities, and in the form of "weekly current information" for settlements, is recognized. The study of morbidity from social diseases (tuberculosis, syphilis, etc.) requires special, more complex forms of statistical registration (dispensary statistics). However, for general accounts of susceptibility to these diseases as well, exclusively forms of simplified mass registration (statistical card of diseases) can serve; complex dispensary registration of tuberculosis, venereal diseases, etc., cannot exhaust the general accounting of these diseases. The statistical study of "occupational morbidity" and "pathological affectedness" is the most complex. The basis of the method for studying them is the proposition established by Bogoslovsky more than 20 years ago that the unit of investigation here must be taken as the "detailed profession", i.e., that primary element into which labor breaks down under modern division of labor. The research method consists of the following moments: a) identification of the general morbidity of the entire population of a given locality (as a scale for comparisons), b) establishment of occupational hazards inherent in each detailed profession (compilation of sanitary characteristics of these professions), c) compilation (on the basis of these characteristics) of groupings of detailed professions according to the similarity of their inherent occupational hazards, d) sanitary investigation of those enterprises whose occupational morbidity and pathological affectedness of workers are being investigated, e) detailed investigation of socio-living conditions (the entire way of life) of the studied groups of workers, f) investigation of the state of physical development and health of workers upon their admission to a given enterprise and subsequent periodic investigations of them during their stay at it, g) investigation of the morbidity of these workers during the time between their periodic examinations. In the system of statistical records necessary for the study of occupational morbidity and pathological affectedness, the main form is the "Personal Sanitary Journal" with insert sheets proposed by Bogoslovsky. It contains general statistical data, general status and anamnesis, clinical status, laboratory studies, diagnosis by organs (physician's conclusion, measures of medical-social assistance, etc.). The journal is designed for a series of periodically repeated medical examinations. Observations on diseases that occurred between periodic examinations are entered on the "current observation sheet" inserted into the journal. A special additional sheet to the sanitary journal contains data on the "investigation of the social and occupational conditions of the worker" (individual labor conditions, housing, means of subsistence, nutrition, other conditions of life, general conclusion). In Western Europe, statistics of the general morbidity of the population do not exist, because there was no such basis—the social organization of medical care for the population—upon which this statistics was and is built in the USSR. Western European morbidity statistics concern only individual groups of the population (insured, army, navy, etc.); they operate mainly with data from sick funds, dealing only with diseases proceeding with loss of working capacity; by accounting for them, they also account for "disease days"—the duration of the disease, which our statistics of general morbidity, based on the registration of all diseases, cannot do. The introduction of social insurance also brought to life in the USSR statistics of morbidity with loss of working capacity.
Moscow, 1912; Osipov, E., Statistika boleznennosti naseleniya v Moskovskoy gubernii za 1878–82 gg. [Statistics of Population Morbidity in Moscow Governorate for 1878–82], Moscow, 1890; by the same author, Programma sanitarnogo issledovaniya Moskovskoy gubernii, prinyatoy Moskovskoy gubernskoy zemskoy sanitarnoy komissiey [Program for the Sanitary Investigation of Moscow Governorate, Adopted by the Moscow Gubernia Zemstvo Sanitary Commission] (Review of the Twenty-Five-Year Activity of the Moscow Zemstvo for 1865–1890, Moscow, 1892); Pravila mediko-sanitarnoy registratsii [Rules for Medical-Sanitary Registration], issue 1–2, Moscow, 1927–28; Princing, F., Metody sanitarnoy statistiki [Methods of Sanitary Statistics] with additions by P. Kurkin and P. Kuvshinnikov, Moscow, 1925; Sotsialnaya gigiena [Social Hygiene], edited by A. Molkov, Moscow, 1927; Yakovenko, E., Meditsinskaya statistika [Medical Statistics], Moscow–Leningrad, 1924.
Related articles
Cite this page
“Morbidity.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/morbidity/