Middle Ear
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
A detailed anatomical and embryological description of the middle ear, covering its phylogenetic development, structural components, and the process of pneumatization. This article provides a historical overview of the tympanic cavity, ossicles, and associated structures as understood in the early 20th century.
Encyclopedia article (1928–1936)
MIDDLE EAR. Phylogenesis. In the historical development of the auditory apparatus, an auxiliary, so-called sound-conducting section begins to join the more ancient formation—the inner ear—at a certain stage; the deeper part of this section constitutes the middle ear, and the more superficial part constitutes the outer ear (the auditory canal and the auricle in mammals). Sometimes the terms "middle ear" and "tympanic cavity" are equated, but it would be more correct to consider the first name more general, also encompassing the appendages of the indicated cavity, namely the cellular system of the mastoid process and the Eustachian tube. The middle ear begins to appear in terrestrial vertebrates and consists of skeletal parts, e.g., special cartilaginous or bony formations (operculum in tailed amphibians, columella in tailless amphibians and reptiles, auditory ossicles in mammals), of an air space adjacent to the inner ear from the outside, and the tympanic membrane. The Eustachian tube can be found already in some reptiles (crocodiles). The mastoid process in most mammals is not yet expressed, but instead there is a bony bulla (bulla tympanica), communicating with the tympanic cavity. A hint of it is found in prosimians and monkeys, in which the middle ear very much resembles the human one. Embryology. In the human embryo, the primordium of the middle ear is formed from the first branchial cleft, and in the middle of the second month, one can distinguish the tympanic cavity and the Eustachian tube, as well as the primary closing plate, lying directly under the outer epidermoid layer, in the place of which the tympanic membrane will later appear. The cavities of the middle ear by the 6th–7th month appear filled with mucous tissue; the auditory ossicles develop from the blastema of the first and second branchial arches; the stapes at the end of the 1st month, the other ossicles, as well as the muscles of the tympanic cavity—from the middle of the second. The lumen of the tympanic cavity in the form of a slit, filled with serous fluid, is clearly expressed in an 8-month fetus, but only after birth does the development of free, i.e., air-filled spaces, begin to progress rapidly in the middle ear. A number of factors exert a great influence on this "pneumatization": the degree of patency of the Eustachian tube (in turn depending on the development of the adenoid tissue of the nasopharynx), constitutional features of the temporal bone, inflammatory and related processes in the mucous membrane of the tympanic cavity, etc. The mastoid process begins to develop depending on the tension of the muscles attaching to it, which in turn is connected with the habitual vertical position of the human body, and consequently, a more or less developed process can be encountered no earlier than the second year of a child's life. Pneumatization of the process often ends only by the 5th–6th year of life. The Eustachian tube in children is shorter than in adults and not so curved; thus, in them, the tympanic cavity communicates more easily with the nasopharyngeal cavity than at a later age. Macroscopic structure of the middle ear. The tympanic cavity (cavum tympani) is located in the middle of the temporal bone, approximately at the junction of the pyramid, the squamous part, the mastoid part, and the tympanic bone (os tympanicum); it has 6 walls, of which the inner one is the most complexly arranged, being simultaneously the outer wall of the labyrinth (inner ear). In its center is a protrusion formed by the bony capsule of the basal turn of the cochlea; posterior and superior to it is located the oval window of the labyrinth, closed by the plate of the stapes (membrana obturatoria stapedis); posterior and inferior is the niche of the round window (closed by a connective tissue secondary tympanic membrane). Superior to the oval window is the ridge of the bony canal of the facial nerve, passing here approximately in a horizontal plane; even higher and directly posterior, more correctly speaking already in the wall of the mastoid antrum, the ridge of the lateral semicircular canal often protrudes. The posterior wall in its lower sections includes the continuation of the facial nerve canal, the bony case for the stapedius muscle (eminentia pyramidalis), the canal for the corresponding artery and nerve (a. stapedia and n. stapedius), and the opening for the chorda tympani, and in the upper sections—the opening connecting the tympanic cavity with the antrum of the mastoid process (Fig. 1–3). The upper wall (tegmen tympani) can be very thin and even have lacunae in approximately 10% of all cases (Alexander). It is formed partly by the pyramid, partly by the squamous part of the temporal bone; the slit between these formations is called the fissura petrosquamosa, or mastoideosquamosa. The lower wall is simultaneously the upper wall of the jugular fossa; it is of varying thickness and can also have large dehiscences (lacunae). In the anterior wall there is
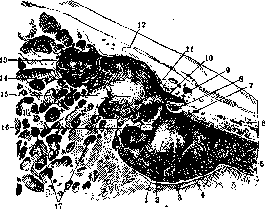
Figure 1. Vertical oblique (axial) section of the middle ear: 1—medial wall of the tympanic cavity (promontory); 2—lower wall of the tympanic cavity; 3—floor (hypotympanon); 4—tympanic nerve plexus; 5—Eustachian tube; 6—semicanal for the tensor tympani muscle; 7—stapes; 8—transverse section of the tensor tympani muscle; 9—cochleariform process (proc. cochleariformis); 10—tendon of the stapedius muscle; 11—protrusion of the Fallopian canal (bony case of the facial nerve); 12—tegmen of the tympanic cavity; 13—antrum; 14—entrance to the antrum; 15—protrusion of the lateral semicircular canal; 16—pyramidal eminence, housing the stapedius muscle; 17—cells of the mastoid
process. (After Spalteholz.)
the opening of the musculotubal canal, the upper half of which is the case for the tensor tympani, and the lower—the Eustachian tube, having its tympanic orifice here. Its medial wall is adjacent to the carotid artery canal, and the bony layer separating this large vessel from the tube and the tympanic cavity can be very thin, also have dehiscences, and pass through itself tiny canaliculi for vessels directly branching off from the internal carotid artery (canaliculi caroticotympanici and aa. caroticotympanicae). In the vicinity of the orifice of the tube and on the floor of the tympanic cavity, there are air cells (cellulae tympanicae et tubariae) similar to the same cells of the mastoid process, as well as cells in the squamous part, the zygomatic process, and the petrous part with strongly expressed pneumatization of the temporal bone. The outer wall consists of a bony curtain—a continuation of the upper wall of the bony external auditory canal (lateral wall of the attic) and the tympanic membrane, which is divided into a large, main part (membrana tensa, s. vibrans) and a smaller one—Shrapnell's (membrana flaccida, s. Shrapnelli), covering all the rest of the space inferiorly, so that a continuous bridge is formed between the tympanic cavity and the cavity of the external auditory canal.
The tympanic cavity is divided by height into two parts: the mesotympanon, i.e., the central part (corresponding to the position of the tympanic membrane), and the upper floor—the attic, cupola (recessus epitympanicus). With a low standing of the floor of the cavity, the depression lying below the level of the lower edge of the membrane receives the name "floor" (hypotympanon). In the tympanic cavity are the auditory ossicles (ossicula auditus), ligaments, tendons, nerves, vessels; all these parts are covered by the mucous membrane. The chain of ossicles consists of 1) the malleus, the handle of which (manubrium mallei) is woven into the fibers of the tympanic membrane, and the head (caput mallei) is placed in the attic; from its neck, a short process extends outwardly, and anteriorly a long one (processus Folianus, processus mallei ant.) together with a rudimentary muscle (m. mallei externus, s. Folii); 2) the incus, having a body articulating with a meniscus joint with the head of the malleus, a short process (processus brevis incudis) directed posteriorly, and a long process (processus longus) articulating with the head of the stapes, sometimes through the intermediary of an intercalary bone—the lenticular (processus lenticularis—ossiculum Sylvii); 3) the stapes, having two crura and the aforementioned plate closing the oval window. The ossicles are attached by ligaments (lig. ossiculorum auditus) to the walls of the tympanic cavity; there is an external and superior ligament of the malleus (lig. mallei ext. superius), a posterior ligament of the incus (lig. incudis post.), and an annular
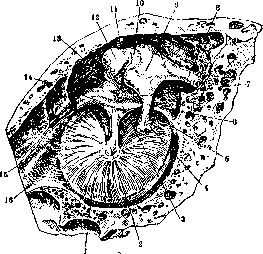
Figure 2. Vertical sagittal section of the tympanic cavity: 1—inner surface of the tympanic membrane; 2—handle of the malleus; 3—chorda tympani; 4—articulation of the incus with the stapes; 5—entrance to the posterior pocket of the tympanic membrane; 6—long process of the incus; 7—plica malleolaris post.; 8—short process of the incus; 9—body of the incus; 10—articulation of the incus with the head of the malleus; 11—superior ligament of the malleus; 12—head of the malleus; 13—attic (epitympanon); 14—anterior (long) process of the malleus; 15—entrance to the anterior pocket of the tympanic membrane; 16—Eustachian tube. (After Spalteholz.)
the stapedial ligament (lig. annulare stapedis). The tendon of the tensor muscle (m. tensor tympani) sharply bends around the cochlear process (on the inner wall of the cavity) and attaches to the upper end of the handle of the malleus; the tendon of the stapedius muscle goes directly to the head of the stapes and attaches there. [The muscles themselves (mm. ossiculorum auditus) are located in the corresponding bone channels mentioned above.] From the nerve trunks, some only pass through the cavity (tympanic chord) or in its bony walls (facial nerve), while others are intended for the innervation of this organ, namely the tympanic plexus, located under the mucous membrane on the inner wall of the cavity. It is formed by branches of the glossopharyngeal, trigeminal, and sympathetic nerves. Vascular branches go either directly from the internal carotid artery through the aforementioned canaliculi or from the system of the external carotid artery, in particular from its branches: the maxillary and posterior auricular; vessels penetrate into the tympanic cavity through the petrotympanic fissure, stylomastoid foramen, and other canals and are called according to their topographic position as the superior, anterior, etc. tympanic arteries and veins. A. carotico-tympanica branches off from the carotid artery and penetrates into the tympanic cavity through the canal of the same name. -The mucous membrane is thin, tightly adheres to the underlying bone tissue, and is covered for the most part by non-ciliated cuboidal epithelium; its character changes as one moves away from the opening of the Eustachian tube: near it, there may be glands and cilia, closer to the attic it becomes similar to the epithelium of the cells of the mastoid process - it flattens and becomes single-row. Folds and pouches of the mucous membrane form pockets; the largest of them are Treach's (corresponding to the posterior-superior quadrant of the tympanic membrane) and Prussak's (corresponding to the Shrapnell's membrane, between it and the neck of the malleus).
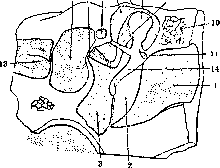
Figure 3. Diagram of the location of the ear cavities on a vertical frontal section: 1-external auditory canal; 2-tympanic membrane; 3-middle attic of the tympanic cavity (mesotympanon); 4-cavity of the inner ear; 5-oval window; 6-lumen of the Fallopian canal; 7-upper attic of the tympanic cavity (epitympanon); 8-roof of the tympanic cavity; 9-head of the malleus; 10-lateral wall of the attic; 11-Prussak's pocket; 12-tendon of the muscle tensing the tympanic membrane; 13-internal auditory canal; 14-handle of the malleus.
the system of the external carotid artery, in particular from its branches: the maxillary and posterior auricular; vessels penetrate into the tympanic cavity through the petrotympanic fissure, stylomastoid foramen, and other canals and are called according to their topographic position as the superior, anterior, etc. tympanic arteries and veins. A. carotico-tympanica branches off from the carotid artery and penetrates into the tympanic cavity through the canal of the same name. -The mucous membrane is thin, tightly adheres to the underlying bone tissue, and is covered for the most part by non-ciliated cuboidal epithelium; its character changes as one moves away from the opening of the Eustachian tube: near it, there may be glands and cilia, closer to the attic it becomes similar to the epithelium of the cells of the mastoid process - it flattens and becomes single-row. Folds and pouches of the mucous membrane form pockets; the largest of them are Treach's (corresponding to the posterior-superior quadrant of the tympanic membrane) and Prussak's (corresponding to Shrapnell's membrane, between it and the neck of the malleus). Physiology. The M. e. serves to conduct sound vibrations to the labyrinth, transmitted to the tympanic membrane from the external environment, and to regulate the intralabyrinthine pressure through the oval and round windows. The first function is performed by the chain of auditory ossicles, the mechanism of which allows the vibrations of the membrane to cause synchronous but reduced amplitude vibrations of the stapes plate, which in turn causes vibrations of the labyrinthine fluid. The meaning of such a device is seen in the fact that sound waves, especially of low frequency, cannot be transmitted so easily from the air directly to the wall of the labyrinth, and therefore the apparatus of the tympanic cavity, on the one hand, increases auditory sensitivity, and on the other, expands the range of audible tones, mainly downward. Some authors adhere to the view that even with bone conduction, sound waves penetrate into the labyrinth through the M. e. and even through the tympanic membrane; consequently, according to this view, the tympanic apparatus is an integral part of sound transmission. Pressure regulation occurs either automatically due to the fact that with changes in external pressure, the chain of auditory ossicles and the secondary tympanic membrane play, or reflexively, due to the muscles of the tympanic cavity, which by their antagonism maintain a certain tension in the chain of ossicles. It is believed that the tensor helps to dampen vibrations and protects the labyrinth from excessive pressure, while the stapedius muscle holds the stapes plate in a state of unstable equilibrium and therefore contributes to greater sensitivity to suddenly occurring sounds (alerting muscle). With its paralysis, excessive sensitivity to certain sounds - hyperacusia - is sometimes observed. The function of the mastoid process apparently comes down to slight resonance, especially with bone conduction, and to isolating the labyrinth from extraneous sound and thermal influences. The function of the Eustachian tube lies mainly in equalizing the pressure in the tympanic cavity, which would otherwise decrease due to the absorption of air by the walls of this cavity. In addition, it is also assigned a protective function (prevents the penetration of infection into the tympanic cavity) (see Eustachian tube). Examination of the M. e. by sight is possible by otoscopy through the external auditory canal, performed with the naked eye or with optical magnification (Bennighaus's loupe, Bruning's, Lüscher's microscope), and the condition of the tympanic cavity has to be judged by the appearance of the tympanic membrane: for example, with its retraction or with transillumination of exudate through it, one concludes about disorders of air exchange in the M. e., by its copper-red color and bulging - about purulent inflammation, etc. If the membrane is destroyed, the walls of the cavity can be seen directly, mainly the inner one; the niche of the round window, the stapes, the tympanic chord, the head of the malleus, and other formations are also visible with corresponding defects in the outer wall of the tympanic cavity; some formations are visible through an intact membrane, for example, the long process of the incus, the crus and head of the stapes, etc. The presence of fluid (transudate or exudate) is confirmed by inflating the ear by various methods (Valsalva's, Politzer's, by catheterization); the tone of the tensor tympani and tubal muscles can be determined by means of otometry. In pathological cases with perforations of the membrane, the tympanic cavity becomes accessible to probing, taking bacteriological samples, trial irrigations, and some other direct diagnostic interventions. -Examination of hearing often 455
CPE, also allows one to conclude about the participation of the middle ear in the pathological process. Modern techniques allow for photographic images of the eardrum and even to cinematograph such phenomena as, for example, the pulsation of scars on it. X-ray examination makes it possible to judge the condition of the bony parts, mainly the degree of pneumatisation and other features of the mastoid process. Developmental anomalies are often associated with abnormalities in the structure of the outer and inner ear and consist in the walled-off condition of the tympanic cavity by a bony plate, dystopia of the styloid process (prominentia styloidea), the upper end of which protrudes into the tympanic cavity, reduction in the volume of this cavity, absence of one or another auditory ossicle, their ankylosis with each other, formation of diverticula of the Eustachian tube (Kirchner) and diverticula of Rosenmüller's fossa (Pertik).-Traumatic injuries may be isolated, for example, when foreign bodies, including fragments of projectiles, shot, bullets, enter the tympanic cavity through the external auditory canal, or when the eardrum is intentionally or unintentionally injured by some object (pin, tweezers), or they form part of a more extensive injury to the skull from direct or indirect violence to it. Fractures of the base of the skull often involve both the inner ear and the middle ear and disrupt the integrity of its various walls, including the eardrum. Hemorrhage into the tympanic cavity can be recognized by the dark blue translucence of the eardrum; when the eardrum itself is injured, blood appears in the external auditory canal, and during otoscopy the site of its rupture can be seen (see Eardrum). The most common form of disease of the middle ear are acute and chronic otitis media (see Otitis). A distinction is made between 1) catarrhal processes, depending on the obstruction of the Eustachian tube (see Eustachian tube and Eustachianitis) and the accumulation of transudate (or, during exacerbation, exudate), and 2) true inflammations of the tympanic cavity, usually with greater or less participation of infection entering it by various routes (in a healthy state the tympanic cavity is probably sterile). Purulent otitis often runs as a severe disease and can give dangerous intracranial and general complications. Such otitis also pose a threat to hearing, as the process from the middle ear can spread to the labyrinth and in this case cause any degree of deafness (see); but even if the disease is localized in the area of the middle ear, then under unfavorable circumstances significant defects occur in the structure of the organ, for example, a permanent hole may remain in the eardrum, ankylosis of the ossicles, adhesions, etc., which exclude the possibility of good hearing in the affected organ. Preventive and therapeutic measures come down to the general hardening of the body and raising its resistance by proper hygienic regimen. In mesotympanitis, characterized by the location of a marginal perforation of the eardrum in the center or in the anterior quadrants, great importance is attached to the sanitation of the upper respiratory tract, and in diseases of the attic (epitympanitis), accompanied by a marginal perforation of the eardrum in the posterior quadrants or Shrapnell's part (see Eardrum),-to surgical intervention in the form of one or another variety of 'radical' operation.--Methods of correcting hearing defects consist of acoustic operations, having the aim of at least partially restoring the former function of the affected tympanic cavity. Examples of such interventions: tunneling of the mastoid process in atresia of the auditory canal, myringoplasty (artificial closure of a perforation of the eardrum) and myringotomy (artificial production of a perforation of it), mobilization of the stapes, trepanation of the labyrinth in otosclerosis (with the help of an operative loupe-microsurgery) and some others. A prosthesis is an artificial eardrum, in the form of a small circle of thin rubber, a rubber cap, or a small cotton ball soaked in glycerin, and hearing aids of two kinds: an example of the first is the horn, known since ancient times, an example of the second are the latest microphone amplifiers-phonophore, acoustic, etc. (see Deafness-apparatus for improving hearing).
The pathology of the mastoid process, due to its territorial and systemic proximity to the tympanic cavity, is closely related to the condition of the latter. It is believed that acute otitis is always accompanied by a certain reaction on the part of the cells of the process (painfulness on pressure on it; their obscuring on X-ray films); an even more marked participation is designated as mastoiditis and is a relatively frequent complication of acute purulent otitis. In chronic forms it occurs less frequently and is not so typical, since chronic stages of otitis are usually accompanied by hardening of the process and absence or very small quantity of cells in it, consequently the inflammatory process does not have a convenient base for the formation of empyema, and more often causes caries of the bony walls and spread of the suppuration to neighboring deeper organs (labyrinth, cranial fossae, sinus). New formations of the middle ear may be of inflammatory origin (polyps, granulomatous tumors arising on the basis of purulent otitis) or true tumors, but standing in connection with otitis, but often accompanied by secondary suppuration of the tympanic cavity. Most often one deals with carcinomatous and sarcomatous tumors, primary or metastatic, less frequently neurofibromas, myxomas, chloromas and other forms.-The participation of the middle ear in contagious diseases is observed extremely frequently. In acute infections, the complication of otitis often characterizes one or another epidemic as a distinctive sign. Chronic forms also often involve the tympanic cavity, causing secondary suppuration in it. Thus, for example, tubercular tubercles can be localized on the eardrum (myringitis tuberculosa, see Eardrum) or in other parts of the middle ear, and then one speaks of tuberculosis of the ear; more rarely does syphilitic affection of the mastoid process, tympanic cavity and Eustachian tube occur (a hard chancre of its orifice is possible when using inadequately disinfected catheters). Cases of scleroma of the ear have been described.-Professional diseases of the middle ear are possible primarily in occupations that are associated with the danger of catching cold, therefore wherever workers are exposed to sharp fluctuations in temperature, for example when working on locomotives, in engine rooms of steamships, near smelting furnaces. Indirectly, working conditions can affect it in that, if they act unfavorably on the upper respiratory tract, they create a favorable soil for the formation of otitis. With sharp fluctuations in external pressure, in caisson work, in artillerymen when firing from cannons, ruptures of the eardrums and hemorrhages into the walls of the tympanic cavity, prolonged spasms of the tympanic muscles are observed. (On protective devices see Protective devices in industry.) Method of examining the middle ear at autopsies. A simplified and sequential method are distinguished. In the first, after the usual opening of the skull, removal of the brain and stripping of the dura mater, a flat layer of bone is planed off approximately parallel to the upper edge of the pyramid, whereby the tympanic cavity, the cells of the mastoid process and the cochlea are exposed, or a polygonal plate corresponding to the roof of the tympanic cavity and the cave is planed off with more perpendicular blows. In the second method, either the individual organs-mastoid process, attic, Eustachian tube-are carefully dissected with chisels and forceps, or the temporal bone and adjacent areas of adjoining bones are sawed out entirely and the specimen is subsequently subjected to special processing for microscopic investigation by proper fixation in solutions of formalin and acetic acid (for cell nuclei), potassium bichromate and osmic acid (for protoplasm) and decalcination, preferably in 5% nitric acid; they are embedded in celloidin, series of sections are made on a microtome, usually in two perpendicular planes-horizontal and vertical-and stained by various methods, depending on the purpose of the research: hematoxylin-eosin, by van Gieson, etc. In experiments on animals, they are subjected to vital fixation, which to a significant extent guarantees against post-mortem changes. Lit.-see and Ear. literature to the article Otorhinolaryngology by V. Volchkov.
Related articles
Mentioned in
Cite this page
“Middle Ear.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/middle-ear/