Malaria
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article provides a historical and parasitological overview of malaria, detailing its discovery, the identification of its causative agents, and the development of the understanding of its life cycle. It covers the transition from early theories of 'bad air' to the scientific establishment of the Plasmodium parasite and its transmission by mosquitoes.
Encyclopedia article (1928–1936)
MALARIA, from the Italian malaria—bad air, intermittent, remittent, marsh fever (malaria, febris intermittens, French: paludisme). This name encompasses a group of closely related diseases characterized by a specific clinical course, in particular, a strict periodicity of febrile paroxysms. I. History. Clinically, malaria has been known for a long time, and accurate descriptions of it were provided by physicians of ancient Greece (Empedocles and Hippocrates), as well as a number of physicians of ancient Rome. Galen denied the necessity of separating malaria from the general number of febrile diseases, and this view held until the 16th–17th centuries, when the question of malaria as an independent disease was raised again (Fracastoro, Sydenham). The turning points in the history of malaria are: for therapy, 1640—the importation of cinchona bark into Europe from America, and for the study of the disease—November 6, 1880, when Laveran in Constantine (Algeria) discovered the causative agent of malaria. In the autumn of 1885, Golgi began his famous work on establishing the connection between the development of parasites and the clinical manifestation of malaria. In 1891, Romanowsky proposed his method of staining blood parasites, which made it possible to study the structure of protozoa. In 1884, Laveran suggested the role of mosquitoes as transmitters of the disease. In 1895, R. Ross experimentally proved the transmission of malaria by mosquitoes in birds and in 1898 provided a description of the development of protozoa in the mosquito's body. In 1898, Bignami first described a case of experimental infection of a healthy person with malaria through the bite of an infected mosquito. A large number of subsequent works on the study of the biology of the parasite and the mosquito significantly clarified the epidemiology of malaria and made it possible at the present time to conduct rational control of malaria, the enormous economic significance of which in the life of entire nations was realized and proven only recently. II. Parasitology. Historical data. In the 1860s–70s, various plant cells and algae were considered the causative agent of malaria. In 1879, Bacillus malariae was described by Klebs, the role of which in the etiology of malaria was generally accepted for a number of years, and therefore the discovery in 1880 by Laveran of the blood parasite, the malaria plasmodium, which he classified as a type of protozoa (Protozoa), was initially met by most researchers with distrust and even hostility. However, subsequent work firmly established the role of the plasmodium. The place of this parasite among protozoa remained unclear for a long time. Mechnikov classified it into the class of sporozoans (Sporozoa). Many authors hold this view to this day. Hartmann (1907–1912) classifies it into the class Mastigophora, subclass Flagellata, order Binucleata, family Plasmodidae. A feature of the parasites included in the order Binucleata is their inherent multifaceted cycle of development, which reduces to asexual (schizogony) and sexual (gamogony) development with adaptation to different species of animals. Morphology and biology of the parasite. A detailed study of the morphological features of the plasmodium, as well as protozoa in general, became possible only after Romanowsky (1891) discovered a method of elective staining of protoplasm and the nucleus with a mixture of methylene blue and eosin (this method was first applied by Chenzinsky in Odessa in 1888). This method, like all its later modifications (Laveran, Ziemann, Leishman, Giemsa, etc.), gives a bright blue color to the protoplasm and an intense red color to the nucleus. When studying the details of the parasite's structure, a thin blood smear is stained, while for diagnostic purposes at the present time, the method of staining an unfixed thick blood drop according to Ross is used; the hemoglobin of erythrocytes is leached out during staining; the plasmodia, which usually have changed their shape somewhat, stand out sharply against a light, unstained background. The body of the plasmodium consists of protoplasm, a nucleus, and pigment. The latter is a product of hemoglobin breakdown and is deposited in the protoplasm in the form of minute grains, which are located along the periphery or clumped in one place. When observing a living plasmodium, one can see the lively movement of the pigment. Both Laveran and a number of other researchers accepted the existence of a single species of malaria plasmodium, believing that the different clinical course of tertian, quartan, and tropical malaria is caused by the adaptation of the parasite to the clinical, racial, and individual characteristics of the host. At the present time, the majority, in contrast to this view of the unitarians, adheres to the theory of the multiplicity of species of the causative agent—pluralism. This is supported by data from comparative morphology and development of the parasite, culture data, and the absence of microscopic examination data confirming the transition of one species of plasmodium into another. The presence of at least three species is established: Plasmodium vivax (Grassi et Feletti, 1890), the causative agent of tertian malaria; Plasmodium malariae (Laveran, 1881), the causative agent of quartan; and Pl. immaculatum (Schaudinn, 1902), the causative agent of tropical malaria. Experimental infection of humans with malaria for the treatment of progressive paralysis has shown that each of the three types of human malaria strictly retains its original character and does not transition into another type. Thus, Mühlns and Kirschbaum (1921) performed 20 passages in humans with Pl. vivax, 4 with Pl. immaculatum, and 3 with Pl. malariae; the parasite always retained its species. By the present time, there are already many hundreds of passages of Pl. vivax and Pl. malariae through humans, and the above-mentioned position on the independence of all three types of human malaria remains unshaken. The most commonly used names for malaria causative agents: tertian—Plasmodium vivax (Grassi et Feletti, 1890), Haemamoeba vivax (Grassi et Feletti, 1890), Pl. malariae tertianum (Labbé, 1889), Haemosporidium tertianum (Lewkowicz, 1887); quartan—Plasmodium malariae (Laveran, 1881), Oscillaria malariae (Laveran, 1881), Haemamoeba malariae (Grassi et Feletti, 1890), Haemosporidium quartanae (Lewkowicz, 1897), Pl. malariae quartanum (Labbé, 1899), Laverania malariae (Jancso, 1905); tropical—Pl. immaculatum (Schaudinn, 1902), Plasmodium praecox (Doflein, 1901), Haemamoeba malariae (Laveran, 1890), Laverania malariae (Grassi et Feletti, 1890), Haemamoeba praecox (Grassi et Feletti, 1890), H. Laverani (Labbé, 1894), H. immaculata (Grassi et Feletti, 1891), Pl. falciparum (Blanchard, 1905), Haematozoon falciparum (Welch, 1897). The position of other plasmodium species in the zoological system is still far from clear. Ziemann describes Laverania perniciosa, a form very close to Pl. immaculatum and differing from it only in insignificant morphological and biological features: small pigment, a smaller number of merozoites, a small number of crescents, etc. Close to this same species are Pl. tenue (Stephens, 1914) and Pl. caucasicum (Marzinowski, 1916). Emin (1914) described as a separate form Pl. vivax, varietas minuta—a parasite that in the early stages of its development approaches Pl. immaculatum, and in later stages—Pl. vivax. Mixed infection—the simultaneous presence of parasites of different species in the blood—is observed not infrequently: up to 10% and higher. The presence of two and even three specimens of plasmodia in one erythrocyte is most often encountered in infection with Pl. immaculatum. A distinctive feature of the malaria causative agent is a double cycle of development. Asexual development (schizogony), described by Golgi (1885), proceeds exclusively in erythrocytes. The formation of sexual forms also occurs here. The sexual cycle proceeds in the body of the mosquito (R. Ross, Grassi, Bignami, Bastianelli). Schizogony (Fig. 1) proceeds in general terms identically in all three species of plasmodium. All forms resulting from schizogony are called schizonts. When a person is bitten by a mosquito infected with plasmodia, a sporozoite—the final product of the parasite's development in the mosquito's body—enters the blood. It consists of protoplasm and a small nucleus and has the appearance of an elongated body pointed at both ends. Having penetrated an erythrocyte, it turns into a rounded lump consisting of transparent protoplasm with a small vacuole and a pinpoint chromatin nucleus, and takes the form of a ring—a signet ring, in which the stone is the nucleus (red when stained according to Romanowsky), and the rim is the protoplasm (blue). The lumen in the ring is formed by the vacuole. The plasmodium grows, the protoplasm increases in size, acquires the ability of amoeboid movement, and can take on the most diverse outlines. The amount of chromatin increases, the vacuole grows. The hemoglobin of the erythrocyte is absorbed by the plasmodium and turns into clumps of pigment, minute yellow-brown grains. A semi-mature form is obtained. Upon further growth, the parasite reaches full development, a mature schizont is formed, after which the process of division begins. The nucleus divides by simple constriction into 2, 4, 8, 16, 32 parts depending on the species of parasite. Simultaneously, the dividing protoplasm surrounds each nucleus. The pigment in the form of a lump accumulates in the center of the remaining undivided protoplasm.
The erythrocyte disintegrates, the pigment and the remaining part of the protoplasm remain in the form of a dead residue (5), and the young plasmodia-merozoites enter the bloodstream and penetrate an erythrocyte (6). The cycle is completed and begins again (7-11). During schizogony, simultaneously with the asexual forms (agamonts), sexual forms (gamonts, gametocytes, gametes) are formed. Young and semi-mature forms (1a-3a and 1b-3b) of gametes differ from schizonts by the absence of a vacuole and amoeboid movement. Mature forms (4a, 5a, 4b) are characterized by the presence of a large nucleus and rounded protoplasm with coarse pigment in the form of rods embedded in large quantities. Female forms (macrogametocytes) (1a-4a) have a small nucleus and a lot of protoplasm saturated with nutrient substance, which stains intensely dark blue. In male forms (microgametocytes) (1b-4b), the nucleus is large, the protoplasm is poor in nutrients, and it stains weakly. For the gametocytes of Plasmodium immaculatum, crescent forms (22), which differ sharply from other species, are characteristic. In the human bloodstream, even outside the erythrocytes, sexual forms can circulate unchanged for a long time (months). In individual cases, schizogony of gametes is observed, i.e., asexual reproduction of an unfertilized macrogamete (Fig. 1, 5a-7a). This process was described by Schaudinn under the name of reverse development-schizogony of macrogametes (parthenogenesis of other authors). Outside the bloodstream, apparently under the influence of changes in physical conditions (temperature, properties of serum, change in surface tension of erythrocytes, etc.), a metamorphosis of sexual forms is observed. Under natural conditions, this process occurs only in the stomach of a mosquito, but it can also be observed in an artificial environment, for example, when examining a thick drop. Sporogony (Fig. 1, I-XIII). Having entered the stomach of a mosquito along with the blood of a malaria patient, mature gametocytes, having emerged from the erythrocyte (1a and 1b), undergo a series of transformations. In the male cell, division of the nucleus occurs (IIb), as well as the formation of 4-6 flagella-whips (IIIb), which separate from the cell and possess lively movement (spermatozoa); in the female cell, a so-called reduction division occurs. A part of the chromatin substance of the nucleus—the reduction body—is cast off, moves to the periphery of the cell, and disappears (IIa). The significance of this process is not clear. The cell becomes oval, the protoplasm bulges, and a tubercle is formed—a fertilization mound, a mound.
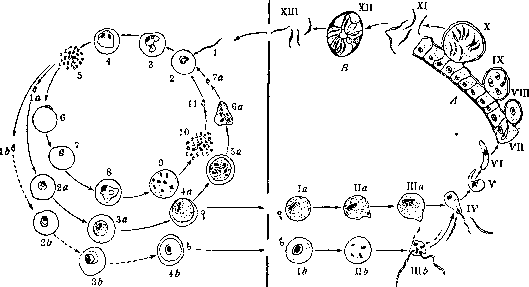
Figure 1. Diagram of the asexual and sexual development of the malaria parasite.
Figure 1. Blood in malaria tertiana: 1 and 2-rings; 3-semi-adult schizont; 4-adult schizont; 5-beginning of division; 6-later stage of division; 7-merulation; 8-male gamete; 9-female gamete. Anisocytosis; poikilocytosis; polychromatophilia. Figure 2. Blood in malaria tropica: 1-rings; 2-beginning of division; 3-merulation; 4-male gamete; 5-female gamete with erythrocyte remnants; 6-female gamete, free from Maurer's clefts. Figure 3. Blood in malaria quartana: 1-ring; 2-transition of the ring into a band; 3-band; 4 and 5-schizonts; 6-merulation; 7-male gamete; 8-female gamete; 9-polychromatophil. Figure 4. Plasmodium praecox (Proteosoma) in the blood of a siskin: 1-merozoite; 2-schizont; 3 and 4-merulation; 5-female gamete; 6-female gamete in plasma. Figure 5. Malaria parasites in the blood of monkeys: 1, 2 and 3-Plasmodium Reichenowi of the chimpanzee; 4, 5, 6 and 7-Plasmodium malariae in the chimpanzee; 8, 9 and 10-Plasmodium Kochii. (According to Gander-Berenberg-Gossler.) Figure 6. Malaria parasites in the blood of Vespertilio Daubentoni: 1-young merozoite; 2, 3 and 4-schizonts; 5-merulation; 6-female gamete. (According to Shingareva.) Figure 7. Brain in comatose malaria; capillaries packed with parasites appear as dark lines. Figure 8. Liver in malaria; abundance of pigment in the cells of the reticulo-endothelium. Fig. 9. Brain in malaria. Dürck's granuloma with hemorrhages. Infected erythrocytes fill the capillaries.
(To the illustration for the article Malaria.)
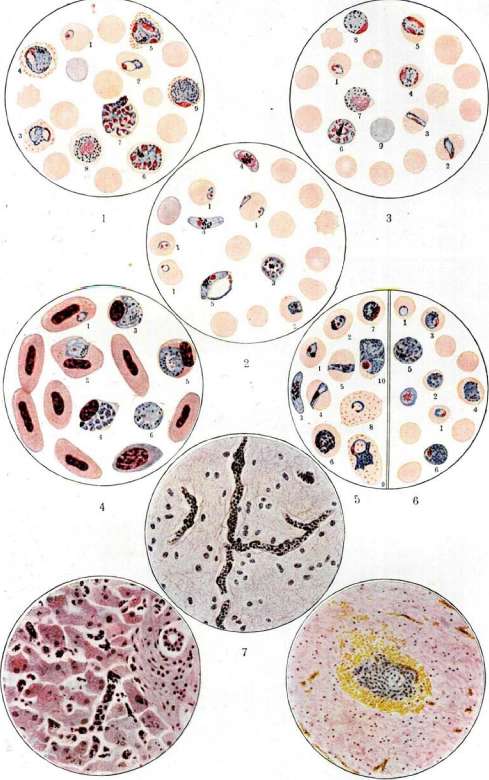
To the article Malaria.
perception (Ilia). The sporozoite rushes toward it and is drawn into it. The nuclei of both cells fuse, and thus copulation (IV) occurs. The fertilized cell is surrounded by a mucous membrane, which prevents the further penetration of sporozoites into it. After 24 hours, a zygote or ookinete—a motile egg cell (V-VII)—is formed, possessing active movement. It penetrates the stomach wall of the mosquito (A) up to the serous membrane. Here it transforms into a spherical or oval pigmented oocyst (VIII). The process of the ookinete's penetration into the stomach wall is completed within 48 hours. As a result of continuous nuclear division, the oocyst increases in size, and daughter cysts—sporoblasts (IX)—are formed. They are filled with sickle-shaped bodies arranged in a rosette (X). Upon the maturation of the sporozoites, the sporoblast bursts, and its contents enter the body cavity of the mosquito (XI). Sporozoites are found in all organs of the mosquito, but they are mainly concentrated in the salivary glands (B), in the cells of which they are located with their pointed ends directed toward the lumen of the excretory duct (XII). Together with saliva (XIII), they enter the human blood (1) during a bite, causing infection. In oocysts, curved dark bodies are sometimes found—Ross bodies, black spores. Ruge and others took them for involution forms of sporozoites, Noe for stages of Nosema development, Kerr for a special type of protozoa (a mosquito parasite)? Their nature has not been definitively clarified. Main (W. M. Maune), based on the fact that they always give a reaction to chitin and are almost always found as thickenings at the ends of tracheal tubes, considers them an anomaly of the development of the tracheal system. The duration of sporogony is from 10 to 20 days, depending on the species of the parasite and external (temperature) conditions. The number of oocysts can be very large (up to several hundred). The number of sporozoites in the salivary glands reaches 10,000. The question of the possibility of sporozoites overwintering in the mosquito's body has not been definitively resolved. The possibility of transmitting the parasite to the mosquito's offspring through the egg is apparently excluded. The process of sporogony, like schizogony, is in general terms the same for all three species of malaria parasites. Mitzmain observed that a large number of gametes of Pl. immaculatum pass through the intestine of Anopheles maculipennis and are expelled with the mosquito's feces, since the number of oocysts developing on the stomach wall of the Anopheles is not proportional to the quantity ingested. This question is of great importance for the epidemiology of M., as it explains the percentage of Anopheles infection with malaria. In experiments with feeding Anopheles on individuals with gametes in their blood, it was not always possible to infect the Anopheles with M. The quantity of gametes in 1 mm3 of the patient's blood is also important, since with 150-200 gametes in 1 mm3 of blood, a person does not infect even 50% of the Anopheles that fed on their blood. The ability of different species of Anopheles to be infected by different species of human M. is not the same. Thus, the work of Dutch authors (Swellengrebel and others) experimentally proved that Anopheles ludlowi is infected by Pl. immaculatum in 100% of cases, by Pl. vivax in 80%, and by Pl. malariae only in 4.7%, whereas in Anopheles kochii, Pl. immaculatum does not develop at all, just as Pl. malariae does not, while Pl. vivax develops in 16.7%. Species of parasites (see separate table, figs. 1-3). The morphological features of the most frequently encountered species, Pl. vivax (from the Latin vivax—living, mobile), are indicated in the description of the parasite's development cycle in the human body. The duration of schizogony is 48 hours. The following changes in the morphological picture of the blood are characteristic of this parasite: erythrocytes are enlarged, pale, and upon staining according to Romanowsky, Schüffner's granulation is often observed (see separate table, figs. 1-3 and 9). Delicate, light-red granules, which apparently form as a result of changes occurring in the composition of the erythrocyte protoplasm under the influence of the parasites' penetration into them, are evenly distributed throughout the erythrocyte. Young forms (rings) of Plasmodium malariae (fig. 2, II) differ almost not at all from Plasmodium vivax, but are smaller. Amoeboid motility is weakly expressed; even semi-mature schizonts have a rounded shape. Very characteristic is the formation of the so-called band—the plasmodium stretches from one edge of the erythrocyte to the other in the form of a strip of protoplasm with parallel edges (fig. 2). There are usually no more than 8 merozoites; they are arranged in the form of a rosette (fig. 2). The sexual forms are significantly smaller than those of Pl. vivax (fig. 2). The size of the erythrocytes does not change. The development cycle is 72 hours. From the schizonts of Pl. immaculatum (formerly called Pl. praecox), usually only ring forms are observed in the peripheral blood (fig. 2, III). They are very small, there is little protoplasm in them, and the rim of the ring is very thin. The presence of two nuclei in one ring is often observed (see separate table, fig. 2, 1). Schizogony takes place in the internal organs (capillaries of the brain, bone marrow, spleen). The number of merozoites is most often 16-20 (fig. 2). The development cycle is 24-40 hours. The appearance of the sexual forms is characteristic. As they grow, they lengthen and take on the appearance of a crescent. The pigment is located in the middle of the plasmodium (fig. 2). The erythrocyte is not enlarged. Upon staining, one can detect Maurer's clefts—large, coarse red granules, usually grouping in one place. A scheme of the main distinguishing features is provided in Table 1. The cultivation of the M. pathogen with subcultures, with the production of a series of generations in the sense that this is observed in bacteria, has not yet been resolved to this day. It has not yet been possible to inoculate parasites of human M. into any experimental animal, despite the enormous labor expended by a number of authors. For example, Bass (1922) unsuccessfully inoculated human M. into horses, dogs, foxes, monkeys, rabbits, mice, guinea pigs, hedgehogs, bats, wolves, cats, domestic and wild pigeons, magpies, owls, turtles, frogs, and lizards. Not a single animal became infected with M., although in some guinea pigs, remnants of malaria parasites circulated in the blood for 24 hours. Yoshino (1926) claims that he managed to inoculate Pl. vivax into young guinea pigs, but the drawings attached to his work are not convincing. Zia S. H. and Faust E. (1928) also unsuccessfully attempted to infect young hamsters (Cricetulus griseus). Table 1. Scheme of the main distinguishing features of M. pathogens. Plasmodia (forms) and erythrocytes: Young forms... Semi-adult forms... Adult forms... Division... Development cycle... Erythrocytes affected by parasites... Adult forms... Pl. vivax: Asexual forms - agamonts: Ring. 1/4-1/5 of erythrocyte diameter. Large ring with pigment. Amoeboid forms. 1/2-3/4 of erythrocyte diameter. Oval or round. Pigment—one or several clumps. Size up to 1 1/2 erythrocytes. 18-24 merozoites. More often 16. Mulberry shape. 48 hours. Pale, enlarged. Schüffner's granulation. Pl. malariae: Same. Rounded or bands. Pigment often golden-yellow. Much pigment. Same, but size smaller than erythrocyte. 6-12. More often 8. Daisy. Normal. Pl. immaculatum: Thin, very small ring. 1/5-1/4 of erythrocyte diameter. Ring. Up to 1/6 of erythrocyte diameter. Often 2 nuclei. Rare in peripheral blood. Rounded. Up to 1/2-3/4 of erythrocyte diameter. Pigment delicate. 8-24. More often 16-20. Morula. Small. Not enlarged. Maurer's clefts. Sexual forms - gamonts: Larger than erythrocyte. Irregular disk. Pigment brown, fine-grained. Smaller than erythrocyte. Irregular disk. Pigment dark brown, coarse-grained. Straight or curved crescents. Cultivation of plasmodia. All attempts to cultivate plasmodium on nutrient media until 1912 ended in failure. Sakharov (Tiflis) managed to maintain the viability of the plasmodium in leeches that had drunk the blood of M. patients with a large number of parasites for 7 days. Ziemann—only one day. The morphological features of the plasmodium did not change, but no further development was observed. In 1912, Bass, and later a whole series of researchers (Ziemann, Gurko and Hamburger, Mülhens, Perekropov, and others) managed to obtain both cultures and subcultures of the second and even third generation when inoculating human blood. Bass maintained the development of the plasmodium in culture for up to 7 weeks. Bass's method (1914): blood taken from a patient's vein is immediately defibrinated, and 0.1 cm3 of a 50% dextrose solution is added to every 10 cm3 of blood. Row (1917) and Sinton (1922) described a method that allowed for the growth of one generation of parasites even in a few drops of blood. Zhukov (Moscow) and Perekropov (Kazan) managed to obtain sporozoites in cultures according to Bass.
P. Mufel. III. Epidemiology. The epidemiology of malaria is determined by four main factors: the reservoir of the virus, the vector, the susceptible organism, and the external environment. The reservoir of the virus in malaria is formed by an infected person when sexual forms of the plasmodium—gametes (resp. gametocytes)—are present in their blood. Gametocyte carriers are the sole source for the infection of the vector that spreads the infection; this determines their exceptional epidemiological significance. The infection of the vector itself is possible only if a sufficient quantity of mature male and female gametes is present in the peripheral blood of the carrier. All other conditions being equal, the vector becomes infected more heavily the more gametes are in the carrier's blood. Hence the particularly important significance of malaria cases with an abundant content of parasites in the blood. In endemic areas, children are the main reservoir of the malaria virus; incoming populations after their infection can have an equivalent epidemiological significance—in both cases, the parasites are particularly abundant in the blood. However, the adult population of malarial regions also often contains parasites in the blood, although usually in limited quantities. Gametocyte carriers can be found among malaria patients; they are also encountered in latent and clinically mild forms of the infection. In primary infection, gametes usually appear in the blood some time after the onset of the disease, on average after 8-15 days in the tropical form, and after 7-10 days in the tertian and quartan forms (Dopter and de Lavergne; 1927). However, they can also be detected in the first days of the disease, according to Biedl (1917) even during the incubation period. The number of gametes increases from attack to attack: according to Ruge, in newly infected individuals they constitute up to 17-25% of schizonts, and in relapses 25-65%. The quantity of gametes is particularly large in tropical malaria, in which it can reach 50-150,000 (Knowles; 1928) and even 240,000 (Simons; 1919) per 1 mm3. This circumstance undoubtedly has great significance for the epidemic spread of tropical malaria. In tertian malaria, the quantity of gametes is smaller, but it is characterized by the frequency of relapses with the appearance of gametes. In quartan malaria, the quantity of gametes is the smallest, but the parasites persist in the blood for a long time. According to the observations of some authors, seasonal fluctuations in the appearance of gametes are observed in the same individuals. Thus, according to Sinton (1926) in India, during a systematic study of 2,000 people, gametes of Pl. immaculatum (praecox) were detected in 1% to 4% during July-October and reached 15% in November, falling to 0% in February. The sex ratio of gametes changes in different phases of the infection: in the first days of the appearance of gametes, male ones predominate, later female ones; later the male ones disappear and the female ones remain. Thus, according to Simons (1919), during the first 10 days, male and female gametes were in ratios of 3-7-9:1, during the 15th-18th day in ratios of 1:9-32-35; from the 21st day, male gametes disappeared completely (study of 12 cases of tropical malaria). The absolute number of gametocyte carriers in endemic areas can be very large. Thus, Craig in the Philippines observed up to 33% gamete carriers among patients with tropical malaria and up to 80% in latent cases of infection; carriage in latent tertian and quartan malaria was noted in 30%. According to many years of observations by Bogoyavlensky in Azerbaijan, among 3,633 malaria patients with parasites in the blood, gametes were detected in 61-70%; in different seasons of the year, the percentage of gametocyte carriers for different forms fluctuated as follows: Pl. vivax yielded 50-80%, Pl. malariae 70-100%, Pl. praecox 35-85%. The vector of malaria is mosquitoes of the genus Anopheles. However, not all species of Anopheles are equally susceptible to infection, and thus not all species are equivalent in epidemiological terms; for example, according to Brumpt (1927), out of 38 studied species of Anopheles, only 16 have particularly important significance in the spread of malaria; the role of 13 species is secondary, and the significance of 9 species is doubtful or unproven. The relative significance of various species of Anopheles is determined not only by their susceptibility to the plasmodium, but also by the peculiarities of their biology. Thus, "domestic" species (e.g., Anopheles maculipennis) are much more dangerous than "wild" species (e.g., A. bifurcatus). Species of Anopheles that have particularly important significance in the spread of malaria include An. maculipennis (Europe), An. culicifacies (Asia), A. funestus (Africa), and A. albimanus (America). Among the species that have practically no significance for the epidemiology of malaria, one can note An. rossi and An. jamesi (India), An. pharoensis (Egypt), and An. malefactor (Panama). Some observations allow for the possibility of seasonal fluctuations in the susceptibility of Anopheles; thus, according to observations by Bentley in Bombay, depending on the season of the year, the infection rate of Anopheles fluctuated from 0% to 15-19% with relatively small changes in temperature. Data on the elective susceptibility of various species of Anopheles to specific species of plasmodium are contradictory and unconvincing (Wenyon). Infection of the vector with the plasmodium occurs only under certain conditions. As already indicated, it is possible when a sufficient quantity of mature male and female gametes is present in the blood: according to Darling, at a ratio of gametes to leukocytes of 1:100, and according to James, 1:100-120. The repetition of mosquito bites is of essential significance: according to James, two-day feeding results in an infection rate of 40%, five-day feeding in 70%, and seven-day feeding in 100%. External temperature is of decisive significance, as sporogony is possible only in certain temperature zones. The minimum temperature for Pl. malariae is 16.5°, for Pl. vivax 17.5°, and for Pl. praecox 18° (Grassi). The optimal temperature for Pl. vivax and praecox is 24-30°, for Pl. malariae 19-24°. A temperature above 30°, while not improving the sporogony of Pl. vivax and praecox, has a harmful effect on the vector; Pl. malariae does not develop at 30°. The speed of sporogony depends directly on temperature: at 28-30°, the sporogony of Pl. vivax and Pl. praecox is completed within 7-8 days, and at 20-21° in 19-20 days. It is important to note that oocysts that have partially developed at a favorable temperature can safely withstand temporary drops in temperature, maturing subsequently when it rises accordingly. Thus, according to King (1917), Pl. vivax oocysts withstand: -1° for 3 days, -0.5° for 4 days, 7.3-10.6° for 6-7 days, 3.3-14° for 17 days; according to Wenyon, Pl. praecox oocysts that had partially developed at 22° withstood 9.7-18.7° for 15 days and subsequently matured at 21-24°. The duration of the vector's infectivity with sporozoites can be very significant, and one and the same mosquito can infect a mass of people. Thus, in experiments by James (1926), an infected Anopheles maculipennis was under observation for about 3 1/2 months (August-November), after which dissection revealed the presence of live sporozoites in it; during the experiment, the mosquito was kept for 3 weeks at 23-24°, for 2 1/2 months at 4-6°, and the rest of the time under various transport conditions; over 40 progressive paralytics were infected by the bites of the aforementioned mosquito (Knowles). The percentage of Anopheles infection under natural conditions represents a very conditional value that depends on the circumstances of its study (examination of "wild" or "domestic" mosquitoes, collections from premises with patients, collections from animal stalls, etc.); in general, the infection rate is higher the more malaria patients there are in the immediate vicinity. The statistics of findings are extremely varied. According to Celli, in highly malarial places, the infection rate of the vector usually does not exceed 1-2-4%; an infection rate of up to 10% is considered an exception (Wenyon). The overwintering of plasmodia in the body of the vector is denied by most authors, but the latest observations compel a reconsideration of this question. Wenyon in Macedonia observed infection with immature oocysts of Anopheles superpictus throughout the year with the following ratios: XI/1917-II/1918=0.5%, III-VI/1918=0.3%, VII-X/1918=1.5%, XI/1918=0.2%. If one takes into account that oocysts can mature with a corresponding increase in temperature, the possibility of the parasites overwintering appears credible. The number of vectors has only relative significance and is far from always proportional to the actual spread of malaria in a given area; in particular, despite a very limited number of Anopheles, malaria can be quite widespread. The presence of infected mosquitoes is of decisive significance, and it is necessary to take into account that one and the same infected mosquito can serve as a source of mass diseases for a relatively long time (attacking over the course of a number of days and multiple bites during one and the same night). On the other hand, the mosquito factor has significance only in the general complex of other factors. In the absence of a reservoir of the virus or the necessary external temperature conditions, despite an enormous number of vectors, an area can be free of malaria. In particular, the diversion of the vector from humans by animals (especially large ones) has great practical significance. Anopheles attacks animals quite willingly (apparently even preferentially), as they provide it with blood meals under the most accessible conditions (large surface area).
With appropriate quantitative ratios between mosquitoes, animals, and humans, a peculiar equilibrium can be established, under which humans are, as it were, freed from mosquito attacks. Such ratios can acquire significant importance for the epidemiology of malaria, limiting the spread of malaria despite the large number of vectors. Some authors, especially Roubaud, believe that as a result of prolonged animal feeding, "zoophilic races of Anopheles" can form that do not attack humans; these races are also distinguished by morphological features of the maxillary armature (14-15 teeth on the maxilla). With such "zoophilia," Roubaud attempts to explain the spontaneous disappearance of malaria in some places (e.g., in France) despite the preservation of a huge number of Anopheles ("anophelism without paludism"). However, in the opinion of many authors, there is no basis for recognizing special "zoophilic" races; the whole phenomenon is explained by simple ratios of labile equilibrium (see Biocenosis, Zoophilia). Susceptible organism. The causative agent of malaria is capable of infecting a human regardless of age, sex, or race; but a whole range of factors can, to one degree or another, exert an influence, relatively predisposing one to the disease or, conversely, protecting against it. Thus, children easily contract malaria, as they are especially accessible to the vector (tenderness of skin, lack of self-defense, weak resistance), while robust subjects can better withstand the disease compared to those who are emaciated, etc. All factors that in one way or another lower the resistance of the organism contribute to its infection with malaria and the severity of the infection. This includes insufficient nutrition, overwork, lack of adaptation to the climate among immigrants, occupational factors predisposing to infection (agricultural workers in rural areas, the army), various states of pathological burden (alcoholism in particular), moral depression, and others. The summation of unfavorable factors can lead to catastrophic consequences, especially among immigrants arriving in malarial areas; under these conditions, as a rule, the most severe epidemics of malaria develop. An illustration of this kind is provided by the malaria epidemic experienced in 1920 by the army in Azerbaijan, when military units were subjected to practically universal infection (from June to December, 21,920 malaria patients were registered in the hospitals of Baku, of whom 646 died). Social catastrophes under known conditions (mass resettlement of malaria patients, lack of quinine, etc.) can lead to a pandemic spread of malaria across the territory of entire states. A sharp example in this regard is also the most severe malaria pandemic that arose in the USSR during the Civil War (see below—statistics). The possibility is not excluded that with the infection of fresh masses, an increase in the virulence of the plasmodium takes place thanks to its mass passage. The question of congenital malaria has not yet received a final resolution. The majority of Western authors deny its possibility. However, a number of observations, and in particular those of Russian authors, establish with sufficient evidence that under known conditions, placental infection in malaria can take place. In this regard, findings of plasmodia in the blood and organs of premature fetuses are especially indicative. For example, in one case (Leger; 1918), Pl. vivax was found in the blood of a 7-month-old fetus born to a mother suffering from tertian malaria. In the case of Zdrodovsky (1929), crescents of Pl. praecox were discovered in the spleen of a dead fetus of 6-7 months of age, born to a mother in a state of malarial coma. In this same case, the barrier role of the placenta was clearly revealed (a large number of plasmodia in the mother's blood and in the placenta with a negligible content of them in the organs of the fetus). According to Ziemann, the normal placenta apparently represents an impassable barrier for plasmodia. It is possible that cases of placental infection arise only in the presence of pathological changes in it (e.g., infarcts). The relative rarity of congenital malaria speaks for the plausibility of such an assumption. Of special interest is the question of malaria among the permanent population of endemic regions; it is connected with the general problem of immunity relations in malaria. Immunity. Innate immunity to malaria is absent, and if it is observed in some subjects (Celli), it is only as a very rare exception. Racial immunity is also absent, although indications of the relative resistance of Negroes have been made repeatedly (Laveran and others); in the latter case, the question is obviously only about acquired endurance to infection (see below). In full analogy with the majority of protozoal infections, malaria is not capable of causing sterilizing immunity: the disease suffered does not protect against subsequent infections. This was especially clearly revealed in experiments with artificial inoculation of malaria. Only in some cases of artificial infection with blood containing Pl. vivax is a more or less prolonged (6-20 months) immunity to subsequent infection with virulent blood of the same species noted; however, even here, susceptibility to infection through a mosquito bite is preserved. Sterilizing immunity to malaria is not created among the population of endemic localities either. At one time, R. Koch (1899-1900) attempted to substantiate the existence of such immunity on the basis of a comparative age-based examination of the population of severely malarial tropical localities (Java and New Guinea). According to his observations, in such places, only children of younger age (up to 5-10 years) contain parasites in the blood with a maximum of infection (80-100%) within the range of up to 2 years; the semi-adult and adult population, on the contrary, is free of parasites due to immunity acquired thanks to infection in childhood. However, later numerous observations in various countries refuted Koch's position, showing that the adult population very often contains plasmodia in the blood even in the most severely malarial regions despite universal infection in childhood. Thus, for the adult population of tropical Africa, during mass examinations, the following figures for findings of parasites in the blood were established: Plehn (1906) - 50%; Ziemann (1909-1910) - up to 60%; Reichenow (1917) - 50-54%; Leger and Nogue (1923) - 47%; the same according to Bass (1917) in the Mississippi region - 19.2%; according to Christophers (1925) in India - 50%, etc. For an illustration of immunity relations in malaria, the following data from mass examinations of the local population in Azerbaijan at different ages can serve (see Table 2). Table 2. Thus, in endemic regions, the child population is affected by malaria to a particularly sharp degree, but the adult population, even at a deeply elderly age (examination of 30 old people at the age of 71 and above), can show infection with plasmodia in a large percentage. Sterilizing immunity in malaria does not develop. This lack of immunity, however, is compensated by the relative endurance to infection, which the malaria-diseased population gradually develops as a result of continuous infections; but this endurance is actually connected with the presence of latent infection. In other words, the relations of immunity in malaria are formed according to the general principle of labile infections (see Immunity, immunity in protozoal infections). The acquired endurance, however, is relative (possibility of relapses upon disturbance of equilibrium and only relative resistance to superinfection). Later observations by Christophers (1925) in India provide particularly indicative illustrations of the dynamics of the gradually developing resistance of the malaria-affected population in relation to malaria. According to Christophers' studies, children up to 2 years old, with a parasitic index equal to 100%, contained plasmodia in the blood in quantities of over 10,000 per 1 mm3 and all showed a temperature reaction; at the age of 2-5 years, with 100% infection (parasitic index 100%), the quantity of plasmodia in the blood was equal to 1,200, with the temperature reaction not being observed constantly; at the age of 6-10 years, with the same percentage of infection, the quantity of parasites in the blood fell below 1,000, and fever a) Childhood age (Bogoyavlensky; 1924-29). Age (years)....... Spleen index (in %). Plasmodia (in %)...... 40.7 2 47.3 50.8 57.1 52.1 4 54.9 57.4 5 64.8 53.0 6 63.1 44.9 7 66.6 35.4 74.3 35.8 75.2 34.0 10 78.7 26.3 On average 63.1 42.9 b) All ages. Winter examination after a sharply epidemic season (Zdrodovsky and Lindtrop; 1922-23). Age (years)...... Spleen index (in %) Plasmodia (in %)..... 1-5 6-10 11-15 16-20 100.0 100.0 97.8 87.5 83.4 77.0 60.0 40.6 21-30 77.2 45.6 31-40 79.1 40.9 41-50 51-70 62.1
47.8 29.0 | 30.4 On average 82.0 50.7 was absent; in adults, parasites were detected in 50%, there was no temperature reaction at all, and only in 10% were there enlarged spleens. External environment. In the complex of external environmental factors, climate and specifically temperature relations are of particularly important significance. The epidemiological role of temperature is twofold: it decisively influences sporogony and at the same time exerts a significant influence on the biology of the vector. The significance of temperature for sporogony has already been examined. As for the biology of the vector, temperature primarily affects its aquatic metamorphosis. All other conditions being equal, this metamorphosis occurs the faster, the higher the temperature. Thus, according to Martini, at 24-27° the metamorphosis of Anopheles ends within 7-9 days; at 16-19°—within 20-30 days. According to observations by Brenn and Voskresensky in Azerbaijan (1927), the aquatic metamorphosis of Anopheles maculipennis under natural conditions in different months had the following durations: VII—average temperature = 24.5°, VIII—average temperature = 26.9°, IX—average temperature = 18.9°; corresponding duration of metamorphosis: 17-19 days, 17 days, 30 days. Thus, the longer and warmer the summer season, the more generations of the vector are born; conditions ensuring sporogony proceed in parallel. As a result, countries with a long hot season show the greatest predisposition to malaria; hence the special predisposition of subtropical and tropical countries. Temperature relations change depending on the altitude of the terrain; hence the significant importance of the orographic factor for the spread of malaria. Lowlands are particularly predisposed to malaria, while heights, on the contrary, are less favorable and beyond a certain limit become immune. These limits, however, vary greatly in different places. Sometimes foci of malaria are encountered at significant altitudes; for example, at an altitude of up to 1,000 m in Macedonia, 1,600 m in German East Africa, 2,000 m in the Himalayas, 2,500 m in Peru (Mühlens; 1921). An example of the dependence of the spread of malaria on the altitude of the terrain is provided by the experience of surveying the Ganjin district in Azerbaijan: in the lowlands (below 250 m) in 30 villages among 829 children, the splenic index turned out to be 71% and the parasitic index 34%; in the same district in 9 villages from the foothills and mountains (from 750-800 m to 1,000-2,000 m) among 417 children, the splenic index was 11.3% and the parasitic index 1.4% (Chergeshtov; 1925). Of other climatic factors, some authors (Bentley et al.) point to the significance of relative humidity. The significance of winds "carrying" mosquitoes to leeward places occurs only in limited cases (Rudnik notes the significance of winds in some regions of Macedonia). The water factor, along with the temperature factor, is of decisive importance for the epidemiology of malaria, since the breeding sites of Anopheles are connected with it; the latter can be characterized only schematically. In typical cases, these are non-agitated, stagnant, or weakly flowing bodies of water with relatively clean and not overly saline water and developed submerged or floating flora. This characteristic, however, is conditional and corresponds only to the optimal type. Thus, Anopheles breeding sites can also be found in heavily polluted bodies of water (e.g., with oxidizability according to Kubel up to 545 mg—Voskresensky and Brenn); the salt content in them can sometimes be very high: 19.5‰ (Anopheles maculipennis—Corsica), 25-30‰ (Anopheles Rossi—India), 40‰ (An. multicolor—Sahara); according to observations by Zdrodovsky in Transcaucasia, the limiting concentration is 10‰. The optimal pH for the development of Anopheles larvae is 7.2-7.6 (observations on peat quarries by Smorodintsev, Odovaya, and Sebentsov). On the other hand, if the presence of submerged or floating flora (e.g., "water wool" in Transcaucasia) is particularly characteristic, at the same time breeding sites can also be in the absence of flora or in the presence of only emergent vegetation (observations by Zdrodovsky and Voskresensky in Transcaucasia). For some species of Anopheles, breeding sites are extremely peculiar (e.g., accumulations of water in tree hollows—Anopheles nigripes). There is also observed elective colonization of certain types of water bodies by specific species of Anopheles (e.g., stagnant water bodies in the beds of mountain rivers in Azerbaijan are electively colonized by Anopheles superpictus). Water bodies can be sites of abundant Anopheles breeding regardless of their size (sometimes small water bodies acquire particularly important significance); but water bodies must have a certain duration of existence, ensuring the minimum period of Anopheles metamorphosis. Hence, for example, on the southern outskirts of the USSR, water bodies with a duration of less than 2 weeks have no epidemiological significance. Evaporation, infiltration, and surface runoff are the main types of water circulation; any kind of obstruction in this natural circulation can lead to the formation of water stagnation and breeding sites. By origin, stagnant water bodies can be classified according to the following, practically most common types: a) Stagnant flooding of spontaneous and natural origin: "flood" inundations along river systems due to spring river overflows; coastal stagnation in rivers, as well as accumulations of stagnant water in river beds (e.g., in the beds of mountain rivers); water stagnation in the mouths of rivers flowing into the sea, during dune blockages; swamps of the coastal strip, formed due to the obstruction of the outflow of waste waters by dune deposits ("liman type"); spring-fed waterlogging; waterlogging from exposed high-standing groundwater; infiltration waterlogging of depressions from neighboring water systems; lake type of water bodies; surface accumulations of atmospheric water, etc. b) Stagnant flooding of artificial origin: water stagnation from irrigation systems—inside canals (stagnation from thickets, coastal stagnation, stagnation from the destruction of banks) and around canals (waterlogging from water breaches and infiltration waterlogging of natural or artificial depressions); waterlogging from irrigation waste systems; waterlogging from irrational irrigation ("flooding" irrigation); waterlogging of rice plantations during continuous irrigation with slowly flowing water or flooding; water stagnation in improperly constructed open drains; waterlogging from the discharge of excess or used water; subsurface and infiltration flooding of artificial earth excavations (quarries along railway tracks, peat quarries, etc.), artificial ponds, pools, economic reservoirs; gushing water supply sources; drinking wells, cisterns, etc. Epidemiological characteristics of a malarial area. Geographical location, orography, climate, hydrography, state of the vector, distribution of the population by orographic zones, socio-economic conditions, etc., determine the general predisposition of a given area to malaria. Statistics of the actual incidence of malaria in the population and mortality from it, accounting for the movement of primary and recurrent diseases in a year, and an analysis of their comparative parasitology provide objective elements for the general characterization of a malarial area; long-term statistical observations are especially valuable. Detailed data on the malarial prevalence of populated areas (or individual groups of the population) are compiled by determining so-called malaria indices on mass material. Among the latter, the following are distinguished: 1) Splenic index, or the percentage ratio of persons with an enlarged spleen to the total number of those examined. The index is relatively stable and provides a very valuable characteristic of the spread or extensiveness of malaria in a given area. 2) The Ross index is an indicator of the average degree of spleen enlargement among those examined; it characterizes the intensity of malarial prevalence in the population; it is calculated by the formula: (a+3b+6c+9d)/(a+b+c+d), where a is the number of non-enlarged spleens (the volume of a normal spleen is taken as unity), b is the number of small spleens protruding from under the costal arch by 1-2 transverse fingers (enlargement by 3 times), c is the number of medium spleens protruding by 3-5 fingers (enlargement by 6 times), d is the number of large spleens, i.e., reaching the navel and more (enlargement by 9 times); the Ross index in practical settings provides a quite satisfactory characteristic of intensity; an increase in this index to 5 and higher indicates particularly severe prevalence. 3) Parasitic index, or the percentage ratio of persons with plasmodia in the blood to the total number of those examined; the index is extremely valuable, as it provides a characteristic of the virus reservoir (especially when accounting for gametes), but is very variable and therefore not very accurate; it depends in particular on the research methodology; at the present time, it is determined as a rule using a thick drop. 4) Endemic index, or the total percentage of persons in whom objective signs of malaria are detected.
(enlargement of the spleen and plasmodia, in combinations or separately), the index may yield higher values compared to the splenic and parasitic ones, because in the absence of spleen enlargement, there may be plasmodia in the blood and vice versa. 5) Cyst and sporozoite index, or the percentage of findings of infected mosquitoes; an index that is particularly valuable in epidemiological terms, but extremely conditional, because it depends on a whole series of factors (see above). The sporozoite index has preferential value, because findings of cysts do not yet speak to the actual ability of Anopheles to infect humans (e.g., immature cysts in overwintering mosquitoes). Malaria indices determined in humans, including the splenic one, in countries with seasonal malaria undergo changes depending on the season (higher values during the malaria season and lower ones outside of it). For surveys using malaria indices, children (usually up to 10 years old) are preferred as the most sensitive and at the same time the most sedentary element. The presence of a malaria focus in a given locality is most accurately determined by two signs: the presence of Anopheles and the occurrence of demonstrably primary diseases (e.g., among children born after the end of the malaria season of the previous year). Based on the survey of populated points (all or representative ones) with the determination of splenic indices, a malaria map of the given area is compiled, on which the malaria prevalence of individual points is depicted graphically.
Zdrodowski. IV. Statistics and geographical distribution. 1. Worldwide distribution. Malaria is one of the most widespread diseases on the globe, both in terms of the number of people suffering from it and the vastness of the areas where it is observed endemically. Its largest foci are concentrated in countries with a hot and humid climate, in particular in tropical and subtropical countries; but its spread goes far beyond the borders of these countries and extends in the Northern Hemisphere in some places to the northern borders of the temperate zone. Its distribution by individual parts of the world is as follows. In Asia, it is a great calamity for British India, where its spread reaches enormous proportions. Over the last 10 years, over 1 million people were treated for malaria annually in the hospitals of India, and over 2,000 died. In some provinces, more than 50% of all children die from malaria. In Bengal, about 0.5 million people died from malaria in 1925/26, which constitutes 66% of total mortality. In individual cities of India, mortality from malaria in recent years has reached 250 per 100,000 population (see below). In Ceylon (pop. 4.5 million), about 1 million malaria patients were treated in dispensaries annually from 1922-26, and about 30,000 in hospitals. In the Dutch East Indies, according to data from 171 hospitals for 1924, malaria patients constitute about 10% of all patients. In the Malay Federation (pop. 1,534,000 in 1928), 16,531 deaths from malaria were registered in 1926, and 20,736 in 1927. Malaria accounts for over 30% of all causes of death. On the island of Cyprus in 1926, malaria accounted for 75.8% of all infectious diseases. Malaria is strongly prevalent in Asia Minor, in South China, and in the Philippine Islands. Table 3 presents mortality rates from malaria in recent years in some cities of Asia. Table 3. Mortality from malaria per 100,000 population. Cities Bombay... Calcutta Madras... Manila... Rangoon... Singapore... Tehran... 1926 1927 1928 19.0 1929 14.3 42.7 25.5 149.3 119.7 110.2 78.9 258.6 249.9 - 126.8 16.1 10.4 10.8 13.0 61.6 59.2 64.7 45.7 396.0 259.3 240.3 201.3 155.2 98.4 93.2 30.4 Africa is the classic country of malaria, which is the main enemy of the colonization of the country (Nocht). Numerical data on the spread of malaria are extremely scarce. It is strongly prevalent in Egypt. In Kenya in 1926, 42,972 people were treated in hospitals (2,565,000 pop.); on the island of Mauritius (pop. 388,000), about 2,000 people died from malaria annually in 1925-27. In Nyasaland (pop. 1,306,000), 3 to over 4 thousand people died from malaria annually during the same years. In Tanganyika, mortality from malaria constitutes 21.5% of total mortality. In Uganda (pop. 3,242,000), about 30,000 cases of malaria are registered annually. Malaria is strongly
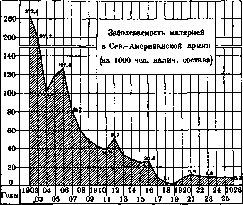
Figure 3.
prevalent in America. In the USA, about 160,000 cases of malaria are registered annually in recent years. It was extremely strongly prevalent there even at the beginning of the 20th century, but at the present time, it has significantly decreased. An indicator of the success of the fight against malaria in America is the decrease in its incidence in the North American army: the incidence of malaria among it was 272.3 per 1,000 personnel in 1902; in 1919, the incidence decreased to 2.3; in subsequent years, like in many other countries, it showed an increase, only to begin to decrease again later (Figure 3). In Mexico, from 8 to 9.5 thousand deaths from malaria were registered annually for 1925-28. In the West Indies, in Haiti (pop. 2,500,000), about 1,000 people die from malaria annually; in Puerto Rico, mortality from malaria in 1911 was 190 per 100,000 population; in 1921, it dropped to 114; in 1925, it was 105 per 100,000 population; on the island of Jamaica, in the city of Kingston, mortality from malaria was 40 in 1924, 80 in 1925, and 31 per 100,000 population in 1926. Large foci of malaria are concentrated in Central America. The digging of the Panama Canal entered the history of malaria: the first period of construction (1881
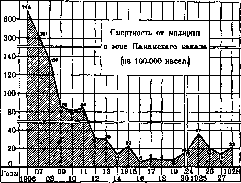
Figure 4. 1889), when a French company was at the head, was accompanied by such cruel mortality of workers from malaria and yellow fever (annual mortality up to 240 per 1,000) that work had to be completely stopped. In the second period of construction, carried out by the Americans (1905-12), malaria initially also showed a high increase, but soon, thanks to systematically conducted anti-malaria measures, it decreased sharply and dropped to very small figures. The incidence and mortality in the Panama Canal Zone for 1906-1921 are given in Table 4 and in Fig. 4. Table 4. Incidence and mortality from malaria in the Panama Canal Zone for 1906-1921 (per 1000 population). Years Incidence Mortality 1906, 1907, 1908, 1909, 1910, 1911, 1912, 1913, 821, 424, 282, 215, 187, 184, 110, 76, 7.45, 3.51, 1.37, 0.85, 0.81, 0.84, 0.31, 0.30 Years Incidence Mortality, 82, 0.14, 0.23, 1916, 1, 16, 0.06, 1917, 0.09, 1918, 0.08, 1919, 0.08, 1020, 0.15, 1921. In recent years (1925-28), from 1,000 to 1,500 cases of malaria and from 20 to 48 deaths from malaria are registered annually in the Panama Canal Zone (population 127,000). In South America, malaria is especially prevalent in the valleys of the Orinoco and Amazon rivers, in particular in Argentina and Brazil. For some South American cities, mortality from malaria per 100,000 population for recent years is expressed in the following indicators (Table 5): Table 5. Cities Belem... Callao... Lima... Manaus... Mexico... Nictheroy... Rio de Janeiro... Salvador... Santos... 1926 1927 1928 271.2 248.8 233.8 77.4 39.1 41.3 68.9 45.7 50.4 562.8 697.2 781.2 8.2 5.7 4.1 26.6 22.8 28.5 25.2 25.4 21.5 175.3 137.9 143.7 36.4 42.5 44.0 The construction of railways in malarial areas of America encountered the greatest difficulties due to malaria. 1856-60. Table 6 gives an idea of the level of malaria at the end of the 19th century, showing mortality from malaria per 100,000 population, on average per year for 1891-1900 for some countries of Western Europe. Table 6. States | Mortality | from malaria States
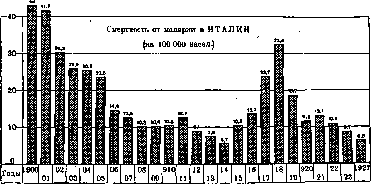
Figure 5.
difficulties due to malaria. In Australia, over the last 10 years, from 50 (1916) to 35 (1926) people per 100,000 population die from malaria annually. The most affected is the state of Queensland. In Western Europe, malaria is most prevalent in the countries of the Mediterranean Sea. Since ancient times, vast regions where Greek and Roman culture once flourished have suffered heavily from it. Many researchers believe that the fall of ancient culture was facilitated by malaria, which spread rapidly in these areas. "Where beautiful cities flourished in antiquity, now there are only frail, malaria-exhausted faces of a very impoverished pastoral and peasant population" (Nocht). Throughout the 19th century, several major malaria epidemics were observed in Europe. The first of them occurred in 1806-12 (Napoleonic Wars), the following ones in 1824-27, 1846-49, 1856-60, 1866-72, and the last one, which covered Holland and northwestern Germany, in 1899-1903. The highest increases, which had the character of pandemics, were the rises in malaria in 1806-12 and Mortality from malaria Italy...
46.2
23.0
Scotland...
1.7
Of the individual countries of Western Europe, malaria is most widespread and best studied in Italy. Thanks to a systematically conducted anti-malaria campaign, it is gradually declining. In 1887, 71 per 100,000 population died from malaria; in 1900, 49 people; in 1926, mortality dropped to 7 per 100,000. During the World War, a significant rise in malaria was observed (Figure 5). Malaria is distributed unevenly across individual provinces. Table 7 (see column 603) indicates mortality from malaria by individual provinces of Italy per 100,000 population (according to data for 1891–1900). Spain is heavily affected by malaria. At the beginning of the 20th century, 4,000 to 5,000 people died from it annually; in recent years, mortality from malaria has dropped below 1,000 (in 1928, 736 people; Fig. 6). Pittaluga estimates the number of malaria patients in Spain at 300,000 people. The province of Cáceres is the most affected by malaria, where mortality from malaria for 1922–1924 amounted to between 41.3 and 63.4 per 100,000 inhabitants per year (the average for Spain for the same years was between 5.5 and 7.1). Malaria is widespread in Greece, in the Baltic states, in Hungary, Galicia, Bosnia, and Dalmatia.
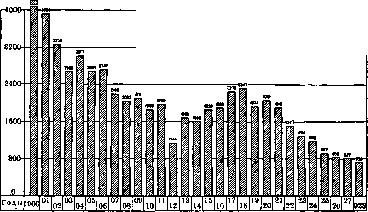
Figure 6. Mortality from malaria in SPAIN (absolute figures).
Table 7. Provinces Mortality from Malaria Provinces Mortality from Malaria Sardinia 255.2 Tuscany 45.4 Basilicata 186.6 Lombardy 11.3 Apulia 116.6 Liguria 7.5 Calabria 109.5 7.1 Sicily 101.0 6.7 Latium 74.9 1.7 Abruzzo 59.0 2. Malaria in the USSR. Before the World War, about 3.5 million cases of malaria were registered annually in Russia, or about 215 per every 10,000 population. Among other infectious diseases, malaria occupied the highest place (see Infectious diseases, Table 9). The highest number of cases was registered in the southern regions, the lowest in the northern ones (see below). While remaining at approximately the same level in one and the same region for a number of years, malaria from time to time produced sharp rises in morbidity in these areas; it acquired the character of an epidemic, which, after a certain period, subsided, and malaria again passed for a number of years into its endemic level, which was usual for the given region. From time to time, malaria went far beyond the limits of its usual distribution, covered huge spaces, and acquired the character of a severe pandemic. Table 8 presents figures for malaria morbidity in Russia and the USSR for the period from 1892 to 1929. Figures 7 and 8 present curves of malaria morbidity in Russia and the USSR from 1892 to 1929 and for 3 provinces: Samara, Saratov, and Simbirsk (Ulyanovsk). These curves give an idea of the periodic rises of malaria—its "epidemics." For Russia as a whole before the war, these rises during the indicated period were in 1894–95, in 1897, in 1899, and in 1903; for Saratov province—in 1896–99, in 1901–04, and in 1907–08. The rises in malaria in the other provinces shown in the figure also fall on approximately these same years. These rises cover significant spaces and owe their origin to causes common to a number of regions. The latter have not been sufficiently studied. One of the most important causes is the fluctuation of meteorological data, which have a great influence on the development of Anopheles. In individual years and in individual regions, the flooding of rivers and the formation of swampy areas are of great importance. In places where artificial irrigation is widely spread, the disruption of the irrigation system has the greatest influence on the fluctuations in the height of malaria. In regions where agriculture is at a low level and depends entirely on climatic conditions, a connection is noted between crop failure and an increase in malaria (Figure 9), which can be explained both by meteorological factors and by a mass weakening of immunity among the population due to malnutrition. [Some authors (Kushev) consider the connection between malaria and famine to be unproven.] The causes of the malaria pandemic in the USSR during the Civil War were more complex (see below).
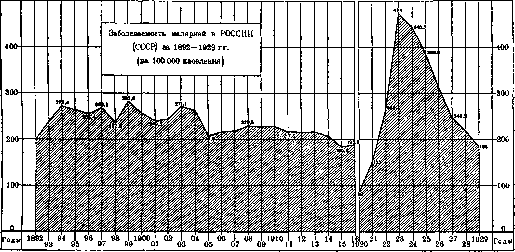
Figure 7.
Table 8. Malaria morbidity in Russia and the USSR from 1892 to 1929. Years Absolute figures Per 10,000 population Years Absolute figures Per 10,000 population 1892 2,227,817 200.0 1911 3,633,656 229.5 1893 2,904,829 240.8 1912 3,497,724 217.5 1894 3,343,682 272.4 1913 3,537,060 215.7 1895 3,220,298 262.0 1914 3,521,213 216.6 1896 3,186,052 255.4 1915 3,119,518 208.1 1897 3,413,999 269.3 1916 2,611,119 185.0 1898 3,056,229 237.2 1917 1,417,335 190.6 1899 3,697,347 282.5 1918 508,157 100.3 1900 3,417,678 256.7 1919 1,266,274 153.0 1901 3,255,684 240.5 1920 2,094,275 268.0 1902 3,347,632 243.3 1921 5,668,079 474.0 1903 3,808,115 271.1 1922 5,865,825 445.7 1904 3,629,933 254.8 1923 4,874,819 388.8 1905 3,021,321 208.9 1924 4,600,650 312.9 1906 3,163,287 215.2 1925 3,718,107 249.9 1907 3,269,699 218.4 1926 3,348,214 219.9 1908 3,492,363 229.5 1927 2,993,072 183.0 1909 3,555,315 227.9 1928 1929 Table 9. Malaria morbidity by individual regions of Russia (per 10,000 population). Regions 1911 1912 1913 1914 Northern 27.0 23.2 18.9 22.7 Lake 17.2 17.0 15.7 13.5 Belarusian 43.7 40.5 38.7 28.1 Moscow-Industrial 78.9 63.7 64.9 59.8 Central-Agricultural 268.9 246.1 241.6 215.8 Middle Volga 334.2 321.8 340.4 336.6 Ural 126.2 128.8 148.0 143.2 Lower Volga 431.4 403.5 394.7 459.6 Little Russian 300.3 301.1 249.6 237.6 South-Western 47.0 43.4 33.0 29.0 Novorossiysk 307.6 280.3 253.1 200.0 Caucasus 732.3 808.2 783.7 679.8 Siberia 100.2 107.6 109.3 88.3 Central Asia 200.0 201.5 222.6 234.8 The distribution of malaria by individual regions of pre-war Russia was far from uniform. Table 9 presents morbidity indicators for different regions of Russia for four years—1911–1914. As a rule, malaria morbidity indicators were 50 per 10,000 population, while in the Caucasus they reached 8% in relation to the population. Of the individual provinces and regions, the following were the most affected by malaria in 1911–14 (Table 10). A more detailed distribution of malaria morbidity by individual provinces for 1902–11 is given in Fig. 10. All the figures cited above give an idea not of the actual number of newly ill with malaria for each year, but only of the number of patients registered by medical personnel. This registration in individual places was very incomplete due to the insufficiency of medical aid to the population. On the other hand, chronic patients could be registered several times and thereby increase the number of registered malaria cases. It is not possible to make the proper correction and establish the true morbidity indicators for individual regions. It can only be noted that in the areas most severely affected by malaria, for example in the Caucasus, medical aid was most poorly organized, and consequently, the morbidity indicator in them must be significantly higher.
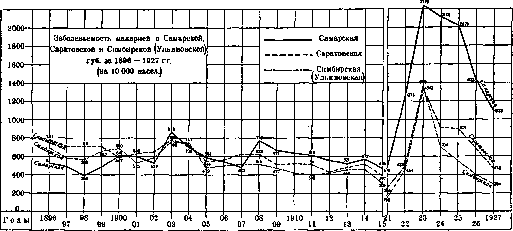
Figure 8.
they increase as one moves from north to south: in the northern regions they constituted relatively small values (in the Northern, Lake, and Belorussian regions—see Table 10. Provinces most affected by malaria in 1911–14 (morbidity per 10,000 population). Provinces and regions: 1911, 1912, 1913, 1914. Black Sea: 1448.8, 1278.2, 1461.4, 1169.8. Kuban: 1145.3, 1204.2, 1253.4, 1067.0. Baku: 826.4, 1151.7, 1028.9, 868.6. Kutaisi: 653.8, 730.7, 711.8, 642.6. Terek: 630.3, 678.7, 674.8, 673.9. Tiflis: 614.4, 656.4, 603.6, 509.2. Dagestan: 558.7, 646.3, 508.9, 438.9. Erivan: 541.0, 640.2, 638.4, 537.8. Stavropol: 585.9, 633.5, 634.2, 386.2. Samara: 610.0, 553.5, 521.0, 566.0. Saratov: 911.2, 430.2, 479.7. Astrakhan: 343.4, 450.4, 452.0, 468.7. Voronezh: 430.1, 398.4, 415.0, 337.9. Tambov: 401.9, 343.9, 362.0, 363.1. Simbirsk: 399.5, 420.6, 458.0, 451.2. It is significantly elevated. Apparently, the relatively low morbidity rates in Central Asia (about 2% in relation to the population), where the actual morbidity was likely significantly higher, are explained by a lack of medical assistance and shortcomings in registration. The World War, and especially the Civil War, prepared the ground for an unprecedented rise in malaria, which by the end of the Civil War had taken on the character of a sharply pronounced pandemic and a severe national disaster in the USSR. The malaria morbidity rate across the entire country, according to official data, rose from 215 per 10,000 population in the pre-war years to 450–475 in 1923–24. Malaria went far beyond its usual distribution; it engulfed the entire country and advanced, in particular, into the northern regions. Severe forms of tropical malaria, observed before the war exclusively in severely malarial regions—in the Caucasus, the Lower Volga region, and Central Asia—spread throughout the republic. Malaria in these years proceeded in very severe forms, with high mortality. The causes of this unprecedented development of malaria are still a subject of study by epidemiologists [both Russian and foreign (Wolter, 1930)]. Individual factors that contributed to the development of the pandemic come down to the following: 1) the unprecedented movement of human masses and the introduction of malaria from affected places into unaffected ones; 2) a change in climatic conditions; a sharp rise in temperature in 1921–22, which contributed to the reproduction of Anopheles; 3) the wilding of the soil due to the cessation of its cultivation in many places; 4) the swamping of vast areas due to the destruction of sanitary-technical structures and water management systems, for example, in Central Asia and the Caucasus; for the entire USSR according to official data it constituted 100 per 10,000 inhabitants—a figure clearly not corresponding to reality. In 1921, it rose to 140 across the country. But already in this year, an unprecedented rise was noted in individual regions. Thus, in the Northern region, with a pre-war morbidity rate of 19–27 per 10,000 (see Table 9), it rose in this year to 119 per 10,000, i.e., it increased by approximately 5 times; in Arkhangelsk Province, where malaria morbidity before the war was about 10 per 10,000 population, the rate in 1921 rose to 176, i.e., it increased 17 times; in North Dvina Province in the same year it rose to 278, and in the Kotlas district, morbidity in 1921 reached 72.5% in relation to the population. Such are some figures relating to the far north. Malaria rose extremely in places
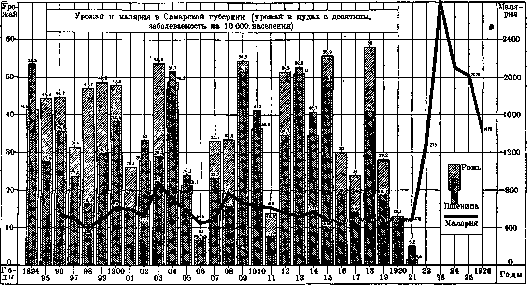
Figure 9. 5) a sharp decrease in the number of livestock, which distracts Anopheles from humans; 6) a complete absence of quinine during the Civil War due to the blockade of the country and the accumulation of a huge number of gametocyte carriers; 7) finally, famine played a large role in susceptibility to malaria, sharply weakening the population's immunity to malaria. It also became the cause of the development of a large number of severe forms of malaria in the starving regions (mass illnesses with comatose forms with high mortality). One can give only approximate numerical expressions of this pandemic. With the beginning of the World War, the number of annually registered malaria patients fell sharply, which must be explained exclusively by the deterioration of their registration. If in 1911–13, an average of 215 malaria cases per 10,000 inhabitants were registered in all of Russia, then in 1914 the morbidity rate dropped to 208, in 1915 to 185, and in 1916 to 190. For 1917–19, the information is so incomplete that it does not give an idea of malaria morbidity. In 1920, the morbidity rate for its usual distribution. Thus, in the Volga German Republic, malaria morbidity in 1921 according to official data constituted 25% in relation to the population. This year must therefore be considered the first year of the pandemic spread of malaria. The following years show its further rise. As a whole for the USSR in 1922, 268 malaria cases per 10,000 inhabitants were registered; in Arkhangelsk Province, the morbidity rate for this year was 274 per 10,000 (27 times higher than pre-war). 1923 gives the highest morbidity rate for the entire USSR: 474 per 10,000, i.e., out of every 100 people of the population, 4.7 were registered as malaria patients. In Arkhangelsk Province for this year, the morbidity rate was 409 per 10,000 (in individual districts—over 8%); in North Dvina—338 (in individual districts—up to 34%), in the Volga German Republic—5,084, in Saratov Province—1,208, in Samara—2,347, in Astrakhan—2,542 (in 1913—452), in Moscow—537 (before the war 120 per 10,000), etc. 1924 gave 445.7 cases for the Union
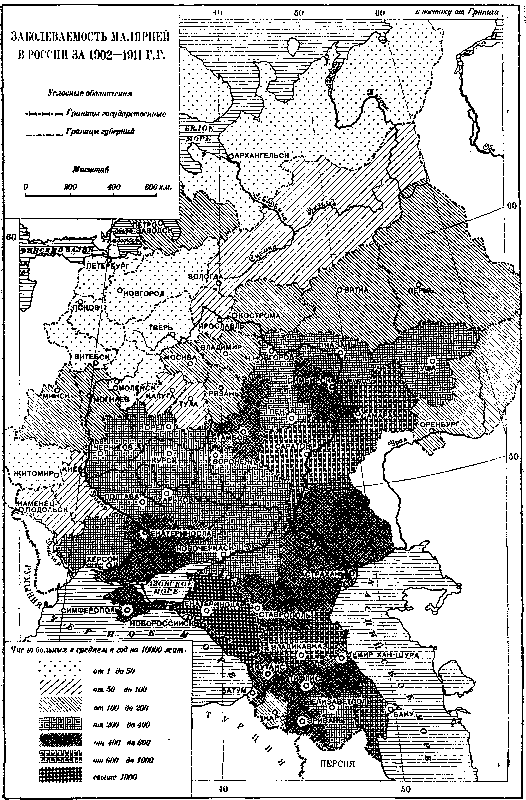
Figure 10.
Morbidity of malaria
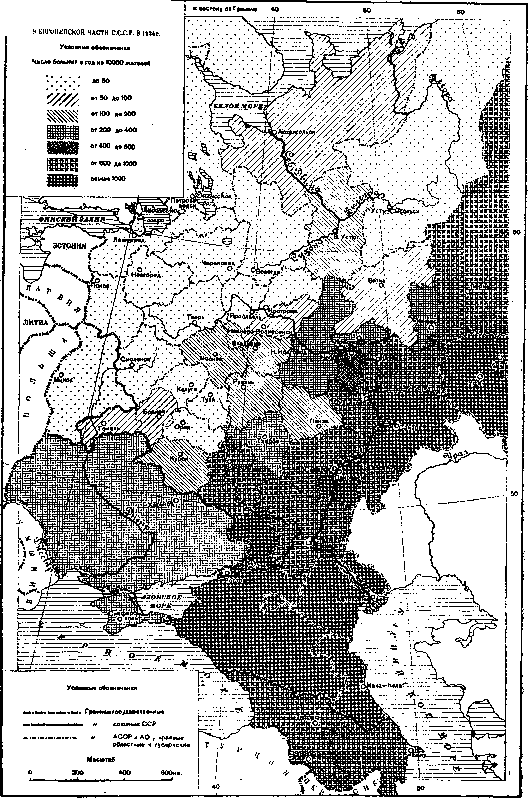
Figure 11.
Morbidity of malaria AND THE NETWORK OF ANTI-MALARIAL INSTITUTIONS IN THE EUROPEAN PART OF THE USSR. In 1928. Legend: Tropical Institutes, Protozoal Departments of Sanitary Institutes, Malaria Stations. Number of patients per year per 10,000 inhabitants: Up to 50, from 50 to 100, from 100 to 200, from 200 to 400. 1 Leningrad, 2 Bogorodsk, 3 Shatura, 4 Mikhnevo, 5 Kudinovo, 6 Power Station named after Klasson, 7 Bolshevo, 8 Orekhovo-Zuyevo, 9 Vladimir, 10 Izhevsk, 11 Yoshkar-Ola, 12 Kazan, 13 Cheboksary, 14 Kanavino, 15 Nizhny Novgorod, 16 Ryazan, 17 Tula, 18 Skopin, 19 Ranenburg, 20 Lipetsk, 21 Ramon, 22 Pavlovsk, 23 Ostrogozhsk, 24 Voronezh, 25 Tambov, 26 Ulyanovsk, 27 Syzran, 28 Penza, 29 Volsk, 30 Kamyshin, 31 Balashov, 32 Saratov, 33 Sverdlovsk, 34 Perm, 35 Chelyabinsk, 36 Ufa, 37 Buguruslan, 38 Buzuluk, 39 Samara, 40 Dergachi, 41 Pugachev, 42 Pokrovsk, 43 Orenburg, 44 Uralsk, 45 Novo-Uzensk, 46 Yalta, 47 Kherson, 48 Nikolaev, 49 Krivoy Rog, 50 Mogilev, 51 Kharkov, 52 Kursk, 53 Sumy, 54 Poltava, 55 Kremenchug, 56 Dnepropetrovsk, 57 Konstantinovka, 58 Izyum, 59 Artemovsk, 60 Lugansk, 61 Stalino, 62 Mariupol, 63 Starobelsk, 64 Kamensk, 65 Sochi, 66 Tuapse, 67 Tiraspol, 68 Gelendzhik, 69 Goryachy Klyuch, 70 Maykop, 71 Novorossiysk, 72 Anapa, 73 Krasnodar, 74 Slavyanskaya, 75 Armavir, 76 Kropotkin, 77 Umanskaya, 78 Yeysk, 79 Rostov, 80 Novocherkassk, 81 Labinskaya, 82 Stalingrad, 83 Yenotaevsk, 84 Krasny Yar, 85 Astrakhan, 86 Dolban, 87 Shelkovskaya, 88 Khasavyurt, 89 Derbent, 90 Buinaksk, 91 Vladikavkaz, 92 Nazran, 93 Grozny, 94 Mozdok, 95 Georgievsk, 96 Pyatigorsk, 97 Ardon, 98 Nalchik, 99 Ochamchira, 100 Zugdidi, 101 Gali, 102 Senaki, 103 Ozurgeti, 104 Poti, 105 Kobuleti, 106 Batum, 107 Karayazy, 108 Kutais, 109 Gori, 110 Echmiadzin, 111 Telav, 112 Idzhevan, 113 Shamkhor, 114 Dilizhan, 115 Lizakh, 116 Ganja, 117 Ani-Abad, 118 Nukha, 119 Kuba, 120 Agdash, 121 Geokchay, 122 Abdully, 123 Dzhebrail, 124 Saliany, 125 Saliany, 126 Megri, 127 Nakhichevan, 128 Davalu, 129 Erivan, 130 Tiflis, 131 Baku, 132 Makhach-Kala, 133 Odessa, 134 Moscow, 135 Kiev, 136 Ivanovo-Voznesensk, 137 Sukhum
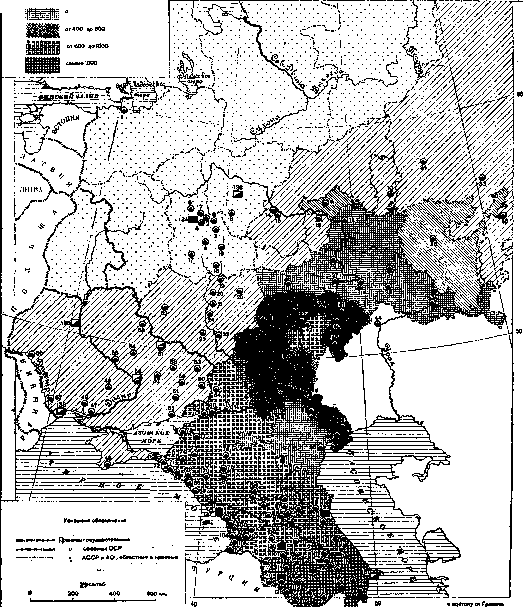
Figure 12. 20 15 per 10,000 population. Malaria incidence by individual provinces for 1924 is shown in Figure 11, and for the most affected provinces for 1923–27 in Table 11. Table 11. Malaria incidence in some affected provinces (per 10,000 population). Provinces and regions: Volga German Republic, Samara Province, Astrakhan Province, Ulyanovsk, Saratov, Bashkir Republic, Tatar, Chuvash, Stalingrad Province, Kalmyk Region, Moscow Province, Voronezh, Mari Region, Vladimir, Tambov, Nizhny Novgorod, Arkhangelsk. Official figures for malaria incidence during the years of its pandemic are significantly lower than reality due to the weakness of the medical network in those years and poor registration of patients. In the opinion of local health workers, these figures for individual districts should be increased by 2 to 5 times or more. If we accept an average correction coefficient for these years of 2.5, then the total number of cases will amount to over 14,000,000 for each of these years (1923 and 1924). Subsequently, malaria incidence gradually decreases to the pre-war level. This decrease is observed steadily from year to year despite a significant improvement in the registration of diseases due to the strengthening of the general medical network each year and the opening of a large number of malaria stations, which contributed to an increase in the influx of malaria patients. Corresponding figures for the entire USSR are given in Table 8 and in Figure 7. Incidence by individual union republics and individual regions. Table 12. Malaria incidence by individual republics of the USSR from 1924 to 1929 (per 10,000 population). Of the individual republics of the USSR, the Transcaucasian ones continue to remain the most unfavorable regarding malaria, in which the malaria incidence rate up to the most recent years amounts to up to 10% or more in relation to the entire population. The endemic indicator of malaria in these republics has no tendency to decrease. The increase in malaria incidence from year to year in some of these republics can, to a certain extent, be explained by the network of anti-malaria institutions expanding every year in these republics and the improving registration of patients. For the RSFSR, the malaria incidence rate in 1929 decreased by almost 3 times compared to 1924, and for Ukraine by approximately 6 times. The endemic indicator of malaria in Belarus remains at a low level for all years. In the Central Asian republics, it is gradually increasing. Malaria incidence by regions of the RSFSR (per 10,000 population). North-Eastern Region (Northern Territory), Leningrad, Karelian ASSR, Western Region, Central Industrial Region, Ivanovo Industrial, Moscow.
624.0 Turkmenistan .... I - Uzbekistan......: - 1925 382.5 229.4 29.1 866.5 866.8 608.2 232.6 291.7 1926 319.7 160.4 10.4 1001.1 947.5 802.8 271.0 285.3 1927 243.7 130.7 18.4 946.9 994.4 779.6 401.4 232.6 1928 1929. The data for the RSFSR for 1924-29 is provided in tables 12 and 13. Morbidity by individual provinces in 1929 is shown in Fig. 12, which should also, to a certain degree, be explained by the improvement in the registration of patients. Among the individual regions of the RSFSR, the most unfavorable regarding Malaria continue to be Dagestan, the North Caucasus, the Lower Volga Territory, the Kyrgyz Republic, and the Middle Volga Territory. It is registered at the lowest levels in the northern regions. 3. Table 14 provides an overview of mortality from Malaria in recent years, where mortality rates from Malaria for 1926-28 are given for some cities of the USSR (according to the Central Statistical Administration data). The table includes only those cities where mortality from Malaria averaged over 3 years is higher than 10 per 100,000 population.
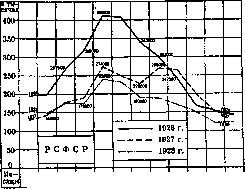
195.8 92.5 27.7 996.0 912.6 830.5 461.2 255.5 163.1 58.0 11.3 1386.1 1 080.4 781.6 540.5 341.5 Table 14. Mortality from Malaria in some cities of the USSR for 1926-28 (per 100,000 population). Cities 1926 1927 1928 1926-28; Maykop, Grozny, Stalingrad, Astrakhan, Orenburg, Pyatigorsk, Samara, Baku, Syzran, Ulyanovsk, Tambov, Barnaul, Ufa, Vladikavkaz, Novosibirsk, Kazan, Chelyabinsk, Novorossiysk, Armavir. Many of these cities have higher mortality from Malaria than from typhoid fever and other infectious diseases. These cities are located mainly in the North Caucasus, in the Lower and Middle Volga regions, and in Transcaucasia, but some of them are in the Central Black Earth Region (Tambov), in the Urals (Ufa, Chelyabinsk), and in Siberia (Barnaul). In Moscow, on average for 1926-28, mortality from Malaria was 0.5, in Leningrad - 0.2 per 100,000 population. 4. Malaria in cities and rural areas. According to official registration data, about 20% of all Malaria cases are registered in cities, and about 80% in rural areas. In relation to the population, Malaria morbidity is registered higher in cities than in rural areas. Table 15 provides the corresponding indicators for 1924-27 for the RSFSR. Table 15. In percentage terms, per 10,000 population: Cities, Rural areas. 1924: 19.7, 80.3, 590.1, 451.0. 1925: 20.8, 79.2, 466.5, 343.7. 1926: 19.2, 80.8, 453.0, 308.0. 1927: 24.5, 75.5, 345.5, 221.4. The same ratio of morbidity is noted in the majority of the regions most affected by Malaria. Table 16 shows morbidity in 1927 per 10,000 of the corresponding population in cities and rural areas of individual regions of the RSFSR. The higher Malaria morbidity in cities is likely explained to a significant degree by the more complete registration of patients in them. 5. Morbidity and mortality from Malaria by age. In endemic regions, Malaria affects children particularly severely. R. Koch in New Guinea found small children up to 5 years old to be heavily infected, while among older people, parasite carriers were rare. Panse in Africa, by examining blood, found infected individuals among children under 1 year old - 48%, from 1 to 3 years - 87%, from 4 to 7 years - 65%, among older children - 39%, among adults - 15%. Examinations in the USSR also showed high Malaria infection rates in children. During the pandemic, children turned out to be heavily affected by Malaria in various regions of the USSR: in Orekhovo-Zuyevo (Moscow province) in 1923, among children in nurseries, 21.9% were found to be sick with Malaria, in children's homes - 69%, in first-stage schools - 47% (results of examination for parasitic and splenic indices). In Moscow, children's institutions in the same year yielded from 10% to 21.6% of Malaria patients, in Bryansk province - 31.5%, in Turkestan - from 60% to 100%, on the Tashkent railway - from 75% to 100%. High Malaria infection rates in children in endemic regions are observed even in non-epidemic years. In the Volga region, for example, children up to 10 years old get sick with Malaria more often than other age groups; after 10 years, the number of sick people decreases sharply (Kushev). Mortality from Malaria is registered mainly among children. In 1926 and 1927, in cities of the European part of the USSR with a population over 50,000 (excluding Moscow and Leningrad), deaths from Malaria per 100,000 people of the corresponding age were registered (Table 17): Age: Under 1 year, 1-4 years, 5-14 years, 15-29 years, 30-59 years, 60 years and older. 6. Lethality from Malaria fluctuates depending on the form of Malaria, the nutritional state of the patient, the timeliness of treatment, etc. For 1905-09, it amounted to 0.08% per 100 treated patients in the Austro-Hungarian army, and 0.65% in the French army in Africa. In German hospitals for the period from 1889 to 1897, it averaged 0.9% (Prinzing), in Indian hospitals for 1916-25, about 0.2% (Hoffman). In Russian hospitals before the World War, lethality from Malaria was about 0.8%. During the pandemic, it increased sharply. In 1923, according to inpatient data, it was 2.0% in Yaroslavl, up to 2.3% in Astrakhan, in the medical institutions of Dag-ryba (Dagestan) - from 1.5% to 3.5%, in Tiflis - up to 5%. In relation to the total number of registered patients, lethality from Malaria for that year ranged from 0.5% to 0.8% in the central provinces and in the north, up to 2.4% and higher in some regions of the Lower Volga and the Caucasus. High lethality was observed predominantly in patients with comatose forms of Malaria. For the period from 1923 to 1928, lethality from Malaria in the hospitals of Astrakhan province was: in 1923 - from 0.1% (May) to 2.3% (September); in 1924 - 1.3% (February-April 3.5%); in 1925 - 0.6% (August 1.4%); in 1926 - 0.2%; in 1927 - 0.7%; in 1928 - 0.3%. 7. Seasonality of Malaria morbidity. The monthly distribution of Malaria is not the same in individual regions. In the European part of the RSFSR, in Belarus, Ukraine, and Siberia, the maximum number of cases is observed in the spring (in April-May), in Transcaucasia and the Central Asian republics - at the end of summer or the beginning of autumn (in August-September). Figure 13 shows the monthly curves of Malaria morbidity in 1911 and 1912 in European and Asian Russia (the latter includes the Caucasus, Siberia, and Central Asia); Figures 14 and 15 show the corresponding curves for the RSFSR and Transcaucasia for 1926-28. The unequal monthly distribution of Malaria cases depends on the predominance of its individual forms: where the predominant form is tertian Malaria (in most regions of the RSFSR, in Belarus, etc.), a spring rise is observed; conversely, where the tropical form of Malaria is widespread, a summer-autumn rise is noted (see below). In some regions, two rises are noted from year to year: spring
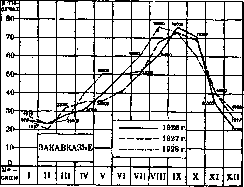
Figure 15. Monthly distribution of Malaria cases in Transcaucasia (abs. figures).
depending on the increase of the tertian form, and the summer-autumn one, due to the development of the tropical form of malaria (certain regions of the Lower Volga, Transcaucasia, and Central Asia). This constancy of the monthly malaria curve is also observed in those foreign countries where malaria is widespread: in Italy, for example, the maximum incidence falls year after year in August (see Figure 16). During the pandemic period, the character of the monthly curve in the USSR changed sharply: in the European part of the USSR, where the maximum of cases had previously fallen in May for many years, it shifted in 1922 to September; in 1923 it was observed in June, and only in subsequent years did the curve again assume its usual character with a maximum in May (Figs. 17 and 18). The indicated distortion of the monthly curve must be explained by the spread of the tropical form of malaria throughout the country during the pandemic years. 8. The ratio of individual forms of malaria. Systematic blood examinations of malaria patients in laboratories
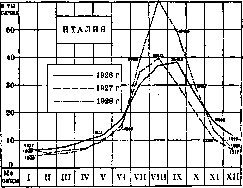
Figure 16. Monthly distribution of malaria cases in Italy (absolute figures).
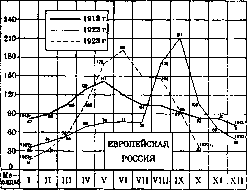
Figure 17. Monthly distribution of malaria cases in the European part of Russia (in relation to the average daily number of cases = 100).
are given for comparison as results for several years. The tropical form of malaria (Plasmodium immaculatum) has a very wide distribution throughout the USSR. In isolated cases, it is noted by stations in Siberia (Omsk, Tomsk), but in Barnaul it is already encountered in large numbers. It is observed relatively rarely in the central provinces. In the Volga region, the North Caucasus, and Transcaucasia, it occupies a very high place. Quartan malaria (Pl. malariae), very rarely
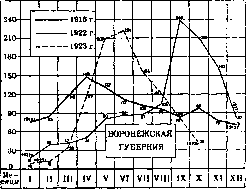
Figure 18. Monthly distribution of malaria cases in the Voronezh province (in relation to the average number of cases = 100).
encountered in Siberia and the central regions, is widely distributed in the North Caucasus and the Volga region, especially on the left bank of the Volga (Samara, Buguruslan, Buzuluk), and the impression is created that in recent years it is growing at the expense of tropical malaria, which is decreasing accordingly. The latter is also decreasing at the expense of tertian malaria (Pl. vivax). Mass laboratory diagnosis of malaria has also made it possible to establish the monthly movement of its individual forms. Regardless of the region where the observations were made, it has been established,
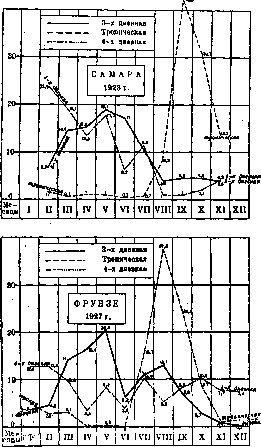
hinders the development of certain industries where it is observed as an occupational disease among workers; in places of endemic spread, it is the greatest brake on the development of industry; in some places, the extinction of the population due to malaria is observed. 1. Wars and Malaria. Wars of the 19th century were often accompanied by severe outbreaks of malaria. Figure 19. Monthly distribution of individual forms of malaria (as a percentage of the annual total of each form). that everywhere tertian malaria (Pl. vivax) reaches its maximum in May, the tropical form (Pl. immaculatum) in August or September, and the quartan form (Pl. malariae) is distributed more evenly throughout the year (Fig. 19). The combination of all forms gives the monthly malaria curve for a given region. V. Malaria as a social disease. Malaria has great social significance. Public disasters (war, famine, etc.) cause its rise and worsen its course. Improperly organized large-scale works, carried out without sufficient consideration of sanitary requirements, lead to mass morbidity and mortality of workers (the digging of the Panama Canal, the laying of railways in malarial areas, etc.). On the other hand, malaria epidemics severely disrupt the national economy; malaria in troops. Thus, in the American Civil War (1861-65), among white troops, an average of 544.7 per year contracted malaria and 5.0 died, while among colored troops, 870.6 contracted it and 18.8 died per every 1,000 men of the effective strength. In total, during the war, 1,163,814 men among the white troops contracted malaria and 8,140 died, and among the colored troops, 152,141 contracted it and 1,923 died. In some departments located along the Mississippi, total morbidity from malaria was observed among the troops. During the Japanese military expedition to Formosa (1874), out of 5,990 Japanese soldiers, 4,673 contracted malaria. In the Russo-Turkish War (1877-78), both the Russian Danube and Caucasian armies suffered greatly from malaria. In some units of the latter, malaria accounted for up to 7/8 of all illnesses. In total, during this war, 610,591 people in the Russian army contracted malaria (247 per 1,000) and 1,293 died (0.5 per 1,000). Russian troops suffered heavily during the campaign in Turkmenistan (1880-81): out of 12,000 military personnel, 8,411 contracted malaria and 65 died. In the Spanish-American War (1898), malaria claimed many victims among the Spanish and American armies: Spanish troops in Cuba in 1897 lost up to 7,000 dead from malaria; among American troops over 5 months (May-September), 38,833 cases and 97 deaths from malaria were observed with an average roster strength of 167 thousand men. The largest outbreaks of malaria were observed during the campaigns of European troops in tropical and subtropical countries, for example, during the French campaign in Senegal (1878), the British in Afghanistan (1878-1879), the French in Tonkin (1884-86) and Madagascar (1884-85 and 1895), the Italians in Abyssinia (1895-96), etc. Morbidity among the armies of various countries per 1,000 men of average strength before the World War (1901-10) was expressed in such
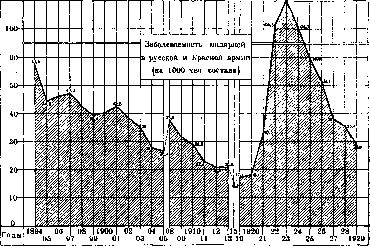
indicators (Table 19; according to Vasilevsky):
59.8
34.1
33.0
29.3
11.6
| 0.2 Branches of labor. The World War gave a significant increase in malaria in various armies. Above (see World Distribution of Malaria), this growth was already noted for individual countries (Italy, Spain, USA). In the German army, the incidence of malaria per 100 thousand people of average strength in individual years of the war was: 1st year of the war - 35; 2nd year of the war - 132; 3rd year of the war - 620; 4th year of the war - 1,370. On the Balkan front, this incidence reached 9,260 in the third year of the war, and 23,240 per 100 thousand in the fourth; on the Turkish front in the third year of the war - up to 65,120, in the 4th - up to 18,370 per 100 thousand men. The incidence in the Russian and Red Armies is shown in Fig. 20. In 1888-92, it averaged 106.5 per 1,000 men in the Russian army annually, in 1900-02 it dropped to 40, in 1913 to 20.8 per 1,000. In 1921, Figure 20. a decrease in morbidity to 104.3 per 1,000 is noted; subsequently, malaria rapidly decreases to 28.9 per 1,000 in 1929 (still higher than in 1911-13). 2. Malaria among the industrial proletariat. According to the Central Administration of Social Insurance, in 1925, out of 100 all cases of illness, malaria accounted for 4.3% among workers in the extractive and manufacturing industries, and 9.2% among railway transport workers. Table 20 shows the number of malaria cases and days of illness from it for every 100 insured in the USSR in 1925. While giving a high percentage for all branches of labor, for some of them in 1925, malaria was still the most frequent disease: among workers in oil extraction and refining, for example, malaria accounted for about 20% of all cases of illness and causes of loss of days due to illness; in the basic chemical industry - about 10%. The average duration of 1 case of malaria for the entire USSR was 9.3 days for men and 10.0 days for women. Corresponding data for Moscow
Malaria
The data for the Moscow Governorate for 1925–28 are presented in Table 21 (per 100 insured persons). Groups of transport (water transport) and agricultural workers (on rice and cotton plantations). Table 21. Industry branch: Metal processing, Woodworking, Fiber/goods, Mineral, Food, Animal products. All industry. Cases of disease/Days of disease 1925, 1926, 1927, 1928. [Table data omitted for brevity in translation, but the text notes:] The highest incidence of malaria during these years was noted among textile workers and workers in the processing of mineral substances. The average duration of a case of disability due to malaria decreases every year. For the entire industry of the Moscow Governorate, it was for both sexes: in 1925—12.8, in 1926—11.6, in 1927—10.3, in 1928—9.6 days. If in the Moscow Governorate, which is relatively well-off regarding malaria, the latter occupies a high place (for the indicated years, malaria, by the number of days of disability among infectious diseases, is second only to influenza and tuberculosis), then for some groups of seasonal workers it continues to remain one of the most frequent diseases. It continues to be registered especially highly among peat workers, for whom malaria is an occupational disease. For the 1927 season (May–November), the incidence of malaria among peat workers is characterized by the following indicators (Table 22): 3. The economic damage from malaria is extremely great. In 1923, the year of the greatest development of malaria, the population of the USSR, according to theoretical calculations, lost 75–112 million working days due to malaria, and insured persons lost about 12,000,000 working days. During the pandemic, the largest sectors of the national economy were disrupted due to malaria: in addition to the peat industry, which was mentioned above, the fishing industry suffered severely from malaria (in the Dagestan fishing industry, on average 65% of workers fell ill, and at individual fisheries up to 100%), as well as the textile, oil, and coal industries, etc. The incidence of malaria among timber rafting workers reached 72.5% (Kotlas). The movement of some railways and shipping was halted due to the universal illness of workers. In many regions, fields remained unsown and unharvested due to the universal illness of the rural population. Malaria causes no less disaster in places of its permanent distribution: in Turkestan and Transcaucasia, the extinction of a number of villages due to malaria has been noted. Everything said makes the fight against malaria one of the greatest social problems.
Dobreytsert. VI. Pathological anatomy. At the center of pathological-anatomical changes in malaria lie changes in the blood, namely, in erythrocytes and blood pigment, which fully corresponds to the general characterization of malaria as an infection of the blood. In connection with this, anemia of one degree or another is always observed during autopsies (especially in chronic forms). Malaria plasmodia can also be detected in a corpse; this concerns mainly tropical forms, in which an abundance of parasites is found in smears from the brain, spleen, and bone marrow; however, Bystrov also found parasites in the blood of a corpse in cases of death from tertian malaria (even 4 days after death). There are indications that it is even possible for the parasite to multiply in the blood of a corpse, similar to the maturation of merozoites from schizonts in vitro on defibrinated blood with dextrose; true, the ability to inoculate new erythrocytes in the blood of a corpse is denied. As a consequence of the destructive processes in erythrocytes, so-called melanemia and melanosis (or hemomelanosis) of organs are noted. By melanosis
#29 implies the deposition of a peculiar dark-brown pigment (hemomelanin) in various organs, and primarily where the reticulo-endothelial system is located: in the Kupffer cells of the liver, in the endothelium of the splenic sinuses, in the lymph nodes, and in the bone marrow. However, even outside this system, significant deposits of pigment may be noted along the stroma of all organs. The amount of the latter can be so great that, even macroscopically, the organs acquire a slate-gray, smoky, or almost black color. The greatest amount of pigment is usually noted in the spleen, liver, and pancreas. Sometimes pigmentation is extremely uneven: for example, in the spleen, one may observe a complete absence of pigment while there is an abundance of it in the liver and in the pancreas. It should be borne in mind that in chronic malaria, as well as during significant intervals between attacks, or in cases where attacks occurred in the distant past, the malarial pigment may almost completely disappear. The amount of pigment, all other conditions being equal, is also subject to strong individual fluctuations, depending apparently on the adsorption capacities of the reticulo-endothelial system itself, the speed of pigment assimilation, and possibly also on the physicochemical properties of the latter. The formation of the pigment occurs in the process of intraparasitic alteration of blood hemoglobin; the pigment is therefore hemoglobinogenic, and although as a rule it does not give the usual reactions for iron, it nevertheless contains it. Some authors, based on findings of iron and a whole series of other properties of hemomelanin, consider the latter to be close to, although not identical with, hematin. Many suggest not using the term "melanin" at all in relation to malaria, leaving it exclusively for proteinogenic pigments (e.g., pigments of the skin, hair) that have no direct relation to hemoglobin and do not contain iron (but do contain sulfur), and instead calling this pigment simply "malarial pigment." Malarial hemomelanin possesses anisotropic properties and is soluble in weak alcohol-aqueous alkalis; the latter circumstance somewhat brings this pigment closer to the so-called formalin pigment. Along with hemomelanin, another pigment is often discovered in the same organs in malaria, which gives the usual reactions for iron and apparently represents hemosiderin. The periodic and prolonged loading of the reticulo-endothelial system with pigment and other colloidal particles formed in connection with the mass destruction of erythrocytes, and finally the very fact of the intravascular parasitism of plasmodia—all this makes understandable the significant participation of the reticulo-endothelial system in the morphological picture of malaria. This participation is expressed in desquamative and proliferative processes, entailing at times very significant changes in the volume and structure of the corresponding organs (hepatomegaly, splenomegaly, cirrhotic changes); an echo of this same participation is the monocytosis in the peripheral blood, which is so characteristic of malaria. Progressive anemia, the overloading ("blockade") of the reticulo-endothelial system with pigment, and atrophic, degenerative, and sometimes sclerotic changes in the organs (see below) often lead to general exhaustion, cachexia, and death. Sometimes, as a severe complication reflecting irreparable disturbances in protein metabolism, amyloidosis of the internal organs, especially the kidneys, spleen, and adrenal glands, supervenes. Finally, death of malaria patients occurs relatively frequently with symptoms of malarial coma. In terms of changes to individual organs, the spleen is of the greatest importance. During acute attacks of the disease, it swells significantly, and its capsule is sometimes strongly stretched; in some cases, for example, during the artificial infection of progressive paralytics with malaria, tears and ruptures of the spleen with fatal hemorrhage are observed. Sometimes, on the contrary, the spleen is sharply flaccid, mushy, with abundant scraping of the pulp. In the malarial spleen, one often observes foci of necrosis of a gray and dark-brown color (infarcts). If the foci are numerous, a peculiar appearance of a marbled spleen is obtained (Shirokogorov). The follicles are sometimes sharply hyperplastic, sometimes barely noticeable. Upon microscopic examination of pulp smears, one discovers an abundant quantity of parasites in all possible stages of development, clumps of pigment, lymphocytes, plasma cells, myelocytes, as well as free cells of the reticulo-endothelium of various sizes containing pigment (macrophages). Chronic, especially tropical, malaria produces the most enlarged and densest spleen (up to 6 kg; Shirokogorov), so that one sometimes speaks of malarial splenomegaly. Such a spleen is often not held by its ligamentous apparatus and becomes highly mobile, unless perisplenitis develops with adhesions, which can wrap around the organ. The development of adhesions is connected either with diffuse perisplenitis or with the development of infarcts, which leave behind scars of various sizes, sometimes sharply disfiguring the contours of the spleen. Parasites in the pulp from chronic cases are often absent; pigmentation, however, is noted to varying degrees; sometimes there is no pigment at all, and such spleens look not dark-brown, but red. The number of free cells of the pulp in these cases is sharply reduced, fibrous tissue develops, and the sinuses are sometimes sharply dilated, which gives the microscopic pattern of the organ an angiomatous appearance. The liver is most often significantly enlarged (mainly in chronic cases); sometimes one can speak of hepatomegaly; in other (also chronic) cases, on the contrary, the liver is reduced and resembles the picture of atrophic cirrhosis. The surface of the organ is usually smooth, though sometimes phenomena of perihepatitis and the development of adhesions with the diaphragm are noted. Pigmentation is usually significant, and the liver looks slate-gray or chocolate-colored on cross-section [see separate table (col. 583, 584), fig. 8]. Malarial pigment lies mainly in the cells of the reticulo-endothelium, often freely in the circulatory system; it is not present in the hepatic cells, but accumulations of hemosiderin are frequently discovered in them. It should be borne in mind that in terms of size and color, the liver, especially in acute cases, can be completely normal. In acute cases, one often observes phenomena of parenchymatous and fatty degeneration, sometimes phenomena of dissociation of the parenchyma, as well as necrobiotic changes encompassing both groups of cells and entire lobules or groups of them. These changes in the parenchyma apparently lie at the basis of that atypism of the structure of the parenchyma, as well as the cirrhotic phenomena that are observed in chronic cases. The lymph nodes are enlarged, especially in chronic cases; the enlargement falls mainly on the glands of the abdominal cavity (region of the porta hepatis, spleen, periaortic). The color of the glands is sometimes light-gray, sometimes brown. Microscopically—desquamative and proliferative changes on the part of the endothelium of the sinuses and the cells of the reticulum. In the bone marrow, there are usually large quantities of hemomelanin; the color of the marrow, instead of red, becomes brownish. In chronic cases complicated by cachexia, mucoid degeneration of the tissue is noted. The bone marrow is apparently the only organ in which sexual forms of plasmodia—gametes—can be found. The pancreas is often distinguished by its sharp pigmentation. Cases of necrosis of the adipose tissue and parenchyma cells are observed, and in chronic cases, cirrhotic changes as well. The peritoneum is often also intensely pigmented. In chronic cases, ascites is observed as a manifestation of marantic edema. On the part of the intestine, one usually notes sharp melanosis of the mucosa. Inflammatory and ulcerative changes of the small and large intestines (malarial enterocolitis) are relatively frequent. In the large intestines, dysentery-like pictures are also observed (malaria dysenterica). In the vessels of the affected areas, an abundant quantity of parasites is found in this process. The very mechanism of the development of intestinal changes should be imagined as toxicoses of the mucosa on one hand, and as a consequence of severe circulatory disturbances on the other. In the stomach, phenomena resembling those in the intestine are possible. Hemorrhages, as well as ulcerative-gangrenous changes on the part of the oral cavity, gums, and pharynx, are apparently related to a complication with scurvy. Shirokogorov also describes necrotic changes in the salivary glands. The lungs, apart from their diffuse pigmentation to a steel color, usually do not present changes; sometimes one encounters edema, pneumonic foci, and infarcts. Shirokogorov points to the significant resistance of malaria patients to tuberculous reinfection. On the part of the heart in acute cases and during coma, one finds ecchymoses of the epicardium and parenchymatous degeneration of the myocardium; on the part of the muscle fibers—sometimes a loss of cross-striation, swelling and vacuolization of the nuclei, and more rarely—perivascular inflammatory infiltrates. In chronic cases, sclerotic changes of the myocardium of a focal and diffuse nature are possible. The arteries do not bear definite changes.
Shirokogorov, however, observed proliferation of the endothelium and adventitial elements in the vasa vasorum, with which he links the sclerotic changes in the intima sometimes observed even in young malaria patients. Skeletal muscles are usually dark red in color, resembling smoked ham; necrobiotic changes of the Zenker degeneration type are possible. The kidneys are often pigmented in the glomeruli. In acute cases, there are pictures of hyaline-droplet and granular degeneration; in chronic cases, amyloid degeneration is not uncommon. Nephritis develops mainly in tropical malaria and in malaria quartana. In rare cases, phenomena of so-called acute hemolytic malaria are observed (see Hemoglobinuric fever). The adrenal glands of those who died in a coma from tropical malaria often show degenerative-destructive changes in the cortex; in the medullary substance, the formation of miliary granulomas is described. The lipoid content in the adrenal cortex in acute malaria usually remains high (Zhenty), which distinguishes malaria from other acute infections. Changes in the testicles in chronic forms are observed frequently and consist of the death of the generative epithelium and the proliferation of interstitial connective tissue. A characteristic picture is presented by changes in the brain in tropical malaria, and more rarely (M. Alekseev) in other forms. Upon autopsy, the smoky coloration of the brain is striking [see separate table (col. 487-488), fig. 1], especially of the gray matter; upon microscopic examination, one finds widespread development of blood stasis, and in the swollen pale erythrocytes, plasmodia with pigment lie everywhere [see separate table (col. 583-584), fig. 7]. These pictures are pathognomonic for so-called malarial coma (see below), and they are based not only on the abundance of parasites but also on changes in the physical properties of the erythrocytes themselves. The process is often accompanied by small hemorrhages, and as a rule, no parasites are found in the extravasated erythrocytes. This indicates the stickiness and phenomena of agglutination of the altered erythrocytes in the vessel lumen, which makes them incapable of diapedesis. In cases of death from uncomplicated acute tertian malaria, Bystrov found a peculiar swelling of the brain without pigmentation of the gray matter and without phenomena of edema and hyperemia. In the brain substance, one can also find pictures of focal encephalitis, expressed in perivascular and periganglionic proliferation of glia, in the formation of so-called Dürck's malarial granulomas [see separate table (col. 583-584), fig. 9]. The development of granulomas is often combined with hemorrhages and necroses, with the zone of necrosis being closest to the vessel, then the zone of hemorrhage, and behind the latter lies the granuloma itself. The radiant arrangement of neuroglia cells gives the granulomas the characteristic figure of a daisy (Gänseblümchen-figur of German authors). There are most granulomas in the white matter and in the central ganglia. In the cortex, there are few or no granulomas despite the abundance of parasites precisely in the cortical capillaries; this circumstance makes the explanation of the causal genesis of granulomas by the direct effect of the parasites themselves on the brain tissue unlikely. There is a hypothesis that on the basis of successive degenerative changes of nerve fibers, mainly their myelin sheaths, pictures of disseminated sclerosis may subsequently arise. However, even at their inception, granulomas have a significant resemblance to fresh foci of disseminated sclerosis (disappearance of medullary sheaths, preservation of axis cylinders, proliferation of glia). The specificity of Dürck's granulomas for malaria should, however, be considered unproven. On the basis of necrotic changes in the brain substance, foci of petrification have also been observed. On the part of the soft meninges, inflammatory changes are sometimes also observed in the form of diffuse lymphocytic infiltrates with subsequent sclerosis and clouding of the membranes. These same infiltrates can penetrate along the vessels into the brain substance. Exanthema in malaria is rare, mainly in comatose forms; it has the appearance of either petechiae or blue-purple spots and erythemas, especially on stretched areas of the skin. Histologically, there are extravasates, intravascular parasitism, and pigment deposits. Herpes sometimes breaks out on the lips. It is necessary to distinguish the pathological anatomy of malaria from the pathological anatomy of malarial coma as the final act of the disease, which is especially frequent in tropical malaria. To the phenomena characteristic of coma, one should first of all attribute massive peripheral blood stasis with widespread parasitism of plasmodia in sharply swollen pale erythrocytes; it must be thought that these phenomena themselves create the most severe conditions for blood circulation. To the manifestations of coma, one should also attribute hemorrhages, pulmonary edema, and also a peculiar yellowish coloration of the integuments, testifying to the onset of hemolytic phenomena. According to data from Moscow prosectoriums for 1923-1927, out of 37,899 autopsies, only 46 cases of death from malaria as the primary affliction were noted; 7 of these cases fall on tropical malaria. In general, these figures show that malarial mortality in the climatic conditions of the middle and northern zones is very small, and the fatality rate is also insignificant, since malaria must still be considered a very widespread affliction. I. Davydovsky, I. Shirokogorov. VII. Pathogenesis. The pathogenesis of malaria is determined by the relationship between the state of the human organism and the vital activity of the plasmodium as a parasite of its erythrocytes. Plasmodia in the form of sporozoites, entering the bloodstream of the bitten person with the mosquito's saliva during a bite, penetrate into the erythrocytes and grow there, feeding on hemoglobin. Upon reaching maturity, the plasmodia divide asexually (schizogony) into daughter cells—merozoites. The latter, destroying the erythrocyte, enter the blood plasma and strive to find shelter in new erythrocytes. In this process, a significant part of the merozoites perishes under the influence of the parasitocidal properties of the blood plasma. Numerous observations have established that the most typical expression of malarial disease—the febrile attack—arises at the moment of the simultaneous division of a large number of blood parasites. The very cause of the febrile reaction of the organism to the indicated moment of the plasmodium's life cycle has not yet been definitively established. Marchoux attributes the destruction of erythrocytes to the action of a hemolytic toxin formed and released by the plasmodium at the height of its maturation. The onset of a febrile attack was linked to the action of a special pyrogenic toxin, the existence of which, however, has not been proven by direct experiments. Another hypothesis explains the onset of the temperature reaction by the entry into the blood of protein bodies formed during the death of part of the blood parasites and the decay of erythrocytes. Varasay induced a typical temperature curve of tertian fever by injecting a rabbit with an egg white solution every 48 hours. Abrami and Senevet consider the malarial attack a clinical expression of a sudden disturbance of the colloidal equilibrium of the plasma (hemoclastic shock) occurring at the moment of plasmodium division. Brown put forward the hypothesis that the attack is caused by the release of malarial pigment (injecting it into rabbits causes a rise in temperature in them). Whatever the mechanism of the malarial paroxysm, the vital activity of the plasmodium underlying it causes, first and foremost, the destruction of a large number of erythrocytes and hemoglobin. In the periods free from a febrile attack, these losses of peripheral blood are more or less quickly replenished, and at the same time, apparently, the physical-chemical state of the blood changes, as a result of which the number of circulating schizonts in it gradually decreases. These immunobiological changes are confirmed by the fact of the spontaneous cessation of attacks with the decrease of blood parasites in the peripheral blood to a minimum not detectable by the methods of investigation available to us. Abrami, Senevet, and Carnot proved the presence of schizontolysins in the blood serum of a malaria patient. The instability of these lysins explains the rapid exhaustion of immunity and the occurrence of early returns (Rückfälle, rechute) of febrile paroxysms. The very mechanism of both these early and later seasonal returns (relapses) of the disease has not yet been definitively clarified. The hypotheses proposed to explain them can be divided into two main groups: according to some, a relapse is a consequence of continuous, only quantitatively increasing schizogony (Ross, Thomson); others assume that the relapse schizogony is preceded by the maturation and fertilization of gametes (Rowley, Biedl, Grassi) or parthenogenesis of gametes (Schaudinn) in the patient's blood. The predisposing causes and factors provoking a relapse are extremely diverse: these include colds, dietary errors, overwork, trauma, etc. However, none of these factors can reliably provoke a relapse. The causes of the mass occurrence of seasonal relapses are generally still not sufficiently clear.
They may lie in both the seasonal fluctuations of the physical-chemical properties of the patient's blood and in the biology of the parasite itself. Malaria—one must distinguish from relapses, the returns of schizogony of the same form of the parasite in the peripheral blood with clinical manifestations of a malarial attack, a reinfection—a new infection with the same form of the parasite after the cure of the primary disease or during its course. A primary infection with each new form of the parasite is defined by the term "fresh infection." VIII. Clinical picture. The clinical picture of malaria includes a number of very diverse painful manifestations that are difficult to fit into a definite classification. In the most general terms, malaria can be characterized as a chronic disease, at times manifesting itself in acute febrile attacks. In accordance with the three varieties of the pathogen, clinically, malaria proceeds in the form of a tertian form (malaria tertiana—pathogen Plasm. vivax), a quartan form (malaria quartana—pathogen Plasm. malariae, s. Laverani), and a tropical form (malaria tropica—pathogen Plasm. immaculatum). During the last pandemic, cases of infection with two or (more rarely) all three types of plasmodium were frequently observed. The incubation period of malaria fluctuates within fairly wide limits depending on the type of parasite, the time of infection, and the state of susceptibility of the infected person. Ziemann considers the incubation period for malaria to be on average 10-14 days; it is shortest in the tropical form, somewhat longer in the tertian form, and longest in the quartan form. Accumulated observations on cases of the primary manifestation of malaria in the early spring months, when infection through a mosquito bite is still improbable, have forced the introduction into the clinical picture of malaria of the concept of a long incubation period. Some malariologists prefer to define this period as a primarily latent infection. Prodromal phenomena are not always sufficiently clearly expressed; often the first febrile paroxysm occurs suddenly; sometimes it is preceded by sensations of vague malaise, fatigue, aching in the limbs, and headache. More often and more sharply, these sensations preceding the febrile attack are noted by patients during relapses of the disease. The intermittency of febrile attacks (febris intermittens), which characterizes an acute malarial disease, is not established from the very beginning of the disease. Often, an initial fever (Fig. 21) of a constant or remittent type is observed, which then passes into a regular intermittent one. According to the observations of Wethmar, initial fever is more common with a short incubation period. Figure 21. Initial fever in mal. tertiana. A typical malarial paroxysm is characterized by a "fairly rapidly following change of short periods of chills, heat, and sweat, which are in close connection with the cycle of asexual development of the malarial parasite in the patient's blood. The chill, with which the attack begins, can be of varying intensity—from barely noticeable shivering and a feeling of goosebumps running along the spine to shaking the patient's entire body and causing uncontrollable chattering of the teeth. The patient cannot overcome the sensation of cold, even after pulling on everything available at hand. The state of chills lasts 20-30 minutes, sometimes significantly longer, and, gradually subsiding, is replaced by a sensation of heat, which is accompanied by headache and thirst. The period of heat lasts from 1 to 12 hours, after which the temperature begins to fall more or less rapidly. First the forehead and the upper part of the chest, and then the entire skin of the torso and limbs becomes moist, and a period of sweating begins, which often takes on the character of a drenching sweat. With the fall in temperature and the appearance of sweat, the distressing sensations disappear quite quickly, the patient usually calms down and falls asleep. During the following period of apyrexia, which coincides with the growth and maturation of schizonts in the erythrocytes, the patient feels only some weakness, which disappears by the beginning of the next attack. With the onset of chills, the skin becomes dry and rough (goosebumps), the limbs become cold, and the lips and fingertips become cyanotic. With the end of the chills, the patient's face flushes, the skin becomes hot and dry to the touch and remains so until the appearance of sweat. In the period of apyrexia, the skin takes on a normal appearance or sometimes remains moist and pale. In individual cases, the appearance of various kinds (see below) of rashes is possible. The tongue in the febrile period is often slightly coated, sometimes swells, and bears impressions—teeth marks—on its lateral surfaces. Breathing shortens and quickens from the very beginning of the chills and returns to normal only after the paroxysm has passed. The pulse quickens from the beginning of the attack, becomes tense, and at the height of the attack, dicrotism is sometimes felt. With the fall in temperature, a significant slowing of the pulse and an improvement in its quality are usually observed. Blood pressure in the chill stage rises quite significantly, gradually returning to normal or even falling below normal in the stage of heat and sweat, due to the weakening of vascular tone (Shabashov, Molchanov and Egorov, Mikeladze). A malarial attack is very often accompanied by vomiting, in severe cases with an admixture of bile in the vomitus. Occasionally, especially in childhood, diarrhea appears along with the attack. The enlargement of the spleen characteristic of malaria, caused by hyperemia of the organ and hyperplasia of its cells, occurs with the onset of febrile attacks, and sometimes even in the prodromal period. In fresh cases, after the attacks have passed, the spleen shrinks quite rapidly to its normal size. It should be borne in mind, however, that neither the very fact of splenic enlargement nor its size and density can serve as a measure of the severity of malaria. During attacks, the liver also enlarges and becomes painful, functioning intensely due to the need to process the mass of erythrocytes destroyed by the blood parasites. The congestion of the bile capillaries and the entry of bile into the blood sometimes cause a jaundiced coloring of the skin and sclera. Regarding the nervous system, during an acute malarial attack, signs of a general diffuse lesion, characteristic of febrile states in general and manifesting in general malaise, headaches, and sometimes delirium or a semi-unconscious state, are noted for the most part. However, from the very first attacks, manifestations of a hyperkinetic character in the form of convulsions of individual muscle groups or paretic states are possible, and in children, general convulsions as well. In accordance with the pathogenesis of the disease, large changes are observed in the erythrocytes. A certain percentage of them (according to Marchiafava and Bignami) show a fine stippling (Schüffner's dots), which is well noticeable with proper staining of the smear. Maurer described analogous changes in erythrocytes in tropical malaria; Maurer's spots are sparser, coarser, and have irregular contours. With vital staining with basic aniline dyes, the number of erythrocytes showing granulation (substantia reticulo-filamentosa) increases significantly in comparison with the norm (Sarkisyan). The decrease in the total number of erythrocytes and the content of hemoglobin in them has already been mentioned above. The malarial attack also causes quite significant changes in the number and composition of leukocytes. Two hours before the onset of chills, leukopenia is noted (Abrami and Senevet), which is replaced by the time of the chills by a slight leukocytosis, which gradually increases at the beginning of the temperature rise and quickly disappears by the time it falls. Along with fluctuations in the number of leukocytes, the ratio of their individual types also changes: the neutrophilia characterizing the beginning of the attack is replaced by the end of it by neutropenia due mainly to segmented forms, relative mononucleosis, and lymphocytosis. Eosinophils decrease in number or even disappear at the height of the attack and reappear during apyrexia. As with other acute infections, Türk cells often appear in the blood during the acute period. Brailovsky, having performed over 1,500 blood tests during the height of the epidemic for various forms of malaria, found that the range and character of the quantitative fluctuation of leukocytes is not related to the type of parasite-pathogen, but in the qualitative composition of the white blood, such a connection is noticed: tertian malaria gives a shift no further than young forms, the number of eosinophils is reduced.
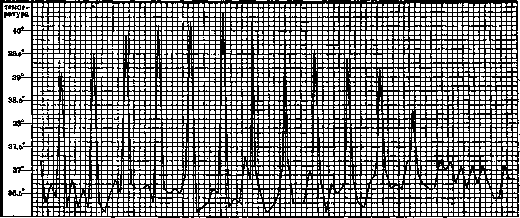
Figure 22. Therapeutic mal. quartana. Spontaneous extinction of fever. Transition of paroxysms.
from evening hours to morning hours. up to 12% in severe cases) contains plasmodia at one stage of development or another depending on the moment of examination. Erythrocytes containing plasmodia are paler due to the depletion of their hemoglobin. In tertian fever, the introduction of Plasm. vivax leads to an increase in the size of the erythrocytes and causes the appearance in their protoplasm of fine, so-called Schüffner's (Schüffner) granulation, and only rarely are they absent. In tropical malaria, the shift of neutrophils reaches myelocytes, is more sharply expressed, eosinophils often disappear completely, monocytes are encountered more frequently than in tertian malaria; usually there is a presence of degenerative forms. Quartan malaria, according to blood changes, is more similar to tertian, but causes greater lymphocytosis. The number of blood platelets decreases. The excretion of urine in the stage of chills may be somewhat increased, then it sharply decreases, and throughout the entire period of heat and sweating, concentrated urine is excreted in small quantities. The specific gravity of the urine is increased due to the content of a large amount of protein breakdown products; the breakdown of erythrocytes also causes an increase in the excretion of iron and urobilin; the amount of chlorides is either unchanged or slightly increased. The above-described symptoms are more or less common to acute attacks of all three forms of malaria. The further course of the disease has peculiarities in each individual form. Quartan malaria is distinguished by the greatest regularity of its course (Fig. 22). Fever attacks in this form repeat after two days of apyrexia at the same hours. Premature onset of an attack (m. anteponens) or its delay (m. postponens) is observed less frequently than in other forms. In the presence of two generations of the parasite, after two days of fever, one day of apyrexia occurs (m. duplicata), and with three generations (m. triplicata), attacks occur daily. Usually, with double or triple m. quartana, one of the generations predominates and gives the temperature curve a distinct 4-day type (Fig. 23). The non-simultaneous maturation of schizonts of Pl. malariae gives this form more noticeably expressed prodromal phenomena in the form of fatigue and headache; the stage of chills is more prolonged, and the rise in temperature proceeds less violently than in other forms. Sweat appears quickly and is usually abundant. Vomiting is less regular in the course of m. tertiana, which is most frequently encountered in our latitudes. An attack of tertian malaria occurs every other day, and in the presence of two generations—daily (m. tertiana duplex) (Fig. 24).
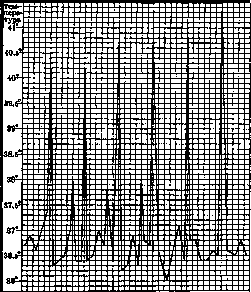
Figure 23. Malaria quartana. Additional weak paroxysms. In m. quartana, it is observed rarely, and in general, the whole disease runs comparatively easily, but at the same time, it is less prone to self-cure, is more difficult than other forms to treat with quinine, and gives persistent relapses. Figure 24. Malaria tertiana duplex. Daily paroxysms. Figure 25. Tropical malaria.
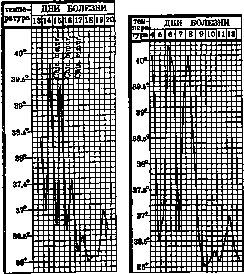
In m. tertiana, a constant or remittent initial fever is observed especially often. Chills during a typical attack of tertian malaria are expressed very sharply but are not prolonged. The warming of the organism occurs quickly, the temperature reaches high figures and then slowly falls. Sweating does not occur immediately and sometimes lasts up to 8 hours. Attacks of m. tertianae are often accompanied by vomiting and intestinal disorders; all clinical phenomena in this form are expressed more sharply than in quartan; in the period of apyrexia, painful sensations do not leave the patient. But m. tertiana is more prone to the spontaneous cessation of attacks and is more easily treated with quinine.
Tropical malaria is distinguished by the most severe and irregular course (Figs. 25 and 26). Its temperature curve rarely retains a tertian character, taking on an extremely irregular course, especially during relapses (Fig. 27). The layering of attacks gives the temperature a remittent or constant character. Other features of the febrile attack are just as inconstant and irregular in m. tropica: chills can be very short and mild, and sometimes are completely absent. The rise in temperature in fresh cases occurs very quickly, usually in the morning or daytime hours. The fever lasts for a very long time, giving a decrease only on the next day, and often the temperature does not manage to fall to normal before the beginning of the next attack. In a later course, on the contrary, short, isolated febrile paroxysms separated by long intervals of apyrexia are possible. The stage of sweating may either be completely absent or be weakly expressed. Clinical symptoms of a tropical malaria attack are similar to those in tertian, but differ in their particular severity: vomiting often takes on a bilious character, nervous phenomena reach their most sharp development; the sleep that occurs after an attack is interrupted by nightmares. The shortness or almost complete absence of apyrexia does not allow for rest, and the patient's strength falls rapidly. Tropical malaria predominantly, and the other two forms more rarely, sometimes take on a malignant course. The following are described: a) typhoid, or hyperthermic form with a constant high temperature (Fig. 28) and phenomena of severe intoxication; b) choleriform, or algid form, proceeding with all the symptoms of a cholera disease; c) dysenteric form; d) pneumonic form with pneumonic foci and pulmonary hemorrhages; e) hemorrhagic form with rashes and hemorrhages. Great caution is necessary in establishing a diagnosis of such malignant forms; it is necessary to exclude the possibility of the coincidence of malaria with typhoid, cholera, dysentery, etc. Special mention should be made of cerebral, or comatose, malaria, which has become widespread, especially in the last pandemic. The occurrence of this form is explained by the influence of a particularly malignant hypothetical toxin (toxic theory) or, more often, by the blockage of the capil-
Figure 26. Figure 27. Figure 26. Tropical malaria. Figure 27. Tropical malaria, fresh disease. Prolonged paroxysms.
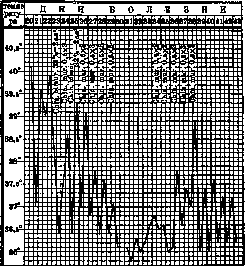
-laries of the brain by destroying infected erythrocytes (mechanical theory). A comatose state in malaria arises in subjects weakened by malnutrition or preceding diseases or pregnancy (Kitaev), or in those who have absolutely no immunity to malaria. In the latter case, coma can arise from the very first clinical attacks of malaria. The temperature in the comatose form is high, of a constant type. Figure 28. Tropical malaria, typhoid form. Relapse.
pa, sometimes it may be, on the contrary, normal (according to Kitaev in 20% of all his cases); the patient is "motionless, in a drowsy, soporous, or completely unconscious comatose state. The pupils are dilated, do not react, the pulse is tense, the patient urinates on himself; often there is continuous sweating. The spleen may not be enlarged at all or only slightly enlarged. In the peripheral blood, a mass of schizonts is usually discovered; at the same time, the appearance of mature schizonts and division forms (Kitaev) is characteristic, which are not observed in the peripheral blood in ordinary cases of tropical malaria. Sometimes, however, the number of parasites in a thick drop is surprisingly small and does not correspond at all to the severity of the disease. Comatose tropical malaria in most cases ends in death despite the most energetic treatment. More rarely, malaria is complicated by hemoglobinuria. The acute febrile stage of any form of malaria can end even without any treatment. After a greater or lesser number of febrile attacks, a prolonged apyrexia sets in. A kind of equilibrium is established between the patient's organism and the vital activity of the plasmodium. The patient feels quite satisfactory, but upon examination of the blood, both sexual forms and schizonts can be detected. The duration of such an inter-paroxysmal period for tertian malaria is on average calculated at 8-11 days, for tropical malaria at 5-7 days. However, these timeframes are subject to extremely wide fluctuations. The early relapses of febrile paroxysms occurring after these apyrexias become less prolonged, milder in manifestations, and more irregular in course with each subsequent relapse. The duration of the inter-paroxysmal period can also be much longer, reaching several months. Thus, in addition to early relapses, late relapses arise, which have a definitely seasonal character. This seasonality is especially clearly expressed in tertian malaria, which recurs in the early spring months; relapses of tropical malaria are observed in the summer-autumn months; quartan malaria recurs in winter. Untreated or poorly treated, long-term relapsing malaria ultimately takes on a chronic course. Chronic malaria leads to greater or lesser significant disorders of the organism as a whole and changes in individual organs. These changes are the more sharply expressed, the more often relapses of febrile paroxysms occur. The latter, as already noted, become atypical, smooth out, and can ultimately proceed almost completely unnoticed. Only sometimes, with prolonged and careful measurement of temperature, is it possible to catch in it a reflection of the cyclically proceeding schizogony (Fig. 29). The patient's sensations also change sharply. Instead of the typical triad characterizing the febrile paroxysm of the acute period, chronic malaria brings with it indefinite sensations of disease: general malaise, fatigue, apathy, aversion to work, headaches, and dizziness, ringing in the ears, aching in the limbs and lower back. Later, a number of complaints arise, caused by changes in various organs. The very appearance of the chronic malaria patient becomes quite characteristic. The skin gradually takes on a greenish-gray, earthy color, sometimes with a slight yellowish tint. Brownish-ashen pigment spots often appear on the face. In the area of the wings of the nose and lips, herpes breaks out from time to time, more often during exacerbations. On the skin of the trunk, rarely, as in the acute period, there may appear either short-lived scarlatiniform or urticarial (Mufel, Sokolov) or more persistent hemorrhagic (Braude, Demyanov) rashes [see separate table (col. 647-648), Fig. 1]. The mucous membranes are usually pale, and in the oral cavity, they may be covered with pigment spots. One of the most characteristic symptoms of chronic malaria is considered to be enlargement of the spleen, most often reaching large sizes in the quartan (Griesinger, Kushev) and tertian forms. Conversely, the tropical form often proceeds without enlargement of the spleen. Enlargement of the spleen occurs either predominantly along the longitudinal axis or in the transverse diameter. Telyatnikov links this difference in the shape of the enlarged spleen to the form of malaria, while Oganesov links it to constitutional factors. A distinctive feature of the enlarged malarial spleen is its density. Malarial splenomegaly, especially frequent and intense in endemically malarial localities, requires great attention, as cases of rupture of large malarial spleens have been described; trauma is more often the etiology of the rupture, but spontaneous ruptures are also possible. In the origin of malarial splenomegaly, repeated hyperplasia of the pulp plays a role, which ultimately takes on a persistent character, and in later stages, the development of connective tissue. The liver in chronic malaria is also sometimes enlarged and indurated; more often, changes in the liver can be detected by determining its functions (Volsky and Sheveleva). Most constant in chronic malaria are changes in the red blood, creating secondary malarial anemia. The number of erythrocytes is reduced, anisocytosis, poikilocytosis, and polychromatophilia appear; in more severe cases, nucleated erythrocytes and erythrocytes with basophilic stippling are found in the peripheral blood. In parallel with the drop in the number of erythrocytes, the percentage of hemoglobin also falls, with hemoglobin continuing to decrease even after the number of erythrocytes becomes stable; their resistance increases. The number of plasmodia parasitizing the erythrocytes of the peripheral blood usually falls to a minimum, not detectable in a thick drop. The number of blood platelets is reduced. Characteristic changes in the white blood for chronic malaria are considered to be leukopenia, a decrease in eosinophils, and monocytosis (Kushev, Svenson). Brailovsky considers the appearance of a large number of degenerative forms, an increase in the number of predominantly large lymphocytes, and the appearance of Türk cells to be characteristic of the chronic course of malaria. Any revival of the vital activity of blood parasites, causing a more or less pronounced clinical manifestation of a relapse, is accompanied by a shift of neutrophilic leukocytes toward band forms and young forms, characteristic of an acute attack, and the shift in such cases has a definite cyclic character associated with the course of the paroxysm. It should be borne in mind that, as in a healthy person, the number of leukocytes and the ratio of their individual types are extremely labile and easily change under the influence of constitutional factors and various extraneous conditions in which the chronic malaria patient may be at the time of the examination. The increase in the bilirubin content in the blood serum noted in the acute period of malaria can be established to a lesser extent in the chronic course of malaria (Russo and Serbinov); however, with a small number of blood parasites, the bilirubin content does not exceed normal figures. In addition to the above-described changes, more or less constant in the acute and chronic courses of malaria, changes can also be observed in other organs and systems. The described bronchitis and pneumonia of "malarial origin" should rather be recognized as secondary, caused by common pathogens of pulmonary diseases and developing on the basis of a weakening of the organism (Tsiman). In some cases of microscopically diagnosed malaria, complications with bronchial asthma and hemoptysis have been described; the etiological dependence of these complications on malaria is usually based on the success of quinine therapy. On the cardiovascular system, the chronic course of malaria is reflected by a persistent weakening of vascular tone (Shabashov). Repeated severe attacks, especially of tropical malaria, can lead to a weakening of the heart's strength and its dilation. These changes are not persistent, and under the influence of rational treatment, the state of the vessels and heart returns to normal. Attempts to attribute inflammatory diseases of the walls of the heart and vessels (malarial endocarditis and endarteritis) to malaria are poorly provable and do not fit with general ideas about the pathogenesis of malaria. Digestive disorders, accompanied by vomiting or diarrhea, are more characteristic of an acute attack of malaria. In malarial localities, chronic muco-hemorrhagic colitis is often associated with chronic malaria. In all cases of such colitis, a thorough bacterioscopic and bacteriological examination of the stool is necessary, which may reveal the true dysenteric (protozoal or bacillary) character of the disease. Long-term chronic malaria, according to observations by Karapetyan and Sharov, disrupts the secretory function of the stomach in the direction of an unstable decrease, and according to old observations by Triantafillides, can be accompanied by persistent diarrhea, sometimes representing the only clinical manifestation of a paroxysm. Such intestinal forms undoubtedly also require an extremely cautious attitude in the sense of establishing their malarial origin. Barbitsky, Puchek, Gurevich, and others, observing transient albuminuria and nephrosis-nephritis in chronic malaria, see confirmation of their malarial etiology in the effect of quinine therapy.
Marsh questions the direct dependence of kidney lesions on malaria; according to Shirokogorov's observations, pathological-anatomical changes in the kidneys in chronic malaria are not the rule. Changes in the nervous system are especially often associated with malaria. During the acute period, they are expressed in transient delirious, soporous, and (as an extreme expression) comatose states. During a prolonged, severe course of malaria, as with any other infection, more persistent infectious psychoses can also arise (see below—malaria psychoses). In the chronic course of malaria, painful manifestations attributed to it on the part of the central nervous system, peripheral nerves, and the autonomic nervous system have been described. Lesions of the central nervous system, depending on their intensity and localization, can manifest in the form of hemi-, mono-, or paraplegia or pareses, aphasias, ataxias, meningo-encephalitic symptoms, or symptoms of multiple sclerosis and more often follow febrile exacerbations of the disease. The mechanism of the emergence of these phenomena is apparently analogous to that in malaria coma (see above). On the part of the peripheral nerves, neuritis and polyneuritis and neuralgias are described, most often of the trigeminal, less often of the intercostal, ulnar, or other nerve branches. These complications, especially neuralgias, are more characteristic of the afebrile period of the disease and are often considered the only manifestation of a malaria attack. Their origin is most often attributed to a toxic factor: poisoning of the nervous system by a hypothetical malaria toxin, as well as general exhaustion of the nervous system under the influence of the anemia accompanying chronic malaria. The lesions of the autonomic nervous system and the endocrine apparatus sometimes attributed to malaria are explained by the same factors. However, they are described significantly less often and have been studied less thoroughly. The frequency of complications on the part of the nervous system is undoubtedly dependent on the intensity of the malaria epidemic; for endemically malarial localities, some authors (Triantafillides for Batum, Grosman for Astrakhan) determine it at 2–3%. In the majority of cases, changes on the part of the nervous system are observed during the course of tropical malaria, but they are also possible in other forms of it. The diagnosis of nervous complications of malaria (neuromalaria) is based on anamnesis data, the characteristic intermittency of symptoms, and the effect of quinine therapy. Confirmation of the diagnosis by finding blood parasites is not always successful and is more characteristic of complications of the acute period. Establishing the malaria etiology of nervous symptoms usually provides a good prognosis ad sanationem. However, with a prolonged course of untreated or poorly treated malaria, more persistent changes are possible that no longer respond to quinine therapy. Among the sense organs in malaria, eye lesions are most often described. During attacks, conjunctivitis may be observed, sometimes unilateral; herpes may localize on the cornea; sometimes true superficial or deep keratitis, retinitis, and hemorrhages are also observed. In chronic malaria, cases of inflammation of the optic nerve have been established, a characteristic feature of which is fluctuations in visual acuity. All these complications on the part of the eye, according to the testimony of ophthalmologists, respond well to treatment with quinine, being extremely persistent with ordinary symptomatic therapy. The dependence of hearing function impairment on malaria is less studied and established. An extreme expression of the changes characteristic of chronic malaria is malaria cachexia, or malaria wasting. Severe anemia, a yellowish-earthy skin color, yellowish-pale mucous membranes, hydremic edema, hemorrhages with an enlarged liver, and a spleen descending below the navel in an ascitic abdomen (see separate table, figure 2) characterize the malaria-cachectic patient. In the origin of cachexia, besides the malignancy of the malaria itself, incoming conditions play a huge role, primarily starvation, accompanying chronic infections, and helminthic infestations. A so-called latent malaria stands apart in the nomenclature of malaria diseases. Under this name, some (Swenson et al.) understand the inter-attack period of malaria, when, in the presence of parasites in the peripheral blood, there are no objective and subjective manifestations of the disease. In another definition, especially widely spread among practical doctors in malarial localities, latent malaria is understood as very diverse and often rather indefinite painful sensations in the absence of clinical signs typical for acute and chronic malaria and parasites in the peripheral blood. This form is called masked (larvata) by Ziemann, Swenson, and others. Most typical for latent malaria in its latter definition are complaints of apathy, reluctance to work, drowsiness, irritable nervous weakness, headache, sweating, etc. Proponents of the diagnosis "latent malaria" confirm the malaria etiology of such disorders by the sometimes noted periodicity of the appearance of symptoms and the effect of quinine therapy. It should be kept in mind that long-term observation and thorough examination in a significant part of such cases allow for the establishment of an etiology other than malaria for such manifestations (initial forms of pulmonary and glandular tuberculosis, blood diseases, helminthic infestations, rheumatism, climacteric, hystero-neurotic states, etc.). Therefore, in order to bring clarity to the recognition of malaria, it is necessary to abandon the term "latent malaria," and the diagnosis of the inter-attack period should be confirmed only on the basis of definite objective data (Toporkov, Kushev). This is all the more important as the deceptive temporary effect of quinine in such cases only distracts attention from proper causal therapy. As a chronic disease, malaria in its course can be combined with various acute and chronic diseases, exerting one influence or another on them and itself undergoing one change or another under their influence. The influence of hereditary and constitutional factors on the course of malaria is very likely, but it has still been studied quite insufficiently. To date, a large number of observations have been accumulated confirming the possibility of congenital malaria disease. Although infection with malaria is possible at any age, the course of malaria in children is sometimes distinguished by particular malignancy. Sex does not exert an influence on the course of malaria. Regarding temperament, Ziemann points out that phlegmatics tolerate malaria better than cholerics and sanguines. The influence of race on the course of malaria apparently boils down to questions of immunity. Residents of localities with endemic malaria gradually accumulate relative immunity to malaria with age and pay tribute to it mainly with their younger ages. Northerners and residents of mountains, upon entering malarial localities, become infected with malaria especially quickly and tolerate it especially severely. Among the nationalities of the USSR, in any case, neither particularly immune nor particularly predisposed to malaria outside the above-mentioned conditions have been noted. The influence of environmental conditions on the course of malaria is completely indisputable. All factors of a physical and psychic order leading to the weakening of the organism can disturb the balance between the vital activity of the plasmodium and the protective function of the organism and lead to the awakening of untreated malaria. Conversely, bodily and mental rest can contribute to the speediest cessation of clinical manifestations of malaria. This last fact can partly explain the sometimes observed self-cure from malaria attacks upon a change of locality, when, with a change of locality, general living conditions also change for the better. The past pandemic, which coincided with the famine in the Volga region, once again confirmed the fact of the enormous influence of famine and malnutrition on the course of malaria. In localities affected by famine, the malignant forms described above were especially often noted, and among them, comatose malaria was in first place. In the best case, malaria took on a persistent chronic course, creating characteristic types of malaria-cachectic patients. In famine years, even m. tertiana and m. quartana, which are relatively mild under ordinary conditions, took on a malignant character characteristic of the tropical form. All kinds of diseases, especially chronic ones, by weakening the organism, also create a predisposition to infection and repeated relapses of the infection. In recent years, the influence of helminthic infestations on the course of malaria and its resistance to treatment with quinine has been especially noted (Permyakov, Mufel). Pregnancy, childbirth, and the postpartum period activate latently proceeding malaria, and malaria attacks, in turn, can harmfully affect pregnancy, threatening premature termination of it. The relationship between malaria and surgical operations is analogous: the latter can provoke malaria attacks, while surgeons, during surgical intervention, should keep in mind the tendency of chronic malaria patients to bleed, the sluggishness of healing and restorative processes in them, etc. Individual observations on the simultaneous course of malaria and typhoid fever, malaria and relapsing fever testify, firstly, that such combinations in any case worsen the patient's condition, and secondly, that the intervention of malaria disrupts the typicality of the temperature curve of the primary disease. However, Swenson and Buchstab did not see such an influence of malaria on typhoid and relapsing fevers in their cases. The influence of malaria on the course of pulmonary tuberculosis has been repeatedly attested by exacerbations of the tuberculous process, hemoptysis, etc.
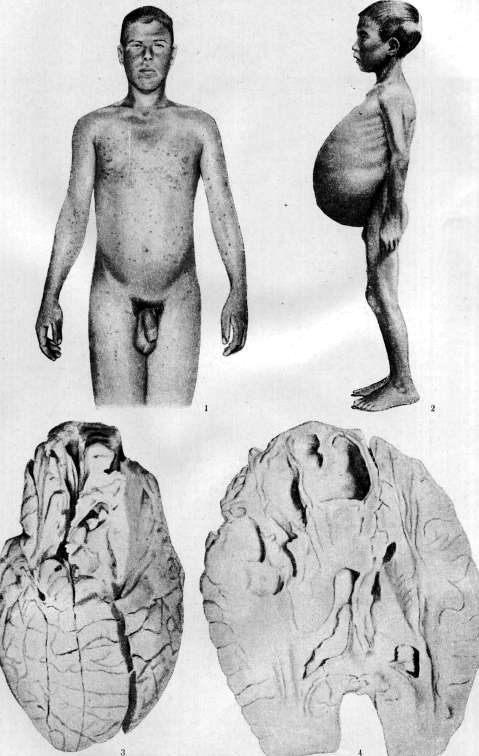
Figure 1. Hemorrhagic rash in a patient with malaria. Figure 2. Splenomegaly in chronic malaria (boy, 5 years old). Figure 3. Destruction of the left frontal lobe by abscesses. Figure 4. Section through the posterior part of F2. Lower part.
abscesses occurring after or during malaria attacks. The observations of Marcou-Mutzner regarding the antagonism between tuberculosis and malaria and the suggestion to use the latter in the treatment of tuberculosis are unfounded. Likewise, the view regarding the incompatibility of cancer and malaria is unfounded. Since the publication by Wagner von Jauregg of observations on the beneficial effect of malaria in the treatment of progressive paralysis, malaria inoculations for therapeutic purposes have been tested in a significant percentage of cases with very satisfactory results on many thousands of progressive paralytics. The use of malaria in the treatment of gonorrhea is in the study stage. In leukemic hyperleukocytosis, Lucherini observed a rapid but transient decrease in the number of leukocytes under the influence of a malarial attack. Attempts to use malaria as a therapeutic agent for some other diseases (dermatitis, interstitial keratitis, etc.) must be considered rather unsuccessful.--For infection for therapeutic purposes, tertian, less often quartan malaria is usually used. Infection is carried out by injecting subcutaneously or (preferably) intravenously several cm3 of parasite-containing blood taken from the cubital vein of a malaria patient. Some prefer infection by natural means, i.e., through the bite of an infected mosquito, which is much more complicated. The incubation period of experimental (therapeutic) malaria, depending on the time and method of infection, the type of parasite, and the individual characteristics of the person being infected, fluctuates within fairly wide limits. On average, with intravenous infection with the tertian form, it is equal to 1-5 days; with infection with the quartan form, it is longer. The incubation periods for subcutaneous infection for both forms are longer and more indefinite. In areas with endemic malaria (observations of the Astrakhan Malaria Station), sometimes infection of local residents does not succeed at all, even with repeated attempts. When infected with Pl. vivax, after several days of initial irregular-type fever (see above), and when infected with Pl. malariae, from the very first attack, the course of febrile attacks typical for one form or another is established. M. quartana is distinguished by particular stability and regularity in this regard (Fig. 22 on pp. 637-638). Physically healthy and strong infected individuals usually tolerate the attacks well and do not give cause to interrupt them prematurely. In case of necessity (threatening condition of the patient, end of treatment), therapeutic malaria is easily controlled and cured by conventional methods. The diagnosis of acutely occurring malaria does not present great difficulties in typical cases, especially if there is an opportunity for long-term observation of the patient. The typical features of a malarial attack described above, its onset predominantly in the pre-lunch hours, its short duration, and the sequential alternation of periods of chills, fever, and sweating allow one to immediately suspect malaria. The onset of the next attack after 48 or 72 hours confirms the diagnosis and resolves the question of the form of malaria. It is more difficult to recognize double forms of tertian and quartan and irregular forms of tropical malaria, when attacks occur daily, and sometimes a new attack is superimposed on the previous one that has not yet ended. In such cases, it is necessary to differentiate from septic diseases, deep abscesses, hectic fever in tuberculosis, late stages of typhoid fever, etc., especially since almost all the named diseases can occur with chills, sweats, and an enlarged spleen. A careful study of temperature, especially if it is not disturbed by the use of antipyretics, helps to clarify the diagnosis by revealing the typical development curve of the main generation of parasites. The diverse manifestations of malignant, predominantly tropical malaria, in particular its comatose form, can present great difficulties for clinical diagnosis, since in them the main features of the attack often disappear and the periodicity of symptoms is smoothed out. Such malignant forms often arise in people who have not previously had malaria, therefore they may also lack the general features of long-term malaria—characteristic skin color, enlarged spleen. One can arrive at the recognition of malaria in such cases sometimes only by way of exclusion, by the absence of signs of typhoid, typhus, and relapsing fevers, miliary tuberculosis, central pneumonia, or uremia in the case of a comatose state. Without the help of a laboratory, the diagnosis in such cases is often extremely difficult. The diagnosis of long inter-attack periods of chronic malaria is even more difficult. The reason for a patient to consult a doctor in such cases is indefinite states of malaise, headaches, aching in the lower back, limbs. It is not difficult to suspect malaria in these complaints when the subjective sensations have an intermittent character; in other cases, suspicion of malaria arises from the patient's statements about previously experienced typical malaria attacks, about his stay in a malarial area. Although fever is absent, careful measurement of temperature in more recent cases can sometimes reveal small, periodically regular fluctuations of it. Among other objective symptoms that make the diagnosis of malaria more or less certain are the characteristic color of the skin and mucous membranes, and enlargement of the spleen. In ordinary diagnostic practice, one is content with palpation of the spleen, which gives an idea of its enlargement and consistency; sometimes percussion of it is resorted to. Osetinsky and Nevyadomsky propose fluoroscopy for recognizing more subtle changes in the size and consistency of the spleen, but this method is difficult to implement for most practical doctors and is not justified by necessity. When assessing the diagnostic significance of an enlarged spleen, one should remember, firstly, that the most severe tropical forms of malaria often occur without enlargement of the spleen, and secondly, that enlargement of the spleen is characteristic of many other disease processes. Zito and Georgievsky attach great diagnostic importance to the presence in malaria patients of a painful point in the ninth intercostal space on the left between the mid-axillary and posterior axillary lines. Tabolov describes a pain point at the level of LII 3 cm to the left of the spine. The absence of an absolute clinical symptom confirming the diagnosis of chronic malaria forces one to differentiate the diagnosis from a whole range of disease forms. Kushev provides a list of 19 diseases with which malaria can be confused. This list can undoubtedly be significantly increased. Most often, one should keep in mind the early stages of pulmonary tuberculosis, and in children, tuberculosis of the lymph (bronchial) glands; only long-term observation of patients using all available diagnostic methods for one disease or the other can make it possible to make a correct diagnosis. Another common cause of disorders similar to chronic malaria can be various helminthic infestations leading to anemia and nutritional disorders. Such misleading conditions are especially often observed in those infected with hookworm; in more northern latitudes, carriers of the broad tapeworm, dwarf tapeworm, ascarids, or whipworms can also exhibit symptoms similar to malaria. Krylov quite correctly warns against confusing chronic septic diseases with malaria, and Rubel warns against endocrine disorders in women, especially since both diseases can be accompanied by recurrent subfebrile states with subjective symptoms that very much resemble the complaints of a chronic malaria patient. In women during the climacteric period, subjective sensations of short-term chills and fever, appearing at different times of the day and usually several times a day, are often mistaken for malarial manifestations. Furthermore, one should keep in mind diseases of the white and red blood, deep-seated malignant formations of internal organs, syphilis of internal organs, familial hemolytic jaundice, etc. In the southern regions of the USSR or in persons who have been there, Malta fever (see) is possible, characterized by an undulating course of febrile attacks, or the rarer kala-azar (see Leishmaniasis), clinically similar to extreme degrees of malarial cachexia. To be confident in a correct diagnosis of chronic malaria, a doctor must be well acquainted with the manifestations of the above-listed diseases, as well as with malaria itself.--A practitioner can use the prescription of quinine ex juvantibus as an auxiliary diagnostic method in difficult cases. However, great caution is required when using this method. Firstly, by using quinine for a long time without results, one can lose time that is precious for proper causal treatment; secondly, quinine can be misleading, exerting a temporary alleviating effect even in non-malarial conditions. Therefore, the diagnostic use of quinine is permissible only in cases where the doctor lacks auxiliary diagnostic methods and should be only short-term and sufficiently energetic, taking into account all possible reasons for its beneficial effect. The possibility of using laboratory research methods immeasurably improves, clarifies, and accelerates the diagnosis of both acute and chronic malaria. The most valuable laboratory method is the examination of blood for the presence of plasmodia in it.
In acute cases, as a rule, the finding of vegetative forms of plasmodia establishes the diagnosis of malaria; their absence (given correctly performed repeated examinations, of course) rejects such a diagnosis. In cases not treated with quinine, plasmodia can be detected during apyrexia, but the use of quinine very quickly reduces their quantity to a minimum, no longer detectable by the research methods available to us. Spleen puncture, and even more so bone marrow puncture, proposed for finding plasmodia in latent malaria, cannot be approved for practical use, as they represent interventions that are too significant for the patient. Moreover, their use is not justified by the results obtained (Telyatnikov, Puchek, Nikolaev). For blood examination for plasmodia, at the present time, the thick drop method is used: a dry-wiped, degreased glass slide is brought into contact with a drop of blood obtained by pricking the pulp of a finger or earlobe; with a circular motion, the size of the blood spot on the slide is brought to approximately 1 cm in diameter, then the drop is dried in the air (protect from flies!) or in a special drying cabinet, and after drying, it is treated with a solution of Giemsa stain (1-2 drops per 1 cm3 of distilled water): during this treatment, the leaching of Hb from erythrocytes by distilled water and the staining of their stroma, leukocytes, blood platelets, and blood parasites with the diluted stain occur simultaneously. After drying, the drop is examined with an immersion microscope system. Rukhadze proposed drying the drop in an inclined position, which concentrates the blood parasites in the lower segment of such a crescent-dried drop. A blood smear, stained according to Giemsa, is used for a more detailed familiarization with the blood parasite and for establishing its species, since in a thick drop this is not always easy to do, especially for an inexperienced researcher. The longer the period of apyrexia, the more difficult it is to detect plasmodia in the peripheral blood; in cases of chronic malaria, plasmodia are rarely detected at the first examination. An exception is the crescents (gametes of tropical malaria), which sometimes remain in the peripheral blood for a very long time even after the acute period has passed. In order to increase the number of plasmodia or to bring them into the peripheral blood, methods of malaria provocation have been proposed; for this purpose, massage, showers, faradization of the spleen area, small doses of quinine, injection of foreign protein, adrenaline, etc., have been used. However, a reliable method of provocation is still unknown to this day. In the absence of plasmodia during repeated examinations for the diagnosis of malaria in the inter-paroxysmal period, one has to resort to auxiliary laboratory methods, the combination of positive results of which, in connection with anamnestic and objective data, can give a certain confidence in the presence of malaria even before the detection of plasmodia in the blood. Among these auxiliary methods, the examination of the leukocyte formula according to Schilling has become widespread. (The state of white blood in acute and chronic malaria is described above.) Simultaneously with the leukocyte count, one can detect the content of pigment in some of them, but such findings are successful only in fresh cases and more often in tropical malaria. A certain sign, but again more for fresh cases, can be thrombocytopenia. Of the changes in red blood, Sarkisyan attaches auxiliary importance for the diagnosis of malaria to an increased number of reticulocytes compared to the norm, detected by vital staining of the blood (see). The erythrocyte sedimentation rate in malaria is accelerated, as in many other diseases: when excluding the latter, it can be a valuable diagnostic sign of malaria. However, in the most difficult chronic cases for diagnosis, the value of the sedimentation rate is smoothed out. The comparative complexity of determining the resistance of erythrocytes to hypotonic NaCl solutions is not justified by the results provided by these determinations. Attempts to involve immunity reactions in the diagnosis cannot yet be considered successful. True, the Wassermann reaction turns out to be positive in a large percentage of cases of acute malaria, but with the disappearance of the paroxysms, it quickly becomes negative. Savchenko and Baronov, Mirochkin, and Kingsbury proposed using specific antigens prepared from the organs of malaria patients or from plasmodia for the complement fixation reaction. Good results with these antigens, obtained by the authors themselves, have not yet been practically used. The precipitin reaction of Taliaferro and the intradermal reaction of Herman and Lifshitz also still require further verification and study. Finally, for the diagnosis of malaria, the fact of an increase in the amount of bilirubin in the blood and the appearance of urobilin in the urine can be used. However, precisely in the inter-paroxysmal periods, which are the most difficult for diagnosis, when the activity of the plasmodium destroying erythrocytes falls to a minimum, bilirubinemia decreases to normal figures, and urobilinuria disappears. Only long-term studies and the plotting of a bilirubin content curve can allow for the detection of the cyclicity of this curve, coinciding with the cyclicity of relapses, especially in tertian malaria (Brzhozovsky, Kataeva, and Klyueva, etc.). The prognosis for malaria disease can usually be considered quite favorable. The outcome of an acute primary illness is largely determined by the speed of establishing the correct diagnosis and the duration of the treatment applied. If, after the cure of fresh malaria, the patient remains under the long-term supervision of a doctor and undergoes repeated anti-relapse treatment, then the transition of malaria to a chronic form usually does not occur. It goes without saying that the outcome of the disease is also largely determined by environmental conditions (labor, nutrition, etc.). Of the individual forms of malaria, tertian and quartan malaria have the mildest course, but they often give persistent relapses, and patients with these forms are subject to particularly long-term control. The tropical form, which is more severe in clinical manifestations, is less prone to relapses with proper long-term treatment. The prognosis becomes very serious in malignant forms and especially in comatose malaria. In the latter, even the most energetic treatment remains unsuccessful in most cases. Poorly and untimely treated or untreated malaria, which passes into a chronic form and (in endemically malarial areas) is supported by repeated reinfections, is rightly compared in its effect on the body with tuberculosis and syphilis. The prognosis for such a chronic form is accordingly significantly less favorable. However, in cases that have not reached severe cachexia and organ degeneration, a quite favorable prognosis is also possible, provided there is proper treatment and (if necessary) the elimination of external factors that delay recovery. F. Toporkov. IX. Malarial psychoses. Malarial psychoses, i.e., mental disorders associated with malaria infection, belong to the number of rather rarely encountered infectious psychoses. Most often they arise on the basis of tropical malaria; therefore, they are more likely to be encountered in subtropical and tropical countries (e.g., in Azerbaijan, Italy, Algeria, etc.). However, the possibility (admittedly rare) of the appearance of malarial psychoses on the basis of m. tertianae and m. quartanae is not excluded. Mild forms of malaria less often give complications from the mental side. Malarial psychoses can arise both in acute and in chronic (manifest or latent) malaria. In most cases, young subjects aged 25 to 35 years fall ill with them. Poor general conditions—hunger, poverty, and fatigue—play an important role in terms of predisposition to the disease of malarial psychoses, but personal predisposition and individual resistance of the psyche to the toxic effect of malaria infection in its malignant form also play a significant role. Pathological-anatomical changes in malarial psychoses essentially boil down to pathological-anatomical changes in the brain during severe malaria infection. The lesion in this case has the character of a severe toxic process with a relatively moderate protective reaction on the part of the tissues. The process itself is essentially a meningoencephalitis with regressive and simultaneously progressive phenomena, which have a more or less generalized character. The dominant role in the pathogenesis of malarial psychoses is apparently played by intoxication, either by specific toxins of malaria parasites (if these toxins exist), or by products of incorrect chemical metabolism that have appeared in the body under the influence of infection, or finally by the decay products of the parasites themselves, pigment, or elements of various tissues. From a clinical and etiological point of view, malarial psychoses can be subdivided into 3 groups: the first includes cases where a mental disorder, having a toxic-infectious character, arises primarily, i.e., during acute or chronic malaria in the height of the infection, in the period of the existence of febrile paroxysms and in the presence of a large number of malaria parasites in the blood.
The second group includes cases where a psychiatric disorder, also of a toxico-infectious nature, arises secondarily, i.e., following the disappearance of febrile attacks, during the period of the subsiding of the malarial infection or its transition into a latent, chronic state. In this case, malarial plasmodia may no longer be present in the blood, but a number of other somatic signs of chronic malarial infection are discovered, up to and including malarial cachexia. To the third group should be assigned cases of non-infectious psychoses (outbreaks of manic-depressive, schizophrenic, and other psychoses) that arose under the influence of a trigger provided by the malarial infection. There appear to be no special clinical forms inherent exclusively to malarial infection. As clinical forms of malarial psychoses, the following symptom complexes are observed: 1) dream-like hallucinatory delirium; 2) syndrome of acute confusion or amentia; 3) manic and depressive states with hallucinatory-delusional phenomena; 4) epileptiform states of agitation; 5) stuporous states; 6) state of paranoid delusion; 7) amnestic (Korsakoff) syndrome; 8) pseudoparalytic syndrome. The aforementioned clinical forms belong to the so-called exogenous reaction types identified by Bonhoeffer and encountered in psychoses with various exogenous toxico-infectious etiologies, including psychiatric disorders on the basis of malaria. In more recent times, there is data suggesting that the appearance of one or another of the above-mentioned syndromes may be connected with the constitutional predisposition of the patient. It should be noted that certain clinical pictures are more characteristic of different stages of malarial infection. Thus, dream-like hallucinatory delirium is more often observed in malarial psychoses belonging to the 1st group (see above), while the amnestic (Korsakoff) syndrome, appearing as a result of prolonged infection, is more characteristic of psychoses of the 2nd group. In their course, psychiatric diseases in Malaria present characteristic features. Psychoses of both the first and second groups can proceed in the following forms: 1) episodic acute psychiatric disease, lasting from several hours to one month, either accompanied by elevated temperature (febris perniciosa delirans) or without it (psychosis delirans). 2) Periodic attacks of psychiatric disorder ('psychosis typica'), usually lasting no more than several hours and following the type of febrile attacks, accompanying the latter with regular intermissions during periods of apyrexia. In some cases, attacks of psychosis typica can replace febrile attacks and become psychiatric equivalents of the latter. 3) Protracted delirium (psychosis delirans protracta) — an episodic psychiatric disorder, like febris perniciosa delirans or like psychosis delirans, but dragging on for a longer period (more than a month, with or without an increase in temperature) and capable in some cases of transitioning into a chronic form, sometimes continuing for years (e.g., in malarial cachexia). Prognosis in malarial psychoses should be considered relatively favorable. The most frequent outcome is complete recovery. Recoveries with a defect are rarer; incurable cases are even rarer. Treatment of malarial psychoses consists of symptomatic measures (usual measures applied in psychiatric practice) and causal measures (quinine, arsenic preparations). Prophylaxis of malarial psychoses can be reduced to general preventive measures applied in relation to malaria.
A. Perelmin. X. Treatment. Malaria is one of the few diseases for which the use of purely specific therapy is possible; other therapeutic interventions are usually not required. However, in chronic, persistent forms, the improvement of the general condition of the patients, especially of the nervous system, is of no less importance (Ostroumov). In cases of very high temperature, decline in cardiac activity, symptoms from the gastrointestinal tract, etc., symptomatic measures are also carried out according to the usual rules of therapy. Adherence to any specific diet is not indicated, although there is an indication that a diet rich in sugar predisposes to relapses. The main, as yet unsurpassed, remedy for malaria is quinine. Among the other medications proposed in large numbers for the treatment of malaria, only methylene blue, organic arsenic preparations, and especially plasmochin, which has been introduced into practice in recent years, deserve attention. The basic principles of malaria therapy boil down to the fact that neither quinine, nor especially any other remedy, nor a combination of these remedies provides a therapia sterilisans magna in malaria, regardless of the dose of the preparation and the duration of treatment. It is not always possible to prevent a relapse in every individual case. When conducting rational therapy, it is necessary to observe the following rules: 1) strict individualization of each individual case (characteristics of the patient, type of parasite); 2) treatment should be started as early as possible; each attack leads to the appearance of new sexual forms and a protracted course of the disease; 3) correctness of the application of the medication both in terms of the choice of preparation, its dosage, and the method of its administration and giving it in the proper form; 4) treatment of the attack and prevention of recurrence; 5) prevention of habituation to the preparation; 6) treatment of the consequences of the infection. The first task is to combat the attacks that exhaust the patient, which usually cease quickly with proper treatment. The recovery that occurs after such basic treatment is, as a rule, only apparent. After a short time, a relapse occurs. In order to give the patient the opportunity to recover and to delay the onset of a relapse for as long as possible, it is necessary to carry out long-term, systematic follow-up treatment. Complications are treated according to general rules. Treatment of a relapse is carried out according to the same principle as the first attack. The use of the provocation method in latent malaria in cases of sluggish infection cannot be recommended, as we are not in a position to foresee the severity of the artificially induced attack. Quinine. The mode of action of quinine in malaria has not yet been clarified. It has not been definitively clarified whether the therapeutic effect of quinine in malaria should be attributed primarily to its direct parasitocidal property or to an indirect influence through the activation of the body's protective systems. Different types of malaria parasites react differently to the action of quinine. The tertian form of malaria is the easiest to treat, the quartan is more difficult, and the tropical is the most persistent. Asexual forms of the parasite are much more susceptible to the action of quinine, especially the young ones. Sexual forms are very persistent. In tropical malaria, it is sometimes necessary to conduct treatment for many months to achieve the disappearance of crescents from the peripheral blood. When using even therapeutic doses of quinine, side effects of the preparation are sometimes observed: headache, tinnitus, dizziness, trembling of the hands. Nausea, vomiting, diarrhea, sweating, confusion of ideas, and clouding of consciousness occur much less frequently. One can also note various rashes, erythema, eczema, urticaria, general skin infiltration, edema, and hemorrhagic diathesis. Taking quinine can be a trigger for the manifestation of an attack of hemoglobinuric fever. Disturbances of vision and hearing are very rare. In most cases, these complications can be avoided by prescribing small doses and simultaneously giving bromine (Solutio Natr. bromati 10%, 1 tablespoon 3 times a day) and calcium preparations (Sol. Calcii chlorati 10%, 1 tablespoon 10 minutes before taking quinine). In patients who do not tolerate quinine (idiosyncrasy), in cases of inflammation of the middle ear, and even more so in the event of a developed attack of hemoglobinuric fever, one has to abandon quinine. Among quinine preparations, Chin. muriaticum is the most common; Chin. sulfuricum is almost equivalent to it. Chinin. tannicum is less effective. Euchinin has a good effect (it is almost insoluble in water, devoid of a bitter taste, and does not have the side effects of quinine); the doses are approximately the same as those of quinine. It is usually used in pediatric practice. The solubility of the preparation in water does not play a role—they are all well absorbed in the intestine. The average dose is 1.0 pro die. High doses have no advantages. Children tolerate quinine well. The average dose is as many decigrams per day as the age in years, and as many centigrams as the age in months. During pregnancy, quinine is not contraindicated; however, it should be prescribed in fractional dosages with long pauses. Quinine for malaria is administered orally, subcutaneously, intramuscularly, intravenously, per rectum, and externally. The simplest and most appropriate method is administration per os. It is best to prescribe it after meals. With proper prescription, it is almost always possible to manage with the oral administration of quinine. The negative aspects are the bitter taste (prescribe in cachets) and the irritating effect on the digestive tract. Quinine tablets must first be tested for their solubility in water. It is useful to monitor the absorption of quinine by analyzing urine for quinine. Parenteral methods of administering quinine—subcutaneous, intravenous, and intramuscular—differ from each other both in the strength of action and in various kinds of complications. Easily soluble Chininum bimuriaticum or Chininum muriaticum with the addition of antipyrine for solubility is administered subcutaneously. For example, Chinini bimuriatici 50%, 1 cm3 per injection; Chinini muriat. 3.0, Antipyr. 2.0, Aq. destil. q. s. ad 6.0, 1 cm3 per injection. The absorbability of quinine is not complete and is somewhat delayed. Abscesses and tissue necrosis are observed. With intramuscular administration (the same prescription), tissue necrosis occurs more often. These methods have no special advantages and are indicated in cases of insufficient absorption due to damage to the gastrointestinal tract. Intravenous administration of quinine has the advantage that the preparation is introduced directly into the blood at the proper moment and in the proper concentration (e.g., Chinini muriatici 1.0, Sol. Natr. chlorati physiol. ad 100, 50.0–100.0 per infusion). However, the possibility of obtaining severe complications with intravenous administration of quinine, up to a fatal outcome, limits the indications for it to cases where a rapid effect is required, for example, in the comatose form of malaria. Contraindications: blood in the urine, vascular diseases, clearly expressed jaundice, diseases of the endocrine glands. Administration of quinine per rectum cannot gain wide application in view of the inconsistency of the results obtained due to the insignificant absorption of quinine through the colon. Rubbing into the skin is completely unjustified. Administration by means of iontophoresis does not give satisfactory results. Despite the large number of different methods of treatment, they can be divided into two main groups: 1) more or less short-term treatment aimed exclusively at combating attacks; 2) long-term treatment, in which follow-up treatment is carried out, aimed at delaying the onset of a relapse. In the treatment of only the attack, the administration of quinine according to the method proposed by R. Koch is often used a few hours before the expected onset of the attack. Koch pointed out the rationality of administering quinine in such a way that it circulates in the blood in the maximum amount at the moment of the appearance of large schizonts in it, i.e., the forms of the parasite least resistant to quinine. He advised judging the time of appearance of one or another stage of development of the plasmodium in the blood with the help of a microscope. Practically, this is difficult to implement, and the matter boils down to giving a daily dose of quinine 4–6 hours before the start of the expected attack. But even clinically, it is often not possible to establish the onset of an attack. The works of Celli, Grassi, Giemsa, and Schaumann proved that with small doses of quinine given to a patient at short intervals, one can achieve the same, if not greater, therapeutic effect as with treatment with a single large dose of quinine. When giving fractional doses, a summed effect of quinine is obtained, which allows one not to reckon with the stage of development of the parasite. These conclusions were used by Nocht and formed the basis of the intermittent treatment with fractional doses of quinine proposed by him. The therapeutic dose of quinine is distributed into several small ones and given throughout the day. When giving fractional doses over several days, the body is constantly under the influence of quinine in a concentration sufficient to prevent the occurrence of new attacks. The advantage of this method is the possibility of not reckoning with the stage of development of the parasite, the prolonged action of the medication, the reduction of its side effects, and the elimination of the possibility of habituation to it.
The basis for the majority of treatment methods proposed by various authors lies in the views of Koch or Nocht set forth above. Treatment methods. Strümpell administered quinine 5-6 hours before the expected attack, 1.5-2.0 per dose. In case of a new attack, the treatment is repeated. Zakharin proposed the following method: for a month, quinine is given daily at 0.3 every hour (1.5 per day). In case of ringing in the ears, every 2 hours. Nocht's method became widely used. Initially, upon establishing the diagnosis, Nocht gave quinine at 0.2 every 2 hours (5 times a day) for 7 days. Then followed an alternation of days with quinine administration and pauses in the following order: 3 days pause, 3 days quinine; 4 days pause, 3 days quinine and further: 5 and 3, 6 and 3, 7 and 3, 7 and 1, 7 and 1, 7 and 1, 7 and 1. Total 72 days. The modified method boils down to the following: 10 days, 6 times a day every 2 hours, 0.25 of quinine; then pauses of 2, 3, 4, 5, and 6 days, alternating with two days in which quinine is given; 4 pauses of 7 days, alternating with one day with quinine. Total 72 days. The latest scheme: quinine is given at 0.3 three times a day during attacks and for the following 5 days. Then 4 days pause, 3 days quinine, and so on for 6-8 weeks. Ochsner uses the following method: 1) on the evening before giving quinine, the patient receives 0.1 calomel; 2) during treatment, nutritious soups are given (rice, barley, vegetable, etc.); 3) for 48 hours continuously, every 2 hours, 0.15 of quinine is given; washed down with hot water; 4) for six days, quinine is not given; 5) on the eighth day, a laxative; 6) from the 9th day, the procedure is repeated; 7) upon completion of treatment, tonics are given for several weeks. Moshkovsky assumes that the effect of quinine manifests in the circulating blood, especially at the moment of quinine's entry into the blood, and therefore he strives, through appropriate administration, to ensure a sufficient concentration of quinine during the entire asexual development of the parasite. He gives 0.2-0.3 of quinine around the clock at four-hour intervals; for tropical and tertian malaria—a total of 15-16 doses, and for quartan—20-24 doses; after a 5-6 day break, the treatment is repeated with a new pause (the subsequent days of quinine administration correspond to the most frequent times of disease relapse). Depending on the severity of the case, this plan allows for individual deviations. Methylene blue acts on adult and sexual forms of the plasmodium. Side effects: irritation of the kidneys and bladder, pain during urination (strangury), epigastric pain, nausea, vomiting, diarrhea, headache, paresthesia, convulsions in children. Urine is colored blue or green. It gives the best results in m. quartana. To prevent strangury, nutmeg is given simultaneously. Average dose 0.1-0.2 per dose, up to 1.0 per day in cachets. E.g., Methylenblau 0.1-0.2, Pulv. Nuc. moschat. 0.1, M. D. in capsul. gelatin., 1 capsule 3 times a day. Arsenic. Inorganic preparations are successfully used as an additional measure in the treatment of malaria. They are prescribed orally (Ac. arsenicosum, Liquor arsenic. Fowleri) or subcutaneously (Sol. Natr. kakodylici 10%, Sol. Natr. arsenicici 1%). Good results are obtained by combining arsenic with quinine, e.g., Chinini ferrocitrici 6.0, Ac. arsenicosi 0.1, Strychnini nitrici 0.06, Mas. pil. q. s. ut f. pil. No. 60; 1 pill 3 times a day. Complex organic preparations (Neosalvarsan, etc.), as possessing parasitotropic action, have been proposed for specific therapy. These preparations have a good effect in m. tertiana; in m. quartana they are of little effect, and in m. tropica, activation of the process is often observed. Indications: 1) severe exhaustion and emaciation of the patient (for the purpose of quickly obtaining an immediate result); 2) gastrointestinal symptoms; 3) quinine resistance and idiosyncrasy to quinine. Dosage of Neosalvarsan: men 0.45-0.6, women 0.3-0.45, children 0.15-0.3. Repeated infusions after 4-6-8-10 days are necessary. Ziemann injects neosalvarsan three times in a row at intervals of 6 days in doses of 0.45-0.6-0.6. Immediately after the infusion, treatment with quinine follows. On the day of the infusion, quinine is not given. An organic arsenic preparation, Osarsol, is also successfully used against malaria orally in the usual dosage (0.25, three to four tablets a day, a total of 18-20 tablets per course). Plasmochin is a preparation prepared synthetically; its active principle is a base of the quinoline series (diethylamino-isopentyl-8-amino-6-methoxyquinoline). Introduced into practice in recent years, it gives good results in all forms of malaria. Its destructive effect on the sexual forms of tropical malaria is especially pronounced; it acts more weakly on the asexual forms of tropical malaria. The treatment methods are the same as for quinine. Dosage: adults 3 times a day at 0.02, children from 5 to 10 years 3 times a day at 0.01, from 1 to 5 years 1-2 times at 0.01, infants 0.01 per day. This dosage must not be exceeded due to the possibility of side effects, mainly the appearance of cyanosis as a result of methemoglobin formation. Isolated fatal cases have also been described after plasmochin in severe anemias with jaundice. Cardiac decompensation is a contraindication for giving plasmochin; in hemoglobinuric fever, plasmochin is not contraindicated. Combined treatment. In a number of cases of persistent malaria, combined treatment yields better results than using each agent separately. Most often, combined therapy with quinine and methylene blue is carried out. Good results are obtained by Kushev's method: for 12-15 days, 1 cm3 of a solution containing 0.5 Ch. bimuriatici and 0.03 methylene blue is injected subcutaneously. Rubashkin advises prescribing iodine-quinine orally (T-rae Jodi 5%, Sol. Chinin. mur. spir. 10% aa 10.0; 25 drops 2 times a day) or subcutaneously (for 2 months, 5-10 cm3 of a solution containing 0.01-0.02 iodine and 0.5-1.0 quinine). Three days of injections, 3 days of pause. Good results are noted with combined treatment with quinine and organic arsenic compounds, as well as methylene blue and neosalvarsan (Lyakhovetsky). In cases of tropical malaria, combined treatment with quinine, which acts on schizonts, and plasmochin, which destroys sexual forms, is recommended. In Germany, the preparation Plasmochinura compositum has been released. A tablet contains 0.01 Plasmochini and 0.125 Chinini sulfurici. Dosage: 2 tablets 3 times a day. Treatment method: same as quinine according to Nocht. At the Tropical Institute of the People's Commissariat of Health (Moscow), the following scheme of combined malaria treatment has been adopted: Plasmochin. purum 0.01 and Chininum mur. 0.2-0.3 are given per dose, 5 doses per day, for 3 consecutive days, with a four-day pause; such treatment lasts 4-6 weeks. In persistent cases, especially with significant splenomegaly, intramuscular injections of iodine-salol according to David are prescribed; Jodi puri 0.2, Saloli 2.0, 0.01 Olivarum 10.0, 5-8-10 cm3 once a week. Folk remedies. Favorite preparations among the population are various drops and tinctures from sunflower, eucalyptus, wormwood, lilac leaves, aspen bark, oak, willow, etc. Their prevalence must be explained by their inherent bitter taste, which resembles quinine. The use of these agents to replace quinine has no basis and cannot but affect the patient's condition in the sense of its deterioration. By taking an easily accessible but indifferent in terms of specificity surrogate, the patient gains confidence that they are being treated and only neglects their disease. XI. Anti-relapse and prophylactic quininization in malaria. Directly adjacent to the treatment of malaria is the so-called anti-relapse therapy, the conduct of winter-spring prophylactic treatment of malaria patients. Its task is the completion of treatment of the malaria patient during the winter time and the prevention of the occurrence of spring relapses, at least in all those who were ill in the previous malaria season. In part, this measure is also carried out during long-term systematic therapeutic quininization. This idea is far from new. At one time, it was widely propagated in Italy. In a number of cases, good results were also obtained in the USSR. In implementing this measure, there are a number of obstacles, which are far from always easy to overcome. However, the results obtained justify the energy expended. And here the position is confirmed that the treatment of malaria patients has significance not only as a measure of an individual nature—curing the patient—but also as a measure of broad prophylactic significance. At the present time, it must be considered fully proven that organized, systematically conducted treatment of malaria patients and plasmodium carriers, extended also to the inter-epidemic period, is expedient and sufficient in terms of the results achieved, even in the case when it is conducted as the only anti-malaria measure. Prophylactic quininization. One has to deal with all the above-mentioned difficulties when conducting prophylactic quininization.
In the true sense of the word, this measure cannot be called purely prophylactic, since by carrying it out, one cannot prevent infection, cannot hinder the penetration of the parasite into the human organism, and cannot paralyze its vital activity. Even in the case of implementing systematic quinization, the matter boils down to preventing even the onset of a malaria attack. The methods of prophylactic quinization are very diverse and boil down to the systematic administration of quinine daily or with greater or lesser intervals. The following regimens have gained the greatest distribution: a) Daily quinization, especially popular among Italian, French, and English authors. The main method is that of Celli (the Italian method): 0.4 g of quinine daily. b) Intermittent quinization; popularized mainly by German authors. It has two variants. 1. Intermittent quinization with short intervals: the ordinary Plehn method - 0.5 g of quinine for two days in a row, a break of 3 days, etc. The reinforced Plehn method: 1st day 1.0, 2nd day 0.5, a break of 3 days, etc. The Ziemann method: 1.0 every 3-4 days. According to Laveran, quinine is prescribed at 0.5 every other day; according to Moshkovsky, 0.3-0.4 for two days with intervals of 3 days. 2. Intermittent quinization with long intervals. The Koch method: 1.0 per day every 10th or 10th and 11th day. The modified Koch method: 1.0 for two days in a row, a break of 5 days, etc. (Nocht). None of these methods provides an absolute guarantee against contracting malaria. Prophylactic quinization should begin with the onset of warm weather and end no earlier than the onset of cold weather. The dates are established depending on the climatic conditions of the area. The expediency of this measure is far from recognized by everyone. Opponents point out that in many of those undergoing prophylaxis, the disease is not prevented, but only the moment of its acute manifestation is delayed. The result is a large number of latent malaria carriers, which, in the opinion of some, makes this measure even dangerous in an epidemiological sense. The disease is not prevented, not cured, but only hidden foci of malaria are created. On the other hand, defenders of prophylactic quinization point to a significant decrease in morbidity among those being quinized, as well as to the fact that the disease observed in a portion of those undergoing prophylactic quinization is pushed back to the winter period, which is not dangerous in the sense of further transmission of the disease, which undoubtedly has a definite epidemiological significance. The possibility of protecting large masses during the most important moments of their activity—the construction season, field work, peat extraction, bridge construction, etc.—is of no less importance in economic terms. Finally, the strategic importance of prophylactic quinization among military units during the camp period, during maneuvers, and during military situations is also noted. In the USSR, in recent years, prophylactic quinization has been carried out in some places on a large scale, but the results obtained are nevertheless contradictory. Regularity of quinization is of great importance. In Rostov, during the implementation of prophylactic quinization among workers of a number of enterprises, 4,007 who were regularly quinized yielded only 0.3% of cases, against 4.3% among 928 who were quinized irregularly, while 1,401 who were not quinized yielded 28% of cases. When carrying out prophylactic quinization, it is necessary to reckon with the following basic provisions. Prophylactic quinization should be carried out only among organized, fully disciplined groups of the population, and at the same time, those placed in conditions of easy infection with malaria: peat workers, workers on land reclamation projects, Red Army soldiers, etc. An indispensable prerequisite is the significant development of malaria in the given area. The organization of the work must guarantee the regularity of quinization and accurate recording of results. It is mandatory to simultaneously carry out systematic, prolonged treatment of all malaria patients. Favorable results can be obtained only on the condition that the work is entrusted to special "quinizers" under the mandatory supervision of a physician.
Mufel. XII. Malaria in children. The prevalence of malaria among the child population in various places varies depending on the general conditions that determine the spread of malaria; during the last pandemic (1921–25), the percentage of patients among certain groups of the child population reached 50% and higher. No age group possesses immunity against malaria, but infants, who are usually more carefully protected from mosquito bites, have comparatively fewer cases of the disease; the older the group of children examined, the higher the percentage of those infected turns out to be. Children suffering from congenital malaria are in some cases born prematurely, anemic, weak, and with enlarged livers and spleens. In other, more frequent cases, children of malarial mothers are born on time and completely normal, but after 10–20 days they begin to show symptoms of the disease, and then blood examination reveals malaria parasites in them. In such cases, transmission of the infection from the mother during childbirth is assumed, at the moment of placental detachment and rupture of the villi, when mixing of the mother's blood with the child's blood can occur. The clinical picture of malaria in children differs from that of an adult the more, the younger the sick child is. The first clear illness of a child with malaria is often discovered in early spring, when infection via mosquitoes could not yet have occurred. Such cases may represent relapses of diseases that began in the previous year, the first manifestations of which remained unnoticed or unrecognized. More often, these are the results of last year's infection with a very long incubation period. A child infected with malaria becomes sullen or irritable; their skin becomes increasingly pale, and then subicteric; the mucous membranes also pale; they eat worse, do not gain weight, or even lose weight. Some time after the onset of the disease, the spleen increases in size in almost all cases, which at first may be painful and very hard. Liver enlargement occurs less frequently and is more pronounced the younger the patient is. In infants, a typical malaria attack is observed very rarely; they almost never have chills; at the beginning of an attack, they turn pale and become cyanotic; vomiting often occurs at this time, sometimes convulsions. The rise in temperature in many cases is insignificant or completely absent. There is also no profuse sweating after an attack; usually, only the head and neck become slightly moist. After an attack, the temperature sometimes drops very little, so the temperature curve has the character of a continua. At this age, malaria often manifests only as severe anemia, enlargement of the liver and spleen, and ever-increasing cachexia. In older children, malaria generally proceeds as it does in adults, but the child's organism reacts to the malarial infection with pathological phenomena faster and more strongly than the adult organism. Severe forms of anemia develop here more often and faster than in adults; diarrhea, sometimes taking on the character of colitis, nephritis and nephrosis, meningeal symptoms, etc., are also not uncommon in malarial children. In neglected cases, cachexia develops faster in children than in adults. With a prolonged course of malaria, it affects the general development of children, so that in areas with endemic malaria, the height, weight of children, and other anthropometric indicators lag behind the norm. By lowering resistance to various harmful factors, malaria very unfavorably affects the course of other diseases in children; on the other hand, various childhood diseases, such as measles, less often scarlet fever, can provoke latent malaria in a child. Due to the atypical course, the absence of pronounced attacks, and numerous manifestations from various organs in malaria in children, symptom complexes often arise that present a clinical similarity now to congenital syphilis, now to tuberculosis, typhoid fever, meningitis, or other diseases. The outcome of childhood malaria is in most cases favorable, provided that the disease is recognized early enough and treatment is carried out long and energetically enough. For the prevention of congenital malaria, persistent and prolonged treatment of malaria in pregnant women is required. In a malarial area, children should not be allowed to go out after sunset, and in the house, they should be protected from mosquito bites by installing screens on windows and doors, bed canopies, etc. When choosing a place for playgrounds, summer colonies, pioneer camps, and other children's institutions, beware of the proximity of bodies of water, swamps, etc. Conduct health education work with children in schools. Give children quinine prophylactically in the spring and after debilitating acute illnesses. Treatment. Rest, proper nutrition, and other general measures that increase resistance are of great importance. Quinine should be used for a long time and in relatively large doses; children tolerate it better than adults; the schedule of its administration is of less importance. The daily dose for older children is 0.1 g for each year of age; in infancy, 0.02 g per 1 kg; this dose is divided into 2–3 doses. Undoubtedly, this dose can also be increased. Easily soluble preparations are preferable due to better absorption, but if sometimes, due to their bitter taste, they have to be replaced by insoluble and therefore tasteless ones, such as Aristochin, Euchinin, Insipin, etc., the dosage should be 30–50% higher. In case of persistent vomiting from internal doses, intramuscular injection or quinine per rectum in an aqueous solution is used. Intravenous infusions (of a 10% solution of quinine hydrochloride) should be used only in cases requiring emergency aid, e.g., in the comatose form, etc. Until the temperature normalizes and for 2 weeks after that, the patient receives a full dose of quinine daily, after which they must take either half-doses daily or full doses with breaks according to one of the accepted schemes for at least two months. For the chronic form, in addition to quinine, methylene blue in an amount of 0.01 g for each year of age or plasmochin at 0.01–0.02 g 2–3 times a day is recommended (poisoning phenomena can occur). For subsequent treatment, arsenic and iron. No known method of treatment guarantees against relapses; only very prolonged treatment with large doses of quinine, according to some authors, prevents recurrences (so-called massive quinization). E. Lepsky. XIII. The fight against malaria. 1. Methodology of the fight against malaria. The fight against malaria is built on the modern doctrine of the essence of malarial infection, taking into account the accessible influence on the complex of factors that lie at the basis of its epidemiology. In theoretical terms, the principles of the fight against malaria have been developed exhaustively. However, in practice, measures are very often and even in the majority of cases difficult to implement. As a result, the problem of fighting malaria, despite its detailed development in methodological terms, actually remains one of the most complex problems. The paths to a radical solution to this problem usually go far beyond the capabilities of health authorities. For areas with a wide spread of malaria, the fight against it is a problem of national scale. It requires systematic work by all links of the state apparatus with the mandatory cooperation of the population itself. The correct implementation of the fight against malaria is possible only if there is special anti-malaria legislation. In accordance with modern data on the epidemiology of malaria, measures to combat it are divided into two main groups: 1) measures to combat the causative agent of malaria (Koch's method) and 2) measures to combat the mosquito (Ross's method). In addition, 3) measures of personal and public prevention in the proper sense and 4) measures of a social order can be distinguished into a special group. A. Measures to combat the causative agent of malaria consist of the systematic implementation of mass treatment of malaria patients and parasite carriers. The goal of the method is the sterilization of the virus reservoir and the exclusion of the possibility of infecting the vector. The main means of the method is quinine. In countries with seasonal malaria, it is especially important in a prophylactic sense to carry out the method in the pre-epidemic season (March–May or April–June, depending on the beginning of the malaria season). The correct implementation of the method assumes systematic examination of the population and good registration of malaria patients. The organizational form of implementation is the dispensary. The method of treating malaria patients is the main prophylactic means for fighting malaria, since the fight against vectors, difficult in itself, is often not very accessible in the necessary volume. The difficulty of implementing the method is connected with the need to organize a wide dispensary network and the mass expenditure of quinine. B. Measures to combat the mosquito have the goal of destroying the vector and its breeding grounds; methods of protection against mosquito attacks (see below) also belong here. The fight against the vector is built with direct consideration of its biological characteristics. The methods of fighting are extremely diverse, in a certain part very complex and expensive (fighting large-scale swamping). The choice of methods always requires caution and careful coordination with local conditions. Ignoring the latter point easily leads to the unproductive waste of funds.
At the same time, properly organized measures can sometimes yield high efficiency even with a small expenditure of funds. Measures as a whole can be summarized according to the following scheme. 1. Measures for the destruction of the vector. a) Combatting winged mosquitoes has limited significance due to technical inaccessibility. The destruction of overwintering females (Anopheles maculipennis, Anopheles superpictus) is most indicated. It is carried out primarily by gas methods: fumigation of premises with sulfur (5-10 g of sulfur per 1 m3), disinsection with cyanide gas in a concentration of 0.02-0.03% (dangerous!); stunning with tobacco smoke (burning tobacco dust mixed with 30% saltpeter) or simple smoke (burning pine needles, etc.) followed by the collection and destruction (burning) of the stunned mosquitoes. Spraying with appropriate liquids is also used (e.g., Malinin liquid, 1% soap-cresol solution, 3% lysol solution). In some cases, burning mosquitoes with a flame (stone basements) or simply catching them can be used. The breeding of bats, which destroy mosquitoes in large quantities, is rational. Special towers are used for breeding bats. b) Destruction of mosquitoes at the larval stage is much more effective and is one of the radical means. Measures related to this must be carried out in an area with a radius of up to 2-3 km from residential premises (the average range of Anopheles spread from breeding sites). However, the treatment of water bodies located in the immediate vicinity is of particularly great importance. The methods of greatest practical importance include the use of so-called 'larvicidal' agents (chemical method) and the stocking of water bodies with pests that destroy larvae (biological method). The use of larvicidal agents is based on the treatment of water bodies with various chemical substances that destroy larvae. Various chemical compounds and compositions have been proposed as larvicidal agents: oil and kerosene, saprol (a mixture of mineral oil with 35-40% cresol), Panama liquid (a mixture of crude carbolic acid, resin, caustic soda, and water prepared according to a special recipe), 'larvicide' (a mixture of aniline dyes), Paris green, calcium chloride, etc. The greatest practical importance belongs to the flooding of water bodies with kerosene or oil (petrolization and oiling) and the dusting of water bodies with Paris green. Both methods are used for the periodic treatment of water bodies every 10-15 days throughout the entire mosquito season, i.e., from early spring to late autumn (e.g., in the south—from April to October inclusive, every 10 days). Petrolization and oiling consist of flooding water bodies with kerosene or oil with the calculation of forming a film on the treated water surface. The action of the method is toxic and suffocating; the efficiency is high and universal (all aquatic stages of mosquitoes of the genera Anopheles, Culex, and Aedes perish within approximately 3 to 6 hours). The norm of kerosene and oil is from 20 to 40 cm3 per 1 m2 of water surface. It is most rational to perform the flooding with the help of a hydraulic pump (ordinary or special); in the absence of the latter, one can use garden watering cans. The scattering of sawdust moistened with oil or kerosene, as well as running a rag soaked in kerosene or oil and attached to a pole over the water surface, is practical. Depending on the width of the water body, the flooding is performed from the shore (a good hydraulic pump can deliver a jet to a distance of up to 5-7 m) or from a boat. If there are significant thickets in the water body, preliminary cleaning is necessary. For the treatment of canals with flowing water, one can use the drip method: a barrel with a hole, into which a wick is inserted, is installed on boards thrown across the ditch; the liquid drips along the wick into the water. Oiling has no harmful effect on fish. Dusting with Paris green, introduced by Barber and Hayne (1921), is one of the most modern methods for destroying Anopheles larvae. The radical nature of the action, along with practicality and cheapness, has gained the method wide popularity in America and Europe. The essence of the method is that Paris green [CuHAsO3 + Cu(C2H3O2)2] is mixed with dust and distributed over the water body in the form of a film. Anopheles larvae, which usually feed on the surface, ingest the floating particles of the arsenical preparation and quickly perish. The method acts only on Anopheles larvae, but does not act on its pupae, nor on Culex and Aedes larvae. Paris green must contain no less than 50% arsenious anhydride (quality test: 1 volume of green should dissolve without residue in 3-4 volumes of ammonia to form a blue color). The technique of dusting is as follows: Paris green is thoroughly mixed with dry, sifted road dust in a ratio of 1:100 (mixing is best done in a closed rotating box). The mixture is sprayed on the surface of the water body at a rate of 10 cm3 of the mixture (0.1 cm3 of Paris green) per 1 m2 of water surface. Spraying is performed with the help of special dusters (garden dusters work well) or by hand. For dusting large areas, airplanes are also used with success. Cleaning water bodies of vegetation is not mandatory. When using Paris green in the above-mentioned concentrations, the method is harmless both to fish and to animals (Martini; 1927). Among the biological methods of destroying Anopheles larvae, the stocking of water bodies with special breeds of fish, of which the American Gambusia (see) has acquired well-deserved popularity, deserves special attention. The attempted experiment of stocking water bodies with Gambusia in the south of the USSR (Transcaucasia) was completely successful; the fish have been successfully cultivated to the present time (Georgia, Azerbaijan). Gambusia destroys Anopheles larvae well, but only on the condition of a sufficiently dense stocking of water bodies with it. As an anti-larval measure, the distribution of Gambusia deserves great attention. It is necessary, however, to note that other fish (e.g., carp) also energetically destroy Anopheles larvae and therefore can be recommended for breeding in appropriate water bodies. On the other hand, some domestic birds (ducks) also energetically devour larvae and therefore deserve attention in this regard. The same must be noted regarding the aquatic plant 'bladderwort' (Utricularia), the bladders of which capture penetrating larvae. Abundant growth of duckweed (Lemna) makes water bodies little suitable for colonization by Anopheles larvae. 2. Hydrotechnical measures for the destruction of stagnant accumulations of water, which serve as breeding places for Anopheles, have very great preventive significance when properly indicated and executed. They can be extremely diverse in character, scale, cost, and accessibility. In a practical sense, one can speak of small hydrotechnical measures, which do not require complex devices and are accessible for manual execution (small bonification); they can be contrasted with large hydrotechnical measures carried out by engineering means (large bonification). The general scheme of measures for combatting water stagnation can be summarized as follows (see also Melioration): 1) Evaporation, being one of the factors of the natural circulation of water in nature, can have great significance for the drainage of water accumulations under appropriate climatic conditions (example—Mugan Steppe). The evaporation of water through plants, in turn, is a very strong drainage means (cereals suck up to 900 cubic meters of water per 1 hectare from the soil during the growing season, sugar beets—up to 2,600 cubic meters). Hence—the rationality of planting appropriate plants for the purpose of drainage. In particular, the planting of eucalyptus (daily evaporation up to 35 cubic meters of water per 1 hectare), sunflowers, willow, etc., is recommended. 2) The installation of absorption wells (vertical drainage) is used for the drainage of water bodies formed during the delay of water infiltration by impermeable rocks. 3) Ensuring surface runoff of water is the most common method of drainage and prevention of waterlogging. It is used everywhere where the discharge of water accumulations into rivers, the sea, etc., is possible. When water accumulations are located above the level of the discharge reservoir, the diversion of water is carried out by a continuous system of diversion canals. In the opposite case, preliminary lifting of water by machine means (installation of pumps of various systems) is ensured. 4) Filling in of water bodies [artificial colmatage (from the Italian colmare—to fill)] is practiced everywhere where possible; it is especially recommended for the destruction of small water bodies. 5) Natural colmatage or silting of a flooded lowland by the intake of water rich in suspended particles is used in cases where other methods (water discharge, etc.) are inaccessible. The goal of the method is to raise the level of the lowland with settling silt.
The method requires prolonged application and is indicated only in special cases. 6) Deepening of water bodies with appropriate treatment of the banks is practiced in cases where the elimination of water accumulation is inaccessible or impossible. The goal is the transformation of the water body into an uninhabitable one for Anopheles. 7) Construction of closed or open drains (see) for the diversion of soil waters is practiced as one of the usual measures for draining marshy areas. Open drains require constant supervision, as they can easily turn into a breeding place for Anopheles. 8) Construction of barrier dams, embanking of banks and their reinforcement, regulation of riverbeds are the main means for preventing flood inundations. 9) Elimination of water stagnation in irrigation and drainage ditches by cleaning them (overgrowth), construction of steep banks and their reinforcement, regulation of water flow, etc., are a mandatory condition for the sanitary improvement of irrigation and drainage systems. 10) Application of intermittent, or alternative irrigation and water filling, recommended by Vasilyev (Tashkent; 1911) and Sergent (Sergent) for neutralizing stagnant flooding. Principle: water is let in for a week; in the following week the water inflow is stopped, the waterlogging dries out, and the larvae perish; water is again let in for a week, etc. The method is practical but applicable only with sufficient evaporation. As observations have shown, in particular in Azerbaijan and Armenia, the principle of intermittent irrigation can be successfully used for rice cultivation. The plantation is flooded for 10 days with a subsequent interruption of water inflow for 4 days. Four-day drying ensures the death of larvae and is well tolerated by the rice crop (Voskresensky and Brenn; 1927). 11) Destruction of plant overgrowth in water accumulations is a very important auxiliary measure for eliminating breeding sites. 12) Mechanical protection with lids or nets of wells, vats, cisterns, and other reservoirs is a mandatory measure for preventing their colonization by mosquitoes. Elimination of piles of broken dishes, cans, etc., prevents the emergence of small accumulations of water, which can turn into breeding places for mosquitoes. By analogy with anti-larval measures, measures to combat waterlogging should be carried out within a radius of up to 2-3 km from residential premises. It is important to pay special attention to the liquidation of small accumulations of water, which often have extremely great epidemiological significance. Generally speaking, it is very often the most accessible measures (minor land improvement) that are not carried out; meanwhile, with their help, very significant results can be achieved. At the same time, the effectiveness of large hydrotechnical works can be paralyzed by ignoring minor waterlogging. V. Prophylactic measures in the proper sense pursue the task of preventing malarial diseases in endemic areas among individuals (personal prophylaxis) or groups (public prophylaxis). The methods related to this are directed either at the pathogen of Malaria (prophylactic quinization) or at the vector (mechanical prophylaxis, etc.). 1. Prophylactic quinization boils down to systematic intake of quinine for the purpose of preventing Malaria disease. In essence, this is preventive treatment of Malaria, calculated on the possibility of eliminating the infection upon its emergence or in the latent period. Prophylactic quinization should be systematically carried out throughout the entire malaria season or the duration of stay in a malarial area and additionally for 6-8 weeks after its end or after leaving the malarial area. (For methods of quinization, see above - anti-relapse and prophylactic quinization for Malaria.) 2. Mechanical prophylaxis has the goal of protection from mosquito bites. Its varieties are as follows: a) Screening of dwellings. The measure, tested with good results by Celli in Italy, has received universal recognition and deserves the widest application. Windows, doors, chimney and other openings are subject to screening; special attention is paid to the protection of sleeping quarters. The mesh of the nets is about 1.5-2 mm in diameter; nets made of stainless metal are preferable. Gauze can also be used. Screened premises require systematic supervision (condition of the nets, formation of gaps, etc.). b) Use of canopies made of gauze, muslin, or cheesecloth is the most practical and generally accessible measure for individual protection from mosquitoes during sleep. It is also rational to use head nets and gloves to prevent bites in the open air. c) Use of special towers for sleeping and the location of residential premises on upper floors is extremely rational in connection with the very limited ability of Anopheles to fly in a vertical direction (usually no higher than a few meters, rarely up to 20 m). 3. Other prophylactic measures. When living in malarial areas, it is important to observe a certain regimen: limited stay in the open air after sunset and during the night (the period of vector activity) is recommended; it is recommended to avoid any injuries that undermine the body's resistance (overwork, insufficient nutrition, alcohol abuse, etc.). Dwellings should be built at a sufficient distance (2-3 km) from waterlogged areas. Immigrants should avoid settlements in the immediate vicinity of local infected residents. It is rational to keep domestic animals in stalls on homesteads, which energetically distract Anopheles to themselves. Special mention should be made of measures to combat Malaria among incoming masses (military units, workers, settlers) arriving in severely malarial areas. They require special attention, as the inevitable diseases among them can easily take on epidemic spread, sometimes threatening with catastrophic consequences. Regarding military units in field conditions, the necessary measures boil down mainly to carrying out prophylactic quinization. In camp conditions, along with quinization, it is necessary to widely implement accessible measures of protection from mosquito bites and destruction of the vector. In particular, it is recommended to choose sites for camp locations as far as possible from waterlogged areas and villages affected by Malaria; possible placement of units on upper floors of buildings; screening of residential premises; use of canopies during sleep, where available; limiting stay in the open air after sunset and at night; carrying out minor hydrotechnical works to destroy stagnant water accumulations in the area of camp locations, destruction of Anopheles larvae (oiling, dusting); destruction of mosquitoes in residential premises (fumigation, use of appropriate liquids). Along with this, preliminary (before entering malarial areas) and sequential (during the stay in malarial areas) medical examinations of units are necessary for the purpose of timely identification of malaria patients and 'carriers' for their treatment. Regarding the masses of workers arriving in malarial areas, in general, the same measures are carried out (quinization, mechanical prophylaxis, combating minor waterlogging, combating the vector, organization of medical-sanitary service, etc.). It is necessary to especially note the danger of earthworks accompanied by the formation of waterlogging. Here, all measures are necessary to prevent the latter or to neutralize it (oiling, dusting). As for the protection of settlers, here, along with prophylactic measures of a general order, the question of preventing waterlogging, which often arises in connection with construction and irrational development of land plots (water use, irrigation), deserves special attention. Among the measures of personal prophylaxis, besides quinization, the use of canopies is especially indicated; the construction of towers for sleeping is also expedient. Settler masses must undergo a preliminary medical examination to identify malaria patients and 'carriers', who are subjected to mandatory treatment. In the future, settlers must be provided with proper medical-sanitary organization, under the direct guidance of which all measures to protect them from malaria are carried out. G. Social measures. The fight against Malaria as a whole and the problem of its radical resolution are inseparable from the general problem of social progress. The growth of culture and economic well-being are those prerequisites without which one cannot count on radical achievements in the fight against this infection, which in itself represents a deeply social problem. The very character and scale of anti-malarial measures are such that they are unthinkable for systematic implementation without ensuring them by the entire state organization. On the other hand, questions of everyday life and the economy of the rural population have a direct and often decisive significance for the successful resolution of the malaria problem. This includes, in particular, questions of housing, water supply and water use; questions of general culture, public activity, and hygienic education of the population; questions of intensification of agriculture and rationalization of irrigation work; questions of rational development of 'wild' lands and their reclamation, etc.
Of particular importance is raising the cultural level of the population and the problem of its sanitary education (compulsory teaching of hygiene in schools, etc.). In essence, the most accessible measures in the fight against Malaria become unrealistic in the absence of sanitary consciousness among the population. Finally, the question of anti-malaria legislation is of exclusively great importance, without which there can be no basic approaches to the proper organization of the fight against Malaria. For severely malarious regions, legislation must regulate mandatory measures for anti-malaria labor protection with all the consequences flowing therefrom. Legislative regulation of the order of water use and irrigation, etc., is also necessary. Given the variety of methods and directions that modern malariology provides for the fight against Malaria, the preferential choice of one or another measure presents a rather complex task. It must be solved in relation to the specific conditions of a given locality on the basis of a preliminary study of epidemiology. The implementation of uniform measures (fighting according to the Koch principle or the Ross principle) is not rational. It is necessary to implement the entire complex of measures and means that are accessible and indicated under the given conditions (the combined method). Systematicity and persistence in carrying out measures to fight malaria with a steady increase in their scope are of decisive importance.
P. Zdrodovsky. 2. The fight against Malaria in foreign countries. The beginning of systematic control of Malaria in foreign countries can be considered 1901—the time of the appearance of Italian anti-malaria legislation (the collection of the first consolidated data for the whole country dates back to 1885). In most other countries, systematic control of Malaria began after the imperialist war, which caused a rise in malaria morbidity in almost all countries affected by Malaria. Thus, the USA began the fight in 1926, Spain in 1924, Yugoslavia in 1918–1920, Palestine in 1920, Bulgaria in 1910 and 1919, Turkey in 1926 (the indicated years are the years of the publication of the first laws relating to the fight against Malaria). As a rule, this legislation, with the exception of Palestine, where the British issued decrees based on the experience of work in India, is based on Italian legislation. Anti-malaria organizations. There are organizations for the fight against Malaria that have an international character: the Malaria Commission under the hygiene section of the League of Nations, the Rockefeller Foundation, and the Pan-American Union. The first meets annually for sessions where it discusses measures of anti-malaria control, sends special expeditions to survey the most affected countries (such an expedition was in the USSR in 1924), and organizes annual courses for training anti-malaria workers in Paris, Hamburg, and Rome with subsequent internship in the most endemic countries. The Rockefeller Foundation maintains a number of experimental stations (Italy) for studying measures to combat Malaria, subsidizes scientific institutes in a number of countries (France, Spain, Palestine, Yugoslavia, etc.) in the study of the fight against Malaria, and provides scholarships for some of those studying in the League of Nations courses. The Pan-American Union was founded at the 2nd Pan-American Congress in 1916, at which all American republics pledged to develop a plan for the fight against malaria. Within individual states, the anti-malaria organization is different. In Italy, the entire fight is directed by the Department of Public Health under the Ministry of Internal Affairs, under which there are 3 commissions: for finding methods of better cure for Malaria, for X-ray treatment and prevention of Malaria, and for developing methods and plans for bonification (small sanitary works, mainly of a hydrotechnical nature). The entire practical fight against malaria is conducted by the general medical network. Only in the most affected places are there Rockefeller malaria stations and stations of Red Cross organizations. Supervision of the implementation of sanitary measures is entrusted to communal sanitary doctors. There is a special children's sanatorium for malaria patients. In Spain, there is a central anti-malaria commission under the Department of Health of the Ministry of Internal Affairs. Subordinate to it is the protozoan department of the Alfonso XIII Sanitary-Bacteriological Institute in Madrid and all malaria stations (about 25). The latter are engaged in the treatment of patients and preventive measures (see below). The organization in Yugoslavia is built on the same type, led by the Ministry of Health, which links all major hydrotechnical works with the Ministry of Labor. In Greece, there is an interdepartmental state anti-malaria commission. The "Voluntary Malaria Association" and the administration of the Ministry of Communications work most energetically in the fight against Malaria. The leadership of the practical fight has recently been concentrated in the hands of the Ministry of Hygiene, which has three special inspectors for this purpose. Likewise, only in recent years have about 100 detachments for the fight against Malaria been created, headed by medical students who have completed a short-term course on the fight against Malaria. The detachments work under the guidance of a department doctor. In Bulgaria, since 1919, a special anti-malaria inspectorate has been created in areas recognized as malarial by the Supreme Sanitary Council. The inspectorate consists of a malaria doctor, a hydro-engineer, and a zoologist in each district and autonomously directs anti-malaria measures in the area of its operation. Quinine distribution is carried out by paramedics, the clergy, and officials of village self-government. In every village declared affected by Malaria, a special person is assigned, whose duty is to distribute quinine, take blood from patients, and send it to the laboratory for examination. In Romania, there is no special anti-malaria organization. In Australia, under the Federal Ministry of Health, there is a Department of Tropical Hygiene, which also includes anti-malaria work. In the same ministry, there is an administration for hydrotechnical works. In Turkey, in places declared affected by Malaria, there are special commissions to which courses for special personnel and other anti-malaria organizations are subordinate. General leadership lies with the Ministry of Hygiene. In the USA, the leadership is headed by a National Committee of representatives of health and agricultural bodies, representatives of scientific organizations and universities, insurance companies, and other public organizations. Its tasks include: a) stimulating scientific and public interest in the malaria problem; b) serving as an intermediary between societies and individuals interested in the study and prevention of Malaria; c) coordinating their efforts with state and local authorities. The National Committee is divided into six sections: administrative, entomological, medical research, education and propaganda, sanitary engineering, and statistical, which conduct work according to their competence. Federal authorities subsidize the fight against malaria on the condition of a double investment to the allocated sum on the part of local bodies. In Peru, which began the fight against Malaria earlier than other South American republics, everything is organized under the Department of Public Health, which annually includes specific sums in the budget for the fight against Malaria. Quinine imported for the fight against Malaria is exempt from duty. Railways, individuals, and all organizations using hired labor are obliged to organize medical assistance to their workers either themselves or through dispensaries under the control of the inspectorate. Orders have been issued regarding the screening of houses and the planting of flooded crops. A period of 1 to 4 years was given for bringing land plots into a sanitary condition. Those who performed this best were awarded prizes. System of measures. I. Mandatory registration of Malaria as an infectious disease exists in most countries, even in such as Norway, Latvia, and Australia, where cases of Malaria are very few. Very few countries do not have mandatory registration (Bulgaria). II. In the presence of significant morbidity, legislation in Italy, Spain, Bulgaria, Turkey, etc., grants either the Ministry of Health or malaria commissions the right to declare an area unfavorable or affected by Malaria, which entails a whole system of mandatory measures, such as screening of premises, creation of anti-malaria detachments, free chemicalization, etc. III. In Italy and Bulgaria, there is a monopoly on quinine. In Italy, there is a state factory producing quinine salts from cinchona bark for the whole country. The income from sales goes to strengthening measures to combat Malaria. In Yugoslavia, Greece, Turkey, and Spain, the state purchases part of the quinine for the needs of anti-malaria organizations and for free distribution to patients. IV. Special training of anti-malaria personnel is conducted in almost all countries heavily affected by Malaria. In Italy, there is a school in Nettuno; in Spain, training is conducted partially at the Alfonso XIII Institute and mainly at the anti-malaria institute in Navalmoral. In other countries, special courses are organized for graduating students, paramedics (Bulgaria), etc. In Italy, in addition, hydrotechnical engineers and teachers are trained in relation to malaria. V. According to the decision of the anti-malaria commission of the League of Nations, the most essential measure for the fight against malaria is recognized as persistent and systematic treatment of all malaria patients and the finding and treatment of gametocyte carriers. To carry out this task, special outpatient clinics have been organized at malaria stations (Spain, Yugoslavia, Italy), quinine distribution points, and special quinine dispensers who travel daily in their area of work (Spain); finally, local medical personnel are widely involved both for special payment (Spain) and on a mandatory basis in case an area is declared unfavorable for malaria. The sale of quinine, in addition to pharmacies, is carried out by mail (Palestine), in tobacco shops, and at special points (Italy). Quinine is used almost exclusively internally; only in exceptional cases is subcutaneous administration performed. In most organizations, quinine is given for a single dose. In case of long distances, quinine is given to the patient for several days of intake; in order to combat the sale of quinine received by patients, the freely distributed quinine is specially tableted and colored. The sale of quinine issued free of charge is punishable by a fine in the amount of 20 times the cost (Turkey).
As for prophylactic quinine treatment, it is applied only to workers working in places particularly dangerous for malaria, in schools (Italy), and among troops (Bulgaria). Precise control over prophylactic quinine treatment has been established almost nowhere. -VI. Microscopy of blood, both for diagnostic purposes at the beginning of treatment and during mass examinations, as well as for monitoring the success of treatment, is performed both in the laboratories of malaria stations and in general-type laboratories, to which the attending physician can send blood for examination. In Spain, rural doctors in villages surrounding a malaria station send thick blood smears by mail car and begin treatment only in the case of a positive diagnosis. The answer is given on the same day. Dispensary care for the population, i.e., mass examination and treatment of all suspicious cases, is performed almost nowhere. Only in some countries, e.g., in Palestine, is there mandatory examination of all schoolchildren three times during their entire period of schooling and treatment of all those having malaria. Thus, about 20,000 children are under observation. Selective examinations of the population, especially schoolchildren, are conducted in Italy and Spain in order to establish the effectiveness of anti-malaria measures. These examinations are conducted in Italy in the winter months in order to exclude acute cases as much as possible. -VII. Mechanical prophylaxis by screening residential premises has significant prevalence along railways in Italy, and in particularly affected provinces of Spain, Yugoslavia, Greece, and Bulgaria. In the latter, the anti-malaria inspectorate in heavily affected places provides nets free of charge. The provision of mosquito nets is mandatory for hotels in Venice and for troops in Yugoslavia. -VIII. From the field of anti-malaria propaganda, one must point out the work among schoolchildren in Italy, where systematic instruction of students by teachers is conducted, and attempts in this direction in Bulgaria and Spain, where special brochures have been issued for this purpose. -IX. The fight against the mosquito is conducted both against the larval stage and the winged form. The legislation of a number of countries (Italy, Turkey, Palestine, etc.) provides for the maintenance of water reservoirs in a certain order and cleanliness and the destruction of unnecessary ones, not needed for life, by filling in, draining water, etc., with the law establishing certain penalties, mainly fines, for violation of these regulations. In those basins that cannot be destroyed, periodic cleaning of vegetation and the breeding of Gambusia fish are prescribed. In Spain, in many villages, there is a specially designated, most cleanly maintained basin for breeding and keeping Gambusia in large quantities, from where they are distributed every spring to all accumulations of standing water remaining after floods or left for watering vegetable gardens. In Palestine, the law mandates the screening of wells necessary for drinking in order to prevent the laying of mosquito eggs. In Port Said and Ismailia, a special inspection of all courtyards by a special anti-malaria detachment has been established, which pours oil into water bodies in order to fight mosquito larvae. Here, the fight against flies is also combined, which is carried out by the same detachment, pouring liquid into cesspools and latrines. In those places where drainage cannot be carried out and where water is not used for consumption, the destruction of larvae is applied by mandatory pouring of crude oil (Bulgaria), kerosene, and oil (Palestine). The use of Paris green has become particularly widespread. The fight against larvae is, as a rule, conducted in a three-kilometer zone around a village. A three-kilometer zone from a village is also established by the legislation of a number of countries for rice fields. In places located not far from the sea (the Black Sea coast in Bulgaria and Ferrara in Italy), the salinization of freshwater lakes and lagoons is performed by introducing seawater with the aim of preventing the development of malaria mosquito larvae. There were attempts to use chemically water-soluble substances: thus, copper sulfate at a ratio of 1:50,000 was used in the Drina River valley in Yugoslavia during spring floods. In Spain, in one region, pyrite was used for the purpose of poisoning larvae. During the imperialist war in Macedonia, a method of fighting the development of mosquito larvae in shallow streams was widely used by damming them and periodically releasing water, thus creating at times a very fast current, which led to the death of the larvae. Cementing the edges and bottoms of water reservoirs, as well as converting open wells to closed ones and using pumps, is widely spread and yields good results. Such measures have been decreed in Turkey, Yugoslavia, and other Balkan states. Measures to fight winged mosquitoes, aimed both at reducing the total number of vectors and (which is especially important) destroying infected specimens that are not yet able to transmit the disease, are especially recommended by the Malaria Commission of the League of Nations and are classified as priority measures. For the destruction of mosquitoes in houses, fumigation with smoke (Yugoslavia), spraying of a patented special liquid that kills mosquitoes (Italy), and finally, simply mechanical catching, performed regularly in houses and livestock premises (in some villages of Spain), are used. The fight against mosquito hibernation sites is by no means conducted everywhere. In Italy and Bulgaria, it is not conducted at all, based on the fact that all hibernating females cannot be destroyed, and the remaining ones can lay a sufficient number of eggs to produce the first generation, and furthermore, according to observations in Italy, it has been established that in a certain size of water body, only a certain number of mosquitoes can hatch due to nutritional conditions, since all other larvae, no matter how many eggs were laid, die from a lack of food. In Palestine, mandatory sulfur fumigation of water storage cisterns, where winged mosquitoes very often accumulate, has been decreed. -As a measure to divert mosquitoes from human dwellings, it is recommended to set up livestock yards nearby, where all mosquitoes flying to the dwelling rush. This measure has its supporters, especially in France and southern Italy. The catching of adult mosquitoes is also performed to account for the effectiveness of anti-larval measures. For this purpose, in the zone of operation of the station where the fight against larvae is being conducted, 10-20 points (houses, barns, etc.) are selected, and there, daily for 1/4-1/2 hour, the catching of mosquitoes and their counting is performed. Thus, a curve of mosquito density is established, and it becomes possible to establish the direction from which the main mass of mosquitoes flies into the village served by the station. In those cases where it is difficult to catch mosquitoes simply with a test tube, all openings and windows of the building are covered, with one window or door remaining open and covered only with gauze, after which fumigation is performed. The stupefied mosquitoes fly to the bright rectangle of the window, where they are caught on the gauze. This method is practiced when fumigating large barns in Italy. - X. Measures for the destruction of marshy areas and places of accumulation of standing water are provided for in almost all legislation of malaria-affected countries. In Turkish legislation, adopted in 1926, it is forbidden to create water bodies that could serve as a breeding place for mosquitoes. The destruction of unnecessary water bodies is carried out by labor service of citizens from 15 to 65 years old annually for 5 days. The same law imposes on every municipal administration the duty to build a water supply system within two years. In Palestine, there is a special subsection under the Department of Health for sanitary structures, through which all drainage projects pass. In Spain, the involvement of landowners in the costs of draining swamps is provided for by an order of the central malaria commission. In Bulgaria, the main measures for fighting malaria are considered to be bonification (sanitary hydrotechnical) works, while all others, such as quinine treatment and the fight against larvae, are considered secondary. The classic country for hydrotechnical works is Italy. Some drainage measures, e.g., near Grosseto and in the Pontine Marshes, date back more than a hundred years. The main types of bonification works are colmatage, drainage with free flow, and with water pumping by pumping stations. Natural colmatage is performed in Yugoslavia and around Grosseto in Italy. In Grosseto, the silting of the marshy valley has been carried out for several decades by periodically flooding it with the waters of the Ombrone River, which carry a great deal of suspended silt. At the present time, the first stage of work has been completed, which made it possible to sanitize the surroundings of Grosseto, and the second stage of work is underway, which covers several tens of thousands of hectares of land. The most common type of bonification is drainage. It is very widely practiced in foreign countries.
It is necessary to mention new methods of digging underground drains between the main water-collecting canals by means of a metal 'mole,' which creates an underground pipe from canal to canal. In those places where, due to terrain conditions, it is impossible to carry out direct drainage into the sea or into a large water artery, as for example in enclosed valleys or in coastal valleys cut off from the sea by a dune, water is collected by open drainage canals into a main trunk canal and then pumped by pumping stations into a high-lying artificial canal for discharge into the sea. Such structures exist in Italy in a number of places and are usually organized by joint-stock companies of landowners with a state subsidy, P. Sergiev. 3. The fight against Malaria in the USSR. Before the revolution, the fight against Malaria on a state scale was not conducted in Russia. This fight began only under Soviet power. A systematic fight against Malaria is possible only with its correct accounting and the identification of foci. For this purpose, the People's Commissariat of Health of the RSFSR in 1921 issued an order on the mandatory registration of Malaria patients. Subsequently, a special card was developed for the registration of malaria patients. In this card, in addition to questions common for the registration of infectious patients (surname, age, place of residence, profession), there are also the following: 1) diagnosis: clinical, laboratory, type of parasite, form of Malaria—primary, relapse, reinfection, Malaria carrier, chronic Malaria; 2) spleen enlarged, to what size; 3) liver enlarged, to what size; 4) complications; 5) combined disease with other diseases, which ones; 6) treatment. For individual forms of Malaria, the following definitions are given: 1) primary Malaria—a disease of persons in whose anamnesis Malaria had not been noted until the present time; 2) relapse—a return of acute manifestations of malarial infection in persons who had already been ill with Malaria in the current or previous season; 3) reinfection: a) a case of Malaria in conditions not excluding the possibility of new infection in persons who had previously been ill with Malaria, but who had not had any clinical manifestations of it in either the present or previous seasons; b) a disease with a new form of parasite, confirmed by laboratory blood analysis; 4) Malaria carriers (latent infection)—persons with the presence of a parasite in the blood, but in the absence of any clinical manifestations: elevated temperature, enlargement of the spleen, etc.; 5) chronic Malaria—a patient with clinical signs of malarial infection, but without acute manifestations. Correct registration made it possible to establish the foci of Malaria and the nature of these foci. At the same time, the question was raised about the systematic study of Malaria and methods of fighting it. For this purpose, the State Tropical Institute (see Institutes) was created in Moscow in 1920; institutes of a similar type were subsequently opened in Kharkov, Erivan, Baku, Tiflis, Sukhumi, Bukhara, Makhach-Kala (Dagestan), and Stalinabad. Protozoan departments were deployed at large sanitary-bacteriological institutes (Rostov, Saratov, Tashkent, etc.). One of the first tasks assigned to the tropical institutes was the training of personnel for the fight against Malaria through annually organized courses on Malaria, work with interns and graduate students, etc. The creation of a cadre of specially trained doctors made it possible to gradually deploy a network of anti-malarial institutions, which, along with scientific work, mainly conduct practical work on the fight against Malaria; such are the malaria stations (in Transcaucasia, 'tropical stations'). They were opened gradually: in 1921, 7 were opened; in 1922, there were already 24; in 1923, 71; at the present time, more than 200 (see art. 613-614). The stations are the basic cells for the fight against Malaria. Each of them includes an outpatient clinic, a laboratory, and a museum-exhibition for sanitary-educational work. Some of them have inpatient facilities for clinical observation of patients; other stations use general hospitals for this purpose. The stations collect epidemiological material on Malaria, compile maps of the distribution of Malaria and Anopheles, and direct preventive work for the fight against Malaria in the area of their location. The work of the stations is coordinated by the tropical institutes. A supplement to the stations are malaria posts and detachments working under the guidance of the stations. They are either permanent or seasonal (for the spring-summer period), and in recent times they are being widely deployed in malarial areas, in particular in state farms and collective farms. An excerpt from the 'Regulations on Tropical Stations' of Armenia can give an idea of the nature of the activities of malaria stations. 1) In the field of scientific research, these stations study: a) the etiology, epidemiology, and clinical picture of tropical diseases; b) the distribution of tropical diseases in a given area through mass surveys of the population with the establishment of corresponding indices; c) the flora and fauna, hydrology, and meteorology of a given area; d) the peculiarities of the labor and life of the population and their role in the spread of tropical diseases, etc. 2) In the field of prevention: a) they conduct a campaign to destroy hibernating mosquitoes; b) they carry out petrolization and dusting of swamps and other water bodies dangerous in relation to Malaria, as well as other methods of destroying mosquito larvae (breeding Gambusia, etc.); c) they stimulate the self-activity of the population for carrying out hydrotechnical measures (draining swamps, repairing canals, etc.); d) they supervise proper water use with the aim of preventing damage to the irrigation network; e) they conduct preventive quinization of individual settlements and individual social groups of the population. 3) In the organizational field: a) they direct the work of sanitary sections, health units, etc.; b) they conduct and organize planned sanitary-educational work among the broad masses of the population; c) they prepare cadres of workers for the fight against Malaria on the spot. 4) In the therapeutic field: they provide free medical assistance—outpatient and inpatient—to all who apply to the station, and also actively involve chronic patients, carriers, etc., in treatment. A 'Tropical Station' has in its composition an outpatient clinic, a laboratory, a pharmacy, a museum-exhibition, and an inpatient ward. For the summer months, these stations organize a network of malaria posts located at a distance of 3-10 km from the station in the centers of individual groups of malarial villages. Similar 'Regulations on Malaria Stations' exist in other union republics. The corresponding 'Regulations' were approved by the People's Commissariat of Health of the RSFSR on May 14, 1923, and June 4, 1929 (published in the official section of 'Health Issues,' 1929, No. 7). Malaria stations serve the population using the dispensary method: in the area of the station's activity, through a universal repeated examination of the entire population or its individual most vulnerable groups (children, workers), all Malaria patients are identified, who are registered and subjected to systematic treatment. Figure 30 gives an idea of such work, which was carried out by the malaria station of the Krasyukovskaya settlement in the North Caucasus in 1924. The entire population of both this settlement and a number of adjacent villages was universally examined for Malaria. As a result, plans of all examined settlements were drawn up with an indication of Malaria patients in each hut. The persistent implementation of this system yielded very favorable results in terms of a significant reduction in Malaria. (The figure shows a section of the Krasyukovskaya settlement with an indication of the number of patients in individual [houses]).
Malaria stations keep a systematic record of the state of water bodies, both permanent and temporary (drying up), and plot them on appropriate maps, indicating their distance from the nearest housing, designating places where mosquito larvae were found and their quantity, places where oiling was carried out, etc. (Figure 31). The flora of the water body is also indicated. The Tropical Institute (Moscow) has proposed a special form for designating the species of mosquitoes found during the examination of water bodies and the nature of the vegetation (Fig. 32). Small hydrotechnical works are carried out directly by malaria stations or under their guidance. Large-scale land reclamation and hydrotechnical works of an anti-malarial nature are by law entrusted to the bodies of the People's Commissariat of Agriculture, which coordinate them with health authorities, in particular with malaria stations. To unify the work of individual departments in the field of the fight against malaria during the malaria pandemic, a central malaria commission was organized in Moscow (in Transcaucasia—a malaria committee), and on the periphery—regional and provincial malaria commissions ("Regulations" on them were approved by the People's Commissariat of Health of the RSFSR on May 14, 1923). They still function today in malarial regions. To account for scientific achievements and practical results in the fight against malaria, congresses on the fight against malaria are periodically convened: all-Union (in 1923, 1924, and 1925) and regional [in the Volga region (in 1924, 1925, 1926, and 1928), in the North Caucasus, in Transcaucasia, in Central Asia], as well as on specific issues, for example, on the fight against malaria in peat extraction areas (in 1926 and 1928); the materials of these congresses are published in the corresponding "Proceedings" of the congresses. Among the government decrees on the fight against malaria, the following decrees of the Council of People's Commissars of the RSFSR should be mentioned here: 1) dated September 13, 1923, according to which all plans for hydrotechnical works developed by various departments are subject to coordination with health authorities; the People's Commissariat of Health is granted the right to supervise the execution of these works from the point of view of compliance with sanitary requirements; 2) dated May 12, 1924, "On measures to combat malaria," according to which the duty of carrying out sanitary and sanitary-technical measures for the prevention and control of malaria is assigned to executive committees and individual departments (People's Commissariat of Railways, Supreme Council of the National Economy, etc.), and the duty to organize in schools and through schools the widespread dissemination among the population of information on issues of the fight against malaria is assigned to the People's Commissariat of Education; 3) dated December 6, 1923, on the duty-free import of quinine (quinine in the USSR is delivered exclusively from abroad). The People's Commissariat of Health of the RSFSR has issued a number of instructions on the fight against malaria (the most important of them are collected in the "Collection of decrees, instructions, and orders on issues of the fight against malaria," Moscow, 1925). The decree of the Council of People's Commissars of the RSFSR dated August 19, 1930 ("On the fight against epidemics") proposes: 1) the People's Commissariat of Health and the State Planning Committee of the RSFSR, when revising the five-year health plan, to provide for measures ensuring the maximum reduction in malaria incidence in the shortest possible time; 2) the North Caucasian, Lower Volga, and Middle Volga regional executive committees and the Council of People's Commissars of the Dagestan ASSR to develop a plan for hydrotechnical works related to the elimination of malaria foci; 3) the People's Commissariat of Health and executive committees to attract the initiative of the population in the order of carrying out the sanitary minimum to the implementation of a number of works to combat malaria, such as: oiling, dusting of water bodies, filling in swamps, etc.; 4) the People's Commissariat of Health to increase the network of malaria institutions (malaria stations, points, and detachments) in areas unfavorable for malaria.
Legislation and the fight against malaria in peat extraction areas stand apart. The high prevalence of malaria in peat extraction areas (see above) raised the question of implementing a special system for fighting malaria there; in general terms, it boils down to the following: a network of malaria stations has been organized in the peat extraction areas, the tasks of which include the inspection of all workers arriving at the extraction sites, the identification, registration, and treatment of all patients and parasite carriers, and supervision of the implementation of preventive measures (screening of windows in dwellings, oiling, and other methods of neutralizing water bodies, etc.). In the places of permanent residence of seasonal workers arriving at the peat extraction areas, a network of anti-malarial institutions (stations and points) has also been organized, which are entrusted with the duty of systematic treatment of the local population for malaria. The work of both stations takes place in a coordinated manner. This system of work resulted in a significant reduction in malaria in peat extraction areas. The entire anti-malarial organization in peat extraction areas is maintained at the expense of special credits provided for in the estimates of economic bodies in accordance with the Decree of the Central Executive Committee and the Council of People's Commissars of the USSR dated March 26, 1926 (0.06 kopecks for each pood of peat production). Regarding individual water bodies, the following information is required: shape, dimensions, depth measurements (zones with a depth of up to 1/2 meter, up to 1 m, up to 2 m, and above 2 m), character of the bottom, zone usually covered by plants, flow, water regime, water consumption, and evaporation.
Sanitary education plays a large role in the fight against malaria. For these purposes, special films, slides, posters, and brochures on malaria have been released, and corresponding exhibitions have been organized (including exhibition train cars). Special attention is paid to involving schoolchildren and students in the fight against malaria. In malarial areas, malaria is a subject of instruction in schools; schoolchildren study the biology of the mosquito and methods of combating it (oiling of water bodies, fighting hibernation, etc.). Special legislation on the fight against malaria has been issued in those union republics where malaria is particularly widespread (Transcaucasian and Central Asian republics). The decree of the Council of People's Commissars of the SSR of Armenia dated May 21, 1923, concerns rice plantations and artificial irrigation. Rice can be sown 1) at a distance of at least 5 km from the inhabited outskirts of the city of Erivan; 2) in other regions of Armenia—at a distance of at least 3 km from cities, villages, railway stations, and other settlements; 3) no closer than 2 km from main roads and 4) no closer than 1 km from country roads and railway tracks. As for artificial irrigation, the law provides for the proper maintenance of existing canals and ditches and the proper construction of newly built ones, with the slope of all canals being calculated so that the flow velocity per second is at least 25 cm. The decree of the Council of People's Commissars of the SSR of Armenia dated September 9, 1925, provides in particular for 1) the implementation by district executive committees of necessary measures for the improvement of the soil and the drainage of swamps, lakes, and other stagnant waters; 2) the submission for the conclusion of the People's Commissariat of Health, for the purpose of preventing waterlogging, of projects for newly built and subject to capital repair railways, highways, and other roads, irrigation ditches, and canals; 3) the dissemination among broad strata of the population and in schools of information on the fight against malaria. A similar law exists in Azerbaijan (dated July 8, 1925). In particular, this law provides for 1) maintaining water flow in places of artificial irrigation during cotton cultivation in order to prevent waterlogging of the soil; 2) the implementation by the People's Commissariat of Railways of hydrotechnical works on soil drainage in places where the railway track causes an obstruction of the natural flow of water; 3) the implementation by economic bodies in the areas of enterprises of works on the drainage of waterlogged areas, the maintenance of malaria stations in these areas; 4) the implementation of screening of residential houses; 5) the production of systematic oiling of waterlogged places in the areas of settlements; 6) the conduct of preventive quinine treatment among workers and employees in malarial areas; 7) coordination with the People's Commissariat of Health of plans and projects for new settlements and new buildings for workers' housing; 8) the inclusion in the retraining program for all social education workers of the study of malaria; 9) the introduction in schools of the I and II stages of the study of malaria according to a special program. The decree of the Council of People's Commissars of Uzbekistan dated May 26, 1928, provides for the prohibition of rice sowing within the residential part of cities and urban-type settlements, as well as a three-kilometer strip from it, and more complete provision of medical assistance in those kishlak regions where rice sowing is carried out. A similar law was also issued in the Tajik Republic (dated February 26, 1927).
I. Dobritser. XIV. Malaria in birds and animals. Malaria in birds and animals is of exceptional interest due to the work of Ross (1898), who elucidated the complete cycle of the parasite's development in the mosquito and proved that the infection of birds occurs from the penetration of sporozoites from the mosquito's salivary glands into the bird's blood during a bite, which subsequently served as the key to deciphering the epidemiology of human malaria. Pigmented parasites of avian erythrocytes were first discovered by V. Y. Danilevsky (Kharkov; 1888), who established in 1890 that they cause an acute disease in birds. Grassi and Feletti (1890) first defined the pigmented parasites of birds as true malaria parasites and named them Haemamoeba praecox, assigning them to the genus Haemamoeba, to which they also assigned the parasite of human malaria. Labbé (1894) assigned the parasite of avian malaria to the genus Proteosoma, and Wenyon (1926) believes that the pigmented parasite of avian malaria should be assigned to the same genus as the parasites of human malaria, i.e., to the genus Plasmodium, and called Plasmodium praecox. Pl. praecox is often found in birds in tropical and subtropical countries; it has also been discovered in more temperate countries: England, France, Germany, Austria, Italy, Switzerland, the USSR, North America, Africa, Japan, India, and Australia. It is more often found in small birds: sparrows, canaries, larks, siskins [see separate table (cols. 583-584), fig. 4], small birds, etc.; but it is also found in larger ones—pigeons, crows, owls, partridges, ducks, and others, for the malaria parasites of which separate names have been proposed. Malaria parasites in individual birds are currently still insufficiently studied. Pl. praecox (Grassi and Feletti) is morphologically very similar to the parasite of human malaria, from which it differs, besides the fact that it is non-pathogenic to humans, also by its larger size, just as the nucleated erythrocyte of birds is larger in size than a human erythrocyte. Asexual development (schizogony) of this parasite occurs in the erythrocytes of birds, and the sexual cycle occurs in mosquitoes of the genus Culex, from the bites of which natural infection of birds occurs, which usually proceeds mildly, whereas laboratory infection by inoculation of blood containing parasites proceeds more severely and is often fatal, especially for canaries, siskins, etc. On autopsy in such cases, hypertrophy of the liver and spleen is noted, which become darker, with the pigment distributed in the same way as in human malaria. The cycle of development of the avian malaria parasite in the Culex mosquito depends on the external temperature, just as it does in the Anopheles mosquito in human malaria. Et. and Ed. Sergent (1910-1921) studied avian malaria from the point of view of immunity. They found that the injection of sporozoites that had been in the salivary glands of Culex pipiens for several months, or sporozoites that had been preserved for a long time in vitro, reduces mortality among birds. Recently, avian malaria has again attracted attention due to work in search of synthetic preparations capable of replacing quinine. Among such works, one should note the work of W. Roehl with Plasmochin, which, after testing on canaries, was introduced for the treatment of human malaria. As for malaria in small mammals, one should point out the plasmodia of bats, which were first discovered by Dionisi (1899) in Vespertilio murinus. In the USSR, they are also found in Vespertilio Daubentoni [see separate table (cols. 583-584), fig. 6] (Shingareva A. I.; 1926) and others. Malaria parasites in monkeys were first discovered by R. Koch in 1898. At present, findings of malaria parasites are known in a number of lower monkeys—guenons, macaques, and also in anthropoid apes [see separate table (cols. 583-584), fig. 5]—the orangutan (Laveran; 1905), the chimpanzee (Reichenow; 1917), with Plasmodium pitheci being inoculable to orangutans but not inoculable to other lower monkeys; Pl. inui is inoculable to macaques but not inoculable to orangutans. It is not possible to infect monkeys with the human malaria parasite Pl. vivax; it has also not been possible to infect humans with the malaria parasites of monkeys—Pl. kochi and Pl. reichenowi. Malaria in monkeys proceeds in acute and chronic forms, i.e., the same as in humans. P. Popov.
Related articles
Mentioned in
Cite this page
“Malaria.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/malaria/