Leishmaniases
Historical document, translated for reference. It reflects medical knowledge of the 1920s–30s and is not medical advice.
Summary
This article from the first edition of the Great Medical Encyclopedia (1928–1936) covers the leishmaniases, including cutaneous leishmaniasis, American forest leishmaniasis, kala-azar, and canine leishmaniasis. It details the history of discovery of the causative agents, etiology, and morphological characteristics of Leishmania.
Encyclopedia article (1928–1936)
LEISHMANIASIS. Contents: Cutaneous leishmaniasis.................574 American forest leishmaniasis.......588 Kala-azar.....................588 Canine leishmaniasis................604 Leishmaniasis is a disease of hot countries that affects humans and certain domestic animals. The disease is caused by a specific parasite and proceeds either in the form of skin lesions or as a febrile disease affecting internal organs, and only in exceptional cases is a combination of these two forms observed. Cutaneous leishmaniasis is a disease characteristic exclusively of a hot climate; it has the appearance of a pimple that subsequently turns into an ulcer. Etiology. The question of the causative agent of oriental sore received its final resolution relatively recently. The first attempts to find the causative agent of the disease date back to 1868, when Smith described worm eggs of Distoma in the discharge of ulcers; apparently, he mistook hyaline clumps for eggs, which are frequently encountered in cutaneous leishmaniasis. Cunningham described specific formations on frozen sections from an ulcer, which he considered to be parasites (family Monadina). Firth confirmed Cunningham's observations and gave these parasites the name Sporozoa furunculosa. Undoubtedly, both of these authors mistook tissue cells, in the protoplasm of which actual parasites (Leishmania) were located, for parasites. Subsequent research followed the path of searching for the causative agent among bacteria, and the most diverse bacteria were described: micrococci, streptococci, fungi of the species Streptothrix, capsular micrococci, which apparently represented, judging by their size, not bacteria, but leishmanias. Borovsky (1898) in 20 cases of cutaneous leishmaniasis discovered special bodies, ranging in size from 0.5 to 2-3 µ, in sections as well as in smears of ulcers. Studies of the juice from papules and ulcers in a hanging drop showed the presence of a multitude of motile bodies. In smears, they had a thin process, the size of the diameter of the body itself, often with a spherical thickening at the end. Sometimes there were 2 or 3 such processes. In these formations, a nucleus could be found lying in the center or on the periphery of the body. Undoubtedly, he was dealing with the true causative agent of the disease - Leishmania tropica. Shulgin (1902) on a small material (3 patients) confirmed Borovsky's observation. Martsinovsky jointly with Bogrov (1903) in one case of Persian sore discovered special parasites, which were described under the name Ovoplasma orientale. Simultaneously with this work, the work of Wright was published, who also in 1 case discovered the same parasites and described them under the name Helcosoma tropicum. These studies finally established that the causative agent of oriental sore is a parasite belonging to Protozoa and now known under the name Leishmania tropica (in honor of Leishman, who first described a similar parasite in kala-azar). Wenyon (1926) establishes the following place for this parasite among protozoa: type Plasmodroma, order Protomonadidae, family Trypanosomidae, genus Leishmania. Parasites are found in large quantities in smears from the granulations lining the bottom of the ulcer. In the juice from ulcers in a hanging drop, individual bodies show weak amoeboid movements. The bodies are round, oval, or rice-seed-shaped and have a size of from 2 to 4 µ. When stained with Giemsa in their protoplasm, which stains a pale blue color, there is located... Figure 1. Lipofuscin in nerve cells of the sympathetic ganglion. Figure 2. Spleen in kala-azar: 1-atrophy of the follicle; 2-thickened trabecula; 3-pulp, poor in cells; reticuloendothelial cells packed with leishmanias are visible; 4-erythrocytes. Figure 3. Bone marrow smear in leishmaniasis: 1-large reticuloendothelial cell packed with leishmanias (2); 3-erythroblast; 4-erythrocyte (other bone marrow elements are not depicted). Figure 4. Liver in leishmaniasis: 1-expanded intertrabecular spaces in which hypertrophied Kupffer cells packed with a mass of leishmanias are visible; 2-hepatic trabeculae; 3-endothelium. Figure 5. Splenic pulp: 1-sharp depletion of the pulp in cells; swelling of the reticuloendothelial stroma; leishmanias in reticuloendothelial cells; 2-sinuses with free cells of the reticuloendothelium. Figure 6. Splenic pulp: 1-atrophy of the pulp; almost exclusively reticuloendothelial cells (pale) are visible; 2-expanded sinuses in which swelling of the endothelium, free macrophages, and erythrocytes are observed. Figure 7. Leishmanias in culture. Figure 8. Smear from ulcer granulations in leishmaniasis. (To the illustr. of the art. Leishmaniases, Lipofuscin.) 9 ->.
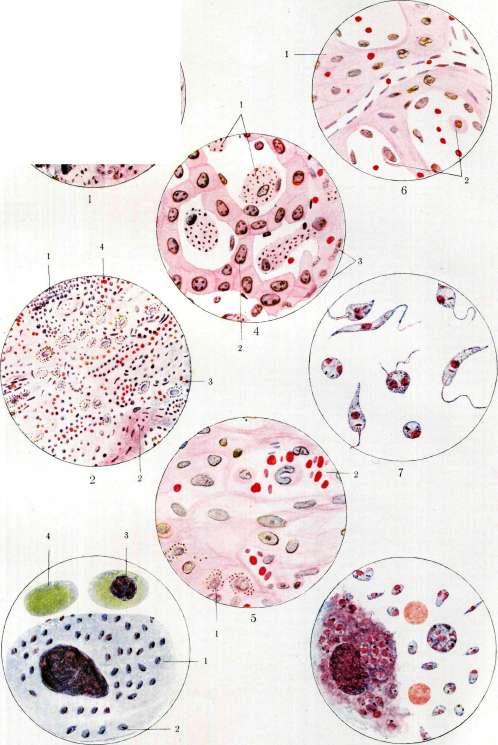
To the article Leishmaniasis, Lipofuscin. GOZNAK. a large round or slightly oval nucleus, opposite to which lies a smaller accumulation of chromatin, known by the name of blepharoplast or kinetonucleus. From the blepharoplast towards the nucleus stretches a short thread, the rhizoplast. The blepharoplast is of round or rod-like shape. The protoplasm of dead parasites stains a uniform reddish color. Leishmania tropica belongs to the group of intracellular parasites. On stained preparations from the granulations of the ulcer (see separate plate, figure 8), even at low magnification, it is possible to notice round mononuclear cells whose protoplasm is stuffed with small granules staining in the color of the nucleus. At high magnification, the aforementioned granules represent chromatin masses of leishmania. Up to 70 parasites and more are found in a cell. Individual giant cells are encountered in which they are sometimes numbered by the hundreds. Occasionally these parasites are also found in polynuclear leukocytes; this made it possible to draw a conclusion about the possibility of their entering the bloodstream, which was subsequently confirmed. Falling into the intercellular space upon cell destruction, the parasites begin to multiply by direct division and are captured by new cells. During reproduction, the nucleus moves to the wider end of the parasite, and the blepharoplast is located at the narrower one. It takes the form of a rod standing perpendicular to the long axis of the parasite, and begins to divide in half. The body of the parasite increases somewhat in volume. A little later, the nucleus also divides into 2 parts, and finally the entire parasite breaks up into 2 new individuals. Sometimes division is multiple. In individual cases, formations known by the name of gangue are found on preparations, which represent the process of multiple division or, more likely, parasites tightly squeezed into one heap. In sections from a young ulcer, enormous quantities of parasites enclosed in cells are sometimes encountered, with which the entire field of view is speckled; they lie in special mononuclear epithelioid cells, and sometimes in giant cells. Parasite culture. Nicolle (first obtained a culture of leishmania on blood agar (NNN) (agar 14.0, sodium chloride 6.0, and distilled water 900.0. To 10 cm3 of agar in a test tube, 1 cm3 of rabbit blood is added; seeding is done into the condensation water, which must be colored with Hb). Reproduction of parasites is observed as early as the 2nd-3rd day. Upon the first appearance of parasites in the culture, it is possible to note 2 types of them: some have pale-stained protoplasm and a large loose nucleus, others stain an intense blue color, with a nucleus of comparatively smaller size. When parasites transform into flagellate forms, the difference in staining disappears. In cultures, parasites have an elongated body, in the middle of which lies a round or oval nucleus, and at the front, narrower end—the blepharoplast, from which a long flagellum departs (see separate plate, figure 7). Parasites in culture possess lively movement. In old cultures, small blackish grains of velutin can be noted in the protoplasm of the parasites. Cultures withstand many generations. By inoculating parasites from an ulcer, as well as from a culture, it was possible to obtain the disease in certain animals, namely, in monkeys Macacus rhesus and others, dogs, mice, and guinea pigs. The question of the routes of infection of cutaneous leishmaniasis cannot yet be considered finally resolved. It must be considered most probable that blood-sucking insects play a role in the spread of the disease. The very name of the disease in some localities is associated with the bite of insects: pasha-khurda in Turkmenia (means mosquito bite), cuncir in Africa (comes from the word cunci—flea), and the like. Many of the blood-sucking insects with greater or lesser grounds were indeed suspected of transmitting the disease both on the basis of experiments and on the basis of epidemiological data. Patton and others found the appearance of flagellate forms of the leishmania parasite in bugs which they infected with the help of L. tropica and L. Donovani; Adie found flagellate forms of the parasite in the salivary glands of infected bugs. Chatton and Blanc discovered flagellate forms of leishmania in bugs that fed on gecko lizards. All these experimental data, however, do not give the right to assume that bugs play a role in the epidemiology of cutaneous leishmaniasis, since these insects are extremely widespread, while the foci of cutaneous leishmaniasis are rather sharply limited. Experiments with fleas (Wenyon) and with lice (Patton) also gave negative results. Many observations were also made in relation to mosquitoes. Thus, Wenyon described the development of flagellate forms of leishmania in infected mosquitoes of the genus Aedes aegypti; but the results of the experiments were negative. Similar observations existed in relation to blood-sucking flies; in particular, Gachet experimented with flies Hippobosca canina, and he describes the appearance of leishmaniotic pimples in two people at the site of the bite by these flies. Finally, phlebotomine mosquitoes Phlebotomus were suspected in the transmission of infection, in which flagellate forms of parasites of the Herpetomonas type were repeatedly discovered in the digestive tract by many authors. Thus, Acton in Mesopotamia found 6% of infected Phlebotomus; Patton in India—10%. Mackie discovered them in the same place in Phlebotomus minutus, and Laveran and Franchini—in Phlebotomus papatasi (France). The latter authors, with the help of parasite cultures obtained from these insects, caused a general infection in mice and guinea pigs, and in dogs—skin lesions resembling ordinary leishmaniasis. Experiments with Phlebotomus minutus (bites and injections of emulsion) on man, monkey, and mice gave negative results for Sergent, Lemaire, and Senevet. In Africa, the following observations were made (Sergent, Parrot, Donatien, Beguet): 94 Phlebotomus papatasi were caught in military hospitals, and 3-4 days later they were sent 600 km to Algeria, to an area where leishmaniasis does not occur; 71 Phlebotomus arrived alive; no parasites were found in the emulsion from them, but upon rubbing this emulsion onto the scarified skin of the forearm of an Algerian, a papule with a large number of L. tropica parasites appeared at this place after 84 days. Thus, the possibility of transmitting this disease through phlebotomine mosquitoes seemed to be proven, but this by no means resolves all questions of epidemiology. Usually, Phlebotomus are always found in the foci of cutaneous leishmaniasis; nevertheless, it can be thought that along with them there may be some other transmitters of the disease. Reservoirs of the virus. In places of endemic distribution of cutaneous leishmaniasis, the disease of dogs is very often encountered (see below—leishmaniasis of dogs), in which the disease proceeds either in the form of general leishmaniasis or in the form of skin lesions. Cutaneous leishmaniasis is comparatively less common in cats. Cutaneous leishmaniasis in camels has also been described by Nicolle. Sergent and Nicolle discovered leishmanias in geckos (Tarentola mauritanica) in 15.7%; it is difficult to say whether the parasites of the mentioned animals are identical with human parasites, but morphologically they are extremely similar. Laveran infected geckos with the parasite L. tropica; Chatton and Blanc also obtained a positive result in 3 experiments with geckos. In favor of the role of the gecko as a reservoir of the virus, one can cite the observations of Parrot, who fed 8 Phlebotomus on 6 specimens of geckos. The Phlebotomus flew out, and 3 months later 3 people fell ill with cutaneous leishmaniasis in this house. Nicolle, Blanc, and Laveran injected the blood of a gecko with a natural infection into 2 humans and monkeys, as well as the culture into 3 humans and a monkey. In all cases, the result was negative. Thus, there are no sufficient grounds to assert that geckos are a reservoir of the virus for man. Diseases of camels with leishmaniasis are rarely observed, cats fall ill just as rarely. Only dogs remain, in which the course of ulcers closely resembles similar ulcers in humans, and Phlebotomus can often be found on ulcers in dogs. Using a culture obtained from dogs in Baghdad, Adler and Theodor (1930) infected a man, and papules formed in the skin at the site of the injection, in sections of which parasites were found. The authors believe that L. tropica is a common parasite for dogs and humans. Nicolle and Manceaux obtained infection of man and monkey by inoculating them with granulations from dog ulcers. Thus, it can be assumed that the virus in leishmaniasis can also survive outside the human body. However, there are yet no sufficient data to assert that the disease can be transmitted from dogs to man; thus, in Central Asia in many foci of this disease, such as in Ashkhabad, in Merv, it was not possible to encounter dogs with cutaneous manifestation of leishmaniasis (Marcinowsky), a very small number of them were also discovered with internal leishmaniasis during autopsies. These same cities are major foci of cutaneous leishmaniasis, although the reverse should also be noted; thus, Bukhara in recent years has been a major focus of cutaneous leishmaniasis, and similar diseases of dogs are also observed there quite often. Brumpt points out that in Biskra and Gafsa there are no dogs sick with cutaneous leishmaniasis. It can be assumed that Phlebotomus become infected from dogs sick with general leishmaniasis, and by their bites inoculate the cutaneous form of it to man.
In any case, the question of the virus reservoir in cutaneous leishmaniasis cannot yet be considered definitively resolved. The geographical distribution of cutaneous leishmaniasis covers extremely vast areas between 15° West and 20° East longitude and from 23° to 45° North latitude (Arendt). The disease is very widespread in North Africa from Algeria to Morocco in numerous oases of the Algerian (Biskra) and Tunisian (Gafsa) Sahara, in the French Congo, in Sudan, and along the African coast of the Red Sea. It is found in Asia Minor, Syria, Mesopotamia, Arabia, Persia, Afghanistan, India, China, Central Asia, in the valleys of the Murghab, Tedzhen, and Atrek (Termez, Kerki, Tashkent, Kokand, Merv, Ashkhabad, Bukhara, and others), in the Transcaucasian republics of the USSR [in Azerbaijan (Baku, Lenkoran, Ganja), in Georgia (Gori)], on the islands of Crete and Cyprus, in southern Italy, Sardinia, and Sicily, in Brazil, Uruguay, Colombia, Bolivia, and French Guiana, in the Philippine Islands, on the island of Ceylon, and in Australia. In connection with such a vast distribution, cutaneous leishmaniasis has an extremely large number of names, which partly characterize its essence. The most widespread of them are: Aleppo button (bouton d'Alep), Biskra button (bouton de Biscra), Tunisian button, Nile button, Delhi button, Sahara chancre, bessep-temur of the Arabs, Yemen ulcer, Pendjeh ulcer, oriental sore (bouton d'Orient, furunculus orientalis), ilchoban of the Turkmen (annual ulcer), il-yarasy of the Turks (annual ulcer), solek of the Persians (annual ulcer), godyvik in the Caucasus, Baghdad boil, Delhi boil, granuloma endemicum, Kandahar sore, Pendjeh sore, l. dermalis, s. cutanea, and finally leishmaniosis americana, l. oro-pharyngealis as a special form of cutaneous leishmaniasis. Throughout the vast expanse where the distribution of oriental sore has been noted, it occurs in the form of separate foci, sometimes extremely sharply limited; for example, a fairly large focus of this disease until recently existed in Ganja (formerly Elizavetpol), while three versts away from the city, in a large railway settlement connected to the city by a horse tram and a continuous row of buildings, it was completely absent. New foci of cutaneous leishmaniasis may arise, and old ones sometimes die out temporarily and even forever. Thus, for example, Lebert mentions cutaneous leishmaniasis in the Crimea (Eupatoria), whereas leishmaniasis has long since disappeared there. Another example is Kokand, which was previously known as a large focus of cutaneous leishmaniasis (kokandka), and now yields a very insignificant number of cases. Bukhara at one time was also considered a large focus of this disease, then the number of cases began to drop sharply; in recent years, cutaneous leishmaniasis has again intensified and become widespread. Lenkoran and Ganja, where leishmaniasis is currently almost completely absent, should be classified among the dying-out foci of cutaneous leishmaniasis. Among the newly emerged foci in recent times, Baku and Gori should be pointed out. Frequently, the disease goes beyond the limits of its endemic distribution and produces outbreaks of large epidemics. Usually, this has to be linked either with sharp changes in climatic conditions or with any natural disasters, such as famine or war. As an example, one can cite the epidemic among the British garrison in Delhi. Beginning in 1857, from the moment of the arrival of troops there, from 50% to 70% of patients with cutaneous leishmaniasis were noted among the soldiers, sometimes in a very severe form, and only in 1873, with the adoption of a number of sanitary measures, these diseases sharply decreased. During the campaign of the Russian troops on Kushka (1885) in the so-called Murghab detachment, the Pendjeh ulcer spread strongly, which significantly hindered military operations. Out of the entire detachment of 1,800 people, more than 50% fell ill (Manotskov). In 1921, from Red Army units stationed in Serakhs, 150 people sick with severe forms of cutaneous leishmaniasis were evacuated within one month. In 1922, in the same place, one company of 250 people gave about 60% morbidity (Krasnovsky). In 1929, in connection with the mass appearance of locusts in Turkmenistan, so-called "locust regiments" were organized, which suffered greatly from the development of pendinka among them. Race apparently has no significance in terms of infection with cutaneous leishmaniasis, and if there are contradictory indications in the literature that Europeans who fall into a focus of leishmaniasis fall ill more often than the local population, this is explained by insufficiently precise observations. Sex likewise plays no role in predisposition, although in some localities a higher incidence is noted among men, but this is explained by the greater mobility of the male population. All age groups of the population are susceptible to the disease to an equal degree. In endemic foci, children fall ill at a relatively early age, which is why the impression is created as if cutaneous leishmaniasis is predominantly a disease of childhood. Ulcers are rarely encountered before the age of one. This disease is not transmitted by inheritance. Social and living conditions undoubtedly influence the spread of the disease; however, it is not yet possible to accurately account for all factors in this area. Nevertheless, it should be noted that the improvement of the general sanitary situation certainly influences the decrease in morbidity. Immunity to cutaneous leishmaniasis is created quite solidly, which with mass illness of the population can subsequently lead to the liquidation of the endemic focus of this disease. There are indications that the Tekke Turkmens who settled in the valley of the Lende River initially suffered greatly from cutaneous leishmaniasis, and then diseases among them ceased (Lyubimov). During the aforementioned campaign of Russian troops to Kushka, more than 50% fell ill, whereas among the Tekke Turkmens, cases of cutaneous leishmaniasis were not observed at all. Thus, immunity develops as a result of the disease suffered. Natural non-susceptibility to cutaneous leishmaniasis does not exist; similarly, despite isolated indications, hereditary transmission of immunity (Satinsky) cannot yet be considered proven. In the development of immunity, the number of ulcers, their size, and the duration of the course apparently have great significance. In abortive forms of cutaneous leishmaniasis, immunity does not have time to develop, and a new infection can occur the following season. Finally, if cutaneous leishmaniasis was observed in childhood, then after many years the immunity may disappear, which can lead to a new infection. Cases of reinfection have been described by many authors. Of great interest is the question of the relationship of cutaneous leishmaniasis to visceral leishmaniasis (kala-azar). Experiments on monkeys show that infection with the virus of kala-azar imparts a certain degree of immunity in relation to cutaneous leishmaniasis, although according to Nicolle's observations, it was possible in individual cases to inoculate cutaneous leishmaniasis into monkeys that had undergone infection with kala-azar. There are isolated observations of illness with cutaneous leishmaniasis in patients with kala-azar. Pathological anatomy. Cutaneous leishmaniasis in its structure belongs to the so-called infectious granulomas. The patho-anatomical picture varies depending on whether there is a pure lesion of leishmaniasis or one complicated by a secondary infection. In the initial stage, when there is a papule or tubercle, the following changes can be noted in the skin: the epithelial layer is swollen, slightly edematous; multinucleated leukocytes are visible here and there in the intercellular spaces; in the corium there is an inflammatory infiltrate consisting of round and epithelioid cells located predominantly around the blood vessels. Giant cells with nuclei located at the periphery, as well as hyaline lumps of various sizes, are also encountered among the infiltrate. The number of mast cells is noticeably increased, the vascular endothelium is swollen and in places completely closes the lumen of the blood vessels themselves. Subsequently, the inflammatory infiltration in the center of the nodule reaches such sizes that the pattern of normal skin completely disappears. In places, small extravasates and small foci of tissue necrosis are encountered among the infiltrate, which, merging with each other, give rise to an ulcer. The amount of fibrin in the affected tissue is increased (Unna); the sweat and sebaceous glands are obliterated; in this case, keratinization of the root sheath occurs (Kunn), due to which hair growth at the site of the lesion ceases and scars after ulcers are devoid of hair. Some of the sebaceous glands during the scarring of the ulcer turn into small cysts, which are usually located at the periphery of the ulcer in the form of milium-like translucent formations. Sudakevich discovered sharp changes on the part of the elastic tissue in the ulcer: it is in a state of complete disintegration, and fragments of elastic fibers are also encountered in giant cells. Upon healing of the ulcer, the infiltration can be seen permeated from the periphery by connective tissue carrying small blood vessels. In the center of the nodule, a large number of giant cells can sometimes be found. At certain moments in the development of the ulcer, it is very easy to confuse it with skin tuberculosis. Parasites (leishmaniae) begin to disappear from the center and hold out relatively longer at the periphery. The healing of the ulcer by scarring proceeds in the same way as the scarring of any other ulcer.
During the very development of the ulcer, Laveran notes several stages: 1) formation of the infiltrate focus at the site of the penetrated infection; 2) irritating effect of this infiltrate on the epidermis and the papillary layer; 3) appearance of a large number of macrophages and connective tissue-type cells in the infiltrate; 4) disappearance of parasites in the center of the nodule, involvement of phagocytes in the process, and consequent secondary infiltration; 5) appearance of inflammatory infiltration in the necrosis foci with transition to suppuration, and 6) suppuration due to secondary infection by microorganisms. Experimental leishmaniasis. The first attempts to inoculate cutaneous leishmaniasis from a sick person to a healthy one were made by Russel in the middle of the 18th century, but without result. A large number of new attempts in this direction must also be recognized as unsuccessful, since in the vast majority of cases cutaneous lesions of an inflammatory nature appeared shortly after inoculation and quickly disappeared. As an example of such attempts, one can cite the experiment of Murray, who in Delhi inoculated dry crusts into 6 natives with a negative result and 24 with granulations, wherein in 23 cases an inflammatory skin irritation resulted at the inoculation site, terminating by the 10th day. Later in the same city, Nicolle and Nourry-Bey inoculated ulcers with undoubtedly positive results, with their incubation period lasting on average from one week to two months, and the resulting papules and nodules, which subsequently turned into an ulcer, persisted for about seven months. The most convincing experiment must be considered that of Marcinovsky, who in 1908 inoculated an ulcer onto himself from a child in whose ulcer leishmaniasis was found; after 70 days, a papula first appeared at the inoculation site, which then turned into a nodule, upon examination of which after 17 days leishmanias were found. Several days later this nodule was surgically removed. In 1921, Shurenkova inoculated herself with oriental sore, and Marcinovsky was secondarily infected from her. Since the first ulcer existed for about 3 weeks and was removed, immunity did not result, and an ulcer developed at the site of the new infection, which healed spontaneously after 41/2 months. Repeated inoculations after 8 months, a year, two years, and five years yielded a negative result, and finally the injection of a large amount of culture, administered after 5 years, caused only a slight skin swelling that subsequently disappeared without a trace. Clinical features of cutaneous leishmaniasis. In the description of the clinical picture of the disease by old authors, there are many contradictory data, which is quite understandable, since only the establishment of the true causative agent of the disease made it possible to sharply distinguish cutaneous leishmaniasis from other similar diseases. In former times, cutaneous leishmaniasis was often confused with various ulcerative processes in the skin and even with ordinary acne. The incubation period for cutaneous leishmaniasis lasts from 2 weeks to several months; on average it is approximately two months. Apparently, the length of the incubation period is influenced by the amount of virus that has entered the body, as well as the time of infection (infections in late autumn sometimes give rise to the disease in April, May). The prodromal period is usually absent, except in rare cases of mild itching at the site of the future ulcer; only in multiple ulcers do patients sometimes note slight malaise and an insignificant increase in temperature. Usually a small copper-red spot appears on the skin, turning into a papula, and then into a glossy nodule of the same color. There can be a large number of papules at once in various parts of the body, but often the development of papules does not proceed simultaneously, and some of them have already managed to turn into an ulcer, while others are just appearing. In mild cases, papules can undergo regressive development and disappear completely, without even leaving a scar behind; sometimes they turn into scaly plaques up to 4-5 cm in size, which can also disappear without a trace. More often, however, the nodule increases, tissue necrosis occurs at its apex due to lack of nutrition, and in this stage it represents a small elevation in the skin, covered with a brownish-red crust. Subsequently, the growth of the nodule continues, and at the same time tissue breakdown proceeds under the crust. If the crust is torn off, an ulcerated surface is visible beneath it, covered with pale insensitive granulations, which can be removed with tweezers without any pain for examination. The further course of the ulcer can follow two paths: if there is no secondary infection, the ulcer increases in surface area and depth, remaining covered with a blackish-brown tightly adhering crust, which comes off only in separate pieces ("dry" form); if infection by pyogenic microbes has occurred, the ulcer is covered with a yellowish-brown crust, upon pressing which a pus-like fluid exudes; the crust is usually easily removed, and an ulcerated surface covered with pus is discovered beneath it. The circumference of the ulcer similarly exhibits signs of inflammation ("wet" form). Fully developed ulcers reach the size of a silver coin or even the palm of the hand. Ulcers can sit isolated, or several closely lying ulcers merge into one. The period of blooming of the ulcer lasts from 3 to 6 months. Sometimes a nodule or even a small ulcer develops slowly and can exist in such a position for several years (2, 5, 7). On average, the duration of the disease takes about a year, which is reflected in local names—yil-yarasy (yil-year, yarasy-ulcer), salek (Persian for annual ulcer). The course and duration of the disease in various localities are not identical, which depends on climate and other factors. Thus, ulcers complicated by secondary infection heal faster, since in them leishmanias die sooner. With a large number of ulcers and with their phagedenic character, there are sometimes increases in temperature up to 39-40°. During the healing period of ulcers, the bottom of the latter becomes covered with juicy, red, and painful granulations, and the healing process itself proceeds in the same way as with any other ulcer. Scarring often proceeds from the center to the periphery, with the middle of the ulcer already representing a scar, on the periphery of which there are areas of the ulcerated surface covered with a crust. Scars are at first pigmented, and then, when the pigment is resorbed, they are whiter than the normal skin. Often, especially in children, the scars are so delicate that they are difficult to notice. In cases where the ulcers are located directly above the bone, where there is little subcutaneous adipose tissue, they can cause severe pain, but usually they are painless. When afflicted with other infectious diseases (typhus, influenza), ulcers can suddenly disappear; conversely, in depleted individuals, patients with syphilis, scurvy, etc., ulcers often take on a malignant phagedenic character. Depending on the localization of the pathological process, scarring of the ulcer sometimes causes retraction of the wings of the nose, distortion of the mouth, eversion of the eyelids, and destruction of skin mobility, interfering with the play of mimic and chewing muscles. In the circumference of the scarring ulcer, small miliary nodules are sometimes encountered; in rarer cases, upon healing of the ulcer in individual places along the periphery of the scar, small tuberculoid-type nodules appear, which gave reason to think of a combination of leishmaniasis with tuberculosis. However, microscopic examination of the nodules made it possible to establish their leishmanial nature. Mention should also be made of traumatic forms of leishmaniasis, when a leishmanial ulcer develops at the site of a bruise.
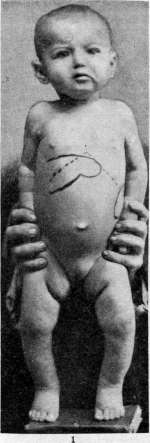
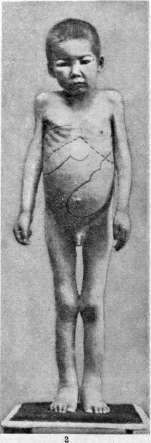
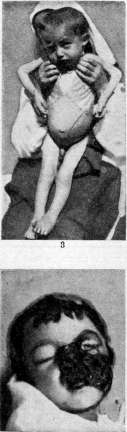
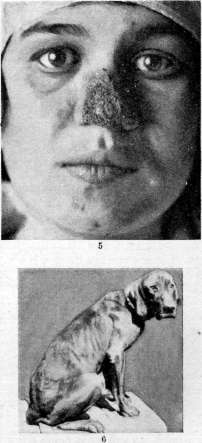
Figure 1. Kala-azar; case of a short, acute, severe course with a fatal outcome; exudative-hemorrhagic diathesis. Fig. 2. Kala-azar; severe case with marked edema of the face and extremities; ascites. Figure 3. Kala-azar; severe case with a prolonged course. Figure 4. Kala-azar; case complicated by noma. Figure 5. Cutaneous leishmaniasis of the face. Figure 6. Typical habitus of a dog suffering from visceral leishmaniasis (ulceration of the eyelid margin, dried pus crusts around the eyelids due to conjunctivitis, ulcers on the lips and wings of the nose).
case leishmanias may persist in the lymph glands, from where they enter the locus minoris resistentiae. Often near the ulcer it is possible to palpate thickened and painless lymphatic vessels in the form of a cord, and along the course of the latter, nodules ranging in size from a pea to a small cherry. In these nodules it was possible to detect leishmanias and obtain them from there in a pure culture. The classification of ulcers, most satisfactory, was proposed by Ledantec, but it is already obsolete and requires changes. It is more correct to distinguish the following forms of this disease: 1) abortive, when the entire process is limited to the formation of a papule or nodule, which subsequently resolves; 2) desquamative, when leishmaniasis also proceeds without ulceration, in the form of a scaly plaque; 3) the usual dry form of an ulcer covered with a crust; 4) a suppurating ulcer as a result of secondary infection; 5) phagedenic form; 6) impetiginous form with a short course (approx. 2-4 months), resembling an impetiginous rash (secondary infection with pus-producing microbes); 7) keloid rash, described by Balfour, when the entire process proceeds without ulceration, and the nodes consist mainly of dense connective tissue penetrated by foci of infiltrate; 8) papillomatous form; 9) leishmaniasis with predominant lesion of the mucous membranes (American leishmaniasis). Ulcers in a patient are rarely single; more often there are 3-5 of them, and sometimes their number reaches 200 and 300 and can cause temporary disability. Location of ulcers. As a rule, ulcers are located on the open parts of the body; but they can also appear on the closed parts of the body. On the face, their favorite place is the region of the zygomatic arch, the tip of the nose (see separate table, figure 5), the bridge of the nose, the chin, lips, forehead, eyebrow, the edge of the ear. On the extremities, ulcers usually affect the dorsal surfaces of the joints. Sometimes ulcers occur on the genitals in men and women, which usually gives rise to confusing them with syphilis. Complications. First of all, one has to reckon with the disfigurement that ulcers often cause. All other complications, such as phlegmons, erysipelas, gangrene, septicemia, etc., essentially represent complications of ulcers in general. Prior to the establishment of the true causative agent of the disease in the old literature, cases of involvement of muscles, cartilage (of the ear, nose), fascia, joints and bones by the ulcerative process, loss of teeth, arrest of nail growth, abscesses in the liver, etc., were described. However, since the finding of leishmania was taken as the basis for the diagnosis of Oriental sore, such complications have no longer been described by anyone, and undoubtedly they have nothing to do with leishmaniasis. Differential diagnosis. Cutaneous leishmaniasis is a granuloma, and it is often confused with similar processes in the skin, namely with lupus, syphilis, blastomycosis, yaws, erythema multiforme and finally with tropical ulcer. Cutaneous leishmaniasis differs from these diseases by the peculiar location of the ulcers, their course, and also by its connection with the endemic focus of leishmaniasis. In addition, the finding of leishmania should be the basis of diagnosis. It is more difficult to distinguish leishmaniasis from tropical ulcer; the latter proceeds more acutely, and spirochetes and Vincent's bacilli are found in the juice of the ulcers. Treatment. There is perhaps no other disease in which so many diverse methods of therapy are used. This is partly explained by the fact that if one begins treatment of an ulcer with any preparation during the period when it passes into the final phase of healing, the effect is brilliant; conversely, in the treatment of the initial forms of the ulcer, almost all medicinal preparations usually turn out to be ineffective. Cauterizing and tissue-destroying agents have always been of particularly wide use. Thus, ulcers are cauterized with a hot iron, a thermocautery, and in the stage of a papule and nodule this often yields positive results. Various ointments with Cuprum sulfuricum, Stibio-Kalium tartaricum (20%), etc. are used. The latter ointment is successfully applied to the ulcer, resulting in edema and inflammation, infected granulations are destroyed, and subsequently the ulcers begin to scar. Potassium hypermanganicum should also be attributed to this group of preparations, which is sprinkled in the form of a crushed powder onto the surface of the ulcer exposed from the crust. Cardamatis and Melissidis proposed using methylene blue in the form of an ointment 2-3 times a day, for 15-20 days. Such treatment can give relatively good results. Next should be mentioned the injection of 2% emetine around the ulcer and finally antimonial preparations (Stibenyl, Stibosan, Neostibosan, etc.), which are administered for 1-2 weeks, for 3 days in a row, with 5-7 day intervals and can be considered to a certain extent specific for this disease. Finally, recently X-rays, radium and ultraviolet rays have been used. The results from X-rays in the initial forms of the ulcer are insignificant, but in the flowering period, along with other therapy, it gives good results in terms of faster healing of ulcers. Regarding ultraviolet rays and radium, there is very little material, which does not allow for final conclusions. In the initial stages of leishmaniasis, removal of the affected area surgically gives good results. A change of climate has little effect on the course of the disease process. Prophylaxis of cutaneous leishmaniasis and measures to combat leishmaniasis. The increased communication between the peoples of the USSR in recent years leads to the fact that many tropical diseases, including leishmaniasis, become common even far beyond the limits of their endemic distribution. In connection with this, issues of prophylaxis acquire great importance. The transmission of cutaneous leishmaniasis through insect bites dictates appropriate preventive measures, namely: 1. In the foci of this disease, it is necessary to sleep under canopies, dense enough so that phlebotomes cannot penetrate through them. It is desirable that the canopy be white, blue or red, because phlebotomes are almost invisible on a gray, yellow or even pale orange background. 2. The walls should also be painted in the specified colors. 3. If you do not use a canopy, it is necessary to close the windows by inserting nets into them, and sleep in bright light, because phlebotomes are nocturnal insects and usually bite at night or in shaded rooms. 4. Since phlebotomes usually inhabit houses, in the south it is better to sleep outside the house—in the garden or on a flat roof, but mandatory under a canopy. In general, in order to break the epidemiological chain, it is necessary to block the access of phlebotomes to the patient or, rather, to his skin lesions as sources of infection; for this purpose, as a therapeutic method, one should apply dusting the ulcers with Kalii hypermanganici powder or keep them under a bandage. The fight directed against phlebotomes presents great difficulties, because the biology of these insects has not yet been sufficiently studied. Phlebotomes breed near human habitation, and although the exact places of their breeding have not yet been studied, nevertheless it can be argued that the life of these insects is associated with unsanitary conditions of the yard. Therefore, the basis of control measures against phlebotomes should be maintaining cleanliness in the yard, dusting outhouses with lime, timely removal of garbage, cleaning of ditches (aryks), etc., in general, careful toilet of the soil surface of the populated area. Since the improvement of sanitary conditions of each individual yard largely depends on the improvement of general sanitary conditions, serious attention should also be paid to this side (water supply, sewerage). 5. Since there are a number of indications that the reservoir of the virus is sick dogs and relatively rarely other animals, it is necessary to properly organize the fight against dog leishmaniasis. For this purpose, it is necessary to destroy sick dogs and issue appropriate mandatory regulations. 6. Prophylactic vaccination and vaccination with killed cultures. Marcinovsky, Shurenkova and others (see above) established that experimental Oriental sores, as long as they exist for at least 3-4 months and heal independently, provide a rather persistent immunity, and reinfections even after 5-7 years are unsuccessful. Thus, by inoculating granulations from a patient onto the forearm or leg of a healthy person, we obtain the development of an ulcer at the site of inoculation, which guarantees against a new infection through an insect. The practical inconvenience of this method is obvious, and recently various authors (Marcinovsky, Khodukin, Latyshev) have been making attempts to obtain vaccines from killed leishmania cultures. Such vaccines have been tested on a fairly large amount of material, and although final conclusions about their effect cannot yet be made, the impression is favorable. American forest leishmaniasis (syn.: leishmanioso americano, uta, buha, forest?, aws, espundia, leishmaniosis oro-pharyngealis). It is found in hot wooded areas, starting from Mexico and ending with the northern part of Argentina; it has existed in America for a long time, even before the arrival of Europeans there. In Peru on pottery dating back to the time of Inca rule, there are drawings depicting this type of leishmaniasis (uta). The disease is found mainly among workers engaged in gathering rubber and making mats in the virgin forests of America.
Migone notes that in certain forests of Paraguay the morbidity among workers reaches 70-80% during the first months of their stay. Symptomatology: after an incubation period of two to three months, the disease begins with the appearance of one or several erythematous papules, sometimes itchy and resembling insect bites. After a few days, a small accumulation of pus-like fluid forms at the apex of the papule, and then upon scratching, the fluid protruding from here hardens, forming a blackish crust. Subsequently, tissue breakdown occurs beneath the crust, sometimes with the formation of pus, which exudes upon pressing the crust, emitting an unpleasant odor. Very often, such ulcers are accompanied by lymphangitis and the appearance of nodules along the course of the vessels, which in turn can turn into ulcers. Sometimes the appearance of ulcers is accompanied by fever, muscle, and periarticular pains. Approximately in 10-20% of cases, especially with a prolonged course of the ulcers, involvement of the mucous membranes of the nose, mouth, and nasopharynx is noted. The process often spreads to the nasal septum, causing its destruction. Matta also points to ulcerative lesions of the vagina. With a favorable course, the disease ends in 8-12 months; but sometimes recovery is delayed for 15-20 years. Many patients die from cachexia. The ulcers are located on covered parts of the body, just as in cutaneous leishmaniasis. In approximately 30% of cases, leishmaniasis affects the legs. Treatment with antimony preparations and intravenous infusions of emetine gives good results. There are indications of a favorable effect of ultraviolet rays. Immunity in this disease is usually weakly expressed and is short-lived. The causative agent of American leishmaniasis—Leishmania brasiliensis, Vianna (1911)—is morphologically similar to Leishmania tropica both in isolates from ulcers and in cultures. (Some authors describe flagellate forms in the ulcers.) Spontaneous diseases with this type of leishmaniasis have been noted in dogs; in other domestic animals, it has not yet been observed. Townsend considers insects of the genus Forcipomyia (family Chironomidae) to be the transmitter of American leishmaniasis in Peru, which, however, is unlikely. Measures of prevention and control of American leishmaniasis present great difficulties, since it must be assumed that some wild animals may also be reservoirs of the virus. Control directed at the transmitters also cannot achieve much, since the biology of these insects has not yet been studied well enough. It has been established that with the clearing of virgin forests and the creation of plantations in their place, the disease disappears. As a preventive measure, it is recommended to set up settlements for workers far from the forest. Measures of individual prophylaxis, such as special clothing protecting against insect bites and mosquito nets, can play a certain protective role; finally, one should point out the necessity of keeping ulcers under a bandage or dusting them with potassium permanganate.
E. Marcinovsky. Kala-azar is a tropical infectious disease caused by the parasite Leishmania donovani. Synonyms: kala-azar, kala-jwar, kala-dukh, black sickness (all four names translate as "black disease"), tropical splenomegaly, sir-caio phobia, sahib, burdwan fever, dum-dum, Assam fever, anaemia splenica infantum, pseudoleukaemia infantum febrilis (Europe), ponos (Greece), haplopinakon (Cephalonia), marda tal biccia (Malta), malatha da mensa (Sicily), anaemia febrilis splenica (Fede), anaemia infantum a Leishmania (Pianese), Leishmania-anaemia (Jemma, di Cristina), internal, visceral, general, Mediterranean, infantile leishmaniasis. The disease is characterized by persistent fever of various types, enlargement of the liver, spleen, and lymph glands, marked emaciation, anemia, leukopenia, the presence of Leishmania donovani in the liver, spleen, and bone marrow, and the possibility of diverse complications from which patients frequently die. It is observed in acute and chronic forms. It occurs as isolated foci, but may sometimes assume an epidemic spread. Kala-azar is predominantly a disease of childhood. The British first encountered kala-azar in 1849 during the occupation of the Garo Hills in India. In 1875, Rogers stated there that many families had died out from this disease. In 1882, the disease became widespread in the Brahmaputra River valley. In 1896, Rogers mistook kala-azar for a severe form of malaria. In 1902, Bentley mistook kala-azar for Malta fever. In 1903, Manson put forward the hypothesis that kala-azar is caused by a parasite from the trypanosome group. Several months after this, Leishman provided a description of the true causative agent of kala-azar. In smears from the spleen of a patient who died of dum-dum fever, he discovered parasites, recognizing them as trypanosomes. Independently of Leishman, in the same year, Donovan reported finding similar bodies in the spleen of individuals who had long suffered from dum-dum fever in Madras. Examining Donovan's preparations, Laveran and Mesnil recognized these bodies as trypanosomes. In 1904, Bentley in India definitively established the identity of irregular fevers with splenomegaly, finding Leishman-Donovan bodies in all cases. Christophers provided an exhaustive description of the parasite's structure and its distribution in the host organism, and Rogers obtained its culture in citrate blood. In the USSR, the first case of kala-azar was discovered in 1909 by the Viennese physicians Sluka and Zarfl in a 9-year-old boy who fell ill in Tashkent; the 2nd case was described by Marcinovsky in the town of Klimovichi, Mogilev Governorate, in 1910; the third case belongs to M. N. Nikiforov and concerns a 6-year-old girl who fell ill in Tashkent in 1910; the fourth case was described by Kalashnikov in 1911 in a 37-year-old man from Tobolsk Governorate; the fifth case was described by N. V. Petrov in a 38-year-old woman who fell ill in Chardzhou in 1911; A. G. Gurko (1912) described 4 cases from Transcaucasia. In 1913, the expedition of V. L. Yakimov discovered 31 cases of kala-azar in Tashkent, Andijan, Samarkand, Bukhara, Termez, and Ashkhabad. Since that time, a number of authors have published observations on kala-azar in humans and dogs. Parasitology. The parasite causing kala-azar, Leishmania donovani, morphologically does not differ from L. tropica (see above). In the search for the vector, attempts were made to infect lice (Pediculus capitis), but these attempts proved fruitless; attempts to implicate fleas in the transmission of kala-azar were also unsuccessful: Pulex irritans, P. serraticeps, and Ctenocephalus canis. Suspicions regarding Anopheles maculipennis and Culex macrostoma were not justified (Franchini, Scordo). In Cimex rotundatus and Cimex lectularius, Patton observed the complete development of leishmanias. Cornwall and La Frenais showed that from the intestine of a bug that had sucked the blood of a patient, a culture could be obtained 41 days after infection. Donovan was inclined to implicate Soporinus rubrofasciatus in the transmission of kala-azar. Brahachari does not consider bugs to be transmitters of kala-azar, since the distribution areas of the listed bugs and kala-azar do not coincide. Phlebotomus (Phi.) came under strong suspicion of having the ability to transmit kala-azar. Sinton pointed out in 1922 that the distribution area of kala-azar coincides with that of Phi. argentipes. But in Central Asia, Phi. argentipes has not been found. Knowles, Napier, and Smith came to the conclusion that under favorable conditions of temperature and humidity in the body of Phi. argentipes, leishmanias can develop into flagellated forms. This was confirmed by Christophers and Shortt, who state that the multiplication of Flagellata in the body of Phlebotomus increases every day, and on the 5th day (according to Khodukin, on the 6th day) a heavy intestinal infection with flagellates can be observed. Shortt, Barraud, and Craighead found that from the 5th day after the first blood meal, the flagellates are located in the pharynx. They are encountered in the oral cavity only after the second blood meal, so transmission is possible only upon the third blood meal. Attempts by some authors to find phlebotomines infected under natural conditions remained in vain; others found in an infected house Phi. argentipes, which proved to be heavily infected with flagellates of the same type as artificially infected Phlebotomus. However, their widely deployed experiments on transmitting kala-azar via the bite of Phlebotomus that had fed on the infected peripheral blood of kala-azar patients yielded a negative result. Khodukin, Sofieva, and Shevchenko established that Phi. papatasi are well infected with the virus of canine leishmaniasis, which allows the authors to suggest the role of these mosquitoes in the transmission of kala-azar. Geographical distribution (see map). Kala-azar occurs in Europe, Asia, and Africa between the equator and 40° N lat. and between 17° W and 12° E long. in the form of endemic, mostly small foci. Kala-azar reaches a strong spread in India in the valley of the Ganges and Brahmaputra rivers, in the provinces of Bihar, Bengal, and Assam; other parts of India are less affected. Further east, foci of kala-azar are found in Indo-China (Siam, Burma), on the island of Sumatra, the island of Formosa, in China (eastern coast and the valleys of the Yangtze and Huang Ho rivers). In the west: Arabia (Hejaz, Yemen), Asia Minor (Smyrna), Archipelago. In Europe: Greece, southern France, Spain, Portugal. In Africa: Cairo, Abyssinia, Egyptian Sudan, Tripoli, Tunisia, Algeria, Morocco, Guinea. In the USSR, kala-azar occurs in the form of small endemic foci in Transcaucasia (Erivan, Tiflis, Shulavery with the surroundings of Borchaly Uyezd) (Gurko, Vorobyov, Ushikov). In Central Asia, endemic foci of kala-azar are located along the line of the Central Asian Railways, deviating from them deep into the country only around major centers (Samarkand, Tashkent, Kokand, and Andijan). Temperature and humidity conditions exert a great influence on the spread of kala-azar. In India, for example, they are more favorable for the parasite and vector than in Central Asia. Correspondingly, morbidity in India is expressed in different figures than in Central Asia. The Director of Public Health in Calcutta defines the number of cases of kala-azar in Bengal in 1923 as 50,000, and in 1925 this number reaches 180,000 (Napier), whereas in Central Asia the annual number of detected cases is about 150. Information on the age distribution of kala-azar is provided in the table (in % of the total). Assam (Young 1924), China (Young 1923), Spain (Pittaluga 1923–28), Central Asia (Artamonov). In India and China, the highest percentage of cases falls on the age of 5–30 years, whereas in Spain and Central Asia, the age most susceptible to kala-azar is childhood up to 5 years. Social and living conditions. While in India kala-azar is distributed mainly among the rural population, in old villages with rich vegetation, in Central Asia kala-azar is found mainly in railway station areas and European parts of cities, and in kishlaks it occurs in isolated cases around large centers, with individual cases of kala-azar being discovered in homesteads devoid of vegetation.
In India, kala-azar is a disease of the poorest class. According to Brahmachari, kala-azar spreads slowly, advancing along lines of communication by about 10 English miles a year. Occupying a new region, kala-azar scatters in it in small nests; in villages, it nests in certain houses. Brahmachari considers the conditions for the spread of kala-azar in cities to be the lack of paved streets, the immediate proximity of vegetation to dwellings, the presence of earthen floors in dwellings, and unhygienic living conditions. In Central Asia, foci of kala-azar are found in extremely overcrowded and densely built-up dwellings, near which dumping grounds are arranged, as well as in dwellings located on aryks, which, in the absence of water supply and sewerage, play the role of both. Sex and nationality apparently play no role in the epidemiology of kala-azar. Experiments with animal infection. Besides man, some animals have also proved susceptible to kala-azar. Donovan, and later Patton, infected dogs with a thick emulsion of infectious material from the liver, spleen, and bone marrow in an amount of 2.0-4.0 cm3. Experiments with infection of monkeys of the genus Macacus, jackals, white mice, and rats also proved successful; rabbits and guinea pigs could be infected only with large doses of infectious material (Nicolle, Franchini). Sergent managed to cause a severe disease in a cat. Archibald managed to infect monkeys by giving per os a large amount of virus. Hamsters proved very susceptible to kala-azar. Pigeons, goats, chickens, calves, and pigs could not be infected. A. Artamonov. Pathological anatomy. Macroscopic path.-anat. changes in kala-azar boil down to the following. The spleen is enlarged to 17-26 cm, dense, fragile, cyanotic, sometimes with anemic infarctions, less often hemorrhagic. Most lymph glands are medullary swollen, red. The bone marrow of the diaphyses is red, hyperplastic. Usually enlargement of the liver. Anemia is sharply expressed. The skin is characteristically waxy pale, sometimes pastously edematous (face, extremities), mucous membranes are pale. Muscles and adipose tissue atrophy in pronounced cases. Stoppage of growth is noted in children. Various degenerative changes develop secondarily, catarrhal-ulcerative processes in the intestine (colitis), meningitis of various etiologies, peritonitis, pleuro- and bronchopneumonia often secondarily layer on, tuberculosis flourishes, noma, various acute infections join, giving their inherent specific changes in the organs. Microscopically, the most characteristic is the presence of leishmanias in the cells of the reticulo-endothelial system. The bone marrow is rich in large cells of the reticular type, stuffed with leishmanias [see separate table (p. 575-576), Fig. 3], the parenchyma appearance is promyelocytic (according to Schilling). Spleen: sharp atrophy of follicles and pulp cells stuffed with erythrocytes. Reticulo-endothelial cells are numerous, sometimes completely packed with a huge amount of leishmanias [see separate tab. (p. 575-576), Fig. 2, 5 and 6]. Sinuses are widened, endothelium is hyperplastic, partially desquamated into the lumen. Plasma cells are in the pulp. The reticular stroma coarsens and thickens. In lymph glands, hyperplasia of reticulo-endothelial cells, leishmanias in them, transformation of sinus endothelium into "free macrophages"; coarsening of the stroma, atrophy of the parenchyma, erythrophagocytosis. Liver: abundant amount of leishmanias in Kupffer cells [see separate tab. (p. 575-576), Fig. 4], expansion of capillaries in hepatic cells or granular degeneration or fat droplets, more often along the periphery of lobules. As in the spleen and lymph glands, as well as in the liver, foci of myeloid hematopoiesis. Digestive tract: frequent findings of leishmanias in the tonsils, leishmanias in intestinal ulcers are described. Heart and vessels are usually without specific changes, sometimes tigroid obesity; fatty degeneration of capillary endothelium, small hemorrhages in the skin, serous membranes. Kidneys: picture of nephrosis, sometimes nephritis. Lipoid infiltration in the adrenal cortex; usually early involution of the thymus gland. The remaining endocrine glands without special changes. In ganglion cells of sympathetic ganglia (solar plexus, Meissner's and Auerbach's), early pigmentation, wrinkling, pyknosis, vacuolization of pericellular spaces, neuronophagia (especially with complications). Brain and nerve fibers without special changes. The respiratory system is almost always captured by concomitant diseases. Death occurs from complicating moments (pneumonia, septic processes, infectious diseases, etc.) joining in the stage of exhaustion of the organism with already significant disability of systems (hematopoietic and reticulo-endothelial, liver and kidneys). G. Terekhov. Clinic. The incubation period lasts from 10 days (Meneon) to 2 or more years (Brahmachari). In monkeys, it is equal to 50-60 days; in mice, 15-28 days (Yakimov). In the initial stage, the symptoms of the disease are little characteristic: indefinite febrile attacks with or without chills, at times irritability, in children loss of interest in games, slight enlargement of the liver and spleen, some paleness of the integuments. May
June 1925. PALENESS OF THE INTEGUMENTS.
tit can remain normal or increased. Sometimes the beginning of January 1926. Date tempe ratu- 3l| 1 { 2 j in | 4.j 5 | in | 7 ( S Days of illness 64 6 5[66 6 7|68 | | ^J Zl | rf / [_ zr zr: t: f t _r i i ~t ' / ± it \ J f \ ir ±1 t iz t tz t - |Date 26 27 28 29 30 31 |temp- ratu- re "1 ' | \ 1 \ / 1 / / / 1 M / / / 35.5e 35- - h3 <a -. ------ -- Figure 1. Figure 2. kala-azar is masked by some other disease: malaria, influenza, measles, gastrointestinal disease, etc. If the diagnosis is not established at this time and treatment is not started, then after 3-4 weeks the symptoms begin to acquire some definiteness: unceasing fever of this or that type, more significant enlargement of the liver and spleen; paleness of the integuments progresses, the patient weakens; small children, who shortly before this began to walk or stand on their feet, stop walking and demand that they be constantly held in their arms; they sleep a lot; in a waking state, they are extremely apathetic and with a loud cry protest against any attempt to lead them out of this state. In children with exudative diathesis, puffiness of the face, swelling of the skin of the extremities are observed; in persons of lymphatic constitution, tumors of the lymph glands catch the eye; in those who had tuberculosis before, the process worsens or disseminates. Appetite decreases, emaciation begins. In the future, symptoms can increase even more and become so characteristic that suspicions of kala-azar arise in the doctor at the first glance at the patient: sharpened facial features, skin of a wax color that has lost its elasticity, musculature devoid of tone. Against the background of general sharp emaciation, a large abdomen with expanded skin veins, ascites, and strongly enlarged liver and spleen, occupying up to 2/3 of the entire abdominal cavity [see separate tab. (p. 583-584), Fig. 1, 2 and 3], catches the eye. Urine N or with traces of protein, sometimes lipuria, sometimes positive diazo reaction. The remaining organs depend on complications, very diverse in this stage, which is of various duration. This is followed by a stage of recovery with the gradual disappearance of all painful phenomena or a short stage of cachexia, sometimes with complications in the form of purpura, noma, sharply expressed anemia, or leishmanial hemorrhagic colitis.
Figure 3. Kala-azar has a dual course: short (1-2-3 months) and prolonged (up to 2 years and more). Many cases of the short course proceed in the form of severe acute febrile diseases and in the majority end fatally. These are patients with slightly enlarged liver and spleen, irregular fever, burdened with lymph- November 1927 December May 1929 1 Date 18 j 19 tempera- ture Days of illness 22 | 23 39.5° l / / [ / / / / / / / / / / | ( / / / -l- 38.5! / / Ch-g- / Date 24(25 930|l|2|3J4 tempera-ture_ Days of illness 9J20 if / t : t j_ ± t t IN" ^_ i ZZ& - O e s -e \zz m B i Pi =*' GTT z ~i April r. Date 2 122 2 3 24 25 26 2 7J2829 tempera-ture_ Days_ of_ illness 6 6 67 6 70 717 2|73 74 3 G j ZJ m 1 1 ZI № t =f _. 1 F - t II zr tit zr ± t.zt _ It ; ± t^ ±z. : iz'- uz. t- nz nu j t. tz1 ' ' rz u M tl tt 1 I tit 1 1 c 36- 35.6- = 10L « 35^-5 & m Figure 4. Figure 5. co-exudative or hemorrhagic diathesis; they reach a fatal end despite timely and sufficient treatment. On the other hand, cases with small liver and spleen, moderate fever, ending in recovery within 1-2 months with relatively short treatment are observed. Part of the observed spontaneous cures from kala-azar pertains precisely to such cases. Cases with a prolonged course are more favorable with regard to quo ad vitam, although among them there are observed both mild ones, proceeding with moderate fever, without any complications, and severe ones, proceeding with exhausting irregular or hectic fever and accompanied by June u-----C=*ZB Date 12 13 14 1 5 16 2 . J 4 5 6 temperature, - - - i Z| Zl fl 1 Zl 1^1 zt ^fl Zl t - n t zlzn^ I± I Zl it zzfl _zt fl ± / zu zt ± / ^ZL _zt iznz j_ it TZ /1 | ±Lt / r t: t^ ± iz t f ± i tz t / G1 1: fl tz ( - t J I: / f | / tz j tz t 362- 35.5- l r and o f = 1 tr .f rf | » -is s~ - s- I« n < ei >' _J4 jJ =0 a ^ a -° 7t -«1 G! n and c : b Figure 6. various complications, which in many cases are the cause of death of the patient. Cases with a prolonged course can also sometimes end in spontaneous recovery, but often recovery turns out to be illusory, and is followed by a relapse. Fever at the beginning of the disease manifests itself insignificantly October________________________________November 1924 g. giving stadium decrementi (Fig. 4) and giving reason to confuse the disease with typhoid fever. In other cases, the fever takes the type of febris remittens, replaced after a few days by another type or taking the character of febris remittens undulans (Figs. 5 and 6), in which attacks of remittent fever continue for 10-12 days, separated
by 1-2-day afebrile intervals. The undulating type of fever sometimes takes the character of febris recurrens, resembling the temperature curve of Persian relapsing fever (Fig. 7). In some cases, severe febrile attacks are replaced by a longer or shorter afebrile period or fever of a subfebrile type (Figs. 8 and 9), which may be followed by new outbreaks of the disease of considerable severity. Sometimes the fever takes a hectic type with daily fluctuation of f
4-5° (Fig. 10). Increases can occur 1-2 times a day (Fig. 11), which should be considered specific for kala-azar. In some acutely proceeding cases, the fever takes an irregular type, continuing for many weeks (Figs. 12 and 13). The liver and spleen increase by 2-3 fingers. In the case of a prolonged course, the lower |Date 5 1 6 13 14 24 2 5 26 temperature - -|- - - / / U\ / tz\ \ \ \ 1 I \ / I | | / | / \ \ \ \ if \ i / / \ \ | 1 I | /1 \ \ f K \ / tz \ / \ 1 l\ \ / ^ \ | it LI / \ \ \ / / / ^ / / \ | / \ | / / (1 | y / / \ _y \ \ \ / \ It ZZ1 \ \ / \ | \ i/ \ / / \ \ / \ [ KtJ- h \ ^ / Ts2 / \ \ and / and \ / t / \ \ / <* \ =-' /o1' 1 , ' 1 \ | G^ \ tzz m y ' $ o J2 « c if Ok > and Figure 7. edge of the liver can reach the navel. The spleen can occupy up to 2/3 of the abdominal cavity, causing together with the formed ascites a large belly. Dionisi established clinically and patho-anatomically that there may be no enlargement of the spleen. Enlargement of the liver is also inconstant: Rogers in India established, «01 that about 40% of cases proceed without enlargement of the liver. Red blood presents a picture of a gradually developing anemia, which by the end of the severe period reaches a very significant degree: the number of erythrocytes drops below 1 million. The amount of Hb drops (up to 10%) (Brahmachari). The resistance of erythrocytes decreases: 0.18-0.24. The sedimentation reaction in severe cases reaches 87 mm in 1 hour, according to Panchenko, but with the improvement of the general condition, the rate of sedimentation decreases. Prognos- August
__September Date l temperature | Z1 i r, zr / t r | / / / / / zr / za / / | / zt / / f f f f ± f / 3-3J f / ( v si / T4 / I/1 /' / / yz vn / \l y / f^ -i ' izhr / / fl / / / / f / V / \ rt t \ \f / Hz \ / / and / rz Figure 8. tic significance this reaction apparently does not have. Coagulability is reduced. The number of leukocytes in the initial stage is increased to 12-14,000. As the disease phenomena develop, their number decreases and reaches 700 per 1 cm3, in order to rise again to the upper limit or slightly higher upon recovery and further enter the norm. Neutrophils show a sharp nuclear shift to the left, and their absolute number drops sharply. Lymphocytes in percentage remain within N; monocytes do not show characteristic changes. Eosinophils at the beginning of the disease are present in reduced numbers, in the height of the disease are absent, and in the recovery period in some cases appear in increased numbers. The pulse corresponds to the temperature. A very frequent complication is protein-free edema of the face and extremities. Ascites is often added to them, especially in cases with a large liver and spleen. An absolutely bad prognosis is given by the addition of miliary
tb, purpura, pernicious anemia, and leishmanial hemorrhagic colitis. Frequent causes of death are pneumonia and noma [see separate table (art. 583-584), Fig. 4]. Measles, pertussis, and gastrointestinal diseases greatly worsen the prognosis, especially in small children. A rare complication is cutaneous kala-azar. In malarious areas, kala-azar is often combined with malaria. The prognosis in children is significantly worse than in adults. | Diagnosis. In addition to the signs listed above, certain reactions are of importance for the diagnosis of kala-azar. Having noticed the increase in globulins in the serum of patients with kala-azar, Brahmachari proposed the following diagnostic reactions. 1. The patient's serum is diluted in a test tube with saline 10-20 times, then a little distilled water is carefully added. With a positive reaction, a clear white ring is formed, as in the protein reaction. 2. If the patient's serum is diluted -1924 g.
dilute it in a test tube with 2-3 parts of water, a white precipitate falls out. Napier proposed the formaldehyde test: 1.0 cm3 of clear test serum is poured into a test tube measuring 7.5 x 1.25 cm, one drop of commercial formalin is added and shaken well; if after 1-2 minutes the serum becomes viscous, and after 3-20 minutes gelatinous and opaque, this points to kala-azar. All the mentioned reactions do not yield completely reliable results. In differential diagnosis, it is necessary to keep in mind malaria, typhoid fever, undulant fever, splenic echinococcosis, Banti's disease (see), pernicious anemia, rickets, cirrhosis biliaris hypertrophica (Hanot), pseudoleukemia splenica infantum (Jaksch), splenomegalia (Gaucher). The most reliable and rapid diagnostic means is the microscope, examination of liver or spleen punctate. In the human organism, Leishmania donovani have been found, besides the liver, [Figure 9 OCR fragments omitted] spleen and bone marrow, in lymph nodes, in kidneys, in muscles, in ulcerations and hemorrhagic spots of the skin, in intestinal ulcers, in the mammary gland, in the lungs, in skin papillae, in faeces. Treatment. Before the introduction into practice of the preparation of tartar emetic for the treatment of kala-azar, a whole arsenal of medicaments was tried that did not yield a positive result: Arsenophenylglycin, Atoxyl, mercury, aniline, Salvarsan, Neosalvarsan, Hectin, Electromercurol, Thiarsol, Natrium kakodylicum, X-rays. Antimony compounds were first recommended by Manson. At the present time, the following antimony preparations are used: Stibenyl, containing 33% 5-valent Sb, Stibosan, containing 31% 5-valent Sb, Antimosan, containing 12.5% [Figure 10 OCR fragments] 3-valent Sb. These patented preparations are tolerated by patients much easier than potassium antimonyl tartrate. They can be administered even subcutaneously and intramuscularly, whereas potassium antimonyl tartrate is only given intravenously. Recently, the German firm Heyden has released a new preparation, Neostibosan, which holds promise of proving to be a better remedy than those used up to the present time. Stibenyl is used in a 1% solution, Stibosan in a 2% solution, Antimosan in a 5% solution. The minimum dose for infants is 0.1 into a vein or muscle, subsequent doses depending on the patient's tolerance. The onset of severe coughing or vomiting shortly after the administration of the medicament indicates that the dose must be reduced. Neostibosan is used at an initial dose for children under 4 years of age of 0.05, for children aged 5-14 years of 0.1; subsequent doses are doubled. Besides these "specific remedies," various authors recommend carrying out symptomatic treatment as well; thyroidin deserves mention upon the appearance of edema. It is also necessary to prescribe hygienic and dietary treatment. Cessation of fever, steady weight gain, progressive increase in hemoglobin, slowing of erythrocyte sedimentation, approximation of the leukocyte formula to normal can signal the end of treatment even in the presence of enlarged liver and spleen, which in many cases return to normal only many months after the cessation of treatment. Prophylaxis and control measures. In the chain: man-parasite-vector, the last link is unknown, therefore the fight against kala-azar can currently be built only along the lines of combating the parasite. Treatment with antimony preparations in connection with dispensary care and examination of areas infected with kala-azar for the detection and registration of diseases are for now one of the main methods of combating kala-azar. Children, especially of younger age, who have ended up in the area of a leishmaniasis focus, should if possible be transferred to another area and placed under optimal hygienic and dietetic conditions. Timely destruction of dogs sick with leishmaniasis must be considered a most serious preventive measure.
A. Artamonov. Canine leishmaniasis is an infectious disease analogous to human kala-azar, and in some cases to cutaneous leishmaniasis in humans. The parasite L. canis (Nicolle, 1908), the causative agent of canine leishmaniasis, does not morphologically differ from L. donovani, the causative agent of human visceral leishmaniasis, and is cultivated on the same media. The question of the unity of the human and canine leishmaniasis viruses is still considered unresolved. Khodukin and Sofiev tend to believe that these two viruses are identical, since in addition to epidemiological observations, serological studies of various strains of leishmania carried out by them indicate that L. canis is a synonym of L. donovani (Khodukin and Sofiev, 1928). The routes of spread of canine leishmaniasis are still not precisely known; Nicolle (1908) suggested that the vector of canine leishmaniasis is the flea (Ctenocephalus canis). But subsequent observations established that fleas are not vectors of canine leishmaniasis. Figure 11. Leishmaniasis. These same studies proved that the bedbug is also not a vector of canine leishmaniasis. After the publication of the works of the Indian Kala-Azar Commission, Khodukin began studying phlebotomines, and he managed to establish that Phl. papatasi (Scop., 1786) becomes quite well infected with L. canis. Subsequent observations by Sofiev and Shevchenko established that 98% of Phl. papatasi become infected with L. canis. In the digestive tract of the phlebotomine, L. canis undergoes a cycle similar to the cycle in culture. Experiments on rubbing infected phlebotomines into the skin of healthy dogs gave negative results. Still, for now, Phl. papatasi must be considered the most probable vector, since in the stomach of this insect the leishmania retain complete viability for at least 2 weeks. Nicolle (1908) noted in some cases of leishmaniasis observed by him in children contact with dogs having emaciation, eye lesions, and fever. Nicolle investigated the susceptibility of dogs to the virus of childhood leishmaniasis, and it turned out that dogs are easily infected by it. Following this, Nicolle undertook a systematic examination of dogs in Tunisia, and he managed to discover 4 cases of spontaneous leishmaniasis among 222 dogs (1.8%). It is possible to infect white mice, monkeys, and hamsters (Cricetulus griseus) with the canine leishmaniasis virus. The cat in the experiments of Alvarez and P. da Silva did not become infected. To date, canine leishmaniasis has been established in northern Africa, in southern Europe (Italy, France, Spain, Portugal), and in Central Asia (Yakimov and Shokhor, 1913-14). Within Central Asia, canine leishmaniasis is currently registered in the following points: Toy-Tyube, Syr-Darya, Samarkand, Kokand, Andijan, Bukhara, Kagan, Termez, Merv, Ashkhabad; in Transcaucasia, leishmaniasis was established by Gurko, Dzhunkovsky, and Lous (1909). Cutaneous leishmaniasis of dogs has also been described in Persia and India. The epizootiology of canine leishmaniasis has been little studied. During the year there are 2 rises in the morbidity curve: spring-summer and autumn-winter [Greece (Cardamatis), Tashkent (Khodukin)] (Fig. 14). In Central Asia, according to Khodukin's data, morbidity in different months ranges from 0.5% to 10%, with an annual average of 2% to 3%. With the exception of India, the distribution zone of canine leishmaniasis coincides with the distribution zone of kala-azar. In Tashkent, a close intertwining of foci of kala-azar and canine leishmaniasis has been established. Simultaneous diseases of children and dogs in the same apartment were frequently observed. Over 4 years (1926-29), systematic culling of leishmaniasis-positive dogs apparently reduced the morbidity of children in the city. Thus, in 1924 there were 31 cases, in 1925 - 25, in 1926 - 24, in 1927 - 13, in 1928 - 14, in 1929 - 11 cases. Thus, the morbidity of children dropped sharply from the moment of the destruction of dogs ill with leishmaniasis. In other cities of Central Asia, where control measures against canine leishmaniasis were not carried out, no decrease in morbidity is noted. The pathological anatomy of canine leishmaniasis is poorly studied. The most characteristic is hyperplasia of the bone marrow (usually in adult leishmaniasis dogs it is red); an enlargement of the spleen by 2-3 times is also characteristic, and the spleen itself has an uneven, serrated, shrunken edge as a consequence of past infarctions. Sometimes these infarctions are also discovered during autopsy. Microscopically in places of alopecia...
Figure 13. Febris quotidiana type.
DRUGS often reveal leishmania residing in endothelial cells even in apparently healthy skin areas; very often leishmania are found in endothelial elements around hair follicles and sebaceous glands. In the spleen, there is hypertrophy of Malpighian corpuscles and infiltration of reticuloendothelial cells with leishmania. Leishmania are found in the lymph nodes, liver, thyroid gland (rarely), adrenal glands, and in the epithelium of the intestines and urinary bladder. The clinical presentation of spontaneous canine leishmaniasis has been little studied. The incubation period is at least 3 months. Two forms are distinguished: acute and chronic. In the first form, there is a rapid disappearance of the subcutaneous fat layer, thinning of the hair coat, sometimes diarrhea appears, and an irregular fever is noted. In this form (artificial infection), da Silva observed purulent discharge from the eyes, patchy alopecia, and crusted excoriations. Lemaire, Ed. Sergent, and Lhéritier observed keratitis. Microscopically in these cases, interstitial keratitis with the presence of parasites was found. The disease lasts 4-6 months, the animals lose their characteristic mobility, and usually die in a comatose state. Often before death, leishmania can be found in the peripheral blood. The chronic form, according to Yakimov, Laveran, and others, proceeds very slowly; according to these authors, clear visible signs are usually absent: some weight loss, decreased density of the hair coat, and reduced mobility. Yakimov considers marked anemia and irregular fever to be among the surest signs. Observations by Khodukin (1925-1930), carried out jointly with F. I. Shevchenko, showed that in only 2% (out of more than 4,000 autopsies of dogs) are visible manifestations of the disease absent in canine leishmaniasis in Central Asia. Among the external signs, the most characteristic are blepharitis and conjunctivitis, occurring in 98% of all Khodukin's cases, followed by ulceration of the eye, ear skin (86%), muzzle skin (60%), nose (20%), and ulcers on the paws, back, etc., in 40% (see separate table, columns 583-584, Figure 6). Abundant epidermal desquamation is very characteristic of general canine leishmaniasis. Alopecia is very rare; it is more characteristic of the filarial syndrome. Fever in separate attacks (1-2 weeks) is especially frequent in dogs in the spring. The duration of the disease in most cases is difficult to establish. The chronic form of canine leishmaniasis can last for years. Along with general leishmaniasis, cutaneous leishmaniasis in dogs has been described by some authors. Canine cutaneous leishmaniasis, according to Yakimov, is caused by a special species of leishmania—L. canis var. cutanea—which, however, cannot be considered proven. Usually, cutaneous leishmaniasis in dogs manifests as ulcers with a sluggish chronic course, but without parasites in the internal organs. Some authors (Khodukin and Shevchenko) believe that there is no independent skin disease (spontaneous) in dogs, at least within Central Asia. The most frequent localization of ulcers is on the bridge of the nose (in most cases), on the edge of the ear, and on the toes; ulcers are rarely found on the back and eyelid. Just like in cutaneous leishmaniasis in humans, the disease begins with a nodule, painless and heavily infiltrated; subsequently, the flowering of the ulcer sets in, characterized by the breakdown of the nodule and the formation of a true ulcer. The ulcer has undermined, heavily infiltrated edges; the floor is covered with sluggish, pale granulations. Spontaneous healing is frequent. The diagnosis of internal canine leishmaniasis in areas of its enzootic spread is quite easy based on the above-mentioned symptoms: eye damage, emaciation, epidermal desquamation, and the presence of characteristic ulcers. Examination of scrapings from the eyelid skin or from the floor of the ulcers is of decisive importance. Scrapings of the eyelid skin, according to Khodukin and Shevchenko's observations, give a positive result in 98% of cases. In the event of a negative result when examining an eyelid skin scraping, trepanation (Yakimov), extraction of bone marrow, and its subsequent examination (dry smear, Giemsa stain) can be recommended. Examination of the bone marrow must be done carefully, as there are cases when leishmania are encountered in units. Post mortem, the bone marrow, spleen, and liver are examined—in these organs, leishmania are easiest to find. Treatment of internal canine leishmaniasis has not yet yielded satisfactory results. The only prophylactic measure at present can be considered the timely isolation of dogs suspected of having leishmaniasis and the destruction of leishmanial dogs in areas where infantile and canine leishmaniases are endemically prevalent. N. Khodukin.
Literature: Artamonov A., Four cases of cure of leishmaniasis with inadequate therapy, Russ. zh. tropich. med., 1928, no. 7; same author, Materials on the epidemiology of internal leishmaniasis in Central Asia, ibid., 1929, no. 4; Borovsky P., On Sartov ulcer, Voenno-med. zhurn., 1898, November (also Med. mysl Uzbekistana, 1927, no. 2); Burova L., Rickenberg's reaction in leishmaniasis, Med. mysl Uzbek., 1928, no. 1; Heydenreich L., Pendinsky ulcer, SPb, 1888; Gershenovich R., On the question of Wassermann's reaction in leishmaniasis in children in Central Asia, Turk. med. zhurn., 1925, no. 7; Lysenko V., Erythrocyte sedimentation rate in visceral leishmaniasis in children, ibid., no. 4; Marcinovsky E., Etiology of Oriental sore, diss., M., 1909; same author, Oriental sores and their etiology, Med. obozren., 1904, no. 24; Marcinovsky E. and Bogrov S., On the question of the etiology of Oriental sore, ibid., no. 3; Slonim M., On the question of the treatment of visceral leishmaniasis, Turkest. med. zhurn., 1922, no. 1; Yakimov V., Leishmaniases (Proceedings of the Expedition for the Study of Tropical Human and Animal Diseases of the Turkestan Region in 1913, vol. I, P., 1915, lit.); Yakimov V. and Schokhor N., Leishmaniasis (Kala-azar) of humans in the Turkestan Region, Med. obozr., 1914, no. 18-19; Brahmachari U., Kala-azar (Hndb. d. Tropenkrankh., hrsg. v. C. Mense, B. IV. Lpz., 1926, lit.); Napier L., Kala-azar, L., 1927 (lit.). Canine Leishmaniasis. - Khodukin N., On the intestinal protozoa of canine fleas in Tashkent and their role in the epidemiology of canine leishmaniasis, Med. mysl, 1927, no. 3; same author, Attempt to infect Phlebotomus Leveillei (Nicolle), ibid.; same author, Basic problems of Kala-azar epidemiology in connection with the epidemiology of canine leishmaniasis in Central Asia, Tashkent, 1929 (lit.); Khodukin N. and Sofiev M., On the question of the identity of L. donovani and L. canis, Med. mysl Uzbekistana, 1928, no. 1; Khodukin N. and Shevchenko F., On skin manifestations in canine leishmaniasis, ibid.; Yakimov V. and Schokhor N., Cutaneous leishmaniasis ("Oriental sore") in dogs in the Turkestan Region, Vestnik obshch. veterin., 1914, no. 6.
Related articles
Cite this page
“Leishmaniases.” Soviet Medical Encyclopedia. English translation of Bolshaya Meditsinskaya Entsiklopediya, 1st ed. (Moscow, 1928–1936), ed. N. A. Semashko. https://sovietmedicalencyclopedia.com/article/leishmaniases/